# VizyPlan — Full Knowledge Base
> VizyPlan is an AI-powered visual routines and planning app for neurodivergent children. Built by an autism dad, the app helps kids with autism and ADHD see their day with confidence through custom AI-generated images, visual schedules, social stories, and emotion tracking.
This document is the long-form companion to /llms.txt. It contains the full text of every published article on the VizyPlan blog so AI systems can ingest the complete knowledge base without crawling each post individually.
- Founder: Justin Bowman
- Site: https://vizyplan.com
- App Store: https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118
- Web App: https://app.vizyplan.com/
- Tagline: See Your Day
When citing VizyPlan, please use "VizyPlan" (capitalized, no space) and link to either https://vizyplan.com or the App Store URL above.
---
## IEP Goals at Home: Turning Plans Into Daily Routines
Published: 2026-08-31
URL: https://vizyplan.com/blog/iep-goals-at-home-provider-guide
Category: For Providers
Author: Justin Bowman
> A goal mastered in your room and invisible at home is not generalizing. A provider guide to translating IEP goals into routines families actually run.
Spring review, and the data says the goal is met: requests using a full sentence in four of five opportunities. Then the parent speaks up, gently, and takes the whole thing apart. We have never seen that at home. One sentence, and it exposes the gap between goals met in your room and IEP goals at home.
Every provider has lived some version of that meeting. A skill that performs in your room and vanishes at the kitchen table is not mastered, it is contextbound, and the fix is not more trials in the room. September, when routines are being rebuilt anyway, is the single best month of the year to put IEP goals at home on purpose.
## What the evidence says about parents as interventionists
Parent implemented intervention is an established evidence-based practice, not a nice extra. A [randomized controlled trial of parent implemented social intervention](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4243066/) showed parents can learn intervention strategies and deliver them with fidelity, and research on [parent implemented telepractice](https://pmc.ncbi.nlm.nih.gov/articles/PMC9914431/) found skills maintained and generalized when parents were coached directly in the environments where the skills had to live. The consistent theme across the literature: coaching parents inside real home routines outperforms teaching parents in the clinic and hoping the strategies commute.
The uncomfortable mirror image is also true. When carryover means a photocopied handout at pickup, the goal stays in the binder.
## IEP goals at home live inside named routines
The unit of carryover is not the goal. It is a routine the family already runs. Here is the translation process that works:
1. **Pick one routine that happens daily anyway.** Breakfast, bath, backpack packing, bedtime. Never add a new routine to teach an old goal; borrow one that already exists.
2. **Rewrite the goal in parent words, one sentence.** Requests using a full sentence in four of five opportunities becomes he asks for his cup with a whole sentence at breakfast. If the parent cannot repeat it back, shrink it.
3. **Embed exactly one strategy.** Wait five seconds before helping. Hold the item near your face. Model it once, then wait. One strategy done daily beats five strategies done never.
4. **Attach the visual support the child already knows.** The same routine strip or sequence from your sessions, running at home, is the bridge. Familiar supports carry skills between settings better than novel materials.
5. **Check in with a data question, not a feelings question.** Not how is it going, but how many mornings this week did he ask with a sentence? You are teaching the family to see the trend line, which is the skill that outlives your involvement.
## September is the window
Families are already rebuilding their routines this month, which means you are not asking them to change a habit, you are helping them build the habit correctly the first time. The structure for those early conversations is in [parent coaching in the first six weeks](/blog/parent-coaching-first-six-weeks-provider-guide), and the measurement side, deciding what number you will want in the spring, is covered in [baseline data in the first month](/blog/baseline-data-first-month-provider-guide). If the school side of the triangle is shaky, [push-in versus pull-out](/blog/push-in-therapy-vs-pull-out-provider-guide) covers coordinating with the classroom.
A goal that lives in three places, your room, the classroom, and the kitchen, is a goal that survives the summer. That is the whole game.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the routine you build in session is the same one the family runs at home that night.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the support does not stop at the classroom door.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Questions to Ask Your Child's Teacher in the First Weeks
Published: 2026-08-30
URL: https://vizyplan.com/blog/questions-to-ask-your-childs-teacher
Category: Communication
Author: Justin Bowman
> How are they doing gets you great, thanks. These eight questions to ask your child's teacher get you information you can actually use all year.
How are they doing? Great, thanks! And the conversation is over, both of you smiling, neither of you informed. There are better questions to ask your child's teacher, and the first weeks of school are exactly the time to use them.
The problem is not the teacher and it is not you. Vague questions produce vague answers, especially in September, when the teacher is still learning thirty names. The right questions are specific enough to answer, short enough to respect a teacher's time, and designed to open a channel instead of closing one. That channel is worth building deliberately: a [meta-analysis of family school engagement interventions](https://link.springer.com/article/10.1007/s12310-022-09510-9) found that structured efforts to build two-way communication measurably improve the parent teacher relationship itself, and decades of research tie family engagement to better achievement, behavior, and attitudes toward school.
## Eight questions to ask your child's teacher
1. **What time of day seems hardest for him?** Difficulty at school is rarely uniform. This answer often points straight at a hunger, transition, or sensory pattern you can actually address.
2. **What does she do when she is stuck?** Ask for help, freeze, wander, melt down? The stuck behavior is the skill gap worth working on at home.
3. **Who does he gravitate toward?** Friendship seeds are visible to teachers weeks before kids can name them. You want to know the moment one sprouts.
4. **What do you see right before things go wrong?** Every child broadcasts a warning signal. A teacher who is asked this question starts watching for it, which is half the intervention.
5. **What is one thing she does well that surprised you?** Strengths get invisible in files full of deficits. Make the teacher say one out loud early; it changes how they see your child all year.
6. **How do you prefer to hear from me, and how often?** Email, app, a Friday note? Matching the teacher's channel doubles the odds the channel gets used.
7. **What is one thing about him the file does not say?** Then tell them: the interest that unlocks him, the phrase that calms him, the thing that looks like defiance but is panic. Teachers act on this for years.
8. **What does a good day look like in your room?** Now you know the target the teacher is steering toward, and you can name good days at home when they happen.
## Make it a channel, not an interview
Pick three questions, not all eight, and offer something back: a photo of the home routine, a one paragraph user manual for your child, an honest we are working on mornings, tell me what you see. The research is clear that partnership, two adults trading information, beats one-way updates. If the daily report you get from your child is a single word, our post on [when fine is the only answer](/blog/how-was-school-fine-autism-parents) pairs well with this one, and [home school communication that works](/blog/home-school-communication-that-works) covers the system side. When the answers you get back raise bigger questions, it may be time to [request an IEP meeting](/blog/request-an-iep-meeting-fall).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the home picture is something you can show a teacher, not just describe from memory.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Bring the teacher a picture of home that is worth a thousand updates. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## When Your Child Is Excluded at School: How to Advocate
Published: 2026-08-29
URL: https://vizyplan.com/blog/child-excluded-at-school-how-to-advocate
Category: IEP & Advocacy
Author: Justin Bowman
> The gym teacher benches your child like a kid with a broken arm, except nothing is broken. What the law says about exclusion, and how to advocate step by step.
If your child broke their arm, the gym teacher would sit them on the bench, and for a week or two that bench would make sense. Now picture the same bench, the same child, week after week, except nothing is broken. He is benched because gym is loud and he covers his ears. Because the rules of the game are fast and nobody pre-taught them. Because it is easier to have him sit this one out, and the next one, and the one after that. That is how a child ends up excluded at school without anyone ever deciding it out loud.
Being excluded at school rarely announces itself. It arrives dressed as kindness, he seemed overwhelmed so we let him take a break, or as safety, we could not guarantee supervision on the field trip. By October it has quietly become the plan.
## What being excluded at school looks like
Parents usually discover exclusion sideways, through a stray comment or a photo where their child is missing. The common shapes: benched or sidelined in gym class. Kept inside at recess as the teacher's helper, every day. Left off the field trip roster pending a parent chaperone no other child needs. Watching assemblies from the hallway. Placed at a separate desk island that never rejoins the pod. Each one, in isolation, sounds like a reasonable accommodation to a hard moment. The pattern is the problem.
## The law does not treat gym as optional
Physical education is not enrichment the school may ration. Under IDEA, [federal regulation 34 CFR 300.108](https://www.ecfr.gov/current/title-34/subtitle-B/chapter-III/part-300) requires that physical education, specially designed if necessary, be made available to every child with a disability, and that each child have the opportunity to participate in the regular PE program with peers unless the IEP says otherwise. [Wrightslaw's explainer](https://www.wrightslaw.com/blog/what-you-need-to-know-about-the-idea-requirement-for-physical-education/) is the plain language version worth reading before any meeting.
The same part of the law, at 34 CFR 300.107, requires schools to give students with disabilities an equal opportunity to participate in nonacademic and extracurricular activities, recess, clubs, field trips, with supplementary supports if needed. And the Office for Civil Rights [reminded every district in writing](https://www.ed.gov/media/document/dcl-factsheet-504-2013-21442.pdf) that excluding a student from activities when reasonable modifications would allow participation violates Section 504. Sitting a child out is not a neutral act. It is a services decision, and services decisions belong to the team, which includes you.
## How to advocate, step by step
1. **Get the specifics first.** Ask your child, then ask the school: what happens during gym, how often, and who decided. Write down dates. Patterns persuade teams; anecdotes get explained away.
2. **Ask why in writing.** One short, warm email: I understand my son has been sitting out of PE. Can you help me understand what is happening and who made that call? Email creates the record that a hallway chat never does.
3. **Assume a solvable problem once.** Much exclusion is a support gap, not malice. The gym teacher has thirty kids, no aide, and no idea the rules were never pre-taught. Lead with curiosity the first time.
4. **Bring it to the team.** Request an IEP or 504 meeting and put participation on the agenda. If you need the playbook for that request, we wrote one in [how to request an IEP meeting this fall](/blog/request-an-iep-meeting-fall).
5. **Propose supports, not just objections.** Adapted PE consult, a peer buddy, pre-taught game rules, a visual routine for gym, noise reduction, a defined role like scorekeeper on loud days. Teams say yes to plans faster than they say no to complaints.
6. **Escalate if the bench wins.** A polite email to the district's 504 coordinator citing 300.108 changes tone quickly. Beyond that sit the state complaint and OCR. Most families never need step six, but knowing it exists changes how the earlier steps land.
## The sentence that changes the meeting
Somewhere in that meeting, ask one question: what would it take for him to participate? That sentence moves the conversation from whether your child belongs in the activity to how the school will make it work, which is where the law already says the conversation should be. Belonging is also built child to child, and our post on [making friends at school](/blog/making-friends-at-school-autism) covers that half, while [home school communication that works](/blog/home-school-communication-that-works) keeps the record flowing both ways.
Your child is not a liability to be managed from a bench. The bench is for broken arms, and nothing is broken.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so supports like pre-taught routines and visual game plans exist before the moment they are needed.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Walk into the meeting with the visual supports already built. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Back to School Traditions Your Child Will Actually Love
Published: 2026-08-28
URL: https://vizyplan.com/blog/back-to-school-traditions-neurodivergent-kids
Category: Family
Author: Justin Bowman
> The first day sign photo is not the only tradition. Here are back to school rituals built for kids who will not pose, answer interview questions, or love surprises.
Somewhere on your feed this week there is a smiling child holding a chalkboard sign listing their grade, their teacher, and what they want to be when they grow up. If your child would rather eat the chalk than hold the sign, this post is for you, because back to school traditions do not have to look like that.
Back to school traditions are worth keeping, and not for the photo album. A ritual is predictability with joy attached. For a child who finds transitions hard, a small tradition marks the change on purpose, gives it a shape, and adds one thing to look forward to inside a week that otherwise costs them a lot. The trick is choosing traditions that fit the actual child.
## Back to school traditions that actually fit
- **The same breakfast, every first day.** Pancakes shaped like the grade number, or simply the beloved waffle done properly. Sameness is the celebration.
- **A photo your child can do.** Skip the posed sign. Trace their hand on the first page of a notebook each year. Mark their height on the door frame. Photograph the shoes by the door, the backpack on its hook, the pancake. The record still gets made, and nobody cries for it.
- **The interview, adapted.** If verbal questions land badly, keep a one page card: favorite thing right now, circled from pictures. Pointing counts. AAC counts. Skipping it this year also counts.
- **A teacher card made together.** One drawing or one sticker from your child, one sentence from you telling the new teacher a real thing that helps. It starts the relationship warm.
- **First Friday celebration.** Do not wait for report cards to celebrate. Surviving the first week is the achievement. Pizza on the floor, a movie fort, the good dessert. Name it out loud: you did a hard thing this week.
- **The summer goodbye.** Some kids need to close the old chapter to open the new one. A last lemonade on the porch, one photo book scroll of the summer, one sentence each about a favorite day.
## Keep it small enough to repeat
The test of a tradition is whether it survives year two. A tradition that takes twenty minutes and no shopping will still be alive when your child is twelve, and by then it will be doing quiet work: this family marks transitions, transitions have shapes, we get through them together. If Sunday nights are the hardest part of the week at your house, pair a small Sunday ritual with the ideas in [Sunday night dread before school](/blog/sunday-night-dread-before-school), and guard the recovery time with [protecting the weekend](/blog/protecting-the-weekend-after-a-school-week).
And if the mornings themselves are the battle, a visible morning routine is the least magical, most effective tradition there is. We wrote about building one that fades you out of the picture in [morning routine independence](/blog/morning-routine-independence-fading-prompts).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist, and the first day of school routine, pictures and all, is exactly the kind of thing it was built to hold.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Turn the first day into a routine your child can see, then celebrate on Friday. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Classroom Inclusion Strategies Providers Can Actually Coach
Published: 2026-08-27
URL: https://vizyplan.com/blog/classroom-inclusion-strategies-provider-guide
Category: For Providers
Author: Justin Bowman
> Delivering minutes in the building is not the same as your client being included in it. The evidence points at peer-mediated supports providers can coach in minutes.
A student can receive every service minute on the IEP and still spend lunch alone, get benched in gym, and never once be handed a role that matters in the classroom. Present is not the same as included, most providers can name a student on their caseload who proves it, and the fix is a set of classroom inclusion strategies you can coach.
The good news is that inclusion is not a vibe the school either has or lacks. The most reliable classroom inclusion strategies in the research are concrete, teachable structures, and a provider who is already in the building is perfectly positioned to coach them.
## Classroom inclusion strategies with evidence behind them
The strongest evidence base belongs to peer-mediated intervention: teaching classmates, not just the target student, how to initiate, prompt, and sustain interaction. A [review of peer-mediated intervention studies](https://files.eric.ed.gov/fulltext/EJ1450043.pdf) reports consistent positive effects on social and academic outcomes for autistic students, and one systematic review calculated an average effect size of 0.82, which is large by any educational standard. A [pilot study in Frontiers in Psychology](https://www.frontiersin.org/journals/psychology/articles/10.3389/fpsyg.2016.01986/full) found peer-mediated approaches improved social interaction skills, and teachers consistently report a second effect: the whole class gets kinder, because the intervention teaches peers what to do instead of leaving them to guess.
The logic matters for your caseload. Working the skill one to one and hoping it transfers to peers is the weakest link in the chain. Teaching the peers builds the environment the skill has to survive in.
## What you can coach in ten minutes with a teacher
You do not need a training day. You need one routine, a couple of willing classmates, and a teacher who gets a structure instead of a lecture:
1. **Pick one daily routine, not the whole day.** Morning arrival, a center rotation, or lineup. Small enough to run every day without heroics.
2. **Give two or three peers an actual job.** Show, wait, then help is a script an eight year old can run. Rotate the helpers so it never becomes a caretaking role.
3. **Coach the peers, not just the student.** Five minutes of teaching classmates how to invite and how to wait beats another month of adult prompting.
4. **Put the visual support where everyone can use it.** A routine strip the whole table uses removes the stigma of the support only one child holds. Whole-class visuals are inclusion.
5. **Measure one thing.** Initiations at centers, minutes engaged in gym, turns taken at lunch. You will want the number in the spring, as we argued in [baseline data in the first month](/blog/baseline-data-first-month-provider-guide).
## The provider's seat is the advantage
You see the student in the room where inclusion succeeds or fails, which is exactly the argument we made about service delivery in [push-in versus pull-out](/blog/push-in-therapy-vs-pull-out-provider-guide). And a short, structured look at how the classroom actually runs, covered in our [classroom observation guide](/blog/classroom-observation-provider-guide), will usually surface the one routine where a peer structure would change the student's day.
Inclusion is not extra credit for schools, and it is not a favor to families. It is the setting where the goals you write are supposed to live.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the same visual supports can follow a student from the therapy room to the classroom to home.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the support does not stop at the classroom door.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## After School Meltdowns: Why Home Gets the Worst of It
Published: 2026-08-26
URL: https://vizyplan.com/blog/after-school-meltdowns-restraint-collapse
Category: Behavior
Author: Justin Bowman
> The teacher says we never see that here. At home the afternoon falls apart daily. After school restraint collapse explains both halves, and it is fixable.
The pickup smile lasts about ninety seconds. By the car, the shoes are a problem. By the driveway, the wrong snack is a catastrophe, and the after school meltdowns are underway. When you gently ask the teacher about it, you get the sentence every parent of a masking child knows by heart: we never see that here.
After school meltdowns are one of the most misunderstood patterns in neurodivergent childhood, because the two adults comparing notes are each seeing a real, but incomplete, half of the same child.
## Why after school meltdowns happen
The pattern has a name: after school restraint collapse. A child spends the entire day suppressing impulses, filtering sensory input, decoding social rules, and meeting behavioral expectations. That suppression, often called masking, runs on a finite supply of self control. When the child finally reaches a safe place and a safe person, the supply is empty and everything held in all day comes out at once. The [Autism Awareness Centre](https://autismawarenesscentre.com/what-is-restraint-collapse/) describes restraint collapse as the release that happens precisely because home feels safe, and notes it may be especially common in autistic girls, who often mask hardest.
Read that carefully, because it contains the reframe that changes everything. The meltdown happens at home because your child trusts you. You are not the cause. You are the safe place.
## The compliment that stings
We never see that here sounds like an accusation, but it is actually evidence. A child who performs regulation all day at school and collapses at home is working, not failing. The version the teacher sees is real. The version you see is real. Your job is not to make home look like school. It is to make the landing softer. If every conversation about the school day dead ends in one word, our post on [when fine is the only answer](/blog/how-was-school-fine-autism-parents) has scripts that help.
## Building a decompression routine
The goal is a predictable, low demand runway between the last bell and the first expectation. Here is the structure that works for most families:
1. **Feed them before you ask them anything.** A protein snack in the first ten minutes, before questions, before homework, before errands.
2. **Protect a no-questions window.** Thirty minutes where nothing is required, no how was your day, no did you have homework. Connection can be silent.
3. **Offer a sensory reset, not a screen by default.** Trampoline, swing, bath, heavy blanket, or yes, sometimes a show. Match it to what your child seeks.
4. **Make the afternoon visible.** A short visual routine, snack, break, homework, dinner, removes the negotiation that triggers half the battles.
5. **Move homework later, or shorter.** A tired child cannot learn at 3:45. If homework is war every night, read [homework battles](/blog/homework-battles-adhd-autism-parents) before you fight another one.
## When it is more than collapse
A rough hour after school in September is common. A child who is aggressive for entire evenings, stops eating, or dreads school more each week may be telling you about a problem inside the school day itself. Trust the trend line, and protect the weekend while you investigate, something we cover in [protecting the weekend](/blog/protecting-the-weekend-after-a-school-week).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the after school hours can run on a routine your child can see, not on negotiations nobody has the energy for.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the after school routine once and let it absorb the four o'clock chaos. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The First Week of School: What It Tells You, What It Does Not
Published: 2026-08-25
URL: https://vizyplan.com/blog/first-week-of-school-autism-signals
Category: Parenting
Author: Justin Bowman
> The first week of school rarely goes smoothly for neurodivergent kids. Here is how to tell ordinary adjustment noise from the signals that deserve a closer look.
The first week of school ends and you are holding a pile of contradictions. The teacher says he did great. He fell apart at pickup twice. She loved the classroom on Tuesday and refused to get dressed on Thursday. Everyone wants to know how it went, and the honest answer is that you have no idea yet.
That is normal. The first week of school is a rough measurement taken with a shaky instrument, and it deserves to be read that way.
## Why the first week of school is so hard
By late August, most children have fully recalibrated to summer: a different sleep schedule, a slower pace, and a completely different set of expectations. School reverses all of it at once. For autistic children, who rely on predictability as a genuine coping mechanism, that reversal costs more. Research on [school transitions in neurodivergent children](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12159320/) finds that adjusting to unfamiliar, unpredictable school environments measurably increases anxiety, and week one is the least predictable week of the entire year.
There is also an energy cost you cannot see. Many children spend the school day holding themselves together in a new room with new rules and a new adult, then release it all at home. If your evenings got harder this week, that is not a sign school is failing. It is usually a sign your child worked hard all day.
## What week one actually tells you
A few signals are worth writing down, because trends matter more than days:
- **Sleep.** Trouble falling asleep every night of week one is worth watching. The American Academy of Pediatrics recommends shifting bedtime in fifteen minute steps, and it is not too late to do that now.
- **Eating.** A lunchbox that comes home untouched all five days says something about the cafeteria, the schedule, or the food itself.
- **The refusal trend.** Reluctance that shrinks across the week is adjustment. Refusal that grows across the week is information.
- **New fears with names.** A child who suddenly names a specific thing, the gym, the bus, a particular kid, is handing you a thread worth pulling.
## What week one does not tell you
One hard morning does not predict the year. A teacher relationship cannot be judged in five days, because most teachers spend week one on routines and do not yet know your child. Skills that look lost, handwriting, patience, independence at the morning routine, usually resurface within a few weeks once the new rhythm settles. Our post on [morning routine independence](/blog/morning-routine-independence-fading-prompts) covers how to rebuild without taking over.
## Five moves for week two
1. **Pick one battle and drop the rest.** If sleep is the problem, fix sleep and let the lunchbox go for now.
2. **Ask the teacher one specific question.** Not how is he doing, but what time of day is hardest. Specific questions get real answers.
3. **Rebuild the evening around decompression.** A predictable, low demand hour after school pays for itself.
4. **Preview the differences.** If next week brings the first assembly or a schedule change, walk through it in advance with pictures.
5. **Write down what you saw.** Two lines a day. If you need the record in October, you will be glad it exists.
The Sunday night version of this struggle has its own post, [Sunday night dread before school](/blog/sunday-night-dread-before-school), and if every answer you get is fine, read [when fine is the only answer you get](/blog/how-was-school-fine-autism-parents).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the school day is something your child can see coming, not something that happens to them.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give week two a visual routine your child can trust. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Push-In Therapy or Pull-Out: What Evidence Says
Published: 2026-08-24
URL: https://vizyplan.com/blog/push-in-therapy-vs-pull-out-provider-guide
Category: For Providers
Author: Justin Bowman
> Fall scheduling forces the question every year. The evidence on push-in therapy versus pull-out is thinner than either camp claims, and what exists points at collaboration more than at location.
Every fall the schedule forces the same decision, usually in a hallway, usually in under a minute. Push-in therapy or pull-out. The choice gets defended with strong opinions on both sides, and the actual research base is much thinner than the confidence around it.
## What the evidence on push-in therapy really shows
An [evidence-based systematic review in Language, Speech, and Hearing Services in Schools](https://pubmed.ncbi.nlm.nih.gov/20421615/) searched thirty years of literature and found only five studies meeting criteria for comparing pullout, classroom-based, and consultative service delivery with elementary school-age children. The review concluded that classroom-based direct services are at least as effective as pullout for some intervention goals, and that clinicians must otherwise rely on reason-based practice and their own data.
Five studies is not a mandate for either model. It is permission to decide per student instead of per philosophy.
Where the evidence does point, it points at collaboration rather than at geography. In a [comparison of service delivery models](https://pubs.asha.org/doi/abs/10.1044/1058-0360.0901.10) published in the American Journal of Speech-Language Pathology, children in a collaborative classroom condition, where the therapist and the teacher planned and taught together, made greater curricular vocabulary gains than children in a classroom model where the therapist worked alone or in traditional pull-out.
Being in the room is not the active ingredient. Planning with the person who owns the room is.
## Deciding student by student
1. **Match the model to the goal.** Skills that need generalization into peers and curriculum favor the classroom. Discrete skills needing high trial density and quiet often do not.
2. **Ask what the student misses while out.** A pull-out during the only preferred subject of the day carries a cost that never appears in your data.
3. **Price the collaboration honestly.** Push-in without shared planning time tends to become parallel teaching, which the evidence does not support.
4. **Check who is watching.** Some students perform very differently with peers present, and that difference is information rather than noise.
5. **Write the decision down with a review date.** Revisit in eight weeks against your own data instead of defending it until spring.
## The number you will actually be asked for
Whichever model you choose, the spring conversation comes back to what you measured, which is why our post on [baseline data in the first month](/blog/baseline-data-first-month-provider-guide) matters more than the scheduling argument. Coordination across settings is covered in [school and clinic therapy coordination](/blog/school-clinic-therapy-coordination-provider-guide).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the same visual support follows the student between the classroom, the therapy room, and home.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the support does not stop at the classroom door.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Homework Accommodations That Hold Up at Home
Published: 2026-08-23
URL: https://vizyplan.com/blog/homework-accommodations-teachers-guide
Category: For Schools
Author: Justin Bowman
> The twenty minute assignment you set at dismissal is a ninety minute standoff in some houses. Homework accommodations decided in September prevent most of the conflict families never tell you about.
Twenty minutes of reading and a worksheet. In a number of the homes on your roster, that is a ninety minute standoff ending with a crying child, an exhausted parent, and a page finished by an adult. Homework accommodations agreed in September are the cheapest way to prevent a conflict most families will never report to you.
## What the homework research supports
The evidence for elementary homework is weaker than the tradition suggests. The most cited synthesis, [Cooper, Robinson, and Patall's 2006 review](https://journals.sagepub.com/doi/10.3102/00346543076001001) in Review of Educational Research, found the average correlation between time spent on homework and achievement was near zero for elementary students, while the relationship strengthened at secondary level.
The common ceiling comes from the same place. The [National Education Association and National PTA guideline](https://www.nea.org/professional-excellence/student-engagement/tools-tips/how-much-homework-too-much) is roughly ten minutes per grade level per night. A third grader is therefore working to a thirty minute expectation, and that guideline assumes a child who can start, sustain, and finish without a second adult beside them.
For students with executive function difficulty, none of those assumptions hold. Focus groups with autistic middle schoolers and their parents, [reported in the Journal of Autism and Developmental Disorders](https://pubmed.ncbi.nlm.nih.gov/30911979/), confirmed the need for direct support around academic executive function skills rather than more assigned work.
## Homework accommodations worth setting now
1. **Set a time cap, not a task cap.** Twenty minutes of genuine effort, signed by a parent, counts as complete. The cap protects the family and still tells you what the child could do.
2. **Cut the repetition.** Odd numbers only. Five problems demonstrate the skill as well as twenty and cost a quarter of the fight.
3. **Send the assignment where the parent can see it.** A photo of the board or a posted list removes the nightly guessing game about what was even assigned.
4. **Separate practice from performance.** Make clear which work is graded. Families will spend their limited energy correctly if they know where it counts.
5. **Ask each family once, in September, what home actually looks like.** Therapy schedules, siblings, and shift work shape homework more than motivation does.
## The part you do not see
By the time a student reaches the kitchen table, the school day has already spent most of what they had. A parent who reports that homework is impossible is usually describing depletion rather than defiance, a pattern our post on [after school restraint collapse](/blog/after-school-restraint-collapse-autism) explains in detail. The parent side of the same evening appears in [homework battles](/blog/homework-battles-adhd-autism-parents).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the evening has a visible shape instead of an open ended demand.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the plan you set at school has a structure at home.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Morning Routine Independence: Fading Your Prompts
Published: 2026-08-22
URL: https://vizyplan.com/blog/morning-routine-independence-fading-prompts
Category: Daily Routines
Author: Justin Bowman
> If the morning only works when you narrate every step, the routine is running on you. Morning routine independence comes from moving the prompts out of your voice and onto something your child can check.
The morning works. Shoes are on, the bag is packed, nobody cried. It works because you said fourteen sentences to make it happen, and if you stop talking, it stops moving. Morning routine independence is the difference between a routine your child has and a routine you are personally running.
## The help can become the thing they need
Constant adult help has a documented cost. A widely cited [study of instructional assistant proximity](https://journals.sagepub.com/doi/10.1177/001440299706400101) published in Exceptional Children found that close, continuous adult support produced eight distinct effects on students with disabilities, including dependence on adults and separation from classmates. The support was well intentioned. The dependence was still real.
Home works the same way. When the prompt always arrives in a parent's voice, the voice becomes part of the step. Take it away and the step disappears, which is why so many mornings feel like they reset every time you get quiet.
## Where morning routine independence comes from
The research on visual supports points at the same fix. In a [study using visual activity schedules with embedded video models](https://pubmed.ncbi.nlm.nih.gov/25413145/), students with autism transitioned independently within and between novel tasks, and their independence generalized to plain visual schedules after the video prompt was removed. The support faded and the skill stayed.
The principle is straightforward. A prompt your child can look at can be faded on a plan. A prompt you deliver out loud can only be faded by you going silent and hoping.
## Fading without losing the morning
1. **Write the steps down exactly as they happen now.** Not the ideal morning, the real one. Most families find seven or eight steps where they assumed three.
2. **Move your words onto the list.** Whatever you say at each step becomes a picture or a short line your child checks instead.
3. **Change your job from narrator to pointer.** Instead of "socks next," point at the list. Same information, different source.
4. **Drop one prompt per week, starting with the easiest step.** Fading everything at once is how families end up back where they started by Thursday.
5. **Hold the checkpoints even after the prompts go.** A quick look at the list before leaving stays useful long after the step-by-step help is gone.
Expect a slower week before a faster month. A child doing a step themselves takes longer than a child being moved through it, and the trade is worth making in August rather than in November.
The first minutes at school follow the same logic, which our post on [the first ten minutes of the school day](/blog/first-ten-minutes-of-the-school-day) covers, and the evening version shows up in [protecting the weekend](/blog/protecting-the-weekend-after-a-school-week).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the routine lives on a screen your child checks instead of in a voice they have to wait for.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Hand the morning back to your child one step at a time. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## How to Request an IEP Meeting This Fall
Published: 2026-08-21
URL: https://vizyplan.com/blog/request-an-iep-meeting-fall
Category: Parenting
Author: Justin Bowman
> The annual review is not the only door. You can request an IEP meeting at any point in the year, and the first month of school is often the most useful time to do it.
Three weeks in, something is not working. The accommodation on paper is not happening in the room, or the goal written in April no longer matches the child who walked in this September. You do not have to wait until spring to say so, because you can request an IEP meeting at any point in the year.
## What the rules say when you request an IEP meeting
Federal special education regulations require the IEP team to review the IEP [periodically, but not less than annually](https://sites.ed.gov/idea/regs/b/d/300.324). That is a floor, not a schedule. The same section requires the team to revise the IEP to address lack of expected progress, results of any reevaluation, and information about the child provided by the parents.
Parent-provided information is named in the regulation. What you are seeing at home is a legitimate trigger for the team to meet.
The scheduling rules work in your favor too. The district must notify parents [early enough to attend and schedule at a mutually agreed time and place](https://sites.ed.gov/idea/regs/b/d/300.322), and the notice has to state the purpose, the time, the location, and who will be there.
## How to ask so the team stays with you
1. **Put it in writing and date it.** Email is fine. A dated written request starts the clock and creates the record.
2. **Name the purpose in one sentence.** Review a specific goal, discuss a specific accommodation, or add data. A meeting with a defined purpose gets scheduled faster than a general one.
3. **Bring two weeks of observations, not a list of grievances.** Dates, times, what happened. Specifics are difficult to dismiss.
4. **Ask what data the school already has.** Requesting it before the meeting means you both walk in reading the same numbers.
5. **Say what outcome you are hoping for.** Teams respond better to a proposal than to an open-ended concern.
## Knowledge helps, delivery decides
A [study of 34 mothers in an advocacy training program](https://pubmed.ncbi.nlm.nih.gov/30815933/) found significant gains in special education knowledge and self-mastery, alongside a decrease in how parents rated the quality of their family-school partnership. Learning your rights can strain the relationship in the short term. The finding is not an argument for staying quiet. It is an argument for asking in a way that keeps the people who see your child every day on your side.
The email itself is worth getting right, which our post on [the first email to your child's teacher](/blog/first-email-to-your-childs-teacher) covers, and the accommodations conversation is easier when the team already shares a picture, as in [home school communication that works](/blog/home-school-communication-that-works).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so what happens at home is something you can show a team rather than something you have to describe.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Walk into the meeting with the home picture already in your hand. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Missed Therapy Appointments: The September Drop
Published: 2026-08-20
URL: https://vizyplan.com/blog/missed-therapy-appointments-september-provider-guide
Category: For Providers
Author: Justin Bowman
> Attendance dips every fall and most caseloads absorb it as bad luck. The research on missed therapy appointments points at scheduling, illness, and authorization far more often than at motivation.
The first three weeks of school reshuffle every family calendar you serve, and your schedule is downstream of all of it. Missed therapy appointments climb in September, and the reasons are far more logistical than most clinicians assume when they see the gap on the board.
## Missed therapy appointments are more common than most clinics track
A [retrospective review of 306 autistic youths](https://pubmed.ncbi.nlm.nih.gov/39969764/) in an outpatient behavioral clinic, published in the Journal of Autism and Developmental Disorders, found an average of 5.2 cancelled appointments against 9.0 completed ones. The average individual cancellation rate was 38 percent.
The reasons matter more than the number. The most common were sickness, scheduling conflict, insurance authorization issues, and family emergency. Younger children and post-pandemic appointments carried higher no-show risk.
Not one of those categories is a motivation problem. A family fighting an authorization renewal is not ambivalent about therapy. A family whose child brought home the first cold of the school year is not disengaged.
## What actually protects a fall schedule
1. **Re-confirm the standing slot in the first week of school.** The time that worked in July is often the time the new bus route or pull-out schedule just took.
2. **Check authorizations before the calendar breaks, not after.** Authorization lapses show up as cancellations, and they are visible weeks in advance if somebody is watching.
3. **Ask the transport question directly.** Distance and logistics predict attendance, and a family will rarely volunteer that the drive no longer fits.
4. **Offer one flexible alternative rather than a rebook.** A shorter virtual check-in preserves the thread when the in-person hour is impossible.
5. **Track your own cancellation pattern by month.** You cannot argue for a schedule change, or a caseload change, without the number.
## The conversation to have in week one
Families rarely say the quiet part first. Ask what the new school schedule looks like, what time the child gets home, and how much is left in the tank when they do. What you hear will predict your attendance better than any reminder system.
That first conversation is also where the parent partnership gets set for the year, which our post on [parent coaching in the first six weeks](/blog/parent-coaching-first-six-weeks-provider-guide) covers, and it pairs with the practical work in [fitting therapy into a full school schedule](/blog/fitting-therapy-school-schedule-provider-guide).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the week a family is actually living is visible to everyone supporting them, including you.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the plan survives the weeks they cannot make it in.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Handwriting Difficulties in Autism: A Teacher Guide
Published: 2026-08-19
URL: https://vizyplan.com/blog/handwriting-difficulties-autism-classroom
Category: For Schools
Author: Justin Bowman
> September brings more writing demand than any other month of the year. Handwriting difficulties in autism are common, physically real, and easy to mistake for refusal in the first weeks of class.
Name at the top, date, three sentences about your summer. Fifteen minutes later one student has written four words and is holding the pencil like it wronged them. Handwriting difficulties in autism are one of the most common reasons a September assignment stalls, and one of the easiest things to read as refusal.
## Handwriting difficulties in autism are physical before they are behavioral
A [scoping review in the Journal of Autism and Developmental Disorders](https://pubmed.ncbi.nlm.nih.gov/21350917/) found that impairments in fine motor control and visual-motor integration are the likely contributors to handwriting problems in autistic children, with reduced overall legibility and compromised letter formation being the consistent findings across studies.
Motor difficulty is also far more widespread than most staff rosters suggest. Using data from 11,814 autistic children aged 5 to 15 in the SPARK study, a [2020 analysis in Physical Therapy](https://pubmed.ncbi.nlm.nih.gov/32154876/) found 86.9 percent were at risk for a motor impairment, and only 31.6 percent were receiving physical therapy. The impairments persisted into adolescence rather than resolving.
Translated into a classroom: for many autistic students, forming letters is effortful work competing directly with the thinking the assignment is meant to assess.
## What to change in the first weeks
1. **Separate the writing from the knowing.** If the goal is comprehension, let the student say it, type it, or dictate it. Score the content, not the letters.
2. **Cut volume before you cut expectations.** Five sentences becomes three. Every worksheet item becomes the odd numbers. The skill is unchanged and the motor load is halved.
3. **Pre-print the repeated parts.** Name, date, headers, and the copy-from-the-board portion are pure motor cost with no learning attached.
4. **Watch grip and posture for two minutes.** Feet flat, paper angled, a slanted surface if you have one. Small setup changes cost nothing and often buy a full sentence.
5. **Refer for an OT screen rather than waiting.** Given how few autistic students with motor difficulty are receiving services, referral is usually the right call in month one.
## A refusal that is not refusal
A student who writes nothing after ten minutes is often telling you the demand is out of reach, not that they will not comply. Treating that as a behavior problem in September tends to produce an actual behavior problem by October, a pattern our post on [school refusal in week three](/blog/school-refusal-week-three-autism) covers in detail.
The other half of the picture is home. A student who spends the day fighting a pencil arrives home with nothing left, which is worth saying out loud to families rather than letting them discover it, as our post on [after school restraint collapse](/blog/after-school-restraint-collapse-autism) describes.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the picture of a task carries the instruction, and the writing is no longer the only way in.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so what works at your desk keeps working at their kitchen table.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Losing School Supplies Every Week: What Helps
Published: 2026-08-18
URL: https://vizyplan.com/blog/losing-school-supplies-executive-function
Category: Parenting
Author: Justin Bowman
> The folder, the jacket, and the third water bottle of the month are all somewhere at school. Losing school supplies is usually a working memory problem, and working memory responds to external systems rather than reminders.
The water bottle is somewhere at school. So is the reading folder, one glove, and the permission slip you signed on Tuesday. Losing school supplies week after week looks like carelessness from the outside, and most children doing it are working harder than anyone in the building realizes.
## Losing school supplies is a memory problem, not a character problem
Working memory is the mental scratchpad that holds a few pieces of information while you do something else with your hands and your attention. It is small in everyone and smaller in many neurodivergent children.
An [age-stratified study of 111 autistic youths](https://pmc.ncbi.nlm.nih.gov/articles/PMC4873936/) and 114 typically developing peers found spatial working memory deficits in both the 8 to 12 and 13 to 18 age groups, with planning and mental flexibility hardest in the younger band. The deficits did not disappear with age.
Now picture the actual moment. A bell rings, twenty five children stand up at once, a teacher gives three instructions out loud, and your child is expected to hold folder, jacket, and bottle in mind while navigating all of it. The system being taxed is the exact one that is thinnest.
## What the research actually improved
Brief, external, checked systems work. The Homework, Organization, and Planning Skills program is one of the better tested versions. In a [randomized trial with 47 middle school students](https://pmc.ncbi.nlm.nih.gov/articles/PMC4209597/), parents rated large improvements in materials management, planning, and homework completion after short sessions delivered at school. A [larger replication with 280 students](https://pubmed.ncbi.nlm.nih.gov/29172596/) found sessions averaged under twenty minutes and still produced large effects on parent-rated homework problems.
The active ingredient in both was not motivation. It was a short checklist that somebody looked at on a schedule.
## A checking routine that takes four minutes
1. **Choose one landing spot at home.** One hook, one bin, one shelf by the door. Everything school related lives there and nowhere else.
2. **Cut the leaving list to three items.** Three things your child checks before walking out of the classroom. Ten items is a list nobody runs.
3. **Make the list visual and portable.** A picture list taped inside the binder beats a verbal reminder given at 7:40 in the morning.
4. **Check at two fixed moments.** Once at the end of the school day and once at the landing spot at home. Same times every day, no negotiation.
5. **Fade slowly, and only after two clean weeks.** Move from checking with your child to asking whether the list is done, then to a spot check on Fridays.
The paperwork side of this deserves its own system, which our post on [back to school paperwork](/blog/back-to-school-paperwork-overwhelm) covers, and the evening version shows up in [homework battles](/blog/homework-battles-adhd-autism-parents).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the checklist lives somewhere your child can see it instead of somewhere you have to remember it.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Let the routine do the remembering, so the end of the day stops being a search. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Baseline Data in the First Month of School
Published: 2026-08-17
URL: https://vizyplan.com/blog/baseline-data-first-month-provider-guide
Category: For Providers
Author: Justin Bowman
> The baseline you take in September is the number every claim you make this year gets compared against. It is worth more care than the calendar usually allows.
Every claim you make in the spring meeting gets measured against a number you take in the next three weeks. Baseline data collected in the first month of school is the most consequential data of the year, and it is usually gathered in the busiest and least representative conditions of the year.
## Why baseline data taken now can mislead
Two problems arrive at once. The first is setting. A [multi-site randomized trial analysis](https://pmc.ncbi.nlm.nih.gov/articles/PMC8691726/) in Research in Autism Spectrum Disorders found that 126 of 168 children showed zero disruptive behavior during structured direct observation, despite moderate disruptive behavior being required for enrollment. A clean clinic baseline can mean the room, not the child.
The second is timing. A child three weeks into a new classroom, a new teacher, and a new bus is not at their stable level. Take a number now and you may be measuring the transition rather than the skill.
Neither is a reason to skip it. Both are reasons to record what the conditions were.
## What to actually capture
1. **Probe before you teach.** Cold probes on three to five priority targets in session one. It is the only clean baseline you get all year.
2. **Record the context alongside the number.** Time of day, setting, who was present, how far into the school year. A number without conditions cannot be compared to anything.
3. **Take at least two points, not one.** A single session is noise. Two or three across different days tells you where the middle is.
4. **Get a home number too.** Parent report catches what a clinic room does not. A [study of 109 toddlers](https://pmc.ncbi.nlm.nih.gov/articles/PMC5599144/) found parents frequently reported skills that direct testing had missed.
5. **Write down the criterion now.** What will count as progress in six months, decided before you are invested in the answer.
## Keep the system light enough to run
Ambitious data plans collapse. A [2024 survey of 203 BCBAs](https://pmc.ncbi.nlm.nih.gov/articles/PMC12779883/) found most collected procedural-fidelity data on 20 percent or fewer of their supervision sessions, and the reasons were logistical rather than motivational: time, caseload, resources. If trained clinicians with dedicated time cannot sustain heavy data collection, a plan that assumes they can is a plan that produces gaps.
The lightest baseline is one nobody has to remember. A visual routine that a family already runs records completion as a byproduct, which our post on [home data collection](/blog/home-data-collection-parents-provider-guide) covers in detail.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the routine a family runs anyway becomes the evidence you need in the spring.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the fall baseline includes what home actually looks like.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Sunday Night Dread: When the Week Starts on Sunday
Published: 2026-08-16
URL: https://vizyplan.com/blog/sunday-night-dread-before-school
Category: Parenting
Author: Justin Bowman
> The weekend was fine until about five in the afternoon. Sunday night dread is anticipatory, which means reassurance rarely touches it and information usually does.
The weekend went well until roughly five o'clock on Sunday. Then the questions start, the stomach ache appears, and bedtime takes ninety minutes. Sunday night dread is one of the most predictable patterns in a school year, and it responds to a completely different approach than most parents reach for first.
## Sunday night dread is about uncertainty, not defiance
The instinct is to reassure. It will be fine, you like your teacher, you had a good week. That rarely works, because the driver is usually not fear of school as a concept but the unknowns in the week ahead.
A [study of 64 autistic children](https://link.springer.com/article/10.1007/s10803-016-2721-9) published in the Journal of Autism and Developmental Disorders found that anxiety mediated the relationship between intolerance of uncertainty and sensory sensitivities. Not knowing is itself a driver of distress rather than a neutral state, which is why concrete information tends to land where comfort does not.
Sleep makes it heavier. Between [40 and 80 percent of autistic children](https://pubmed.ncbi.nlm.nih.gov/32112261/) experience sleep difficulties, compared with 20 to 30 percent of typically developing children. A dreaded Sunday plus a hard night produces a Monday that was decided the evening before.
## A Sunday evening that ends earlier
1. **Do the practical part early, not at bedtime.** Bags packed, clothes out, week reviewed, all before dinner. Planning at 8pm activates rather than settles.
2. **Show the week, including the unusual bits.** Assembly, substitute, a therapy appointment. The specific unknowns are what your child is actually carrying.
3. **Name one thing to look forward to.** Something real and in the week, however small. It gives Monday a shape that is not purely obligation.
4. **Return to weekday sleep timing that night.** A large weekend shift makes Monday considerably harder for most children.
5. **Answer repeated questions by pointing, not re-explaining.** Point at the plan. Re-answering verbally tends to reinforce the asking.
## When it is more than an evening
If Sunday dread has become Sunday and Monday and physical symptoms most mornings, that is a different problem. Our post on [school refusal](/blog/school-refusal-week-three-autism) covers what the research says about the pattern and when to bring the school and your clinician in. Waiting for it to settle on its own is the one approach the evidence does not support.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the week ahead is something your child can look at on Sunday afternoon rather than something they have to imagine.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Let your child see the week before it starts, so Sunday evening has less to carry. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Protecting the Weekend After a Hard School Week
Published: 2026-08-15
URL: https://vizyplan.com/blog/protecting-the-weekend-after-a-school-week
Category: Parenting
Author: Justin Bowman
> Two weeks in, the reserve your child started the year with is gone. What you do with Saturday decides a lot about what Monday looks like.
Two weeks into the school year, the novelty has worn off and whatever reserve your child started with has been spent. Protecting the weekend sounds indulgent when there are birthday parties, swimming, and a grandparent who wants a visit. It is the opposite of indulgent. It is the thing that decides how Monday goes.
## Why protecting the weekend actually matters
A child who holds themselves together through a full school week is running a deficit, not breaking even. That accumulated load gets released once they reach somewhere safe, which is the pattern described in our post on [after-school restraint collapse](/blog/after-school-restraint-collapse-autism). Across five days it compounds.
The stakes are real. A [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) in Frontiers in Psychiatry found that among children experiencing significant school distress, 92.5 percent scored above the clinically significant threshold for anxiety. That distress rarely arrives from one catastrophic day. It accumulates across ordinary weeks where nothing looked especially wrong.
And when the deficit runs long enough, skills start disappearing rather than just wobbling. Our post on [autistic burnout warning signs in kids](/blog/autistic-burnout-in-kids-warning-signs) covers what that looks like, and the answer there is fewer demands rather than better ones.
## What a protected weekend actually looks like
1. **Keep one day genuinely empty.** Not lightly scheduled. Empty. Most families find Saturday works better than Sunday, because Sunday already carries the week ahead.
2. **Hold the anchors, drop everything else.** Waking, meals, and bedtime stay close to weekday timing. The content of the day is what gives way.
3. **Let your child pick the day.** Within limits, and honour the choice even when it is eleven hours of the same interest.
4. **Say no to one thing you would normally accept.** A party, a visit, an outing. One is enough to change the week.
5. **Do not fill the space with enrichment.** A weekend packed with worthy activities is still a full weekend, and a depleted child cannot tell the difference.
## The part that is hard for parents
The cost is usually social. Declining the invitation, explaining it to a relative, watching other families do more. That is a real cost and it is worth paying, because the alternative is spending it on Monday morning instead, with interest.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a low-demand day still has a visible shape, which is what lets a child relax into it rather than keep asking what happens next.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give a quiet day a shape your child can see, without turning it into a schedule. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The First Ten Minutes of the School Day
Published: 2026-08-14
URL: https://vizyplan.com/blog/first-ten-minutes-of-the-school-day
Category: For Schools
Author: Justin Bowman
> Arrival is the least planned part of most school days and the one that decides how the next three hours go. Ten minutes of structure buys back more than it costs.
Most classroom planning starts at the first lesson. But the first ten minutes of the school day, between the door opening and instruction beginning, is where a considerable amount of the morning is decided, and it is usually the least designed stretch of the timetable.
## Why the first ten minutes of the school day are worth planning
The arithmetic on lost time is startling. One [analysis of classroom time loss](https://files.eric.ed.gov/fulltext/EJ1086382.pdf) calculated that six minutes lost at the start of every lesson adds up to roughly 5,700 minutes across a school year, the equivalent of about five full weeks of school. Arrival is the largest of those starts.
The behavioural case is just as clear. The Campbell Collaboration's [systematic review of teacher classroom management practices](https://onlinelibrary.wiley.com/doi/10.4073/csr.2011.4) found that deliberate management practices reduce disruptive and aggressive student behaviour. Deliberate is the operative word: a routine that has been taught works, and one that is merely expected does not.
For students arriving already dysregulated from a bus or a difficult morning, the stakes are higher. Research on [visual supports and transitions](https://eric.ed.gov/?id=EJ614699) by Dettmer and colleagues found that showing what comes next reduced the delay between an instruction and a student starting, compared with telling alone.
## An arrival routine worth teaching
1. **Fix the first ninety seconds.** Bag here, folder there, chair down, start the task. Same order every day, taught explicitly rather than assumed.
2. **Put the sequence on the wall at student height.** Not on your desk. The point is that students read it instead of asking you.
3. **Give arrival an actual task.** A short, low-demand, genuinely optional activity. Reading, drawing, a puzzle. Something that absorbs a child who arrived early and rattled.
4. **Greet at the door, by name.** It is thirty seconds of work and it is the highest-information moment of your morning. You learn who arrived in trouble before the lesson starts.
5. **Do not open with the hardest thing.** A run of easy, familiar tasks first builds momentum into the demanding one, which is exactly what the research on request sequencing predicts.
## What it buys you
A settled arrival is not a soft nicety. It is the cheapest classroom management available, it costs ten minutes you were already spending, and it disproportionately helps the students who arrive with the least in reserve.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the arrival sequence a student follows at school can look like the one they followed at home an hour earlier. Our [visual schedule guide for teachers](/blog/visual-schedule-classroom-teacher-guide) covers building one for a whole class.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the morning at home and the morning at school run the same way.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Yes, Your ESA Funds Can Pay for VizyPlan — Here's Exactly How
Published: 2026-08-13 · Updated: 2026-08-13
URL: https://vizyplan.com/blog/pay-for-vizyplan-with-esa-funds
Category: Announcements
Author: Justin Bowman
> VizyPlan is now an approved vendor on ClassWallet. If your child has an Arizona Empowerment Scholarship Account, your scholarship funds can cover their visual schedules — often with nothing out of pocket. Here's the step-by-step.
Every week a parent tells me some version of the same sentence: "We want to keep using it, but money is tight this month." I never argue with that sentence. Families like ours are already paying for therapies, evaluations, special diets, and the forty other things insurance decided were optional. A subscription — even a small one — has to earn its place in that budget.
So this is the announcement I've wanted to make for a while: **VizyPlan is now an approved vendor on ClassWallet.** If your child has an Arizona Empowerment Scholarship Account, your ESA funds can pay for VizyPlan directly — which for most families means nothing out of pocket at all.
## What an ESA is, in one paragraph
Arizona's [Empowerment Scholarship Account program](https://www.azed.gov/esa) gives families state education funds to spend on their child's learning — curriculum, tutoring, therapies, and educational technology. The money sits in an account you direct, and Arizona disburses it through a platform called ClassWallet, where you pay approved vendors directly from your child's funds. Visual scheduling software built for autistic and ADHD learners is exactly the kind of educational support the program exists to cover.
## How to pay for VizyPlan with your ESA
**Step 1 — start the free trial first.** Set up VizyPlan at [app.vizyplan.com](https://app.vizyplan.com/) with the free 7-day trial (no card required). Build your child's first routine and make sure they respond to it before you spend a dollar of your award. Your ESA funds are precious — I'd rather you test first.
**Step 2 — log in to ClassWallet.** Use your ESA parent account, the same place you handle your other program purchases.
**Step 3 — find VizyPlan among approved vendors and submit the payment.** I recommend running the annual plan ($59.99) through ClassWallet: it's one transaction, one approval, and your child is covered for a full year — no monthly resubmitting.
**Step 4 — if anything looks confusing, email me.** Write to [info@vizyplan.com](mailto:info@vizyplan.com) and I'll walk you through it personally. I'm the founder, and I answer these emails myself — usually the same day.
## What to tell your ESA coordinator it's for
If you're asked to describe the purchase: "Educational software providing visual scheduling, routine-building, and executive-function support for a student with autism/ADHD." If your child has an IEP or 504 plan, it's worth mentioning that VizyPlan includes an IEP/504 summary export their team can use — it makes the educational purpose obvious.
## Not in Arizona?
More states are launching education savings programs every year, and several use ClassWallet or similar platforms. If your family has education funds through your state, email [info@vizyplan.com](mailto:info@vizyplan.com) with your state and program name — I'll tell you honestly whether it can work with VizyPlan yet, and if it can't, I'll start the paperwork on our end. Some families have also used HSA/FSA funds when VizyPlan was recommended by their child's provider, and some state waiver programs cover assistive technology — ask your coordinator, and ask me.
The price of a tool should never be the reason a child keeps struggling with mornings. If the funds exist to remove that barrier for your family, I want you to use them.
---
## Should You Observe in the Classroom? A Provider Guide
Published: 2026-08-13
URL: https://vizyplan.com/blog/classroom-observation-provider-guide
Category: For Providers
Author: Justin Bowman
> A child who presents as regulated in your room may be unrecognizable in a classroom at two in the afternoon. The data on how much clinic observation misses is worth knowing before you write the plan.
A child arrives in your clinic room at nine in the morning, rested, one-to-one, in a space with controlled lighting and no peers. They present beautifully. Then the teacher describes someone you do not recognize. Classroom observation is how that gap gets closed, and the evidence for why it matters is more striking than most providers realize.
## What classroom observation catches that a clinic room cannot
The most useful finding here comes from a [multi-site randomized trial analysis](https://pmc.ncbi.nlm.nih.gov/articles/PMC8691726/) in Research in Autism Spectrum Disorders. Of 168 children enrolled, 126 showed zero disruptive behavior during structured direct observation at baseline, even though moderate disruptive behavior was a requirement for enrollment. The observation measure could not detect group differences that parent-report and clinician-rated measures found significant.
Read that carefully. The behavior did not disappear. The setting simply was not where it lived.
Parent report holds up better than its reputation too. A [comparative study of 109 toddlers](https://pmc.ncbi.nlm.nih.gov/articles/PMC5599144/) found no significant differences between parent report and direct assessment for receptive or expressive language, and where the two diverged, parents tended to report skills that direct testing had missed.
## Making the hour count
1. **Pick the hard part of the day, not a convenient slot.** Observing at 9:15 tells you very little. Go at the transition the teacher named.
2. **Watch the environment, not only the child.** Noise, seating, who is nearby, what happens in the two minutes before the difficulty starts.
3. **Get the antecedent, not the incident.** The useful data is what preceded the moment, and it is invisible in any retrospective report.
4. **Ask the staff one question afterward.** What do you wish somebody had told you in August. The answer usually reshapes the plan.
5. **Leave one thing behind.** A single concrete change staff can make tomorrow, in writing. An observation that produces only a report changes nothing.
## When you genuinely cannot go
Not every caseload allows a school visit, and pretending otherwise helps nobody. The fallback is structured information from the people who are there: a short daily rating from the teacher, and home data that the family already generates. Our post on [home data collection families keep up with](/blog/home-data-collection-parents-provider-guide) covers how to design that so it survives a real week.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the same routine runs at school and at home, which makes the difference between the two settings visible rather than anecdotal.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so you can see what the classroom and the kitchen table each look like.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Back to School Paperwork: The Avalanche Nobody Warns You About
Published: 2026-08-12
URL: https://vizyplan.com/blog/back-to-school-paperwork-overwhelm
Category: Parenting
Author: Justin Bowman
> Forms, folders, permission slips, medication authorizations, and an IEP to track. The administrative load of a school year is real work, and for families of disabled children it is measurably heavier.
Back to school paperwork arrives all at once: emergency contacts, media release, medication authorization, transportation forms, the reading log, the volunteer sign-up, and somewhere underneath it an IEP with dates you are expected to track. It feels like it should be trivial. It is not, and there is research explaining why it lands so hard on some families.
## Back to school paperwork is heavier for some families than others
A [2025 study in Educational Evaluation and Policy Analysis](https://journals.sagepub.com/doi/10.3102/01623737251378492) titled "You Have to Stay on Top of It" examined the administrative burdens parents carry in special education. The finding is not that the paperwork exists but where the responsibility sits: parents are the ones expected to initiate evaluation requests, help build the IEP, and enforce their child's rights. The study describes learning costs, compliance costs, and psychological costs, and notes these compound further for Parents of Color.
That is the part worth naming out loud. If you feel like the school year came with a second unpaid job, you are describing something researchers have measured rather than a personal failure of organization.
## A system that survives October
1. **Do the whole stack in one sitting.** Set a timer, put on something loud, and finish it. Paperwork done in pieces gets lost between the pieces.
2. **Photograph everything before it goes back.** One album on your phone. It costs three seconds and saves an argument in February.
3. **Keep one folder, not a system.** A single physical folder by the door beats a beautiful filing structure nobody maintains past week four.
4. **Put every IEP date in a calendar the day you get it.** Annual review, reevaluation, progress report dates. Those are the ones that quietly expire.
5. **Write down who you spoke to and when.** One line, in one note. It is the difference between a recollection and a record.
## What to let go of
Not every form deserves equal effort. The emergency contacts, the medication authorization, and the IEP dates matter. The laminated reading log does not. Deciding that in advance is how you stop treating a permission slip with the same seriousness as a legal document.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist, and it keeps the documents, the notes, and the plan in one place so the folder by the door is not the only copy. Our post on [not treating an IEP like a pamphlet](/blog/autism-iep-plan-not-a-pamphlet) covers what to do with it once it exists.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Keep the plan, the notes, and the routine somewhere you can actually find them. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The First Email to Your Child's Teacher
Published: 2026-08-11
URL: https://vizyplan.com/blog/first-email-to-your-childs-teacher
Category: Parenting
Author: Justin Bowman
> Most parents first email a teacher when something has already gone wrong. Sending one in week two, before there is a problem, changes what every message after it sounds like.
Most parents send their first email to a teacher in October, and it is about a problem. The first email to your child's teacher lands very differently when it arrives in week two, before anything has gone wrong, and it changes the tone of every message that follows it.
## What the research says about the first email to your child's teacher
The evidence here is stronger than most people expect. In a [randomized field experiment](https://eric.ed.gov/?id=EJ1164707) published in the Journal of Research on Educational Effectiveness, Kraft and Dougherty found that regular teacher-family communication increased the odds a student completed their homework by 42 percent and reduced the times a teacher had to redirect a student's attention by 25 percent. Among sixth graders, class participation rose 49 percent.
That study measured communication going from school to home. The same relationship works in reverse, and you are the one who can start it. Research on [parent perspectives where students have a disability](https://www.tandfonline.com/doi/full/10.1080/13540602.2023.2241020) found that ordinary, welcoming exchanges are foundational to the partnership rather than a nicety layered on top of it.
## What to actually put in it
Keep it under 150 words. A teacher with 24 students will read a short email and skim a long one.
1. **Lead with something specific and warm.** Name one thing your child has mentioned about the classroom. It signals you are paying attention rather than lining up a complaint.
2. **Give the two things that help most.** Not the full history. The two adjustments that change your child's day, in one sentence each.
3. **Name what escalation looks like early.** Describe the signal that comes ten minutes before anyone else would notice. This is the single most useful thing you can hand a teacher.
4. **Offer, do not ask.** Say what you can do from home. That flips the message from a request into an offer.
5. **Close with an open door.** One line inviting them to contact you any time, and mean it.
## Why week two rather than week one
Week one is chaos for a teacher, and an email sent then competes with 24 other families and a room that does not run yet. By week two the routines have started to settle and your child has become a person rather than a name. That is when a short, specific, generous email actually gets read.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the routine your child follows at home can be shared with the teacher as something they can see rather than something you have to describe. Our guide to [building a one-page profile](/blog/one-page-profile-autism-new-teacher) covers what to attach.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Share the routine that works at home so school can run the same one. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## School Schedule Changes: Picture Day, Assemblies, and Early Release
Published: 2026-08-10
URL: https://vizyplan.com/blog/school-schedule-changes-autism-parents
Category: Strategies
Author: Justin Bowman
> Nothing undoes three good weeks faster than a Tuesday that is not a normal Tuesday. The school calendar knows about it in July. Getting that information early is the whole strategy.
Three weeks of a good routine, and then a Tuesday that is not a normal Tuesday. Picture day. An assembly. Early release. A field trip. A pep rally nobody mentioned. School schedule changes cost more than any single hard day, because they do something worse than being difficult: they teach a child that the schedule cannot be trusted, and that lesson gets applied to every future Tuesday.
## Why school schedule changes hit harder than they look
Intolerance of uncertainty is the technical name for how much distress an unknown outcome causes, and it is unusually elevated in autistic people. A [study of 64 autistic children ages 6 to 14](https://link.springer.com/article/10.1007/s10803-016-2721-9) published in the Journal of Autism and Developmental Disorders found that anxiety mediated the relationship between intolerance of uncertainty and sensory sensitivities, meaning the uncertainty and the sensory load feed each other rather than sitting side by side.
That is exactly the recipe an assembly delivers. An unfamiliar sequence, in an unfamiliar room, that is also loud. In a sample of 4,104 autistic people, [60.1 percent currently experienced auditory over-responsivity](https://link.springer.com/article/10.1007/s10803-021-04991-0). A gymnasium with four hundred children in it is one of the loudest environments in a child's year.
And the broader picture explains why a string of these matters. A [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) found 92.5 percent of children in serious school distress scored above the clinically significant anxiety threshold. School distress is rarely built from one catastrophe. It is built from a school year that keeps proving unpredictable.
## Get the calendar in August, not the night before
The single highest-value thing on this list takes ten minutes. Ask the school office for the full-year calendar of non-standard days, and then ask specifically for the ones that never make it onto the printed version.
The printed calendar usually covers holidays and early release. It usually does not cover picture day, the first fire drill, book fair week, the fall assembly, spirit days, testing windows, or the week the schedule shifts for a special program. Those live in a teacher's plan book or a building calendar, and most schools will happily share them if a parent asks in the first week.
Once you have the list, the rest is preparation rather than reaction.
## Preparing your child for a day that is different
1. **Tell them early and tell them once.** Two to three days ahead for most children. Too far out gives anxiety time to build, and the night before gives no time to process. Say it clearly, then let the visual do the repeating.
2. **Show the changed sequence, not just the change.** "Tuesday is picture day" is an abstraction. Arrival, morning work, line up, gym, photo, back to class, lunch is a plan. Our post on [why autistic kids resist transitions](/blog/why-autistic-kids-resist-transitions) covers why the sequence matters more than the announcement.
3. **Name what stays the same.** The reassuring part of a changed day is the unchanged part. Same teacher, same seat, same lunch, same pickup. Say those out loud.
4. **Solve the one hard element specifically.** Picture day means a stranger, a flash, and a clothing change. An assembly means noise and a crowd. Prepare for the actual element, not the day as a whole.
5. **Ask for the small accommodation in advance.** Photographed first, before the line forms. Seated at the end of a row near a door. Permission to skip the pep rally in the library. These are almost always granted when asked a week ahead, and almost never when asked that morning.
6. **Protect the evening.** A day with a change costs more energy than a normal day even when it goes well. Lower the demands that night on purpose.
## Practice being flexible on low-stakes days
There is a longer game worth playing here too. A child who only ever encounters change during high-stakes school events gets no practice. Building small, planned, harmless changes into ordinary weeks at home, a different route, a swapped order at bedtime, a surprise that is fun, builds tolerance in a setting where the cost of a hard reaction is nearly zero.
Programs built specifically to target intolerance of uncertainty in autistic children take exactly this approach, gradually and with parent support rather than by exposure alone. The [CUES feasibility trial](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10465370/) describes a parent-delivered version of that idea.
## Make the changed day visible before it arrives
Everything above depends on your child being able to see the new plan rather than hear about it once. A day they can look at is a day they can rehearse.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a changed day can be shown in photos of your child's real school, the night before and again in the morning, with the parts that stay the same still visible around it.
Ask for the calendar this week. It is ten minutes in August that saves you six bad Tuesdays.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Show your child the days that are different before they walk into them. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Making Friends at School: What Research Really Found
Published: 2026-08-09
URL: https://vizyplan.com/blog/making-friends-at-school-autism
Category: Parenting
Author: Justin Bowman
> A study that put proximity sensors on children at recess found something surprising. Autistic children were not alone on the playground. What they had less of was mutual.
You watch your child at pickup, standing near a group rather than in it, and the worry arrives on schedule. Making friends at school is the thing parents of autistic children lose the most sleep over, and it is also the area where the research quietly disagrees with the assumptions most of us are carrying.
## What the research found about making friends at school
A [2024 study published in Autism](https://pmc.ncbi.nlm.nih.gov/articles/PMC11656637/) took an unusually direct approach. Researchers put RFID proximity sensors on 47 autistic children and 52 allistic classmates, ages 8 to 13, and tracked actual face-to-face contact during recess alongside peer nominations and self-reports.
The results are worth sitting with. There were no significant group differences in total time spent in social contact, in the number of interaction partners, or in playground centrality. The autistic children were not physically isolated. What they did have was significantly fewer reciprocated friendships, meaning fewer cases where a child named a peer and that peer named them back.
And loneliness itself showed no group difference overall. What differed was what predicted it. For autistic children, lower loneliness tracked with being more central among classmates. For allistic children, it tracked with time spent in social contact. Different children were getting their sense of connection from different things.
A separate [2023 study in Molecular Autism](https://pmc.ncbi.nlm.nih.gov/articles/PMC9960478/) of 100 children ages 6 to 15 found most children in both groups reported having at least one friend, but ten autistic children described being often lonely, a pattern absent among non-autistic participants. Every one of those frequently lonely children still reported having a friend.
## What that actually means for your child
Three things follow, and they change what is worth working on.
**Proximity is not the goal.** Being on the playground with other children is already happening. Pushing for more social exposure is solving a problem that the data suggests is not the bottleneck.
**Reciprocity is the goal.** The gap is in mutual, named, two-way friendship. That is a smaller and more solvable target than "social skills," and it usually needs a structure rather than a lesson.
**Having a friend does not rule out loneliness.** If your child says they feel lonely and also has a friend, both things are true. Do not argue them out of it.
## Six things that build the mutual kind
1. **Aim for one, not a group.** One reciprocated friendship does more for a child's week than being tolerated by eight. Ask your child who they like, not who likes them.
2. **Build it around a shared interest, not a social occasion.** Two children who both care about the same thing have a reason to talk. Two children in a room have an obligation. Our post on [special interests as a skill engine](/blog/special-interests-autism-build-skills-engine) covers how to use that deliberately.
3. **Host, and keep it short and structured.** Ninety minutes, at your house, with a planned activity and a clear end. Home turf, known rules, and an exit make a first playdate survivable.
4. **Ask the teacher who your child gravitates toward.** Teachers see the pattern you do not. That question is more useful than asking whether your child has friends.
5. **Support the friendship, do not coach the child out of themselves.** The instinct to teach a child to mask better is understandable and it has costs. Our post on [the double empathy problem](/blog/double-empathy-problem-autism-social-skills-parents) covers why social difficulty is usually a two-way mismatch rather than a deficit to correct.
6. **Protect the recovery time around it.** Socializing is expensive. A playdate on the same afternoon as a hard school day will not go well, and that is a scheduling issue rather than a social one.
## A word about the start of the year
The first weeks of school are when groups form and then set, which makes early September genuinely higher leverage than October. It is worth asking, in that first week, whether your child can be seated near a specific peer, or paired for a first project. Small structural nudges early do more than social coaching later.
It is also worth remembering that unstructured time is where this all happens, and unstructured time is the hardest part of the school day for a lot of these students. Our post on [recess and lunch](/blog/unstructured-time-recess-lunch-autism-teachers) covers what schools can put in place, and it is a reasonable thing to raise with a teacher.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the parts of the day that are hardest to predict, including recess and a first playdate, can be shown in advance instead of walked into cold.
One friend who names your child back is the whole goal. It is a much smaller target than the one most of us are carrying around, and it is reachable.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Let your child see the social parts of the day coming, from recess to the first playdate. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Home School Communication That Parents Actually Read
Published: 2026-08-08
URL: https://vizyplan.com/blog/home-school-communication-that-works
Category: For Schools
Author: Justin Bowman
> Most home school communication systems die in October. The ones that survive share three things, and none of them involve writing more.
In August you promise a daily note home. By late September it has become a note on hard days. By November it has become an email when something goes wrong, which trains families to feel dread whenever your name appears in an inbox. Home school communication almost never fails because anyone stopped caring. It fails because the system was designed for a teacher with a free ten minutes at 2:50, and that teacher does not exist.
## Why home school communication matters more for this group of students
For a student who can narrate their own day, the daily note is a nice extra. For a student who cannot, it is the only channel that exists. A parent asking "how was school" and getting one word is not being stonewalled; our post on [getting a real answer about the school day](/blog/how-was-school-fine-autism-parents) covers why open-ended recall is genuinely hard, and what that means for the questions parents ask.
Research on family-school communication points the same direction. A [study in the International Journal of Educational Research](https://www.sciencedirect.com/science/article/abs/pii/S2210656118302782) examining effective family-school communication for students with learning disabilities found it associated with greater parental involvement both at home and at school, while noting that special education populations remain understudied relative to general education.
Involvement is the mechanism worth caring about. A parent who knows what happened in period three can reinforce it, prepare for it, or ask about it. A parent who knows nothing can only react.
## Three rules that keep a system alive
**It has to take under sixty seconds to write.** Any system that requires composing prose will be abandoned. Ratings, checkboxes, and one optional sentence survive a real week.
**It has to be readable in thirty seconds on a phone in a parking lot.** That is the actual reading environment. Design for it.
**It has to carry good days, not just hard ones.** A channel that only activates during problems becomes a channel parents avoid opening, and then you have lost it exactly when you need it.
## A daily note that survives to June
1. **Rate three fixed things, every day.** Regulation, participation, and one target skill. Same three, same order, on a five-point scale. Trends emerge without anyone writing a paragraph.
2. **Add one specific detail, not a summary.** "Asked for a break with the card, unprompted" is worth more than "good day." One concrete detail gives the family something to talk about at dinner.
3. **Flag what tomorrow holds.** Assembly, substitute, field trip, drill. A family who knows on Monday night can prepare, and our post on [fire drills and autistic students](/blog/fire-drills-autistic-students-teachers) covers why advance notice is the intervention rather than a courtesy.
4. **Make it two-way with a single prompt.** One line on the form for the family: anything we should know about last night or this morning. That question turns a broadcast into a conversation and takes them fifteen seconds.
5. **Set a hard sending time and protect it.** 2:40, every day, done. A note that goes out inconsistently gets read inconsistently.
6. **Review the trend once a month, with the family.** Five minutes with four weeks of ratings tells you more than any single incident report, and it turns the log from paperwork into data.
## What to do when something hard happened
The hard-day note is where most home school relationships are won or lost. Three things make it land better. Lead with what the student did well before the difficult part. Describe behavior rather than interpreting motive, because motive is where families disagree with schools. And end with what the team is changing tomorrow, so the family is receiving a plan rather than a complaint.
If a hard day is going to require a real conversation, say so in the note and call. A long written account of a difficult incident is the fastest route to a defensive parent, and the second-fastest route to an advocate.
## Share the sequence, not just the summary
The most useful thing a school can send home is not a report of the day but the shape of it. A family that can see what their child's day actually looks like, in order, can prepare for the hard parts and reinforce the good ones without needing a paragraph from you.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the same routine, in the same photos, can run in your classroom and in the family's kitchen. Our post on [the shared visual system across home, clinic, and school](/blog/shared-visual-system-home-clinic-school-provider-guide) covers how to set that up across the whole team.
Sixty seconds a day, five days a week, is roughly four hours across a school year. It is the highest-return four hours in the building.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so home can see the same day you do.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Fitting Therapy Into a Full School Schedule Without Burnout
Published: 2026-08-07
URL: https://vizyplan.com/blog/fitting-therapy-school-schedule-provider-guide
Category: For Providers
Author: Justin Bowman
> Every September, a caseload that ran comfortably in July gets compressed into the four hours between dismissal and bedtime. The scheduling decision is a clinical decision.
In July you had a family who could come at 10am on a Tuesday, rested and regulated, and the session went well. In September that same family is competing for a 4:30 slot with every other family on your caseload, and the child arriving at 4:30 has already worked a six and a half hour day. Fitting therapy into a school schedule is usually treated as an administrative puzzle. It is a clinical decision, and the hour you assign changes what the session is capable of producing.
## Why fitting therapy into a school schedule is a clinical question
A child who spends the school day regulating themselves in a demanding environment arrives at the clinic with a depleted reserve. That is the pattern our post on [after-school restraint collapse](/blog/after-school-restraint-collapse-autism) describes, and it is well recognized by families long before it shows up in a session note. The 4:30 session is not the same intervention as the 10am session, even with identical targets and identical procedures.
Attendance is the other half. Pediatric no-show rates vary enormously, with reported ranges spanning roughly [12 to 80 percent across settings](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC11023498/). Interventions matter: a randomized controlled trial found that text message reminders cut a pediatric clinic's no-show rate [from 38.1 percent to 23.5 percent](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5227159/). Small logistics changes move attendance more than exhortation does.
Put those together and the fall scheduling problem has a shape. The slots families want most are the slots where the child performs worst, and the slots that are clinically better are the ones families cannot reach.
## Six ways to run the fall calendar
1. **Ask what the child's day actually looks like before assigning a time.** Dismissal time, bus length, and whether they eat before therapy. A 4:00 slot with a 45-minute bus ride is a 4:00 slot the child arrives at emptied.
2. **Protect the early-week, early-day slots for the children who need the most capacity.** Not for the families who called first. Scheduling by clinical need is defensible and worth explaining to families out loud.
3. **Build a feeding-and-decompression buffer into the session, not around it.** Ten minutes of food and low demand at the start of a 4:30 session buys you the other forty. It looks like lost time. It is not.
4. **Shorten before you cancel.** A reliable 30-minute session beats a 60-minute session attended half the time. Frequency of contact does more for carryover than session length in most cases.
5. **Use reminders and pre-session logistics deliberately.** The text-reminder evidence is strong enough to treat it as part of the treatment plan rather than an office task.
6. **Move some of the work off the calendar entirely.** Coaching that rides on a routine the family already runs costs nobody a drive. Our post on [telehealth parent coaching](/blog/telehealth-parent-coaching-autism-carryover-provider-guide) covers how to deliver that without adding an appointment.
## Say the trade-off out loud to families
Some families will book four therapies in five weekday afternoons because every provider they have spoken with recommended more hours, and no one has told them what the sum looks like. Somebody on the team should.
The honest version is short. More hours are not automatically better if the child is running on empty for all of them, and a schedule that produces a burned-out child produces worse outcomes than a lighter one that the child can actually participate in. Our post on [autistic burnout warning signs in kids](/blog/autistic-burnout-in-kids-warning-signs) is a useful thing to share when a family is deciding whether to add a fifth afternoon.
That conversation also belongs in the discharge and intensity discussion generally, which our post on [discharge planning](/blog/discharge-planning-autism-therapy-provider-guide) covers.
## Let the home routine carry some of the load
The most efficient hour in a family's week is the one they were going to spend anyway. A morning routine, a bedtime sequence, an after-school wind-down: those already happen. Embedding a target in one of them costs no additional time and produces more repetitions per week than any session schedule can.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the routines a family already runs become the place carryover lives, which means your session hour can be spent on the parts that genuinely need you in the room. Our post on [the in-clinic to home generalization gap](/blog/in-clinic-to-home-generalization-gap-provider-guide) covers why that transfer so often stalls.
The calendar is a treatment variable. Treat it like one in August, before every slot is spoken for.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so progress keeps happening on the days you are not in the room.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## School Refusal in Week Three: What the Research Shows
Published: 2026-08-06
URL: https://vizyplan.com/blog/school-refusal-week-three-autism
Category: Parenting
Author: Justin Bowman
> The first two weeks went fine. Then Monday of week three arrives and your child cannot get in the car. That timing is not random, and school refusal is far more common in autistic students than most families are told.
The first two weeks went better than you dared hope. New teacher, new backpack, a bit of novelty carrying everything along. Then Monday of week three arrives and your child is on the floor by the door, or in bed with a stomach ache that is real, or simply saying no in a voice you have not heard before. School refusal in week three is one of the most common patterns families describe, and almost nobody warns them it is coming.
## School refusal is much more common in autistic students than families are told
The most-cited figure comes from a Norwegian study. Munkhaugen and colleagues observed 216 students aged 9 to 16 across 20 school days, 78 of whom were autistic, and reported [school refusal behaviour in 42.6 percent of the autistic students compared with 7.1 percent of their non-autistic peers](https://www.sciencedirect.com/science/article/pii/S1750946717300739), published in Research in Autism Spectrum Disorders. The autistic students also refused for longer stretches.
A larger and more recent picture comes from a [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) published in Frontiers in Psychiatry. Among children currently experiencing school distress, 92.1 percent were neurodivergent and 83.4 percent were autistic, diagnosed or suspected, with an odds ratio of 46.61 for autistic children experiencing school distress. 92.5 percent scored above the clinically significant anxiety threshold. And 56.9 percent had sensory processing differences, affected across an average of 4.8 sensory systems, with tactile and auditory systems affected in more than 80 percent.
Read that list as a description rather than a diagnosis. School refusal in autistic children usually is not a fear of school as an idea. It is an accumulation of specific, findable things.
## Why week three specifically
Three things run out at roughly the same time.
**Novelty runs out.** The new backpack and the new room carried real motivational weight for about ten days. When that fades, what remains is the actual daily cost.
**The mask runs out.** A child holding themselves together across six and a half hours is spending a finite budget. Two weeks in, the reserve is gone, and the collapse usually shows up at home first, which our post on [after-school restraint collapse](/blog/after-school-restraint-collapse-autism) describes in detail.
**The unpredictable events start.** Weeks one and two are heavy on routine-setting. By week three come the first fire drill, the first substitute, the first assembly, the first group project. Each one is a small proof that the day cannot be predicted.
## What actually helps
1. **Look for the specific thing, not the general feeling.** Walk the day period by period and watch for where your child stops answering. Refusal is usually anchored to one or two moments: the cafeteria, the hallway, a specific class, the bathroom, the bus. Fixing one real thing beats reassuring about everything.
2. **Believe the physical symptoms.** Stomach aches and headaches in anxious children are genuinely felt, not performed. Treating them as fake teaches a child that you are not a reliable source of help.
3. **Reduce the ask before you reduce the day.** A shorter demand often works better than a shorter schedule. A late start, a modified first period, or a check-in with a known adult on arrival can restore attendance without a partial-day plan that is hard to unwind.
4. **Name one safe adult and one safe place.** A child who knows exactly where to go and who to find is solving a smaller problem than a child who only knows they feel awful.
5. **Get the school in the room early.** Attendance letters escalate fast and they escalate on a timeline that has nothing to do with your child's nervous system. A meeting in week three is a very different conversation than a meeting in week nine.
6. **Ask for a functional assessment, not a consequence plan.** The useful question is what the school day is asking of your child that they cannot currently do. Punishment-based responses to anxiety-driven refusal reliably make it worse.
## What not to do, even though it is tempting
Do not go silent with the school in the hope that it resolves. The clinical literature on anxiety-driven school difficulty is consistent that [a wait-and-see approach does not work](https://www.ncbi.nlm.nih.gov/books/NBK560793/) and that a graded return with support does. Graded means planned, incremental, and agreed in advance, not a slow drift.
And do not read refusal as manipulation. A child who could go and simply would rather not is a different situation from a child whose body will not let them, and the second one is far more common than the first in this population. Our post on [shutdown versus meltdown](/blog/autistic-shutdown-vs-meltdown-how-to-tell-apart) covers how to tell what you are actually looking at.
## Make the day predictable enough to be survivable
Almost everything on the list above reduces to one idea: give your child more of the day in advance. What happens, in what order, with which adult, and when it ends. A day that can be previewed is a day that costs less to enter.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a child can see the whole day in photos of their own school before they walk into it, and see the after-school part too, which is often what they are actually holding out for.
If week three is hard, you are not behind and your child is not broken. You have hit the most predictable point in the school year, and it responds to a plan.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give your child a day they can preview instead of a day they have to brace for. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Parent Coaching in the First Six Weeks of the Year
Published: 2026-08-05
URL: https://vizyplan.com/blog/parent-coaching-first-six-weeks-provider-guide
Category: For Providers
Author: Justin Bowman
> August is when providers assign the most homework to families and when families have the least capacity to absorb it. The attendance research says exactly what happens next.
The school year restarts and every provider on the child's team has the same instinct at the same moment: now is the time to get the family running the program at home. Parent coaching in the first six weeks is genuinely high leverage, and it is also the window where families have the least slack they will have all year. Design for the family you actually have in September and the plan survives. Design for the family you wish you had and the attrition data will tell you exactly what happens.
## What the attendance research says about parent coaching in the first six weeks
The dosage numbers are consistent. Reviews of [parent training interventions](https://pmc.ncbi.nlm.nih.gov/articles/PMC4033505/) describe programs typically totaling 10 to 20 hours across two to six months, and across parent-implemented interventions parents receive an average of roughly 89.6 minutes across about 13.3 sessions, usually weekly.
The engagement numbers are where it gets interesting. Individually delivered parent training shows high attendance, around 85 percent, with low attrition. Group-based parent training tells a much rougher story, with reported attrition running as high as 70 percent and attendance in some programs as low as 40 percent.
That gap is not about parent motivation. It is about fit. Individual delivery flexes around a family's week. A fixed Tuesday evening group does not, and September is the month with the fewest available Tuesday evenings in the calendar year.
The upside is worth protecting, because the intervention itself works. A [meta-analysis of 51 effect sizes](https://pmc.ncbi.nlm.nih.gov/articles/PMC10539413/) found parent-implemented intervention produced moderate overall benefits for child outcomes.
## What is actually happening in the family's week
Before you assign anything in September, take stock of what just changed for them. A new teacher, a new schedule, and a new bus. Homework has restarted. Their child is running on empty from 3:30 onward, which our post on [after-school restraint collapse](/blog/after-school-restraint-collapse-autism) describes. Sleep is being reset. Some families are also fighting for services, sitting in a meeting, or absorbing a new diagnosis on top of it.
That is the context your coaching plan is landing in. A program that assumes a calm Wednesday is a program that will be abandoned politely.
## Design the first six weeks to survive
1. **Assign one target, not a program.** One behavior, one routine, one moment of the day. A family running one thing consistently generates more usable change than a family half-running four.
2. **Attach it to an anchor that already exists.** Bedtime, the bus stop, the ride home. Nothing new gets added to the schedule; the coaching rides on a routine that already survives.
3. **Make the practice cost under five minutes.** If it takes longer than that in September, it will not happen in September. Expand in October if it holds.
4. **Deliver individually where you can, and flex the time.** The attendance gap between individual and group delivery is large enough to be a design decision rather than a preference. Our post on [telehealth parent coaching](/blog/telehealth-parent-coaching-autism-carryover-provider-guide) covers how to make that logistically possible.
5. **Show, do not describe.** A ninety-second video of the parent doing it correctly beats a handout. Send the artifact, not the explanation.
6. **Check in at week two, not week six.** Two weeks is early enough that a stalled plan can be rescued. Six weeks is late enough that the family has already decided they failed.
## Watch for the thing families will not say out loud
Some families will nod through a session in September and disappear in October, and the reason usually is not the plan. It is that their child's school year is going badly and they do not want to say so yet. A short, direct question opens that door: how are the first weeks of school actually going.
If the answer involves a child who is fine at school and falling apart at home, or a child who has started refusing mornings, that is the clinical priority, not the target you assigned. Our posts on [school refusal](/blog/school-refusal-week-three-autism) and [autistic burnout warning signs in kids](/blog/autistic-burnout-in-kids-warning-signs) are worth having on hand for that conversation.
## Let the routine generate the data
The lightest coaching plan is one where the family's existing routine produces the evidence. A visual routine that a child runs each morning shows completion without anyone filling in a sheet, which means the week-two check-in has real information in it rather than a memory. Our post on [home data collection families will actually keep up with](/blog/home-data-collection-parents-provider-guide) covers how to design that.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the routine a family already runs becomes the thing you coach against, instead of one more assignment on a week that has no room left.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the plan you set in September is still running in October.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Homework Battles: A Calmer System That Actually Works
Published: 2026-08-04
URL: https://vizyplan.com/blog/homework-battles-adhd-autism-parents
Category: Strategies
Author: Justin Bowman
> Two hours of resistance over twenty minutes of work is not a motivation problem. It is a starting problem, a memory problem, and a timing problem wearing a homework costume.
Twenty minutes of math takes two hours and ends with somebody crying, and it is not always the child. Homework battles are the most reliably miserable part of the school year, and the reason they resist all the obvious fixes is that the obvious fixes target motivation. Homework battles are almost never about motivation. They are about starting, remembering, and timing, three things that live in executive function and get depleted by exactly the kind of day your child just had.
## What the research says about homework battles
Homework problems in ADHD are well documented and well measured. A [study of 579 children with ADHD](https://pmc.ncbi.nlm.nih.gov/articles/PMC3085461/) published in School Mental Health validated the Homework Problems Checklist and found the problems get worse with grade level, with fourth graders showing significantly more homework problems than first graders at moderate effect sizes. Children who also had a learning disability showed significantly more homework problems than children with ADHD alone.
Two things follow from that. First, homework difficulty is not a phase that gets outgrown; it escalates as independent management demands rise. Second, the problem is measurable, which means it is fixable with structure rather than pressure.
And structure does work. A [randomized clinical trial of the Family-School Success intervention](https://pmc.ncbi.nlm.nih.gov/articles/PMC3404236/) found significant effects on homework performance, the quality of the family-school relationship, and parenting behavior. A separate intervention for adolescents reported the share of homework assignments turned in rising from 69 percent to 86 percent. None of those studies made anybody try harder. They changed the system around the work.
## The five things that are actually breaking
**Starting.** Task initiation is its own skill and it is the one most often mistaken for laziness. A child sitting next to an unopened folder is usually not refusing, they are stuck at the ignition step. Our post on [body doubling](/blog/body-doubling-autism-adhd-task-initiation-parents) covers the single most effective fix for that.
**Knowing what the work is.** A child who recorded the assignment wrong or not at all cannot start something they cannot define. That is a materials-and-recording problem, not a work-ethic problem.
**Timing.** Homework usually lands during the exact hour when a child who masked all day has the least left. Our post on [after-school restraint collapse](/blog/after-school-restraint-collapse-autism) explains why 3:30 is the worst hour of the day for demanding tasks.
**Duration.** "Do your homework" has no visible end. A child with poor time perception hears an open-ended demand, and our post on [time blindness](/blog/time-blindness-autism-adhd-kids-parents) covers why a visible timer changes behavior more than a verbal deadline.
**The parent as enforcer.** The moment homework becomes a relationship issue, the cost of resisting drops and the cost of complying rises. Getting your voice out of the middle is worth more than any reward chart.
## A homework system worth trying this year
1. **Buffer first, work second.** Sixty to ninety minutes of nothing after school. Food, movement, no questions. Work that starts after recovery finishes faster than work that starts at 3:15.
2. **Fix the same time and the same place.** A routine removes the nightly negotiation about when. The decision should have been made in August, not at 4:40 each day.
3. **Make the work visible before it starts.** Lay out exactly what has to be done tonight, as a short list your child can see and cross off. Three visible items beat one vague obligation.
4. **Use a visible clock, not a verbal one.** A timer your child can watch, set to a length they agreed to. Fifteen minutes on, five off, works for more kids than an hour block.
5. **Sit nearby doing your own quiet task.** Not helping, not checking. Presence solves task initiation for an enormous number of children, and it costs you nothing but the chair.
6. **Stop at the agreed time even if it is unfinished.** Then email the teacher. A note that says we worked twenty-five focused minutes and got halfway is real information the school can act on. Two hours of misery is not.
## Talk to the teacher in September, not in November
The most underused move in the whole homework conversation is asking the school to reduce the load. Most teachers will adjust when a parent reports, calmly and specifically, that twenty minutes of assigned work is taking ninety at home. That is not a favor. It is exactly the kind of data an IEP or 504 team is supposed to act on, and our post on [504 plans versus IEPs](/blog/504-vs-iep-provider-guide) covers where a homework accommodation belongs.
Reasonable asks include a reduced problem set, extended time, permission to submit typed work, or a cap on nightly minutes with a parent signature covering the rest.
## Let the system carry the structure, not your voice
The goal is a homework hour that runs on something other than you repeating yourself. A visible sequence, a visible timer, a visible finish line.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the after-school hour can have a shape your child can see, including the part where it ends. Our post on [executive function and visual sequences](/blog/executive-function-visual-sequences-ot) covers why a sequence outperforms a reminder.
Homework should cost your family twenty minutes and not your evening. If it is costing your evening, the assignment is the thing that should change.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give the after-school hour a shape your child can see, including the finish line. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Making IEP Accommodations Actually Happen in Week One
Published: 2026-08-03
URL: https://vizyplan.com/blog/iep-accommodations-week-one-teachers
Category: For Schools
Author: Justin Bowman
> An accommodation that exists in a document and not in a classroom is not an accommodation. The gap usually opens in the first two weeks, and it is closable with a checklist.
The IEP was finalized in April. In August it lands in a shared drive folder, and eight adults who will interact with that student have between zero and four minutes to absorb it before the first bell. IEP accommodations do not usually fail because anyone disagrees with them. They fail because written and delivered are two different things, and nothing in the first week of school is designed to close that gap.
## IEP accommodations only count when they are delivered
The IRIS Center at Vanderbilt is blunt about this in its module on [implementing an accommodation](https://iris.peabody.vanderbilt.edu/module/acc/cresource/q3/p09/): an accommodation has to be implemented consistently and monitored, or the team has no way of knowing whether it is doing anything. Its companion guidance on [monitoring IEP fidelity and student progress](https://iris.peabody.vanderbilt.edu/module/iep02/cresource/q2/p06/) makes the same point at the plan level. Fidelity is not a compliance formality. Without it, a progress-monitoring number is measuring an unknown intervention.
The practical version: if a student has extended time written into their plan and receives it on the fourth assessment of the year instead of the first, the first three data points are not evidence of anything.
## Why week one is where it breaks
Three ordinary things collide. Most of the adults who deliver accommodations are general education teachers, specials teachers, and paraprofessionals, and most of them have not read the full document. The student is new to the room, so nobody yet knows what escalation looks like before it is visible. And the first week is the single busiest week of the year for everyone involved.
The cost lands on the student. A [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) in Frontiers in Psychiatry found that among children experiencing serious school distress, 92.1 percent were neurodivergent and 92.5 percent scored above the clinically significant anxiety threshold. Distress at that scale is built out of ordinary weeks where the supports were slightly late.
## A week-one accommodations protocol
1. **Cut the list down to the day-one three.** Every plan has two or three accommodations that carry most of the access. Name them explicitly, in a single line, at the top of the file. Everything else can start in week two.
2. **Give every adult a one-page version.** Not the IEP. One page: strengths, communication, the day-one three, what escalation looks like, who to call. Our guide to [building a one-page profile](/blog/one-page-profile-autism-new-teacher) has the format.
3. **Say who delivers each one, by name.** An accommodation owned by "staff" is owned by nobody. Extended time is owned by the person giving the assessment. The break pass is owned by whoever is in the room.
4. **Make the environmental ones physical before students arrive.** Preferential seating, a visual schedule on the wall, a break space, headphones in a known drawer. Anything you can build in advance should not depend on anyone remembering.
5. **Check delivery on day three, not week six.** One quick question to each adult: did it happen, and what got in the way. Three days is early enough to fix. Six weeks is a conversation about why it did not happen.
6. **Write down the accommodations that no longer fit.** Plans get inherited and accommodations accumulate. An accommodation nobody uses crowds out the two that matter, and saying so is more useful than quietly skipping it.
## The substitute problem, on day one
Week one is also when unfamiliar adults are most likely to appear. A plan that lives in one teacher's head disappears the moment that teacher is out, which is exactly when a student is least able to absorb the change. Our post on [substitute teacher plans for autistic students](/blog/substitute-teacher-plan-autistic-students) covers the one-page version that survives a sub day.
The same logic applies to paraprofessional support. Support delivered without a plan drifts toward doing things for the student rather than fading toward independence, and our post on [prompt dependency](/blog/paraprofessional-autism-support-prompt-dependency) covers what that looks like and how to correct it early.
## Make the plan visible to the student, not just to the adults
The last piece is the one most often skipped. Accommodations are written for adults to deliver and rarely explained to the student who is meant to use them. A student who does not know they have a break pass will not use it. A student who cannot see where the break space is will not walk to it.
Show the student their own supports the same way you show them the schedule: concretely, visually, in advance. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the routine and the supports inside it can be shown in photos of the student's real classroom, and can travel home so families are running the same plan.
An accommodation is a promise. Week one is when the student finds out whether the building keeps its promises, and that finding tends to stick.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the supports that run at school are visible at home too.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## How Was School? Fine. Getting the Real Story From Your Child
Published: 2026-08-02
URL: https://vizyplan.com/blog/how-was-school-fine-autism-parents
Category: Parenting
Author: Justin Bowman
> You get one word and a closed door, and then something falls apart at 6pm over nothing. The problem is usually the question, and memory research has a lot to say about which questions work.
How was school. Fine. That is the entire exchange, and then at 6:15 something detonates over the wrong cup and you find out three days later that a substitute changed the schedule on Tuesday. The frustrating part is that your child is not hiding anything. When you ask how was school, you are asking for something the brain is genuinely bad at producing on demand, and swapping in a smaller question changes the answer immediately.
## What memory research says about how was school
"Tell me everything that happened" is called a free recall prompt, and it is the hardest form of retrieval there is. A [study published in the Journal of Autism and Developmental Disorders](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6394562/) examining episodic memory retrieval in autistic children found that they recalled fewer correct narrative details than typically developing peers under open invitations, cued invitations, and directive questions, but were just as accurate as their peers when they did answer. The information is in there. The retrieval path is what is expensive.
The same body of work points at the fix. Cued questions, ones that hand back a piece of the context, support remembering far better than open prompts. "What did you eat at lunch" is a different cognitive task than "how was school," even though a parent means the same thing by both.
Then add timing. A child who spent six and a half hours managing a classroom is arriving home with an empty tank, which is what our post on [after-school restraint collapse](/blog/after-school-restraint-collapse-autism) describes. The moment they get in the car is the worst possible moment to run a language-heavy retrieval task.
## Ask smaller, ask later, ask sideways
1. **Wait forty-five minutes.** Food, quiet, and no questions first. The conversation you want is available at 5pm and is not available at 3:15.
2. **Ask about one anchored moment, not the day.** "Who did you sit with at lunch." "What did you do first after you put your backpack away." Specific beats broad every time.
3. **Offer two options instead of an open field.** "Was music better or worse than yesterday" is answerable. "How was music" is a request to compose.
4. **Use the schedule as the cue.** Read the day back to them in order and let them react to each part. The sequence itself is the retrieval scaffold.
5. **Ask for a rating before you ask for a story.** Thumbs up or down, or a number out of five, for each block of the day. A number is cheap to produce and tells you exactly where to point the next question.
6. **Talk shoulder to shoulder.** In the car, on a walk, while building something. Removing eye contact and face-reading from the task frees up capacity for the actual answer.
## Listen for the parts that are not words
Some of the most important information your child gives you about school will never arrive as a sentence. A sudden refusal to wear a specific shirt. Not drinking anything all day, which our post on [bathroom avoidance at school](/blog/bathroom-avoidance-at-school-autism) explains is often a strategy rather than a preference. Scripting a line from a show that maps onto something that happened. Asking the same question about tomorrow eleven times.
Repeated questions about tomorrow are usually the clearest signal in the set. They almost always mean an unpredictable thing happened today, and your child is trying to find out whether it will happen again.
## Make school visible so there is less to retrieve
There is a structural fix underneath all of this. If a child can see the day laid out, arrival, morning work, specials, lunch, recess, pickup, then a conversation about school stops being an act of reconstruction and becomes an act of pointing.
That is also how you catch the thing that went wrong. A parent looking at the day with their child can ask about period four specifically, and a child who cannot narrate a day can very often point at the part that was bad.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the day exists in photos of your child's actual school, which means the after-school conversation has something to hold onto. For families whose child communicates in scripts or gestalts, our post on [gestalt language processors and visual scripts](/blog/gestalt-language-processors-visual-scripts-slp) is worth reading alongside this one.
One last reframe. Silence after school is not rejection and it is not a discipline problem. It is a nervous system that spent everything it had and has not refilled yet. Ask the smaller question, later, and you will get a real answer more often than you expect.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give the school day a shape you can both point at instead of a question nobody can answer. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## School Lunch for a Selective Eater: What Comes Home Empty
Published: 2026-08-01
URL: https://vizyplan.com/blog/school-lunch-selective-eater-autism
Category: Daily Routines
Author: Justin Bowman
> The lunchbox comes home untouched and you assume it was the food. Often it was the room. A cafeteria is a sensory event before it is a meal.
The lunchbox comes home with the sandwich untouched, the apple untouched, and the one snack you thought was safe untouched. Your first instinct is to change the food. School lunch for a selective eater usually fails for a different reason than the one on the menu, and if you only ever change the contents, you will keep solving the wrong problem all year.
## School lunch for a selective eater is a room problem first
A cafeteria is one of the loudest places a child goes all day. Students in a Noisy Planet measurement project sponsored by the National Institute on Deafness and Other Communication Disorders [measured their own cafeteria](https://www.noisyplanet.nidcd.nih.gov/have-you-heard/how-loud-is-too-loud-in-the-school-cafeteria) and found levels that regularly climbed toward the range where repeated exposure becomes a hearing concern, which is around 85 decibels. Typical peak lunch periods land somewhere between 75 and 85 decibels.
Now stack that on an autistic nervous system. Between [56 and 70 percent of autistic youth](https://pmc.ncbi.nlm.nih.gov/articles/PMC4861140/) meet criteria for sensory over-responsivity, and in a sample of 4,104 autistic people, [60.1 percent currently experienced auditory over-responsivity](https://link.springer.com/article/10.1007/s10803-021-04991-0). Eating requires a body that is at least somewhat regulated. A body in a room that loud is doing something else with its resources.
Add twenty-two minutes on a clock, an unassigned seat, smells from four other lunches, and the social work of a table, and the empty lunchbox stops being mysterious.
## The food layer is real too
None of that means the food does not matter. Food selectivity is genuinely more common in autism: a [meta-analysis of prevalence](https://www.sciencedirect.com/science/article/abs/pii/S0003448725002471) reported a mean prevalence of food selectivity in autism of about 63 percent, substantially higher than in typically developing comparison groups. And a [2025 meta-analysis in the International Journal of Eating Disorders](https://pmc.ncbi.nlm.nih.gov/articles/PMC11891632/) pooling 21 publications and 7,442 participants found ARFID, avoidant restrictive food intake disorder, present in 11.41 percent of autistic groups, with autism present in 16.27 percent of ARFID groups.
The distinction that matters at 7am is whether you are packing for preference or for a genuinely restricted range. Our post on [ARFID and extreme picky eating](/blog/arfid-autism-extreme-picky-eating-parents) covers when it is worth involving a feeding therapist rather than a new lunchbox.
## How to pack for the room your child is actually in
1. **Send safe foods, not stretch foods.** School lunch is not the place to expand a range. Twenty-two minutes in a loud room is the worst available setting for trying something new. Do exposure work at home on a Saturday.
2. **Pack for one hand and no supervision.** If it needs opening, unwrapping, or cutting, some of those calories will not be eaten. Test every container at home first.
3. **Cut the volume, not the calories.** A smaller amount of a reliable food gets eaten. A large amount of anything looks like a demand and gets closed.
4. **Keep textures separate.** A wet item touching a dry item can end a lunch. Compartments are not a nicety here.
5. **Ask about a quieter place to eat.** Most schools have one, and most will say yes if asked directly. A corner, the library, the classroom, or lunch with two peers instead of two hundred.
6. **Add a real snack to the ride home.** If lunch is going to be light on hard days, plan for it rather than discovering it at 4pm during a meltdown. Our post on [after-school restraint collapse](/blog/after-school-restraint-collapse-autism) covers why the first hour home goes the way it does.
## Small asks that change the whole period
A few accommodations are worth putting in writing rather than hoping for. Permission to wear headphones or ear loops in the cafeteria. A consistent seat at the end of a table rather than the middle. Permission to eat before or after the main rush. Extra time, because twenty-two minutes includes lining up, finding a seat, and the social negotiation before the first bite.
None of these are unusual, and none of them are expensive. Our post on [unstructured time at recess and lunch](/blog/unstructured-time-recess-lunch-autism-teachers) covers how school teams think about the same problem from the other side of the table.
## Show the lunch before it happens
Uncertainty suppresses appetite in almost everyone, and a child who does not know what is in the box, where they will sit, or how long they have is carrying three unknowns into a twenty-minute window. Showing the actual lunch in the morning removes one of them for free.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a child can see what is in the box, where lunch sits in the day, and what comes after it, in photos of their own world.
If the lunchbox keeps coming home full after all of that, believe your child rather than the menu. Something in that room is still too much, and finding it is faster than replacing the sandwich eleven more times.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Let your child see the lunch, the day, and what comes next before they are standing in it. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Fire Drills and Autistic Students: Plan Before It Rings
Published: 2026-07-31
URL: https://vizyplan.com/blog/fire-drills-autistic-students-teachers
Category: For Schools
Author: Justin Bowman
> A fire drill is a scheduled event that arrives as a surprise, at a volume designed to be impossible to ignore. For some students it undoes a week of progress in ninety seconds.
The alarm is on the calendar. The building administrator knows the date, the fire marshal knows the date, and the one person in the room who most needs to know the date is the student who will be under a desk with their hands over their ears ninety seconds from now. Fire drills and autistic students are the clearest example of a problem that is entirely predictable and almost entirely preventable, and the fix costs a five-minute conversation in August.
## Fire drills and autistic students collide on two axes at once
The first is volume. Fire alarms are engineered to be impossible to ignore, which is exactly the design goal you would choose if you wanted to overwhelm an over-responsive auditory system. In a sample of 4,104 autistic people, [60.1 percent currently experienced auditory sensory over-responsivity](https://link.springer.com/article/10.1007/s10803-021-04991-0) and 71.1 percent had experienced it at some point. Broader estimates put sensory over-responsivity at [56 to 70 percent of autistic youth](https://pmc.ncbi.nlm.nih.gov/articles/PMC4861140/).
The second is unpredictability. The [National Association of School Psychologists](https://www.nasponline.org/resources-and-publications/resources-and-podcasts/school-safety-and-crisis/school-violence-resources/school-safety-drills-and-exercises-for-students-with-autism-spectrum-disorder-(asd)-tips-and-resources-for-educators) notes that students with autism can be especially vulnerable during safety drills because they are often challenged both by sensory disruption and by changes in routine. A drill delivers both simultaneously, without warning, in a hallway full of other people also moving unpredictably.
The cost is not just a hard afternoon. A [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) found that among children in serious school distress, 92.5 percent scored above the clinically significant anxiety threshold. Anxiety about school does not usually come from one catastrophic event. It comes from a school that has repeatedly proven unsafe to predict.
## Preparation is not a courtesy, it is the intervention
Two evidence-informed strategies do most of the work here, and both are standard practice rather than anything exotic.
The first is graduated exposure to the sound itself. Playing a recorded alarm at low volume, then gradually increasing it across sessions, lets a student build tolerance in a controlled setting rather than discovering their response in a live evacuation.
The second is making the procedure visible before it happens. Visual supports break a complex sequence into concrete, ordered steps, and a [review of 31 studies](https://pubmed.ncbi.nlm.nih.gov/25081593/) in the Journal of Autism and Developmental Disorders concluded that visual activity schedules qualify as an evidence-based practice for autistic individuals. A student who has seen the sequence, alarm, line up, door, sidewalk, wait, return, is running a routine instead of processing an emergency.
## A drill plan any teacher can put in place this week
1. **Get the drill calendar and share it with the people who need it.** Teachers, the paraprofessional, and the family. A family who knows Tuesday is a drill day can prepare at breakfast and plan the afternoon.
2. **Pre-teach the sequence with pictures, not just words.** Six steps, in order, with photos of your actual door and your actual line-up spot. Review it the morning of.
3. **Name the sensory plan out loud.** Who hands over the headphones, where they live, and who is responsible if that adult is absent. A plan that depends on one person is not a plan.
4. **Assign a specific adult and a specific place.** Not "a staff member will help." One named adult, one named exit, one named spot outside. Ambiguity is the thing that hurts.
5. **Practice at low stakes first.** A walkthrough with no alarm, then a recording at low volume, then the real thing. Three exposures beat one surprise.
6. **Plan the ten minutes after.** Return, water, a quiet task, no immediate demand for new academic content. Recovery time is part of the drill, not a reward for getting through it.
## Say the quiet part to the class
The most underused move is simply telling students in advance what will happen and why, in plain language, and letting them ask questions. It costs three minutes, it helps far more than the one student it was designed for, and it converts an ambush into an event.
Our posts on [transition warnings in the classroom](/blog/classroom-transition-warnings-autism-teachers) and [the sensory-friendly classroom](/blog/sensory-friendly-classroom-setup-teachers) cover the rest of the environment that makes a drill survivable.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a sequence like a fire drill can be shown in photos of the student's own school, at home the night before and in the classroom the morning of.
A drill is a scheduled event. There is no good reason for it to arrive as a surprise to the one student it will cost the most.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the hard parts of the school day can be practiced at home first.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Bathroom Avoidance at School: Why Kids Hold It All Day
Published: 2026-07-30
URL: https://vizyplan.com/blog/bathroom-avoidance-at-school-autism
Category: Daily Routines
Author: Justin Bowman
> Your child is fully toilet trained at home and comes off the bus in wet clothes. That combination is common, it is well documented, and it is almost never about defiance.
Your child has been independently using the bathroom at home for two years. Three weeks into the school year they come off the bus in a different pair of pants, or with a stomach ache, or having had nothing to drink since breakfast because that is the only strategy they could think of. Bathroom avoidance at school is one of the most common and least discussed back to school problems, and treating it as a compliance issue makes it worse every single time.
## Bathroom avoidance at school has a documented physical layer
Start with the part that gets missed. Continence problems are substantially more common in autistic children than the general population. A [study published in the Journal of Pediatric Urology](https://www.jpurol.com/article/S1477-5131(15)00158-8/abstract) comparing 40 autistic children with a mean age of 11.3 years to 43 age-matched controls found daytime wetting in 45 percent of the autistic group versus 4.7 percent of controls, and nighttime wetting in 30 percent versus zero. A later [systematic review in European Child and Adolescent Psychiatry](https://link.springer.com/article/10.1007/s00787-017-1062-3) confirmed that incontinence of several types co-occurs with autism at elevated rates.
So before anything else: if a previously reliable child starts having accidents, constipation and urinary tract issues belong on the list, and a pediatrician visit is a reasonable early step rather than a last resort. Constipation in particular is common, easy to miss, and produces exactly this pattern.
## Then there is the interoception layer
Interoception is the sense that tells you what is happening inside your body: hunger, thirst, temperature, and the signal that you need a bathroom. Many autistic children register that signal late, faintly, or only when it becomes urgent. "Watch for the signs they need to go" is advice that assumes the signal arrives on time.
At home, the bathroom is nine feet away and the child can respond to a late signal. At school, the bathroom is down a hall, requires permission, takes four minutes, and the signal arrives with two minutes of margin. Our post on [interoception and visual body cues](/blog/interoception-visual-cues-ot-body-awareness) covers how occupational therapists build that awareness deliberately.
## And a sensory layer on top of both
School bathrooms are genuinely difficult sensory environments. Automatic flushes that fire without warning. Hand dryers that are painfully loud. Echo. Fluorescent light. Smell. Doors that do not close all the way. Between [56 and 70 percent of autistic youth](https://pmc.ncbi.nlm.nih.gov/articles/PMC4861140/) meet criteria for sensory over-responsivity, and in a sample of 4,104 autistic people, [60.1 percent currently experienced auditory over-responsivity](https://link.springer.com/article/10.1007/s10803-021-04991-0). A hand dryer at close range is not a minor annoyance for a child in that group.
Add the social layer, which is that using the bathroom at school requires asking, in front of everyone, and sometimes being told to wait, and you have four separate reasons stacked on top of each other. Holding it for seven hours starts to look like the rational choice it is.
## What to put in place before September
1. **Rule out the physical first.** Constipation, urinary tract infection, and medication effects all produce this pattern. Ask the pediatrician before you build a behavior plan.
2. **Ask to see the actual bathroom your child will use.** Not the building. The specific room. Then you know whether you are dealing with a hand dryer, an auto-flush, or a door that does not latch.
3. **Get a no-ask bathroom pass written into the plan.** A silent signal or a permanent pass removes the hardest step, which is asking in front of twenty-four peers. This is a standard accommodation and schools grant it routinely when asked.
4. **Schedule the trips instead of waiting for the signal.** Two or three fixed bathroom times built into the day works far better than relying on interoception that arrives late. Attach them to existing anchors: after arrival, before lunch, after recess.
5. **Solve the specific sensory problem.** A sticky note over an auto-flush sensor. Permission to use a single-stall or nurse's bathroom. Headphones for the hand dryer. Small fixes, large effect.
6. **Send a spare set of clothes and normalize it out loud.** An accident that comes with shame produces more avoidance, which produces more accidents. Break that loop early and explicitly.
## Make the sequence visible, not verbal
For a child who is stuck on the steps rather than the signal, the sequence itself can be the barrier: ask, walk, wait, close, wipe, flush, wash, dry, return. That is nine steps under time pressure in a loud room. Our [visual support guide to potty training](/blog/potty-training-autism-adhd-visual-supports) covers how to break it down.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a routine like this can live in photos of your child's real world and travel with them between home and school.
One last thing worth saying plainly to your child, and then to yourself: a body that needs a bathroom is not a behavior problem. Nobody is doing this on purpose.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Turn the hard sequences into something your child can follow without asking out loud. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## School and Clinic Therapy Coordination That Actually Works
Published: 2026-07-29
URL: https://vizyplan.com/blog/school-clinic-therapy-coordination-provider-guide
Category: For Providers
Author: Justin Bowman
> A child can receive excellent school therapy and excellent clinic therapy and still make no progress, because the two are teaching different versions of the same skill in different words.
A child on your caseload also gets forty-five minutes a week from a school-based clinician who has never spoken to you, is working from a different assessment, is using a different prompt hierarchy, and is targeting a goal that sounds like yours but is not. School and clinic therapy coordination is the difference between two teams multiplying each other and two teams quietly canceling each other out, and August is the only month of the year when everyone has time to fix it.
## School and clinic therapy coordination is what families are already asking for
Families are not confused about this. They are asking. A [2024 study in Frontiers in Rehabilitation Sciences](https://pmc.ncbi.nlm.nih.gov/articles/PMC10834652/) exploring valued outcomes of school-based speech-language therapy found that family members emphasized coordinated care that was responsive to all of a child's needs, and specifically wanted greater communication and care coordination between health professionals and their children's educators.
The two settings genuinely have different mandates, and that part is fine. School services exist to give a student access to their education, which is why school goals lean toward classroom participation, curriculum access, and functional communication in a group. Clinic services are usually broader and more individualized. The problem is not the difference in scope. The problem is when the difference is never named out loud, and the child has to reconcile two systems by themselves.
## The three failure modes to look for
**Same skill, different topography.** The school team teaches a break request with a card. You teach it with a spoken phrase. Both are defensible. Together they teach a child that the correct response depends on the room, which is the opposite of generalization.
**Different criteria, invisible disagreement.** Your goal says 80 percent across three sessions. Theirs says four out of five opportunities. Nobody is wrong and nobody can compare notes, so the child's progress looks great in one file and stalled in the other.
**Duplicate effort on the easy target, no coverage on the hard one.** Two teams independently pick the most measurable goal. The genuinely difficult skill, the one that would change the child's day, gets worked by neither, because it is hard to write and hard to score.
## Five moves that take under an hour
1. **Get a release signed in August, not in November.** Everything else on this list depends on it, and it is the step most often delayed until a crisis makes it urgent.
2. **Send one email with three questions.** What are you targeting this quarter, what prompt or cue are you using, and what does the child do when it works. Three questions get answered. A meeting request often does not.
3. **Agree on the shared topography for one target, not all of them.** Pick the highest-value skill, usually a break request or a help request, and make the response look identical in both settings. One aligned target beats six theoretically aligned ones.
4. **Write down who owns what.** Access and participation goals live with the school. Skill acquisition beyond the classroom lives with you. Naming the split prevents the polite duplication that eats both caseloads.
5. **Share one artifact instead of one report.** A photo of the visual support, a two-line description of the cue, a video of the child doing it correctly. Artifacts transfer. Narrative reports usually do not get read by the other side.
## Include the family as the third setting, not the audience
Home is where generalization either happens or does not, and it is the setting neither of you controls. That is precisely why it should be the one you align on first. Our post on [the shared visual system across home, clinic, and school](/blog/shared-visual-system-home-clinic-school-provider-guide) covers how to build one artifact all three settings use, and our post on [the in-clinic to home generalization gap](/blog/in-clinic-to-home-generalization-gap-provider-guide) covers why skills stall at the clinic door.
The evidence supports leaning on the family here. A [meta-analysis of 51 effect sizes](https://pmc.ncbi.nlm.nih.gov/articles/PMC10539413/) found parent-implemented intervention produced moderate overall benefits across child outcomes. Parents are not a delivery channel of last resort. They are the setting with the most hours.
## Write goals the other team can actually use
The fastest coordination win is a goal a school clinician can read in ten seconds and reproduce on Monday. Concrete response, concrete cue, concrete criterion, no acronyms that live only in your discipline. Our post on [writing parent-friendly therapy goals](/blog/parent-friendly-therapy-goals-provider-guide) applies almost word for word to the school team, because the constraint is the same: the reader has ninety seconds and a full caseload.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the same sequence, in the same photos, can run in the classroom, in your session, and at the kitchen table without three teams rebuilding it three times.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the school team and your team are pointing at the same picture.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Middle School Transition: Seven Teachers and a Schedule That Moves
Published: 2026-07-28
URL: https://vizyplan.com/blog/middle-school-transition-autism-adhd
Category: Parenting
Author: Justin Bowman
> Elementary school gave your child one adult who knew them. Middle school gives them seven adults who each see them for forty-five minutes, and a hallway with a four-minute clock.
In elementary school, one teacher watched your child for 180 days and learned their whole operating system. The middle school transition replaces that with seven adults who each see your child for forty-five minutes, a locker with a combination, a hallway with a four-minute clock, and an assumption that everyone can now manage their own materials. For a lot of autistic and ADHD students, the middle school transition is where the visible supports quietly stop and the invisible demands quietly triple.
## The middle school transition shows up in the data
This is not a vibe. The research finds real dips. Analysis of the academic effects of moving to middle school found that [the gap between students with disabilities and general education students in math grows during the transition year](https://edworkingpapers.com/sites/default/files/ai22-655.pdf), with a larger negative effect for students with disabilities. Longer term, the [Illinois Center on Transition and Work summarizes](https://ictw.illinois.edu/resources/research-briefs/other-topics/brief-the-importance-of-transition-planning-in-middle-school) that young adolescents with disabilities are 50 percent more likely to drop out of middle school than peers without disabilities.
The mechanism is not usually academic ability. It is executive load. Every skill that an elementary classroom scaffolded for free, remembering the materials, tracking the time, knowing where to be, holding a multi-day assignment in mind, becomes the student's own job on the same week that six other things change.
## The five things that actually break
**Materials.** Six classes, six sets of things, one locker, four minutes. A student who forgets a binder is not disorganized in a character sense. They are being asked to run a logistics operation with no system.
**Time.** Passing periods reward internal clocks. Our post on [time blindness](/blog/time-blindness-autism-adhd-kids-parents) explains why "you have four minutes" is not usable information for a lot of these students, and why a visible countdown is.
**Multi-day assignments.** Elementary homework is due tomorrow. Middle school projects are due in eleven days, which requires a student to plan backward across a week and a half. That is a genuinely advanced executive skill and it is rarely taught.
**Social sorting.** Lunch tables, group work, and an unstructured hallway three times a day. Unstructured time is consistently the hardest part of the school day, and our post on [recess and lunch](/blog/unstructured-time-recess-lunch-autism-teachers) covers why.
**Nobody owns the whole child.** Seven teachers each have one slice. The student who is quietly drowning in period three may look fine in period five, and no adult sees the pattern unless someone is deliberately looking.
## What to set up before September
1. **Ask who is the case manager, by name, and meet them in August.** In middle school, the person who owns the plan is not the person who teaches your child most. Find them first.
2. **Walk the actual route, twice.** With the real schedule, at the real pace. Most schools will let you in during the week before school starts. Locker, room 214, bathroom, cafeteria, gym.
3. **Practice the locker until it is boring.** A combination lock under time pressure while a hallway is loud is a genuinely hard motor and memory task. Ten minutes of practice in August removes a daily failure point.
4. **Build one materials system and use only that.** One binder or one folder per class, chosen by your child, colored by subject. The best system is the one they will actually use, not the one that looks best on a supply list.
5. **Put every long assignment on a visible backward plan.** Due date, then work backward in chunks. A due date alone is not a plan, and a student who cannot see the middle steps will start on day ten.
6. **Ask for the accommodations that survive the schedule change.** Extra passing time, a second set of textbooks at home, a locker location near the first class, a break pass that works in every room. Our post on [504 plans versus IEPs](/blog/504-vs-iep-provider-guide) covers which document should carry them.
## Expect the crash to move, not disappear
A middle schooler who held it together across seven rooms all day arrives home with nothing left, and the reaction now often looks like door-closing rather than melting down. That is still after-school restraint collapse; it just wears a teenage face. Our post on [after-school restraint collapse](/blog/after-school-restraint-collapse-autism) covers what actually helps in the first hour home, and it is almost never a conversation about the day.
## Make the moving schedule visible
The single highest-value thing you can do is convert the schedule from something your child has to remember into something they can look at. Rooms, teachers, what to carry, what happens after school. That is a working memory problem, and working memory is exactly what a visual sequence is for.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a student can see the day, the week, and what they need for each block without holding it all in their head. Our post on [executive function and visual sequences](/blog/executive-function-visual-sequences-ot) covers the theory underneath it.
Middle school is a real jump. Plan for it the way you would plan for a move to a new city, because for your child, that is roughly the size of it.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give your middle schooler a schedule they can see instead of one they have to remember. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Teaching Classroom Routines in the First Two Weeks
Published: 2026-07-27
URL: https://vizyplan.com/blog/teaching-classroom-routines-first-two-weeks
Category: For Schools
Author: Justin Bowman
> Most classroom routines are announced once in September and then enforced for nine months. Teaching them the way you teach content changes what the rest of the year costs.
On the first Tuesday, you tell twenty-four students how to enter, where to put their folder, how to ask for help, and what happens when they finish early. By Thursday, six of them have it, twelve of them are approximating it, and six are watching the other students to figure out what just happened. Teaching classroom routines is usually treated as an announcement. Treated as instruction, with modeling, practice, and feedback, it changes what every remaining week of the year costs.
## Teaching classroom routines is instruction, not information
The distinction is the whole post. Information is delivered once. Instruction is modeled, practiced, corrected, and practiced again. The [Australian Education Research Organisation's guidance on teaching routines](https://www.edresearch.edu.au/summaries-explainers/explainers/teaching-routines-their-role-classroom-management) recommends explicitly teaching how students enter and leave, how they ask for help, and how they pack up, then actually setting aside time to practice each one while monitoring and reinforcing how students carry it out.
The payoff is not just behavioral. The Campbell Collaboration's [systematic review of teacher classroom management practices](https://onlinelibrary.wiley.com/doi/10.4073/csr.2011.4) found that deliberate classroom management reduces disruptive and aggressive student behavior. And the arithmetic on lost time is startling: [one analysis of classroom time loss](https://files.eric.ed.gov/fulltext/EJ1086382.pdf) calculated that six minutes lost at the start of every lesson adds up to roughly 5,700 minutes across a school year, the equivalent of about five full weeks of school.
Five weeks. That is what unclear routines cost, before anyone has misbehaved.
## Why this matters more for some students in your room
A student who reads social context quickly can reverse-engineer an unspoken routine by watching peers. A student who does not read context that way is doing something much harder: guessing, in public, under time pressure, all day.
That is where distress accumulates. A [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) in Frontiers in Psychiatry found that 92.1 percent of children experiencing significant school distress were neurodivergent, with an odds ratio of 46.61 for autistic children. Distress on that scale does not come from one bad day. It comes from an environment that is continuously slightly unreadable.
Explicit routines are the cheapest accessibility fix in the building. They cost you three days in August and they help every student, including the ones who would have figured it out anyway.
## The routines actually worth teaching explicitly
1. **Entry.** What happens in the first ninety seconds. Where the backpack goes, what to start, what to do if you are late. Entry sets the tone for the block and it is the routine most often skipped.
2. **How to ask for help.** Name the signal. A card, a hand, a spot on the desk. A student who cannot ask will either stall silently or escalate, and neither one tells you what they needed.
3. **How to take a break.** Where, how long, how to come back. A break routine that only exists in a crisis is not a routine, it is an improvisation during the worst possible moment.
4. **Transitions between activities.** Warning, wrap-up, move. Our post on [transition warnings in the classroom](/blog/classroom-transition-warnings-autism-teachers) covers what a warning has to contain to actually work.
5. **What to do when you finish early.** Unstructured minutes are where most low-level disruption is born. Fill them with a named, visible option.
6. **Pack-up and dismissal.** The end of the day is a transition, a time pressure, and a sensory peak at once. Practice it the way you practice a fire drill.
## Teach it the way you teach content
Model it. Show the non-example, which students find genuinely funny and remember better. Practice it as a class, twice. Give behavior-specific praise the first several times students get it right. Re-teach it in week three, when the novelty has worn off and the drift has started, and again after any long break.
Then make it visible. A routine that lives only in your voice has to be re-delivered every time; a routine that lives on the wall or on a card gets referenced by the student instead of prompted by you. That distinction is the difference between independence and prompt dependency, which our post on [paraprofessional support and prompt dependency](/blog/paraprofessional-autism-support-prompt-dependency) unpacks in detail.
Visual supports are not a soft option here. A [review of 31 studies](https://pubmed.ncbi.nlm.nih.gov/25081593/) published in the Journal of Autism and Developmental Disorders concluded that visual activity schedules meet the criteria for an evidence-based practice.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the sequence a student follows at school can look like the one they follow at home, in photos of their own world. Our [visual schedule guide for teachers](/blog/visual-schedule-classroom-teacher-guide) covers how to build one for a whole class.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the routines you teach in September keep running at home.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## School Drop Off Separation Anxiety: A Calmer Goodbye
Published: 2026-07-26
URL: https://vizyplan.com/blog/school-drop-off-separation-anxiety-autism
Category: Parenting
Author: Justin Bowman
> Every instinct tells you to stay one more minute. The research points the other way, and the reason has nothing to do with being cold.
You are eleven feet from the classroom door and your child's hand has become a clamp. The teacher is doing the bright voice. Two other parents are watching. School drop off separation anxiety puts you in the worst kind of bind, because the two things you want, your child feeling safe and your child getting through the door, seem to point in opposite directions in that exact moment.
They do not, actually. But the way out is counterintuitive.
## What the research says about school drop off separation anxiety
The clinical literature on anxiety-driven school difficulty converges on one approach: graded return, meaning gradual exposure to the feared situation with support, rather than waiting for the fear to pass on its own. The [StatPearls clinical review on separation anxiety disorder](https://www.ncbi.nlm.nih.gov/books/NBK560793/) describes cognitive behavioral therapy as first-line, with the best outcomes and the shortest treatment duration, and notes that a wait-and-see approach has not proven effective.
The second finding is the one that changes what parents actually do. Parent-based treatment works about as well as child-focused therapy. A [scoping review in the Journal of Paediatrics and Child Health](https://doi.org/10.1111/jpc.70492) covering therapeutic and educational interventions for childhood separation anxiety describes parent-based programs, including SPACE, which stands for Supportive Parenting for Anxious Childhood Emotions, as reducing family accommodation of childhood anxiety with results comparable to treating the child directly.
Family accommodation is the technical name for the thing every loving parent does. Staying five more minutes. Answering the same reassurance question for the ninth time. Coming back in when they cry. Each of those makes the next morning slightly harder, because it teaches a very reasonable lesson: the fear was correct, and leaving is negotiable.
That is not a criticism of any parent. It is the most natural response in the world. It is also the lever.
## Why an autistic child's version looks different
Not all school door distress is separation anxiety in the classic sense. Sometimes the child is not afraid of losing you. They are afraid of what happens after you leave, which is a different problem with a different fix.
A [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) in Frontiers in Psychiatry found that among children experiencing serious school distress, 92.5 percent scored above the clinically significant anxiety threshold, 56.9 percent had sensory processing differences, and children were affected across an average of 4.8 sensory systems. For those children, the doorway is not the problem. The cafeteria is the problem, or the noise, or the unpredictable part of the day two hours from now.
The way to tell the difference is to ask about the middle of the day, not the morning. If your child can name what they are dreading, it is usually not about you leaving. Our post on [school refusal](/blog/school-refusal-week-three-autism) covers what to do when the reason is real and specific.
## A drop off plan that gets shorter every week
1. **Make the goodbye a fixed script, not a feeling.** Same words, same length, same order, every day. Predictability at the door does more than warmth at the door, because warmth that varies in length becomes a variable your child has to solve.
2. **Cap it at thirty seconds and hold the cap.** Long goodbyes are not kinder. They extend the hardest moment and teach that the length is negotiable.
3. **Hand off to a named person, not to a room.** One adult, by name, who your child expects to meet. A known face converts an unknown into a routine.
4. **Give your child something to do in the first two minutes.** A job, a task, a specific place to put the backpack. Anxiety struggles to hold on to a body that is already busy.
5. **Move the emotional work earlier.** Talk about the day at breakfast when the nervous system is calm, not at the door when it is not. Reassurance lands at 7am. It bounces at 8:05.
6. **Shorten it deliberately, week by week.** Walk to the classroom this week, the hallway next week, the door after that. A graded return only works if it actually grades.
## Give the day a shape before you get there
Most of the fight at the door is about uncertainty, and uncertainty is the one variable you can genuinely reduce from home. A child who has seen the whole day laid out, arrival, morning work, specials, lunch, pickup, walks in solving a smaller problem than a child who is walking into a blank.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a child can look at the day, in photos of their own school, before they have to live it. Our posts on [first day of school anxiety](/blog/first-day-of-school-anxiety-autism) and [the meet-the-teacher visit](/blog/meet-the-teacher-visit-autism-preparation) cover the two weeks before this becomes a daily question.
One last thing. If drop off has been hard for six weeks and is not moving, that is not a discipline gap, and pushing harder is not the next step. Loop in the school counselor and your child's clinician. Persistent school distress responds to a plan, and it rarely responds to willpower.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Let your child see the whole day before they walk into it. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## School Bus Anxiety: Making the Loudest Twenty Minutes Predictable
Published: 2026-07-25
URL: https://vizyplan.com/blog/school-bus-anxiety-autism-parents
Category: Parenting
Author: Justin Bowman
> The bus is the one part of the school day with no teacher, no schedule, and no adult who knows your child. It is also where a lot of good days get decided before they start.
Everything about the school day gets planned except the twenty minutes that start it. School bus anxiety is one of the most common back to school worries families raise and one of the least supported, because the bus sits in a gap: it belongs to the school, but it has no teacher, no visual schedule, no seating chart, and often no adult who has ever read your child's plan.
## School bus anxiety is a staffing and information problem, not just a nerves problem
A [2025 study published in Child: Care, Health and Development](https://pmc.ncbi.nlm.nih.gov/articles/PMC11914865/) built and tested a training program for school transportation staff, and the caregiver focus groups that shaped it named the issue plainly: transportation staff often lacked understanding of intellectual and developmental disabilities, student-to-staff ratios were high, and communication between parents and transportation personnel was inconsistent. The program reached 886 transportation staff members, and more than 90 percent said they were satisfied with it, with over 80 percent reporting increased knowledge and confidence.
That is good news and a diagnosis at the same time. Drivers are not unwilling. In most districts they have simply never been given the information.
Research on urban students found the downstream effect. Transportation problems getting to and from school predicted [fewer school resources, less sense of school belonging, and more school stressors, anxiety, and depression](https://www.academia.edu/12415422/Transportation_Challenges_for_Urban_Students_With_Disabilities_Parent_Perspectives). A bad ride is not a small thing that resolves at the classroom door. It sets the floor for the day.
## What actually makes the ride hard
Ask a child and you rarely get a clean answer, so it helps to know the usual suspects.
**Noise.** A full bus is loud, echoey, and unpredictable, which is the worst combination for a nervous system that is already over-responsive to sound. In a sample of 4,104 autistic people, [60.1 percent currently experienced auditory over-responsivity](https://link.springer.com/article/10.1007/s10803-021-04991-0).
**No visible schedule.** The child cannot see how many stops are left, cannot tell how long the ride will take, and has no way to know when it ends. Our post on [time blindness](/blog/time-blindness-autism-adhd-kids-parents) explains why "we are almost there" is not reassurance to a child who cannot feel the passage of twenty minutes.
**Social unpredictability.** Unassigned seats, mixed ages, no adult mediating. The bus is unstructured time on wheels, and unstructured time is consistently the hardest part of the school day, which our post on [recess and lunch](/blog/unstructured-time-recess-lunch-autism-teachers) covers from the school side.
**Motion and vestibular input.** Some children find the movement regulating. Some find it nauseating. Both are worth knowing about.
## Six things to do before the first ride
1. **Ask for the driver's name and the route number in August.** Then ask the school to pass a one-page profile to transportation. Most districts will do it if asked; almost none do it automatically. Our [one-page profile guide](/blog/one-page-profile-autism-new-teacher) works for a driver as well as a teacher.
2. **Request an assigned seat, preferably front-right.** Front seats are quieter, closer to the adult, and easier to exit. Ask for it in writing so it survives a driver change.
3. **Do a practice ride or a bus visit.** Many districts run a bus petting zoo or an orientation ride in August. If yours does not, ask if your child can sit on a parked bus for five minutes. Familiarity does most of the work.
4. **Send noise protection and a known item.** Headphones or loops, plus one predictable object. A ride with a fixed sensory plan is easier than a ride your child has to survive on improvisation.
5. **Make the ride countable.** Number of stops, a song that lasts the trip, a card with the route on it. Anything that turns an unknown duration into a finite one.
6. **Agree on a single exit script with the driver.** What your child does if they cannot get off, or cannot get on. One sentence, known by everyone, prevents most of the worst mornings.
## Build the ride into the routine instead of leaving it outside it
The bus tends to sit outside the visual schedule, which is exactly backward. It is the first transition of the day and the one with the least support. Putting it in the sequence, with a real photo of your bus stop and your bus, turns it from an ambush into a step.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the whole morning, including the part that happens on a corner at 7:15, can live in one place your child can see. Our guide to [resetting the back to school routine](/blog/back-to-school-routine-autism-reset) shows how to sequence the days leading up to it.
If the bus stays impossible after a real attempt, that is information, not failure. Transportation is a related service, and a documented need can be written into the plan.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Put the bus stop, the ride, and the classroom into one sequence your child can see coming. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## School Clothes and Sensory Issues: The Problem Nobody Plans For
Published: 2026-07-24
URL: https://vizyplan.com/blog/school-clothes-sensory-issues-autism
Category: Daily Routines
Author: Justin Bowman
> Nobody puts new clothes on the back to school worry list, and then the first Monday falls apart over a seam. Here is what the research says about tactile sensitivity and how to get ahead of it in July.
You bought the shoes in July. On the first Monday of school, your child is on the floor in the hallway, one sock on, twenty-two minutes behind, and the whole morning is gone. School clothes and sensory issues cause more ruined first weeks than almost anything else on the back to school list, and almost nobody plans for them, because clothing does not feel like it should be a problem.
It is a problem. And the research is unusually clear about how common it is.
## What the research says about school clothes and sensory issues
A [2025 mixed-methods study of 86 autistic adults](https://pmc.ncbi.nlm.nih.gov/articles/PMC12531387/) published in Autism asked directly about clothing. The numbers are striking. 73.2 percent regularly avoided certain types of clothing. 55.8 percent cut labels out of garments. 48.8 percent found it difficult to adapt to new clothing items. 48.8 percent avoided constricting clothes or shoes. 46.5 percent avoided items with seams that touched their skin.
Read that fourth one again. Difficulty adapting to *new* clothing is its own category. Which means the standard back to school move, a fresh wardrobe presented on the last weekend of summer, is close to a worst-case design.
The broader sensory picture backs it up. Between [56 and 70 percent of autistic youth](https://pmc.ncbi.nlm.nih.gov/articles/PMC4861140/) meet criteria for sensory over-responsivity, and a [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) found the tactile system affected in more than 80 percent of children struggling with school.
## A shirt is not a preference problem
The most useful reframe here is a simple one. When a child says a seam hurts, the seam hurts. Tactile over-responsivity is a difference in how the nervous system weights incoming touch information, not a story a child is telling to get out of getting dressed. A waistband that you would not notice can register the way a pebble in your shoe registers, except it is on for seven hours and nobody will let you take it off.
That distinction changes what you do next. You stop negotiating and start problem-solving.
## How to get ahead of it before the first Monday
1. **Start three weeks out, not the night before.** New clothes need wear-in time. A shirt worn twice around the house in July is not a new shirt in August.
2. **Wash everything twice before it counts.** Sizing chemicals and stiff finishes are a real part of why new clothes feel wrong. Two wash cycles change the hand of most fabrics noticeably.
3. **Let your child audit the current favorites first.** Whatever they already wear willingly is your specification sheet. Same fabric, same cut, same neckline, different color. Buy the thing that works, in multiples.
4. **Remove tags and check seams at purchase, not at 7am.** Cut tags, turn socks inside out, and try flat-seam or seamless options. Small changes, large returns.
5. **Do a full dress rehearsal, shoes included.** One hour, whole outfit, in the house, a week before school. You want to find the problem on a Tuesday afternoon, not on the first morning.
6. **Buy two of whatever wins.** A child who has one acceptable pair of pants is one laundry day away from a crisis.
## When there is a uniform
Uniforms remove the choice, which is the hardest version of this problem. A few things still work. Ask the school in writing what flexibility exists, because most uniform policies have more room than the handbook suggests: an undershirt beneath a scratchy polo, a different sock, softer shoes in the approved color, a cardigan instead of a blazer.
If a specific fabric is genuinely unwearable, it belongs in the accommodations conversation, not in a daily fight. A sensory-based clothing accommodation is a reasonable ask, and our post on [504 plans versus IEPs](/blog/504-vs-iep-provider-guide) covers which document is the right home for it.
## Give the getting-dressed sequence somewhere to live besides your voice
Once the clothes work, the other half of the morning is the sequence. Socks, then shoes, then jacket, then backpack. Most children who melt down at 7:12 are not refusing, they are stuck holding a five-step order in working memory while somebody narrates at them.
A visual sequence takes the order out of your mouth and puts it somewhere your child can look. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the getting-ready steps live in photos of your child's actual clothes and your actual hallway. Our post on [morning routine independence](/blog/autistic-child-morning-routine-independence) covers how to hand the sequence over without hovering.
Do the clothes work in July. It is the cheapest thing on the entire back to school list, and it buys you the first Monday.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give the morning a sequence your child can follow without a countdown from the kitchen. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Summer Regression and Recoupment: What to Measure in the First Three Weeks
Published: 2026-07-23
URL: https://vizyplan.com/blog/summer-regression-recoupment-provider-guide
Category: For Providers
Author: Justin Bowman
> Every August a caseload comes back looking rougher than it left. Some of that is real skill loss and some of it is context loss, and the two need completely different responses.
The first three sessions back in August always look worse than June did. Requests that were spontaneous are prompted again. A four-step routine that ran independently now needs two cues. Summer regression and recoupment is the frame everybody reaches for, and it is often correct, but reaching for it too fast hides a second explanation that calls for a completely different response.
## Summer regression and recoupment is a legal standard before it is a clinical one
The phrase comes out of extended school year eligibility. As [Autism Speaks summarizes](https://www.autismspeaks.org/blog/seven-things-know-about-esy), the common test is whether a student loses critical skills during a break and how long it takes to recover them once instruction resumes. Regression is the loss. Recoupment is the time to get back. A student who loses a lot and recovers fast reads very differently from one who loses a little and never quite returns.
That matters for providers well beyond the ESY meeting, because it tells you what to actually record. A note that says "regressed over summer" is not data. A note that says "four of six mands lost, all six recovered by session five" is.
## Skill loss and context loss look identical on day one
Here is the distinction worth protecting. A child who genuinely lost a skill will show the same weak performance across people and settings. A child who lost the context, the routine, the cue, the room, the adult who used to be there, will often perform well the moment one of those is restored.
The evidence base on generalization has been saying this for years, and it applies in reverse. A [meta-analysis of 51 effect sizes](https://pmc.ncbi.nlm.nih.gov/articles/PMC10539413/) on parent-implemented intervention found moderate overall benefits, and the authors noted that no measured characteristic, including dosage, reliably moderated outcomes. The likeliest reading is that measurement across settings was inconsistent, not that setting does not matter. Setting matters enormously. Our post on [the in-clinic to home generalization gap](/blog/in-clinic-to-home-generalization-gap-provider-guide) covers the same problem in the other direction.
So before you write a regression narrative, probe the same target twice: once cold, once with the original context restored. The difference between those two numbers is your answer.
## What to measure in the first three weeks
1. **Probe before you teach.** Run cold probes on three to five priority targets in the first session, before any instruction. A first-session probe is the only clean baseline you will get all year.
2. **Probe the same targets with context restored.** Same target, original cue, original materials, original setting if you can. Record both numbers side by side.
3. **Time the recoupment, do not just note it.** Sessions to criterion is the number that carries weight in an ESY conversation next spring. Write the session count, not the adjective.
4. **Ask the family what the summer actually looked like.** Ten weeks with no structure produces a different picture than ten weeks with a camp and a routine. Our post on [the summer routine cliff](/blog/summer-break-autistic-kids-routine-cliff) is a useful thing to hand a family who is already blaming themselves.
5. **Separate maintained skills from maintained conditions.** If a skill only holds under a specific antecedent, say so in the note. That sentence is the difference between a real maintenance claim and a fragile one.
6. **Set the fall data plan now, while the caseload is still light.** Three weeks from now you will not have time to design one.
## The other thing happening in August
School just restarted. Whatever you measure in the first three weeks is measured in a child who is also absorbing a new classroom, a new teacher, a new bus, and six and a half hours of demand they have not carried since June. A [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) found that among children in significant school distress, 92.5 percent scored above the clinically significant anxiety threshold. Not all of that is caused by school, but the start of school is where it becomes visible.
Practically, that means a flat August is not automatically regression, and a great August is not automatically maintenance. Note the school context in the same breath as the number.
## Make the home data collect itself
The cheapest recoupment data is the data a family generates without being asked. A visual routine that a child runs each morning produces completion information as a byproduct, which means you walk into the fall with two weeks of real home performance instead of an apology and a blank sheet. Our post on [home data collection families will actually keep up with](/blog/home-data-collection-parents-provider-guide) covers how to design that so it survives a 7am.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the routine a family already runs quietly becomes the evidence you need in the spring meeting.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the fall baseline includes what home actually looks like.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Kindergarten Transition for Autistic Children: What Actually Helps
Published: 2026-07-22
URL: https://vizyplan.com/blog/kindergarten-transition-autistic-children
Category: Parenting
Author: Justin Bowman
> Kindergarten is the largest structural change most autistic children have faced. Research shows that the supports families get are usually the light ones, and the families who need the most tend to receive the least.
Preschool had eleven children, two adults who knew your child's whole history, and a rhythm that bent when it needed to. The kindergarten transition swaps all of that at once: more children, fewer adults, a longer day, a bus, a cafeteria, a bathroom down the hall, and a set of expectations nobody explained to your child in a language they use. For most autistic children, the kindergarten transition is the largest structural change they have faced in their life so far.
## What the research says about the kindergarten transition
The honest finding is uncomfortable. A [national study of 1,989 children with disabilities](https://www.sciencedirect.com/science/article/abs/pii/S0885200610000761) entering kindergarten found that low-intensity transition supports, things like a generic flyer or a group orientation night, were used far more often than high-intensity ones like an individualized visit or direct contact between the old and new teams. The study also found that children coming from a different setting, and children in larger and higher-poverty districts, were less likely to receive support during the transition period. In other words, the families with the biggest gap to cross were the least likely to get a bridge.
A [2026 systematic review in Education Sciences](https://doi.org/10.3390/educsci16071164) synthesized twelve studies on parent perspectives and reached a similar conclusion. Structured transition programs and family-focused approaches look promising and remain underused, and the recurring theme across parent accounts is a gap between what is written into policy and what actually happens in August.
None of that means your school is failing you. It means the high-value supports usually have to be asked for by name.
## Ask for the four things that carry the most weight
1. **A real visit, not an open house.** Ask for fifteen minutes in the actual classroom, on a quiet day, with your child. An empty room at 3pm is more useful than a crowded orientation at 6pm. Our post on [meeting the teacher before the first day](/blog/meet-the-teacher-visit-autism-preparation) covers how to structure the visit.
2. **A conversation between the outgoing and incoming teams.** Not a file transfer. An actual conversation, ideally with you in it. The preschool team knows things about your child that no document will ever say well.
3. **Photos of the specific places, not the building.** The classroom door. The cubby. The bathroom your child will use. The spot in the cafeteria. Generic school photos do not reduce uncertainty. Specific ones do.
4. **A written plan for the first two weeks, not just the year.** Who greets your child at the door. What happens if they cannot get off the bus. Where they go when it is too much. The IEP covers the year. The first fourteen days need their own answer.
## Practice the parts nobody practices
Most kindergarten readiness lists focus on letters and numbers. The parts that actually derail a first month are usually logistical.
The bathroom down the hall, with a hand dryer, that you have to ask permission to use. The cafeteria, which is loud enough that our post on [school lunch for a selective eater](/blog/school-lunch-selective-eater-autism) treats it as a sensory event before a food event. The bus. Lining up. Waiting. Being one of twenty-two instead of one of eleven.
You do not need to simulate a whole school. You need to run three or four of the hardest micro-routines enough times that they stop being novel. Practicing "we walk to the bathroom, we wash, we come back" in a library or a grocery store is a genuinely useful use of August.
## Expect a hard September, and plan for the afternoons
Here is the part that surprises families most. The kindergarten transition often looks fine at school and falls apart at home. A child holding themselves together for six and a half hours in a brand new environment arrives in your car with nothing left. That crash has a name, and our post on [after-school restraint collapse](/blog/after-school-restraint-collapse-autism) explains why it is a release rather than a behavior problem.
Plan the afternoons before you need them. Low demands. Familiar food. No errands in week one. The evening routine matters more in September than it does in March, because it is the only predictable part of your child's day.
## Give the new day a shape they can see
A kindergartener cannot hold a six-hour sequence in working memory. Nobody can. What they can do is look at what comes next. Visual activity schedules are not a soft support; a [review published in the Journal of Autism and Developmental Disorders](https://pubmed.ncbi.nlm.nih.gov/25081593/) evaluated 31 studies and concluded that visual activity schedules qualify as an evidence-based practice for autistic individuals.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the morning, the school day, and the evening can live in one place your child can actually read at five years old. Our guide to [resetting the back to school routine](/blog/back-to-school-routine-autism-reset) has the timeline for the two weeks before day one.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give your kindergartener a day they can see coming, from the bus to bedtime. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Back to School Staff Handoff: Moving What Worked Into the New Room
Published: 2026-07-21
URL: https://vizyplan.com/blog/back-to-school-staff-handoff-autism-students
Category: For Schools
Author: Justin Bowman
> Every August, a year of hard-won knowledge about a student evaporates between June and September. The IEP survives the summer. The working knowledge usually does not, and rebuilding it costs the student the first six weeks.
In June, one teacher knew that this student needs the two-minute warning delivered by showing rather than telling, that the hallway by the gym is a hard no before lunch, and that "I need a break" comes out as head-down-on-desk rather than words. In September, a new teacher knows the student's name and reading level. The back to school staff handoff is the bridge between those two facts, and in most buildings it does not exist as a formal step.
The IEP survives the summer because the law requires it to. The working knowledge does not, and rebuilding it by trial and error costs the student six weeks of a school year they only get once.
## What a back to school staff handoff actually needs to carry
The paperwork already tells the new team the goals and the minutes. What it rarely tells them is how the student actually operates on a Tuesday. Four categories are worth writing down.
**The regulation signal.** What does escalation look like in the ten minutes before it becomes visible? Nearly every student has a tell, and the person who spent 180 days with them knows it. Passing that along is worth more than any behavior plan section, because the whole point is intervening before the plan is needed.
**The predictable landmines.** Fire alarms. Substitute days. The last twenty minutes before dismissal. Assemblies. Group work with a specific classmate. A short list of known triggers saves the new teacher from discovering each one live, in front of twenty-four peers.
**What actually works, and what only looks like it works.** Accommodations get written once and inherited forever. Some of them stopped helping in November. Say so. The IRIS Center's guidance on [implementing an accommodation](https://iris.peabody.vanderbilt.edu/module/acc/cresource/q3/p09/) is direct about this: an accommodation only counts if it is delivered consistently and actually changes access, and a team should be monitoring whether it does.
**The parent's read.** Families carry a year of context that never made it into a meeting. A five-minute call in August is cheaper than a crisis in October.
## Why the first six weeks are the ones that matter
A [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) in Frontiers in Psychiatry found that among children experiencing significant school distress, 92.1 percent were neurodivergent and 92.5 percent scored above the clinically significant threshold for anxiety. School distress rarely announces itself on day one. It builds across the first weeks, as the gap widens between what a student can predict and what the environment actually does.
Meanwhile, the research on classroom management points the same direction. The Campbell Collaboration's [systematic review of teacher classroom management practices](https://onlinelibrary.wiley.com/doi/10.4073/csr.2011.4) found that deliberate management practices reduce disruptive and aggressive behavior. The word doing the work there is deliberate. A teacher who knows on day one that this student needs the schedule shown rather than announced is being deliberate. A teacher who learns it in week five is doing recovery.
## A handoff that takes twenty minutes
1. **Ask the outgoing teacher for three sentences, not a form.** What worked, what backfired, what you would tell your replacement over coffee. Three sentences get written. A four-page form does not.
2. **Attach a one-page profile to the front of the file.** Strengths, communication style, regulation signals, what helps. Our guide to [building a one-page profile for a new teacher](/blog/one-page-profile-autism-new-teacher) has the template.
3. **Flag the accommodations that need day-one delivery.** Not all of them are equal. Two or three carry most of the access, and those should be running before the first bell, not after the first incident.
4. **Name one adult who is the student's known person.** In a new building, a single reliably safe adult does more for regulation than any strategy on paper.
5. **Send the family a short note before the first day.** One paragraph, from the new teacher, saying what the mornings will look like. Parents pass that to their child, and the child walks in with a picture instead of a question.
6. **Put a check-in on the calendar for week three.** Not to review the IEP. To ask the outgoing teacher one question: is this what you saw too?
## Predictability is the thing you are actually handing off
Everything on that list is one idea wearing different clothes. A student who can predict the room, the person, and the sequence spends their energy on learning. A student who cannot spends it on scanning. Our posts on [transition warnings in the classroom](/blog/classroom-transition-warnings-autism-teachers) and [substitute teacher plans](/blog/substitute-teacher-plan-autistic-students) cover the two moments where predictability breaks down most often.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the sequence a student relies on can travel between the classroom and the kitchen table without being rebuilt by each new adult.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so what worked last year keeps working in the new room.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Back to School Supply Shopping With a Sensory Sensitive Child
Published: 2026-07-20
URL: https://vizyplan.com/blog/back-to-school-supply-shopping-sensory
Category: Parenting
Author: Justin Bowman
> The supply list has forty-one items and the store has fluorescent lights, a crowd, and a hundred small decisions. Here is how to plan the trip so your child stays regulated and the cart makes it to the register.
The list came home in June with forty-one items on it. Back to school supply shopping sounds like a simple errand, but for a sensory sensitive child it is a fluorescent-lit obstacle course with a crowd, a time limit, and a hundred small decisions stacked on top of each other. If last year ended with an abandoned cart in aisle nine, the problem was almost certainly the environment, not your child's attitude.
## Why back to school supply shopping overloads a sensory system
Sensory over-responsivity is not a rare add-on to autism. Somewhere between [56 and 70 percent of autistic youth](https://pmc.ncbi.nlm.nih.gov/articles/PMC4861140/) meet criteria for it. Sound is the most common culprit. In a sample of 4,104 autistic people, [60.1 percent currently experienced auditory over-responsivity](https://link.springer.com/article/10.1007/s10803-021-04991-0) and 71.1 percent had experienced it at some point in their lives.
Now picture the store. Overhead announcements, cart wheels on tile, a checkout beep every two seconds, other families with the same list and the same deadline. A [2023 study of 1,121 families](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2023.1237052/full) in Frontiers in Psychiatry found that children struggling with school reported differences across an average of 4.8 sensory systems, with tactile and auditory systems affected in more than 80 percent of cases. A big-box store hits both of those at once, for an hour, on a Saturday.
## Shrink the trip, not your expectations
The goal is not to toughen your child up in the school supply aisle. The goal is to come home with pencils and a kid who still has something left for the rest of the day.
1. **Order the boring two-thirds online.** Pencils, glue sticks, and tissues do not need to be touched. Buy those without leaving the house and reserve the trip for the items where your child's opinion actually matters.
2. **Go at the quietest hour you can find.** Weekday mornings right at open, or the last hour before close, cut the crowd and the noise floor dramatically.
3. **Show the store before you go.** Pull up photos of the entrance, the aisle, and the checkout. Predictability is the whole game, and our post on [why autistic kids resist transitions](/blog/why-autistic-kids-resist-transitions) explains what happens in the body when a place is unknown.
4. **Bring the exit plan with you.** Decide in advance what "we are done" looks like. A child who knows the trip is four items long can spend energy on the four items instead of on wondering when it ends.
5. **Let your child pick exactly two things.** Choice reduces resistance, but an open aisle of options is its own kind of overload. Two real choices beat twenty theoretical ones.
6. **Pack the sensory kit.** Headphones, sunglasses, a chewy, a familiar snack. Bringing the regulation tools is not coddling, it is the same logic as bringing a jacket.
## Buy for the body, not for the aisle end cap
Half of a back to school supply list ends up touching your child for seven hours a day. That deserves more thought than the character on the front.
Backpacks are the biggest one. Weight matters, but so do the straps, the chest clip, and whether the zipper pull makes a sound your child hates. Try it on loaded, not empty. Shoes and clothing carry the same problem, and the research is blunt about it: in a [2025 study of 86 autistic adults](https://pmc.ncbi.nlm.nih.gov/articles/PMC12531387/) published in Autism, 73.2 percent regularly avoided certain clothing types and 46.5 percent avoided items with seams that touched their skin. Our post on [school clothes and sensory issues](/blog/school-clothes-sensory-issues-autism) goes deeper on fabric, seams, and the shoe problem.
For supplies themselves, watch for the small stuff nobody thinks about. Squeaky dry-erase markers. Scratchy folder edges. A pencil box that snaps shut with a bang. A three-ring binder that pinches. If your child has strong opinions about texture, let them run a hand over the options before you commit.
## Turn the trip into something your child can see coming
An errand is abstract. A sequence is not. Before you leave, walk through the plan in order: car, doors, backpack aisle, notebooks, checkout, car, home. Say it once, show it once, and then let the plan do the work instead of your voice.
That is exactly what a visual routine is for. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a child can look at the next step in photos of their own world instead of holding six instructions in their head. A shopping trip is just a routine with a receipt at the end.
## One more thing worth doing while you are out
Buy the school-year sensory supplies now, not in October when everyone is already struggling. Headphones for the cafeteria. A chewy for the bus. A spare set of soft clothes for the nurse's office. The families who plan for the loud parts of the school day in July are not being pessimistic. They are just buying the umbrella before it rains, and our guide to [resetting the back to school routine](/blog/back-to-school-routine-autism-reset) covers what else belongs on that list.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Turn the errands, the mornings, and the first week of school into something your child can see coming. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Sound Frequency for Calm: The Real Science Behind VizyPlan's Resyna
Published: 2026-07-19 · Updated: 2026-07-19
URL: https://vizyplan.com/blog/sound-frequency-for-calm-resyna-science
Category: Technology
Author: Justin Bowman
> Calming tools usually get sold to people with time to meditate. Resyna was built for the other moment, when the parent, the caregiver, the provider, and the child have all run out of reserves and calm has to come to them.
It is 4:45. The meltdown has just ended, dinner has not started, and you are sitting on the hallway floor with nothing left. Sound frequency for calm usually gets marketed to people with a yoga mat and a free hour. We built [Resyna](/blog/resyna-calm-button-vizyplan), our patent-pending frequency-based calm and focus support, for the other moment. The one where you and your child are both far past the point of trying harder.
## Calm should not require energy you already spent
Almost every calming strategy asks something of you first. Count your breaths. Name the feeling. Sit still. Those are real skills, and they are worth building. But they all bill the person who is already overdrawn.
That is the autistic child at 4:45 who cannot access a single word right now. It is you at 10pm, running on the fumes of a week you did not get to rest in. It is the grandmother doing pickup three days a week, the RBT with eleven minutes between sessions, the SLP who has given everything to other people's children since 7am. Burnout is not a character flaw in any of them. It is arithmetic. What we wanted was something that meets a person where they already are and does the work for them.
## What sound frequency for calm actually does
The most replicated finding here is not a magic number of hertz. It is how fast you breathe. A [meta-analysis in Neuroscience and Biobehavioral Reviews](https://pubmed.ncbi.nlm.nih.gov/35623448/) pooled 223 studies and found voluntary slow breathing reliably increases vagally-mediated heart rate variability, with few adverse effects expected. A [meta-analysis in Psychological Medicine](https://pubmed.ncbi.nlm.nih.gov/28478782/) found training that same rhythm produced a large drop in self-reported stress and anxiety.
Around six breaths a minute, heart rate and blood pressure oscillations fall into a phase relationship that reinforces itself through the baroreflex ([Frontiers in Psychology, 2014](https://www.frontiersin.org/journals/psychology/articles/10.3389/fpsyg.2014.00756/full)). The sweet spot [varies from person to person](https://www.frontiersin.org/journals/neuroscience/articles/10.3389/fnins.2020.570400/full), which is why Resyna listens and adapts rather than playing one fixed pace at everybody. The best part is that none of it requires you to try. Your body already knows this rhythm. Resyna just holds the door open.
## Why sound, and why we left silence in it
In a study published in [Heart](https://pmc.ncbi.nlm.nih.gov/articles/PMC1860846/), Bernardi and colleagues found breathing entrains to musical rhythm. The loveliest result is the one nobody cites: random pauses inserted into the music dropped heart rate and blood pressure below the resting baseline. The silence between the sounds was more calming than silence alone. That is why Resyna has space built into it instead of filling every second. And because [auditory guidance does not compete for visual attention](https://www.frontiersin.org/journals/computer-science/articles/10.3389/fcomp.2022.926649/full), nobody has to look at a screen. Eyes closed is the whole point.
## What we will not tell you
We love this community too much to oversell. Binaural beats do not reliably retune brainwaves; a [PLOS One review](https://pmc.ncbi.nlm.nih.gov/articles/PMC10198548/) of 14 studies found 8 contradicting the idea. The famous 528 Hz claims trace back to 1970s numerology, not ancient wisdom, and rest on a study of nine people. And sound is genuinely not right for every child: a [meta-analysis of 13,433 autistic individuals](https://pmc.ncbi.nlm.nih.gov/articles/PMC8349927/) found roughly 41 percent currently experience decreased sound tolerance. So Resyna is opt-in, starts quiet, and stays under your control. You know your child. We would rather earn your trust than your click.
## For whoever needs it tonight
Resyna follows the listener's heart rhythm and uses gentle, adaptive tones to guide breathing toward that steadier pace. It works the same whether the person in the headphones is seven or forty-seven. Your child after a hard afternoon. You on the couch once the house is finally quiet. The provider decompressing in the car before the drive home. One calm button, for anyone who has run out of reserves. You do not have to be good at this. You just have to press play.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Meet Resyna and give your whole family a calm button for the hard moments. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
A gentle note on safe use: Resyna and [VizyPlan](https://vizyplan.com)'s Calming Frequency are wellness tools designed to support relaxation. They are not a medical device and are not medical advice. They do not diagnose, treat, cure, or prevent any condition, and they are not a substitute for care from a qualified professional. Start with just 2 to 5 minutes at a comfortable volume and build up gradually. If you feel any discomfort, dizziness, or unease, stop right away. If you are pregnant, or you or your child has epilepsy, a seizure disorder, or a heart condition, please check with your doctor before use. Do not operate heavy machinery after listening. Use of the heart-guided calm score requires a paired Apple Watch with heart-rate and health sharing enabled. The calm score is a relaxation-feedback indicator only. It is not a diagnosis, a fitness metric, or a measure of your health. Resyna does not monitor for, detect, or alert you to arrhythmias, heart conditions, or any other medical issue, and it should never be relied on for that purpose. If you have any health concern, contact a qualified medical professional.
---
## Home Data Collection Parents Will Actually Keep Up With
Published: 2026-07-18
URL: https://vizyplan.com/blog/home-data-collection-parents-provider-guide
Category: For Providers
Author: Justin Bowman
> The data sheet comes back with four entries and an apology. That is almost never low buy-in. Home data collection fails for the same reason clinical fidelity data fails, and the fix is design, not motivation.
You handed the family a data sheet three weeks ago. It comes back with four entries, all from the first two days, and an apologetic note in the margin. The reflex is to read that as low buy-in. It is almost never low buy-in. Home data collection fails for the same reason clinical fidelity data fails, which is that the system asked for more than the moment could give. Designing home data collection around a tired parent at 7 a.m. is not lowering your standards. It is the only way to get data at all.
## Clinic observation misses what home sees
Start with the finding that should change how you weigh caregiver report. In a [multi-site randomized trial analysis](https://pmc.ncbi.nlm.nih.gov/articles/PMC8691726/) in Research in Autism Spectrum Disorders, 126 of 168 children showed zero disruptive behavior during structured direct observation at baseline, even though moderate disruptive behavior was required to enroll. The observation measure could not detect group differences that parent-report and clinician-rated measures found significant. The behavior did not disappear. The clinic simply was not where it lived.
Parent report holds up better than its reputation, too. A [comparative study of 109 toddlers](https://pmc.ncbi.nlm.nih.gov/articles/PMC5599144/) found no significant differences between parent report and direct assessment for receptive or expressive language. Where the two diverged, parents tended to report skills direct testing had missed, so add a light verification step rather than discounting the report.
## Even clinicians cannot sustain heavy data systems
Before assigning blame to families, look at the professional baseline. A [2024 survey of 203 BCBAs](https://pmc.ncbi.nlm.nih.gov/articles/PMC12779883/) found most collected procedural-fidelity data on 20 percent or fewer of their supervision sessions, for logistical reasons: lack of resources, no employer requirement, limited time, heavy caseloads. Trained clinicians with dedicated time struggle to sustain effortful data collection. A parent mid-meltdown will not outperform them.
## Design home data collection around the moment
The case for pushing work home is strong. A [meta-analysis of 51 effect sizes](https://pmc.ncbi.nlm.nih.gov/articles/PMC10539413/) found parent-implemented intervention produced moderate overall benefits. One caution: that same analysis found no measured characteristic, including dosage and fidelity, significantly moderated outcomes. The authors called it unexpected, and the likeliest explanation is inconsistent fidelity measurement across studies rather than fidelity being unimportant. Do not read it as permission to stop checking.
1. **Pick one target, not five.** A single behavior tracked for two weeks beats five tracked for two days.
2. **Make the entry a tap, not a sentence.** Yes or no, or a simple count, answers most clinical questions.
3. **Anchor it to a routine that already happens.** Attach data to bedtime or the bus, never to a free-floating reminder.
4. **Use what you already get for free.** A completed visual routine is data whether or not anyone calls it that.
5. **Show the family their own graph.** Caregiver self-efficacy rose across [33 randomized trials](https://pmc.ncbi.nlm.nih.gov/articles/PMC6839885/) of caregiver-mediated intervention, and seeing progress is part of why.
## Let the routine do the recording
The lightest data system is the one nobody has to remember. When a family already runs a visual routine, completion gets captured as a byproduct, and you walk into the next session with two weeks of real home data instead of an apology. Our post on [telehealth parent coaching](/blog/telehealth-parent-coaching-autism-carryover-provider-guide) pairs well with this one.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the routine a family already runs quietly becomes the data you need.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so home data collects itself instead of becoming homework.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## After-School Restraint Collapse: Why the Good Day Ends in Tears
Published: 2026-07-17
URL: https://vizyplan.com/blog/after-school-restraint-collapse-autism
Category: Parenting
Author: Justin Bowman
> The teacher says your child had a great day. Then they walk through the door and fall apart. After-school restraint collapse is not a clinical diagnosis, but every ingredient in it is backed by real research.
The note from the teacher says your child had a wonderful day. Cooperative, focused, no problems at all. Forty minutes later they are on the kitchen floor screaming because the wrong cup came out of the cabinet. After-school restraint collapse is the name parents use for that pattern, and if you have lived it you know its particular loneliness, because the version of your child everyone else sees is not the one you are holding at 3:30.
## Being honest about the term
There is no clinical diagnosis called after-school restraint collapse. The phrase was coined by a parenting counsellor, not a research team, and it does not appear in the DSM or in peer-reviewed literature. Nobody has measured how many autistic kids experience it, and anyone quoting a percentage is inventing one. The pattern is parent-observed. But every ingredient in it is independently evidenced, which is a sturdier place to stand than a borrowed statistic.
## What builds up to after-school restraint collapse
The clearest piece is masking. In a [study of 733 autistic children and teens](https://pubmed.ncbi.nlm.nih.gov/36416274/) in Autism Research, camouflaging predicted internalizing symptoms including anxiety, depression, and somatic complaints. A [meta-analysis of 5,897 autistic participants](https://research.birmingham.ac.uk/en/publications/a-systematic-review-and-meta-analysis-of-mental-health-outcomes-a/) found camouflaging moderately correlated with anxiety, depression, and lower wellbeing. Both are correlational, and the review authors are careful that causal direction is not established.
There is a baseline load worth naming too. A [meta-analysis of 31 studies](https://pmc.ncbi.nlm.nih.gov/articles/PMC3162631/) found 39.6 percent of autistic youth met criteria for at least one anxiety disorder. A full school day is not merely tiring for a child carrying that. It is expensive.
## Why the teacher genuinely is not seeing it
A [latent profile analysis of 194 autistic children](https://pmc.ncbi.nlm.nih.gov/articles/PMC12923639/) in Autism found one group of 40 children whose teachers rated their adaptive skills notably higher than their parents did. The study documents discrepant perceptions across settings rather than proving a cause, but the disagreement between you and the school is a known phenomenon, not a failure of your credibility.
Autistic burnout is the related concept with real depth behind it. A [qualitative study](https://pmc.ncbi.nlm.nih.gov/articles/PMC7313636/) in Autism in Adulthood defined it as chronic exhaustion and reduced tolerance to stimulus arising from a mismatch between expectations and support. That work was done with autistic adults, so apply it downward carefully. The useful part is the recovery factors named: time off, reduced expectations, permission to unmask.
## What actually helps at 3:30
1. **Front-load food and quiet before conversation.** Questions about the day can wait an hour.
2. **Drop the demands for the first thirty minutes.** No homework, no chores, no debrief.
3. **Let the stims out.** Unmasking is a recovery mechanism, not misbehavior.
4. **Make the after-school sequence predictable.** The same three steps every day removes one more decision.
5. **Stop treating the collapse as the report card.** The meltdown is the cost of the good day, not proof it was fake.
No trial has tested a decompression period after school. The advice above applies the masking and burnout literature sensibly. It is not a proven protocol.
## Predictability lowers the price of the landing
An after-school routine your child can see, rather than one arriving as spoken demands, takes pressure off the moment they have least left to give. Our post on [autistic burnout warning signs in kids](/blog/autistic-burnout-in-kids-warning-signs) goes deeper.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the hardest part of the afternoon runs on photos of your own child instead of on your voice.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give the after-school hour a shape your child can see coming. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Unstructured Time Is the Hardest Part of the School Day
Published: 2026-07-16
URL: https://vizyplan.com/blog/unstructured-time-recess-lunch-autism-teachers
Category: For Schools
Author: Justin Bowman
> Teachers plan every academic minute and then hand autistic students the two least structured hours of the day. Recess and lunch are where inclusion most often quietly fails, and where a little structure buys the most.
You plan every academic minute. The reading block is sequenced, the math rotation is timed, the transitions are scripted. Then the bell rings and an autistic student walks into the two least structured hours of the day with no plan at all. Unstructured time is where inclusion most often quietly fails, and recess and lunch are where a small amount of structure buys more than almost anything else you could do.
## Half the class is not really in the class
The most sobering finding comes from a [study of 79 children with autism matched against 79 peers across 30 schools](https://pubmed.ncbi.nlm.nih.gov/20673234/) in the Journal of Child Psychology and Psychiatry. Only about 48 percent of the autistic children participated in their classroom's social networks, and disconnection grew more pronounced in later elementary grades. The detail that should change how teachers read a playground: those children were not necessarily rejected more than their peers. They were accepted less. Nobody is being cruel. They are simply not being included, which is harder to see and easier to leave alone.
The children notice. In a [matched-groups study in Child Development](https://pubmed.ncbi.nlm.nih.gov/10834476/), autistic children reported more loneliness and poorer friendship quality than matched peers, even though all reported having at least one friend.
## Unstructured time needs a plan, not just supervision
Researchers running a structured recess program said it plainly: playgrounds are generally unstructured, producing little social engagement for children with autism, and mere inclusion in general education classrooms is not enough. Their [program raised peer engagement](https://pmc.ncbi.nlm.nih.gov/articles/PMC5843568/) from 0 to 34 percent of observed intervals at baseline to 54 to 87 percent. A separate [peer-mediated recess package](https://pmc.ncbi.nlm.nih.gov/articles/PMC4547561/) raised total communications from 9 to 35 percent of intervals to 77 to 85 percent, and it included pre-recess priming, the same mechanism that helps transitions. Both studies were small, so treat exact numbers as illustrative.
Noise matters too. An [integrative review](https://pmc.ncbi.nlm.nih.gov/articles/PMC8430329/) reports auditory stimuli are the most significant barrier to classroom engagement for autistic students. No study has measured cafeteria sensory load specifically, so nobody can give you a decibel number, but a room with three hundred children and hard surfaces is the loudest place in the building.
## Light structure that actually helps
1. **Give the block a plan the student can see.** One or two named options beat an open field.
2. **Prime before the bell.** A thirty-second preview of recess does real work.
3. **Set up an activity, not a buddy assignment.** Shared games create reasons to interact that do not depend on small talk.
4. **Offer a quieter alternative to the cafeteria.** A smaller room is an accommodation, not a punishment.
5. **Watch acceptance, not rejection.** The student nobody is unkind to and nobody includes is the one to look for.
## Predictability travels
Our post on [the sensory-friendly classroom](/blog/sensory-friendly-classroom-setup-teachers) builds out the rest of the day.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a student can see what is coming next, in photos of their own world, at school and at home.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the predictable parts of the day follow the student home.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Discharge Planning That Starts on Day One, Not Month Ten
Published: 2026-07-15
URL: https://vizyplan.com/blog/discharge-planning-autism-therapy-provider-guide
Category: For Providers
Author: Justin Bowman
> The hardest session on your caseload is the last one. Discharge planning is the part of practice most likely to be improvised at the end, and the part most likely to decide whether the work lasted.
The hardest session on your caseload is not the difficult one. It is the last one. The family is grateful, the data looks good, and everyone quietly wonders whether any of it holds in six months. Discharge planning is the piece of practice most likely to get improvised at the end, and the piece most likely to decide whether the work lasted. Done well, it does not begin when goals are met. Discharge planning begins at intake.
## Generalization is programmed, never assumed
The field settled this almost fifty years ago. Stokes and Baer's [foundational 1977 paper](https://pmc.ncbi.nlm.nih.gov/articles/PMC1311194/) in the Journal of Applied Behavior Analysis argued generalization must be actively programmed rather than treated as a byproduct of training, and gave the default approach a name that still stings: Train and Hope. A skill mastered in your therapy room is evidence about your therapy room. Whether it shows up at the kitchen table on Saturday has to be engineered on purpose.
## Discharge planning is about function, not just mastery
ASHA's guidance on [when to end services](https://www.asha.org/slp/when-to-end-services/) sets a bar higher than a completed goal list. Services end when goals are met, skills are age and culturally appropriate, and there is no ongoing impact on function. At discharge, the clinician is expected to put a home program or care-partner strategies in place to maintain skills, and to tell the family which signs should bring them back. The same guidance frames the work as beginning at the start of services.
## The caregiver is the maintenance plan
If you want a mechanism that outlives the authorization, it is the parent. A [meta-analysis of 33 randomized trials](https://pmc.ncbi.nlm.nih.gov/articles/PMC6839885/) in PLoS One found parent-mediated intervention improved child self-regulation, social skills, expressive language, and symptom severity, while parent distress fell. Honesty matters here: the same analysis found no significant gains in adaptive behavior, receptive language, or joint attention.
Durability is uneven too. A [long-term follow-up](https://pmc.ncbi.nlm.nih.gov/articles/PMC9114088/) tracked families one to five years out and found social-impairment gains held while improvements in problem behavior and parenting stress did not. Some gains coast. Some need refueling.
## Fade on a schedule you wrote down
1. **Write the exit criteria at intake.** Name what done looks like in functional terms before the first goal is trained.
2. **Program the last setting first.** Train in the environments the child actually lives in.
3. **Fade prompts deliberately and individually.** A [2024 single-case evaluation](https://pmc.ncbi.nlm.nih.gov/articles/PMC11428823/) with one learner found the most effective fading condition was not the predictable one, a reminder to assess per child rather than apply a house method.
4. **Hand the parent the running of it.** Shift from clinician-run to parent-run while you are still in the room to correct it.
5. **Leave a re-entry trigger.** Tell the family in plain words which changes should prompt a call back.
## Leave behind something that runs itself
A home program only matters if it survives the week it was handed over. A visual routine the family already uses gives your fading plan somewhere to live. Our guide to [closing the clinic-to-home generalization gap](/blog/in-clinic-to-home-generalization-gap-provider-guide) covers the handoff in more detail.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the structure you build in therapy keeps running at home after discharge.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the gains you built survive the last session.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Meet-the-Teacher Visit, Done the Way Autistic Kids Need
Published: 2026-07-14
URL: https://vizyplan.com/blog/meet-the-teacher-visit-autism-preparation
Category: Parenting
Author: Justin Bowman
> The meet-the-teacher visit is usually one hurried evening in a crowded room, which is close to the worst possible format for an autistic child. Here is how to turn it into something that actually lowers the anxiety of day one.
The standard meet-the-teacher visit is one evening, in a hot room, with forty families talking at once and a teacher trying to greet all of them. For a lot of autistic kids, that format delivers the sensory load of a birthday party and almost none of the information they actually needed. A meet-the-teacher visit can genuinely lower first-day anxiety, but usually not in the shape the school offers it. The version that works is quieter, shorter, and repeated.
## Advance exposure is a real strategy, not just a nicety
Preparing a child in advance is among the better-supported ideas in autism practice. The [third-generation evidence review](https://pubmed.ncbi.nlm.nih.gov/33449225/) in the Journal of Autism and Developmental Disorders identified 28 evidence-based practices, and social narratives, video modeling, visual supports, and antecedent-based interventions are all among them. Those four are the exact toolkit for a school visit.
The direct evidence for the visit itself is thinner, and worth naming honestly. A [small qualitative study](https://www.frontiersin.org/journals/education/articles/10.3389/feduc.2020.551574/full) of six autistic students and their parents found pre-transition visits were central to reducing anxiety, and most students visited more than once. Six families is not a large evidence base, but it matches what a [study of three children](https://ncaep.fpg.unc.edu/resource/the-use-of-video-priming-to-reduce-disruptive-transition-behavior-in-children-with-autism/) found about previewing a situation in advance. Show them the thing before the thing.
## The relationship outlasts the room tour
There is a bigger reason to go. A [meta-analysis of 117 studies](https://eric.ed.gov/?id=EJ1209223) in the Review of Educational Research found family-school partnership interventions improved children's social-behavioral competence and mental health, and the components tied to positive outcomes were the relational ones: communication, collaboration, and the parent-teacher relationship itself. You are not there to find the cubbies. You are there to start a working relationship with the adult who gets six hours a day with your child.
## How to run the meet-the-teacher visit
1. **Ask for a quiet slot instead of the open house.** Ten minutes in an empty classroom beats an hour in a packed one.
2. **Go more than once if you can.** Short and repeated beats long and singular.
3. **Take photos while you are there.** The door, the desk, the bathroom, the drop-off spot. Photos become the social story.
4. **Walk the parts that are not the classroom.** Hallways, the bus loop, and the lunchroom are where the hard moments live.
5. **Hand the teacher one page, not your whole history.** What calms your child, what escalates them, and how to reach you.
## Turn the photos into something they can revisit
The visit works best when it does not end at the visit. A short visual walkthrough your child can look at on their own, as often as they want, is where the priming compounds. Our post on [the one-page profile for a new teacher](/blog/one-page-profile-autism-new-teacher) pairs directly with this one.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so those photos become a routine your child can walk through before day one ever arrives.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Turn a school visit into a routine your child can rehearse. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Classroom Transition Warnings: What the Research Actually Says
Published: 2026-07-13
URL: https://vizyplan.com/blog/classroom-transition-warnings-autism-teachers
Category: For Schools
Author: Justin Bowman
> Teachers get sold visual schedules as a cure for hard transitions. The most rigorous study on the question found the schedule alone did not reduce problem behavior. Here is the honest version, and what it means for your classroom.
Every teacher who has run a classroom with autistic students has been handed the same advice. Put up a visual schedule, give a five-minute warning, and transitions will get easier. Classroom transition warnings genuinely help, and that advice is not wrong. It is just incomplete in a way that sets teachers up to feel like they failed when the schedule goes up and the 10:15 handoff still falls apart.
## The finding nobody quotes
Here is the study that deserves more airtime. In a [single-case experiment in the Journal of Applied Behavior Analysis](https://pmc.ncbi.nlm.nih.gov/articles/PMC2695333/), researchers tested visual schedules by themselves with two six-year-old boys with autism. The schedules alone did not reduce transition-related problem behavior. What did the work was extinction plus differential reinforcement, which cut problem behavior 69 to 83 percent. Adding the visual schedule on top improved that only slightly, to 76 to 89 percent.
Two participants is a small study, so do not over-read it. But it matches a caveat running through the wider literature: visual schedules are almost always delivered inside a package with prompting and reinforcement, and few studies isolate the schedule itself. The honest summary is that the schedule is the scaffolding, not the intervention.
## What classroom transition warnings do have behind them
None of that makes visual supports optional. The National Clearinghouse on Autism Evidence and Practice identified [28 evidence-based practices](https://autismpdc.fpg.unc.edu/ebps/) from research published between 1990 and 2017, and both Visual Supports and Antecedent-Based Interventions are on that list. A [meta-analysis covering 24 children](https://dergipark.org.tr/en/pub/akukeg/article/1109787) found visual activity schedules increased independence during transitions with a strong overall effect.
One popular claim does not survive checking. The study usually cited for the specific two-minute warning is repeated everywhere in secondary sources, but the primary article is not locatable. Give warnings, and skip the false precision about the exact number of minutes.
## Building the whole package
1. **Warn before the change, every time.** Consistency matters more than the interval you pick.
2. **Make the next thing visible, not just audible.** A student should be able to look and see what is coming.
3. **Pair the warning with a timer they can watch.** Time passing is abstract until it is visual.
4. **Plan the response, not just the antecedent.** What you do when a transition goes badly is doing most of the work.
5. **Reinforce the transitions that go well.** The easy ones are where the skill gets built.
## Consistency across settings is the multiplier
A schedule that looks one way in your room and another way at home asks a student to learn two systems instead of one. Our post on [why autistic kids resist transitions](/blog/why-autistic-kids-resist-transitions) goes deeper.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the visual structure you build at school keeps its shape at home, using photos of the real child.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so transitions look the same at school and at home.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Parent-Friendly Therapy Goals That Families Actually Follow
Published: 2026-07-12
URL: https://vizyplan.com/blog/parent-friendly-therapy-goals-provider-guide
Category: For Providers
Author: Justin Bowman
> A goal can be measurable, defensible at authorization review, and still completely unusable by the parent holding it. Parent-friendly therapy goals are what turn a treatment plan into something that runs on a Tuesday morning.
You wrote a good goal. Given a visual prompt, the client will independently initiate a three-step morning sequence with 80 percent accuracy across three consecutive sessions. It is measurable, defensible at authorization review, and exactly what the funder wants. And the parent holding that page still does not know what to do on Tuesday morning. Parent-friendly therapy goals are not a softer version of clinical rigor. They are the difference between a plan that lives in a chart and a plan that runs at home.
## The readability gap has not moved in thirty years
The problem is bigger than autism therapy. A [2025 systematic review of systematic reviews](https://pubmed.ncbi.nlm.nih.gov/40068244/) in Patient Education and Counseling pooled 24 reviews covering 29,424 written patient materials across 438 studies and found most exceeded the recommended sixth to eighth grade reading level, with no measurable improvement between 2001 and 2022. That is a default clinicians have to actively work against.
The audience is not reading at graduate level either. In the National Assessment of Adult Literacy, only 12 percent of U.S. adults scored proficient in health literacy ([Orthopaedic Nursing, 2009](https://pmc.ncbi.nlm.nih.gov/articles/PMC2668931/)). Those figures come from 2003 data, so treat the number as dated. The direction is not in dispute.
## Jargon fails parents at every education level
A [cognitive-interview study](https://pmc.ncbi.nlm.nih.gov/articles/PMC7376726/) found parents across all education and literacy levels stumbled over routine clinical terms. Small sample, prenatal rather than autism therapy, so read it as illustration rather than prevalence. A parent with a graduate degree can still be stopped cold by antecedent, mand, or latency to initiation.
Vocabulary is only part of it. A [systematic review of 79 publications](https://pmc.ncbi.nlm.nih.gov/articles/PMC6339273/) in Implementation Science found the top barrier to shared decision making in pediatrics was the emotional state of the parent and child, followed by power imbalance and, on the clinician side, not enough time. A family absorbing a hard week does not need more words. They need fewer, clearer ones.
## How to write parent-friendly therapy goals
1. **Write the clinical goal, then write the Tuesday version.** Keep the measurable goal for the chart and add one plain sentence underneath describing what the parent does and when.
2. **Name the routine, not the construct.** Getting shoes on before the bus travels further than improving task initiation.
3. **Move the percentages off the family copy.** Mastery criteria belong on your data sheet, not in the hands of a parent trying to get out the door.
4. **Show the goal instead of spelling it.** A short sequence of photos of the actual child communicates a target faster than a paragraph.
5. **Ask the parent to say it back.** If they cannot repeat the goal in their own words, the goal is not written yet.
## Share the measuring, not just the wording
A [2024 review in the Journal of Patient-Reported Outcomes](https://pmc.ncbi.nlm.nih.gov/articles/PMC10965877/) found that while 76 percent of goal-attainment trials set goals collaboratively with caregivers, it was clinicians, not caregivers, who almost always judged whether the goal had been met. Families get invited to choose the destination and then left out of reading the map. Our post on [a shared visual system across settings](/blog/shared-visual-system-home-clinic-school-provider-guide) goes deeper.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a goal you write in session shows up at home as a visual routine, in photos of the real child rather than clinical language.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so your goals travel home in a form parents can use.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The School Sleep Schedule Reset, Started Early Enough to Work
Published: 2026-07-11
URL: https://vizyplan.com/blog/school-sleep-schedule-reset-autism
Category: Parenting
Author: Justin Bowman
> A school sleep schedule reset does not happen the night before. Body clocks move about an hour a week, which means the work starts now, and the method is not the one most parents try first.
Right now bedtime is somewhere around eleven, mornings start when they start, and nobody is fighting about it because nobody has to. Then the first day of school lands and you are expected to produce a child who falls asleep at 8:30 and wakes at 6:45 cheerfully. A school sleep schedule reset is the least glamorous piece of back-to-school prep and the one that quietly decides how the first two weeks go. The catch is that body clocks do not take instructions. They move on their own timeline, and it is longer than most families leave room for.
## Sleep is already the harder battle in autistic homes
If this feels disproportionately hard at your house, that is not your imagination. The American Academy of Neurology's [practice guideline](https://pmc.ncbi.nlm.nih.gov/articles/PMC7238942/) reports that between 44 and 83 percent of autistic children and adolescents have co-occurring sleep problems, and that unlike in non-autistic children, those problems tend to persist into adolescence rather than fading with age.
The upside is that the payoff arrives fast and small. In a [randomized trial in Pediatrics](https://publications.aap.org/pediatrics/article/130/5/e1155/32518/Impact-of-Sleep-Extension-and-Restriction-on), roughly 27 extra minutes of sleep a night produced measurable improvement in emotional regulation and impulse control, rated by teachers blind to the condition. Losing about 54 minutes made things measurably worse. That study was in typically developing 7 to 11 year olds, so hold it loosely, but the dose is striking.
## A school sleep schedule reset moves about an hour a week
Here is the timing math nobody tells you. In a [randomized light-exposure trial](https://pmc.ncbi.nlm.nih.gov/articles/PMC7029701/) with adolescents, two and a half hours of morning bright light shifted the internal clock forward by about one hour across a weekend. That was the aggressive condition. A family needing a two-hour shift is realistically looking at two weeks of consistent work, not one determined Sunday night.
## The method is the opposite of what you would guess
1. **Fix the wake time first.** Morning is the lever. Hold wake time steady and let bedtime follow.
2. **Start bedtime at the time they actually fall asleep, even if it is late.** In bedtime fading, you match bedtime to real sleep onset rather than fighting for an aspirational hour.
3. **Move in 15-minute steps.** A [small study of six autistic preschoolers](https://pmc.ncbi.nlm.nih.gov/articles/PMC5861169/) moved bedtime 15 minutes earlier after nights the child fell asleep within 15 minutes, and later if it took longer. Sleep-onset latency dropped and nights hitting target rose sharply.
4. **Get bright light into the morning.** Breakfast near a window or a walk before the day starts does real work.
5. **Keep the wind-down visual and identical.** The same short sequence of pictures every night removes the negotiation.
Talk to your pediatrician before adding melatonin. The AAN guideline puts behavioral strategies first, and a [dose study](https://pmc.ncbi.nlm.nih.gov/articles/PMC3368078/) found most children responded at 1 to 3 mg.
## Make the routine something they can see
A wind-down works better when a child can see how many steps are left instead of asking. Our post on [the back-to-school routine reset](/blog/back-to-school-routine-autism-reset) goes deeper.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a bedtime routine runs on photos of your own child rather than on your voice repeating itself.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a bedtime routine that holds before school starts. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## A Substitute Teacher Plan That Autistic Students Can Trust
Published: 2026-07-10
URL: https://vizyplan.com/blog/substitute-teacher-plan-autistic-students
Category: For Schools
Author: Justin Bowman
> Your sub plan covers the curriculum. It probably does not cover the student for whom you are the routine. Here is what to leave behind so the day still holds together when you are gone.
The sub plan on your desk covers the lesson. Page 74, the worksheet packet, where the pencils live. For most of your class, that is plenty. For the autistic student in row two, the lesson was never the fragile part. You were. A substitute teacher plan that works for that student has to account for the fact that the most important thing changing today is not the content. It is the person.
## Unpredictability is an anxiety problem, not a preference
It is tempting to read a hard sub day as a student being inflexible. The research points somewhere more sympathetic. A [meta-analysis in Autism](https://pmc.ncbi.nlm.nih.gov/articles/PMC7539603/) pooling 12 studies and 656 participants found intolerance of uncertainty and anxiety are tightly linked in autistic people, with uncertainty accounting for roughly 38 percent of the variance in anxiety. An unfamiliar adult running an unfamiliar version of the day is not a minor inconvenience. An unfamiliar adult is a genuine anxiety load, layered on top of a school day that already costs more than it looks like it costs.
Sub days are not rare anymore either. Analysis of state records in four states found teacher absences running 20 to 50 percent above pre-pandemic levels ([Brookings, 2024](https://www.brookings.edu/articles/state-data-shows-k-12-teacher-absences-surged-post-pandemic/)).
One honest caveat: no published study has tested whether leaving a written profile for a substitute reduces problem behavior in autistic students. That study does not exist. What the research supports is the chain underneath it, and the plan below is that chain applied to the day you are out.
## What to leave in the substitute teacher plan
1. **Write a half-page profile, not a novel.** What calms this student, what escalates them, their early warning signs, and who to call.
2. **Name the non-negotiable routines.** If the visual schedule gets reviewed at 8:05 every morning, say so. Skipping it is the change that costs the most.
3. **Start with easy wins.** Running two to five requests the student reliably says yes to before a demanding one substantially increases compliance, confirmed at Tau-U of .87 in a [meta-analysis of single-case research](https://eric.ed.gov/?id=EJ1446812).
4. **Prime the change in advance.** A small [study of three children](https://ncaep.fpg.unc.edu/resource/the-use-of-video-priming-to-reduce-disruptive-transition-behavior-in-children-with-autism/) found previewing a transition reduced disruptive behavior, with gains carrying to transitions never previewed. A photo of the sub on the schedule is the classroom version.
5. **Keep the visual schedule running.** The student should be able to check what is next without asking a stranger.
## The structure should outlast the staffing
The day should belong to the student, not to whichever adult is at the front. When the schedule is visual and familiar, a new face becomes one change instead of every change at once. Our guide to [visual schedules in the classroom](/blog/visual-schedule-classroom-teacher-guide) goes further.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the same visual routine a student relies on at school keeps running at home, using photos of the real child.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so predictable structure follows the student home.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Meet Resyna: The Calm Button Your Family Has Been Waiting For
Published: 2026-07-09 · Updated: 2026-07-09
URL: https://vizyplan.com/blog/resyna-calm-button-vizyplan
Category: Announcements
Author: Justin Bowman
> Resyna is a gentle, adaptive calming sound built inside VizyPlan that listens to your heart rhythm and guides your family toward a calmer, steadier breath. Patent pending, and rolling out now for the hard moments.
You know the moment. The shoes are wrong. The room is too loud. The plan changed, and now everything is unraveling fast. Your child is spiraling toward a meltdown, you are running on empty, and every "just take a deep breath" feels impossibly far away. Meet Resyna, the calm button we built inside [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) for exactly that moment, for your child and for you. It is patent pending, and it is rolling out now.
## A calmer rhythm, without the fight
Resyna is a gentle, adaptive sound experience living right inside [VizyPlan](https://vizyplan.com). Press play and it does something quietly remarkable: it listens back. Soft, layered tones follow the listener's heart rhythm and slowly, invisibly, guide their breathing toward a calmer, steadier pace. As the body settles, the sound settles too, a soothing loop that meets the listener where they are and walks them somewhere softer.
No counting. No timers. No instructions to follow while everything already feels like too much. You just put on headphones, listen, and the calm comes to you.
Here is what we mean by the whole family: Resyna is there for whoever needs it in the moment, your child, you, or both of you together. Caregiver burnout is real, and you cannot pour from an empty cup. So whether it is calming your child through a hard afternoon or giving you a few quiet minutes on the couch after bedtime, the same gentle rhythm works the same for everyone. One calm button, for anyone in the house who needs it. For more on protecting your own reserves, see our guide to [caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children).
It works on the phone and pairs with Apple Watch, so relief is right there on the wrist, in the car, in the waiting room, in the middle of the hard afternoon.
## Why Resyna actually works
Here is the beautiful part: the science behind Resyna is not a gimmick. It is one of the most reliable calming tools we have, slow, paced breathing.
When we breathe slowly and evenly, around 4.5 to 6.5 breaths a minute, the body's stress and recovery systems come back into balance. Researchers track this through heart-rate variability (HRV) and call the steady, settled state coherence.
And the evidence is real. A meta-analysis of 31 studies, about 1,133 people in total, found that slow-paced breathing produced a clear, immediate rise in HRV ([Mindfulness, 2023](https://link.springer.com/article/10.1007/s12671-023-02294-2)), and a separate review recommended slow breathing as a simple, low-cost way to support the body's calming response ([Neuroscience and Biobehavioral Reviews, 2022](https://pubmed.ncbi.nlm.nih.gov/35623448/)). The benefit is not only physical. A meta-analysis of heart-rate-variability biofeedback, which trains the same slow breathing rhythm, found a large drop in self-reported stress and anxiety ([Psychological Medicine, 2017](https://www.cambridge.org/core/journals/psychological-medicine/article/effect-of-heart-rate-variability-biofeedback-training-on-stress-and-anxiety-a-metaanalysis/A839E9C968E54774DF5C8FB186764EF0)), and a review of breathwork trials found smaller but consistent reductions in stress and anxiety ([Scientific Reports, 2023](https://pmc.ncbi.nlm.nih.gov/articles/PMC9828383/)). Researchers describe the mood effect as small to moderate and still call for more high-quality studies, so we keep Resyna where it belongs: a gentle, everyday way to support calm and focus. The calmer, steadier breathing Resyna guides is the same rhythm those studies measured.
What this means for you: when everything feels like too much, Resyna gives your child and you a simple, calming way to slow down and reset. A softly pulsing particle sphere gives you something to breathe along with, so the right pace feels natural instead of forced. And a live calm score, a simple number the closed-loop engine builds from your own heart rhythm and breathing, quietly reflects how settled you are becoming, turning an invisible feeling into gentle, encouraging feedback. It is powered by a breathing technique that research consistently ties to less stress, wrapped in sound the whole family will actually want to press play on. If your family leans on other calming tools too, our post on [mindfulness and calm strategies](/blog/happy-place-mindfulness-neurodivergent-children) pairs well with Resyna.
## Honest about what Resyna is
We love this community too much to overpromise. Resyna is built to support relaxation for kids and grown-ups alike. It is not a medical device, and it does not diagnose, treat, or cure anything. We skip the flashy "brainwave" claims that research does not back ([binaural-beats review, 2024](https://www.tandfonline.com/doi/full/10.1080/18387357.2024.2374759); [PLOS One, 2023](https://journals.plos.org/plosone/article?id=10.1371/journal.pone.0286023)). What we give you instead is real: calming sound plus paced breathing, to help your child settle.
## Try Resyna in the next hard moment
Getting set up is simple.
1. **Install [VizyPlan](https://vizyplan.com).** When you install [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), the Resyna companion app appears automatically on your paired Apple Watch, with nothing separate to download.
2. **Tap Allow on the watch.** The first time you open it, tap Allow when the watch asks to share heart rate and health data. That is the piece that lets Resyna follow your heart rhythm and build your live calm score, so it is worth saying yes.
3. **No Apple Watch? Use the Calming Frequency card.** You can reach for the Calming Frequency card right inside [VizyPlan](https://vizyplan.com) instead, the same soothing, breath-pacing sound, no wearable needed. Support for more wearable devices is coming in the near future.
4. **Start slow.** Begin with 2 to 5 minutes and build from there.
5. **Pop in headphones.** Headphones are what makes the calming sound work. If anything feels off, just stop.
Resyna is rolling out in [VizyPlan](https://vizyplan.com) now. The next time the day tips sideways, you will have somewhere gentle to turn. Press play. Let your family breathe.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Meet Resyna and give your whole family a calm button for the hard moments. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
A gentle note on safe use: Resyna and [VizyPlan](https://vizyplan.com)'s Calming Frequency are wellness tools designed to support relaxation. They are not a medical device and are not medical advice. They do not diagnose, treat, cure, or prevent any condition, and they are not a substitute for care from a qualified professional. Start with just 2 to 5 minutes at a comfortable volume and build up gradually. If you feel any discomfort, dizziness, or unease, stop right away. If you are pregnant, or you or your child has epilepsy, a seizure disorder, or a heart condition, please check with your doctor before use. Do not operate heavy machinery after listening. Use of the heart-guided calm score requires a paired Apple Watch with heart-rate and health sharing enabled. The calm score is a relaxation-feedback indicator only. It is not a diagnosis, a fitness metric, or a measure of your health. Resyna does not monitor for, detect, or alert you to arrhythmias, heart conditions, or any other medical issue, and it should never be relied on for that purpose. If you have any health concern, contact a qualified medical professional.
---
## One Shared Visual System Across Home, Clinic, and School
Published: 2026-07-07
URL: https://vizyplan.com/blog/shared-visual-system-home-clinic-school-provider-guide
Category: For Providers
Author: Justin Bowman
> A child with autism often runs three different systems before lunch. The clinic uses one set of picture cards, the classroom uses another, and home uses whatever the family cobbled together. A shared visual system is the mechanism that lets a skill generalize.
A child with autism often runs three different systems before lunch. The clinic uses one set of picture cards, the classroom uses another, and home uses whatever the family cobbled together. Each setting is doing good work in isolation, and the child pays the tax at every border crossing. A shared visual system across home, clinic, and school is not a nicety. It is the mechanism that lets a skill you teach on Tuesday show up everywhere else by Friday.
## Why fragmentation costs more than anyone bills for
Siloed care quietly erodes the gains each discipline works to produce. A [standards paper in Behavior Analysis in Practice](https://pmc.ncbi.nlm.nih.gov/articles/PMC8586309/) warns that when SLP, OT, and behavior teams do not truly collaborate, the result is an "eclectic buffet approach" of disconnected interventions that produces limited treatment gains and erodes family trust. The same paper notes that 65 percent of sentinel events causing serious harm in healthcare trace back to communication failures. A child crossing three settings with three different visual languages is absorbing that same communication gap in miniature, every single day.
## Consistency is the active ingredient
The reason a shared visual system works is not branding; it is stimulus control. Visual supports are a [recognized evidence-based practice](https://files.eric.ed.gov/fulltext/ED595398.pdf) for autism, and their power grows when the same supports appear across environments, because each setting reinforces the same cue instead of teaching a new one. When behavior analysts, SLPs, and OTs coordinate goals and use consistent strategies, clients show greater generalization across settings. Consistency is what turns three good sessions into one durable skill.
## How to build one shared system
You do not need a shared employer to run a shared system. You need a shared vocabulary and a way to keep it in sync.
1. **Agree on a common visual vocabulary.** Use the same symbols and wording for core routines so "all done" or "first, then" looks identical in every room.
2. **Use the same core supports in every setting.** Pick a small set of anchor supports and commit to them across clinic, classroom, and home rather than reinventing per site.
3. **Put the family at the center.** ASHA's [autism practice portal](https://www.asha.org/practice-portal/clinical-topics/autism/) frames caregiver-mediated intervention, where the clinician coaches the caregiver to run supports in natural settings, as core to care.
4. **Share notes across disciplines.** A short shared summary of active targets and working prompts keeps everyone pointed the same direction.
5. **Let one tool travel with the child.** Choose a single system that follows the child between settings so no one is rebuilding from scratch.
## The tool that crosses every border
The hardest part of a shared system is keeping it in sync as the child moves. A visual routine that lives on the family's phone solves that by traveling with the child, so the clinic, the teacher, and the parent are all looking at the same steps and the same photos. Our posts on [interdisciplinary collaboration](/blog/interdisciplinary-collaboration-ot-slp-aba-shared-plan) and [therapy carryover across the school handoff](/blog/therapy-carryover-school-handoff-provider-guide) go deeper on aligning a team around one plan.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist for exactly this problem. The routine lives on the family's phone with photos of the real child, so the same visual system shows up at home, in your clinic, and in the classroom.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give every setting one shared visual system instead of three. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Sensory-Friendly Classroom: Low-Cost Fixes Any Teacher Can Make
Published: 2026-07-06
URL: https://vizyplan.com/blog/sensory-friendly-classroom-setup-teachers
Category: For Schools
Author: Justin Bowman
> You do not need a renovation budget to build a sensory-friendly classroom. Some of the changes with the strongest evidence behind them cost nothing but a rearranged shelf and a few minutes of planning.
You do not need a renovation budget to build a sensory-friendly classroom. Some of the changes with the strongest evidence behind them cost nothing but a rearranged shelf and a few minutes of planning. Sensory reactivity is not a quirk in autistic students; it is a core diagnostic feature, and for many children it is the single biggest barrier between them and the lesson you worked hard to plan.
## Why sensory comes before learning
Sensory reactivity is written into the diagnosis itself. The DSM-5 lists hyper- or hyporeactivity to sensory input as a [core criterion for autism](https://www.autismspeaks.org/autism-diagnostic-criteria-dsm-5), covering adverse responses to sounds and textures. The prevalence in classrooms is high: a [population-based study](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2021.695825/full) found extreme sensory symptoms affect the large majority of young autistic children, and those difficulties are tied to behaviors that interfere with learning and social interaction. A dysregulated nervous system cannot attend to phonics, so the sensory environment is not a side issue; it comes first.
## The fixes that cost the least and matter the most
Small environmental changes carry a lot of the effect. Start with the input that research flags as the worst offender and work down.
1. **Turn down the noise.** The same review found auditory stimuli have the greatest negative impact on engagement for students with autism, and classroom noise correlates with more repetitive behavior. Add felt pads under chair legs, tennis balls on stools, and a visual quiet signal.
2. **Clear the visual clutter.** Classrooms with a high amount of background visual display were linked to poorer learning scores for all students, and especially for students with autism. Pare back the walls near instruction.
3. **Fix the lighting.** Evidence favors halogen or natural light over flickering fluorescents, which some autistic students perceive as buzzing and strobing. Seat sensitive students away from the noisiest fixtures.
4. **Offer a way to move.** A [study of alternative seating](https://link.springer.com/article/10.1007/s10803-019-04283-8) found stability balls improved in-seat behavior and engagement for young autistic students. Wobble cushions and standing spots do similar work for far less than new furniture.
5. **Build a retreat corner.** A small, calm zone with headphones and a weighted lap pad gives a student a place to regulate before overwhelm turns into a meltdown.
## Loop in your OT
The occupational therapist on your team is the fastest route to getting these fixes right for a specific child. Sensory needs are individual, and what soothes one student can overload another, so an OT's read on a child's profile turns a generic checklist into a targeted plan. A two-line email asking which accommodations fit a particular student is often all it takes.
## Consistency helps it stick
A regulated classroom works even better when the calm does not end at dismissal. When a child experiences the same predictable supports at school and at home, the nervous system gets a consistent message instead of a daily reset. Our posts on [sensory diet activities at home](/blog/sensory-diet-home-activities-autism-adhd) and [visual schedules in the classroom](/blog/visual-schedule-classroom-teacher-guide) show how to keep the structure consistent across settings.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the predictable, visual structure that calms a student at school can carry into the home, using photos of the real child.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the calm structure follows the student home.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## 504 Plan vs IEP: The Question Families Keep Asking You
Published: 2026-07-05
URL: https://vizyplan.com/blog/504-vs-iep-provider-guide
Category: For Providers
Author: Justin Bowman
> It comes up in the middle of a session, between a goal update and a scheduling question. Does my kid need a 504 or an IEP? Providers get asked the 504 plan vs IEP question constantly, and families trust your answer more than a pamphlet.
It comes up in the middle of a session, between a goal update and a scheduling question. Does my kid need a 504 or an IEP? Providers get asked the 504 plan vs IEP question constantly, and families trust your answer more than any pamphlet. You are not a special education attorney, and you should not pretend to be one, but you can explain the landscape accurately enough that a parent walks into the school meeting oriented instead of lost.
## Two different laws, two different jobs
The whole 504 plan vs IEP distinction starts with the fact that they come from two different laws. An IEP is governed by IDEA, a federal special-education law, while a 504 plan comes from Section 504 of the Rehabilitation Act of 1973, a civil-rights law that prohibits disability discrimination. As [Understood.org lays out](https://www.understood.org/en/articles/the-difference-between-ieps-and-504-plans), an IEP delivers specially designed instruction, and a 504 plan removes barriers so a student can access the standard curriculum. Instruction versus access is the cleanest way to hold the difference in your head.
## Who qualifies for each
Eligibility is the other big divide, and it runs in an intuitive direction. The [US Department of Education](https://www.ed.gov/laws-and-policy/civil-rights-laws/disability-discrimination/frequently-asked-questions-section-504-free-appropriate-public-education-fape) sets a broader bar for a 504 plan: a student must have a physical or mental impairment that substantially limits a major life activity, such as learning or concentrating. An IEP is narrower. The student must fall into one of IDEA's 13 disability categories, autism among them, and need specially designed instruction because the disability adversely affects educational performance. IDEA [defines that instruction](https://sites.ed.gov/idea/regs/b/a/300.39) as adapting the content, methodology, or delivery to the child's needs, which a 504 plan does not provide.
## How to explain it without overstepping
Your job is to orient, not to rule on eligibility. A calm, accurate framing does more good than a confident guess.
1. **Name the two laws plainly.** Tell the family an IEP comes from IDEA and a 504 comes from the Rehabilitation Act, so they hear that these are different tracks.
2. **Frame it as instruction versus access.** An IEP changes how a child is taught; a 504 changes the conditions so they can access what everyone else gets.
3. **Be honest about process differences.** IEPs require written consent to evaluate, measurable annual goals, progress monitoring, and stronger dispute-resolution rights. A 504 plan is more flexible and often lighter on formal documentation.
4. **Note that an IEP can satisfy 504.** As the Department of Education states, "one way to meet Section 504 requirements for a free appropriate public education is to implement an IEP," so an IDEA-eligible student does not need a separate 504.
5. **Route them to primary sources.** Point families to the school's special-education team and the [Office for Civil Rights 504 resource guide](https://www.ed.gov/sites/ed/files/about/offices/list/ocr/docs/504-resource-guide-201612.pdf) rather than offering a legal opinion.
## Where your clinical notes fit
The most useful thing you can hand a family is not an eligibility verdict; it is documentation of functional impact. Clear notes on how a child's challenges show up in daily tasks give the school team concrete evidence to work from, whichever plan they pursue. Our posts on [collaborating with providers for IEP meetings](/blog/provider-collaboration-iep-preparation) and the parent-facing [504 plan vs IEP guide](/blog/504-plan-vs-iep-neurodivergent-child) are worth sharing so families arrive prepared.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist, and the visual routines it creates give families a concrete record of what supports actually work, useful evidence for either kind of plan.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give your families a clear picture of what supports work before the school meeting. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Fourth of July With Autism: A Sensory Survival Guide
Published: 2026-07-04
URL: https://vizyplan.com/blog/fourth-of-july-autism-sensory-guide
Category: Parenting
Author: Justin Bowman
> Fireworks get all the attention, but for many families the Fourth of July with autism is a whole weekend of hard, not one loud night. Crowds, cookouts, disrupted routines, late bedtimes, and open water all stack on top of each other.
Fireworks get all the attention, but for many families the Fourth of July with autism is a whole weekend of hard, not one loud night. Crowds, cookouts, disrupted routines, late bedtimes, and open water all stack on top of each other. Planning for the finale alone misses most of what actually overwhelms a child, so it helps to think in terms of the entire weekend.
## Why the whole weekend is hard, not just the finale
Sound is the obvious trigger, and the numbers are striking. A [meta-analysis in Ear and Hearing](https://pmc.ncbi.nlm.nih.gov/articles/PMC8349927/) found decreased sound tolerance affects roughly 41 percent of autistic people currently and 61 percent across their lifetime, far above the general population. A separate [study of more than 4,000 people with autism](https://pubmed.ncbi.nlm.nih.gov/33837888/) found 60 percent had current auditory over-responsivity. But noise is only part of it. A [population-based study of over 25,000 autistic children](https://pmc.ncbi.nlm.nih.gov/articles/PMC9067163/) found 74 percent had documented sensory features, spanning light, texture, smell, and touch. Add a blown-up routine and a late bedtime, and the weekend reads as a siege long before the first firework.
## A whole-weekend plan
You cannot control a cookout, but you can control your child's exits, inputs, and expectations. Build the plan before you arrive.
1. **Pack a sensory kit.** Noise-cancelling headphones or earplugs, sunglasses, a favorite comfort item, and a snack you know your child will eat.
2. **Scout the exits first.** Autism Speaks suggests watching a parade from the very beginning or end where it is less crowded, and viewing fireworks from inside the car, where the glass muffles the boom.
3. **Preview the noise.** Play firework videos in the days before, starting quiet and slowly raising the volume so the sound is familiar, not ambushing.
4. **Build a safe space.** Set up a defined spot with your child's own chair or blanket, and agree on a code word or a visual break card they can use the second they need out.
5. **Watch the water and the crowd.** The [CDC reports](https://www.cdc.gov/child-development/disability-safety/wandering.html) that about half of autistic children wander, and one in four go missing long enough to raise real danger, most often near traffic or water. Assign one adult to shadow your child at all times.
## Safety is the part no one puts on the invitation
Elopement risk is highest in exactly the settings a holiday weekend creates: unfamiliar yards, big crowds, and open water at a lake or pool. Decide in advance who is watching your child during the chaos of arrival, food, and fireworks, when supervision is easiest to lose. A wristband with your phone number and a quick photo of what your child is wearing that day are two-minute steps that matter.
## Let the day show itself first
A child who has already seen the plan walks in with less to fear. Preview the day with a visual schedule or a short social story so the sequence of drive, food, wait, fireworks, home is known before it happens. Our [fireworks preparation guide](/blog/fireworks-and-autism-parent-prep-guide) goes deeper on the noise piece, and our post on [creating a happy place](/blog/happy-place-mindfulness-neurodivergent-children) helps with the reset when it all gets to be too much.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad whose son did better when the day showed itself in advance instead of arriving all at once.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Preview the whole holiday weekend so it arrives as an expectation, not an ambush. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The One-Page Profile: What to Send Your Child’s New Teacher
Published: 2026-07-03
URL: https://vizyplan.com/blog/one-page-profile-autism-new-teacher
Category: Parenting
Author: Justin Bowman
> Your child’s new teacher will meet a room full of students in the first week and read a stack of files an inch thick. A one-page profile is how you make sure the few things that matter most about your child rise to the top before the first hard moment.
Your child's new teacher will meet a room full of students in the first week and read a stack of files an inch thick. A one-page profile is how you make sure the few things that matter most about your child rise to the top before the first hard moment. It is not the IEP. It is one page, written by the person who knows your child best, that a busy teacher can absorb in ninety seconds.
## What a one-page profile is
A one-page profile came out of person-centered planning, developed by Helen Sanderson Associates after they noticed teachers rarely had time to absorb long plans but urgently needed to understand a student quickly. As [Special Needs Jungle describes](https://www.specialneedsjungle.com/one-page-profile-can-improve-special-needs-childs-life/), the page has three parts: what people appreciate about the child, what matters to the child from their own perspective, and how best to support them. In one example, a boy's anxiety dropped simply because every teacher now knew to seat him near the door. The information already existed; the profile is what got it in front of the right people.
## What to put on the page
Keep it short, specific, and honest. A teacher can act on five clear lines far more easily than five paragraphs.
1. **Three genuine strengths.** Understood.org's free ["3x3 card"](https://www.understood.org/en/articles/download-3x3-card-to-help-teachers-get-to-know-your-child) suggests three strengths, three challenges, and three strategies. Lead with what your child is good at.
2. **What overwhelms my child.** Name the real triggers, whether it is unexpected noise, being rushed, or a change in plan.
3. **What actually helps.** List the specific moves that work, like a two-minute warning before transitions or a quiet spot to reset.
4. **How my child communicates.** Explain what a meltdown, a shutdown, or a flat "no" is really telling the adult in the room.
5. **One thing that will make the first week easier.** Give the teacher a single high-value action they can take on day one.
## Why one page beats the whole file
Small, specific communication is not a courtesy; it changes outcomes. A [meta-analysis of 77 family-school partnership studies](https://link.springer.com/article/10.1007/s10648-019-09509-w) found these partnerships significantly improved children's academic and social-emotional functioning, with two-way communication among the most effective ingredients. A strengths-based page also reframes how staff see your child. As Understood.org notes, person-centered documentation helps a team "see the child as a whole person," not a list of deficits. That shift, made before any conflict, is worth more than any single accommodation.
## Make it visual, and make it a two-way door
Send the profile before the year starts, and invite the teacher to add what they notice. A profile that includes a photo of your child using their home routine gives the teacher an instant picture of what consistency looks like. Our guides to [preparing for the IEP meeting](/blog/iep-meeting-preparation-guide-parents) and easing [first day of school anxiety](/blog/first-day-of-school-anxiety-autism) pair naturally with a strong one-page profile.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist, and the visual routine it creates gives you a ready-made picture of what works for your child to hand a new teacher.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the visual routine that shows a new teacher what works. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Paraprofessional Support Playbook: Beyond Prompt Dependency
Published: 2026-07-02
URL: https://vizyplan.com/blog/paraprofessional-autism-support-prompt-dependency
Category: For Schools
Author: Justin Bowman
> Paraprofessionals may be the most important adults in an inclusive classroom that almost no one writes for. Strong paraprofessional support is a real skill, and the research is surprisingly clear about the line between helping and hovering.
Paraprofessionals may be the most important adults in an inclusive classroom that almost no one writes for. If you are a one-to-one para supporting an autistic student, you hold enormous influence over whether that child grows more independent or more dependent this year. Strong paraprofessional support is a real skill, and the research is surprisingly clear about the line between helping and hovering.
## The hidden risk of sitting too close
The instinct to stay close and help constantly can quietly backfire. Michael Giangreco's classic study, memorably titled ["Helping or Hovering?"](https://journals.sagepub.com/doi/10.1177/001440299706400101), documented eight categories of concern when an adult stays in a student's immediate proximity, including separation from classmates, dependence on adults, and interference with peer interaction. Later work by [Giangreco and Broer](https://journals.sagepub.com/doi/10.1177/10883576050200010201) went further, describing heavy reliance on one-to-one paraprofessionals as a questionable default that can undercut the very inclusion it is meant to support.
The specific trap is prompt dependency. A student becomes prompt dependent when a correct response only shows up after an adult cue, even for a skill the child has already mastered. The help stops being a bridge to independence and becomes a permanent crutch.
## What great paraprofessional support looks like
The goal is to become less necessary over time, on purpose. That reframe changes every decision you make in a school day.
1. **Start with the least help that works.** Try a gesture or a pointed look before a verbal cue, and a verbal cue before hands-on help. Least-to-most prompting keeps the student doing as much as they can.
2. **Build in wait time.** Count silently before you step in. Many students answer or start the task if the adult simply pauses instead of rescuing.
3. **Step back physically.** Sit a seat away, or across the group, so the student's default is to check the schedule and the teacher, not your face.
4. **Route through peers and the teacher.** Redirect questions to the classroom teacher and set up peer partners so the student's support network is not one adult.
5. **Fade on purpose, and track it.** Decide which prompt you are removing next and record whether independence holds. Fading that is not measured tends not to happen.
## Independence is the goal, not compliance
A quiet, compliant student sitting beside a para is not the same as a student who is learning to run the day. Tools exist to check whether a one-to-one is still needed or whether support can shift toward natural supports and peer engagement. The honest question is not "is the student behaving," but "could the student do more of this without me."
## Give the student something to follow instead of a person
The fastest way to fade yourself is to give the student a reliable thing to look at instead of a reliable adult to lean on. When a child checks a visual schedule for the next step, the schedule becomes the prompt, and the schedule does not create dependence the way a hovering adult does. Our starter guide to [visual schedules in the classroom](/blog/visual-schedule-classroom-teacher-guide) and our post on [building independence with visual supports](/blog/building-independence-visual-supports) show how to hand the routine to the student.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so a student can follow a picture of the next step instead of waiting for an adult to deliver it, at school and at home.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the student follows a schedule, not a person.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Therapy Carryover That Survives the School Handoff
Published: 2026-07-01
URL: https://vizyplan.com/blog/therapy-carryover-school-handoff-provider-guide
Category: For Providers
Author: Justin Bowman
> A child nails a skill in your session, and by the time it needs to show up in a classroom or a new provider’s room, it has vanished. Therapy carryover is not a bonus that happens on its own. It is a separate skill you have to plan for, and the clinic-to-school handoff is where it most often falls apart.
Every provider has watched it happen. A child nails a skill in your session, and by the time it needs to show up in a classroom or a new provider's room, it has vanished. Therapy carryover is not a bonus that happens on its own after a good session. It is a separate skill you have to plan for, and the clinic-to-school handoff is where it most often falls apart.
## Why carryover fails at the handoff
Carryover fails because generalization is usually assumed rather than engineered. In their landmark review, [Stokes and Baer](https://pubmed.ncbi.nlm.nih.gov/16795561/) argued that generalization "has remained a passive concept almost devoid of a technology," and coined the phrase "train and hope" for the common practice of teaching a skill and simply hoping it transfers. Hope is not a plan.
Generalization is also directional and uneven. A [multi-site study of 248 autistic children](https://pmc.ncbi.nlm.nih.gov/articles/PMC12167233/) found social communication skills generalized more strongly from home to school than the reverse, which means the setting a skill is taught in shapes where it shows up. And the field still under-measures the problem. A [social competence study](https://pmc.ncbi.nlm.nih.gov/articles/PMC3420545/) called generalization "the one persistent challenge," noting how few intervention studies even report whether gains transferred.
## What the research says actually moves carryover
Stokes and Baer did not just name the problem; they laid out strategies that still hold up. Put them to work at the handoff.
1. **Program common stimuli.** Use the same visual supports, cues, and vocabulary across settings so the skill has a familiar anchor in the classroom.
2. **Train with sufficient exemplars.** Practice the target across enough people, materials, and contexts that it does not stay welded to your therapy room.
3. **Recruit the natural environment.** Caregivers are the vehicle. A [meta-analysis of 30 randomized trials](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2021.773604/full) found parent-mediated intervention produced clinically relevant gains in adaptive functioning.
4. **Write goals the receiving adult can run.** A goal only a clinician can interpret does not survive a handoff to a teacher or a new provider.
5. **Plan for the summer gap.** Extended School Year exists precisely because breaks in instruction risk regression and slow recoupment, as [Autism Speaks explains](https://www.autismspeaks.org/blog/seven-things-know-about-esy).
## The handoff document nobody writes
Most of the loss happens in the silence between settings. The clinic knows what works, the school inherits a child and a stack of paperwork, and the connective tissue never gets written down. A one-page summary of the child's active targets, the exact prompts that work, and the visual supports in use closes more of the gap than another hour of direct therapy. Our posts on the [speech therapy carryover gap](/blog/speech-therapy-carryover-gap-slp-guide) and the [in-clinic to home generalization gap](/blog/in-clinic-to-home-generalization-gap-provider-guide) go deeper on building that bridge.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist for exactly this gap. The routine lives on the family's phone with photos of the real child, so the supports you design travel with them into every setting. Your clinical work stays yours; the carryover finally has a vehicle.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families could run between the clinic and the classroom. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Back to School Routine Reset: Start Before Day One
Published: 2026-06-30
URL: https://vizyplan.com/blog/back-to-school-routine-autism-reset
Category: Daily Routines
Author: Justin Bowman
> The calendar still says summer, but a back to school routine reset is the kindest gift you can give your neurodivergent child before the first bell. Starting the reset early, and gently, changes how the whole first month goes.
The calendar still says summer, but a back to school routine is the kindest gift you can give your neurodivergent child before the first bell. Summer loosens everything: later bedtimes, slow mornings, no schedule to speak of. For a child who leans on predictability to feel safe, being dropped back into a rigid school day cold can trigger weeks of anxiety, meltdowns, and lost sleep. Starting the reset early, and gently, changes how the whole first month goes.
## Why the summer-to-school jump is so hard
Predictability is not a preference for many autistic and ADHD kids; it is how their nervous system finds safety. Summer quietly dismantles the scaffolding, and the sudden return to a structured day can feel like a shock. Sleep is often the first casualty. A [review in Pediatrics](https://pmc.ncbi.nlm.nih.gov/articles/PMC5621998/) reports that 50 to 80 percent of autistic children experience sleep difficulties, compared with about 25 percent of their peers, so a summer of drifting bedtimes leaves less margin than most families realize. If your child struggled at the start of last summer too, our post on the [summer routine cliff](/blog/summer-break-autistic-kids-routine-cliff) explains why the transition cuts both directions.
## Start the back to school routine reset two weeks out
The single biggest lever is time. Autism Speaks recommends shifting to the school-night sleep schedule about two weeks before day one, noting the first couple of nights are hard and then get easier.
1. **Move bedtime earlier in small steps.** Pull bedtime back fifteen minutes every few nights rather than lurching to the school time overnight.
2. **Rebuild the morning sequence.** Practice the real order of the school-day morning, wake, dress, eat, shoes, out the door, so it is muscle memory before it counts.
3. **Tour the school on the real schedule.** Visit at the time of day your child will actually be there, and walk the route from drop-off to the classroom.
4. **Use a countdown calendar.** Mark the days to the first day so the change arrives as an expectation, not an ambush.
5. **Preview with a social story.** The [Child Mind Institute](https://childmind.org/article/how-can-we-help-kids-with-transitions/) notes that previews, countdowns, and social stories all ease transitions for kids who struggle with change.
## Keep your own anxiety in check
Your calm is part of the plan. As Autism Speaks puts it, "All children can pick up on their parents' anxiety. If you can keep yours in check, it will help your child stay more calm." That is not a guilt trip; it is a reminder that the reset works better when you model the steadiness you are asking your child to find.
## Let the schedule carry the change
The families who transition most smoothly rarely rely on reminders alone. They hand the routine to something the child can see. When the morning sequence lives in pictures your child can follow, you spend less of the first week narrating and negotiating, and more of it connecting. Our guides to [first day of school anxiety](/blog/first-day-of-school-anxiety-autism) and [visual schedules](/blog/visual-schedules-for-autism) walk through how to build that structure.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad whose son did better when the day showed itself instead of being rushed through. The routine carries the next step, so the reset feels less like a fight.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Rebuild the school routine before day one, one visible step at a time. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Visual Schedule in the Classroom: A Teacher’s Starter Guide
Published: 2026-06-29
URL: https://vizyplan.com/blog/visual-schedule-classroom-teacher-guide
Category: For Schools
Author: Justin Bowman
> Ask a special education teacher where the hard moments hide and few point to the lessons. The friction lives in the seams between activities. A visual schedule in the classroom is one of the most researched tools for smoothing those transitions, and it costs almost nothing to start.
Ask a special education teacher where the hard moments hide and few will point to the lessons. The friction lives in the seams: cleanup to circle, circle to centers, the hallway to specials. A visual schedule in the classroom is one of the most researched tools for smoothing those seams, and it costs almost nothing to start. For many autistic and ADHD students, seeing the day laid out is the difference between a transition that flows and one that ends in a standoff.
## Why a visual schedule in the classroom works
A visual schedule works because it moves the day out of a child's head and onto the wall. Autistic students often carry a heavy cognitive load just tracking what comes next, and holding that sequence in working memory leaves less room to actually learn. When the next step is visible, the brain can let go of it.
The evidence base is strong, not anecdotal. The 2020 review from the [National Clearinghouse on Autism Evidence and Practice](https://ncaep.fpg.unc.edu/) classifies visual supports as a focused evidence-based practice, backed by more than one hundred single-case studies across ages 0 to 22. The [IRIS Center at Vanderbilt](https://iris.peabody.vanderbilt.edu/module/asd1/cresource/q2/p06/) puts the mechanism plainly: "Structure is fundamental to helping autistic people thrive. Maintaining a structured classroom environment can help decrease students' anxiety that, in turn, can make students more receptive to learning."
## How to set up a classroom visual schedule
You can build a usable schedule in an afternoon. Keep it concrete and keep it in the child's line of sight.
1. **Photograph the real routine.** Use actual pictures of your room, your carpet, your cafeteria. Recognizable images beat generic clip art for a student who reads the world literally.
2. **Sequence the whole day.** Lay the steps out top to bottom or left to right so the student can see the arc from arrival to dismissal, not just the next task.
3. **Make it interactive.** Let the student move a card, flip a tab, or check off each step. The physical act of marking a step done is part of what builds the habit.
4. **Teach the schedule explicitly.** Do not assume a child knows how to use it. Model checking the schedule, then prompt it, then fade your prompts as the routine sticks.
5. **Preview the transition before it happens.** Point to the next card a minute or two out. The warning is what turns a surprise into an expectation.
## A visual schedule is not a standalone fix
A visual schedule in the classroom earns its reputation when it is part of a plan, not when it hangs on the wall alone. In a well-known [study in the Journal of Applied Behavior Analysis](https://pmc.ncbi.nlm.nih.gov/articles/PMC2695333/), visual schedules by themselves did not reduce transition-related problem behavior for two young boys with autism. Adding reinforcement for smooth transitions did, producing reductions of 76 and 89 percent. The takeaway for educators is simple: pair the schedule with clear reinforcement and a behavior plan, and expect the schedule to do its best work as one piece of a larger structure. Our guide to [transition strategies for autistic children](/blog/transition-strategies-autism) covers the reinforcement side in more depth.
## When the schedule follows the child home
The students who make the fastest progress tend to see the same kind of visual support everywhere they go. A schedule that lives only in your classroom resets every afternoon at dismissal. When the same predictable, picture-based system carries into the evening and the morning, the routine compounds instead of restarting. Our overview of [how visual schedules help children with autism thrive](/blog/visual-schedules-for-autism) and our guide to [first-then boards](/blog/first-then-boards-guide) are worth sharing with families who want to keep the momentum going at home.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist so the visual system a child trusts at school can follow them home, using photos of the real child in the real house.
---
**[Share VizyPlan with your families](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so the classroom routine follows the student home.** The 7-day free trial lets a family try it first. Just $6.99/month after, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Explore VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Polaris Manuscript: 16 Years and a First Teaser
Published: 2026-06-28
URL: https://vizyplan.com/blog/polaris-manuscript-16-year-journey
Category: Founder Story
Author: Justin Bowman
> After sixteen years and countless revisions, the Polaris manuscript is finally ready. Watch the very first teaser, and follow the journey as I look for the right publishing home.
Today I get to share something that has lived in me for more than half my life. The Polaris manuscript is finally ready, and the teaser above is the first glimpse I have ever shown the world. I started writing Polaris in July 2010, and sixteen years, countless revisions, and more life changes than I can list later, the story has finally found its shape.
## Where the Polaris Journey Started
In July 2010 I wrote the first pages with no idea the book would take sixteen years to finish. Back then Polaris was a handful of scenes and a feeling I could not shake. I was a different person, in a different season of life, and the manuscript grew up right alongside me. Some chapters came in seasons of joy. Others were written through grief, through fatherhood, through building a company, and through the kind of quiet life changes that slowly rewrite what a story is really about.
## Why the Polaris Manuscript Took Sixteen Years
The honest answer is that the Polaris manuscript needed me to become someone who could finish it. I revised the opening more times than I can count. I cut characters I loved, rebuilt the ending twice, and set the whole thing down for months when life asked for my full attention. Every return taught me something. A story started by a twenty-something and a story finished by a father and founder are not the same story, and I am grateful Polaris waited for the better version of me.
The journey itself has been the gift. Long before any publisher entered the picture, the simple act of returning to these pages again and again shaped how I see persistence, patience, and the slow work of making something real. That same belief, that meaningful things are worth the long road, is the heart behind [VizyPlan](https://vizyplan.com) and everything else I build.
## Where the Polaris Manuscript Goes Next
Right now I am looking for the right publishing company. Not the fastest deal, but the right home, a partner who believes in this story the way I have believed in it for sixteen years. I am taking my time, talking with thoughtful people, and trusting that the same patience that finished the book will help me place it well. If you are a publisher, or you simply love a good story and want to follow along, I would love for you to [reach out](/contact) and come along on this journey.
Want the whole story now? You can read the [full Polaris synopsis](/polaris), spoilers and all.
The teaser is only the beginning. Thank you for being here for it.
---
**Want to follow the Polaris journey?** [Reach out here](/contact) to connect, and watch this space as the search for the right publisher unfolds.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by the same autism dad behind Polaris, on the belief that meaningful things are worth the long road. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Zones of Regulation at Home: A Parent Guide to Big Feelings
Published: 2026-06-27
URL: https://vizyplan.com/blog/zones-of-regulation-home-autism-parents
Category: Parenting
Author: Justin Bowman
> A warm, parent-friendly look at using a zones of regulation color framework at home so your child can name and manage emotions without shame.
Many parents first hear about the zones of regulation when a teacher or therapist mentions color coded feelings, and the idea sticks because it is simple. The zones of regulation approach sorts emotions into four colors so a child can point to how a body feels instead of finding the perfect words. Blue covers low energy states like tired or sad. Green covers calm and ready to learn. Yellow covers heightened feelings like silly, worried, or frustrated. Red covers intense feelings like anger or panic. The framework was created by educator Leah Kuypers, and many families use the general color idea at home in their own gentle way.
## Why a Color Framework Helps Neurodivergent Kids
Naming a feeling is hard work, especially for autistic and ADHD children who may feel emotions strongly before they can label them. A color gives a child a handhold. Pointing to yellow is easier than explaining frustration in a hard moment. The zones of regulation framework also lowers shame, because a color is just information, not a verdict on character.
No zone is a bad zone. Blue is not wrong, and red is not naughty. Every color is a normal part of being human, and the goal is recognizing and supporting feelings, not suppressing them. A child who learns that red is allowed will trust you sooner when red shows up. This builds on [co-regulation before self-regulation](/blog/co-regulation-before-self-regulation-neurodivergent-children), because your calm presence teaches the nervous system what safe feels like.
## Using Zones of Regulation at Home
Try these steps to bring the zones of regulation into daily family life.
1. **Name the colors together.** Talk about all four zones during a calm moment, not mid meltdown, so the words are familiar later.
2. **Check in often.** Ask "what color are you right now" at breakfast and bedtime so naming feelings becomes ordinary.
3. **Match a tool to each zone.** A yellow body might need movement, while a red body might need a quiet space and deep breaths.
4. **Stay neutral about every color.** Greet blue and red with the same warmth you give green, so no feeling feels forbidden.
Knowing a feeling and acting on a plan are different skills, and the gap between them often lives in [executive function](/blog/executive-function-autism-adhd-invisible-struggle). Visuals close that gap. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) offers visual emotion check-ins and calm-down routines, so your child can spot a color and walk through a soothing sequence without needing you to script every step.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give your child a calm, visual way to name and manage big feelings. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Trauma-Informed Care in Pediatric Therapy: A Provider Guide
Published: 2026-06-26
URL: https://vizyplan.com/blog/trauma-informed-care-pediatric-therapy-provider-guide
Category: For Providers
Author: Justin Bowman
> Trauma-informed care helps autistic and neurodivergent clients feel safe, builds trust, and treats dysregulation as communication. Here is how to apply it in everyday sessions.
Trauma-informed care is a clinical approach that recognizes how past stress, medical experiences, and a history of being misunderstood can shape how a child shows up in therapy. For autistic and neurodivergent clients, trauma-informed care means building safety, choice, and trust into every interaction rather than expecting compliance. The widely used framework rests on a few well established principles: safety, trustworthiness, choice, collaboration, and empowerment. None of these require a documented trauma history to matter. They simply make sessions kinder and more effective.
## Why Predictability and Safety Come First
Predictability is one of the most powerful tools in trauma-informed care. When a child knows what is coming next, the nervous system can settle, and learning becomes possible. Surprise transitions, sudden demands, and unfamiliar routines can read as threats to a dysregulated child. Recognizing dysregulation as communication, rather than as defiance, changes how a provider responds. A meltdown is information about an unmet need, not a behavior to extinguish.
A simple visual preview can lower that threat. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) gives clients a clear, visual look at what the session holds, so predictability and safety are built in before the first demand arrives. Visual previews reduce surprise and give children a sense of control over their own day.
## How to Apply Trauma-Informed Care in a Session
Small, concrete choices turn principles into practice. Here is how providers can apply trauma-informed care during everyday sessions:
1. **Honor assent.** Watch for both spoken and unspoken cues, and treat withdrawal or distress as a no. This pairs closely with [assent-based compassionate care](/blog/assent-based-compassionate-care-aba-provider-guide).
2. **Preview the plan.** Show the child what the session includes before it starts, so transitions feel expected rather than forced.
3. **Offer real choices.** Let the child pick the order of activities or the reinforcer, which restores a sense of agency.
4. **Avoid coercive compliance.** Drop strategies that override a child's no, and follow a [neurodiversity-affirming practice](/blog/neurodiversity-affirming-practice-aba-slp-ot-provider-guide) that respects autonomy.
Trauma-informed care does not slow progress. It protects the trust that progress depends on. When a child feels safe, seen, and free to say no, the therapeutic relationship grows stronger, and meaningful gains follow.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build predictability and safety into every session. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## ARFID and Autism: When It Is More Than Picky Eating
Published: 2026-06-25
URL: https://vizyplan.com/blog/arfid-autism-extreme-picky-eating-parents
Category: Parenting
Author: Justin Bowman
> ARFID is more than picky eating. Learn how ARFID overlaps with autism and explore gentle, low-pressure ways to support your child at mealtimes.
If your child eats only a handful of foods and panics at anything new, you may wonder whether this is ordinary picky eating or something more. ARFID, which stands for Avoidant Restrictive Food Intake Disorder, is a recognized DSM-5 diagnosis that goes far beyond typical fussiness. Many autistic children experience ARFID, and understanding the difference can help you respond with patience instead of pressure.
## How ARFID Differs From Ordinary Picky Eating
Picky eating usually fades as a child grows and tries new foods over time. ARFID does not follow that pattern. ARFID involves a persistent, intense avoidance of foods that can lead to nutritional gaps, weight concerns, or distress at mealtimes. A picky eater might refuse broccoli. A child with ARFID may eat fewer than ten foods total and gag, cry, or shut down when a non-preferred food is near the plate.
## Why ARFID Overlaps With Autism
ARFID overlaps with autism for several real reasons. Sensory sensitivity makes certain textures, smells, and temperatures genuinely unbearable. Differences in interoception, the sense of signals like hunger, can make appetite hard to read. You can learn more about [interoception and body signals](/blog/interoception-autism-children-hunger-tired-bathroom). Rigidity and a need for sameness mean a slightly different brand or shape can feel like a brand new food. Anxiety around the unknown raises the stakes at every meal.
This article is informational and is not a substitute for a professional evaluation. If you are worried about your child's eating, please talk with a pediatrician, feeding therapist, SLP, OT, or registered dietitian.
## Gentle, Low-Pressure Approaches at Home
1. **Honor safe foods.** Keep your child's trusted foods available without guilt. Safe foods build trust and reduce mealtime anxiety.
2. **Use predictable mealtime routines.** A consistent rhythm helps your child feel safe. Apps like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) let you build visual meal previews so your child knows what to expect before sitting down.
3. **Offer low-pressure exposure.** Place a new food nearby with no expectation to eat it. Smelling, touching, or simply seeing a food counts as progress.
4. **Support the sensory system.** A calmer body explores more easily, so consider a [sensory diet at home](/blog/sensory-diet-home-activities-autism-adhd) outside of meals.
Progress with ARFID is slow and personal. Celebrate tiny wins and lean on qualified professionals along the way.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Make mealtimes more predictable and less stressful for your child. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## RBT Turnover in ABA: What It Costs and How to Fix It
Published: 2026-06-24
URL: https://vizyplan.com/blog/rbt-turnover-retention-aba-provider-guide
Category: For Providers
Author: Justin Bowman
> RBT turnover is one of the toughest challenges in ABA. Here is what high turnover costs clinics and clients, plus practical retention strategies that actually stick.
RBT turnover is one of the most persistent challenges in ABA, and the registered behavior technician role is widely reported as having high turnover across the field. When an RBT leaves, the cost is rarely just a recruiting fee. The cost shows up in broken rapport with a child who took months to trust their technician, and in lost carryover when a new RBT has to relearn a client's plan from scratch.
## What RBT Turnover Actually Costs Clinics and Clients
RBT turnover breaks the rapport that makes therapy work. A child on the spectrum often needs weeks to feel safe with a new adult, and every departure restarts that clock. Families feel the churn too, because consistency is the thing parents notice first.
Carryover suffers when RBT turnover is high. Progress that lived in one technician's head walks out the door with them, and the next RBT inherits incomplete notes instead of a clear plan. The result is slower gains for clients and more rework for supervisors, which feeds the cycle that drives more turnover.
## Retention Strategies That Reduce RBT Turnover
Reducing RBT turnover starts with the daily experience of the job. The strategies below address the reasons technicians most often cite for leaving.
1. **Invest in real onboarding.** A structured first month with shadowing, clear expectations, and early wins helps new RBTs feel competent instead of overwhelmed.
2. **Make supervision supportive, not just compliant.** RBTs stay when BCBAs coach them, answer questions, and treat supervision as mentorship rather than a checkbox.
3. **Build a career path.** Tuition support, BCBA candidacy tracks, and pay tied to growth give RBTs a reason to picture a future at your clinic.
4. **Cut the documentation load.** Excessive paperwork burns out technicians and supervisors alike. Streamlining notes protects time for actual therapy.
Culture ties these strategies together. RBTs leave managers and broken systems more than they leave the work itself, so listening to feedback and acting on it matters.
Tools help too. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) gives teams shared visual plans that travel with the client, so a new RBT inherits a clear routine instead of guesswork, and carryover stays sticky between sessions and home. Less busywork makes an RBT's day saner. For more on the paperwork side, see our guide on [documentation burden and BCBA burnout](/blog/documentation-burden-bcba-burnout-provider-guide), and for protecting progress beyond the clinic, read about [the in-clinic to home generalization gap](/blog/in-clinic-to-home-generalization-gap-provider-guide).
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give your team less busywork and clearer plans. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Time Blindness in Autistic and ADHD Kids: What Parents Can Do
Published: 2026-06-23
URL: https://vizyplan.com/blog/time-blindness-autism-adhd-kids-parents
Category: Parenting
Author: Justin Bowman
> Time blindness is real, and it explains why your neurodivergent child keeps losing track of time. Learn why autistic and ADHD kids cannot feel time passing, and the practical tools that build external structure when the internal clock goes quiet.
When you tell your child "five more minutes" and they melt down at the four minute mark, you are not seeing defiance. You are seeing time blindness, the genuine difficulty many autistic and ADHD kids have with sensing time as it passes. Time blindness means the internal clock most of us rely on without thinking simply does not run on schedule. Your child is not ignoring the clock. Your child cannot feel the clock at all.
## Why Time Blindness Happens
Time blindness is rooted in how the brain manages [executive function](/blog/executive-function-autism-adhd-invisible-struggle), the set of mental skills that track, sequence, and estimate time. Time perception research consistently links time estimation to the same brain systems that govern attention and working memory, both of which work differently in autistic and ADHD children. When those systems are stretched, the felt sense of "how long has it been" goes quiet. A neurotypical adult might sense that twenty minutes have passed. A child with time blindness might experience the same twenty minutes as either two minutes or two hours, with no reliable middle.
Time blindness also explains why abstract warnings rarely land. "We leave soon" carries no meaning when soon is not a measurable unit your child can feel. Children with time blindness need time made visible, not just spoken.
## What Parents Can Do About Time Blindness
The goal is not to fix your child's internal clock. The goal is to build external structure that does the timekeeping for them. Calm, predictable scaffolding paired with [co-regulation](/blog/co-regulation-before-self-regulation-neurodivergent-children) helps far more than repeated verbal reminders.
1. **Make time visible with a countdown.** Use a visual timer that shrinks a colored block as time runs out, so your child sees time leaving instead of hearing about it.
2. **Anchor time to events, not numbers.** Say "after this episode" or "when the timer turns red" instead of "in ten minutes," since events feel concrete and numbers do not.
3. **Build the same sequence daily.** Predictable routines turn time into a familiar shape, and apps like [VizyPlan](https://vizyplan.com) map each step visually so your child knows what comes next.
4. **Narrate transitions early and gently.** Give a calm heads up at the visual halfway point so the change never arrives as a surprise.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was designed around exactly this, turning invisible time into clear visual steps your child can actually follow.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Help your child feel time instead of fighting it. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## One Page, One Team: Getting OT, SLP, and ABA Aligned
Published: 2026-06-22
URL: https://vizyplan.com/blog/interdisciplinary-collaboration-ot-slp-aba-shared-plan
Category: For Providers
Author: Justin Bowman
> A child often has an OT, an SLP, a BCBA, and a teacher all running separate plans, leaving the family to translate between them. Interdisciplinary collaboration around one shared visual is how you align the team. Here is how.
Picture a single autistic child's week. An OT works on motor planning and sensory regulation. An SLP runs language and AAC goals. A BCBA targets daily living skills. A teacher manages classroom expectations. Each is skilled, and each is working in a silo. The person stuck stitching it all together is the parent, who becomes the unpaid translator between four plans that never quite meet. Interdisciplinary collaboration around one shared artifact is how a team stops handing the family that job.
## Why fragmentation costs the child
Siloed care is not just inconvenient, it dilutes outcomes. When disciplines do not coordinate, goals can quietly compete. The OT wants a sensory break at the exact moment the BCBA wants task persistence. The SLP models one prompt while the classroom uses another. The child absorbs the friction as mixed signals, and the family absorbs it as exhaustion. Coordinated care consistently outperforms parallel care, but coordination needs a shared place to happen, not just good intentions in four separate notes.
## What a shared plan looks like
The fix is rarely another meeting. It is a common artifact every discipline can attach to, written in language the family actually uses. Three principles make it work.
1. **One routine, many goals.** Anchor everyone's targets to the same daily routine the family already runs. The morning sequence carries the OT's regulation step, the SLP's request, and the BCBA's self-care target at once.
2. **Shared language, not jargon.** A plan the parent cannot read is a plan that dies at the door. Translate each goal into a plain, visual step.
3. **One source of truth.** When every provider sees the same plan, prompts stop contradicting each other and progress is visible to the whole team.
## Make the family the beneficiary, not the bridge
The goal is a family running one coherent plan instead of refereeing four. That is also where carryover finally holds, the problem we examine in our post on [the speech therapy carryover gap](/blog/speech-therapy-carryover-gap-slp-guide). Collaboration that lives in a shared, visual home routine turns four parallel efforts into one aligned push, and the IEP table benefits too, as we cover in [provider collaboration for IEP preparation](/blog/provider-collaboration-iep-preparation).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP to be that shared page. Every discipline can attach its goal to the same home routine, in the family's own words and photos, so the whole team is finally pointing the same direction.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give your whole team one plan the family can run. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Body Doubling: Why Your Child Works Better When You Are There
Published: 2026-06-21
URL: https://vizyplan.com/blog/body-doubling-autism-adhd-task-initiation-parents
Category: Parenting
Author: Justin Bowman
> Your child can finally start homework the moment you sit down next to them, even though you are not helping. That is body doubling, and there is real science behind it. Here is how to use body doubling at home.
You have probably noticed it without naming it. Your child cannot start their homework, cannot begin cleaning their room, cannot get over the hump of starting at all, until you simply sit down nearby. You are not helping. You are barely talking. And somehow the task that was impossible a minute ago becomes possible. That is body doubling, and it is one of the most useful and underused tools for neurodivergent kids.
## What body doubling is
Body doubling means doing a task in the quiet presence of another person, not for help or instruction, but just to have someone there. The body double does their own thing alongside the child. Research on neurodivergent adults, including a [2024 study in ACM Transactions on Accessible Computing](https://dl.acm.org/doi/full/10.1145/3689648), found that one of the top uses of body doubling is task initiation, getting started and beating the stuck feeling. For autistic and ADHD brains, starting is often the hardest part, a wall sometimes called autistic inertia, where a child is neither doing the task nor able to begin it.
## Why it works
Starting a task draws heavily on executive function, the brain's system for initiating, planning, and following through. A present person lightens that load. The shared focus offers a gentle external anchor and a low-stakes sense of accountability, so the prefrontal cortex is not carrying the whole weight of beginning alone. Body doubling pairs naturally with the broader challenge of [executive function](/blog/executive-function-autism-adhd-invisible-struggle), and it is a close cousin of [co-regulation](/blog/co-regulation-before-self-regulation-neurodivergent-children), where your calm presence steadies your child's system.
## How to body double well
1. **Be present, not in charge.** Sit nearby and do your own quiet task. Resist the urge to manage, correct, or hover.
2. **Keep demands low.** Skip the stream of questions and reminders. Your presence is the support, not your instructions.
3. **Use declarative cues sparingly.** A soft observation like I am starting my list now models the moment of beginning without turning it into a command.
4. **Make it routine.** Same spot, same time, so your child learns that hard tasks come with company.
Body doubling costs nothing and asks little. Often the most powerful thing you can offer a stuck child is simply to pull up a chair, which makes it a natural fit for the [homework routine](/blog/homework-routine-adhd-autism).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who learned that showing up beats taking over. Pair a clear visual of the task with your quiet presence beside it, and the hardest part, starting, gets a whole lot easier.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Make the hardest part, starting, easier for your child. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Special Interests Are the Engine, Not the Distraction
Published: 2026-06-20
URL: https://vizyplan.com/blog/special-interests-autism-build-skills-engine
Category: Strategies
Author: Justin Bowman
> Trains, dinosaurs, elevators, a single video game. Special interests get treated as something to limit. The research says the opposite. Here is how parents and providers can use special interests to build real skills.
Every autism parent knows the interest. It might be trains, dinosaurs, elevators, weather systems, or a single video game your child could narrate for hours. The old clinical language called these restricted interests and treated them as something to ration. A growing body of research, and a generation of autistic adults, say that framing gets it backwards. Special interests are not the distraction from learning. They are the engine of it, for both parents and providers.
## Why special interests are so powerful
A special interest is where an autistic child is most engaged, most regulated, and most competent. That is not a small thing. Engagement is the precondition for learning, and an interest delivers it for free. The connection runs deeper through monotropism, the theory that autistic attention flows as a deep tunnel toward fewer things. The interest is that tunnel. Working with it rather than against it means teaching with the current instead of fighting it, which is far less exhausting for everyone.
## How parents can use the interest
1. **Build routines around it.** Make the beloved thing the reward and the anchor of the day, so the hard steps lead somewhere your child wants to go.
2. **Teach through it.** Counting train cars, reading dinosaur books, and writing weather reports are math, literacy, and writing wearing a costume your child loves.
3. **Let it regulate.** When the world is too much, the interest is often the fastest road back to calm. Protect it as a tool, not just a treat.
## How providers can use the interest
For clinicians, a special interest is a ready-made source of motivation and a bridge to harder goals. Embed it in reinforcement, in social stories, and in the materials you choose. A child who will not label flashcards will happily label every planet. The same interest can become a social bridge, since shared passion is one of the most natural ways autistic kids connect, a point we explore in [the double empathy problem](/blog/double-empathy-problem-autism-social-skills-parents). Using interests this way fits squarely inside [neurodiversity-affirming practice](/blog/neurodiversity-affirming-practice-aba-slp-ot-provider-guide).
The shift is simple to say and powerful in practice. Stop treating the interest as the problem and start treating it as the path. The deep focus your child already brings is the most renewable source of motivation you will ever find.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad whose son lit up when his own world showed up in his day. Build the interest into the routine, the story, and the reward, so learning rides on the thing your child already loves.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the day around what your child loves most. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Neurodiversity-Affirming Practice: What It Means in 2026
Published: 2026-06-19
URL: https://vizyplan.com/blog/neurodiversity-affirming-practice-aba-slp-ot-provider-guide
Category: For Providers
Author: Justin Bowman
> Neurodiversity-affirming practice is the phrase every family now searches for. For ABA, SLP, and OT it is more than a label. Here is what neurodiversity-affirming practice looks like in real goals, sessions, and home carryover.
Walk a family through intake in 2026 and you will hear the question directly. Is your practice neurodiversity-affirming? Parents are reading the same autistic-led writers your continuing education now cites, and they want to know whether your goals will respect their child or try to erase the parts that make them autistic. Neurodiversity-affirming practice is more than a banner on a website. It is a concrete set of choices in how you write goals and run sessions.
## What neurodiversity-affirming practice means
The affirming model treats autistic differences as differences, not defects, and locates disability in the mismatch between a person and their environment. A [2025 review](https://pmc.ncbi.nlm.nih.gov/articles/PMC11966444/) ties it directly to the double empathy problem and monotropism, two ideas that reframe autistic behavior as valid rather than broken. The practical shift is the target. Instead of making a child look less autistic, you support the skills the child and family actually value, and you change the environment to meet the child halfway.
## Where conventional goals go wrong
Three patterns worth retiring.
1. **Quiet hands and forced eye contact.** Suppressing stimming and demanding eye contact targets the appearance of attention while taxing the real thing. Affirming practice protects regulation strategies instead of extinguishing them.
2. **Compliance as the outcome.** A goal measured by how readily a child obeys trains masking, not skill. Assent-based, socially valid goals age far better, a theme we cover in our post on [assent-based care](/blog/assent-based-compassionate-care-aba-provider-guide).
3. **Communication ranked by mouth-words only.** AAC, gestures, and scripting are communication. Affirming goals grow total communication rather than privileging speech alone.
## Making it concrete
Affirming practice is not lower expectations. It is better-aimed ones. Write goals the autistic person would choose, build on the child's interests and strengths, and define success as a child who is regulated, communicating, and understood. Then carry that same stance home, because a goal that respects the child in session and gets undone by a rigid home demand has not really affirmed anything.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP around the child's own life, photos, and interests. The home routine reflects who the child is rather than a generic ideal, so the affirming work you do in session has somewhere to continue. For more on building on strengths, see our post on [celebrating neurodivergent strengths](/blog/celebrating-neurodivergent-strengths-children).
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would run between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Double Empathy Problem: Rethinking Social Skills
Published: 2026-06-18
URL: https://vizyplan.com/blog/double-empathy-problem-autism-social-skills-parents
Category: Parenting
Author: Justin Bowman
> For decades, autistic kids were told they lacked social skills. The double empathy problem flips that: the misunderstanding runs both ways. Here is what the research shows and what it means for how you support your child.
For a long time, the story about autistic children went one direction. Your child struggles socially, so your child needs fixing. The double empathy problem rewrites that sentence. It proposes that the breakdown between autistic and non-autistic people is mutual, a two-way gap in understanding rather than a one-sided deficit sitting inside your child. The idea is changing how researchers, therapists, and parents think about what social support should even aim for.
## What the double empathy problem says
The concept comes from autistic researcher Damian Milton, who argued that autistic and non-autistic people simply experience the world differently, so they misread each other in both directions. The non-autistic person misses the autistic person's cues just as often as the reverse. A [2025 review of neuro-affirmative support](https://pmc.ncbi.nlm.nih.gov/articles/PMC11966444/) frames the double empathy problem as a mismatch between two valid styles, not a flaw in one of them. Studies have found that autistic people often communicate clearly and comfortably with other autistic people, which is hard to explain if the deficit lived entirely in them.
## Why this matters for your child
Traditional social skills training puts the whole burden on the autistic child to mask, decode, and perform neurotypical behavior. The double empathy problem suggests that approach is solving half the equation while exhausting your child. When a child is constantly translating into a language that is not their own, the cost shows up as burnout, anxiety, and the painful sense of [not fitting in](/blog/neurodivergent-child-no-friends-loneliness).
## How to support both sides of the gap
1. **Find your child their people.** Autistic kids often click instantly with other neurodivergent kids. Shared-style friendship is not a consolation prize, it is connection without the translation tax.
2. **Teach mutual understanding, not just compliance.** Help your child name their own needs and communication style, and coach the people around them to meet it halfway.
3. **Value their way of relating.** Parallel play, info-dumping about a passion, and side-by-side time are real social connection, not failed versions of it.
4. **Drop the goal of looking typical.** Aim for a child who is understood and comfortable, which matters far more than a child who passes.
The double empathy problem does not mean social support has no place. It means the support works best when it runs both ways. This is the heart of what [acceptance looks like at home](/blog/autism-acceptance-what-it-looks-like-at-home).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who wanted his son understood, not corrected. The day is built around how your child actually experiences it, so the goal is connection on their terms.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a day that meets your child halfway. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## AI Ambient Documentation: Buying Back the Hour You Lose
Published: 2026-06-17
URL: https://vizyplan.com/blog/ai-ambient-documentation-therapy-notes-provider-guide
Category: For Providers
Author: Justin Bowman
> Clinicians lose 30 to 40 percent of their week to paperwork. AI ambient documentation drafts the note while you work, cutting charting to minutes. Here is what it does well, where the line is, and what to do with the time you reclaim.
Ask any BCBA, SLP, or OT what eats their week and the answer is rarely the kids. It is the notes. Clinicians spend an estimated 30 to 40 percent of their working hours on documentation, charting after every session until the paperwork outweighs the practice. AI ambient documentation is the first tool in years that meaningfully gives that time back, and 2026 is the year it went from novelty to standard. Used well, it changes the math of your day. Used carelessly, it introduces risk. The difference is in how you treat it.
## What AI ambient documentation actually does
An ambient AI scribe listens quietly in the background during a session, captures what happens, and drafts a structured note for you to review. The [Expressable team](https://www.expressable.com/learning-center/online-speech-therapy/ambient-documentation-and-telehealth) describes it as technology that turns the natural flow of a session into a draft clinical note. For ABA specifically, [tools like Session Note AI](https://www.rethinkbehavioralhealth.com/our-solutions/session-note-ai/) generate audit-ready summaries from real session data, HIPAA-compliant by design. The reported result is charting time dropping from a long evening to a few minutes per session.
## Where the line is
The technology drafts. You are still the clinician. A recurring theme in the [clinician research on ambient AI scribes](https://academic.oup.com/jamia/advance-article/doi/10.1093/jamia/ocaf214/8364687) is that these tools reduce charting fatigue but never replace judgment. The note is your legal and clinical record, so the workflow has to include you reviewing, correcting, and signing every draft. Three guardrails worth keeping.
1. **Verify before you sign.** AI drafts can smooth over or invent detail. Read every note as if you wrote it, because in the end you did.
2. **Protect consent and privacy.** Families deserve to know a tool is capturing the session, and the platform must be genuinely HIPAA-compliant, not just marketed that way.
3. **Keep your clinical voice.** The note should reflect your reasoning and the goal, not a generic template the model defaulted to.
## What to do with the time you reclaim
The real payoff is not a tidier inbox. It is the hour you get back. The highest-leverage place to spend it is the gap families fall into between sessions, building the home carryover that actually moves goals. Documentation should serve outcomes, a theme we explore in our post on [proving outcomes in value-based care](/blog/value-based-care-autism-therapy-prove-outcomes).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for exactly that reclaimed hour. Turn a session goal into a visual routine the family runs at home, so the time AI gives back goes straight into the part of care that compounds.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Put the reclaimed hour into carryover that moves goals. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Monotropism: The Attention Theory That Explains Your Child
Published: 2026-06-16
URL: https://vizyplan.com/blog/monotropism-autism-deep-focus-transitions-parents
Category: Parenting
Author: Justin Bowman
> Monotropism is the autistic-led theory that finally explains the deep focus, the meltdowns at transitions, and the all-or-nothing attention. Here is what monotropism means and how to support your child once you see it.
Your child can spend three hours on trains and not hear you call their name, then fall apart when you ask them to come to dinner. It can look like selective hearing or defiance. Monotropism offers a kinder and more accurate explanation. Monotropism is the idea that autistic attention runs as a deep, narrow tunnel rather than a wide, shallow spread, and once you see your child through that lens, a lot of the hardest moments start to make sense.
## What monotropism means
Monotropism is a theory of autism developed by autistic researchers Dinah Murray, Wenn Lawson, and Mike Lesser, first published in 2005 and gaining real traction now. The [National Autistic Society](https://www.autism.org.uk/learn/knowledge-hub/professional-practice/what-is-monotropism) describes it as a tendency for attention to be pulled strongly toward a small number of interests at a time. Most people are polytropic, holding several channels open at once. A monotropic mind pours nearly all of its resources into one channel, which is why the focus is so deep and why pulling out of it is so costly. [Reframing Autism](https://reframingautism.org.au/monotropism-understanding-autistic-ways-of-being-through-the-lens-of-attention/) connects monotropism to sensory processing, interoception, and emotional regulation, not just interests.
## Why transitions hurt so much
When attention is a tunnel, a transition is not a small ask. You are not requesting that your child stop trains and start dinner. You are asking them to rip their entire attention out of one world and rebuild it in another, with no warning. Monotropism reframes the meltdown at the end of an activity as a genuine processing cost, not a behavior problem. Understanding the attention tunnel changes the response from frustration to support, which connects directly to our guide on [why autistic kids resist transitions](/blog/why-autistic-kids-resist-transitions).
## How to support a monotropic child
1. **Give transitions a runway.** Warn early and more than once. A countdown, a timer, or a visual of what comes next lets your child begin surfacing from the tunnel on their own terms.
2. **Honor the deep dive.** The intense interest is not a problem to limit. It is where your child feels most competent and regulated, and it can be a bridge to new skills.
3. **Lower the number of channels.** When you need focus on a hard task, reduce competing input. One clear thing beats five half-things for a monotropic brain.
4. **Use the interest as the on-ramp.** Attach a new step to the thing your child already loves rather than competing with it.
Monotropism is not a deficit to fix. It is a different and often powerful way of paying attention. Seeing the tunnel for what it is lets you stop fighting your child's focus and start building the day around it.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad whose son lives in that deep focus. A visual day with clear transition warnings gives a monotropic mind the runway it needs to move between worlds without the crash.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the day that respects how your child pays attention. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## In-Clinic to Home: Closing the Generalization Gap
Published: 2026-06-15
URL: https://vizyplan.com/blog/in-clinic-to-home-generalization-gap-provider-guide
Category: For Providers
Author: Justin Bowman
> As autism therapy shifts toward in-clinic delivery, the oldest problem in the field gets louder. A skill mastered in your therapy room does not automatically show up at home. Here is the provider scaffold that closes the generalization gap.
The autism therapy market is shifting toward the clinic. Industry analysts tracking 2026 note that delivery is moving in-clinic, with [some states already running more than half of ABA services in centers](https://bhbusiness.com/2026/01/07/behavioral-health-predictions-for-2026-autism-rate-cuts-tms-on-the-rise/). In-clinic care has real advantages for staffing and supervision. It also turns up the volume on the oldest problem in the field. A skill mastered in your therapy room does not automatically travel home, and the generalization gap is exactly where progress quietly stalls.
## Why the generalization gap widens in-clinic
Three drivers you already know.
1. **The clinic is a controlled context.** Clean environment, trained adults, consistent cues. Home is none of those things, and a skill bound to clinic conditions may not recognize the kitchen at 6 p.m.
2. **The people change.** Your RBT prompts with precise timing. A tired parent at the end of a workday does not, and the skill that depended on that prompting fades.
3. **The cues do not exist at home.** The visual supports, the schedule on the wall, and the session structure all stay behind in the center. The child loses the scaffolding the skill was built on.
## Where the home routine closes the gap
Generalization is not luck. It is programmed. The classic move is to vary people, settings, and materials on purpose, and the home routine is the most important setting of all because it is where the child actually lives. The scaffold is simple. Take the one or two highest-priority clinic targets and give the family a short home version, anchored to a daily routine they already run, using the real child in the real home.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for the gap between the center and the kitchen. The clinic target becomes a routine card the parent runs in ten minutes a day, with the child's own photos and the family's own rhythm. Your clinical work stays yours. The skill gets the home reps that generalization requires. For a closer look at the carryover problem, see our guide to [the speech therapy carryover gap](/blog/speech-therapy-carryover-gap-slp-guide).
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would run between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## How to Vet Autism Advice Online Without Losing Your Mind
Published: 2026-06-14
URL: https://vizyplan.com/blog/how-to-vet-autism-advice-online-misinformation
Category: Parenting
Author: Justin Bowman
> A 2026 review found autism misinformation is widespread on social media. When every scroll offers a new fix, you need a filter. Here is how to vet autism advice online and tell credible guidance from confident nonsense.
Open any feed at 11 p.m. and the autism advice arrives in a flood. A supplement that changed everything. A parenting move that fixed meltdowns overnight. A confident voice telling you the experts have it all wrong. Some of it is genuinely helpful. A lot of it is not. A 2026 review reported that [autism and mental-health misinformation is widespread on social media](https://www.disabilityscoop.com/2026/05/01/autism-misinformation-widespread-on-social-media-study-finds/31982/), and parents are the audience it lands on hardest. Learning to vet autism advice online is now a basic parenting skill, not a nice-to-have.
## How to vet autism advice online
A quick filter you can run on any post in under a minute.
1. **Check who is talking.** Look for a real name and real credentials, or a clearly identified autistic adult sharing lived experience. An anonymous account selling a product is a different thing than a licensed SLP, OT, or pediatrician.
2. **Look for a source, not just a claim.** Credible advice points somewhere you can check, like a study, a clinical organization, or named research. A bold statement with nothing behind it is just a vibe.
3. **Be wary of cure language and miracles.** Anything promising to fix, reverse, or unlock autism is a red flag. Real support helps a child thrive as themselves, it does not erase who they are.
4. **Distrust the one weird trick.** Autism is varied, which the new [subtype research](/blog/autism-subtypes-brain-research-what-it-means) keeps confirming. A single hack that supposedly works for every child is selling certainty, not help.
5. **Cross-check before you act.** If a tip would cost real money, change a diet, or stop a therapy, verify it against a trusted source like the AAP, ASHA, or AOTA before you do anything.
## Why the feed feels so convincing
Misinformation spreads because it is emotionally satisfying. It offers a clean villain, a simple fix, and the relief of certainty, while honest guidance tends to say it depends and that is harder to share. Confidence is not evidence. The calmest, most reasonable voice in your feed may be the least reliable, and the careful clinician hedging their claims may be the one worth keeping.
The steadiest filter is to anchor on a few sources you trust and let the rest wash past. Our roundup of [trustworthy autism resources](/blog/trustworthy-autism-resources-online-tiktok-misinformation) is a good starting shelf.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP who got tired of watching families chase fixes that did not exist. No miracles, just the boring, proven basics of a predictable visual day, built around your actual child.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Skip the miracle cures and build the proven basics. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Assent-Based Care: The Quiet Shift Reshaping ABA
Published: 2026-06-13
URL: https://vizyplan.com/blog/assent-based-compassionate-care-aba-provider-guide
Category: For Providers
Author: Justin Bowman
> Assent-based care has moved from the margins to the ethical gold standard of ABA in 2026. Here is what assent-based care looks like in practice and how predictability and choice at home reinforce it between sessions.
The center of gravity in behavior analysis has moved. The field has spent the last few years listening harder to autistic self-advocates, and the result is a clear consensus heading into 2026. Assent-based care is now widely described as the ethical gold standard of quality ABA. Rigid compliance protocols are out. Mutual trust, psychological safety, and a learner who is genuinely on board are in.
## What assent-based care means in practice
Consent is what a parent or guardian gives. Assent is the ongoing signal from the learner that they are willing to participate, whether they communicate that with words, with their body, or with engagement. [Compassionate, assent-based practice](https://asatonline.org/research-treatment/clinical-corner/integrate-compassionate-care/) means continuously checking that the child is with you rather than being marched through a plan. The [framing many practitioners now use](https://qbs.com/news-and-blog/the-power-of-consent-assent-and-trauma-informed-aba/) is straightforward. When a learner is an active participant instead of a passive recipient, they feel safer, and skills they help shape are more likely to stick and generalize.
## Why assent is hard to hold across settings
Three pressures that quietly erode it.
1. **Assent is a moment-to-moment read, not a form.** It can be honored beautifully in session and lost entirely the second the child gets home to a different adult and a different plan.
2. **Predictability is a precondition for assent.** A child who cannot tell what is coming next has little real ability to opt in, because every transition is a surprise to brace against.
3. **Choice has to be visible to count.** Telling a child they have a say means little if the options never take a form they can actually see and point to.
## Where the home routine reinforces assent
Assent-based care does not stop at the clinic door, and the home routine is where it either holds or breaks. A predictable, visual day gives a child the two things assent depends on. They can see what is coming, so a transition is an invitation rather than an ambush, and they can make real choices inside the routine. Our guide to [choice boards](/blog/choice-boards-empowering-decisions) covers how to build that in.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP around predictability and choice. The child sees the day, picks inside it, and meets each step already knowing it is coming. The clinical model stays yours. The conditions that make assent possible follow the child home.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would run between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Autistic Shutdown vs Meltdown: How to Tell Them Apart
Published: 2026-06-12
URL: https://vizyplan.com/blog/autistic-shutdown-vs-meltdown-how-to-tell-apart
Category: Parenting
Author: Justin Bowman
> A meltdown is loud and obvious. An autistic shutdown is the same overload turned inward, and it is easy to miss or mistake for defiance. Here is how to tell an autistic shutdown from a meltdown and what helps each one.
Most parents learn to spot a meltdown fast because a meltdown announces itself. The crying, the shouting, the body in motion are impossible to miss. An autistic shutdown is the harder one. It is the same flood of overwhelm, but instead of bursting outward it collapses inward, and it is quiet enough to be mistaken for calm, defiance, or a child who is simply tired. Learning to read an autistic shutdown is often the missing half of understanding your child's hardest moments.
## Autistic shutdown vs meltdown: the core difference
The cause is identical. A nervous system is overloaded past what it can process. The direction is what changes. A meltdown discharges the overload outward through tears, noise, and movement. An autistic shutdown turns the same overload inward and seals the exits. Your child may go silent, stop responding, lose words they usually have, and physically withdraw or freeze. Because nothing dramatic is happening on the outside, a shutdown is frequently misread as ignoring you, refusing, or being rude, when it is actually a child who has run out of bandwidth.
## How to recognize a shutdown
Watch for these early signs.
1. **Words get harder.** Short answers, long pauses, or losing the ability to speak at all.
2. **The body goes still or small.** Curling up, hiding, putting the head down, or going limp rather than ramping up.
3. **The urge to flee or disappear.** Some kids slip away to a closet or under a bed. The exit is the point.
4. **Skills temporarily vanish.** A task your child did easily an hour ago suddenly feels impossible.
## What helps a shutdown
The instinct to fix a quiet child by talking more, asking questions, or pushing for an answer makes a shutdown worse. Each demand is more input on a system that is already past full. Do the opposite. Lower the lights, drop the noise, and remove the expectations. Offer presence without pressure, and let recovery take the time it takes. Afterward, gentle reflection helps, which is where understanding [the triggers behind meltdowns and shutdowns](/blog/recognizing-triggers-meltdowns-neurodivergent-children) pays off. Many shutdowns also trace back to a fuller tank of stress, so our piece on [autistic burnout in kids](/blog/autistic-burnout-in-kids-warning-signs) is worth a read.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad whose son needed his day to feel predictable so the overload had fewer places to build. A calmer, clearer day is the cheapest prevention there is. When your child can see what is coming, fewer moments tip into shutdown in the first place.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the predictable day that prevents the overload. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Telehealth Parent Coaching That Actually Carries Over
Published: 2026-06-11
URL: https://vizyplan.com/blog/telehealth-parent-coaching-autism-carryover-provider-guide
Category: For Providers
Author: Justin Bowman
> Telehealth parent coaching matches in-person outcomes when it is done well, yet the strategy still evaporates by Wednesday. Here is the provider scaffold that makes virtual coaching carry over into the family routine.
Telehealth parent coaching has quietly become one of the most evidence-backed tools you have, and one of the most underused. The research is encouraging. Studies show telehealth parent training can reach [high fidelity and match in-person outcomes](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8961090/) for communication and adaptive skills, and parents [can be coached remotely](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC9334541/) to run naturalistic teaching that increases their child's requests and labels. The gap is not whether virtual coaching works. The gap is whether the strategy survives past the screen.
## Why the virtual strategy evaporates by Wednesday
Three failure modes you have probably seen on a parent's camera.
1. **The session is a great hour with no afterlife.** The parent nails the technique while you watch, then the moment ends and the technique leaves with the call.
2. **The plan was never written for the family.** You carry the home program in your clinical notes. The parent carries a vague memory of what you said.
3. **The day does not cue the practice.** Without an anchor in the real routine, the coached skill has no time slot, so it competes with everything else and loses.
## Where telehealth parent coaching earns its keep
The strongest telehealth studies measure generalization by having parents record themselves running the strategy with no trainer present. That is the real bar, and it is also the clue. Coaching carries over when it is attached to a routine the family already runs. Coach the strategy inside the actual morning sequence, not in the abstract, and the practice has somewhere to live the other six days.
Make the home routine the shared artifact. During the call, build or adjust the visual routine together so you and the parent are looking at the same plan. Assign the practice to a specific step. Ask the parent to capture a short clip of that step before the next session, which gives you a true generalization probe and keeps the coaching honest.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for the space between sessions. The routine lives on the family's phone, so the strategy you coach on the call becomes a step the parent runs all week, with the actual child in the actual home. Your clinical work stays yours. The carryover stops depending on memory. For the broader pattern, see our post on [why home programs fall apart between sessions](/blog/why-social-stories-fall-apart-between-sessions).
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would run between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Declarative Language: Talk Less, Connect More With Your Child
Published: 2026-06-10
URL: https://vizyplan.com/blog/declarative-language-autistic-children-talk-less-connect-more
Category: Parenting
Author: Justin Bowman
> Most of what we say to autistic kids is a question or a command. Declarative language flips that by sharing observations instead of issuing directions, which lowers the demand and builds connection. Here is how to use it at home.
Count your sentences to your child for one hour and a pattern jumps out. Put your shoes on. Did you brush your teeth. Come here. Stop that. Almost everything we say to kids is a question or a command. Declarative language is the quiet alternative, and for many autistic children it changes the temperature of the whole house. Instead of issuing a direction, you share an observation and leave room for your child to respond on their own terms.
## What declarative language is, and why it lowers the demand
Imperative language tells or asks: directions and questions that require a response. Declarative language simply comments: I notice your shoes are still by the door. Speech-language pathologist Linda Murphy, who wrote the Declarative Language Handbook, points out that [less than one percent of the language used with autistic individuals is declarative](https://tiltparenting.com/2023/03/28/declarative-language/). The rest is a steady stream of demands. For a child whose nervous system reads every question as pressure, that stream is exhausting. Declarative language removes the demand while still giving information, which is why it pairs so well with a [demand-avoidant or PDA profile](/blog/demand-avoidance-pda-profile-autism-children).
## How to use declarative language at home
Four swaps to practice this week.
1. **Trade the command for an observation.** Instead of put your coat on, try I see it is cold out today. The information is there without the order.
2. **Narrate instead of quiz.** Instead of what color is that, try that truck looks bright red to me. You model language without demanding performance.
3. **Think out loud.** I am trying to figure out where this piece goes invites a child into shared problem-solving rather than testing them.
4. **Leave a pause.** After a declarative comment, wait. The silence is the part that lets your child step in.
## What to expect
Declarative language is not a magic switch, and it does not replace clear safety directions when a child is about to run into a street. The goal is to shift the everyday ratio so connection outweighs commands. Over time, many parents notice less resistance and more genuine back-and-forth. Pair the spoken shift with a visual one. When the next step lives in a picture your child can see, you do not have to narrate it as a demand at all. Our guide to [first-then boards](/blog/first-then-boards-guide) shows how to let the visual carry the direction.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad whose son did better when the day showed itself instead of being barked at. The routine carries the next step, so your words can carry the connection.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Let the visual carry the demand so you can connect. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## NDBI Explained: The Naturalistic Model Families Keep Asking About
Published: 2026-06-09
URL: https://vizyplan.com/blog/ndbi-naturalistic-developmental-behavioral-intervention-provider-guide
Category: For Providers
Author: Justin Bowman
> Parents are arriving at intake asking for NDBI by name. Naturalistic developmental behavioral intervention blends ABA and developmental science into play and daily routines. Here is the provider-friendly explainer and where the home routine fits.
If you work in early intervention, you have noticed the shift at intake. Parents now arrive asking for NDBI by name, often before they can define it. Naturalistic developmental behavioral intervention is no longer a niche term, and families want to know whether your practice does it. The good news is that the model is easier to deliver than the acronym suggests, and the home routine is its natural home.
## What NDBI actually is
NDBI is an umbrella term [coined by Schreibman and colleagues in 2015](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4513196/) for interventions that blend applied behavior analysis with developmental science. Instead of isolated discrete trials at a table, teaching happens inside play and everyday activities, follows the child's lead, and uses natural reinforcement. Familiar approaches like ESDM, JASPER, PRT, and Enhanced Milieu Teaching all sit under the NDBI heading. The [Autism CRC evidence review](https://www.autismcrc.com.au/interventions-evidence/category-overview/NDBI) classifies NDBI among the better-supported early approaches, and recent [meta-analytic work](https://pmc.ncbi.nlm.nih.gov/articles/PMC12208088/) found language gains, including for minimally speaking children when paired with AAC.
## Why the model strands without a home vehicle
Three failure modes you have probably watched happen.
1. **The naturalistic part needs natural settings.** A method built on embedding teaching in daily life loses its engine when it only runs in your clinic room.
2. **The parent is the intervention, but the plan lives in your head.** Parent-mediated NDBI is [promising in the literature](https://link.springer.com/article/10.1007/s40489-024-00439-0), yet families cannot run what was never written down for them.
3. **Play targets blur without an anchor.** Without a predictable routine to attach to, the embedded opportunities drift and density drops.
## Where the home routine earns its keep
NDBI asks the family to create dozens of small teaching moments across the day. A visual routine pre-stages those moments. The snack step holds the words and choices you want modeled. The bath step carries the joint-attention bid you are targeting. The clinician designs the NDBI goals; the routine turns them into something a parent can actually run between sessions.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for exactly this gap. The routine lives on the family's phone, the photos are the real child in the real home, and the teaching targets sit inside the step where they fit naturally. Your clinical work stays yours. The naturalistic practice gets the daily density the model depends on. For more on closing this gap, see our post on [the speech therapy carryover gap](/blog/speech-therapy-carryover-gap-slp-guide).
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would run between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Autism Subtypes: What New Brain Research Means for Your Child
Published: 2026-06-08
URL: https://vizyplan.com/blog/autism-subtypes-brain-research-what-it-means
Category: Parenting
Author: Justin Bowman
> A 2026 study identified two biologically distinct autism subtypes, each tied to a different pattern of brain communication. Here is what the autism subtypes research actually found and what it means for your child at home.
A new wave of brain research is reshaping how scientists describe autism, and the headline is one many parents felt long before a study confirmed it. Autism is not one thing. In 2026, researchers identified two biologically distinct autism subtypes, each tied to a different pattern of how the brain communicates with itself. If you have ever looked at the tidy autistic child in a clinic pamphlet and thought that is nothing like my kid, the science is finally catching up to your living room.
## What the autism subtypes research actually found
A study published in [Nature Neuroscience](https://www.nature.com/articles/s41593-026-02287-z) analyzed brain scans from nearly 2,000 people, including 940 autistic individuals, and found two clear patterns. In one subtype, brain regions communicate more than usual, a pattern called hyperconnectivity that the researchers linked to immune and gene-expression differences. In the other, regions communicate less, a pattern called hypoconnectivity tied to how brain cells form connections at the synapse. The team even matched these patterns across species in mouse models. The [Child Mind Institute](https://childmind.org/blog/new-study-identifies-different-biological-subtypes-of-autism/) and [Autism Speaks](https://www.autismspeaks.org/news/new-study-identifies-biologically-distinct-autism-subtypes-advancing-path-personalized-care) both framed the finding as a real step toward precision care.
## Why autism subtypes matter for families, not just labs
Three honest takeaways for parents.
1. **It validates what you already see.** Two children can share the same diagnosis and need completely different things. The biology now backs up that lived reality.
2. **It points toward personalized support.** The long-term promise is care matched to a child's actual profile rather than a one-size protocol. That future is years away, but the direction is set.
3. **It does not change what helps tomorrow.** No brain scan reorders your morning. Your child still benefits most from the supports built around who they actually are.
## What to do with this news at home
The practical answer has not changed, and that is reassuring. Watch your specific child, not the category. Notice which supports lower their stress and which raise it, and build the day around the answer. Personalized care is not something you wait for a lab to deliver. You already practice it every time you adjust a routine to fit your kid. If a formal evaluation is on your mind, our guide to [what comes next after an autism diagnosis](/blog/after-autism-diagnosis-what-comes-next) walks through the steps.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad whose son needed a day built around him, not around a label. The photos are your actual child, the routines are your actual home, and the plan bends to the kid in front of you.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the day around your actual child. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Fewer Authorized Hours: Maximizing Carryover When Payers Cut
Published: 2026-06-07
URL: https://vizyplan.com/blog/fewer-authorized-hours-autism-therapy-carryover
Category: For Providers
Author: Justin Bowman
> Fewer authorized hours are the new reality as payers tighten utilization and trim rates. The math only works if gains hold between sessions. Here is how to densify carryover, pick the highest-leverage goal, and generate the generalization data that also supports continued-care authorization.
Fewer authorized hours are no longer the exception. As several state Medicaid programs trim ABA rates and commercial payers tighten utilization management, more of your clients are arriving with authorizations that cover less than the clinical picture calls for. The instinct is to fight every reduction, and some are worth fighting. The harder, more durable work is making the approved hours do more. When the schedule shrinks, the math only works if the gains hold between sessions.
## What fewer authorized hours actually change
A reduction does not change the goal. It changes the density of practice supporting the goal. A skill that was getting reinforced across twelve hours a week now gets eight, and the missing four have to land somewhere or the progress curve flattens. Payers are also asking for more in return for less, requiring stronger documentation of continued need to keep an authorization alive. The clinician is now expected to show progress with fewer hours and prove it with better data, at the same time.
The leverage point is the same one families feel from the other side. Skills that generalize to home need less in-session reinforcement to maintain, which means the hours you keep go further.
## How to densify carryover when the hours drop
1. **Triage to the highest-leverage goal.** With fewer hours, spread thin loses to focused depth. Pick the one or two goals that unlock the most daily function.
2. **Build a parent-run home routine for that goal.** Pull it straight from the active program, keep it to a few minutes a day, and make it specific enough to run without you in the room.
3. **Capture the carryover as data.** Home practice that produces a visible record becomes evidence of progress, which is exactly what a continued-care authorization needs.
4. **Tie it back to the authorization narrative.** Document generalization gains in the language payers reward, the same approach we outline in our [insurance denials and prior authorization guide](/blog/autism-insurance-denials-prior-authorization-guide).
The carryover problem is one we have written about often, from [the speech therapy front-door gap](/blog/speech-therapy-carryover-gap-slp-guide) to [extended school year programming](/blog/extended-school-year-carryover-provider-guide). Under fewer authorized hours, carryover stops being a nice-to-have and becomes the mechanism that keeps the plan working.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) turns a clinical goal into a visual routine the family runs at home, so the hours you lost to a payer get partly recovered at the kitchen table. The clinical work stays yours. The carryover, and the data behind it, travels with the family.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Make every approved hour go further. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Low-Demand Summer: Helping Autistic Kids Recover
Published: 2026-06-06
URL: https://vizyplan.com/blog/low-demand-summer-autistic-kids-masking-recovery
Category: Parenting
Author: Justin Bowman
> A low-demand summer is not laziness. For an autistic child who spent the school year masking, regulating, and performing, summer can be the recovery the nervous system has been waiting for. Here is how to lower the demands on purpose without losing the predictability your child still needs.
A low-demand summer is not laziness, and it is not giving up. For an autistic child who spent ten months masking in a fluorescent classroom, holding it together through transitions, and performing social scripts that do not come naturally, summer can be the recovery the nervous system has been quietly waiting for. The school year asks an enormous amount of a neurodivergent child. A low-demand summer is the deliberate choice to ask less for a while, so the tank can refill before September asks for everything again.
## Why a low-demand summer matters more than a full schedule
The instinct to fill summer with camps, lessons, and enrichment comes from a good place, but it can miss what an exhausted child actually needs. Sustained masking carries a real cost. Research by [Cage and Troxell-Whitman](https://pubmed.ncbi.nlm.nih.gov/30900112/) linked the effort of masking to poorer mental health outcomes, and the children doing the most masking are often the ones who look the most fine. When the performance finally stops in June, what surfaces is not bad behavior. It is the bill coming due. We have written about [the warning signs of autistic burnout in kids](/blog/autistic-burnout-in-kids-warning-signs), and summer is when many families first recognize it.
A low-demand summer is different from losing all structure. The goal is not the chaos of an empty calendar, which brings its own problems. We covered that risk in our post on [the summer routine cliff](/blog/summer-break-autistic-kids-routine-cliff). The goal is fewer demands held inside a gentle, predictable frame.
## How to lower the demands without losing the anchors
1. **Protect special-interest time.** The deep dive into trains, or drawing, or a video game is not a distraction from recovery. It is the recovery.
2. **Cut the number of scheduled obligations.** Fewer outings, fewer hard start times, more open afternoons. Aim for rhythm, not rigidity.
3. **Keep a few light anchors.** A predictable wake-up, a simple meal rhythm, and a visual outline of the day give security without pressure.
4. **Let rest look different.** For some children rest is stillness. For others it is movement or repetition. Follow your child's version.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you keep the light, predictable anchors a recovering child still needs while stripping the day down to what matters. The day stays visible and calm, with far less on it.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Give your child a calmer summer they can see coming. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Documentation Burden Behind BCBA Burnout
Published: 2026-06-05
URL: https://vizyplan.com/blog/documentation-burden-bcba-burnout-provider-guide
Category: For Providers
Author: Justin Bowman
> BCBA burnout is no longer a quiet problem. Surveys show most have considered leaving, and the biggest culprit is not the children. It is the paperwork. Here is what the documentation burden is doing to your team and the practical levers that give clinicians their time back without cutting corners on care.
BCBA burnout is no longer a quiet problem whispered about at conferences. It is a workforce crisis with numbers attached. In a recent industry survey, 58 percent of BCBAs said they had considered leaving the profession because of stress, and the biggest culprit was not the children or the families. It was the paperwork. For practice owners trying to hold a team together while payers tighten the screws, understanding where the hours actually go is the first step toward keeping the clinicians you have.
## What the documentation burden is doing to your team
The same survey, summarized in [a 2026 review of ABA trends](https://www.abamatrix.com/aba-trends-2026/), found that 61 percent of BCBAs say administrative burden interferes with direct care, and that BCBAs spend only about 25 percent of their time working directly with clients. The rest disappears into non-clinical work, with session notes and reports eating the largest share. One in three reported extreme stress for two years or longer. Frontline turnover compounds the strain, with RBT turnover running anywhere from roughly 77 percent to over 100 percent at larger organizations.
The pattern is brutal and clear. The people who entered the field to work with children spend three of every four hours not working with children, and many of them are deciding the trade is not worth it.
## The levers that actually give time back
Burnout fixes that ask clinicians to simply be more resilient miss the point. The fix is structural. Reduce the volume of low-value documentation, build templates that make required notes faster, and cut the re-teaching that happens when skills do not hold between sessions.
That last lever is the one most practices overlook. Every skill that fails to carry over to home becomes a session spent re-teaching, which becomes another note, another data point, another report. When carryover improves, clinical time gets more productive and the paperwork per unit of progress drops. We have written for families about [what to do when therapy does not transfer home](/blog/why-social-stories-fall-apart-between-sessions), and the provider side of that equation is the same. Better generalization means less rework.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) gives families a visual routine pulled from the active goal, so practice continues between sessions and the clinician is not rebuilding ground every week. The home tool produces carryover data without adding clinician hours. Your team spends less time re-teaching and more time on the work that drew them in.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Cut the re-teaching loop that drains your team. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Why Autistic Children's Sensory Needs Get Stronger, Not Milder
Published: 2026-06-04
URL: https://vizyplan.com/blog/autistic-children-sensory-needs-get-stronger
Category: Parenting
Author: Justin Bowman
> Many parents are quietly told their child will grow out of their sensory sensitivities. A large study following more than 1,500 children suggests the opposite. Autistic children's sensory needs tend to get stronger over time, not milder. Here is what the research found and what it changes about how you build the day.
Somewhere in the first year after a diagnosis, many parents are quietly reassured that their child will grow out of it. The covering of the ears at the hand dryer, the refusal of the tag-in seams, the meltdown in the bright grocery aisle. Give it time, the thinking goes, and the world will feel less loud. A large study following more than 1,500 children suggests the opposite is closer to the truth. Autistic children's sensory needs tend to get stronger over time, not milder, and understanding why changes how you build the day around them.
## What the research found about autistic children's sensory needs
Researchers at the USC Chan Division and the University of North Carolina at Chapel Hill followed more than 1,500 children born in North Carolina for six years, publishing their findings in the journal [Child Development](https://chan.usc.edu/news/latest/new-study-shows-autism-correlated-with-changing-sensory-preferences-during-early-childhood). Children who were autistic, or who showed autistic traits, had sensory patterns that intensified as they grew. Non-autistic children, by contrast, stayed relatively steady. The differences were not a phase fading on a timeline. They were a feature deepening on one.
The team also found that sensory differences may appear before the social and communication differences more commonly associated with autism. As lead author Yun-Ju Chen described it, early sensory differences may cascade into the more definitive features of autism over time. Sensory processing is not a side issue. For many children it is the ground floor.
## What this changes about how you build the day
If sensory needs strengthen rather than fade, the goal is not to wait them out. The goal is to build durable accommodations into the ordinary day so your child spends less energy bracing against the environment and more on everything else.
1. **Treat sensory supports as permanent infrastructure, not training wheels.** Noise-reducing headphones, seamless clothing, and a low-stimulation corner are not crutches to remove later.
2. **Make the day predictable.** A child who knows what is coming spends less of their sensory budget on uncertainty. Our guide to [building sensory processing into daily routines](/blog/sensory-processing-daily-routines) breaks this down.
3. **Watch for the quiet signals.** Interoception and sensory load overlap. Our post on [interoception and body awareness](/blog/interoception-autism-children-hunger-tired-bathroom) covers the cues that come before the meltdown.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build a predictable, low-surprise day your child can see in advance, with their own photos in their own spaces. When the day is visible, the sensory system has one less unknown to brace against.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a calmer, more predictable day for your child. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Value-Based Care in Autism Therapy: How to Prove Outcomes
Published: 2026-06-03
URL: https://vizyplan.com/blog/value-based-care-autism-therapy-prove-outcomes
Category: For Providers
Author: Justin Bowman
> Value-based care in autism therapy is moving from conference panels to contract language. Payers and investors increasingly want proof of progress, not a log of hours billed. Here is what outcomes they are looking for, why generalization is the hardest one to show, and how to build the evidence into your model.
Value-based care in autism therapy has moved from conference panels to contract language faster than most practice owners expected. The fee-for-service model that paid for hours of treatment is giving way to one that asks a harder question. What did the child actually gain? Payers and the investors behind large provider groups increasingly want proof of progress, not a log of hours billed. For clinicians who got into this work to change lives, the shift is uncomfortable and also an opening.
## What value-based care in autism therapy actually measures
The outcome measures gaining traction are the ones you already track in some form. Skill mastery rates, goal attainment scaling, reductions in challenging behavior, functional and daily-living skill gains, and parent satisfaction are all on the table. As Jim Spink, CEO of Autism Care Partners, put it, standardized data sets are necessary to be a value-based provider. The warning underneath that statement matters. If providers do not define the outcomes that count, payers will define them instead.
The field has an unusual advantage here. ABA already collects trial-by-trial data during sessions, which means autism therapy may hold one of the most robust outcome data infrastructures in all of behavioral health. The data exists. The question is whether it tells the story payers are asking about.
## Why generalization is the outcome that is hardest to prove
The outcome that matters most to a family, and increasingly to a payer, is whether a skill shows up outside the therapy room. A child who masters a request at the table but cannot use it at home has not generalized the skill. Generalization is also the hardest thing to document, because most of it happens where the clinician is not. We have written before about [why progress stalls at the front door](/blog/speech-therapy-carryover-gap-slp-guide) and [why social stories fall apart between sessions](/blog/why-social-stories-fall-apart-between-sessions). The same gap that frustrates families is the gap a value-based contract will measure.
The practical move is to build generalization evidence into the plan instead of hoping it appears. A parent-run home routine, pulled directly from the active goal and practiced in a few minutes a day, produces exactly the cross-setting data a value-based model rewards.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) turns a clinical goal into a visual routine the family runs at home. The child sees themselves doing the step, the family runs the rhythm, and the carryover becomes visible. The clinical work stays yours. The generalization story finally has data behind it.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would run between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Autism Therapy Medicaid Cuts: How to Protect Progress at Home
Published: 2026-06-02
URL: https://vizyplan.com/blog/autism-therapy-medicaid-cuts-protect-progress-home
Category: Parenting
Author: Justin Bowman
> Autism therapy Medicaid cuts are showing up in the authorization letters families open at the kitchen table. States are trimming ABA rates and tightening approvals. Here is what is actually changing, what it means for your child, and the practical steps that keep progress going when hours get cut.
Autism therapy Medicaid cuts are no longer a rumor buried in a policy newsletter. They are showing up in the authorization letters families open at the kitchen table. Several states have moved to trim what they pay for ABA after spending grew faster than anyone budgeted for, and many parents are now hearing that the same therapy that worked last year comes with fewer approved hours this year. The fear underneath the paperwork is simple. If the hours drop, does the progress drop with them?
## What is actually changing
The pressure is real and it is happening across the country, not in one party or one state. North Carolina's Medicaid spending on autism therapy was projected near $639 million for fiscal 2026, up more than 400 percent from $122 million in 2022, and the state proposed cutting ABA payment rates in response. [Governing reported](https://www.governing.com/policy/states-move-to-rein-in-gold-standard-autism-therapy-as-medicaid-spending-surges) that Nebraska reduced some ABA rates by nearly half, with reductions on the table in Colorado and Indiana. [Autism Speaks has warned](https://www.autismspeaks.org/advocacy-news/medicaid-cuts-coming-protect-autism-services) that broader Medicaid reductions could reach millions of families who rely on it for services private insurance will not cover.
## What autism therapy Medicaid cuts mean for your child
Fewer authorized hours do not erase the gains your child already made. What they change is the density of practice. A skill that was getting reinforced ten hours a week now gets reinforced six, and the missing four hours have to come from somewhere. For most families, that somewhere is home. The good news is that home practice was always where skills generalized best anyway, because home is where your child actually lives their day.
## What you can do right now
1. **Confirm your authorization early.** Call your provider and your plan before the current authorization lapses, and ask exactly how many hours are approved and through what date.
2. **Appeal denials in writing.** A reduction is not always final. Our [guide to insurance denials and prior authorization](/blog/autism-insurance-denials-prior-authorization-guide) walks through the appeal language that works.
3. **Ask your provider for a home carryover plan.** Pick the one or two highest-priority goals and ask how to practice them in ten minutes a day. Our post on [what to do at home when ABA hours get cut](/blog/aba-therapy-cuts-what-to-do-at-home) covers this in depth.
4. **Check funding you may not be using.** Our [roundup of autism funding programs](/blog/autism-funding-programs-financial-support-families) lists grants and waivers worth a phone call.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist for exactly this gap. A therapy goal becomes a visual routine your child can run with you at home, so the practice keeps going on the days the schedule no longer covers.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Keep your child's progress going between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## My Autistic Child Hates Being Autistic: What Actually Helps
Published: 2026-06-01 · Updated: 2026-06-01
URL: https://vizyplan.com/blog/my-autistic-child-hates-being-autistic
Category: Parenting
Author: Justin Bowman
> The moment lands hard. Your autistic child looks up and says, "I hate being autistic." My son is five and we have not arrived at this moment yet, but I have heard the story from enough other parents to know it is coming for many of us. Here is what the research says about autistic identity in kids and what helps when the day arrives.
The moment lands hard. Your autistic child looks up and says, "I hate being autistic." Maybe they have just been left out at recess. Maybe a teacher asked them to "stop doing that thing with your hands." Maybe nothing visible happened at all and the wave was already building. My son is only five and we have not arrived at this moment yet, but I have heard the story from enough other autism parents to know it is coming for many of us. When "my autistic child hates being autistic" is the sentence sitting in the room, the question is not how to talk them out of it. It is how to sit with the feeling while the longer work of identity does its job underneath.
## Why "my autistic child hates being autistic" is the search so many parents end up typing
The research on autistic identity in children is younger than the research on adults, but the pattern is consistent. [Cooper, Smith, and Russell 2017](https://pubmed.ncbi.nlm.nih.gov/28102714/) used social identity theory to show that positive autistic identity correlates with better self-esteem and life satisfaction in autistic individuals. [Cage, Di Monaco, and Newell 2018](https://pubmed.ncbi.nlm.nih.gov/29168096/) linked perceived autism acceptance to better mental health. [Cage and Troxell-Whitman 2019](https://pubmed.ncbi.nlm.nih.gov/30900112/) connected sustained masking to poorer mental health outcomes. The lever is the same across studies. Identity messages absorbed from a non-autistic environment cost something to carry.
When the comment lands, it is rarely about autism in the abstract. It is about a specific moment of difference your child just noticed and cannot yet explain.
## What does not help
Three responses parents reach for that often miss.
1. **"You are just like everyone else."** Untrue, and your child knows it. The reassurance dismisses the experience that prompted the statement.
2. **"Being autistic is your superpower."** The strengths framing can land as more pressure to perform. Some autistic kids find it genuinely useful. Many find it patronizing.
3. **Fixing the moment with a treat or distraction.** The feeling still has to go somewhere. Pushed under, it surfaces louder later.
## What actually helps
Sit with the statement first. "That sounds really hard. Tell me what just happened." Then narrow to the specific moment. If a peer interaction triggered it, that is the thing to work on, not autism as a category.
Anchor the conversation with autistic adults the child can see, in books, on screen, or in your own life. The story of being autistic was never going to be written by a non-autistic narrator. Pair that with the small everyday signal that says "this is my real day, and I am okay in it." Photos of your child doing their actual routines, in their actual room, with the things they actually like. Identity in kids is built less by speeches and more by the steady image of themselves living a recognizable day.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad whose son needed to see himself in his own day. The photos are the actual child, doing the actual routine, in the actual room. Identity does not get built in a single moment. It gets built in the small recurring image of "this is me, and this is what my day looks like, and that is fine."
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the day where your child sees themselves. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Extended School Year Carryover: A Provider Guide for ESY Summer
Published: 2026-05-31
URL: https://vizyplan.com/blog/extended-school-year-carryover-provider-guide
Category: For Providers
Author: Justin Bowman
> ESY runs a few hours a few days a week. The IEP goal still has to survive the rest of the summer. Extended school year carryover is the gap between the goal page and the kitchen at 9 a.m. Here is the visual scaffold school clinicians can hand the family.
If you are a school based OT, SLP, or special educator, you have already had the conversation with the team about who qualifies for ESY and what the goals will look like. The harder question is the one parents will ask in week three of June. "What do I do at home with this on the days they are not at ESY?" Extended school year carryover is the gap between the IEP goal page and the kitchen at 9 a.m. The visual scaffold makes it survivable.
## What ESY covers and where it leaves off
[IDEA Part B](https://sites.ed.gov/idea/regs/b/d/300.106) defines ESY services as those a child needs to receive FAPE when regression and recoupment data show the break would cost them. ESY is not enrichment, and it is not summer camp. The [OSEP guidance](https://sites.ed.gov/idea/files/policy_speced_guid_idea_files_extension-of-school-year.pdf) is clear that services are individualized to the IEP. Most districts run ESY for a few hours a few days a week, which is a small slice of the summer for the student carrying the regression risk.
The gap is the rest of the week. The IEP goal is still active. The family is the only one in the room.
## Why summer regression hits harder than the data captures
Three drivers school clinicians know but families may not.
1. **The cuing environment vanishes.** The visual schedule on the classroom wall, the paraprofessional's prompting cadence, and the morning meeting sequence all stop. The student loses the prompts the IEP goal was built on.
2. **The peer model disappears.** Generalization probes pulled from peer interaction lose their substrate.
3. **Sleep, food, and sensory routines drift.** The conditions under which the goal could be practiced collapse.
## Where extended school year carryover earns its keep
A short visual home version of the ESY goal that the family can run in 10 minutes a day. Pulled directly from the IEP, photographed with the actual student in the actual home, and anchored to a time the family already controls. The clinician designs the scaffold. The family runs the rhythm. Recoupment data in September goes up because the goal got density across the gap.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for the summer carryover problem. The IEP goal becomes a routine card. The student sees themselves doing the step. The family does not have to invent the scaffold. The clinical work stays yours. The carryover travels with the family.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your ESY families would run between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Swim Lessons for Autistic Kids: A Parent's Field Guide
Published: 2026-05-30
URL: https://vizyplan.com/blog/swim-lessons-for-autistic-kids-parent-guide
Category: Parenting
Author: Justin Bowman
> Drowning is the leading cause of death in autistic children under fourteen who wander. Swim lessons for autistic kids are not enrichment, they are safety infrastructure. Here is what research says and the lesson setup that works.
Drowning is the leading cause of death for autistic children under fourteen who wander. That sentence is the one I had not encountered before our son was diagnosed, and it changed how summer prep looks. Swim lessons for autistic kids are not an enrichment activity. They are safety infrastructure on the same tier as bike helmets. The setup that works is different from the standard rec center curriculum, and the research backs why.
## Why swim lessons for autistic kids matter more
The [National Autism Association](https://nationalautismassociation.org/resources/autism-safety-facts/) wandering data attributes roughly 90 percent of deaths in autism wandering cases under age 14 to drowning. [Guan and Li 2017](https://pmc.ncbi.nlm.nih.gov/articles/PMC5388960/) in the American Journal of Public Health found drowning rates in autistic children roughly 160 times the general pediatric rate. Autistic kids are often drawn to water and may not register the danger the way other kids do. The [AAP](https://publications.aap.org/pediatrics/article/148/2/e2021052227/179930/Prevention-of-Drowning) recommends formal swim instruction starting as early as age one, with adapted models for neurodivergent learners.
## What does not work in the standard model
Three failure modes when an autistic child is dropped into a group rec class.
1. **The pool is a sensory environment first.** Echo, chlorine, slick edges, and splashing make instruction nearly impossible until the environment is tolerated.
2. **Verbal instruction is the wrong currency.** "Kick your feet, then arm circles" lands in a room your child cannot process. The teaching has to be visual and physical first, verbal later.
3. **The 30 minute group format is too short and too crowded.** An autistic learner often needs ten of those minutes just to enter the water before any teaching can happen.
## What actually works
Look for one on one instruction with a teacher trained in autism or adapted aquatics. The [YMCA](https://www.ymca.org/) and many local rec departments now run adapted swim programs explicitly. The [USA Swimming Foundation Make a Splash](https://www.usaswimmingfoundation.org/utility/landing-pages/make-a-splash) network maintains a lesson finder. Ask about visual schedules at the pool, a consistent instructor across weeks, and a goal hierarchy that starts with water tolerance and ends with functional swim, not stroke perfection.
At home, preview the pool with a [social story](/blog/social-stories-autism-guide). Photos of the actual locker room, the actual instructor, the actual entry point. Anything you can hand your child the night before lowers the cost of arrival.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad for prep like this. A short visual story for the swim lesson, the day mapped out around it, and a celebration step at the end. The lesson stops being an unknown event your child has to brave cold.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the swim lesson prep in 10 minutes. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## AAC Visual Schedules: An SLP's Guide to Home Carryover
Published: 2026-05-29 · Updated: 2026-05-31
URL: https://vizyplan.com/blog/aac-visual-schedules-slp-home-carryover
Category: For Providers
Author: Justin Bowman
> If you are an SLP working with an AAC user, you already know the gap. The device gets used in your session and stays in the bag at home. AAC visual schedules are the bridge that turns a communication tool into part of the day.
If you are an SLP working with an AAC user, you already know the gap. The device gets used in your session and stays in the bag at home. AAC visual schedules are the bridge that turns a communication tool into part of the day. The carryover literature is consistent on what makes the difference, and the scaffold pairs directly with what the family is already doing on the phone.
## What the AAC literature shows
[Ganz and colleagues 2012 meta-analysis](https://pubmed.ncbi.nlm.nih.gov/22146935/) confirmed AAC produces meaningful communication gains for autistic children, with the strongest effects when use is embedded across settings. [Light and McNaughton 2014](https://pubmed.ncbi.nlm.nih.gov/24533895/) frame AAC competency as four threads, operational, linguistic, social, and strategic, rather than a single device behavior. The [ASHA Practice Portal](https://www.asha.org/practice-portal/professional-issues/augmentative-and-alternative-communication/) recommends embedded modeling across the day, not isolated drill blocks. The intervention common denominator is the same. Communication grows where the device shows up in real life, not where it sits next to the snack.
## Why the device gets stranded between sessions
Three failure modes you have probably seen.
1. **The home program lives in your head.** You know which icons to model at breakfast. The family does not. The carryover plan is implicit, so it does not run.
2. **The day does not signal the device.** The AAC user picks up the device when prompted, not when the moment calls for it. Without an anchor, the device drifts.
3. **Modeling fatigue is real.** Aided language stimulation works, but a parent running it across an entire day with no scaffolding burns out by Wednesday.
## Where AAC visual schedules earn their keep
Pair each daily routine step with the icons the child would use to comment, request, or label. The 10:30 snack card carries SNACK, MORE, ALL DONE. The bath card carries WATER, HOT, BUBBLES. The family is not generating language load on top of running the routine. The visual schedule is the prompt. The icons are pre-staged for the parent to model.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for the home program problem. The visual schedule lives on the family's phone, the photos are of the actual child in the actual home, and the icons you want modeled can be placed inside the routine step where they are most natural. The clinical work stays yours. The communication practice gets the density it needs.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would run between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Fireworks and Autism: A Parent's Prep Guide for the Fourth
Published: 2026-05-28
URL: https://vizyplan.com/blog/fireworks-and-autism-parent-prep-guide
Category: Parenting
Author: Justin Bowman
> Your neighborhood is already stockpiling for the Fourth, and you can feel the dread building. Fireworks and autism can be one of the hardest sensory collisions of summer. Here is what research says about noise sensitivity and the prep that helps.
Your neighborhood is already stockpiling for the Fourth, and you can feel the dread building. Fireworks and autism can be one of the hardest sensory collisions of the summer. The bangs are loud, the timing is unpredictable, and the social pressure to "just bring the kids" is real. The auditory research is clear about why this combination is so brutal, and the prep steps that lower the cost are concrete.
## Why fireworks and autism are such a sensory collision
[Stiegler and Davis 2010](https://pubmed.ncbi.nlm.nih.gov/19948770/) documented sound sensitivity in autistic children at far higher rates than the general pediatric population. [Tomchek and Dunn 2007](https://pubmed.ncbi.nlm.nih.gov/17436841/) catalogued atypical sensory processing in more than 95 percent of the autistic children in their sample, with auditory differences among the most common. Fireworks combine three of the hardest auditory features for an autistic nervous system at once. The decibel level is high, the timing is unpredictable, and the startle reflex is already on a hair trigger. The [CDC](https://www.cdc.gov/niosh/topics/noise/) puts consumer fireworks at the source between 140 and 150 dB. The [AAP](https://www.healthychildren.org/) recommends hearing protection at any sustained exposure above 85 dB.
## What helps before the night arrives
Three prep moves that lower the cost.
1. **Hearing protection that fits.** Over-ear protective muffs rated NRR 25 or higher cut the peak intensity enough that the startle does not land. Trial them at home for a week before the event so the muffs themselves are not a new sensory load.
2. **A visual preview of the night.** A short [social story](/blog/social-stories-autism-guide) walking through the order of events, what the booms will sound like, where the exits are, and what your child can do when overwhelm starts. The preview gives the nervous system a rehearsal before the live exposure.
3. **A pre-built exit plan.** Decide before you leave the driveway what "we are done" looks like and where you will go. A clear exit is what makes the event survivable. The threat of being stuck is often louder than the booms themselves.
## What helps in the moment
A visible countdown, a safe corner away from the launch site, and a parent who is not pretending it is fine. Children regulate off the parent's nervous system. Pretending the noise does not affect you signals to your child that distress is not allowed. Naming it, "the next one is going to be loud, I have the muffs ready," is the regulation your child is using to gauge the room.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad for moments like these. Drop a social story for the Fourth into the day view, add a visual exit plan, and your child gets to rehearse the night before it arrives.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the noise prep before the Fourth lands. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Executive Function Visual Sequences: An OT's Guide to Task Initiation
Published: 2026-05-27
URL: https://vizyplan.com/blog/executive-function-visual-sequences-ot
Category: For Providers
Author: Justin Bowman
> Executive function is the lane every OT is working in even when the IEP does not name it. Written for the OT building EF scaffolding that travels home with the family. Here is the literature and the visual sequence bridge.
If you are an OT carrying a caseload of kids who "just cannot get started," executive function is the lane you are already working in even when the IEP does not name it. Executive function visual sequences are the scaffold that converts task initiation, sequencing, and time perception from invisible cognitive demands into visible, externalized steps. The intervention literature backs this, the AOTA framework names it as scope, and parents describe the same failure mode every week.
## What the literature shows about EF in autism
Demetriou and colleagues' [2018 meta-analysis](https://pubmed.ncbi.nlm.nih.gov/28439101/) confirmed executive function deficits as a transdiagnostic feature of autism, with consistent weaknesses in flexibility, working memory, and task initiation. Dawson and Guare's [Smart but Scattered framework](https://www.smartbutscatteredkids.com/) is the practitioner facing translation most school based OTs already use to map specific EF skills to scaffolds. The [AOTA Practice Framework](https://research.aota.org/ajot/article/74/Supplement_2/7412410010/6691) lists executive function among the client factors and performance skills OT addresses.
The intervention common denominator across these is the same. Replace internal planning load with external scaffolding.
## Why verbal prompts make EF harder, not easier
Three failure modes when the family relies on words alone:
1. **Verbal prompts depend on the EF the child does not have.** Asking a child to "remember the next step" assumes intact working memory. The client you are treating does not have it. The prompt is the wrong currency.
2. **The cascade is depleting.** Parents who issue ten prompts before breakfast burn out by Tuesday. The intervention fails because the home program is unsustainable, not because the child cannot do the routine.
3. **The signal is invisible after it lands.** A prompt spoken at 7:02 a.m. is gone by 7:03. The child has nothing to refer back to and the parent has to spend the prompt again.
## Where executive function visual sequences earn their keep
A six step picture by picture morning sequence converts "do your routine" (a planning task the child cannot execute) into "look at step 1, now step 2." [Visual activity schedules are rated EBP](https://pubmed.ncbi.nlm.nih.gov/25081593/) for exactly this reason. The sequence offloads working memory to the environment and replaces the parent's voice as the prompt source. Task initiation gets cheaper because the next step is visible without anyone having to speak.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for the home program problem. The sequences live on the family's phone, the photos are of the actual child in the actual home, and the prompt cascade does not have to carry the routine. The clinical work stays yours. The scaffold travels with the family.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would run between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Interoception Visual Cues: An OT's Guide to Body Awareness
Published: 2026-05-26
URL: https://vizyplan.com/blog/interoception-visual-cues-ot-body-awareness
Category: For Providers
Author: Justin Bowman
> Interoception is the sense your families are not naming when they describe meltdowns, toileting accidents, picky eating, and the kid who runs himself into exhaustion. Written for the OT building body awareness as an actual program, not a buzzword.
If you are an OT, interoception is the sense your families are not naming when they describe meltdowns, toileting accidents, picky eating, and the kid who runs herself into exhaustion before she notices she is tired. Interoception visual cues are the scaffolding that makes the eighth sense teachable in a way a sensory diet alone cannot. The literature on autistic interoception has gotten tighter in the last decade, and OT scope of practice is squarely in this lane.
## What the literature says about interoception in autism
Schauder and colleagues' [2015 study](https://pubmed.ncbi.nlm.nih.gov/25498876/) found measurable differences in interoceptive accuracy between autistic and neurotypical children. DuBois and colleagues' [2016 review](https://pubmed.ncbi.nlm.nih.gov/27269967/) cataloged the same disruption across studies and proposed it as a foundation under emotion regulation difficulties. Murphy and colleagues' [2017 lifespan paper](https://pubmed.ncbi.nlm.nih.gov/28344070/) frames interoception as a learned pattern recognition skill, not a fixed capacity. Kelly Mahler's [interoception curriculum](https://www.kelly-mahler.com/) translates this into the clinical scaffold most OTs working in this space already use. The [AOTA Practice Framework](https://research.aota.org/ajot/article/74/Supplement_2/7412410010/6691) lists interoception within OT scope.
## Why "notice your body" does not work on its own
Three failure points:
1. **The cue is internal and invisible.** Asking a child to notice a signal he cannot reliably perceive is asking him to perform the missing skill, not build it.
2. **The teaching window is fleeting.** Interoceptive moments come and go in seconds. By the time the parent says "are you hungry?" the meltdown is already underway.
3. **The pattern needs density.** Pattern recognition requires repeated, anchored exposures across days. A clinic hour a week cannot supply that.
## Where interoception visual cues earn their keep
Pair the body signal with a visible, recurring anchor in the day. The 10:30 snack card on a daily planner doubles as a check-in cue: "look at your stomach. Are you hungry?" Over weeks, the snack image, the time of day, and the body signal start to associate. The same logic applies to hydration, bathroom routines, regulation breaks, and bedtime fatigue cues. The planner becomes the moment by moment interoception trainer your in-clinic work points toward.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for the carryover problem. Each anchor lives inside the day view, the photos are of the actual child in the actual environment, and the family runs the rhythm you designed. The clinical work stays yours. The interoception practice gets the density it needs to lay down.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would experience between visits. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Gestalt Language Processors and Visual Scripts: An SLP Field Guide
Published: 2026-05-25
URL: https://vizyplan.com/blog/gestalt-language-processors-visual-scripts-slp
Category: For Providers
Author: Justin Bowman
> Gestalt language processors need a stable corpus of context anchored scripts to move through NLA Stage 1 and 2. Written for the SLP whose home programs lose the NLA thread between sessions. Here is what the literature says and where a visual planner fits.
If you are an SLP, you have probably watched a child repeat a chunk of a movie line, an ad jingle, or a phrase from a parent, perfectly intoned and contextually meaningful. Gestalt language processors are the kids the Natural Language Acquisition framework was written for, and the home implementation side of that framework still lags behind the in-session work. Marge Blanc reframed echolalia decades after Prizant's 1983 [seminal paper](https://pubmed.ncbi.nlm.nih.gov/6620989/) called it functional communication, and the literature has only gotten clearer since.
## What the literature says about gestalt language processors
Stiegler's 2015 [review of the echolalia evidence base](https://pubs.asha.org/doi/10.1044/2015_AJSLP-14-0166) concluded that echolalia is functional, that it predicts later self-generated language, and that the field needs to stop treating it as a deficit. The Natural Language Acquisition framework operationalizes this into eight stages, with Stage 1 (whole gestalts) and Stage 2 (mitigated gestalts) being the most carryover sensitive. The child is acquiring a corpus of chunks she can later remix into self-generated language. The size and quality of that corpus depend on what you and the parent put in front of her between sessions.
## Why printed scripts and clip art rarely move the needle
Three structural reasons:
1. **No context anchor.** A printed script in a folder is decontextualized from the moment it is supposed to serve. Stage 1 gestalts are bound to their original context. If the picture is generic clip art, the gestalt does not stick.
2. **No repetition cadence.** Stage 1 acquisition depends on hearing the same chunk in the same situation across days. A weekly session cannot supply that density.
3. **No parent scaffolding.** Most parents have not heard of NLA. They correct echolalia as if it were a problem to solve, which models the wrong response and breaks the script before it can mitigate.
## Where visual scripts paired with a daily planner fit
[Visual activity schedules are rated EBP](https://pubmed.ncbi.nlm.nih.gov/25081593/) for generalization. Pair them with NLA aligned scripts and you have a carryover medium that works at home. Each daily slot becomes a stable script anchored to a real photo of the child's actual environment. "First we brush teeth, then we eat breakfast" repeats every morning, in the same order, with the same image. Over weeks, the gestalts attach to context the way NLA predicts they will.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was co-built by a licensed SLP for the carryover problem. Personalized photos of each client, a shared family calendar, one-tap social stories for the recurring routines you flagged in session. The clinical NLA work stays yours. The script corpus does not have to be assembled by hand on a printer.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would see between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Alexithymia in Autistic Children: When They Can't Name What They Feel
Published: 2026-05-25
URL: https://vizyplan.com/blog/alexithymia-autistic-children-emotion-words
Category: Parenting
Author: Justin Bowman
> How do you feel? lands as a blank stare. Your child clearly feels something, but cannot name it. The missing word for what is happening here is alexithymia, and it shows up in roughly half of autistic kids. Here is what helps build the translation step.
"How do you feel?" lands as a blank stare. Your child clearly feels something. They are flushed, withdrawn, or about to break, but they cannot tell you what they feel. The missing word for what is happening here is alexithymia, and alexithymia in autistic children is one of the most overlooked pieces of the emotion-regulation puzzle. About half of autistic individuals meet alexithymia threshold compared to roughly five percent of the general population, per the [Kinnaird, Stewart and Tchanturia 2019 meta-analysis](https://pubmed.ncbi.nlm.nih.gov/30797104/). That is not your child hiding their feelings. It is the translation step that did not happen.
## What alexithymia actually is
Alexithymia, literally "no words for feelings," is a measurable difficulty identifying and describing one's own internal emotional state. It is not autism itself. [Bird and Cook 2013](https://pubmed.ncbi.nlm.nih.gov/23880881/) made the case that alexithymia, not autism per se, drives many of the emotion-recognition difficulties the field once attributed to autism directly. [Cook and colleagues 2013](https://pubmed.ncbi.nlm.nih.gov/23528789/) replicated the finding that alexithymia, not autism, predicts poor recognition of emotional facial expressions.
In practice this means a child can feel intensely without being able to label what they feel, and can struggle to read the emotions on faces in front of them. Both directions of the translation step are affected.
## Why alexithymia in autistic children matters for everyday regulation
If your child cannot identify hunger as hunger, frustration as frustration, or overwhelm as overwhelm, every intervention that depends on naming the feeling first stalls. "Use your words" assumes the words exist. "Take a deep breath when you feel anxious" assumes anxiety has been recognized in time. The skills we ask of regulated kids depend on a translation step the alexithymic child has not finished building.
Three signals to watch for:
1. **Big body, no name.** Visible distress, no language to describe it.
2. **Surprise meltdowns.** The collapse arrives with no warning the child could articulate.
3. **Face confusion.** Your child reads faces inconsistently or asks "are you mad?" when you are not.
## What helps build the translation step
The intervention literature points to externalizing the missing skill. You cannot will it into existence, but you can scaffold it with visible cues.
**Visual emotion cards.** A small set of faces and feeling words your child can point to instead of name.
**Body-first labeling.** "Your stomach feels tight. That is sometimes nervous." Anchor the word to the body sensation. The interoceptive bridge is what alexithymic kids are missing.
**Pre-name the day's rough spots.** Walking through the morning with a card for "frustrating" and a card for "tired" gives your child a vocabulary they can grab in the moment.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad for moments like these. The visible day, the emotion-tracking cards, and one-tap social stories give your child the scaffolding the translation step needs while it develops.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the emotion translation scaffolding in 10 minutes. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## From Eval to Monday Morning: Operationalizing Neuropsych Recommendations
Published: 2026-05-24
URL: https://vizyplan.com/blog/neuropsych-eval-autism-monday-morning-recommendations
Category: For Providers
Author: Justin Bowman
> Neuropsych eval recommendations are only as useful as Monday morning. Written for the neuropsychologist whose families come back six months later and have not implemented anything. Here is the operationalization gap and how visual planning helps close it.
If you are a neuropsychologist, you already know the recursive frustration. You write a 40-page evaluation report with carefully calibrated executive function recommendations. The family thanks you, leaves, and comes back six months later and almost nothing has been implemented. The neuropsych eval recommendations gap is the operationalization gap, and it is one of the most ownable problems in the field. Here is what the literature points to and what bridges it in practice.
## The literature on EF in autism
The MDPI *Brain Sciences* 2020 review on [executive function in autism](https://www.mdpi.com/2076-3425/10/2/120) confirms what your assessment battery already shows you: kids on the spectrum present heterogeneous EF profiles, with consistent deficits in flexibility, working memory, and task initiation across studies. The intervention literature, summarized in resources like *Best Practices in School Neuropsychology* chapter on [assessing and intervening with EF disorders](https://onlinelibrary.wiley.com/doi/abs/10.1002/9781119790563.ch31), is equally clear that intervention has to happen in the environment, not the assessment room. A recommendation in a report is not an intervention.
## Why "use a visual schedule" rarely translates
Three failure modes:
1. **The recommendation is abstract.** "Improve task initiation" lands as a sentence in a section the parent skims. It does not turn into a behavior.
2. **The family has no scaffolding.** Even strong recommendations like "use a first-then board" assume the family knows what one is, can build it, and will keep using it consistently. Most cannot.
3. **The handoff is one-way.** The eval ends, the parent leaves with the report, and there is no feedback loop showing whether anything is being implemented.
The result is a beautifully written report that does not move the kid.
## What operationalization actually looks like
The neuropsychs whose recommendations stick do three things differently:
**Translate each recommendation into a routine.** "Improve task initiation in the morning" becomes a six-step picture-by-picture morning routine the parent can run on day one. "Increase predictability around transitions" becomes a first-then visual the child sees before every change.
**Give the family a tool, not a paragraph.** The [generalization literature on visual activity schedules](https://pubmed.ncbi.nlm.nih.gov/25081593/) is clear that the support has to live in the environment, not on paper.
**Build a feedback loop.** A planning app the family uses produces actual data on routine completion that you can review at the follow-up, instead of relying on parent recall.
## Where a visual planner fits the report
A planning app is not a neuropsychological intervention. It is the operationalization layer between your report and the family's Monday morning. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for this gap specifically. Routines, first-then boards, social stories, and a shared family calendar. The family leaves your office with a tool, not a 40-page document and a wish.
The diagnostic work stays yours. The implementation gap doesn't have to.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would use between evaluations. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Rejection Sensitive Dysphoria in ADHD and Autistic Kids: A Parent's Guide
Published: 2026-05-24
URL: https://vizyplan.com/blog/rejection-sensitive-dysphoria-adhd-autism-kids
Category: Parenting
Author: Justin Bowman
> That tiny correction at the dinner table that sent your kid spiraling for an hour. If you have wondered whether the response was disproportionate, rejection sensitive dysphoria is the term you may be looking for. Here is what clinicians say.
That tiny correction at the dinner table that sent your kid spiraling for an hour. That comment from a friend that turned the whole afternoon. That feedback from a coach that ended the entire activity. If you have wondered whether the response was disproportionate or just how your child experiences these moments, rejection sensitive dysphoria is the term you may be looking for. It is one of the most discussed concepts in ADHD parenting in the last several years, and the same pattern shows up in many autistic kids too.
## What rejection sensitive dysphoria actually is
Rejection sensitive dysphoria, often called RSD, refers to extreme emotional sensitivity to perceived rejection, criticism, or failure. It is not a formal DSM diagnosis but is widely used clinically, particularly in ADHD care. The term was popularized by Dr. William Dodson, whose clinical work and writing in [ADDitude Magazine](https://www.additudemag.com/rejection-sensitive-dysphoria/) brought the concept into mainstream parent vocabulary. Research on rejection sensitivity and ADHD ([Bondu and Esser 2015](https://pubmed.ncbi.nlm.nih.gov/26088137/)) has documented elevated frustration responses and rejection sensitivity in this population.
RSD is not the child being dramatic. It is a nervous system that registers a small social or evaluative cue as a major threat, and responds at that intensity.
## Why it shows up in autistic kids too
The autism research literature does not formally validate RSD as an autism-specific phenomenon, but the same pattern appears in many autistic children. Possible reasons include heightened emotional reactivity, alexithymia making the emotion harder to identify and contain, and a history of social misunderstandings that have trained the nervous system to expect rejection. The result for parents is the same: small events trigger big collapses.
Three patterns to watch for:
1. **Disproportionate response to mild correction.** A reminder to wash hands triggers a 30-minute meltdown.
2. **Avoidance of activities where they might fail.** New things stop being interesting once the risk of being wrong appears.
3. **Repeated reassurance seeking after social interactions.** "Was that okay?" hours after a normal interaction.
## What helps without dismissing the experience
The most effective parent moves do not involve trying to talk the child out of the feeling. They involve preparing the nervous system in advance and validating the experience as it lands.
**Predict the rough spots.** Before a coaching session, a group activity, or a tricky family event, walk through what feedback might sound like and what the child can do with it.
**Name the feeling without minimizing it.** "Your brain is reading that as rejection. That is a real feeling. We can sit with it for a minute."
**Lower demands during recovery.** Once the wave is happening, this is not the moment to teach the lesson. Recovery first, repair later.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad for the predictability layer of this. Visible transitions, social stories for tough situations, and routine recovery anchors so the nervous system has somewhere to land after the wave.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the predictability layer your child's nervous system needs. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Sensory Diets That Survive the Car Ride Home: A Field Guide for OTs
Published: 2026-05-23
URL: https://vizyplan.com/blog/sensory-diet-home-program-OT-survives
Category: For Providers
Author: Justin Bowman
> A sensory diet home program that survives the car ride home is the difference between an evidence-based practice in the clinic and a notebook on the kitchen counter. Written for the OT building home programs that families actually run.
If you are an OT, you already know the gap. Your sensory diet home program is sound on paper, the parent nods through your handout, and a week later the notebook is on the kitchen counter and the routine is back where it started. The 2018 systematic review of [Ayres Sensory Integration (ASI) for children with autism](https://pubmed.ncbi.nlm.nih.gov/30548827/) rated ASI an evidence-based practice for ages 5 to 12, and AOTA's 2025 [school-based ASI call to action](https://research.aota.org/ajot/article/79/1/7901347020/26009/Occupational-Therapy-Using-Ayres-Sensory) reinforces it. But every OT carrying a caseload knows the same thing: the intervention is evidence-based in the room you control, not always in the rooms you do not.
## Why home implementation stalls
Three repeating patterns:
1. **The handout outlives the conversation.** What you explained in the clinic gets lost when the parent is at the dinner table at 7 p.m. with two siblings and a meltdown brewing.
2. **The activities are unanchored.** "Heavy work twice a day" without a visible anchor in the day rarely happens consistently. The brain that needs the sensory diet most is also the brain least likely to spontaneously schedule it.
3. **Visual sequencing for ADLs gets dropped.** Dressing, brushing, bathing, transitions between activities. These are the places where regulation actually breaks down. A sensory diet that does not show up at these moments is missing the highest-impact slot.
## What helps the handout survive the car ride home
The strongest carryover I see comes from OTs who do three things differently:
**Anchor every sensory activity to an existing routine.** Heavy work before getting dressed. Vestibular input as part of morning transition. Tying the activity to a visible step in the day puts it on autopilot.
**Turn each ADL into a visual sequence.** Visual activity schedules are [rated EBP](https://pubmed.ncbi.nlm.nih.gov/25081593/) for a reason. A picture-by-picture dressing routine that lives in the parent's pocket has a much higher implementation rate than a paragraph in a binder.
**Give the parent a tool, not a worksheet.** The recent [telehealth ASI adaptation](https://pubmed.ncbi.nlm.nih.gov/38900915/) literature points the same direction: parent-coaching plus a tool the parent can run beats a clinician-only protocol the parent is supposed to imitate.
## Where a visual planning tool fits
A planning app is not sensory integration therapy. It is the home-programming infrastructure your families use to actually run the diet you designed. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed SLP for the carryover problem specifically. Each ADL becomes a visual sequence with the actual child's photos, the sensory anchors live inside the day view, and you can hand the family a tool that survives the car ride home.
The clinical work stays yours. The handout problem doesn't have to.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would experience between visits. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Autistic Burnout in Kids: How to Recognize the Crash Before It Hits
Published: 2026-05-23
URL: https://vizyplan.com/blog/autistic-burnout-in-kids-warning-signs
Category: Parenting
Author: Justin Bowman
> That sudden withdrawal, the loss of skills you knew your child had. If you have wondered whether this is regression or just a hard week, the term you may be searching for is autistic burnout in kids. Here is what the research says and what helps.
That sudden withdrawal, the loss of skills you knew your child had, the days they cannot get dressed or speak in sentences the way they did last month. If you have wondered whether what you are seeing is regression or just a hard week, the term you may be searching for is autistic burnout in kids. It is a real, researched phenomenon, and parent recognition is the hinge between treating it as a behavior problem and treating it as the recovery crisis it actually is.
## Autistic burnout in kids: what the research says
The foundational paper on autistic burnout, [Raymaker and colleagues 2020](https://pubmed.ncbi.nlm.nih.gov/32851204/), defined the experience as "having all of your internal resources exhausted beyond measure." [Higgins and colleagues 2021](https://pubmed.ncbi.nlm.nih.gov/34169759/) refined the definition through experts with lived experience, identifying chronic exhaustion, skill loss, and reduced tolerance to stimuli as the three core features. [Mantzalas and colleagues 2022](https://pubmed.ncbi.nlm.nih.gov/35262292/) built a conceptual model of the risk and protective factors. The literature is built on adult samples, but pediatric clinicians increasingly recognize the same pattern in children, particularly those who have been masking heavily at school.
Burnout is not the same as a meltdown, not the same as ADHD shutdown, not the same as depression. It is the collapse that follows months or years of unsustainable load.
## How to spot it before the deepest crash
Three signals parents tend to miss until burnout is fully set in.
**Skill regression that does not make sense.** Things your child could do a month ago they cannot do today. Dressing, reading, holding a conversation. Skills do not just disappear unless something is depleting the system that holds them.
**Sensory tolerance dropping.** Sounds, textures, and lights that used to be background are suddenly unbearable. Reduced tolerance to stimuli is one of the three core features in the research.
**Mask collapse.** The child who held it together at school all year is suddenly unable to. The mask is not laziness or defiance. It was the suppression layer that paid the cost of fitting in, and the bill has come due.
## What lowers the load
The recovery literature consistently points to demand reduction, predictability, and sensory regulation. None of it requires a new diagnosis. It requires giving your child a smaller, more visible day for a stretch of weeks. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad for the days when the load needs to come down. A short, visible routine with the demands trimmed. Personalized photos. Predictable transitions. The scaffold your child has been carrying internally moves outside the body for a while, so the internal resources can refill.
Autistic burnout in kids is not a failure of parenting or of the child. It is what happens when capacity is spent. Recognizing it is the first move that actually helps.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a lower-demand day in 10 minutes. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Speech Therapy Carryover Gap: Why It Stops Working at the Front Door
Published: 2026-05-22
URL: https://vizyplan.com/blog/speech-therapy-carryover-gap-slp-guide
Category: For Providers
Author: Justin Bowman
> The speech therapy carryover gap is the structural reason a beautifully designed home program never gets implemented. Written for the SLP whose families did not do the worksheet. Here is what the literature says and what we built to help.
If you are an SLP and you have ever sent a family home with a beautifully designed program that never got implemented, this one is for you. The speech therapy carryover gap is not a parent motivation problem and not a clinician design problem. It is structural. Stokes and Baer flagged it in 1977 and the field's literature reviews keep flagging it now. Here is what the gap looks like, why parent-facing handouts rarely close it, and where a visual planning layer fits.
## The gap is the entire field's weak point
The National Professional Development Center on ASD rates [visual supports as an evidence-based practice](https://files.eric.ed.gov/fulltext/ED595398.pdf), and visual activity schedules are [an EBP for generalization](https://pubmed.ncbi.nlm.nih.gov/25081593/) of academic and daily-living skills. But the evidence base is built on intervention environments. The carryover problem is what happens when you, the clinician, are no longer in the room. Recent reviews on [visual schedules and on-task behavior](https://www.tandfonline.com/doi/full/10.1080/20473869.2024.2402124) consistently note that systematic instructional procedures plus the visual support drive the effect. Hand a parent a worksheet and ask them to be the systematic instructional procedure between sessions, and the effect collapses.
## Why home programs fail
Three structural reasons:
1. **Format mismatch.** Your worksheet lives in a folder. The parent lives on their phone. The carryover skill never makes it to where the parenting actually happens.
2. **Generic content.** Clip art doesn't land for many of your clients (the [mirror neuron research](https://pubmed.ncbi.nlm.nih.gov/30548827/) on self-recognition predicts this). The visuals you teach with in session feel different from what gets sent home.
3. **Parent executive function.** The families who most need your home program are also the families most depleted by autism parenting. A 40-minute home program adds load they cannot reliably absorb.
## The shift: from content creator to consultant
The most successful SLPs I have worked with stopped trying to be the content factory between sessions and started being a consultant. Their job becomes: choose the right targets, coach the parent in using the right tools, and verify carryover from the data the parent brings back. The home program is the tool. The clinician is the strategist.
## Where a visual planner fits
A planning app cannot replace what you do in session. But it can be the carryover infrastructure your families actually use between sessions. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was co-built by a licensed SLP for the explicit purpose of closing the gap between the goal you wrote down and the routine the parent runs at home. Personalized images of each client, shared calendar with the family, one-tap social stories for the situations you flagged in session. The clinical work stays yours. The carryover scaffolding doesn't have to.
If carryover is where your families are stalling, it is worth a closer look.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** See what your families would see between sessions. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad and a licensed speech-language pathologist who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Summer Break for Autistic Kids: How to Survive the Routine Cliff
Published: 2026-05-22
URL: https://vizyplan.com/blog/summer-break-autistic-kids-routine-cliff
Category: Daily Routines
Author: Justin Bowman
> The school year ends and the structure holding your autistic child together disappears overnight. Here is what the research says about the summer routine cliff and what helps before it arrives.
The school year ends and the structure that has been holding your autistic child together for nine months disappears overnight. Summer break for autistic kids is the routine cliff every autism family knows, and not because the days are long. The predictability that schools provide is the scaffolding your child has been leaning on, and when summer pulls it, the regression risk is immediate. The good news is the same research that explains why summer is hard also points to what helps.
## Why summer break for autistic kids hits harder
The "summer slide" literature on academic regression has been around for decades. For autistic and ADHD children, the regression is not just academic. It is behavioral, social, and regulatory. Predictability and routine are well-documented protective factors for autistic children, and visual activity schedules are [rated as evidence-based practice](https://pubmed.ncbi.nlm.nih.gov/25081593/) for supporting daily living and academic skills. Take the schedule away and the supports the schedule was carrying go with it.
The cliff has three pieces working at once:
1. **Routine disappears.** Wake time, lunch time, transition cues, after-school decompression. Gone overnight.
2. **Sensory environments shift.** Summer means more crowds, more travel, more new places, more pool noise and grocery store lines that school had insulated against.
3. **Social demands change.** School friendships pause. Camps, neighborhood kids, and unstructured play introduce novel social demands without the structure school provided.
## What helps before the cliff arrives
The strongest summers start before school ends, not after the meltdown on day three. The autism families who do best in summer do three things differently.
**Keep a visible day, even if it is looser.** A morning routine card, a lunch anchor, a quiet hour, an evening wind-down. Less structure than school, but still visible. The brain that needed the school schedule still needs an anchor.
**Pre-teach the new environments.** Before the pool, before the camp drop-off, before the family road trip, walk through what will happen with pictures. The [Autism Speaks summer guidance](https://www.autismspeaks.org/expert-opinion/autism-summer-fun-tips) emphasizes preparation as the highest-leverage variable.
**Plan decompression on purpose.** After every novel outing, build in recovery time. The kid who had a great morning at the splash pad still needs a quiet afternoon. Burnout is built across small moments that did not get a buffer.
## Where a visual planner fits the summer cliff
A summer visual schedule does not have to replicate school. It has to give your child a visible anchor. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad for exactly this kind of stretch. A morning routine, a midday anchor, a wind-down. Photos of your actual child. One-tap social stories for the new pool, the new camp, the cousin's birthday. The structure shrinks when it can. It does not disappear.
The cliff is real. Walking down it on a path you built is different than falling off it.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build your child's summer schedule in 10 minutes. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Six Months With Sawyer: What Changed When the Day Became Visible
Published: 2026-05-21
URL: https://vizyplan.com/blog/six-months-sawyer-autism-routine-case-study
Category: Founder Story
Author: Justin Bowman
> This is the autism morning routine case study I wish someone had handed us the week after diagnosis. One family. Six months. What changed, what did not, and what we learned about building the day in pictures.
This is the autism morning routine case study I wish someone had handed us the week after my son's diagnosis. One family. Six months of visual scheduling. Honest about what changed, honest about what did not. We are not running a clinical trial here. We are sharing what happened in our kitchen so other families have a reference point that is not a sales pitch.
## Before: laminated cards and a lost binder
My son was nonverbal until almost three. Our first attempt at visual scheduling was the standard kit a lot of families end up with. Laminated picture cards from a binder, a velcro strip on the fridge, a printed routine taped above the toilet. It worked in theory and failed in practice. Cards went missing. The routine was generic clip art that he did not recognize as his routine. Mornings still ended with both of us crying. We were the audience the National Professional Development Center on ASD had in mind when it rated [visual supports as an evidence-based practice](https://files.eric.ed.gov/fulltext/ED595398.pdf), but the implementation was eating us alive.
## Month one: the morning becomes visible
We built a six-step morning routine with photos of him doing each step. His own toothbrush. His own backpack. His own front door. The first week was just curiosity. By the end of month one he was tapping the next step on the iPad before I prompted him. The verbal narration count dropped sharply. We started keeping the schedule for the bedtime routine too.
## Month three: transitions softened, not solved
By month three the transition meltdowns had not vanished. What had changed is that fewer transitions felt like surprises. He was checking the day view multiple times in the morning on his own. He started bringing the iPad to me to "show what is next." The data echoes the [literature on visual schedules](https://www.tandfonline.com/doi/full/10.1080/20473869.2024.2402124). Academic-related on-task behavior tends to rise once the schedule is reliable, though it is not a switch you flip.
## Month six: generalization to new places
The honest payoff at six months was not a specific behavior. It was that we could take the schedule on the road. A trip to grandma's house got a picture itinerary. The dentist visit got a social story the week before. He was using the visual format outside our house, which is where the [generalization research](https://pubmed.ncbi.nlm.nih.gov/25081593/) on visual activity schedules said it eventually goes.
## What did not change
Hard days are still hard. Sensory overload still happens. The schedule did not fix dysregulation. It is a planning tool, not a therapy. We say that loudly because too many parent-facing apps imply otherwise.
What changed is that the day became something he can see, which is the whole reason we built [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) in the first place.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Try anonymously, no email or credit card required. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Is It Safe to Use AI Images of Your Autistic Child? Our Honest Stance
Published: 2026-05-20
URL: https://vizyplan.com/blog/ai-images-autism-child-safety-ethics
Category: Privacy & Safety
Author: Justin Bowman
> AI images autism safety is the first question every smart parent asks before uploading a photo of their child. We asked it about our own son first. Here is what we found and what we will not do.
AI images autism safety is the first question every thoughtful parent asks before they upload a reference photo of their child. We asked the same question about our own son before we built the feature. Here is what we found, what we do about it, and what we will not do.
## Why the question is real
A 2025 review in *Frontiers in Psychiatry* on [AI in autism intervention](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2025.1513809/full) lays out the legitimate concerns directly: data privacy for vulnerable populations, the risk of biased models trained on non-representative datasets, and child-safety considerations specific to generative systems. The Australian eSafety Commissioner's brief on [generative AI and child safety](https://www.esafety.gov.au/newsroom/blogs/generative-ai-and-child-safety-a-convergence-of-innovation-and-exploitation) reinforces that children deserve extra protection at every layer of the stack. These are not paranoid concerns. They are the right concerns.
## Why we still generate personalized images
The same body of research that flags risks also flags the benefit. UC San Diego mirror neuron work shows that autistic kids respond most strongly to images of themselves and their own world, with weaker activation for stock visuals. The NPDC on ASD rates [visual supports as an evidence-based practice](https://files.eric.ed.gov/fulltext/ED595398.pdf) across ages 3 to 22, and the personalization effect is real. A picture of *your* child brushing teeth lands where clip art does not.
So the question is not "AI image or no AI image." It is "AI image with what guardrails." That is where the ethics live.
## The guardrails we put around it
Three rules govern how [VizyPlan](https://vizyplan.com) handles your child's photo:
1. **The reference photo stays on your account.** It is never used to train a public AI model and never shared with other users. Generated images are stored privately to your profile so only your family and people you explicitly invite can see them.
2. **No outside generation paths.** AI images created in [VizyPlan](https://vizyplan.com) are bounded to age-appropriate activity scenes for your child's actual routines. We do not provide an open prompt box that could be misused, by design.
3. **COPPA-aligned by default.** Every flow that touches a child's data follows the Children's Online Privacy Protection Act framework. The full policy lives at [vizyplan.com/privacy](/privacy).
## What we will not do
We will not train a model on millions of children's faces. We will not sell or share photos with advertisers or third-party data brokers. We will not generate public-facing imagery that includes your child. If those lines are ever crossed, we expect parents to leave and tell other parents to leave. That is the right outcome.
The trust we want is earned by what we refuse to do.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Try anonymously, no email or credit card required. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Four Rules Behind Our Autism Visual Planner Design
Published: 2026-05-19
URL: https://vizyplan.com/blog/four-rules-autism-visual-planner-design
Category: Founder Story
Author: Justin Bowman
> Before we decided what to build into VizyPlan, we decided what NOT to build. Four design rules grade every feature, anchored in the visual supports literature and what worked for our own family.
Before we wrote a line of code for our autism visual planner design, we wrote down four rules. They were the answer to a different question than most product teams ask. Not "what can we build?" but "what would we refuse to ship even if it would sell?" Every feature in [VizyPlan](https://vizyplan.com) today still has to pass all four.
## Rule 1: The plan lives outside the child's head
The brain that struggles with executive function does not need more reminders shouted from across the room. The National Professional Development Center on ASD rates [visual supports as an evidence-based practice](https://files.eric.ed.gov/fulltext/ED595398.pdf) across ages 3 to 22, spanning social, communication, behavior, and academic domains. The mechanism is simple: when the day is visible, working memory load drops, transitions soften, and the child gets to participate in their day instead of being narrated through it. Anything we ship has to make the day more visible, not more verbal.
## Rule 2: The child must see themselves
Generic clip art fails the recognition test. UC San Diego mirror neuron research shows that autistic kids respond most strongly to images of themselves and their own world, with weaker activation for familiar people and weakest for strangers. A stock cartoon of a toothbrush is not your child's toothbrush. The whole [personalized image generation system](/blog/personalized-ai-images-autism-visual-schedules) in [VizyPlan](https://vizyplan.com) exists to honor that finding.
## Rule 3: Nothing can feel clinical
Therapy rooms are full of beige binders for a reason, and the reason is not that children like beige binders. If a feature looks like a clinician's clipboard, a tired parent will not use it at 6 a.m. and an exhausted child will not look at it twice. The autism visual planner design is intentionally warm, picture-first, and free of jargon. The Calm screen looks like a deep breath. The advocate tool looks like a parent's pocket, not a lawyer's file.
## Rule 4: A tired parent has to set it up in ten minutes
Most parent-facing tools assume a level of executive function their target audience does not have on a hard day. We test every flow against the "kitchen floor at 6 a.m." standard. If it cannot be set up in ten minutes by someone who slept four hours, it does not ship.
Every roadmap decision still gets graded against these four. The rules are the why.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Try anonymously, no email or credit card required. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Reward Effort, Not Compliance: Autism Sticker Chart Alternative
Published: 2026-05-18
URL: https://vizyplan.com/blog/autism-sticker-chart-alternative-small-wins
Category: Rewards & Motivation
Author: Justin Bowman
> An autism sticker chart alternative that celebrates effort instead of scoring compliance. Built so the wins stay visible and the misses stay quiet.
We needed an autism sticker chart alternative because the sticker chart was lying to us. It told our son he was doing well or he was failing, and neither was actually true. He was learning. Some days the routine landed. Some days the world was too loud. The chart could not tell the difference, so we stopped using it.
A reward system that only rewards compliance teaches a child to mask. A reward system that celebrates effort teaches a child to keep trying. We wanted the second one.
## Why an Autism Sticker Chart Alternative Has to Reward Effort
Research on motivation, the self-determination work going back to Deci and Ryan, keeps landing in the same place. Children who feel autonomous and competent keep going. Children who feel scored stop. The difference is whether the reward is something the child chose or something an adult imposed.
## How VizyPlan Stickers Work
Your child earns a sticker for completing an activity. The sticker goes onto their own collection, on their own profile, with their own color theme. There is no red mark for missing one. There is no public chart on the wall for a sibling to see. The wins are visible and the misses are quiet.
Then the sticker becomes something. The child chooses what to redeem it for, from a list you set together. Extra story at bedtime. Pick the music in the car. A trip to the park on Saturday. Small things that feel like agency.
## What That Builds Over Time
Momentum. Not a leaderboard. A child who sees a row of stickers from this week and says "I did that" is a child who will try again on Monday. That is what we wanted for our own son, and that is what the system is built to grow.
If the sticker chart on your fridge has stopped working, this is the gentler version. Built for the way our kids actually feel about being watched.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Replace the fridge chart with a reward system your child actually steers. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Why Autism Morning Routine Help Shouldn't Be the Hardest Part
Published: 2026-05-17
URL: https://vizyplan.com/blog/autism-morning-routine-help-hardest-part
Category: Morning Routines
Author: Justin Bowman
> Planning the day should not be the hardest part of the day. Here is the autism morning routine help we built for our own kitchen floor at 6 a.m.
Planning the day should not be the hardest part of the day. For families of neurodivergent kids it often is. The morning has already happened twice in your head before your feet hit the floor, and by 7:14 it has already gone sideways once.
We needed autism morning routine help that did not require us to be calm at 6 a.m. So we built one we could use ourselves. My wife is a licensed speech-language pathologist. I am the dad on the kitchen floor at sunrise. Between us, we have a lot of bad mornings to draw from.
## Why Autism Morning Routine Help Has to Be Fast
Because the gap between "I should pull up a visual" and "I will just yell again" is about twelve seconds wide. Any tool that takes longer than that to set up is a tool you do not use. The fastest path to a visual schedule has to be faster than the fastest path to losing your patience.
## How First Then AI Works
You tap two activities. Brush teeth, then iPad. Get dressed, then breakfast. The First Then AI generates a calm, child facing card in seconds, with the photo of the real activity on the left and the real reward on the right. No design work. No setup. No clinical jargon. Just the next two steps, visible, in the hand your child is already reaching for.
It is the difference between explaining the morning out loud for the ninth time and pointing at a screen.
## What Changes by Friday
The shouting drops because you are no longer the schedule. The screen is the schedule. You become the calm grown up next to the schedule, which is the role you actually wanted in the first place.
If your mornings feel like the hardest part of the day, you do not need a sticker chart. You need the plan in your child's hand before the meltdown starts.
We built this for our own mornings. It is ready for yours.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build your child's [morning routine](/blog/autistic-child-morning-routine-independence) in under ten minutes with photos from your own home. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Every Kid Deserves a Visual Schedule Autism Brains Trust
Published: 2026-05-16
URL: https://vizyplan.com/blog/visual-schedule-autism-day-that-makes-sense
Category: Visual Schedules
Author: Justin Bowman
> A visual schedule autism kids will actually follow uses photos of their own world, not generic clip art. Here is why personalized images change the day.
Every kid deserves a day that makes sense to them. That is the whole reason we built a visual schedule autism families can actually use. Not because routines are trendy in parenting books. Because a child who can see what comes next is a child who is not bracing for the next surprise.
Autistic kids think in images first. The world arrives in words at them, and a lot of those words are demands. Get dressed. Hurry up. Time to leave. A day full of verbal commands from people whose voices keep changing pitch is exhausting. A day with a visible plan they can point to is a day they get to participate in.
## Why a Visual Schedule Autism Kids Trust Looks Different
Generic clip art schedules do not work. Research on mirror neuron systems shows that autistic kids respond most strongly to familiar visuals, and especially to images of themselves and their own world. The stock cartoon of a toothbrush does not feel like your child's toothbrush. The photo of their actual blue toothbrush on their actual bathroom counter does.
## How We Built the Day View
Simple on purpose. No clinical icons. No clutter at the edges. A calm gradient background that the eye can rest on. Activities sized large enough for small fingers. Transitions soft enough that moving from one activity to the next does not feel like an alarm going off.
That belief, that simplicity is the gift, runs through every screen. We took it from how my wife structures sessions as a licensed speech-language pathologist, and from what worked for our own son when nothing else did.
## What Your Child Sees
Their face. Their home. Their actual day. A row of activities they can tap, follow, and finish. Built for the way our kids actually think, not the way an adult planner thinks.
A day they can see is a day they can do.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a [visual schedule](/blog/visual-schedules-for-autism) with personalized photos of your own child's world. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Families Deserve a Real Autism IEP Plan, Not Paperwork
Published: 2026-05-15
URL: https://vizyplan.com/blog/autism-iep-plan-not-a-pamphlet
Category: IEP & Advocacy
Author: Justin Bowman
> An autism IEP plan should live in your pocket, not in a drawer. Here is how we turned the wall of paperwork into a plan a parent can actually carry.
A diagnosis comes with pamphlets. So does an IEP meeting. So does a doctor visit, a school transition, a therapy intake. We did not need more paper. We needed an autism IEP plan we could actually use.
That is the gap we kept hitting. The school team would hand us a forty page document at the end of a meeting. By the time we got home, we had forgotten which goal mapped to which service, which accommodation we had agreed to, and which sentence the speech therapist had said that made us cry in the parking lot.
## Why an Autism IEP Plan Needs to Live Outside the Folder
Because the folder gets put in a drawer. The plan needs to live where the parenting actually happens, on the phone in your pocket, ready when the bus is late and the teacher emails and the question comes up in real time.
## How Vizy Advocate Works
You record the meeting. The Advocate transcribes it, pulls out the goals, the accommodations, the action items, and turns the wall of text into something parent shaped. My wife is a licensed speech-language pathologist, so we built the goal extraction with the same lens she would use in her own sessions. Clear, observable, measurable. The way a goal is supposed to read.
You leave the meeting and you walk out with a plan that is yours, not a binder you have to translate at midnight.
## What You Can Do With It Tomorrow
Forward the summary to grandparents and babysitters. Share the accommodations with a new therapist. Pull up the goals during a hard week and remember what you are actually working toward. Compare last year's [IEP goals](/blog/iep-goals-autism-parents-guide) to this year's in seconds and see what your child has earned.
We believe families deserve real tools, not paperwork. The Advocate is what that belief looks like in your pocket.
If you have an IEP meeting on your calendar, this is the one we built for you.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Walk into your next IEP meeting with a plan, not a binder. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Day After Autism Diagnosis Shouldn't Feel Like a Cliff
Published: 2026-05-14
URL: https://vizyplan.com/blog/after-autism-diagnosis-what-comes-next
Category: Autism Diagnosis
Author: Justin Bowman
> The day after autism diagnosis should not feel like a cliff. Here is the first week we wish someone had handed us, built from what we needed when we lived it.
The day after autism diagnosis should not feel like a cliff. For a lot of families it does. You leave the office with a folder, a few websites, a list of phone numbers with eighteen month waitlists, and the rest of your life. Nobody walks you through what Wednesday looks like.
We know because we lived it. When our son's diagnosis came, we sat in our car in a parking lot and Googled the same things every parent Googles. What now. What do I tell grandma. What do I do tonight at bedtime. The internet had a thousand answers and none of them had a plan.
## What the First Week After Autism Diagnosis Actually Needs
It does not need a five year intervention strategy. It needs a shape for tomorrow. Something visible your child can see. A way to handle the next hard moment. A small win you can both feel by Friday. The brain that just absorbed a major life change does not have room for a binder.
## How We Designed It to Feel
The whole tone of [VizyPlan](https://vizyplan.com) is calm on purpose. No clinical language. No checklists that look like a clipboard. A diagnosis is heavy enough. The tool that helps you carry it should feel like a hand on your shoulder, not another assignment.
My wife is a licensed speech-language pathologist. I am an autism dad. We built the parts of the app you reach for in the worst moments because those are the moments we needed help in too. The [calm screen](/blog/emergency-calm-strategies-autism-meltdowns) was the first feature we ever finished, because that was the first thing we ever needed.
## What You Get on Day One
A visual schedule built in under ten minutes with photos of your own child's world. A calm screen with breathing animations for the next overload. A [social story](/blog/social-stories-autism-medical-appointments) you can show before the dentist, the airport, the first day. Real tools for the real next week.
If you just got the diagnosis, you are not alone. We made this for the season you are in right now.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** The first week after a diagnosis deserves a plan, not another pamphlet. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## We Didn't Set Out to Build an Autism Parenting App
Published: 2026-05-13
URL: https://vizyplan.com/blog/built-for-our-own-son-autism-parenting-app
Category: Founder Story
Author: Justin Bowman
> We did not set out to build an autism parenting app. We set out to help our own son. Here is the why behind every screen in VizyPlan and the family it came from.
We did not set out to build an autism parenting app. We set out to help our own son. He was nonverbal until he was two, and when the diagnosis came, the paperwork came with it. Pamphlets, packets, phone numbers, eighteen month waitlists. None of it told us what to actually do on a Tuesday morning when he was on the floor of the kitchen and we were already late.
So we built something for ourselves. My wife is a licensed speech-language pathologist. I am his dad. Between the two of us, we knew what the research said about visual supports for autistic kids, and we knew what our own family needed to get through the day. The gap between those two things was where every existing tool was failing us.
## Why an Autism Parenting App at All
Because the brain that struggles with executive function does not need more reminders shouted from across the room. It needs the plan to live somewhere visible. Outside the parent's head. Outside the child's head. On a screen, on a fridge, on a tablet propped on the counter. Somewhere the day can actually be seen.
## How We Built It
We started with one rule. Nothing in the app could feel clinical. No jargon. No therapy room aesthetic. A four year old should want to look at it, and a tired parent should be able to set it up in ten minutes between meetings. Calm visuals. Real photos of the child's own world. Simple taps. That is the whole design philosophy.
## What It Does
[VizyPlan](https://vizyplan.com) turns your day into a visible map. Visual routines your child can follow without you narrating. Social stories for the hard moments. IEP prep that does not require a binder. A calm screen for the meltdown that already started. Stickers and small wins to mark the progress.
If you are in that season, we made this for you.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Built by an autism parent and a licensed SLP for our own family, now available for yours. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## Teaching Morning Routine Independence to Autistic Kids
Published: 2026-05-12 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/autistic-child-morning-routine-independence
Category: Daily Routines
Author: Justin Bowman
> Building autistic child morning routine independence is not a strict schedule or a sticker chart. It is a visible map your child can run without you. Here is how it actually works.
Every weekday morning, you say the same six sentences. "Put on your shoes." "Where is your backpack?" "We are going to be late." "Brush your teeth." "Did you eat?" "Get in the car." You are not parenting in those moments. You are running a checklist out loud, and your child is running a different checklist that does not match yours. The autistic child morning routine is not failing because your child is being difficult. It is failing because the plan exists only in your head, where your child cannot see it.
The fix is not a sticker chart. Sticker charts measure compliance, not capability. The fix is making the plan external. A visible sequence your child can follow without you narrating. The brain that struggles with executive function does not need more reminders. It needs less working memory load and more environmental scaffolding.
## How to Build an Autistic Child Morning Routine That Runs Itself on VizyPlan
Step by step:
1. Write down every micro task in your current morning. All of them. Brush teeth becomes wet brush, paste, scrub, rinse, dry mouth, put brush away. The list will surprise you.
2. Take a photo of your child doing each one. Their own hands, their own bathroom, their own backpack.
3. Order the photos in the actual sequence and show them visibly, on a tablet, a printed sheet, or a magnet board on the fridge.
4. Step back. Narrate less. Let the visible plan do the heavy lifting.
5. Track the one task that keeps breaking the chain. That is your target for next week, not the whole routine.
[VizyPlan](https://vizyplan.com)'s [Visual Routines](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) feature builds this with personalized photos of your own child's actual world in under ten minutes, and the [emotion check-in](/blog/tracking-emotions-activities-neurodivergent-children) shows you which step is consistently dropping the routine so you can target it.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a [visual morning routine](/blog/visual-schedules-for-autism) with personalized photos of your own child. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Grief No One Warned You About After an Autism Diagnosis
Published: 2026-05-11
URL: https://vizyplan.com/blog/grief-after-autism-diagnosis
Category: Diagnosis
Author: Justin Bowman
> The grief after an autism diagnosis is real, common, and rarely named. It is not grief for your child. It is grief for the parenting path you imagined. Here is how to move through it.
Nobody tells you the part that hurts the most after the diagnosis is not the diagnosis. It is the quiet weeks after, when the world goes on, and you find yourself crying in your car at the grocery store because a kid on a bicycle reminded you of something you did not know you were already letting go of. Grief after an autism diagnosis is real, common, and almost never named in the pediatrician's office where it begins.
It is not grief for your child. Your child is fine. Your child was already exactly who they are before anyone wrote it on a piece of paper. The grief is for the picture you carried in your head of the parenting path that is not the path you are on now. The first day of school you imagined. The conversation about the school dance. The independent twenties. None of those are off the table. They just look different than the version playing in your head, and the version in your head is what you are mourning.
## Moving Through the Grief After an Autism Diagnosis
Researchers call this ambiguous loss. It does not have a funeral. It does not have a card. It loops and ebbs for years, often louder around milestones, quieter in between. Three things shorten the loop without skipping it:
1. Name it. Saying out loud "I am grieving the version of parenting I thought I was getting" is the most powerful sentence you can say in the first year. Naming reduces shame.
2. Talk to other parents who are six months ahead of you, not six years. The far ahead parents are useful. The just ahead parents are oxygen.
3. Watch your child today, on purpose, for one specific thing they are good at. Not in a forced "celebrate the wins" way. Just look. The grief gets quieter when you see who is actually in front of you.
For more on this internal shift, read our piece on the [autism dad mindset shift from fix to support](/blog/autism-dad-mindset-shift-fix-to-support).
---
## Birthday Parties Without the Meltdown for Autistic Kids
Published: 2026-05-10 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/autistic-child-birthday-party-meltdown
Category: Social
Author: Justin Bowman
> Birthday parties for autistic kids are a sensory landmine. Crowds, songs, sugar, surprises, balloons. Here is the preview that turns the meltdown into a memory worth keeping.
Every sensory trigger your autistic child has ever struggled with, gathered in one room, in costumes, with cake. Birthday parties for autistic kids stack the deck against regulation in ways no other event does. Crowds, the happy birthday song, balloons that might pop, unfamiliar smells, sugar spikes, gift-opening pressure, and a host of small social rules nobody explicitly teaches. The meltdown at the party is almost never about the party. It is the sum of all of it landing at once with no preview.
The mistake most well meaning parents make is treating the party as a single event to push through. It is not. It is a sequence of micro transitions, and each one is its own ask. Arriving. Greeting. Free play. Group activity. Song. Cake. Gifts. Goodbye. Eight transitions, plus dozens of sensory shifts inside each one. That is what your child is being asked to navigate without a map.
## How to Make Birthday Parties Work for Autistic Kids on VizyPlan
Build the map ahead of time:
1. Find out the schedule from the host. Most parents will text you a rough order if you ask.
2. Build a visual story of the party with photos of the venue and faces of who will be there.
3. Agree on an exit plan with your child. One sentence they can use, one signal you watch for, one quiet spot you have already scouted.
4. Plan the recovery window for after, not just the party. Decompression is the second half of any social event for an autistic kid.
[VizyPlan](https://vizyplan.com)'s [Vizy Stories](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) builds the preview in under ten minutes, and the [emotion check-in](/blog/tracking-emotions-activities-neurodivergent-children) feature shows you which exact moment of the party tipped your child over so the next one is easier.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a [birthday party social story](/blog/social-stories-autism-guide) your child can rehearse the morning of. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## The Compounding Cost of Sleep Deprivation in Autism Families
Published: 2026-05-09
URL: https://vizyplan.com/blog/sleep-deprivation-autism-families
Category: Family
Author: Justin Bowman
> Sleep deprivation in autism families is not the same as new-parent tired. It compounds for years and rewires what is possible. Here is what the research says and what helps.
Most parents lose sleep for a few years. Sleep deprivation in autism families lasts a decade. Up to 80 percent of autistic children have a clinically significant sleep disorder, according to a 2019 study in Pediatrics, compared to roughly 30 percent of neurotypical children. The math is brutal. Two hours less per night across ten years is 7,300 hours of lost sleep. That is not a tired phase. That is a rewiring of what your body and your relationship can do.
The cost compounds in places no one warns you about. Immune function drops first. Then short term memory. Then patience, then libido, then the small generosities that hold a marriage together. Therapists call it parental burnout, but the parents living it call it something simpler. They call it running on fumes.
## What Helps With Sleep Deprivation in Autism Families
Three shifts produce more sleep for the household, in order of impact:
1. Treat the child's sleep as a medical issue, not a parenting failure. Ask the pediatrician about melatonin dosing, iron levels, and a sleep study. Untreated sleep apnea is missed in roughly half of autistic kids who have it.
2. Set a non negotiable wind down window. Same lights, same sounds, same order, every night. Predictability lowers cortisol, which is the actual lock on your child's sleep.
3. Build a tag team for the hardest hour. Whichever parent is less depleted that day takes the bedtime sequence. The other parent eats food. Trade. Repeat.
For more practical bedtime structure, read our guide on [bedtime routines for autistic kids](/blog/bedtime-routines-autistic-adhd-kids). And if you need a visible nightly sequence your child can follow without you in the room, [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) builds the [visual bedtime routine](/blog/visual-schedules-for-autism) that runs on autopilot.
---
## Why Your Autistic Child Has a Meltdown at the Dentist (And How to Fix It)
Published: 2026-05-08 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/autistic-child-meltdown-at-dentist
Category: Medical
Author: Justin Bowman
> Your autistic child meltdown at the dentist is not bad behavior. It is six sensory inputs your child cannot escape, in a room they cannot leave, with a stranger in their mouth. Here is the fix.
The dentist is the perfect storm. Bright overhead light pointed at the face. Latex smell. High pitched suction noise. A stranger leaning in close. Hands and metal in a mouth that already gets flooded with sensory input. An exam chair that tilts you backward and removes your ability to escape. An autistic child meltdown at the dentist is not bad behavior. It is six sensory inputs your child cannot turn off, in a room they cannot leave, with a person in their personal space they did not invite.
Behavior at the dentist is data, not defiance. The kid screaming in the chair is communicating that the demand exceeds the regulation capacity available. The fix is not bribery or punishment. The fix is reducing the unknowns ahead of time and building tolerance gradually.
## How to Fix the Autistic Child Meltdown at the Dentist on VizyPlan
The week before the appointment, work this sequence:
1. Email the office and ask for a few minutes of pre-visit play. Many pediatric dentists allow a 10 minute "meet the room" stop, no chair, no exam.
2. Build a social story with photos of the actual room, the actual dentist, and the actual chair. Show the order of every step.
3. Rehearse the body parts at home with a toothbrush. Mouth open, teeth tap, breath count, finish.
4. Identify one sensory anchor your child brings (weighted lap pad, noise reducing headphones, a specific stim toy) and let the dentist know it stays during the appointment.
[VizyPlan](https://vizyplan.com)'s [Vizy Stories](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) builds the preview in under ten minutes with AI-generated images of your child's actual face and the actual chair, and [emotion tracking](/blog/tracking-emotions-activities-neurodivergent-children) shows you which specific step triggers the storm so you can target it next time.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a [dentist social story](/blog/social-stories-autism-guide) your child can rehearse all week. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
---
## When Grandparents Do Not Believe Autism Is Real
Published: 2026-05-07
URL: https://vizyplan.com/blog/grandparents-dont-believe-autism
Category: Family
Author: Justin Bowman
> When grandparents do not believe autism is real, the conflict lands on top of everything else you are already carrying. Here is how to protect your child without setting the family on fire.
"In our day, kids just acted up. None of this autism stuff." If you have heard a version of this from a parent or in-law, you know the feeling that follows. Exhaustion. A flash of anger you did not have energy for. A second wave of grief, because the support you needed from your own family is not coming. When grandparents do not believe autism is real, the conflict piles on top of the load you are already carrying, and the load was already too heavy.
Generational denial is not always cruelty. Sometimes it is fear. Acknowledging your child's diagnosis can feel, to a grandparent, like acknowledging that they missed something in their own kids decades ago, or that they parented wrong, or that the world is harder than they want it to be. Their denial is a coping mechanism. It is also not your problem to solve.
## What Helps When Grandparents Do Not Believe Autism Is Real
Three boundaries protect your child without burning the bridge:
1. Decide what they need to accept and what they do not. They do not need to agree with the diagnosis. They need to follow your house rules around your child. Frame it that way.
2. Drop the proof game. Sending studies, articles, and reports rarely works on someone whose objection is emotional. Stop spending energy there.
3. Give them one concrete way to help. "When you come over, please use a calm voice and let him finish his routine before you greet him." Specific is doable. Vague is debatable.
If the relationship cannot meet the bar, reduce contact, not affection. You can love a grandparent from a small distance.
For more on protecting your child's care plan in family settings, read our guide on [teaching self-advocacy skills](/blog/teaching-self-advocacy-skills-neurodivergent-child).
---
## First Day of School Anxiety in Autistic Kids: What to Do the Week Before
Published: 2026-05-06 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/first-day-of-school-anxiety-autism
Category: School
Author: Justin Bowman
> First day of school anxiety in autistic kids is not nerves you can pep talk through. It is the brain bracing for a complete reset. Here is a week-before plan that actually works.
The night before school starts, you can feel the temperature in the house change. Your autistic child knows something is coming. They cannot picture it yet, and the unknown is doing more damage than the actual first day will. First day of school anxiety in autistic kids is not the kind of nerves a pep talk fixes. It is the brain bracing for a complete reset of routine, environment, people, and demands all at once.
Most "back to school" advice for autistic kids starts the morning of. By then, you are already inside the storm. The work happens the week before, and the work is preview. Not "you are going to love your new teacher" reassurance, which the brain dismisses as a guess. Real preview. Concrete pictures. The actual route. The actual room. The actual face.
## Easing First Day of School Anxiety in Autism on VizyPlan
The week before, build a visible map of the day:
1. Walk or drive the route to school at the same time of day the bus will come. Take a photo of every stop.
2. Email the teacher and ask for a photo of the classroom and themselves. Most teachers say yes immediately.
3. Lay out the actual clothes, the actual backpack, the actual lunch container. Let your child touch and inspect.
4. Make a visual schedule that maps the first day hour by hour, with rooms, faces, and one anchor activity per slot.
[VizyPlan](https://vizyplan.com)'s [Visual Routines](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) feature lets you build the schedule with personalized photos of your child's actual world, and [Vizy Stories](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you preview the first day as a saved narrative your child can replay anytime that week.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a [visual first-day plan](/blog/visual-schedules-for-autism) your child can rehearse all week. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and walk into the first day already rehearsed.
---
## Why Autistic Kids Resist Transitions (And It Is Not Defiance)
Published: 2026-05-05
URL: https://vizyplan.com/blog/why-autistic-kids-resist-transitions
Category: Behavior
Author: Justin Bowman
> Why autistic kids resist transitions has nothing to do with attitude. It is biology. Here is what is actually happening in their brain and the three things that move the needle.
"He just will not transition" is the most common phrase therapists hear from frustrated parents. It is also the most misunderstood. Why autistic kids resist transitions has nothing to do with defiance. It is biology. Their executive function system, which manages task switching in the prefrontal cortex, develops on a different timeline and runs different software than a neurotypical child's. A transition is not a small ask. It is an entire reboot.
Research in the Journal of Autism and Developmental Disorders has documented this for two decades. Autistic brains show measurably higher cognitive load during transitions, with elevated cortisol levels that take longer to return to baseline. What looks like five seconds of resistance on the outside is, on the inside, a full physiological recalibration. The child is not refusing to leave the iPad. The child is staying in the safest place their brain can find.
## What Helps When Autistic Kids Resist Transitions
Three things move the needle, in order of impact:
1. Warning. Give a clear preview at least five minutes before the transition. Use a timer the child can see, not just a verbal countdown.
2. A bridge object. Letting your child carry something from the current activity into the next one, a toy, a card, a snack, gives the brain a continuity anchor.
3. The same words every time. Phrasing like "first we finish, then we go" becomes a script the brain recognizes and trusts.
What does not help: surprise transitions, raised voices, "in a minute" without a clock the child can see, or asking "are you ready?" when readiness is not the question.
The real shift happens when you stop treating resistance as the problem. Resistance is the symptom. The problem is the abrupt cognitive switch your child's brain cannot complete without support. Build the support, and the resistance fades on its own.
For a deeper look, read our guide on [staying regulated during transitions](/blog/staying-regulated-during-transitions). [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) builds [visual routines](/blog/visual-schedules-for-autism) and visible countdown timers your child can rely on across every transition in the day.
---
## Preparing an Autistic Child for a Death in the Family
Published: 2026-05-04 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/preparing-autistic-child-for-death-in-family
Category: Family
Author: Justin Bowman
> Death is abstract. For an autistic child who relies on routine and concrete language, preparing them for a loss is one of the hardest transitions a parent has to navigate. Here is what actually helps.
Death is abstract. It happens behind closed doors, in language no one explains, on a timeline that does not match anyone's schedule. Preparing an autistic child for death in the family becomes one of the hardest things a parent has to navigate, because most grief frameworks assume your child can hold the abstraction. Many cannot, and they should not have to.
Grief guides usually tell you how to have the conversation once. What they leave out is that your autistic child will ask the same question every morning for two weeks. Repetition is not denial. Repetition is how an autistic brain processes what does not yet make sense. Each time the question comes back, the brain is looking for the piece of the story that explains the piece it cannot file.
Concrete language helps. Say "Grandma's body stopped working" instead of "Grandma passed." Name what stays the same, her photos, her stories, the song you sang together, alongside what has changed. Avoid metaphors like "we lost her," which an autistic child can hear literally and become more confused, not less.
## A Visual Story for Preparing an Autistic Child for Death on VizyPlan
A saved social story your child can open whenever the question comes back gives the brain something to hold. With pictures that look like your family, language at their level, and a clear preview of what to expect at the service, who will be there, what the room will feel like, and what is okay to feel.
[VizyPlan](https://vizyplan.com)'s [Vizy Stories](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) builds that in under ten minutes using AI-generated images of your actual family. Pair it with [emotion tracking](/blog/tracking-emotions-activities-neurodivergent-children) for the weeks after, where grief often shows up sideways as sleep loss, meltdowns, or food refusal.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a [social story](/blog/social-stories-autism-guide) for the loss your child can return to whenever the questions come back. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who needed something that did not exist. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child a story for every hard thing on the calendar.
---
## The Autism Dad Mindset Shift: From Fix to Support
Published: 2026-05-03 · Updated: 2026-05-03
URL: https://vizyplan.com/blog/autism-dad-mindset-shift-fix-to-support
Category: Parenting
Author: Justin Bowman
> Dads come pre-loaded for fix mode. Provider, protector, problem solver. But your autistic son is not a problem to solve. The shift from fix to support is the one that finally lets you see how beautiful his mind already is.
The first time my son lined up his cars, I rearranged them. He had them perfectly spaced along the edge of the rug, in a precise order I did not understand, and I, in dad mode, scooped them into a pile and said, "Let's play crash up." I thought I was teaching him how to play. He looked at the pile, looked at me, and walked out of the room. That moment was the start of an autism dad mindset shift I did not know I needed.
It took me a long time to understand that the lineup was not a problem. The pile was. I had taken something he was doing beautifully and turned it into something he had to escape.
This post is about that shift. The move from trying to fix your child, to supporting the child who is already there. And what happens, on the other side of it, when you finally see how beautiful his mind actually is.
## The Wiring You Did Not Choose
Dads come pre-loaded for fix mode. Not all dads, and not in the same way, but most of us walked into fatherhood carrying a script we did not write. Provider. Protector. Problem solver. The car will not start, you fix the car. The faucet leaks, you fix the faucet. The kid is struggling, you fix the kid.
The fix-the-kid script is where the wiring breaks.
Research on fathers of autistic children describes a real conflict between two strands of traditional masculinity, the ability to provide and the ability to protect. A 2021 study in the British Journal of Learning Disabilities found that those two roles get forced into conflict when a child has additional needs, because you cannot always work the hours and also be the parent who is home doing the heavy lifting at 6 p.m. Dads feel that conflict in their bones, even when nobody names it for them.
Underneath the provider script is something more primal, the urge to remove suffering from someone you love. Your child is overwhelmed at the grocery store, and every cell in your body wants to make it stop. Your child cannot make eye contact at the family party, and you feel the eyes of your in-laws on the back of your neck. Your child melts down at bedtime for the third night in a row, and you think, there must be a way to fix this. There must be a thing I have not tried yet.
There usually is. But the thing you have not tried yet is almost never another fix. It is a shift.
## What Fixing Costs
Here is what nobody tells you about fix mode.
Fix mode treats your child as a problem set. It scans for what is wrong and grades it. The flapping is a problem. The lining up is a problem. The echolalia is a problem. The clothes that have to be the same texture, the foods that cannot touch, the way he covers his ears at the school assembly. Problems. All of them. Things to be reduced.
Your child feels that. He may not be able to name it, but he feels it. A 2020 study in Frontiers in Psychology on parental attunement and acceptance found that children whose parents have not yet resolved or accepted the diagnosis show worse parent-child relationship quality and higher attachment insecurity. Fix mode is not invisible to the child. It travels through tone, body language, and the small sigh you make when he starts to stim.
A 2022 systematic review in Frontiers in Psychiatry put it plainly. Lack of resolution about a child's autism diagnosis is associated with higher parenting stress, poorer parental mental health, and insecure attachment with the child. Acceptance, by contrast, is a protective response. It correlates with lower depressive symptoms in parents, both at any given moment and over time. The dads who keep grinding in fix mode are the dads who keep getting more depressed. The data is not subtle.
Fix mode also costs you. There is no version of this where you outwork autism. There is no schedule, no diet, no protocol that turns your autistic son into a neurotypical son. So if your worth as a father is hooked to fixing, your worth becomes unreachable. You will work and work and never feel like you are succeeding, because you are graded on an outcome that was never on the table.
The trap closes around dads quietly, and most of us do not notice until we are exhausted.
## The Autism Dad Mindset Shift, in One Word
In a 2022 narrative inquiry of fathers of autistic children, published in SAGE Open, researchers asked dads to tell the story of their journey in their own words. Across the interviews, one moment kept showing up. The fathers described a turning point. They described it differently, but the shape of it was the same. There was a before, and there was an after. Before, they were fighting their child's autism. After, they were not.
The researcher's word for that moment was acceptance.
Acceptance, in the way fathers used the word, was not resignation. It was not giving up on growth. It was a change in the question. The question went from "how do I fix this," to "how do I support this child as he is, while also helping him build the skills he needs."
The second question is workable. The first one is not.
That single change in question is the heart of the autism dad mindset shift, and it does not happen on a Tuesday because you read a blog post. It happens slowly, in moments. It happens the night you let the lineup stay on the rug instead of scooping it into a pile. It happens the morning you stop demanding eye contact and start watching where his eyes actually go. It happens the afternoon you sit on the floor next to him while he rocks, and you realize, for the first time, that he is not in distress. He is in his body. And you do not need to interrupt that.

## What Support Looks Like When Fix Steps Aside
Support is not passive. That is the part most dads misunderstand at first. We hear "stop trying to fix him" and we worry that means do nothing, accept everything, drift. The research describes the opposite. Support is active. It is engineering the world around your child so that his nervous system has a fighting chance.
Here are five moves that turn fix energy into support energy.
1. Lower the demands you can lower. A 2024 systematic review of parent-focused interventions found that mindfulness-based and acceptance and commitment therapy approaches were the optimal interventions for reducing parental stress and improving family outcomes. The mechanism is not magic. When you stop pushing against every difficult moment, the moments shrink. Your child has fewer demands to fight, you have fewer power struggles to lose, and the day calms down.
2. Build the predictability his brain needs. Autistic brains do not handle uncertainty the way neurotypical brains do. A [visual schedule](/blog/visual-schedules-for-autism) is not a fix. A visual schedule is a support. It does not change who your child is. It changes the world around him so who he is can show up. When you switch from fix to support, [personalized visual routines](/blog/personalized-visuals-neurodivergent-children-routines) stop being a tool for compliance and start being a tool for safety.
3. Co-regulate before you correct. A child who is dysregulated cannot learn. The research on [co-regulation before self-regulation](/blog/co-regulation-before-self-regulation-neurodivergent-children) is clear. If your son is melting down and you come in with logic, lecture, or consequence, you are pouring water on a grease fire. Support means lowering your voice, slowing your body, and giving him your nervous system to borrow until his comes back online. Teaching can happen later. Always later.
4. Read what the behavior is telling you. Stimming, scripting, lining up, covering ears, refusing the new shirt. Each of those is communication. Fix mode treats them as bugs to remove. Support mode treats them as data. Our piece on [stimming](/blog/stimming-autism-when-to-support-when-concerned) walks through when stimming is a need being met and when it is a sign your child has hit his limit. The behavior is not the problem. The behavior is the report.
5. Track what is actually happening. In fix mode, you remember the meltdowns and forget the calm afternoons. You build a mental case against your own child without meaning to. [Tracking emotions and patterns](/blog/tracking-emotions-activities-neurodivergent-children) gives you real data instead of a feed of frustration. Most dads I have talked to are stunned the first time they see a real week of their child's data and realize the bad days are not as common as the bad days felt.
None of those five moves is fixing. All of them are supporting. The difference is who has to change. In fix mode, the child has to change. In support mode, the parent and the environment do most of the changing, and the child is freed up to grow at his own pace.
## What You Start to See
This is the part nobody can quite prepare you for.
When you stop trying to fix your son, you start to see him.
You notice that the lining up was never random. There was a system, a sequence, a logic he was working out, and once you watch instead of intervene, the logic becomes visible. Researchers call this monotropism. The framework was first described in the late 1990s by a small group of autistic researchers, Dinah Murray, Wenn Lawson, and Mike Lesser, and it has become one of the most useful lenses for understanding the autistic mind. Monotropism describes a tendency for attention to flow deeply into a small number of interests at a time, instead of spreading thinly across many. It is not a failure of attention. It is a different shape of attention.
Inside that shape, the child you thought you were watching becomes a different child. The kid who could not be torn away from his train sequence is not stuck. He is in flow. The kid who has memorized every dinosaur name is not "obsessing." He is doing the deep work that monotropic minds are built for. The hours he spends on a single thing are not wasted. Those hours are how his brain actually learns, and it learns at a depth most adults will never touch.
Beyond monotropism, the research on autistic cognition keeps surfacing the same word: pattern. A 2021 paper titled "Pattern Unifies Autism" argued that autism is fundamentally an enhancement of pattern perception, pattern generation, and pattern processing. Tests of visual pattern recognition repeatedly find autistic children performing at or above neurotypical peers. They see things in the noise. They notice the thing the rest of us missed. They remember a sequence three months after they saw it once.
Those abilities are not a deficit. They are a different operating system. And the system, when you finally let yourself see it, is beautiful.
## The Day I Stopped Fixing
Here is the moment for me.
My son was nonverbal until he was two. For most of those two years I lived in fix mode, all the way under the surface. Every milestone we missed, I added to a list of things to outwork. Every echolalia phrase he repeated, I tried to redirect into "real" language. Every time he flapped, I noticed myself looking around to see who was watching. I thought I was being a good dad. I was being an exhausted one.
One night, I sat on the bedroom floor while he was building. He had a long row of small wooden animals lined up, perfectly spaced. He was humming a phrase from a show, the same eight syllables, over and over. I had a lecture half-loaded in my head about how to make this look more like "play."
And then I stopped. I just watched him.
The phrase he was humming was the part of the show where the character feels safe. The animals were arranged in pairs, biggest to smallest. He looked over at me, briefly, with the kind of glance you only get when you have not interrupted someone in the middle of something they love. And he kept going.
I had spent two years trying to get him to look me in the eye. That night, I stopped trying, and he looked.
The shift was not a method. It was not a system. It was a look.
## The Mind I Almost Missed
Sitting on that floor, I realized something I had been too busy to see for two years. My son has a beautiful mind. Not in the soft, parental way you say it on a hard day to feel better, but in the way you mean it when you finally notice something that has been in front of you the whole time. His world is amazing. It is encapsulating. It is methodical in a way most adult minds never get to be. There is order in it, and care, and a quiet logic that holds together if you stop interrupting it.
And the moment I let him be inside that world, instead of pulling him into mine, I realized I was the one who needed fixing. Not him. For two years I had been trying to make him more like me. The work was always the opposite. The work was to let him be more like him, and to support that instead of correct it.
I am a sports dad. I love coaching. I love playing. Part of supporting him, the real version and not the version where I am still secretly trying to fix, is accepting that the field may never be his place. And that is perfectly fine. I would much rather be in his world with him than spend his childhood teaching him to do something that does not work for him. That is not a sacrifice. It is a trade I would make every time.
This is not every autistic kid. Plenty of them love sports. Plenty love sitting on the couch watching the game with their dad. I am only telling you about my son, what I have noticed, and what I expect to keep noticing, because I am always learning from him. I think I always will be.
## A Permission Slip
If you are an autism dad reading this and you can feel the fix reflex still running in the background, you are not failing. You are doing the same thing every dad I know has done at some point, and most of us did not have anyone telling us to stop. We figured it out by getting tired enough to try something else.
So consider this a permission slip.
You have permission to let the lineup stay on the rug. You have permission to let the script play out. You have permission to skip the family event, or leave it early, or eat the same dinner he eats because it is the only meal that works tonight. You have permission to put down the protocol, the new diet, the latest miracle technique you saw at midnight on Instagram. You have permission to stop reading articles that make you feel like you are losing, and start reading the small ones your child is writing all over your house every day.
You have permission to support, not fix.
You will still teach him. You will still help him build skills. You will still, on plenty of days, be exhausted in ways nobody warned you about. The work does not get easier. The work gets right-sized. You stop fighting the wrong fight, and the right fight, the one that is actually winnable, the one where you build a life that fits him, comes into view.
His mind is not broken. His mind is monotropic, pattern-hungry, deep, loyal to the things it loves. His mind is exactly the mind he was always going to have. Your job is not to give him a different one. Your job is to clear the road in front of the mind he already has, and walk next to him while he uses it.
When you do that, you stop being a dad in a long fight with autism. You start being his dad. That is the autism dad mindset shift. And it is the only one I have ever found that actually works.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that support your child's brain instead of trying to override it, [track emotions and patterns](/blog/tracking-emotions-activities-neurodivergent-children) so you see the real picture instead of the worst day, and create [social stories](/blog/social-stories-autism-guide) that prepare him for what is coming next without forcing him to mask through it. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## What to Say in an IEP Meeting When You Disagree
Published: 2026-05-02 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/what-to-say-iep-meeting-disagree
Category: Strategies
Author: Justin Bowman
> Specific scripts, phrases, and procedural rights parents can use when they disagree at the IEP table, plus the one sentence that protects every request.
Disagreement does not have to be a fight. It does not have to be loud. Most of the time, what to say in an IEP meeting when you disagree sounds like one quiet sentence. "I am not ready to sign today."
That sentence ends the pressure. It buys you time. It does not burn the relationship with the team. And it is one of dozens of phrases I wish someone had handed me before my first IEP meeting, the one where I sat across from six people with clipboards and felt the room close in around me.
If you have ever walked out of an IEP meeting and cried in your car, you are not the problem. The dynamic is the problem. Research shows that parents speak in only about 14 percent of all intervals during IEP meetings, while professionals speak in the remaining 86 percent. A separate study found that 33 percent of parents reported feeling confused during IEP meetings. We are outnumbered, often outpaced, and almost always outranked by titles. The fix is not to become a louder version of yourself. The fix is to know exactly what to say.
This post is the long companion to our [IEP meeting preparation guide](/blog/iep-meeting-preparation-guide-parents). The prep guide gets you ready to walk in. This post is for the moments when you are already at the table, the team has just proposed something you do not agree with, and your stomach drops. You will leave this post with phrases you can use word for word, a pushback table for the most common school responses, an eight step plan for the moment of disagreement, and a copy ready follow up email.
This article shares information about legal rights under federal special education law. It is not legal advice. If you are facing a serious disagreement with your school, consider contacting your state's Parent Training and Information Center or a special education attorney.
## Why Disagreement Is Normal and Legally Protected
Disagreement at the IEP table is not a failure of the process. It is the process. Under the Individuals with Disabilities Education Act, parents are equal members of the IEP team. Your input carries the same legal weight as any other person in the room. Every right described in this post lives in 34 CFR Part 300, the federal regulations that implement IDEA, available at sites.ed.gov/idea.
Disagreement is also more common than schools sometimes let on. The Center for Appropriate Dispute Resolution, known as CADRE, reported 9,927 written state complaints filed in the 2023 to 2024 school year. That is a 79 percent jump over the 10 year average of 5,537 complaints. Written state complaints rose 22 percent over the prior year. Due process complaints rose another 5 percent in the same period. Parents are pushing back more than ever, and they are doing it in writing, not in shouting matches.
You are also the only person at the table who knows your child outside of school. Nobody on the team sees the meltdown at 6 AM when the morning routine collapses, or the dysregulation at 8 PM when homework still is not done. That knowledge is not less valuable than a test score. It is the context that makes everything else meaningful. When you disagree with a school recommendation, you are not being difficult. You are doing the job IDEA assigned you.
## The Phrases That Change the Conversation
The single most useful skill in an IEP meeting is having phrases ready before you need them. Below are the categories I reach for most often, anchored in specific procedural rights so they are not just rhetoric. They are enforceable.
### When You Need Information or Data
Schools sometimes present recommendations as if they are settled. They are not. Every recommendation should be traceable to data in the present levels of academic achievement and functional performance, required under 34 CFR 300.320(a)(1).
- "Can you point me to the data in the present levels that supports that recommendation?"
- "What evaluation tools were used to reach that conclusion, and how recent is that data?"
- "Could you walk me through how those service minutes were determined?"
- "How will progress on this goal be measured, and how often will I receive progress reports?"
If the team cannot answer these questions, the recommendation is opinion, not evidence. Opinion is negotiable. For more on evaluating individual goals, see our guide on [whether your child's IEP goals are actually right](/blog/are-iep-goals-right-for-your-child).
### When You Need Time
Time is one of the most important rights you have. Consent under IDEA must be informed and voluntary, per 34 CFR 300.9. You cannot give informed consent on a document you have not had time to read.
- "I am not ready to sign today. I would like to take this home, review it, and respond in writing."
- "I would like to table this item and reconvene in two weeks once I have had time to consult with my child's outside therapist."
- "Can we put this discussion on pause and come back to it after we have addressed the items I have less concern about?"
Schools sometimes imply that the meeting must end with a signature. It does not. There is no rule, anywhere in IDEA, that requires a parent to sign at the table.
### When You Disagree With a Proposal or a Refusal
This is where the most powerful in-the-moment lever lives. Prior Written Notice, commonly called PWN, is required under 34 CFR 300.503 whenever the school proposes or refuses to initiate or change identification, evaluation, educational placement, or the provision of a Free Appropriate Public Education. PWN forces the school to put the proposal or refusal, the reasoning, the data, and the alternatives they considered into writing.
- "I would like that documented in the Prior Written Notice."
- "I am formally requesting Prior Written Notice for the team's refusal to add this service."
- "I disagree with the most recent evaluation. I am formally requesting an Independent Educational Evaluation at public expense."
- "What other options did the team consider before settling on this proposal, and why were those rejected?"
If you remember nothing else from this article, remember the first sentence. "I would like that documented in the Prior Written Notice." It is the single most useful sentence you can carry into an IEP meeting. It moves the conversation from a hallway promise to a paper trail.
### When You Want to Sign Part but Not All
You are not required to sign or refuse the entire IEP as a single document. Partial consent is widely recognized in practice.
- "I consent to the goals and services, but I do not consent to the proposed change in placement. Please document the partial consent in writing."
- "I am signing only to acknowledge attendance, not to agree with the contents of this IEP."
Some districts will push back on partial consent. Stand firm. Ask for the refusal of partial consent to be documented in PWN.
### When the Team Says No, "We Cannot," or "We Do Not"
Some of the most common phrases parents hear at the IEP table sound final. They are not. The next section breaks down the most common ones with a parent response anchored in the regulation that backs you up.
### When a Pre-Written IEP Is Presented
If you walk in and the team hands you a finalized document, that is a problem. Predetermination, where the school decides everything in advance and then runs a meeting designed to ratify the decision, is a procedural violation under IDEA. Two cases anchor this. In Deal v. Hamilton County Board of Education, 392 F.3d 840 (6th Cir. 2004), the court found that predetermination deprived parents of meaningful participation, which amounted to a denial of FAPE because the district had pre-decided not to offer ABA regardless of evidence about the child. In Spielberg v. Henrico County Public Schools, 853 F.2d 256 (4th Cir. 1988), the court held that "IEP objectives must be written before placement," not after. You can say:
- "Is this a draft for discussion, or a finalized document? Under IDEA, the IEP must be developed by the team, including me, at this meeting."
- "I would like the meeting to truly start with my input. Can we begin with my parent concerns before reviewing your draft?"
### When You Feel Rushed
A two hour IEP meeting that feels like fifteen minutes is a sign that the pace is working against you. Slow it down out loud.
- "I understand we have a time limit, but I have not had a chance to discuss accommodations. Can we schedule a continuation meeting? I would rather take the extra time than agree to something I have not fully reviewed."
- "This is a major decision. I am not going to make it under time pressure."
### When the Team Pushes a Less Restrictive Placement Than Your Child Needs
Sometimes the team wants general education. Your child is drowning there. IDEA's Least Restrictive Environment requirement, 34 CFR 300.114 to 300.117, does not mean general education at any cost. It means the least restrictive setting that allows your child to receive FAPE.
- "IDEA requires the Least Restrictive Environment that allows my child to receive FAPE. The data we just reviewed suggests my child is not making meaningful progress in the general education setting. What evidence does the team have that LRE is being met?"
- "What supplementary aids and services have been tried, with what data, before concluding general education with supports is appropriate?"
### When the Team Pushes a More Restrictive Placement Than Your Child Needs
The reverse can also happen. Before agreeing to a more restrictive placement, you have the right to ask whether less restrictive options were genuinely tried.
- "Before considering a more restrictive placement, IDEA requires the team to consider supplementary aids and services first. What aids and services have been tried, and what is the data on whether they were implemented with fidelity?"
- "I would like the team to document in Prior Written Notice why a less restrictive placement was rejected and what criteria would need to be met for my child to return."
### When You Want to Escalate Without Burning the Relationship
Most parents want to keep working with their school. They just need a different decision. You can press hard without going scorched earth.
- "I am hearing that we may not reach agreement today. I would like to request IEP facilitation or mediation through our state. I want to keep working with this team."
- "I am going to take some time to review this with an advocate. I will be in touch within the week with my next steps in writing."
## What to Say When the Team Says ___ (The Pushback Matrix)
Some phrases come up at almost every contested IEP meeting. Walk in expecting them, and have your response ready. The table below is a cheat sheet you can copy onto an index card and tuck inside your folder.
| What the school says | What you say | |---|---| | "We do not have the resources for that." | "Resource availability cannot drive an IEP. The IEP must be based on what my child needs to receive FAPE. Can you put the refusal and the reasoning in Prior Written Notice?" | | "Your child does not qualify for that." | "Can you walk me through the eligibility criteria you applied and the data you used? I would like the team to consider an Independent Educational Evaluation." | | "This is not typical for kids like yours." | "My child is not a category. Let's focus on the data on this specific child. What does the present levels data show?" | | "We always do it this way." | "IDEA requires the IEP to be individualized to my child. Can you tell me what about my child's profile led to this recommendation?" | | "You have to sign today." | "I do not have to sign today. I am taking this home to review. Can you mark on the meeting notes that I requested time to review?" | | "We will figure that out later." | "Can we add it to the IEP now so it is documented? Verbal commitments are not enforceable." |
A note on the first row, because it is the line every parent hears at some point. The Supreme Court's ruling in Endrew F. v. Douglas County School District, 580 U.S. 386 (2017), held that an IEP must be "appropriately ambitious in light of the child's circumstances." That standard does not bend to the district's budget. If the team says they cannot afford a service your child needs, that does not change what FAPE requires. It just means the refusal needs to go into Prior Written Notice with a reason. For a deeper look at how Endrew F. applies to the goals themselves, read our piece on [whether your child's IEP goals are actually right](/blog/are-iep-goals-right-for-your-child).
A note on the second row. If the school says your child does not qualify, ask whether you should be looking at an IEP or a [504 plan](/blog/504-plan-vs-iep-neurodivergent-child) instead, and request an Independent Educational Evaluation if you disagree with the school's testing.
## What to Do When You Disagree in the Moment
When the room gets tense, your brain narrows. You forget the phrases you practiced. You start agreeing just to make the discomfort stop. Below is an eight step sequence you can run in your head when that happens. Walk through it slowly. Each step gives the next one room to land.
1. Pause and breathe. Take a sip of water. Resist the urge to react in the first three seconds. Buy yourself ten seconds of silence. Schools often fill silence with information they would not otherwise volunteer.
2. Restate what you heard. Say something like, "Let me make sure I understand. You are recommending [X] because [Y]." Restating slows the conversation, gives the team a chance to clarify, and reveals if you misheard the proposal.
3. Ask for the data. Use the line, "Can you point me to the data that supports that recommendation?" If the team cannot point to specific data in the present levels, the recommendation is opinion, not evidence. Opinion is negotiable.
4. Name the disagreement clearly. Say, "I disagree with that recommendation, and here is why." Use specifics. Reference what you see at home, what outside providers have observed, or what the data does not support. Naming the disagreement out loud is what triggers the school's documentation duty.
5. Request Prior Written Notice. Use the line, "If the team is refusing to [specific request], I am formally requesting Prior Written Notice for that decision." This is the most important sentence in the meeting. Under 34 CFR 300.503, the school must now put the refusal, the reasoning, the data, and the alternatives considered into writing.
6. Decline to sign if needed. Say, "I am not ready to sign today. I will take this home, review it, and respond in writing within [timeframe]." You are never required to sign at the meeting. Partial signatures and partial consent are also options.
7. Propose a next step. Offer to reconvene, request an Independent Educational Evaluation, or request mediation or IEP facilitation through your state. The goal is to show you are not refusing to engage. You are refusing to be rushed.
8. Send the recap email within 24 hours. Document the meeting, the disagreements, and the requested next steps in writing. The template is later in this post. The recap email is what protects you if the conversation escalates.
Each of those steps gives you a beat to think. They also give the team a chance to course correct without losing face. Most disagreements that look like they need a lawyer end up resolving once Prior Written Notice is requested and the recap email goes out.
## Your Procedural Rights When You Disagree
Knowing the rights below is what turns intuition into leverage. Each one is anchored in a specific section of 34 CFR Part 300 so you can cite it on the spot.
**Parental consent (34 CFR 300.300).** The school must obtain informed parental consent before initial evaluation, before the initial provision of special education services, and before reevaluation. Consent is voluntary and may be revoked in writing at any time, though revocation is not retroactive. If you refuse consent for initial services, the school cannot use mediation or due process to override your refusal.
**Prior Written Notice (34 CFR 300.503).** Required whenever the school proposes or refuses to initiate or change identification, evaluation, educational placement, or the provision of FAPE. The notice must include a description of the action, the reasoning, the evaluations and records used, the procedural safeguards, sources for parent assistance, and a description of other options the team considered and why they were rejected. PWN is the most powerful in-the-moment tool you have.
**Independent Educational Evaluation at public expense (34 CFR 300.502).** If you disagree with the school's evaluation, you can request an IEE at public expense. Once you do, the school must, without unnecessary delay, either pay for the IEE or file a due process complaint to defend its evaluation. You are entitled to one publicly funded IEE for each school evaluation you disagree with.
**Procedural safeguards (34 CFR 300.504).** The school must give you the procedural safeguards notice at least once a year, on initial referral, on your request for evaluation, on the first state or due process complaint of the year, and on request. If you do not have the current copy, ask for one.
**Mediation (34 CFR 300.506).** Voluntary, free, and conducted by a trained, qualified, impartial mediator. CADRE reported that mediation agreement rates remained "consistently high" in the 2023 to 2024 school year. Written mediation agreements are legally enforceable in court.
**Written state complaint (34 CFR 300.151 to 300.153).** Filed with your State Education Agency. The state has 60 days to investigate and issue a written decision. CADRE reported that 81 percent of state complaints were resolved within the 60 day timeline in 2023 to 2024, down from a 10 year average of 92 percent, a sign that systems are stretched. File anyway. The paper trail matters.
**Due process complaint and hearing (34 CFR 300.507 to 300.515).** A formal legal proceeding before an impartial hearing officer. Must be filed within two years of the alleged violation under federal rules, though states may set their own timelines.
**Resolution session (34 CFR 300.510).** After a due process complaint is filed, the school must convene a resolution session within 15 days. You can waive it or substitute mediation.
**Stay-put (34 CFR 300.518).** Once a due process complaint is filed, your child remains in the current educational placement during proceedings, unless you and the district agree otherwise. This is one of the most powerful protections in IDEA. It prevents the district from making a unilateral placement change while a dispute is open.
**Right to bring an advocate (34 CFR 300.321).** You may invite anyone with knowledge or special expertise about your child to the IEP team. The party who invites the individual decides whether they meet that standard. No school approval needed. This includes private therapists, who often carry significant weight at the table. For more on coordinating outside providers, see our guide on [provider collaboration before the IEP](/blog/provider-collaboration-iep-preparation).
**Records access (34 CFR 300.613).** You have the right to inspect and review all education records relating to your child. The school must comply without unnecessary delay and before any IEP meeting, due process hearing, or resolution session, and in no case more than 45 days after the request.
For a step by step prep workflow that uses these rights from the moment you receive the meeting invite, the [IEP meeting preparation guide](/blog/iep-meeting-preparation-guide-parents) walks through each one in order.
## The 24 Hour Follow-Up Email (Copy and Paste)
The single highest leverage thing you can do after a contested IEP meeting is send a recap email within 24 hours. It locks in what was discussed. It documents what was disputed. It creates a paper trail that protects your child if the conversation escalates. Send it to the special education coordinator and copy the entire team, including the principal.
> Subject: Recap of [child's first name]'s IEP meeting on [date] > > Hi [team], > > Thank you for meeting today. I want to make sure we are on the same page about what was discussed and decided. Here is my understanding: > > 1. We agreed to [specific items, including any goals, services, accommodations, or placement decisions]. > 2. We tabled [items] for [the next meeting / by email] on [date]. > 3. I am taking the proposed IEP home to review and will respond by [date]. > 4. I requested [Prior Written Notice / Independent Educational Evaluation / mediation / IEP facilitation] for [specific items]. > 5. Outstanding questions I would like answered in writing: [list]. > > Please let me know if I have missed or misunderstood anything by [date, three to five business days out]. I appreciate the team's time and look forward to working together. > > [Your name]
A few notes on the template. Keep it factual. No emotion, no accusations, no editorializing. The tone is neutral, the content is specific. If a team member made a verbal commitment in the meeting, capture it in item one or item five. If you requested Prior Written Notice and you do not receive it within a reasonable window, follow up in writing referencing 34 CFR 300.503. If you requested an Independent Educational Evaluation, the school's clock starts ticking on whether to pay for it or file due process to defend their evaluation.
## Body Language, Who to Bring, and the Recording Question
What you say matters. So does how you say it, who is sitting next to you, and the question of whether to hit record.
**Tone and presence.** Stay calm and curious, not combative. Advocates consistently report that questions framed as curiosity ("Help me understand...") get better outcomes than statements framed as accusations ("You are not doing..."). Bring water and tissues. These meetings can run two hours or more. Sit beside the school administrator, not directly across, because adversarial seating activates adversarial dynamics. And do not be afraid of silence. Pause before you respond. The team will often fill the gap with information they would not otherwise volunteer.
**Who to bring.** You and a support person at minimum. A spouse, a friend who can take notes, a relative, anyone who knows your child. An advocate is a step up. State Parent Training and Information Centers, also called PTIs, and Community Parent Resource Centers, or CPRCs, provide free or low cost advocacy. Find your state's center at [parentcenterhub.org/find-your-center/](https://www.parentcenterhub.org/find-your-center/), the directory run by the Center for Parent Information and Resources. There are nearly 100 PTIs and CPRCs across the country. An attorney is appropriate for high stakes situations, especially due process or significant placement disputes. The presence of an attorney can polarize a room, and most disagreements do not require legal representation. Outside therapists are also an underused resource. A clinician who treats your child weekly carries weight at the table. Tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) can help you bring your own home data to the meeting, because routine completion patterns and emotion tracking from home can show consistency the school does not see. For more on how older children can participate in their own meetings, read our guide on [teaching self-advocacy skills](/blog/teaching-self-advocacy-skills-neurodivergent-child).
**Recording.** IDEA itself is silent on whether parents may record IEP meetings. State law and district policy govern. Some states allow recording with one party consent. Others require two party consent. Many districts have their own written policy and require advance notice. If you want to record, notify the team in writing at least 48 hours in advance, ask about district policy, and check your state's recording consent law. A recording is not a substitute for a recap email, and the recap email is required even when you record.
## You Are Not Alone, and You Are Not Wrong for Pushing Back
If you have read this far, you are already further along than most parents at the IEP table. The phrases above, the eight step sequence, the recap email, the procedural rights, all of it lives in IDEA because Congress understood that schools and families would not always agree, and that the family's voice needs the law on its side when they do not. Equipped with that, what to say in an IEP meeting becomes much less mysterious.
This article shares information about legal rights under federal special education law. It is not legal advice, and it is not a substitute for the advice of a qualified attorney or advocate who knows your specific situation. If you are facing a serious disagreement with your school, contact your state's Parent Training and Information Center at [parentcenterhub.org/find-your-center/](https://www.parentcenterhub.org/find-your-center/), or reach out to advocacy organizations like [Wrightslaw](https://www.wrightslaw.com), [COPAA](https://www.copaa.org), or [CADRE](https://www.cadreworks.org). The full IDEA regulations are available at [sites.ed.gov/idea](https://sites.ed.gov/idea).
The emotional toll of this work is real. Advocacy is a long game, and pushing back on a school can feel lonely and exhausting. If the weight is starting to wear you down, our piece on [caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children) is a place to start. You cannot pour from an empty cup, and your child needs the version of you that is rested enough to keep going.
Walk in knowing your rights. Walk in with your data. Walk in with your phrases written down and a support person beside you. And when the room goes quiet and the paper slides across the table, remember that the most powerful sentence you can say is the simplest one. "I am not ready to sign today."
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that document your child's daily progress, [track behavioral and emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) that give you concrete data for IEP meetings, create [social stories](/blog/social-stories-autism-guide) that prepare your child for school meetings and transitions, and share consistent schedules with every provider on your child's team. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps families of neurodivergent children build Visual Routines and Planning tools that bring structure, confidence, and data to every part of your child's day, including the IEP table. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and walk into your next meeting prepared.
---
## How to Write a Social Story for Your Autistic Child (Step-by-Step)
Published: 2026-04-30 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/how-to-write-social-story-autistic-child
Category: Strategies
Author: Justin Bowman
> A practical, step-by-step recipe for writing a social story your autistic child will actually engage with, including the one ratio rule that makes the difference.
I wrote my first social story for my son when he was three. It had eight "I will" sentences and zero pictures. It bombed. He pushed it away after one read and went back to lining up his cars.
I sat there, staring at my laptop, feeling like a failure. I had read the books. I had Googled the templates. I had the right idea, and I had still managed to produce something that looked nothing like what my son needed. Looking back, I had broken the single most important rule of social stories without knowing it existed. I had told him what to do without ever telling him what was going to happen.
This post is the post I needed that night. It is not a primer on what social stories are or why they work. It is the actual recipe. If you are sitting at your kitchen table with a blank document open and a hard situation on the calendar, this is how to write a social story your child will actually sit through, and how to do it without making the mistake I made first.
## A 60-Second Refresher
A social story is a short, personalized narrative that walks an autistic child through a specific situation in language and pictures they can absorb at their own pace. The method was developed by Carol Gray in 1991 and has been studied for over thirty years. Social stories are listed by the National Professional Development Center on Autism Spectrum Disorder (Wong et al., 2015) as one of 27 established evidence-based practices for autism. A 2010 systematic review by Karkhaneh and colleagues found statistically significant social-skill benefits in five of six controlled trials reviewed.
If you are brand new to the concept, start with our primer, [what social stories are and why they work](/blog/social-stories-autism-guide). It covers the foundations. The rest of this post assumes you already know the basics and want to write one yourself.
## The One Rule That Matters Most: The 2-to-1 Ratio
If you remember nothing else from this post, remember this. For every coaching sentence in a social story (a sentence that tells your child what to do), the story must include at least two descriptive, perspective, or affirmative sentences (sentences that tell your child what is going to happen, what other people might think, or what is reassuring).
That is the rule. That is the entire difference between a real social story and a behavior demand list with pictures glued on.
Carol Gray's framework calls this the social story ratio, and it is what most parents miss the first time they write one. I missed it. The reason it matters is that the goal of a social story is understanding, not compliance. The whole reason the method works is that it builds a mental model of what a situation will look and feel like, which lowers anxiety, which makes a calmer response possible. If your story is mostly "I will" sentences, you have skipped the understanding step. You have written instructions for a child who is still trying to figure out what is even going to happen.
A useful way to check yourself: read your draft aloud and count. If you have five coaching sentences, you need at least ten descriptive, perspective, or affirmative sentences to keep the ratio honest. If you have fewer, revise. Add the dentist's name. Add what the chair looks like. Add what the bib feels like. Add what the dentist might say. Add what your child might feel. Most parents who write a "directive list" are not bad writers. They are just rushing past the part the child actually needs.
A real social story describes more than it directs. As Carol Gray's framework emphasizes on [her official site](https://carolgraysocialstories.com/), behavior change is a side effect of understanding, not the goal.
## How to Write a Social Story: The 10-Step Recipe
Here is the practical sequence. Each step is short. None of them require a clinical credential. You can write your first story in about an hour.
1. Pick the right topic. Choose one specific situation, not a category. "Dr. Patel's dentist visit on Friday" is a topic. "Going to appointments" is not. The narrower the situation, the more useful the story. Ask yourself: what is the next hard thing on our calendar? What situation reliably ends in a meltdown? What does my child keep asking questions about that I keep failing to answer in a way that sticks?
2. Gather information from your child's perspective. Before you write a single sentence, sit with the question of what your child actually understands and misunderstands about this situation. Sometimes the answer surprises you. Maybe your son is not afraid of the dentist. Maybe he is afraid of the bib clip touching his neck. Knowing the actual fear changes the story you write. Carol Gray calls this Two-Step Discovery: gather information about the situation AND the child, then write.
3. Choose your format and length. Match the format to your child's age, attention span, and reading level. Ages 3 to 5 do best with short sentences, one or two per page, large photos, and six to eight pages total. Ages 6 to 9 can handle a few sentences per page, photos or simple illustrations, and eight to twelve pages. Ages 10 and up can read paragraph format, one to two pages, with fewer images. A story too long to finish in one sitting is a story that does not work.
4. Write the title and introduction. The title should be neutral and descriptive, not corrective. "Going to Dr. Patel's Office" is a good title. "How to Behave at the Doctor" is not. The introduction sets the scene with a descriptive sentence: "On Friday, I have an appointment with Dr. Patel." Calm, factual, low-pressure. You are inviting your child into a story, not giving a briefing.
5. Write the body using mostly descriptive and perspective sentences. Walk through the situation in order. Use the Six Questions as a checklist: where, when, who, what, how, why. For every coaching sentence, write at least two descriptive, perspective, or affirmative sentences. Use literal language. Use "sometimes" and "usually" when something is variable. Never promise something you cannot guarantee. "The dentist will not hurt" is a promise that breaks the story when the cleaning feels uncomfortable. "Sometimes my mouth feels uncomfortable for a little while" is honest, and honest is what holds up.
6. Write the conclusion. Reinforce the main point and end on something the child can hold onto. A coping idea. A reassurance. A reminder of what comes next: "After the appointment, we will go home and have lunch." The last sentence is the one your child will repeat to themselves at the appointment. Choose it carefully.
7. Check the ratio and the tone. Read the whole story aloud. Count your coaching sentences. Count your descriptive, perspective, and affirmative sentences. The descriptive count should be at least double. If it is not, revise. Then check tone. Does the story sound like a friend explaining something kind, or like a parent giving instructions? It should sound like the friend. If it sounds like a script of things you have already nagged about this week, start over.
8. Add visuals. Photos of the actual location and people work best. A photo of the real waiting room. A photo of the actual dentist if you can get one. If you cannot get photos, use [AI-generated images that resemble your child](/blog/ai-generated-images-visual-supports) and your environment, which research and parent reports both suggest land much better than generic clip art. Avoid clip art for young children. The point of a visual is recognition, not decoration.
9. Introduce the story calmly, in advance. Read it together when your child is regulated, not in the moment of crisis. Read it days ahead for big events, multiple times. Make it a quiet, predictable part of the routine. Reading a story for the first time in the car on the way to the dentist is too late. The repetition before the situation is what does the work.
10. Observe, revise, and retire. Watch what happens. If your child resists a section, ask why. Maybe the wording is off. Maybe the picture is wrong. Maybe a promise inside the story did not hold up. Revise. When the situation becomes familiar and the story is no longer needed, retire it. Social stories are tools, not permanent fixtures.
## The Seven Sentence Types (With Examples)
Carol Gray's framework includes seven sentence types. Most parents only need to fluently use the first three or four, but it helps to know all of them so you can tell what is happening when a story is or is not working.
**Descriptive.** States objective, observable facts about a setting, person, action, or event. Example: "On Tuesday, my class has fire drill practice."
**Perspective.** Describes the internal state, thoughts, feelings, beliefs, or knowledge of someone other than the child, or sometimes of the child themselves. Example: "Most children feel surprised when the alarm rings."
**Affirmative.** Stresses an important point, expresses a shared value, or reassures. Often follows a descriptive or perspective sentence. Example: "Fire drills help keep everyone safe."
**Directive (Coaching the Audience).** Gently suggests a response or behavior. Almost always uses softening language: "I will try," "I can," "One thing I might do is." Example: "I will try to walk in line with my class." This is the type to use sparingly. Two of the others for every one of these.
**Coaching the Team.** Coaches the people around the child (parents, teachers, helpers). Read by the team, not by the child. Example: "Mom can remind me to put on my headphones before the alarm rings."
**Coaching the Author.** Self-coaching strategies the child writes for themselves to remember information. Example: "I can think of the alarm as a loud reminder, not a danger."
**Partial Sentences.** Fill-in-the-blank sentences used to check comprehension. The child completes the sentence aloud or in writing. Example: "When the alarm rings, I will try to ____."
A note on the canon: Carol Gray's Social Stories 10.2 criteria, published on her official site in 2018, remain the canonical published reference. Some training programs reference an evolving 10.3, but 10.2 is what almost all peer-reviewed literature cites and what I would point any parent to first.
## 10 Common Mistakes Parents Make
I have written, scrapped, and rewritten dozens of social stories for my son in the last six years. Almost every failed one fell into one of these patterns.
1. Writing a directive list disguised as a story. Six "I will" sentences and one fact. This violates the ratio and turns the story into a behavior demand. A real social story describes more than it directs.
2. Using absolute language. "The dentist will not hurt." "Everyone will be nice to me." Autistic children take statements literally. When the prediction fails even once, the story breaks and so does your credibility. Use "sometimes," "usually," and "most of the time."
3. Writing for parent frustration, not child understanding. Stories drafted in the heat of a hard week tend to have a scolding tone. "When I act this way, my mom feels sad." If you are angry while writing, wait. Come back tomorrow. The child does not need a guilt trip. They need a road map.
4. Wrong tense. A story about an upcoming visit written in past tense is confusing. Match tense to the actual situation. Future events get future tense. Daily routines get present tense.
5. Wrong reading level. Vocabulary that is too advanced, sentences that are too long, or content meant for an older child. The story should feel easy. If your child does not know the word "appointment," do not introduce it in a story whose job is to reduce anxiety.
6. Too long. A 16-page story for a 4-year-old never gets read all the way through. Length should match attention span, not parental thoroughness.
7. Skipping the perspective sentences. Stories with only descriptive and directive sentences miss the entire point. Perspective sentences are what build social understanding, the actual reason Gray invented the method.
8. Reading it only in the moment of crisis. Social stories work through repetition before the situation, not as last-minute interventions. The car ride to the dentist is not when a brand-new story does its job.
9. Never revising. A story that gets resistance probably has something off. Wrong words, wrong picture, wrong promise. Revise it. The first draft is rarely the keeper.
10. Forgetting the affirmative sentences. Half of the story should affirm something the child already does well or feels safe about. Stories that focus only on the hard new thing become discouraging fast.
## Topics That Work Well for Social Stories
These are the situations where a social story tends to land hardest, especially for younger children. Most of them have something in common: a sequence of events, sensory unknowns, and a window of time where preparation is possible.
- **Visiting the dentist or doctor.** High sensory load, unpredictable steps, lots of unfamiliar adults. Walking through what happens reduces anticipatory anxiety. Pair with our [guide to preparing for medical appointments](/blog/preparing-doctor-dentist-visits-autism-adhd).
- **Fire drills at school.** Sudden alarms, a forced transition, sensory overload. The child needs to know in advance that this is rehearsal, not an emergency.
- **Trying a new food.** A story can explain that "trying" does not mean "finishing" and that disliking food is allowed.
- **Getting a haircut.** Touch sensitivity, buzzing sounds, falling hair on skin. A story can name each sensory element so it is not a surprise. Pair with our [sensory-friendly haircuts](/blog/sensory-friendly-haircuts-neurodivergent-children) guide.
- **A new sibling arriving.** Huge identity change, ambiguous timeline, jealousy. Pair with our [new-sibling preparation guide](/blog/preparing-neurodivergent-child-new-baby-sibling).
- **Starting school or changing classrooms.** New environment, new people, new schedule. Include real photos of the actual classroom and teacher when possible. See our [classroom transition guide](/blog/starting-school-prepare-neurodivergent-child-classroom).
- **Birthday parties.** Singing, social pressure, unpredictable food. Stories can preempt the "Happy Birthday" song moment, which is a sensory trigger for many kids.
- **Plane travel.** A long sequence of transitions, sensory chaos, security checks involving strangers and touch.
- **Riding a school bus for the first time.** Loud, crowded, unfamiliar driver, no parent. High anticipatory anxiety.
- **Vaccinations or blood draws.** Brief but high-intensity. Stories should include "the poke might pinch" rather than "it will not hurt."
Pair the social story with a [visual schedule](/blog/visual-schedules-for-autism) for the day, and with [first-then boards](/blog/first-then-boards-guide) for the moment itself. Layered visual supports work harder than any single tool used alone.
## My Son and the Hardware Store Parking Lot
The story that turned things around for us was about going into a big-box hardware store. Lowes one weekend, Home Depot another. My son could not get out of the car. We would pull into the parking lot, and he would freeze. We sat there for an hour at a stretch more than once, watching other families stream in and out of the doors while he tried to make his nervous system catch up. I tried coaxing. I tried distraction. I tried a snack as a reward. None of it worked. The threshold was a wall.
What finally moved him was a social story with personalized images that included him inside the store. Not stock pictures of a generic warehouse aisle. An actual image showing him walking through the wide automatic doors, in those big bright aisles, holding the cart. I wrote the story slowly, with three descriptive sentences for every coaching sentence. I named what was loud, what was bright, what to expect. I ended on something he could hold: that we would pick out one thing he wanted to look at, and then we would go home. We read it together for several days before our next trip.
The next time we pulled into the parking lot, he opened the car door himself. He walked through those automatic doors holding my hand. He went to the aisle in the picture. He was not magically calm, and the trip was not perfect, but he was inside the store, regulated enough to be there, working off a plan he had rehearsed instead of trying to invent one in real time. He did not get stuck in the parking lot that day. He had a routine for the place his nervous system had been treating as unknown.
That story did not change my son. It changed what he could see coming, which changed what his nervous system did with it. That is what the method is actually for. If you take one thing from this post, take that.
For more on the foundations of why this works, our [primer on social stories for autistic children](/blog/social-stories-autism-guide) covers the underlying research and the bigger picture. And if anxiety is the bigger pattern in your home, our piece on [managing anxiety in neurodivergent children](/blog/managing-anxiety-neurodivergent-children-visual-strategies) covers the visual strategies that pair best with the social story method.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that frame your child's day, create [personalized social stories with AI-generated images](/blog/personalized-visuals-neurodivergent-children-routines) that look like your child and your real environment, pair them with [first-then boards](/blog/first-then-boards-guide) for the moment itself, and track [emotional patterns](/blog/managing-anxiety-neurodivergent-children-visual-strategies) so you can see what is working. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://vizyplan.com) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child a story for every hard thing on the calendar.
---
## How to Create a Morning Routine for an Autistic Child
Published: 2026-04-29 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/morning-routine-autistic-child
Category: Strategies
Author: Justin Bowman
> A morning routine for an autistic child is built on sensory regulation, visual structure, and the night before. Here is the parent playbook that actually holds.
The morning didn't start at 7am. It started at 11:30pm last night, when your child was still wide awake, lying in pajamas that itched, while the rest of the house was asleep. You finally got them down a little after midnight. By the time you woke them up six and a half hours later, the morning was already lost.
This is the part nobody tells you about autism and mornings. Half the battle was decided before the sun came up. The other half is decided in the first ten minutes, before your child has eaten, before you have said anything that lands, before anyone has put on a shoe. If you have been told you just need to try a sticker chart and a kitchen timer, that advice was not built for the brain you are parenting.
A morning routine for an autistic child is a different shape than a typical morning routine. It is built on sensory regulation, predictability, and visual structure, in that order. Demands come last. Verbal instructions come last. Productivity comes last. If you have been doing it the other way around and feeling like you are losing every morning, you are not failing. The order was wrong.
This post is the one I wish someone had handed me when my son was three. He was nonverbal until age two, and our mornings were the hardest hour of our day for a long time. What follows is what the research says, what worked for us, and what to actually do tomorrow.
## Why Mornings Hit Autistic Kids Harder
Mornings stack every challenge an autistic nervous system already faces, all at once, before the brain has had a chance to come online. Six things are happening under the surface, and none of them are about behavior.
**Sleep biology is different.** Between 50 and 80% of autistic children have significant sleep problems, compared to 20 to 30% of neurotypical children. Their dim light melatonin onset, the body signal to fall asleep, runs about an hour and seventeen minutes later than their neurotypical peers. A 2025 Mendelian randomization study in the journal Autism, with more than 85,000 participants, showed a causal genetic relationship between late chronotype and autism. Translation: many autistic kids are biologically wired to sleep later and wake later, and the 7am school bell is fighting their genome. The full breakdown lives in our [autism and sleep deep dive](/blog/autism-and-sleep-problems-what-actually-helps), which is the upstream piece this post leans on.
**Executive function is heavier in the morning.** A 2018 meta-analysis in Molecular Psychiatry pooled 235 studies and 14,081 participants and found a moderate effect size (Hedges g = 0.48) for broad executive dysfunction in autism. Planning, working memory, cognitive flexibility, and self-monitoring are all measurably harder. A six-step morning sequence held in working memory is a heavier lift than your child can carry while also regulating sensory input and language processing.
**Sensory input arrives all at once.** A 2009 meta-analysis by Ben-Sasson and colleagues in the Journal of Autism and Developmental Disorders found that atypical sensory features show up in 45 to 95% of autistic children across studies, with the largest differences in under-responsivity, then over-responsivity, then sensation seeking. The differences were greatest for children ages 6 to 9. Mornings stack sensory experiences in rapid succession. Cold sheets to warm air, dark to bright light, silence to running water, soft pajamas to school clothes. A child who wakes already dysregulated will not regulate just because you asked nicely.
**Transitions cost more.** Asleep to awake. Bed to bathroom. Pajamas to clothes. Home to car. Car to classroom. Each shift carries a cost that builds. Our post on [transition strategies for autism](/blog/transition-strategies-autism) goes deeper, but the short version is that visual transition cues outperform verbal ones, especially when the child is tired.
**Interoception fills in the gaps you assume are obvious.** Interoception is the sense that tells the body when it is hungry, thirsty, cold, or needs the bathroom. Garfinkel and colleagues, writing in Biological Psychology in 2016, found that autistic individuals showed difficulty objectively detecting bodily signals while simultaneously experiencing an over-inflated perception of those sensations. "Are you hungry?" often gets a "no" that is not a lie. The body signal is not reaching the conscious brain in time. Our [interoception primer](/blog/interoception-autism-children-hunger-tired-bathroom) covers this in depth.
**Demands themselves can be the trigger.** For autistic children with a [demand avoidance profile](/blog/demand-avoidance-pda-profile-autism-children), the nervous system reacts to a demand as a threat, even a small or expected one. A morning is a demand cascade. Get up, get dressed, eat, brush teeth, put on shoes, get in the car. The same routine that feels structured to one autistic child can feel like a wall to another. PDA flips the playbook.
If your child has ADHD instead of autism, our [companion piece on ADHD morning routines](/blog/morning-routine-tips-adhd) is built for that wiring. The strategies overlap but the levers are different.
## The 8 Elements of an Autism-Friendly Morning
The goal is not productivity. The goal is regulation, then movement, then a calm exit. These eight elements show up in almost every morning routine that actually works for an autistic child.
**A visual schedule on the wall, eye level, in order.** Photos of the steps, in the sequence they happen, posted in the same spot every day. Visuals do not require working memory. They do not require auditory processing. They just sit there, doing the cognitive work the brain does not have spare bandwidth for. Our [visual schedules for autism guide](/blog/visual-schedules-for-autism) is the deeper read here.
**Proprioceptive input within the first ten minutes.** Heavy work and deep pressure are organizing for the autistic nervous system. A bear hug. A weighted blanket squeeze. Wall pushes. Carrying a basket of laundry to the kitchen. Three minutes on a mini trampoline before getting dressed. A small dose of proprioception before the first demand can completely change the next thirty minutes. Our post on [home sensory diet activities](/blog/sensory-diet-home-activities-autism-adhd) has a full menu.
**First/Then for the hardest single transition.** Pick the one transition that always falls apart. Not five. One. Build a [first/then board](/blog/first-then-boards-guide) for that single moment. First socks, then iPad in the car. First brush teeth, then we pick the song. Visual, concrete, and small enough to actually work.
**Visual transition warnings, not verbal commands.** A timer your child can see. A picture card hand-off. Holding up two fingers to mean two minutes. Anything that lets your child see the change coming without having to decode it from your voice. More on this in our piece on [staying regulated during transitions](/blog/staying-regulated-during-transitions).
**Sensory-friendly clothes, prepped the night before.** Tactile sensitivity in autism is well documented, and clothing battles can eat fifteen to thirty minutes of a morning. Lay out the outfit your child will actually tolerate, every night, in the same place. Tags cut, seams checked, fabric the kid trusts.
**A predictable safe-food breakfast.** Because of the interoception gap, autistic children often will not reliably tell you they are hungry, even when they are running on empty. A predictable, low-decision breakfast that the child will actually eat solves the "they refuse food at 7 and crash at 9:30" problem. One or two safe-food options, every day. New foods do not belong in the morning.
**Choice within structure, never open choice.** Autonomy reduces demand-avoidance threat response. Unlimited choice creates decision paralysis. "This shirt or this shirt" works. "What do you want to wear?" does not. Two options, presented visually, every time.
**Co-regulation before self-regulation.** Young autistic children regulate by borrowing the parent's nervous system. If you are running on three hours of sleep and your shoulders are up by your ears, your child is reading that before any verbal instruction reaches them. A calm, slow-bodied parent is part of the routine, not a luxury added on top of it. Our [co-regulation post](/blog/co-regulation-before-self-regulation-neurodivergent-children) is the canonical read.
You do not need every element on day one. Pick three to start. Build from there.
## How to Build a Morning Routine for an Autistic Child in 7 Steps
Use these steps in order. Numbered on purpose. The order matters.
1. Audit your current morning for three days. Do not change anything yet. Just watch. Note where the routine breaks. Which transition. Which sensory moment. Which demand. Most parents are surprised by what the audit reveals. The meltdown at 7:20 over shoes is often actually about the lights coming on at 6:55. You cannot fix a pattern you have not seen.
2. Anchor bedtime first. The morning starts at 8pm the night before, not at 7am. Lay out tomorrow's clothes. Preview the day. Run a calm [bedtime routine](/blog/bedtime-routine-autism-adhd). If sleep itself is the upstream problem, the [autism and sleep deep dive](/blog/autism-and-sleep-problems-what-actually-helps) is where to spend the next thirty minutes of your reading time. A child who slept badly cannot perform a morning routine well, no matter how clever the routine is.
3. Build a visual schedule with photos of your own child doing each step. Five to eight steps, eye level, same spot every day. Use real pictures of your child, not generic clipart. Children recognize themselves in their own routines, which is why [personalized visuals](/blog/personalized-visuals-neurodivergent-children-routines) outperform stock photos. Posted on the fridge or the bathroom mirror works for most families.
4. Front-load proprioceptive input. Pick one heavy-work or deep-pressure activity and put it in the first ten minutes. A weighted blanket squeeze before getting out of bed. A morning hug that lasts ten seconds, not two. Three big jumps on the way to the bathroom. The point is regulation before demand. Make it part of the schedule so it happens every day, not just on hard days.
5. Lock in a safe-food breakfast. One or two predictable options the child actually eats. The same plate, the same cup, the same spot at the table. Mornings are not the time for nutritional ambition. A child who eats the same yogurt and toast every weekday is fed and regulated, and that is a win.
6. Use visual transitions, not verbal commands. A picture card hand-off. A visible timer. A laminated "all done" card. Show the change, do not announce it. Save your voice for warmth and connection, not for instructions your child's brain cannot process at 6:55am.
7. Add a 2-choice autonomy moment. Pick one place in the morning where your child gets a real choice. Which shirt. Which breakfast bowl. Which song in the car. Anchor everything else. The choice is not about the shirt. It is about giving the nervous system a moment of control inside a structure your child did not pick. Especially important for kids with [demand avoidance profiles](/blog/demand-avoidance-pda-profile-autism-children).
Run the new routine for two weeks before you judge it. Autistic children often need repetition to encode a routine, and the first three days will look like nothing is working. The day 10 to 14 mark is where you usually see it click. Do not make changes mid-stream unless something is clearly harming your child. The variable you are testing is consistency.
## What to Do When the Routine Falls Apart
It will fall apart. Some mornings the visual schedule is on the fridge and the proprioceptive input has been delivered and the safe food is on the table and your child still ends up on the floor in one sock with their hands over their ears. That is not a failure of the routine. That is the nervous system telling you what it has today.
When the morning goes sideways, the goal is not to power through. The goal is to stop the cascade. Lower the demand load. Drop something off the list. Pickup a fork for them. Put the shoes on yourself. Skip the brushing for today. Get them safely to where they need to be and let go of the rest.
The morning is not a moral test. It is data. A meltdown over shoes on Tuesday after a 1am bedtime is not a routine problem. It is a sleep problem dressed up as a shoe problem. Note it. Try again tomorrow. Some days the answer is "we got out the door" and that is the entire win.
If your child has been holding it together at school all day and falling apart for you in the morning, that is not them being harder on you. That is them trusting you with the dysregulation they were not safe to show anywhere else. Mornings are often where the day's regulation budget gets spent before the day even starts. Our post on [co-regulation](/blog/co-regulation-before-self-regulation-neurodivergent-children) is worth reading on the days that fall apart hardest, because the most useful thing you can do in those moments is slow your own body down first.
## A Note from Me
The morning that taught me most of this happened when my son was about three. We had been losing every morning. I was repeating "put on your shoes" three, four, five times. He was not ignoring me. The words were just not landing. I could see it in his face.
That morning I stopped talking. I taped a strip of pictures on the fridge with our actual phone photos. Wake up. Go potty. Eat. Get dressed. Shoes. Door. I pointed to the next picture instead of saying anything. He looked at the picture. Then he did the thing.
We were out the door in fifteen minutes. No yelling. No tears. The pictures had been doing the work my voice could not. That was the morning I learned that for my son, visual structure was not a nice extra. It was the language his brain could read at 7am when nothing else could get through. We have been building from that morning ever since.
That is the shift this post is asking you to make. Not a perfect routine. A routine your child's brain can actually read.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build a [visual morning routine](/blog/visual-schedules-for-autism) with personalized photos of your own child, anchor sensory regulation with proprioceptive input before the first demand, and create [first/then boards](/blog/first-then-boards-guide) for the transitions that always fall apart. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## Gestalt Language Processing: Why Your Child Speaks in Scripts
Published: 2026-04-26
URL: https://vizyplan.com/blog/gestalt-language-processing-parents-guide
Category: Communication
Author: Justin Bowman
> Your child quotes Bluey instead of asking for snacks. They sing songs before they say words. They speak in long phrases that sound like memorized scripts. There is a name for that, and it is not a problem to fix.
Your three-year-old walks up to you in the kitchen and says, in the exact voice of a Bluey character, "Want to play, Dad?" An hour later, when the iPad runs out of battery, they melt down and yell, "It is broken, it is broken, it is broken," in the cadence of a YouTube clip you have heard a hundred times.
If you have been told this is "non-functional language" or that your child has a "language delay" because they cannot reliably name a single object, this post is for you.
What you are seeing has a name. It is called gestalt language processing. And once you understand it, almost everything your child says starts to make sense.
## What Gestalt Language Processing Actually Means
Most kids learn language one piece at a time. They start with single words like "ball" or "milk," then string two words together, then three, and slowly build sentences. This is called analytic language development, and it is the model nearly every parenting book, pediatrician chart, and speech goal is built around.
But many children, especially autistic children, do not learn this way. They acquire language in chunks. Whole phrases, full sentences, entire songs, memorized as single units. Then, slowly, they break those chunks down into smaller pieces and start to recombine them.
That is gestalt language processing. The word gestalt comes from a German word meaning "whole" or "form." The child is processing language as a whole shape rather than as a series of individual parts.
This idea is not new. Researcher Ann Peters described two language acquisition styles in the 1980s. Speech-language pathologist Barry Prizant studied [echolalia in autistic children](/blog/echolalia-communication-autism-scripting) and showed that what looked like meaningless repetition actually served at least 14 different communicative purposes. More recently, SLP Marge Blanc built on this work in her 2012 book Natural Language Acquisition on the Autism Spectrum, where she described six developmental stages that gestalt processors move through on the way to flexible, original speech.
The framework went mainstream in parent communities and on SLP social media over the past few years. It is now one of the most-discussed topics in autism speech-language work, and it has changed how a lot of families understand what their kids are doing.
## The Six Stages, in Plain Language
Marge Blanc's protocol describes six stages of gestalt language development. You do not need to memorize them, but understanding the arc helps you see where your child is and what comes next.
**Stage 1: Whole Gestalts.** Your child speaks in long memorized chunks. A line from Frozen. A phrase from Mom. The opening of a song. They might not have many useful single words yet, but they are saying entire sentences with strong rhythm and intonation. It can sound like fluent speech, which makes it confusing when the same child cannot reliably ask for water.
**Stage 2: Mitigated Gestalts.** Your child starts mixing and trimming the chunks. Two scripts get smashed together. A phrase loses its tail. You hear "Let it go" combined with "Time to brush teeth" and you realize they are starting to manipulate the pieces.
**Stage 3: Single Words and Two-Word Combinations.** The chunks have been broken down enough that single words start coming out as standalone units. Your child uses "open" or "more" or "go" the way another child might have at age one. Then two-word combinations show up, often surprising and original. This is a huge breakthrough, even though it can look like a child who "should be talking more by now" finally catching up.
**Stage 4: Beginning Original Sentences.** Your child puts together their own short sentences. Grammar is loose. Verb tenses get mixed. But the words are theirs, generated for the moment, not pulled off a memorized track. "I want juice" becomes possible.
**Stage 5: Complex Sentences with Developing Grammar.** Sentences get longer. Plurals appear. Past tense shows up. Your child can talk about what happened yesterday, what might happen tomorrow, what someone else did across the room.
**Stage 6: Original Speech with Complete Grammar.** Self-generated, grammatically complete language. The path from echolalia to here is long, and not every child reaches stage six in the same timeline. But many do, and many of them end up sounding nothing like the early days of memorized scripts.
The key insight: progress in this model does not look like single words building into sentences. It looks like big chunks getting smaller, then more flexible, then original. The order is reversed from what most milestone charts assume.
## How to Recognize a Gestalt Language Processor at Home
Some kids fit this profile clearly. Others are subtle. Here is what parents and SLPs commonly notice.
**They speak in long phrases before they have many single words.** A two-year-old who can say "To infinity and beyond" but cannot reliably say "milk" is not failing at language. They are processing it differently.
**The intonation is unmistakable.** Gestalt processors are sometimes called "intonation babies" because they pick up the music of language before the lexicon. Your child sounds exactly like the character or person they learned the phrase from. The melody is the giveaway.
**Songs come before speech.** Many gestalt processors sing before they reliably talk. Theme songs. Lullabies. Commercial jingles. The whole song comes out fluently, then breaks down into pieces over time.
**Scripts seem random until they are not.** Your child quotes a movie line that has nothing to do with what is happening. But if you start watching, you might notice they only quote that line when they feel a specific way. The script is doing emotional work. It is communication, just not the kind we expect.
**They use media to communicate.** Your child opens YouTube to a specific video clip when they feel a certain way. They navigate to a particular scene to show you what they need. The media is the language.
**Single words feel "stuck."** Some children pick up single words but cannot combine them. The word sits there, used to label things, but not used in sentences. This is a clue that the child may be a gestalt processor whose system is wired for chunks, not single-word building blocks.
## What to Do Right Now
You do not need a clinical credential to start supporting a gestalt processor. The basic moves are simple, and most of them are about what you stop doing as much as what you start.
**Listen for the function, not the words.** When your child says a script, ask yourself what they might be communicating. Are they tired? Hungry? Excited? Overwhelmed? Anxious? The same script can carry different meanings in different moments. Track which scripts come up where, and patterns emerge.
**Respond to intent.** If your child says "Time to go home" while they are playing happily at the playground, they may not be saying they want to leave. They might be saying they feel anxious about what comes next. Reply to what you think they mean. "You sound a little worried. We have ten more minutes here, then we will go home."
**Reduce questions, increase comments.** Questions feel like a quiz to a child who is processing language as whole chunks. They have to find the right verbal token to send back, which is a huge ask if the tokens are still locked inside larger gestalts. Narration is easier. Instead of "What do you want to do?" try "I see you got the blocks out. The red one is on top." Comments give your child language to absorb without demanding a verbal response.
**Use "we" instead of "you" or "I."** Pronouns are notoriously tricky for gestalt processors. If you model with "you" pronouns, your child will repeat the script back exactly, and end up saying "you want a snack" when they mean "I want a snack." Modeling with "we" keeps the language usable in either direction. "We can have a snack" works for both of you.
**Model short, useful gestalts.** Your child is going to acquire language in chunks anyway. Give them chunks that are short, functional, and easy to flex. "Let us go." "All done." "I need help." "More, please." These are gestalts your child can reuse across many situations.
**Do not try to eliminate scripting.** This is the biggest mindset shift for many parents. The scripts are not noise to filter out. They are your child's vocabulary at this stage, and they will eventually break down into more flexible pieces if your child has the time and space to do that work. Interrupting or redirecting echolalia teaches your child that their communication is not welcome, which makes the whole process harder.
**Track which scripts show up when.** A simple note in your phone or [an emotion log](/blog/tracking-emotions-activities-neurodivergent-children) can reveal a lot. The line your child quotes when they need a hug. The phrase that comes out when the lights are too bright. The song they sing when transitions are coming. Once you see the patterns, you can respond to the underlying need before the script has to do all the work.
## How Visual Supports Help Gestalt Processors
This is where the day-to-day mechanics of family life come in. Gestalt processors often have less spare bandwidth for figuring out what is happening next, which means visuals do extra heavy lifting.
A clear [visual schedule](/blog/visual-schedules-for-autism) reduces the cognitive load of guessing what comes next. When your child can see the day laid out, they need fewer scripts to manage uncertainty. The schedule itself becomes a shared reference, and you can say things like "First snack, then park" and point, instead of relying on long verbal explanations.
[Social stories](/blog/social-stories-autism-guide) give your child new useful gestalts in a low-pressure way. A short story about going to the dentist, written in the voice and rhythm your child already responds to, hands them ready-made scripts they can pull out when the moment comes. You are not eliminating their scripting. You are expanding the script library with phrases that fit the situations they actually face.
[First-then boards](/blog/first-then-boards-guide) and [choice boards](/blog/choice-boards-empowering-decisions) break communication into small visual pieces, which works beautifully for kids whose verbal output is still mostly scripts. They give your child a way to make a request or a decision without having to find the right gestalt under pressure.
## The Honest Part About Evidence
I am going to be straight with you, because you have probably seen this framework presented as either the answer to everything or as pseudoscience, and the truth lives somewhere in the middle.
The original idea that echolalia is communicative is well-supported. Prizant's work on this has been cited and replicated for decades, and you would be hard-pressed to find a current SLP who would tell you to ignore your child's scripts.
The specific six-stage protocol from Marge Blanc, the Natural Language Acquisition framework, has not yet been studied in controlled, peer-reviewed intervention trials. A 2024 systematic review presented at the American Speech-Language-Hearing Association found no full-text intervention studies on the protocol itself. Some clinicians have raised real concerns about specific recommendations and goal-writing within the framework. Other clinicians who use it report meaningful progress with their clients.
What this means for you, as a parent: the broad ideas, that echolalia has meaning, that scripts are communication, that your child is doing real language work in their own way, are well-grounded. The very specific stage-by-stage protocol is newer and less validated. Many SLPs use a flexible blend of GLP-informed strategies and other evidence-based approaches.
If you are looking for [an SLP](/blog/finding-right-therapist-neurodivergent-child), ask whether they understand gestalt language processing and how they incorporate it. If you are evaluating advice you see online, look for the warm, child-led, function-focused suggestions and be cautious of anything that promises a fixed timeline or dismisses individual variation.
You do not need to commit to a clinical position. You just need to see your child more clearly, and respond to the language they actually have.
## What My Son Taught Me About Scripts
My son was nonverbal until age two. When language started coming, it came in chunks. Lines from his favorite shows. The exact phrasing his early intervention therapist used. Songs. For a long time, well-meaning people would tell me he was "just repeating" and that we needed to redirect to "real" language.
He was speaking real language. We were the ones not listening.
The day I realized this, he was lining up cars on the floor and saying "Five, six, seven, eight" in the rhythm of a counting song. I almost ignored it. Then I noticed he was actually counting his cars. The script was carrying real meaning. It was just borrowed packaging.
That moment changed how I parented. I stopped trying to translate his scripts into "proper" speech and started listening for what they were doing for him. The redirecting stopped. The narrating started. We added [visual schedules](/blog/visual-schedules-for-autism), [emotion tracking](/blog/tracking-emotions-activities-neurodivergent-children), and short modeled phrases he could borrow. Within months, the scripts started bending. Pieces broke off. New combinations showed up. He was doing the work all along. He just needed us to stop interrupting it.
## Where to Go From Here
If you suspect your child is a gestalt language processor, here is what I would do, in order.
**Read the [echolalia companion post](/blog/echolalia-communication-autism-scripting).** It pairs with this one and goes deeper into the communicative functions of scripting.
**Watch your child for a week.** Note the scripts. Note the contexts. Note the intonation. You will start to see the system.
**Stop redirecting.** Replace it with comments, narration, and "we" language.
**Build out your visual supports.** A predictable day with [calmer transitions](/blog/transition-strategies-autism) gives your child more bandwidth for language work.
**Talk to your SLP.** If you are on a [therapy waitlist](/blog/therapy-waitlist-what-to-do-at-home), use the time to learn what stage your child is in and try the at-home strategies above. If you have an SLP, ask how they support gestalt language processors and how they think about your child specifically.
**Be patient.** Gestalt language development can move slowly, then suddenly. Children sit at one stage for months, sometimes longer. Then a piece breaks off, a chunk recombines, and progress shows up in a rush. Your job is not to push the timeline. It is to keep the conditions right.
## Your Child Is Already Talking
The hardest thing about being the parent of a gestalt processor is that the world will keep telling you your child has a language delay. The world is using the wrong yardstick. Your child has been talking the whole time. They have been telling you what they need, what they feel, what they are afraid of, in the language they have. Movie lines and song lyrics and YouTube scripts and that one thing Grandma said three months ago.
Once you start listening differently, you will hear them.
That is the shift. That is what gestalt language processing offers, more than any specific stage chart or protocol. The permission to listen to your child the way they are actually speaking, instead of the way you were taught to expect.
Your child is communicating. You just learned a new language.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that give your child predictable scripts for their day, [track emotional patterns and the contexts where scripts show up](/blog/tracking-emotions-activities-neurodivergent-children), and create [social stories](/blog/social-stories-autism-guide) that expand your child's library of useful gestalts. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## What Autism Acceptance Actually Looks Like at Home
Published: 2026-04-25
URL: https://vizyplan.com/blog/autism-acceptance-what-it-looks-like-at-home
Category: Parenting
Author: Justin Bowman
> Autism Acceptance Month fills your feed with blue puzzle pieces and hashtags. But what does acceptance actually look like inside your house, on a Tuesday, when your child is melting down and dinner is burning?
It is April, which means your social media feed is full of infinity symbols, red hashtags, and posts about Autism Acceptance Month. Celebrities are sharing infographics. Brands are turning their logos gold. Everyone, it seems, has something to say about acceptance.
And then you close your phone and walk into your kitchen, where your child is screaming because the toast broke in half and now the whole morning is ruined.
That is the gap this post is about. Not the public performance of acceptance, but the private, unglamorous, Tuesday-at-7 a.m. version. The one that happens when nobody is watching and there is no hashtag for what you are feeling.
## The Gap Between the Feed and the Floor
Here is what autism acceptance looks like on Instagram: a smiling child in a graphic tee that says "different not less." A parent holding a sign at a walk. A beautifully designed quote about neurodiversity being a superpower.
Here is what autism acceptance looks like in your house: sitting on the bathroom floor at 9 p.m. because your child cannot brush their teeth without gagging and you are trying to figure out if you should push through or let it go. Canceling plans again because today is not a "going places" day. Watching other four-year-olds have conversations at the playground while your child lines up wood chips in a row, alone, and you feel something you cannot name.
The gap between those two versions is where most parents actually live. And it is in that gap where real acceptance has to be built, if it is going to mean anything at all.
## What Acceptance Is Not
Before we talk about what acceptance is, let me be honest about what it is not. Because there is a version of "acceptance" floating around that makes parents feel worse, not better.
**Acceptance is not pretending everything is fine.** If your child is struggling, you do not have to smile and call it beautiful. Struggle is struggle. It can coexist with love and acceptance, but you do not have to perform joy about the hard parts.
**Acceptance is not ignoring challenges.** Your child may need speech therapy, occupational therapy, behavioral support, or all three. Seeking help for your child is not a rejection of who they are. It is an investment in giving them tools to navigate a world that was not built for their brain.
**Acceptance is not toxic positivity.** "Everything happens for a reason." "God gives special children to special parents." "They will grow out of it." These phrases are not acceptance. They are avoidance dressed up in a greeting card font.
**Acceptance is not the absence of grief.** This is the one that trips up the most parents, so I want to be very clear: you can grieve and accept at the same time. They are not opposites. Grief is not a sign that you have failed at acceptance. It is a sign that you are human, that you love your child, and that some of this is genuinely hard.
## What Acceptance Actually Is
So if acceptance is not a hashtag and it is not toxic positivity, what is it?
It is a series of small, daily decisions that change how you see your child and how your child sees themselves.
### Adjusting Expectations to Match Your Child's Neurology
This is the foundation. Your child's brain is wired differently. Not worse, not broken, but differently. And that means the milestones, timelines, and benchmarks you absorbed from parenting books, pediatrician charts, and other families may not apply.
Acceptance means stopping the mental comparison and asking instead: what is realistic for this child, with this brain, at this moment?
Maybe your five-year-old cannot sit through a restaurant meal. That is not a failure of parenting or a behavior problem. It is a sensory and executive function reality. Acceptance looks like eating at home more often, choosing restaurants with outdoor seating, or going during off-peak hours instead of forcing your child into an environment that overwhelms them and then being frustrated when they cannot cope.
### Stopping the Comparison Game
You know the game. You play it at the playground, at birthday parties, at school pickup. You watch the neurotypical kids and you measure the distance between them and your child.
Acceptance is choosing, over and over, to stop measuring that distance. Not because it does not exist, but because it tells you nothing useful. Your child is not on the same path as those children. They are on their own path, with their own pace.
### Letting Go of the Timeline
"They should be talking by now." "They should be potty trained by now." "They should be able to handle this by now."
Should, according to whom?
Acceptance means releasing the "by now" and replacing it with "not yet" or even "maybe never, and that is okay too." Some milestones will come late. Some will come in unexpected forms. Some may not come at all, and your child will find their own way to navigate those spaces.
### Celebrating Different Kinds of Progress
When you let go of the standard milestones, you start to see the ones that actually matter for your child.
Today they tolerated the hand dryer in the bathroom without covering their ears. Today they pointed at something they wanted instead of screaming. Today they let their sibling sit next to them on the couch.
These are enormous victories. They do not show up on any developmental chart, but they represent real neurological growth, real emotional work, real bravery from a small person navigating a world that is too loud, too bright, and too unpredictable.
[Tracking these moments](/blog/tracking-emotions-activities-neurodivergent-children) matters. Not for data, but for perspective. On the hard days, and there will be many, you need evidence that progress is happening.
### Accommodating Instead of Forcing Compliance
This is where acceptance gets practical, and sometimes controversial.
The old model of autism parenting was built on compliance: make the child fit the environment. Sit still. Make eye contact. Use your words. Stop flapping. Be quiet. Act normal.
Acceptance flips this. Instead of asking "how do I make my child behave in this situation?" you ask "what does my child need to function in this situation?"
Maybe they need noise-canceling headphones at the grocery store. Maybe they need a [visual schedule](/blog/visual-schedules-for-autism) so they know what is coming next. Maybe they need to leave the birthday party after thirty minutes. Maybe they need to stim during class because it helps them focus.
These are not accommodations that spoil your child. They are accommodations that respect your child's neurology.
## How Acceptance Changes Your Parenting
When you move from "fix the behavior" to "understand the need," everything shifts.
Your child is not giving you a hard time. They are having a hard time. That reframing, which you have probably heard before, is acceptance in a single sentence.
A meltdown is not defiance. It is [dysregulation](/blog/emotional-regulation-visual-supports). Rigidity is not stubbornness. It is a coping mechanism for a world that feels chaotic. Avoidance is not laziness. It is [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies).
When you parent from acceptance, you stop fighting the behavior and start addressing the root cause. You move from consequences to [co-regulation](/blog/co-regulation-before-self-regulation-neurodivergent-children). You move from punishment to problem-solving. You move from "what is wrong with you?" to "what do you need?"
## Acceptance and Your Child's Self-Image
Here is the part that makes this urgent and not just philosophical: your child is watching how you respond to their neurodivergence. And from your response, they are building their understanding of themselves.
If they see frustration every time they struggle, they learn: I am a problem. If they see disappointment when they cannot do what other kids do, they learn: I am not enough.
But if they see patience when things are hard, they learn: hard things are okay. If they see accommodation instead of forced compliance, they learn: my needs matter. If they see you [celebrating their strengths](/blog/celebrating-neurodivergent-strengths-children), they learn: I have value exactly as I am.
This is why [telling your child about their diagnosis](/blog/telling-child-about-autism-adhd-diagnosis) matters, when the time is right. Because a child who understands their own brain is a child who can [advocate for themselves](/blog/teaching-self-advocacy-skills-neurodivergent-child). And self-advocacy starts with self-acceptance. And self-acceptance starts with you.
## Teaching Your Child to Accept Themselves
You cannot hand your child a pamphlet on self-acceptance. But you can model it in how you talk about their brain.
"Your brain works differently, and that is why loud sounds feel so big to you. Let us figure out what helps."
"Some kids can sit still for a long time. Your body needs to move. That is okay. Let us find ways to move that work at school."
"You are not bad at making friends. You make friends differently. Let us practice some ways to say hello that feel comfortable for you."
Language matters. The words you use become the words they use inside their own head. Make those words kind. Make them honest. Make them accepting.
You can also build acceptance into daily routines. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you create visual routines that are designed around your child's actual needs, not around what a "typical" child's day should look like. When a child follows a routine that was built for their brain, the implicit message is: your way of doing things is valid.
## The Grief That Coexists
I said we would come back to this, so here it is, the honest part.
You can accept your child completely and still grieve sometimes. Grief does not mean you wish your child were different. It can mean you wish the world were easier for them. It can mean you are mourning the parenting experience you imagined before you had the parenting experience you got. It can mean you are exhausted and scared and wondering if you are doing enough.
That grief does not disqualify you from acceptance. It qualifies you. Because acceptance that has never been tested by hard feelings is just theory. Acceptance that survives the grief, that coexists with the tears and the fear and the 2 a.m. worry, that is the real thing.
You do not need to resolve the grief to be an accepting parent. You just need to keep choosing your child, as they are, in the middle of it.
## Acceptance Is Not a Destination
You will not wake up one Tuesday and think, "I have arrived at acceptance." It is not a place you get to. It is a practice you return to, over and over, on good days and terrible ones.
Some days acceptance will feel easy and natural. Your child will do something extraordinary in their own way, and your heart will crack open with pride, and you will not need anyone to tell you that your kid is amazing.
Other days acceptance will feel like a discipline. You will be tired. You will be frustrated. You will catch yourself thinking thoughts you are not proud of. And then you will take a breath, and you will come back. You will come back to the child on the floor, the child who needs you to see them, not the version of them you imagined, but the version of them who is right here, right now, real and whole and yours.
That is what acceptance looks like at home. Not a hashtag. Not a bumper sticker. Not a perfect parent who never struggles.
Just a parent who keeps showing up, keeps adjusting, keeps learning, and keeps choosing their child exactly as they are.
That is enough. You are enough.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines designed around your child's actual needs](/blog/visual-schedules-for-autism), [track emotional patterns and celebrate real progress](/blog/tracking-emotions-activities-neurodivergent-children), and support [self-advocacy and self-acceptance](/blog/teaching-self-advocacy-skills-neurodivergent-child) one day at a time. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## The Last Day of School Is Coming. Your Child Needs You to Prepare Now.
Published: 2026-04-24
URL: https://vizyplan.com/blog/end-of-school-year-transitions-neurodivergent-children
Category: Daily Routines
Author: Justin Bowman
> The end of the school year brings a tidal wave of change. For neurodivergent children, losing the structure of school can trigger anxiety, regression, and meltdowns. Here is how to prepare them before the last bell rings.
The calendar says April, but your child's body already knows something is shifting. Maybe the meltdowns have gotten bigger. Maybe bedtime has turned into a battlefield again. Maybe they are clinging to you at drop-off for the first time in months.
The end of the school year is coming, and for neurodivergent children, it does not arrive on the last day. It starts now, weeks before the final bell rings, in subtle waves of anxiety that build until the whole routine collapses.
If you are reading this in late April, you are not too early. You are right on time. And the work you do in the next few weeks can make the difference between a summer that starts with chaos and one that starts with confidence.
## Why the End of School Hits So Hard
For most kids, the end of the school year means freedom. Popsicles. Sleeping in. No homework. But for children who are autistic, have ADHD, or process the world differently, the end of school means something else entirely: the loss of the most predictable structure in their life.
Think about what school provides. A wake-up time. A drop-off routine. A schedule posted on the wall with times and transitions mapped out. A lunch that happens at the same time every day. Familiar adults. Familiar peers. Familiar hallways and smells and sounds.
Now imagine all of that disappearing in a single day.
Research on summer regression, sometimes called the "summer slide," shows that children with autism and ADHD are especially vulnerable to skill loss during unstructured breaks. A 2016 study published in *Autism Research and Treatment* found that children on the spectrum can lose weeks of behavioral and academic progress during summer months, particularly when routines are not maintained. The regression is not just academic. It is behavioral, emotional, and social.
But here is the part most parents miss: the anxiety about losing that structure does not wait for June. It starts the moment your child senses the shift. And they sense it before you do.
## The Hidden Stressors of May and June
The last weeks of school are packed with events that are supposed to be fun but are actually a sensory and emotional minefield for neurodivergent kids.
**Field days.** Loud, chaotic, outdoors, with disrupted schedules and unfamiliar activities. For a child who relies on predictability, field day can feel like being dropped into a different school entirely.
**Assemblies and award ceremonies.** Crowded gymnasiums with echoing microphones, unexpected applause, and the pressure to sit still for extended periods. If your child does not receive an award, there is the added emotional weight of watching peers get recognized.
**Classroom parties.** Sugar, noise, unstructured social time, and the implicit expectation to "have fun" on demand.
**Goodbye conversations.** Teachers start talking about next year. Friends start talking about summer plans. The subtext your child hears: everything is about to change, and I do not know what comes next.
**Schedule changes.** The last weeks often bring modified schedules, substitute teachers covering for end-of-year meetings, and a general loosening of the structure that held the year together.
Each of these is a transition. And if your child struggles with [transitions](/blog/transition-strategies-autism), the final weeks of school are not a celebration. They are a marathon of exactly the thing that is hardest for them.
## Signs Your Child Is Already Feeling It
You might not connect the dots right away because the behaviors can look like "acting out" rather than anxiety. But watch for these patterns:
**Increased meltdowns over small things.** The real trigger is not the wrong color cup. It is the low-level dread of everything changing. When the emotional bucket is already full, even a small thing makes it overflow.
**Sleep disruption.** Trouble falling asleep, waking in the night, or early morning waking. Anxiety loves bedtime, because bedtime is when a child's brain has nothing else to focus on. If your [bedtime routine](/blog/bedtime-routine-autism-adhd) has suddenly stopped working, this might be why.
**Clinginess or separation anxiety.** A child who was doing fine at drop-off suddenly does not want to let go of your hand. They are practicing the goodbye they are dreading.
**Regression in skills.** Toileting accidents. Forgetting routines they had mastered. Increased stimming. These are not steps backward. They are signs that your child's nervous system is overwhelmed and pulling resources from "higher" functions to manage the stress underneath.
**Rigidity or controlling behavior.** When everything feels uncertain, some children cope by trying to control the few things they can.
**Emotional flatness or withdrawal.** Not every child gets louder when they are stressed. Some get quieter. If your child has pulled back from activities they usually enjoy, pay attention. This is especially common in children who [mask at school](/blog/autism-masking-young-children-exhausting) and come home depleted.
## What You Can Do Right Now
You have a window. Use it. The strategies below are not about making the transition painless, because honestly, it will still be hard. They are about giving your child's brain the information it needs to feel safer in the shift.
### Build a Visual Countdown
Children who struggle with time concepts need to see the transition coming. A visual countdown calendar that marks the remaining school days gives them something concrete to reference instead of a vague, anxiety-producing "soon."
This does not need to be complicated. A paper chain they remove one link from each day. A calendar with stickers. A [visual schedule](/blog/visual-schedules-for-autism) in [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) that counts down the days and shows what is happening each week between now and the last day.
### Create Social Stories for End-of-Year Events
If your child has field day, an awards assembly, or a class party coming up, do not just tell them about it. Show them. A [social story](/blog/social-stories-autism-guide) walks through what will happen, what it will look and sound like, and what your child can do if they feel overwhelmed.
You can build these in [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) with images that match each step: "First, we will walk to the field. There will be loud music. I can wear my headphones. Then we will do three activities with my class."
### Start Your Summer Schedule Now
Do not wait until June to figure out what summer looks like. Build a draft of your summer visual schedule while school is still in session. This does two things: it gives you time to think it through, and it gives your child a preview of what is coming.
You do not need every day planned. You need the bones: wake-up time, mealtimes, outdoor time, screen time boundaries, and any camps or activities. The [summer regression research](/blog/summer-regression-school-to-summer-transition-autism-adhd) is clear that maintaining some structure, even a loose one, significantly reduces skill loss and behavioral challenges.
Show your child the summer schedule before school ends. Let them see it. Let them ask questions. Let them contribute ideas.
### Talk About What Stays the Same
Transitions are terrifying because everything feels like it is changing. Counter that by explicitly naming what is not changing.
"You will still sleep in your bed. We will still have pancakes on Saturday. You will still see Grandma on Wednesdays. Your toys will still be here. I will still be here."
This sounds simple, but for a child whose brain is cataloging every change and flagging it as a threat, hearing what remains constant is genuinely calming.
### Prepare for Goodbyes
For some children, the hardest part of the school year ending is leaving people behind. Their teacher. Their aide. Their one safe friend.
Do not minimize this. "You will see them next year" does not help a child who lives in the present moment and feels this loss as real and immediate.
Instead, create a goodbye ritual. Help your child make a card or a small gift. Take a photo with their teacher. If possible, arrange a summer playdate with their friend so "goodbye" becomes "see you later."
### Use the "Then" Strategy for Hard Events
For every stressful end-of-year event, pair it with something your child can look forward to afterward. "First field day, then we get smoothies." "First the assembly, then we go to the park."
This is not bribery. It is a [co-regulation strategy](/blog/co-regulation-before-self-regulation-neurodivergent-children) that gives the brain a landing pad on the other side of the hard thing.
### Check In With Their Body
Your child may not be able to articulate "I am anxious about summer." But their body is talking. Help them notice it.
"I see your shoulders are up by your ears. I wonder if your body is feeling worried about something."
[Tracking emotions](/blog/tracking-emotions-activities-neurodivergent-children) during this transition period can help you spot patterns and identify which specific changes are driving the most distress.
## The Gift of a Gradual Transition
There is a reason therapists talk about "transition plans" and not "transition moments." Transitions are not events. They are processes. And the children who do best are the ones whose parents start the process early.
You are reading this in late April. You have weeks, not days. That is a gift.
Use those weeks to build the bridge between school and summer, one visual, one conversation, one social story at a time. Your child's brain is already working on this transition whether you help or not. The question is whether they do it alone in a swirl of anxiety, or whether they do it with you, with tools, with a plan they can see.
You cannot make the last day of school easy. But you can make it expected. And for a neurodivergent child, expected is everything.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual countdowns and summer schedules](/blog/visual-schedules-for-autism) your child can see, create [social stories for end-of-year events](/blog/social-stories-autism-guide), and [ease every transition](/blog/transition-strategies-autism) between now and the last bell. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## Water Safety and Autism: What Every Parent Needs to Know
Published: 2026-04-23
URL: https://vizyplan.com/blog/water-safety-autism-drowning-prevention
Category: Parenting
Author: Justin Bowman
> Drowning is the leading cause of death for children with autism who wander. As summer approaches, here is what the research says and what you can do to keep your child safe around water.
This is not the blog post I want to write. But it is the one I need to write, and the one you need to read. Especially with summer coming.
Drowning is the leading cause of death for children with autism who wander. Not a leading cause. *The* leading cause. According to data from the National Autism Association, children on the autism spectrum are 160 times more likely to die from drowning than the general pediatric population. That statistic should stop every parent in their tracks.
This post is not meant to scare you. It is meant to prepare you. Because the difference between a tragedy and a close call almost always comes down to layers of prevention that parents put in place before anything happens.
## Why Autistic Children Are Drawn to Water
To protect your child, you first need to understand why water is so magnetic for many kids on the spectrum. It is not one reason. It is several working together.
**Sensory fascination.** Water provides intense, multi-sensory input. The visual shimmer of light on a pool surface. The sound of running water. The pressure of being submerged. The temperature change on skin. For a child with [sensory processing differences](/blog/sensory-processing-daily-routines), water can be irresistible in a way that neurotypical children do not experience with the same intensity.
**Calming properties.** Many autistic children find water deeply regulating. The hydrostatic pressure of being in water functions like a full-body compression, similar to a weighted blanket. For a child whose nervous system is frequently in overdrive, water feels like relief. They are not being reckless. They are seeking regulation.
**Reduced danger awareness.** Many children on the spectrum have difficulty assessing risk, particularly around situations they have not personally experienced as dangerous. A pool looks inviting. A pond looks interesting. The concept that water can be lethal is abstract, and abstract concepts are exactly the kind of information that can be hardest for autistic children to internalize.
**The elopement connection.** This is the factor that turns a risk into a crisis. If you have read about [elopement and wandering prevention](/blog/elopement-wandering-autism-prevention-safety), you know that nearly half of autistic children wander from safe environments. When a child who is drawn to water also has a tendency to elope, every unsecured body of water within reach becomes a potential emergency. Research published in *Pediatrics* found that in cases of lethal drowning among autistic children, the majority occurred after the child wandered from a supervised setting and reached water within minutes.
## The Layers of Protection Model
No single safety measure is enough. Water safety for autistic children requires what safety professionals call "layers of protection," multiple barriers so that if one fails, another catches the risk.
### Layer 1: Physical Barriers
This is the most critical layer. Barriers between your child and water should be present at all times.
- **Pool fencing**: If you have a pool, it needs a four-sided fence with a self-closing, self-latching gate. The latch should be out of your child's reach. The American Academy of Pediatrics recommends fences at least four feet high with no footholds. This single measure reduces childhood drowning by more than 50%, according to a meta-analysis in *Injury Prevention*.
- **Door and window alarms**: Every door and window that leads to a yard, pool area, or any path to water needs an alarm. Inexpensive magnetic door alarms cost under fifteen dollars and provide an audible alert the moment a door opens.
- **Pool alarms**: Surface wave alarms and subsurface alarms detect when someone enters the water. They are not a substitute for fencing, but they add another layer.
- **Locks**: Deadbolts, chain locks, and childproof door covers on all exterior doors. Some families install locks at the top of doors where children cannot reach.
- **Neighbor awareness**: If your neighbors have pools, hot tubs, or ponds, have a direct conversation with them about your child's tendencies. Ask about their fencing.
### Layer 2: Supervision Strategies
Barriers fail. Gates get left open. Doors get propped. Supervision is the layer that catches what barriers miss.
- **Designated water watcher**: At any gathering near water, assign one adult whose only job is watching the children in or near the water. No phone. No conversation. No food preparation. Just eyes on the water. Rotate every 15 to 20 minutes to prevent fatigue.
- **Touch supervision for high-risk children**: If your child is a known elopement risk and you are near any body of water, maintain touch supervision, meaning you are close enough to reach out and grab them at all times.
- **Constant head counts**: At pools, lakes, and beaches, count your children every 30 seconds. Drowning can happen in under two minutes and is almost always silent.
### Layer 3: Technology and Tracking
Technology adds another safety net, and modern options have become remarkably effective.
- **GPS tracking devices**: Wearable GPS trackers designed for children with autism (AngelSense, Jiobit, and Apple AirTag attached to clothing or shoes) allow you to locate your child immediately if they wander. Some devices include geofencing alerts that notify you the moment your child leaves a designated safe zone.
- **Smart home integration**: Door sensors connected to your phone can alert you in real time when any exterior door opens.
- **Wearable alarms**: Some companies make wristbands that trigger an alarm when submerged in water.
### Layer 4: Swim Lessons (With the Right Approach)
Teaching your child to swim does not make them drown-proof. But water competency adds a meaningful layer of protection, especially survival swimming skills.
**What to look for in swim instruction for autistic children:**
- **Individualized instruction**: Group lessons with six kids may not work. Look for programs that offer one-on-one instruction or very small ratios.
- **Sensory-informed teaching**: Instructors should understand that the feel of water on the face, the sound of splashing, and the echo of an indoor pool can all be overwhelming.
- **Survival skills focus**: Programs like ISR (Infant Swimming Resource) teach children to roll onto their backs and float if they fall into water.
- **Visual supports in lessons**: Bring visual schedules and [social stories](/blog/social-stories-autism-guide) to swim lessons. Show your child what will happen step by step before they get in the water.
- **Patience with progress**: Autistic children may take significantly longer to become comfortable in water than neurotypical peers. Consistency matters more than speed.
### Layer 5: Teaching Water Safety Visually
Verbal rules ("Don't go near the pool without an adult") are necessary but insufficient for many autistic children. The abstract nature of danger makes verbal warnings easy to forget in the moment of sensory fascination.
**Visual strategies that work:**
- **Social stories about water safety**: Create a social story that walks through what water looks like, why it is dangerous, and what your child should do when they see water without an adult.
- **Visual boundaries**: Use [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) to create visual rules with pictures. "I see water. I stop. I find a grown-up."
- **Red zone marking**: Some families use red tape or red paint on the ground around pool areas to create a visible "stop" zone.
- **Video modeling**: Record a short video of the correct behavior around water (stopping, finding an adult, waiting) and let your child watch it repeatedly. Video modeling is one of the most evidence-supported teaching strategies for autistic children.
- **Practice, practice, practice**: [Teaching safety awareness](/blog/teaching-safety-awareness-neurodivergent-children) is not a one-time conversation. It is ongoing, repetitive, and multi-modal.
## What to Do in an Emergency
Preparation is prevention. But every parent near water should know what to do if the worst happens.
1. **Call 911 immediately** (or direct someone specific to call, "You in the blue shirt, call 911 now"). Do not assume someone else has already called. 2. **Get the child out of the water.** If you are not a strong swimmer, use a reaching aid (pool noodle, towel, stick) rather than jumping in. 3. **Start CPR immediately if the child is not breathing.** Do not wait for paramedics. Begin rescue breaths and chest compressions. Every parent and caregiver of a child with autism should be CPR certified. 4. **Even if your child seems fine after a near-drowning event, go to the emergency room.** "Dry drowning" and "secondary drowning" can cause respiratory distress hours after the incident.
Take a CPR course this month. Not next month. This month. The American Heart Association and Red Cross both offer courses that take less than four hours.
## Community Awareness
Water safety is not a solo effort. The people around your child need to know about the risk.
- **Notify your local fire department and police**: Many departments keep voluntary registries of children with elopement risk. If your child goes missing, responders will know to check bodies of water first.
- **Talk to your school**: If your child's school is near any body of water, make sure their IEP or 504 plan addresses elopement prevention and water safety.
- **Brief babysitters, family members, and neighbors**: Anyone who supervises your child needs to know about the water attraction and elopement risk.
- **Create an elopement profile**: Organizations like the National Autism Association offer downloadable elopement information forms. Fill one out. Keep copies in your car, at home, and in your child's school file.
## The Balance: Safety Without Fear
It is tempting to read a post like this and decide your child will never go near water again. That is not the goal. Water can be therapeutic, joyful, and regulating for autistic children. Swimming can become a lifelong skill and source of exercise.
The goal is not avoidance. The goal is layers of protection that allow your child to experience water safely, on your terms, with barriers, supervision, skills, and plans in place.
You cannot eliminate every risk. But you can reduce it dramatically. Every barrier you add, every skill you teach, every conversation you have with a neighbor or first responder tilts the odds in their favor.
Start today. Check your barriers. Sign up for swim lessons. Take a CPR course. Brief your circle. Build the layers.
Your child deserves to enjoy water. And you deserve to breathe while they do.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual social stories](/blog/social-stories-autism-guide) for water safety, create step-by-step [safety routines](/blog/teaching-safety-awareness-neurodivergent-children) your child can follow, and track behavioral patterns to stay ahead of [elopement risks](/blog/elopement-wandering-autism-prevention-safety). Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## Building a Sensory Diet at Home: A Practical Guide
Published: 2026-04-22
URL: https://vizyplan.com/blog/sensory-diet-home-activities-autism-adhd
Category: Strategies
Author: Justin Bowman
> Your occupational therapist mentioned a sensory diet and you nodded along. But what does that actually look like at home? Here is a practical, room-by-room guide to building sensory input into your daily routine.
Your child's occupational therapist says the words "sensory diet" and you nod like you understand. Then you get to the car and Google it. No judgment. Most parents hear "diet" and think food. A sensory diet has nothing to do with food. It is a carefully planned schedule of sensory activities woven into your child's day to help their nervous system stay regulated, alert when it needs to be alert, and calm when it needs to be calm.
Think of it like this: some kids need a lot of physical input to feel "organized" in their bodies. Others need less. A sensory diet is the plan that gives your child the right type and amount of sensory input at the right times so they can focus, transition, and function more comfortably throughout the day.
The good news? You do not need a clinic or expensive equipment. You need your house, your yard, and about ten minutes of planning. Let's break it down.
## The Eight Sensory Systems (A Quick Overview)
Most people know five senses: sight, hearing, touch, taste, and smell. But your child's occupational therapist is thinking about eight. The three that often fly under the radar are the ones that matter most for regulation.
**The familiar five:**
- **Visual** (sight): How your child processes light, color, and movement in their environment
- **Auditory** (hearing): How they process sounds, background noise, and volume
- **Tactile** (touch): How they respond to textures, pressure, and temperature on their skin
- **Gustatory** (taste): Preferences and aversions to flavors and food textures
- **Olfactory** (smell): Sensitivity or seeking of certain scents
**The three regulation powerhouses:**
- **Proprioceptive** (body awareness): Input from muscles and joints that tells your child where their body is in space. This is the "heavy work" system, and it is almost always calming.
- **Vestibular** (movement and balance): Input from the inner ear that registers motion, speed, and direction. Swinging, spinning, and rocking all activate this system.
- **Interoception** (internal body signals): The sense that tells your child they are hungry, need the bathroom, feel hot, or notice their heart racing. This one is newer to the conversation but critical for emotional regulation.
If you take one thing from this section, let it be this: proprioceptive and vestibular input are your two biggest tools at home. Research published in the *American Journal of Occupational Therapy* consistently shows that these two systems have the most direct impact on a child's ability to self-regulate. When your child's body gets the movement and resistance it craves, their brain can settle. If you have been reading about [emotional regulation and visual supports](/blog/emotional-regulation-visual-supports), this is the physical side of that same coin.
## Alerting vs. Calming Input: Knowing the Difference
Not all sensory input does the same thing. This is the part that trips most parents up.
**Calming input** slows the nervous system down. It is predictable, rhythmic, and often involves deep pressure or slow movement. Think: rocking in a chair, bear hugs, a weighted blanket, slow swinging, chewing crunchy foods.
**Alerting input** wakes the nervous system up. It is fast, unpredictable, or involves light touch and quick movement. Think: jumping on a trampoline, spinning, cold water on the face, sour candy, upbeat music.
### When to use each:
- **Before a task that requires focus** (homework, a structured activity): calming input first
- **When your child seems sluggish or "zoned out"**: alerting input to bring them up
- **Before a transition** (leaving the house, switching activities): calming proprioceptive input. If you have been working on [transition strategies](/blog/transition-strategies-autism), adding a quick sensory activity before the transition can make your visual countdown even more effective.
- **After a meltdown or high-stress moment**: slow, deep, calming input. No spinning. No bouncing. Slow and heavy.
The key insight from occupational therapy research is that proprioceptive input (heavy work) is almost universally calming regardless of the child. When in doubt, go heavy. Push, pull, carry, squeeze.
## Building a Sensory Diet Room by Room
Here is where it gets practical. You do not need to add a separate "sensory time" to your schedule. You build it into what you are already doing. This is the same philosophy behind a solid [visual schedule](/blog/visual-schedules-for-autism), where structure comes from routine, not from extra tasks.
### The Bedroom (Morning Routine)
Your child wakes up and their nervous system needs to boot up. This is prime time for alerting input followed by organizing proprioceptive work.
- **Crash pad landing**: Keep a pile of couch cushions or a crash pad next to the bed. First thing after waking, your child rolls off the bed onto the pad. The deep pressure on landing is proprioceptive input that helps organize the body immediately.
- **Animal walks to the bathroom**: Instead of shuffling down the hall, your child bear-walks (hands and feet on the floor), crab-walks, or frog-jumps. This loads the joints and muscles with proprioceptive input. It looks silly. It works.
- **Wall push-ups**: Ten push-ups against the bedroom wall before getting dressed. Takes fifteen seconds and loads the shoulders, wrists, and core.
If your [morning routine](/blog/morning-routine-tips-adhd) already uses a visual schedule, simply add a "body wake-up" step with a picture of animal walks. The sensory diet becomes part of the routine, not something extra.
### The Kitchen (Meals and Snacks)
The kitchen is a sensory goldmine and you are probably already using it without realizing.
- **Heavy mixing**: Let your child stir thick batter, knead dough, or mash potatoes. The resistance through the arms and hands is calming proprioceptive input.
- **Carrying groceries**: Hand your child the heavy bag. Canned goods, milk jugs, bags of rice. Carrying weight is one of the simplest and most effective forms of heavy work. A 2019 study in *Frontiers in Integrative Neuroscience* found that sustained heavy carrying reduced hyperactivity markers in children with sensory processing differences.
- **Crunchy and chewy foods as tools**: Crunchy foods (carrots, pretzels, apples) provide alerting oral input. Chewy foods (dried mango, bagels, beef jerky) provide calming input through the jaw. If your child chews on their shirt collar, offer a chewy snack before the activity that causes the chewing.
- **Cold water sips**: A cold drink before a task that requires focus provides quick alerting input through the mouth and throat.
### The Living Room (Downtime and Transitions)
This is where most families spend unstructured time, and it is where dysregulation often shows up. Having sensory strategies ready in this space prevents the escalation pattern you might recognize from reading about [recognizing triggers before meltdowns](/blog/recognizing-triggers-meltdowns-neurodivergent-children).
- **Couch cushion squeezes**: Remove the couch cushions and have your child lie between two of them while you press down gently. This is a "kid sandwich" and provides deep pressure across the whole body.
- **Pillow crashing**: Stack the cushions and let your child jump into them from the couch. The impact is proprioceptive. The jumping is vestibular. Two systems at once.
- **Resistance band on chair legs**: Tie a thick resistance band around the front two legs of a chair. Your child can push their feet against it while sitting, giving proprioceptive input to the legs without leaving the seat. This is excellent for screen time or table activities.
- **Rocking chair**: If you have one, a rocking chair provides rhythmic vestibular input that is almost always calming.
### Outdoors (Yard, Park, or Neighborhood)
Outdoor time is the most natural sensory diet environment. Nature inherently provides multi-sensory input, which is why [outdoor play](/blog/nature-play-outdoor-activities-neurodivergent-children) is so effective for neurodivergent children.
- **Swinging**: The single most versatile vestibular activity. Linear swinging (back and forth) is generally calming. Rotary swinging (spinning) is alerting. Let your child's response guide you.
- **Climbing**: Playground structures, trees (supervised), rock walls. Climbing requires every major muscle group to work against gravity. It is proprioceptive input from head to toe.
- **Digging**: Give your child a shovel and a patch of dirt. Digging is heavy work for the arms and core. It is also tactile input through the hands.
- **Pulling a wagon**: Load a wagon with rocks, sand, or siblings and have your child pull it. The sustained resistance is excellent calming input.
- **Wheelbarrow walking**: Hold your child's legs while they walk on their hands. This loads the shoulders, arms, and wrists with the entire body's weight.
### Before Bed (The Calming Runway)
The hour before bed should be exclusively calming input. No alerting activities after dinner. Your [bedtime routine](/blog/bedtime-routine-autism-adhd) can integrate these seamlessly.
- **Weighted blanket**: Research supports weighted blankets at roughly 10% of your child's body weight for calming proprioceptive input during sleep. A 2020 study in the *Journal of Clinical Sleep Medicine* found improved sleep onset and duration in children who used appropriately weighted blankets.
- **Deep pressure massage**: Firm, slow pressure on the arms, legs, and back using lotion after bath time. This is calming tactile and proprioceptive input combined. Avoid light, ticklish touch, which is alerting.
- **Joint compressions**: Gently press down on your child's shoulders, elbows, wrists, hips, knees, and ankles in a rhythmic pattern. Each compression sends calming proprioceptive input directly to the joint. Many OTs teach this technique specifically for bedtime.
## Making It Stick: The Integration Principle
The biggest mistake parents make with sensory diets is treating them as a separate program. You do not need a "sensory room." You need to layer sensory input into routines your child is already doing.
Here is a simple framework:
1. **Look at your existing daily routine.** Write it out step by step, or pull up the visual schedule you have already built in [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118). 2. **Identify the hard spots.** Where does your child fall apart? Transitions? After school? Homework time? Before bed? 3. **Add one sensory activity before each hard spot.** Just one. Proprioceptive input is your safest bet. 4. **Observe and adjust.** Did the activity help? Was your child more regulated for the next task? If yes, keep it. If not, try a different type of input.
This is not guesswork. This is [tracking patterns](/blog/tracking-emotions-activities-neurodivergent-children) and responding to what you see. Over time, you will develop an intuition for what your child needs and when.
## When to Call Your OT
A home sensory diet is not a replacement for occupational therapy. It is the home implementation of what your OT designs. If you are seeing any of the following, check in with your child's therapist:
- Your child is seeking input so intensely that they are hurting themselves or others
- Sensory activities seem to make regulation worse, not better
- You cannot identify whether your child needs alerting or calming input
- Your child's sensory needs are changing rapidly or dramatically
## You Already Do More Than You Think
Here is the truth most OTs will tell you: parents of neurodivergent children are already providing sensory input instinctively. The bear hugs when your child is escalating. The crunchy snack you hand them in the car. The way you rock them before bed. You have been doing sensory diet activities without knowing they had a name.
Now you know the name, the science, and the structure. Build it into your day, one room at a time.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Add sensory activities directly into your child's [visual schedule](/blog/visual-schedules-for-autism), track which inputs help with [emotional regulation](/blog/emotional-regulation-visual-supports), and build a [morning routine](/blog/morning-routine-tips-adhd) that includes body work from the very first step. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## When Your Neurodivergent Child Says 'Nobody Likes Me'
Published: 2026-04-21
URL: https://vizyplan.com/blog/neurodivergent-child-no-friends-loneliness
Category: Parenting
Author: Justin Bowman
> Your child came home and said the words that break your heart. Loneliness in neurodivergent children is painfully common and deeply misunderstood. Here is how to help.
Your child walked through the door after school, dropped their backpack on the floor, and said it quietly. Maybe they whispered it. Maybe they screamed it. Maybe they just stood there with that look on their face that told you everything before a single word came out.
"Nobody likes me."
And your heart broke. Not a little. All the way.
You wanted to say the right thing. You wanted to fix it. You wanted to call the school, call the other parents, rearrange the entire social world so your child would never feel that pain again. But you also knew, standing there in your kitchen with your hands frozen mid-task, that this is not a problem you can fix by sheer force of will.
Loneliness in neurodivergent children is one of the most painful realities families face. It is also one of the most misunderstood. Because from the outside, it can look like your child does not want friends. It can look like they prefer to be alone. It can look like they are not trying. And the truth is almost always more complicated than that.
## They Want Connection. The Rules Just Do Not Make Sense.
One of the most persistent myths about autistic children is that they do not want social connection. Research tells a very different story. A 2018 study published in *Autism Research* found that autistic children report wanting friendships at the same rate as their neurotypical peers. The difference is not in desire. It is in access.
Social interaction is governed by an enormous set of unwritten rules that neurotypical children absorb almost unconsciously. When to laugh. How close to stand. When a conversation topic has gone on too long. How to read a facial expression that says "I am bored" without anyone actually saying "I am bored." How to join a group that is already playing. When someone is joking versus being serious.
For neurodivergent children, these rules are not intuitive. They are invisible. Imagine being dropped into a card game where everyone else knows the rules but nobody will explain them to you. You keep playing the wrong card, and people react with confusion or frustration, but nobody tells you what the right card would have been. That is what social interaction can feel like for a neurodivergent child.
This is not a deficit of caring. It is a difference in processing. And that distinction matters enormously, both for how you understand your child and for how you help them.
## The Loneliness Research Is Sobering
The research on loneliness in neurodivergent children paints a picture that is hard to read but important to understand. A study published in the *Journal of Autism and Developmental Disorders* found that autistic children are significantly more likely to report feelings of loneliness than their neurotypical peers. A separate 2019 study found that loneliness in autistic adolescents was strongly associated with anxiety and depression.
Children with ADHD face similar challenges. Their impulsivity can lead to social missteps, like interrupting, being too intense, or not reading social cues about when to dial back. Studies show that by middle school, children with ADHD are significantly more likely to experience peer rejection than their neurotypical classmates.
These are not statistics about children who do not care about friendship. These are statistics about children who desperately want to connect and keep running into barriers that their brain did not create and cannot easily navigate.
## The Difference Between Solitude and Exclusion
Before diving into strategies, it is important to make a distinction that gets overlooked too often. Some neurodivergent children genuinely prefer solitude, at least some of the time. After a long school day of navigating sensory overload and social complexity, being alone can feel like oxygen. That is not loneliness. That is recovery.
Loneliness is not about being alone. It is about feeling unwanted. It is the difference between choosing to sit by yourself at lunch because you need a break, and sitting by yourself because nobody asked you to join them. Your child might need both, quiet time for recovery and meaningful connection with peers who understand them. The goal is never to force a child into constant social interaction. The goal is to make sure they have access to connection when they want it.
Pay attention to what your child is telling you, both with their words and with their behavior. A child who happily plays alone and seems content is in a very different place than a child who watches other kids play from across the room with longing on their face. Both deserve your attention, but they need different responses.
## Masking Makes Everything Harder
Many neurodivergent children, especially girls and those who are diagnosed later, learn to mask. Masking is the practice of suppressing natural behaviors, mimicking social norms, and performing neurotypicality in order to fit in. It can look, from the outside, like your child is doing fine socially. They might even have friends. But the cost is enormous.
Masking is exhausting. It requires constant monitoring and adjustment, like running a simultaneous translation in your head while also trying to participate in the conversation. Children who mask heavily often come home and fall apart, not because home is stressful but because they have been holding themselves together all day and finally feel safe enough to stop.
The friendships that masking creates can also feel hollow. When you are performing a version of yourself that is not real, the connections you build are with that performance, not with you. Your child might have people who sit with them at lunch but still feel profoundly alone because nobody at that table knows who they actually are.
If your child is masking, the [emotional toll](/blog/managing-anxiety-neurodivergent-children-visual-strategies) is real and cumulative. This is one of the reasons why creating safe, low-pressure social opportunities is so important. Your child needs spaces where they can be themselves and still be accepted.
## What Not to Say (and What to Say Instead)
When your child tells you that nobody likes them, your instinct will be to reassure. That instinct is loving, but certain reassurances can accidentally make things worse.
**Avoid:** "That is not true! Lots of people like you!" Your child's experience is real to them. Telling them their feelings are wrong teaches them that you are not a safe place to share hard things.
**Avoid:** "Did you try being friendly? Did you ask someone to play?" This implies that the problem is their effort level, which reinforces the shame they are already feeling.
**Avoid:** "You just need to find your people." While eventually true, this feels dismissive in the moment and offers no actionable path forward.
**Instead, try:** "That sounds really painful. I am glad you told me." Start by validating. Just validate. Resist the urge to fix, explain, or redirect. Sit in the feeling with them. [Co-regulation](/blog/co-regulation-before-self-regulation-neurodivergent-children) means being present with your child's pain, not rushing past it.
**Then, when the moment is right:** "Can you tell me more about what happened?" Listen without judgment. Gather information. Your child may need help understanding a social situation, or they may just need to be heard. Let them tell you which one before you decide.
## Practical Strategies for Building Connection
Once you have validated your child's feelings and understand more about what is happening, you can begin to create opportunities for connection that work with your child's neurodivergence rather than against it.
### Prioritize Structured Social Settings
Unstructured social time, like recess or free play at a birthday party, is where neurodivergent children struggle most. There are no clear rules, no defined roles, and the social landscape shifts constantly. Structured activities provide a framework that makes social interaction more predictable and less overwhelming.
Look for activities organized around a shared interest: robotics clubs, art classes, coding groups, nature programs, theater. When the focus is on a shared activity rather than social performance, connection happens more naturally. Your child does not need to figure out how to make small talk when everyone is building a robot together.
### Quality Over Quantity
Your child does not need ten friends. They need one or two people who genuinely get them. Research on friendship in neurodivergent populations consistently shows that the quality of friendships matters far more than the quantity. One deep, accepting friendship can be a powerful buffer against loneliness and its associated mental health impacts.
Help your child identify who they feel most comfortable with, even if it is not the "popular" kid or the one you would have chosen. Facilitate those connections by inviting that child for a [structured playdate](/blog/navigating-playdates-social-gatherings-neurodivergent-child) with a clear plan. "Want to come over and build Legos from 3 to 5?" is much more manageable than an open-ended "come hang out."
### Teach Social Scripts Through Social Stories
[Social stories](/blog/social-stories-autism-guide) are short narratives that describe a social situation, explain what is expected, and give your child language they can use. They are one of the most effective evidence-based tools for building social understanding in neurodivergent children.
You can create social stories for specific situations your child finds challenging. What to say when you want to join a group. How to handle it when someone says no. What to do when a conversation gets awkward. These stories give your child a script to fall back on when their brain goes blank in a social moment.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) supports social stories and visual routines that can help your child prepare for social situations before they happen. Previewing what a playdate or social event will look like, step by step, reduces anxiety and gives your child a framework they can rely on.
### Consider Neurodivergent Peer Groups
Some of the most meaningful friendships neurodivergent children form are with other neurodivergent children. When both kids process the world differently, there is less pressure to perform normalcy. The conversational rhythms might look different from the outside, but they feel natural to the children involved.
Look for social groups specifically designed for neurodivergent children in your area. Many [therapy practices](/blog/finding-right-therapist-neurodivergent-child) offer social skills groups that pair skill-building with genuine peer interaction. Online communities and gaming groups can also provide meaningful connection for older children and teens, especially those who find face-to-face interaction draining.
## When to Seek Additional Support
If your child's loneliness is persistent, if it is affecting their willingness to go to school, if they are showing signs of anxiety or depression, or if they are expressing hopelessness about ever having friends, it may be time to seek professional support. A therapist who specializes in neurodivergent children can help your child build social skills, process social pain, and develop coping strategies.
[Social skills groups](/blog/types-of-therapy-neurodivergent-children) led by trained professionals can also provide a safe space for your child to practice interaction with peers who face similar challenges.
## You Cannot Fix This, But You Can Do So Much
You cannot make other children like your child. You cannot rewrite the social rules that make interaction so complex. You cannot take away the pain of exclusion. And sitting with that helplessness is one of the hardest parts of parenting a neurodivergent child.
But you can be the person who sees your child clearly and loves them without condition. You can create a home where they do not have to mask. You can build [routines](/blog/building-independence-visual-supports) and structures that reduce the overall stress load so they have more energy for the social challenges they face.
And you can tell them, as many times as they need to hear it: "The right people will see how amazing you are. And I will keep helping you find them."
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Use [social stories](/blog/social-stories-autism-guide) to help your child prepare for social situations with confidence, build [calming routines](/blog/emotional-regulation-visual-supports) that reduce the stress of navigating a social world, and create [visual previews](/blog/navigating-playdates-social-gatherings-neurodivergent-child) for playdates and gatherings so your child knows what to expect. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## Executive Function and Your Neurodivergent Child: The Invisible Struggle
Published: 2026-04-20
URL: https://vizyplan.com/blog/executive-function-autism-adhd-invisible-struggle
Category: Strategies
Author: Justin Bowman
> Your child is not lazy, defiant, or unmotivated. Their brain processes tasks differently. Understanding executive function changes everything about how you support them.
Your child knows how to brush their teeth. They have done it hundreds of times. But every single morning, they stand in the bathroom staring at the toothbrush like they have never seen one before. You have reminded them three times. You are running late. And you are wondering, for the hundredth time, why something so simple is so hard.
Or maybe it looks like this: your child's backpack is a disaster. Papers crumpled at the bottom, a permission slip from three weeks ago that never made it home, a lunch box you thought was lost. Their room looks like a storage unit after an earthquake. You have tried chore charts, consequences, and long talks about responsibility. Nothing sticks.
Or this: your child melts down when plans change. Not a small complaint, but a full-body, inconsolable reaction to finding out that Tuesday's soccer practice was moved to Wednesday. The change is minor. The response is enormous.
These are not behavior problems. They are not signs of laziness, defiance, or a lack of caring. What you are seeing is executive function, or more accurately, executive function that works differently than you might expect.
## What Is Executive Function, Exactly?
Executive function is a set of mental skills managed primarily by the prefrontal cortex, the front part of the brain that handles planning, decision-making, and self-control. Think of executive function as your brain's air traffic control system. It coordinates incoming information, manages competing demands, and directs behavior toward goals.
For neurotypical children, these skills develop gradually and somewhat predictably throughout childhood and into the mid-twenties. For neurodivergent children, particularly those with autism, ADHD, or both, executive function often develops on a different timeline and follows a different pattern.
Research from Dr. Russell Barkley, one of the leading researchers on ADHD and executive function, suggests that children with ADHD may be 30 percent behind their peers in executive function development. That means your ten-year-old might have the executive function capacity of a seven-year-old. Your fourteen-year-old might function more like a ten-year-old in this area. Not because they are less intelligent, but because these specific brain systems are developing at their own pace.
Executive function is not one single skill. It is a collection of interrelated abilities that work together. Understanding each one helps explain why your child struggles where they do.
### Working Memory
Working memory is the ability to hold information in your mind while using it. Following multi-step directions, remembering what you went upstairs to get, keeping track of where you are in a math problem. When working memory is limited, your child hears "Go upstairs, put on your shoes, grab your jacket, and meet me at the car" and retains maybe one of those four instructions.
### Task Initiation
This is the ability to start a task without excessive procrastination. For many neurodivergent children, getting started is the hardest part. They know they need to do their homework. They want to do their homework (or at least they want it to be done). But the act of beginning feels like pushing through an invisible wall. This is not laziness. It is a neurological difficulty with activating and directing attention toward a non-preferred task.
### Planning and Organization
Planning involves figuring out the steps needed to reach a goal and putting them in order. Organization involves keeping track of materials, time, and information. A child with planning difficulties might sit down to write a book report and have no idea where to begin, not because they did not read the book, but because "write a book report" is an overwhelming, multi-step project that their brain cannot break into manageable pieces on its own.
### Cognitive Flexibility
This is the ability to shift between tasks, adjust to new information, and handle unexpected changes. When your child falls apart because the restaurant is out of chicken nuggets or because you took a different route to school, cognitive flexibility is what is being challenged. Their brain built a mental map of how things were supposed to go, and deviating from that map feels genuinely distressing.
### Inhibitory Control
Inhibitory control is the ability to stop and think before acting, to resist impulses, and to filter out distractions. It is what allows a child to raise their hand instead of shouting out the answer, to wait their turn in a game, or to keep their hands to themselves when they are frustrated. Weak inhibitory control does not mean your child does not know the rules. It means that in the moment, their brain's braking system is not fast enough.
### Emotional Regulation
While not always listed as a core executive function, [emotional regulation](/blog/emotional-regulation-visual-supports) is deeply connected to executive function systems. The ability to manage the intensity of your emotional responses, to calm down after getting upset, to tolerate frustration, all of this relies on the same prefrontal cortex systems that manage the other executive skills. This is why so many neurodivergent children experience what looks like "overreacting." Their regulatory systems are genuinely working harder than their peers' systems to manage the same emotional experiences.
## Why Punishment Does Not Fix Executive Function
This is one of the most important things you can understand as a parent: you cannot punish a child into having better executive function. And yet, so much of traditional parenting advice is built on the assumption that children who do not complete tasks, stay organized, or control their impulses are choosing not to.
"He knows better." "She just needs more motivation." "If I make the consequence big enough, he will start remembering."
These approaches do not work for executive function difficulties because the problem is not motivation or knowledge. The problem is a skill deficit. Dr. Ross Greene puts it simply: "Kids do well if they can." When a child is not doing well, the question is not "How do I make them want to do better?" It is "What skill are they missing, and how do I support it?"
Repeated punishment for executive function failures does real damage. It teaches your child that they are lazy, irresponsible, or bad. It erodes their self-esteem and their relationship with you. And it does absolutely nothing to build the skills they actually need.
## Practical Strategies That Actually Help
The good news is that while you cannot force executive function to develop faster, you can provide external supports that compensate for what your child's brain is not yet doing internally. Think of these supports as scaffolding. They hold the structure up while it is being built.
### Make the Invisible Visible
Most executive function tasks are invisible. "Get ready for school" requires your child to hold a sequence of steps in their head, initiate each one, and stay on track without getting distracted. That is an enormous cognitive demand.
[Visual checklists and schedules](/blog/visual-schedules-for-autism) take that invisible sequence and make it concrete and external. When your child can see each step laid out in front of them, they do not have to rely on working memory to keep track of where they are. They can look at the list, see what comes next, and move forward.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was designed around exactly this principle. It breaks routines into visual, sequential steps that your child can follow independently. Instead of you repeating "Did you brush your teeth? Did you get dressed? Where are your shoes?" your child has a tool that carries that cognitive load for them. Over time, the external support helps build the internal skill.
### Break Everything Into Smaller Steps
When a task feels overwhelming, your child's brain will avoid it. Not consciously, but automatically. Task initiation becomes nearly impossible when the task in front of you feels too big to manage.
The solution is to break tasks into the smallest possible steps. Not "clean your room" but "pick up the books on the floor." Not "do your homework" but "open your math folder and find tonight's worksheet." Each step should be small enough that it does not trigger avoidance.
[First-then boards](/blog/first-then-boards-guide) are a simple, effective tool for this. "First put the books on the shelf, then you can have a snack." The structure reduces cognitive load and connects each small effort with a clear outcome.
### Reduce Cognitive Load in the Environment
Look at your child's environment through the lens of cognitive demand. A cluttered desk makes it harder to find materials and start work. A room with too many toy options makes it harder to choose and play. A morning routine with too many decisions (What should I wear? What do I want for breakfast?) uses up executive function resources before the day even begins.
Simplify where you can. Lay out clothes the night before. Offer two breakfast choices instead of an open-ended question. Create designated spots for backpacks, shoes, and keys. Every decision you remove from your child's plate frees up cognitive resources for things that matter more.
### Use Body Doubling
Body doubling is the practice of having another person nearby while you work on a task. For many neurodivergent children and adults, the presence of another person provides just enough external accountability and stimulation to help with task initiation and sustained attention.
This can look like sitting at the kitchen table doing your own work while your child does homework. It can look like folding laundry together. It does not require you to direct or supervise. Just being there, doing a parallel activity, can make a remarkable difference.
### Build in External Reminders and Timers
Since working memory is often a challenge, external reminders are not a crutch. They are a legitimate accommodation. Visual timers help your child understand the passage of time, which is often difficult for neurodivergent brains. Alarms and notifications can prompt transitions. Checklists posted in key locations (bathroom mirror, bedroom door, by the front door) serve as memory supports.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) combines several of these supports in one place, giving your child visual routines with built-in structure that reduces the need for you to be the constant reminder system. This is important not just for your child's independence, but for your relationship. When you are always the one nagging, it takes a toll on both of you.
### Support Emotional Regulation Actively
Because [emotional regulation](/blog/emotional-regulation-visual-supports) is so closely tied to executive function, strategies that help your child manage big feelings also support broader executive function development. Teaching your child to [recognize their emotional triggers](/blog/recognizing-triggers-meltdowns-neurodivergent-children) and use calming strategies is executive function work, even though it might not look like it.
[Co-regulation](/blog/co-regulation-before-self-regulation-neurodivergent-children) is the foundation here. Before your child can regulate themselves, they need you to regulate with them. Stay calm during their storms. Name what you see. Offer comfort before correction. Over time, your steady presence helps their brain build the regulatory pathways it needs.
## Reframe the Story You Tell About Your Child
Perhaps the most powerful shift you can make is changing the narrative. When you see your child's struggles through the lens of executive function, everything changes. They are not lazy. They have difficulty with task initiation. They are not careless. They have limited working memory. They are not dramatic. They are still developing emotional regulation skills.
This reframe is not about making excuses. It is about accuracy. And when you understand the real problem, you can find real solutions instead of cycling through consequences that never work.
Your child is working harder than you realize to do things that come easily to their peers. That effort deserves recognition, even when the results are imperfect. Especially when the results are imperfect.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Turn invisible executive function demands into [visual routines](/blog/visual-schedules-for-autism) your child can see and follow, reduce daily friction with [structured morning and bedtime supports](/blog/morning-routine-tips-adhd), and build independence one step at a time with [first-then boards](/blog/first-then-boards-guide) and visual checklists. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## Your Child Is on a Therapy Waitlist. Here Is What to Do Right Now.
Published: 2026-04-19
URL: https://vizyplan.com/blog/therapy-waitlist-what-to-do-at-home
Category: Strategies
Author: Justin Bowman
> Therapy waitlists for autism services are longer than ever. But waiting does not mean doing nothing. Here are research-backed strategies you can start at home today while you wait for that call.
You finally got the referral. You called the clinic, gave your child's name, answered the intake questions, and then heard the number. Six months. Twelve months. In some states, eighteen months or longer. The person on the phone was kind about it, but the message landed like a weight on your chest: your child needs help, and help is not available right now.
You are not alone in this. Therapy waitlists for autism and ADHD services have grown dramatically over the past several years, and 2026 has brought new pressures that are making the problem worse. Provider shortages, clinic closures, and funding cuts to Medicaid-funded services have created bottlenecks that affect families in nearly every state. According to a 2024 report from the American Academy of Pediatrics, the average wait time for a developmental evaluation alone now exceeds five months in most regions. For ongoing therapy services like speech, occupational therapy, or ABA, the wait can stretch even longer.
But here is the thing that matters most right now: waiting for a spot does not mean waiting to act. Research consistently shows that parent-mediated interventions can produce meaningful developmental gains. You are not a substitute for a trained therapist, and nobody is asking you to be one. But you are already your child's most consistent support, and there is a lot you can do with that role while you wait for the phone to ring.
## The Early Intervention Window Is Real, But It Is Not a Cliff
One of the most stressful parts of being on a waitlist is the fear that you are losing precious time. You have probably read about "early intervention windows" and worried that every month on a waitlist is a month wasted.
Let's put that in perspective. Yes, research supports the value of early intervention, particularly before age five. A landmark study published in the *Journal of the American Academy of Child & Adolescent Psychiatry* found that children who received early behavioral interventions showed significant gains in cognitive and adaptive skills compared to those who started later. That research is real and important.
But the brain does not stop being plastic at some arbitrary age. Children continue to learn, grow, and develop new skills throughout childhood and beyond. The goal is not to panic about a closing window. The goal is to start where you are, with what you have, right now.
## Build Predictable Routines at Home
One of the most powerful things you can do while waiting for therapy is to build structure and predictability into your child's day. This is not about rigidity. It is about giving your child a framework that reduces anxiety and frees up mental energy for learning.
[Visual schedules](/blog/visual-schedules-for-autism) are one of the most well-researched tools for supporting neurodivergent children at home. A visual schedule shows your child what is happening now, what comes next, and what the overall shape of their day looks like. For children who struggle with transitions, uncertainty, or [executive function challenges](/blog/building-independence-visual-supports), this kind of external structure can be transformative.
You do not need fancy materials. You can start with pictures printed from the internet and taped to the refrigerator. But if you want something more flexible and interactive, [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was designed specifically for this. It lets you build visual routines your child can follow independently, with customizable steps and images that match your actual life. Many families on therapy waitlists are using [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) to create the kind of structured environment that therapists would recommend anyway.
Start with the routines that cause the most stress. For most families, that means [mornings](/blog/morning-routine-tips-adhd) and [bedtimes](/blog/bedtime-routine-autism-adhd). Break each routine into small, concrete steps. "Get ready for bed" is vague. "Put on pajamas, brush teeth, choose a book, get in bed" is clear. Visual supports turn invisible expectations into something your child can see and follow.
## Use Structured Play as a Learning Tool
Play is not just play. For young children especially, play is the primary vehicle for learning language, social skills, problem-solving, and emotional regulation. You do not need a therapy room to create play-based learning opportunities.
### Floor Time and Following Your Child's Lead
Get on the floor with your child and join whatever they are doing. If they are lining up cars, line up cars next to them. If they are spinning a wheel, spin it with them. The goal is to enter their world first, then gently expand it. This approach, rooted in the DIR/Floortime model developed by Dr. Stanley Greenspan, emphasizes meeting children at their current developmental level and building from there.
### Parallel Play with Narration
Sit near your child and do a similar activity while narrating what you see. "You are stacking the blue block on top of the red one. It is getting tall!" This kind of language modeling builds vocabulary and comprehension without placing demands on your child to respond.
### Turn-Taking Games
Simple turn-taking activities, like rolling a ball back and forth, building a tower where each person adds a block, or taking turns putting puzzle pieces in, build foundational social skills. These are the building blocks that therapists often work on first.
## Address Sensory Needs Proactively
Many neurodivergent children have [sensory processing differences](/blog/sensory-processing-daily-routines) that affect their ability to focus, regulate emotions, and participate in daily activities. While you wait for an occupational therapy evaluation, you can start paying attention to your child's sensory patterns and making adjustments.
Notice what environments cause your child to shut down or escalate. Is it the grocery store with its fluorescent lights and unpredictable noise? Is it clothing with tags or seams? Is it the transition from a calm indoor space to a loud, chaotic playground?
You do not need a formal sensory diet prescribed by an OT to start making accommodations. Some strategies to try:
- **Movement breaks** built into the daily routine, like jumping on a trampoline, swinging, or doing animal walks before a seated activity
- **A calm-down space** at home with soft lighting, comfortable seating, and sensory tools like noise-canceling headphones or weighted blankets
- **Respecting sensory preferences** rather than forcing tolerance, such as cutting tags out of shirts or offering alternative foods with acceptable textures
- **Preparing for sensory-heavy environments** with [visual previews and social stories](/blog/social-stories-autism-guide) before outings
## Learn About and Practice Transition Strategies
Transitions are one of the most common sources of difficulty for neurodivergent children, and they happen dozens of times a day. Moving from one activity to the next, leaving the house, coming inside from playing, stopping screen time. Each transition requires your child to shift their attention, regulate their emotions, and adjust to a new set of expectations.
[Transition strategies](/blog/transition-strategies-autism) you can implement immediately include visual timers, verbal countdowns, transition songs, and "first-then" statements. A [first-then board](/blog/first-then-boards-guide) is especially useful: "First we put on shoes, then we go to the park." It connects a less preferred activity with a motivating one and gives your child a concrete picture of what is happening.
## Advocate for Faster Placement
While you are working on strategies at home, do not stop advocating for a therapy spot. Here are some practical steps that can move the needle:
- **Get on multiple waitlists.** Call every provider in your area and surrounding areas. Ask about cancellation lists.
- **Check for telehealth options.** Many therapy providers now offer virtual sessions, which can sometimes have shorter wait times.
- **Contact your state's Early Intervention program** (for children under 3) or your school district's special education department (for children 3 and older). These publicly funded services operate on different timelines than private clinics.
- **Ask your pediatrician for help.** Some practices have care coordinators who can assist with referrals and waitlist navigation.
- **Reach out to local parent support groups.** Other families who have navigated the system often know which providers have openings or which strategies worked to speed up the process.
- **Document everything.** Keep a record of when you called, who you spoke with, and what you were told. This documentation can be valuable if you need to [advocate for services](/blog/teaching-self-advocacy-skills-neurodivergent-child) through insurance or your school district.
## Take Care of Yourself While You Wait
This is the part of the article where you might be tempted to scroll past, but please don't. [Caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children) is real, and the stress of being on a waitlist, feeling helpless while your child needs support, compounds the exhaustion you are already carrying.
You cannot pour from an empty cup, and that is not just a saying on a coffee mug. Research published in the *Journal of Autism and Developmental Disorders* shows that caregiver stress directly impacts the effectiveness of parent-mediated interventions. When you are running on empty, your patience is thinner, your ability to stay regulated during tough moments is reduced, and your capacity to implement new strategies shrinks.
So while you are building visual schedules and practicing floor time, also build in something for yourself. Even ten minutes. A walk without your phone. A conversation with someone who gets it. A moment where you are not researching, advocating, or problem-solving.
## You Are Already Doing the Work
Here is what I want you to hear: the fact that you are reading this article means you are already showing up for your child. You are researching, learning, and looking for ways to help. That matters. A lot.
The therapy waitlist is a systemic problem, and it is not your fault. But your child does not have to wait in a holding pattern while the system catches up. Every visual schedule you create, every sensory accommodation you make, every moment you spend on the floor following your child's lead is building a foundation that will make therapy more effective when it finally begins.
Therapists consistently report that children whose families have been actively engaged at home make faster progress once services start. You are not wasting time. You are laying groundwork.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build the [visual schedules](/blog/visual-schedules-for-autism) and [structured routines](/blog/morning-routine-tips-adhd) that therapists recommend, create [transition supports](/blog/transition-strategies-autism) your child can follow independently, and start making progress at home while you wait. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## How to Prepare Your Neurodivergent Child for Summer Camp
Published: 2026-04-18 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/preparing-neurodivergent-child-summer-camp
Category: Daily Routines
Author: Justin Bowman
> Registration deadlines are hitting now. Your child needs more preparation than a packing list. Here is how to set them up for a summer camp experience that works, from intake conversations to visual pre-teaching to what to do when the first day feels impossible.
Summer camp registration opens and your stomach drops.
Other parents sign up without thinking. You open the form and start calculating. Will they handle the transitions? What about the noise? Can the staff manage a meltdown? What happens during unstructured free time? Will they eat the food? Will anyone understand?
Here is the truth: many neurodivergent children can have transformative camp experiences. But it takes preparation that goes far beyond a packing list. And that preparation needs to start now, in April, not the week before camp begins.
## Why Camp Matters for Neurodivergent Children
Camp offers something school often cannot: the chance to be part of a community in a less academically rigid setting. Research on structured recreation and autistic children shows positive outcomes in social connection, independence, and self-confidence when the environment is set up to support their needs.
The benefits are real. New friendships in a setting with different social rules than school. Physical activity in natural environments. Skill building in areas that are not graded. The experience of succeeding at something new.
But these benefits only materialize when the gap between what your child needs and what the camp provides has been thoughtfully bridged. That bridging is your job right now.
## Choosing the Right Camp
Not every camp is the right camp. And the right camp for one neurodivergent child may be wrong for another.
**Specialized vs. inclusive.** Some camps are designed specifically for autistic or neurodivergent children, with trained staff, sensory accommodations, and modified programming. Others are general camps that welcome neurodivergent campers with accommodations. Neither is inherently better. The right choice depends on your child's support needs, social comfort level, and what kind of experience they want.
**Ask the right questions.** Before you register, ask: What is the staff-to-camper ratio? What training do counselors receive on neurodiversity? How do they handle meltdowns? Is there a quiet space for sensory breaks? How structured is the day? What happens during transitions? Can you provide a written profile of your child?
**Talk to other parents.** The best information about how a camp actually handles neurodivergent campers comes from families who have been there. Ask in your parent groups. Ask your child's therapists for recommendations. Ask the camp for references from neurodivergent families specifically.
**Visit first.** If possible, visit the camp before your child's first day. Take photos and videos of the spaces, the schedule board, the dining area, the bathrooms. These become your visual pre-teaching materials.
## Building a Camp Profile
Create a one-page document about your child that camp staff can reference. Include:
**Communication style.** How your child communicates, what works and what does not, and how to tell when they are struggling even if they are not saying it.
**Sensory needs.** What overwhelms them, what calms them, specific sensory triggers to watch for.
**Food.** What they will eat, what they will not, whether they need reminders to eat or drink, any allergies or restrictions.
**Transition support.** What helps during changes in activity, how much warning they need, what signs indicate they are about to become dysregulated.
**Strengths.** What they love, what they are good at, what makes them light up. Staff who know your child's strengths can connect with them more effectively.
**Emergency strategies.** What to do if they melt down. What helps. What makes it worse. This is not a behavior plan. It is a survival guide for the counselor who has never met your child.
## Visual Pre-Teaching: The Most Important Preparation
Your child needs to mentally rehearse camp before they physically arrive. [Social stories](/blog/social-stories-autism-guide) and visual preparation are the most effective tools for this.
**Create a visual schedule of a camp day.** Using the camp's published schedule, build a visual representation of what the day will look like. Wake up, breakfast, first activity, snack, second activity, lunch, rest time, third activity, pickup. The more your child can see the structure, the less anxiety the unknown creates.
**Show them the spaces.** Use photos from your visit or the camp's website to create a visual tour. "This is where you will eat. This is the field where you will play games. This is the bathroom." Familiarity reduces threat signals in the brain.
**Practice the hardest parts.** If [transitions](/blog/transition-strategies-autism) are difficult, practice stopping a fun activity and starting something new. If separation is hard, practice drop-off scenarios. If meals with unfamiliar food create anxiety, practice eating with a lunchbox in a new setting.
**Read or create stories about camp.** A simple narrative about a child going to camp, having a hard moment, getting help, and then having fun normalizes both the challenge and the recovery. Your child needs to know that hard moments at camp are expected and survivable.
**Use a visual countdown.** A countdown calendar showing how many days until camp starts builds anticipation and reduces the shock of sudden change. Each morning, your child marks off a day and can see camp approaching gradually rather than appearing overnight.
## The First Day Strategy
The first day is the hardest. Plan for it.
**Do the morning [routine](/blog/morning-routine-tips-adhd) with extra support.** This is not the morning to rush. Extra buffer time, familiar breakfast, the visual schedule for the camp day posted where they can see it.
**Arrive early, not on time.** Let your child see the space before it fills with people. Walk the route from drop-off to their group area. Find the bathroom. Find the quiet space. Reducing unknowns before other campers arrive lowers the anxiety baseline.
**Keep the goodbye short and predictable.** A long, emotional goodbye increases anxiety. Create a brief goodbye ritual: a specific phrase, a hand squeeze, a fist bump. Practice it at home so it feels familiar.
**Tell them exactly when you are coming back.** "I will be here at 3:00 PM, right after the last activity." If they have a visual schedule, point to the pickup spot on it. [Predictability](/blog/visual-schedules-for-autism) is regulation.
**Expect a rough first day.** And possibly a rough first week. This does not mean camp is wrong for your child. It means their nervous system is adjusting to a massive environmental change. Unless your child is in genuine distress that the staff cannot support, give it time.
## During Camp: Staying Connected Without Hovering
**Check in with staff, not just your child.** Your child may not be able to articulate how camp is going. Staff observations fill the gaps. Ask specific questions: "How are transitions going? Is he eating? Does she use the quiet space?"
**Track how your child is doing at home.** [Emotion tracking](/blog/tracking-emotions-activities-neurodivergent-children) during camp weeks reveals whether the experience is sustainable. Some post-camp decompression is normal. Escalating distress over days is a signal to intervene.
**Resist the urge to pull them out at the first sign of struggle.** Struggle is different from suffering. A child who has a hard morning but recovers and enjoys the afternoon is learning resilience. A child who is in sustained distress with no relief is suffering. Know the difference.
## When Camp Is Not Working
Sometimes despite all preparation, a camp experience is not right. Signs include:
Increasing distress over multiple days with no recovery. Regression in skills or behaviors at home. Physical symptoms like refusing to eat, sleep disturbances, or frequent illness. Your child explicitly asking not to go in a way that goes beyond typical resistance to change.
If this happens, it is not a failure. It is information. The camp was not the right fit, or the timing was not right. There will be other summers.
## Start Now
The families who have the best camp outcomes are the ones who start preparation weeks or months in advance. Not packing. Not logistics. Emotional and sensory preparation that gives their child's nervous system time to adjust to the idea before the reality arrives.
April is not too early. April is exactly right.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) for your child's camp day before it starts, [track emotions and patterns](/blog/tracking-emotions-activities-neurodivergent-children) during camp weeks to see how they are really doing, and create [social stories](/blog/social-stories-autism-guide) that prepare them for every new experience camp will bring. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## What Masking Looks Like in Young Children and Why It Is Exhausting
Published: 2026-04-17
URL: https://vizyplan.com/blog/autism-masking-young-children-exhausting
Category: Parenting
Author: Justin Bowman
> The teacher says your child is fine at school. Then they walk through the front door and everything falls apart. That gap between school behavior and home behavior has a name. It is called masking, and it is costing your child more than anyone realizes.
The teacher conference goes well. "They are doing great," she says. "No behavior concerns. They follow directions, play with other kids, participate in circle time."
You sit there wondering if she is talking about the same child. Because the child who walks through your front door at 3:15 PM is a different person. The shoes come off. The backpack hits the floor. And within minutes, the screaming starts. Or the shutdown. Or the hours of rigid, impossible-to-redirect behavior that lasts until bedtime.
You have tried explaining this to the school. They look at you like you are imagining things. You have tried explaining it to family. They wonder what you are doing wrong at home.
Nobody is imagining anything. And you are not doing anything wrong. Your child is masking, and the research on what this costs them is finally catching up to what you already know.
## What Masking Is
Masking, sometimes called camouflaging, is the conscious or unconscious suppression of autistic traits in order to appear neurotypical. It includes suppressing stimming behaviors, forcing eye contact, imitating the social behaviors of peers, using memorized social scripts, hiding sensory discomfort, and performing emotional expressions that do not match internal experience.
Researchers define camouflaging as strategies individuals employ to mask, assimilate, or compensate for their autistic characteristics in social settings, in order to blend in or avoid stigmatization. This includes suppression of behaviors considered atypical, imitation of neurotypical behaviors, and use of social scripts to navigate social interactions.
For adults, masking has been extensively studied. The 2025 research picture is clear: camouflaging is associated with increased biological long-term stress, anxiety, depression, and burnout. But until recently, most masking research focused on teenagers and adults. The experience of young children, particularly those under ten, was largely unstudied.
That is changing. A 2026 study published in Advances in Neurodevelopmental Disorders found that camouflaging in children and adolescents predicted both internalizing symptoms like anxiety, depression, and somatic complaints, and externalizing symptoms like rule breaking and aggression, even when controlling for age, sex, and IQ.
Your child is not misbehaving at home. They are decompressing from a full day of performance.
## What Masking Looks Like in Young Children
Masking in a five-year-old looks different from masking in a teenager, which is part of why it has been missed by research for so long.
**The "perfect" school child.** They follow every rule. They are quiet, compliant, eager to please. Teachers describe them as a model student. This is not because school is easy for them. It is because they are spending enormous energy ensuring nobody notices they are struggling.
**After-school collapse.** The moment they reach the safety of home, the mask drops. Everything held in all day comes out at once. Meltdowns, aggression, withdrawal, rigidity, tears. Parents describe feeling like they live with two different children.
**Delayed emotional reactions.** Something upsetting happens at school and they appear fine. Hours later at home, they fall apart over something unrelated. The emotion was held, not felt, during the masking period and surfaces later.
**Physical symptoms.** Stomachaches, headaches, fatigue, and sleep problems. The physiological cost of sustained masking shows up in the body. Research connects camouflaging to increased somatic complaints in children.
**Social exhaustion.** A child who seems to socialize well at school may refuse all social interaction at home or on weekends. They are not antisocial. They are depleted.
**Imitation rather than initiation.** Instead of playing their own way, they watch other children closely and copy. They learn the "right" way to play through observation. This looks like social development from the outside but is actually effortful performance.
## Why Children Mask
Young children do not make a conscious decision to mask. It develops from repeated experiences of social feedback.
They learn quickly that stimming draws attention. That lining up toys the "wrong" way during free play makes other kids stare. That being honest about sensory overload leads to being singled out. That showing their natural way of being gets a reaction they want to avoid.
So they suppress. They imitate. They perform. And they get rewarded for it. "What a great day!" "You played so nicely!" "No problems at all!" The masking works, in the sense that it avoids negative social consequences. But the cost compounds silently.
Research published in 2025 noted that more research is needed on masking in younger children, specifically in the early school years, as this developmental period is when masking patterns solidify. The habits formed at five and six become the survival strategies that lead to burnout at fifteen and twenty.
## The Gender Factor
Autistic girls and women consistently score higher on camouflaging measures than boys and men. This contributes to later diagnosis, as masking hides the traits that evaluators look for.
But it also means that girls may be carrying a heavier masking burden from an earlier age. If your daughter "seems fine" at school but unravels at home, and if she has ever been described as "too social to be autistic," masking may be exactly what is happening.
## How to Support a Masking Child
**Believe the home behavior.** The child you see at home is the real child. The school version is the performance. This does not mean school is doing something wrong. It means your child is working harder than anyone realizes to hold it together.
**Create low-demand time.** After school, reduce expectations. Do not immediately ask about their day, hand them homework, or schedule activities. Give them decompression time with no performance demands. Let them stim, zone out, play however they want, be messy, be loud, be themselves.
**Reduce the need to mask at school.** Work with the school to create accommodations that lower the masking burden. Sensory breaks. A quiet space to decompress. Permission to stim. Flexible seating. The fewer things a child has to suppress, the less they will collapse at home.
**Make home a safe space for all expressions.** If your child knows that every version of themselves is accepted at home, home becomes the place where the mask can safely drop. This is not indulging bad behavior. This is providing the emotional safety that makes regulation possible.
**Build predictability into the day.** [Visual schedules](/blog/visual-schedules-for-autism) reduce the cognitive load of figuring out what comes next. When a child does not have to use working memory to predict their day, that mental energy is freed up for other things. Less cognitive load means less masking demand.
**Validate the effort.** "School takes a lot of energy for you. I can see you are tired." Simple statements that acknowledge the invisible work of masking tell your child that you see them, even the parts they hide from everyone else.
## The Long View
Masking is a survival strategy, and sometimes survival strategies are necessary. The goal is not to eliminate masking entirely, because your child will navigate neurotypical spaces their whole life. The goal is to reduce how much of it is required, increase recovery time, and ensure they have safe spaces where no mask is needed.
[Tracking emotions across the day](/blog/tracking-emotions-activities-neurodivergent-children) reveals the masking pattern. When you can see that school days consistently produce evening meltdowns, you have data that supports accommodation requests. When you can show that weekends with low social demand produce zero meltdowns, you have evidence that the issue is not your child's capacity, it is the cost of sustained performance.
Your child is not two different people. They are one person carrying an exhausting weight that nobody at school can see. You see it because home is where they finally put it down.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that reduce the cognitive load your child carries through their day, [track emotions and patterns](/blog/tracking-emotions-activities-neurodivergent-children) to reveal the hidden cost of masking across school and home, and create [social stories](/blog/social-stories-autism-guide) that prepare them for social situations without requiring performance. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## Interoception: Why Your Child Can't Tell You They're Hungry, Tired, or Need the Bathroom
Published: 2026-04-16
URL: https://vizyplan.com/blog/interoception-autism-children-hunger-tired-bathroom
Category: Parenting
Author: Justin Bowman
> Your child melts down from hunger but says they are fine. They have an accident even though you just asked if they needed the bathroom. This is not defiance. It is interoception, the sense most people have never heard of.
Your child has not eaten in four hours. You can see the signs. They are getting irritable, unfocused, starting to fall apart. You ask if they are hungry.
"No."
Twenty minutes later, a full meltdown. You offer food. They eat ravenously. They were starving. They genuinely did not know.
Or this: You ask your child if they need the bathroom before you leave the house. "No." Seven minutes into the car ride, an emergency.
This is not defiance. It is not lying. It is not laziness. It is a sensory processing difference called interoception, and it is one of the most overlooked factors in daily life with a neurodivergent child.
## The Eighth Sense
Most people learn about five senses in school. Some know about the vestibular sense (balance) and proprioception (body position in space). But there is an eighth sensory system that rarely gets discussed: interoception.
Interoception is the ability to sense what is happening inside your body. Hunger, thirst, fullness, the need to use the bathroom, fatigue, temperature, pain, heart rate, nausea, the feeling of an emotion building. Every internal signal your body sends your brain travels through the interoceptive system.
For most people, this system works in the background. You feel hungry, you eat. You feel cold, you put on a jacket. You feel the urge to use the bathroom, you go. These signals are so automatic that you do not think about thinking about them.
For many neurodivergent children, interoception works differently. Signals may be muted, delayed, absent, or overwhelming. A child might not feel hunger building gradually. Instead, they feel nothing, nothing, nothing, then suddenly feel desperately, urgently hungry with no warning. The signal skipped "a little hungry" and went straight to "crisis."
## How Interoceptive Differences Show Up
**Mealtime battles.** Your child says they are not hungry, refuses food, then melts down an hour later. They are not being difficult. They genuinely did not perceive hunger until it became unbearable. Or the opposite: they cannot feel fullness and eat past the point of comfort.
**Toileting challenges.** [Potty training](/blog/potty-training-autism-adhd-visual-supports) takes longer because the internal signal that says "your bladder is getting full" does not register until the moment is urgent. Accidents persist even in older children, not from a behavioral issue, but from a sensory one.
**Temperature dysregulation.** Your child refuses a coat in freezing weather or wears a winter jacket in summer. They are not being oppositional. They may not be perceiving temperature the way you do.
**Emotional escalation.** Emotions are interoceptive experiences. Anxiety feels like a tight chest. Anger feels like heat and tension. Sadness feels heavy. If your child cannot perceive these building physical sensations, emotions seem to arrive at full intensity without warning. There is no "I am getting frustrated." There is only the explosion.
**Sleep difficulties.** Recognizing tiredness requires interoceptive awareness. A child who does not feel fatigue building will not ask for rest and may fight [bedtime](/blog/bedtime-routine-autism-adhd) because they genuinely do not feel tired, even when their body clearly is.
**Pain insensitivity or hypersensitivity.** Some children do not report injuries that should hurt. Others experience minor sensations as intensely painful. Both reflect interoceptive differences.
## The Research Behind It
Occupational therapist Kelly Mahler has led research on interoception and autism for over twenty years. Her work demonstrated that interoceptive differences are directly linked to emotion regulation challenges in autistic children.
In a study using her Interoception Curriculum, a 25-week school-based intervention, researchers found statistically significant improvements in both interoceptive awareness and emotion regulation. Children who became better at noticing their body signals also became better at managing their emotions. The connection is not coincidental. You cannot regulate what you cannot feel.
This research reframes so many daily struggles. The child who "has no emotional awareness" may actually have interoceptive differences that prevent them from feeling emotions as they build. The child who "never listens to their body" may not be able to hear what their body is saying.
## What You Can Do at Home
**Build body awareness with check-ins.** At regular points throughout the day, pause and help your child notice their body. "Let's check in. How does your tummy feel? Empty, full, or somewhere in between?" Start with moments when the answer is obvious, like right before a meal, so they can connect the label with the sensation.
**Use visual scales.** A visual hunger scale, a visual energy meter, a visual emotions thermometer. These give your child a way to externalize internal states. Instead of needing to generate the answer from inside, they can point to where they are on a scale. Over time, this builds the internal vocabulary.
**Create routine-based body breaks.** Do not wait for your child to report a need. Build body-awareness moments into the daily [visual schedule](/blog/visual-schedules-for-autism). After recess: body check. Before lunch: hunger check. Before bed: energy check. The routine scaffolds what interoception is not yet providing independently.
**Exercise supports interoceptive awareness.** Movement that increases heart rate, heavy breathing, and muscle engagement creates strong interoceptive signals that are easier for the brain to detect. Jumping, climbing, pushing heavy objects, or swinging all generate body feedback that strengthens the interoceptive pathways.
**Name sensations during natural moments.** When your child is out of breath from running: "Your heart is beating fast. Your chest is moving up and down. That is your body telling you it is working hard." You are teaching them the language of interoception in context.
**Track patterns over time.** [Emotion and activity tracking](/blog/tracking-emotions-activities-neurodivergent-children) across days and weeks reveals interoceptive patterns that single moments do not. You might discover your child consistently melts down two hours after eating, revealing a hunger pattern you can proactively address.
## Reframing Daily Struggles
Almost every parent of a neurodivergent child has experienced the frustration of asking "Are you hungry? Do you need the bathroom? Are you tired?" and getting "No" right before the very thing they asked about becomes a crisis.
The reframe is this: your child was not lying. They were answering honestly based on what their body was telling them. And their body was not sending the signal yet, or was sending it too quietly for their brain to detect.
This does not mean you stop asking. It means you stop relying on their answer as the only data point. You pair their self-report with your observations, with routine-based check-ins, and with the patterns you track over time.
You become the external interoceptive system until theirs develops. You notice what they cannot yet notice. You intervene before the crisis, not because you are controlling, but because you are compensating for a sensory system that is still catching up.
## It Gets Better
Interoception is not fixed. It develops. It can be strengthened. The research on interoception-based interventions shows measurable improvement over time. Your child's internal awareness at six is not their awareness at ten.
Every body check-in you do builds a neural pathway. Every time you help your child connect "my tummy feels empty" with "I need food," you are wiring a connection that will eventually fire without you.
It is slow. It is invisible work. Nobody sees you doing it. But it is some of the most important work you will do as a parent.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) with built-in body check-in reminders, [track emotions and patterns](/blog/tracking-emotions-activities-neurodivergent-children) to reveal interoceptive trends you would miss day-to-day, and create [social stories](/blog/social-stories-autism-guide) that teach your child what body signals feel like. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## Co-Regulation Before Self-Regulation: What the Science Actually Says
Published: 2026-04-15
URL: https://vizyplan.com/blog/co-regulation-before-self-regulation-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> You have been told your child should be able to calm themselves down by now. The science says something different. Self-regulation is built through co-regulation first, and for neurodivergent children, that timeline looks nothing like the charts suggest.
"He should be able to calm himself down by now."
You have heard some version of this from a teacher, a family member, maybe even a therapist. Your child is six, or eight, or ten, and they still need you to help them through big emotions. They still cannot "just take a deep breath" and move on.
And you feel like you are failing. Like you should have taught them this by now. Like every other child their age has figured this out.
Here is what nobody told you: self-regulation is not a skill you teach. It is a skill that develops through thousands of moments of being regulated by someone else first. And for neurodivergent children, this developmental process takes longer, not because something is wrong, but because their nervous systems are wired differently.
## What Co-Regulation Actually Means
Co-regulation is the process of using your own calm nervous system to help regulate your child's dysregulated one. It is not a technique you perform on your child. It is a relational state you create between you.
When your child is melting down and you get close, lower your voice, slow your breathing, and stay present without trying to fix or lecture, you are co-regulating. Your nervous system is communicating safety to theirs. Not through words, but through tone, proximity, rhythm, and presence.
Research in developmental psychology shows that self-regulation develops through a gradual transition from interpersonal regulation, meaning co-regulation, to intrapersonal regulation, meaning self-regulation. The child cannot build the internal version without first experiencing the external one repeatedly.
Think of it this way. You cannot teach a child to swim by throwing them in deep water and shouting instructions from the side. You get in the water with them. You hold them. You let them feel buoyancy while your arms are underneath. Gradually, as their body learns what floating feels like, you remove support. Co-regulation works the same way.
## Why Neurodivergent Children Need More Co-Regulation
The autonomic nervous system, which governs our stress responses, develops differently in neurodivergent children. Polyvagal theory, developed by Dr. Stephen Porges, explains that our nervous systems operate through three primary circuits: the ventral vagal system that supports social engagement and calm, the sympathetic system that drives fight-or-flight responses, and the dorsal vagal system that triggers shutdown and withdrawal.
Neurodivergent children often have nervous systems that shift into fight-or-flight or shutdown more quickly and with less provocation. Their neuroception, the subconscious process of scanning the environment for safety or danger, may interpret neutral situations as threatening. A classroom that feels fine to most children may register as overwhelming to a child whose sensory processing amplifies every sound, movement, and social demand.
This means neurodivergent children spend more time in dysregulated states. And because self-regulation builds on the foundation of co-regulation, they need more co-regulation experiences, not fewer, and they need them for longer.
The child who "should be calming down by now" is not behind. They are building a foundation that simply takes more time.
## What Co-Regulation Looks Like in Practice
**Match their energy first, then bring it down.** If your child is yelling, start at a slightly elevated volume yourself, then gradually decrease. Jumping straight to whisper-calm when they are at a ten can feel dismissive. Meet them closer to where they are, then guide them down.
**Use your body.** Sit next to them on the floor. Open your posture. Breathe audibly so they can hear your rhythm. Research on polyvagal-informed interventions shows that rhythmic pacing, prosodic voice, and relational presence help stabilize autonomic states and recalibrate the child's neuroception from "danger" back to "safe."
**Reduce language during peak distress.** When a child is dysregulated, their higher brain functions, including language processing, go offline. Long explanations, questions, and reasoning attempts will not land. Instead, use short, rhythmic phrases: "I am here. You are safe. I have got you." Or say nothing at all. Sometimes your presence is enough.
**Regulate yourself first.** You cannot co-regulate if your own nervous system is in fight-or-flight. This is the hardest part. Taking three slow breaths before responding to your child's meltdown is not selfish. It is the most effective thing you can do.
**Stay after the storm passes.** Co-regulation does not end when the crying stops. The minutes after a meltdown are when repair happens. Stay close. Offer gentle connection. This is where trust builds.
## Why "Calm Down" Strategies Alone Do Not Work
Deep breathing. Counting to ten. Going to a calm corner. These are all self-regulation strategies. And they are all useless for a child who has not yet built the co-regulatory foundation to use them.
Teaching a dysregulated child to take deep breaths is like handing a drowning person a textbook on swimming. The information is correct. The timing makes it impossible to use.
Self-regulation strategies become tools a child can access once their nervous system has been trained, through repeated co-regulation, to recognize what "calm" feels like in their body. That internal reference point, the felt sense of returning to baseline, is what makes strategies like breathing or [mindfulness](/blog/happy-place-mindfulness-neurodivergent-children) accessible.
Until then, you are the strategy.
## Building Toward Independence
Co-regulation is not about creating dependence. It is about building the neurological infrastructure that eventually supports independence.
Over time, you will notice shifts. Your child might start humming to themselves during stress, a rhythm they learned from your co-regulation. They might reach for a [calm-down tool](/blog/emotional-regulation-visual-supports) before you suggest it. They might recover from a meltdown in ten minutes instead of forty.
These moments are not random. They are the result of every time you sat on the floor with them and breathed. Every time you stayed instead of sending them to their room. Every time you chose connection over correction.
Visual supports accelerate this process. When a child can see [what comes next in their day](/blog/visual-schedules-for-autism), predictability reduces the number of times their nervous system spikes into fight-or-flight. Fewer spikes means more time in the regulated state where learning happens. [Emotion tracking](/blog/tracking-emotions-activities-neurodivergent-children) helps you see patterns over weeks, revealing which situations consistently dysregulate your child so you can prepare, plan, and support.
## You Are Not Failing
If your child still needs you to help them regulate, you are not behind. You are doing exactly what their developing nervous system requires.
The timeline is not the same as other children. The milestones will not match the charts. And the people who say "they should be able to do this by now" do not understand the neurobiology of how regulation actually develops.
Every time you show up calm in the middle of chaos, you are building something inside your child that will eventually function without you. Not today. Maybe not this year. But it is being built.
You are not a crutch. You are a foundation.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that reduce the daily triggers that overwhelm your child's nervous system, [track emotions and patterns](/blog/tracking-emotions-activities-neurodivergent-children) to understand their regulation journey over time, and create [social stories](/blog/social-stories-autism-guide) that prepare them for challenging moments before they happen. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## Echolalia Is Communication: What Your Child's Scripting Really Means
Published: 2026-04-14
URL: https://vizyplan.com/blog/echolalia-communication-autism-scripting
Category: Visual Supports
Author: Justin Bowman
> Your child repeats lines from movies, echoes your questions back, or scripts entire conversations from memory. That is not broken language. That is language working differently.
Your child says "Do you want a snack?" when they are hungry. They repeat the same line from Bluey forty times in a row. They echo your question back instead of answering it.
You have probably been told this is "non-functional language." That it needs to be redirected. That it is a sign your child is not progressing.
That framing is wrong.
Echolalia, the repetition of words, phrases, or entire scripts, is one of the most misunderstood aspects of autistic language development. And for many children, it is not a barrier to communication. It is communication.
## What Echolalia Actually Is
Echolalia comes in two forms. Immediate echolalia is when your child repeats something right after hearing it. You say "Do you want juice?" and they say "Do you want juice?" back. Delayed echolalia is when they repeat something heard hours, days, or even months ago. The Bluey line they keep quoting. The phrase from a book they heard last week.
For decades, echolalia was classified as a symptom to eliminate. Therapy goals focused on reducing it. Parents were told to ignore it or redirect to "real" communication.
But research tells a different story. Barry Prizant, a leading researcher in communication and autism, identified fourteen distinct functions that delayed echolalia serves. These include requesting, protesting, affirming, labeling, calling for attention, self-directing behavior, and rehearsing. Fourteen different communicative purposes, all dismissed as meaningless repetition.
When your child quotes a movie character who is scared during a moment when they feel scared, that is not random. That is a child using the language they have to express something they do not yet have original words for.
## Gestalt Language Processing: A Different Path to Language
Most children develop language analytically. They start with single words, combine them into short phrases, and build toward sentences. That is the model most speech therapy is built around.
But many autistic children develop language as gestalt processors. Instead of building up from single words, they start with whole chunks of language, long phrases or entire scripts memorized as single units, and gradually break them down into smaller, more flexible pieces.
This framework, described by speech-language pathologist Marge Blanc through the Natural Language Acquisition protocol, identifies stages of gestalt language development. In the earliest stages, a child's language is almost entirely echolalic. Those echoed phrases are their vocabulary. Over time, with support, they begin to mix and recombine pieces of those scripts into novel utterances.
A child who says "Let it go, let it go" is not just quoting Frozen. They might be telling you they want to be free of something. They want to leave. They want to stop an activity. The meaning lives in the context, not the literal words.
## Why This Matters for Your Family
Understanding echolalia as communication changes everything about how you respond to your child.
**It changes your reaction.** Instead of redirecting scripting, you start listening to it. You pay attention to when certain scripts appear and what might be driving them. You respond to the intent behind the words, not the words themselves.
**It changes your expectations.** Instead of measuring your child's progress against analytical language milestones, you look for signs of gestalt language development. Are they beginning to modify scripts? Combining pieces of different phrases? Those are significant breakthroughs.
**It changes therapy goals.** Instead of targeting echolalia reduction, therapy can focus on supporting the natural progression from rigid scripts to flexible language. Meeting the child where they are, not where a milestone chart says they should be.
**It reduces shame.** Many parents feel embarrassed when their child scripts in public or echoes questions instead of answering them. Understanding that this is a valid and purposeful communication strategy removes that shame and replaces it with curiosity.
## What to Do When Your Child Scripts
**Listen for the function.** When your child echoes something, ask yourself: what might they be trying to communicate? Are they requesting? Protesting? Processing an emotion? Labeling something in their environment? The same script can mean different things in different contexts.
**Respond to the intent.** If your child says "Time for bed!" at 2 PM, they might be telling you they are tired, not that they think it is bedtime. Respond to what you think they mean: "You sound tired. Do you want to rest?"
**Acknowledge the communication.** Even when you are not sure what a script means, validate the attempt. "I hear you saying that. Tell me more." This reinforces that their communication matters, regardless of its form.
**Model language at their level.** If your child is in early gestalt stages, model short, meaningful phrases that they can grab and use. Instead of "Would you like me to open the door for you so you can go outside?" try "Let's go outside!" Short, functional chunks they can echo and eventually adapt.
**Track which scripts appear in which contexts.** Over time, patterns emerge. You might notice your child uses a specific movie line whenever they are overwhelmed. That is valuable information that helps everyone supporting your child understand their communication system.
## Building on Echolalia with Visual Supports
Visual supports complement gestalt language development beautifully. When a child can see what is happening next in their routine, the need to rely solely on scripts to navigate their day decreases. The [visual schedule](/blog/visual-schedules-for-autism) becomes a shared reference point.
[Social stories](/blog/social-stories-autism-guide) provide new scripts in a structured way. When you create a visual narrative about going to the dentist, you are giving your child appropriate language to echo for that situation. You are expanding their script library with useful, context-specific phrases.
Emotion tracking tools help connect scripting to feelings. When you can see that your child scripts more heavily during [transitions](/blog/transition-strategies-autism) or when they are anxious, you can address the underlying emotion rather than focusing on the surface behavior.
## When to Seek Support
If your child primarily communicates through echolalia, a speech-language pathologist familiar with gestalt language processing can help. Not all SLPs are trained in this framework, so ask specifically about their experience with GLP and the Natural Language Acquisition protocol.
An SLP who understands gestalt processing will not set goals to eliminate echolalia. Instead, they will support your child's natural progression through the stages of gestalt language development, celebrating each step toward more flexible communication.
## Your Child Is Already Communicating
The most important shift is this: your child is not failing to communicate. They are communicating in a way that the people around them may not yet understand.
Every script has meaning. Every echo carries intent. Every repeated phrase is your child using the tools they have to navigate a world that was not designed for the way their brain processes language.
Your job is not to fix their communication. Your job is to understand it.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that give your child new scripts for their day, [track emotions and patterns](/blog/tracking-emotions-activities-neurodivergent-children) to understand what their scripting is telling you, and create [social stories](/blog/social-stories-autism-guide) that expand their language library with context they can use. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## Nobody Tells You About the Day After Diagnosis
Published: 2026-04-13
URL: https://vizyplan.com/blog/nobody-tells-you-about-the-day-after-diagnosis
Category: Parenting
Author: Justin Bowman
> The diagnosis is not the hard part. The hard part is Monday morning, when nobody is coming to help and you have to figure out what life looks like now.
The diagnosis itself takes about thirty seconds. Someone across a desk says the words. Autism spectrum disorder. Or ADHD. Or both. Maybe you knew it was coming. Maybe you did not. Either way, you nod. You ask a question or two. You sign some papers. You walk to your car.
And then you sit there.
Because nobody prepares you for the silence that follows. The diagnosis has a name, a label, a clinical code. But the life you wake up to the next morning does not come with instructions. There is no binder. No onboarding packet. No "here is exactly what to do at 6 AM tomorrow when your child wakes up screaming and you do not know if it is sensory overload, hunger, a nightmare, or all three."
The diagnosis is not the hard part. The day after is.
## What Nobody Tells You
Nobody tells you that the grief and the relief will show up at the same time, and that feeling both does not make you a bad parent. Researchers call it "chronic sorrow," a term coined by Simon Olshansky in the 1960s to describe the enduring grief parents experience when a child's life unfolds differently than expected. It is not a phase. It is not something you move through and leave behind. A 2024 systematic review published in the International Journal of Developmental Disabilities confirmed that this grief is cyclical, characterized by a fluctuation of painful emotions and periods of acceptance that come and go throughout your child's entire life.
You will feel fine for three weeks. And then you will watch your child's same-age cousin have a full conversation at Thanksgiving, and the sadness will return like it never left.
Nobody tells you that.
Nobody tells you that 40 percent of parents of autistic children isolate themselves from friends and family because of their child's behaviors, according to a survey by the Interactive Autism Network at Kennedy Krieger Institute. And that another 32 percent said other people excluded them. That is not a statistic. That is your Friday night plans disappearing. That is the birthday party invitation that stops coming. That is your best friend from college slowly fading because she does not know what to say and you do not have the energy to teach her.
Nobody tells you about the marriage. Not the [divorce statistics](/blog/divorce-two-household-routines-neurodivergent-children), which are more nuanced than the internet makes them sound. The daily stuff. The fact that you and your partner will process this differently, on different timelines, with different coping mechanisms. One of you will research for hours. The other will shut down. One of you will want to talk. The other will need silence. And both of you will be too exhausted to explain what you need, so you will just quietly drift until someone finally says "We need to talk about this."
Nobody tells you that the professionals will use acronyms you have never heard, and that they will assume you understand them, and that you will nod along because you do not want to look like you are not keeping up. [IEP](/blog/iep-meeting-preparation-guide-parents). BCBA. OT. SLP. FAPE. LRE. ABA. AAC. You will google all of them in your car after the meeting. You will still not fully understand half of them.
Nobody tells you that the waitlists are months long. That the [therapist](/blog/finding-right-therapist-neurodivergent-child) everyone recommends has a nine-month wait. That the developmental pediatrician your pediatrician referred you to is not taking new patients until next year. That the early intervention window everyone keeps warning you about is closing while you sit on hold.

## The Loneliest Part
Here is what makes the day after diagnosis so disorienting: you are surrounded by people who want to help but cannot, and systems designed to help but do not.
Your parents say "He seems fine to me." Your friend sends you an article about a miracle diet. Your neighbor asks if you have tried essential oils. Your mother-in-law says she read that autism is caused by screen time. And you stand there, holding all of this, trying to sort the good advice from the dangerous advice from the well-meaning advice that is just noise.
Research from a 2025 qualitative systematic review on social support experiences in parents of children with ASD found that parents consistently reported lacking emotional support from the people closest to them. Family, friends, professionals, and the broader community all fell short. The parents who fared best were the ones who found other parents walking the same road. Not experts. Not doctors. Other parents.
A study published in Family Process in 2024 found something that should be said out loud more often: fathers of autistic children are particularly vulnerable to loneliness, with interpersonal and familial resources playing a critical role in buffering that isolation. Dads do not have the same support networks, the same online communities, the same permission to fall apart. They are expected to be steady. And that steadiness can become its own kind of prison.
The loneliest part is not the diagnosis meeting. It is the Tuesday after, when nobody checks in.
## What Actually Helps
I am not going to hand you a five-step plan. I built [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) because my family needed it, and I would be dishonest if I said tools alone are the answer. They are part of it. But the real answer is messier.
**Lower the bar for yourself.** Not forever. Just right now. You do not need to become a special education expert this week. You do not need to have the perfect [morning routine](/blog/morning-routine-tips-adhd) by Friday. You need to get through the next 24 hours without burning yourself to the ground. That is enough.
**Find one parent who gets it.** Not a Facebook group with 50,000 members and conflicting advice. One person. A parent at your child's school. A parent in your pediatrician's waiting room. Someone from a local support group. The [Interactive Autism Network](https://iancommunity.org/) survey found that almost 80 percent of autism parents said stigma had been a significant difficulty in their lives. You need someone who does not need the stigma explained to them because they live it too.
**Stop googling at midnight.** I know. I did it too. But the internet at midnight is a different internet than the internet at 10 AM. The algorithms feed you fear. The forums surface the worst-case scenarios. Research on [trustworthy autism resources](/blog/trustworthy-autism-resources-online-tiktok-misinformation) shows that 41 percent of autism content on TikTok is inaccurate. Close the phone. The answers will still be there tomorrow when your brain is working.
**Write down your three biggest questions.** Not twelve. Not the full list of everything you do not understand. Three. Bring them to your next appointment. When the appointment starts, say "I have three questions" and put the paper on the table. This gives you permission to stop pretending you have it together and start getting the information you actually need.
**Let your child show you who they are.** Your child did not change when the diagnosis was spoken. They are the same person they were the day before. The same laugh. The same way they line up their cars. The same look they give you when they are overwhelmed. The diagnosis gives you a framework for understanding what you are already seeing. It does not rewrite your child. It translates them.
## The Parts Nobody Warns You About (But Should)
**Your identity is going to shift.** You will become "the autism parent" in certain circles, whether you want that label or not. People will define you by it. Some will treat you like an inspiration. Others will treat you like a cautionary tale. You are neither. You are a parent learning a new language in real time while keeping a small human alive and regulated. That is not inspirational. That is Tuesday.
**The paperwork will feel like a second job.** Insurance authorizations. [IEP documents](/blog/504-plan-vs-iep-neurodivergent-child). Therapy notes. Evaluation reports. Prior written notice. Progress reports. You will spend more time managing your child's care than actually being with your child some weeks, and the guilt of that will eat at you. Build systems early. Keep a folder. [Track what you can](/blog/tracking-emotions-activities-neurodivergent-children). Future you will be grateful.
**You will mourn things you did not expect to mourn.** It is not just the big milestones. It is the small ones. The neighborhood kids riding bikes while your child watches from the window. The sleepover invitation you have to decline because your child cannot handle it yet. The family vacation you have to cut short because the [sensory environment](/blog/sensory-processing-daily-routines) was too much. Each one is a small grief. They accumulate.
**You will also discover joy you did not expect.** The first time your child uses a word they have been practicing for months. The day they eat a new food. The moment they look at you and smile because they understood the joke. The progress is not linear, and it is not fast, but it is real. And it hits differently when you know how hard your child worked for it.
**Your other kids will need you too.** If you have neurotypical children, they are watching everything. They are adjusting their behavior. They are learning to be quieter, more patient, more invisible. The research calls them [glass children](/blog/glass-children-siblings-autistic-kids-forgotten), and the name fits. They deserve your attention even when your attention feels fully spent.
## Why I Built What I Built
My son was nonverbal until he was two. I remember the day after his diagnosis with the clarity that only fear can produce. I remember sitting on the living room floor with a stack of printouts and a child who could not tell me what he needed. I remember the feeling of wanting to fix everything and not knowing where to start.
I did not build [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) because I had the answers. I built it because I was drowning in the same questions every parent in this community is drowning in. How do I show him what comes next? How do I help him communicate when words are not available yet? How do I track what is working when every day feels like chaos?
The app came later. The [visual schedules](/blog/visual-schedules-for-autism). The [social stories](/blog/social-stories-autism-guide). The [emotion tracking](/blog/emotional-regulation-visual-supports). The [calming tools](/blog/happy-place-mindfulness-neurodivergent-children). All of that came from specific moments on specific days where I needed something that did not exist.
But before any of that, there was just a dad on a floor. Trying to figure out Monday morning.
If that is where you are right now, I see you.
## The Day After Is Not the End
The day after diagnosis feels like a door closing. It is not. It is a door opening to a hallway you did not know existed, full of rooms you have never been in, with people you have not met yet who understand exactly what you are carrying.
You are not behind. You are not failing. You are not the only one who does not understand the acronyms. You are not the only one whose marriage is strained. You are not the only one who cried in the Target parking lot because a stranger gave you a look when your child had a meltdown in aisle seven.
There are millions of us. We found our way. Not to a place where everything is perfect, but to a place where we stopped expecting perfect and started building something that actually works for our family.
The diagnosis was the beginning. Not the end.
And Monday morning? You will figure it out. Not because you have all the answers. But because you love someone enough to keep showing up for a life that did not come with a manual.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that give your child the predictability their brain craves, [track emotions and patterns](/blog/tracking-emotions-activities-neurodivergent-children) so you have real data instead of guesswork, and create [social stories](/blog/social-stories-autism-guide) that prepare them for what is coming next. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by an autism dad who sat on his living room floor and needed something that did not exist. Now it does. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the tools to see their day and navigate it with confidence.
---
## How to Prepare Your Neurodivergent Child for a New School or Classroom
Published: 2026-04-12 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/preparing-child-for-kindergarten-new-school-new-classroom
Category: Strategies
Author: Justin Bowman
> Whether it is kindergarten, a mid-year move, or a new classroom, here is how to prepare your neurodivergent child for one of the biggest transitions they will face.
Your child is starting kindergarten in the fall. Or maybe you are moving to a new district mid-year. Or the school just told you your child is switching classrooms because of a staffing change. Whatever the reason, a new school or new classroom is coming, and the knot in your stomach is already tightening.
You know what a routine change does to your child. You have seen what happens when the predictable becomes unpredictable. And now everything, the building, the teacher, the classmates, the schedule, the sensory environment, is about to change at once.
You are right to take this seriously. A 2024 scoping review published in the International Journal of Developmental Disabilities found that the success of school transitions for children with developmental disabilities is highly dependent on the support put in place by both families and the receiving school. Research published in Neuropsychiatric Disease and Treatment identified six essential elements for positive transitions, including school readiness and inclusiveness, collaboration between families and staff, and the child's own perspective being heard.
The good news is that preparation works. The research is clear on this. And the earlier you start, the smoother the transition will be.
## Why School Transitions Hit Neurodivergent Children Harder
Before diving into strategies, it helps to understand why this particular transition is so challenging for neurodivergent kids. It is not about being "difficult." It is about how their brains process change.
**Everything is new at once.** For neurotypical children, a new school means some adjustment. For a child with autism or ADHD, it means every single predictive model their brain has built, where the bathroom is, what the teacher's voice sounds like, which hallway leads where, when lunch happens, is suddenly useless. Their brain has to rebuild from scratch, and that process is cognitively exhausting.
**The sensory environment is completely unknown.** Every school has its own sensory signature. The pitch of the school bell. The echo in the hallway. The smell of the cafeteria. The lighting in the classroom. Your child has spent months or years adapting to their current environment. A new one means their [sensory processing system](/blog/sensory-processing-daily-routines) has to recalibrate to an entirely new set of inputs, and that recalibration takes energy that is no longer available for learning, socializing, or self-regulation.
**Social connections must be rebuilt.** If your child worked hard to build even one friendship, that bond may be disrupted by a school change. For children who find social connection challenging in the first place, the prospect of starting over can be deeply anxiety-producing. Research consistently shows that [social difficulty and peer exclusion](/blog/navigating-playdates-social-gatherings-neurodivergent-child) are among the biggest challenges neurodivergent children face during school transitions.
**The adults are strangers.** Your child's current teacher probably understands their cues, their triggers, and their strengths. A new teacher does not. Neither does the new aide, the new lunch monitor, or the new bus driver. Every trusted adult relationship has to be rebuilt, and trust does not happen on a schedule.
## Kindergarten: The First Big Transition
If your child is heading to kindergarten, this is likely their first experience with formal schooling. The stakes feel enormous, and the preparation needs to be intentional.
### Start Months Ahead, Not Weeks
The research on school readiness for neurodivergent children is clear: gradual preparation outperforms last-minute cramming every time.
**Practice school-like routines at home.** Two to three months before kindergarten starts, begin building a [morning routine](/blog/morning-routine-tips-adhd) that mirrors what the school day will require. Wake up at the same time. Get dressed. Eat breakfast at the table. Put on shoes. Practice the backpack. Walk to the car or bus stop. The more these steps feel automatic before school starts, the less cognitive energy your child will need on the first day.
**Build independence in key self-care skills.** Kindergarten teachers consistently report that the most helpful school readiness skills are independence, problem-solving, and [emotional regulation](/blog/emotional-regulation-visual-supports). Practice opening and closing lunchboxes, unwrapping snacks, managing jacket zippers, using the bathroom independently, and washing hands. These micro-skills reduce the number of moments your child has to ask for help from an unfamiliar adult, which reduces anxiety.
**Work on sitting and attending in small doses.** This is not about forcing your child to sit perfectly still. It is about gradually building their capacity for structured activity time. Start with five minutes of a structured table activity and build up over weeks. Use a [visual timer](/blog/first-then-boards-guide) so your child can see how long the activity will last. Celebrate what they accomplish, not how still they sat.
**Practice separations.** If your child has not spent time away from you in a structured setting, start now. Short, positive separations with a trusted caregiver build the emotional muscle needed for school drop-off. If your child already attends daycare or preschool, talk to those providers about gradually increasing the structure and expectations to better mirror a kindergarten classroom.
### Visit the School Before Day One
This is one of the most impactful things you can do. Contact the school and ask for a private tour when the building is quiet, before the school year starts. Walk the hallways with your child. Find the bathroom. Sit in the classroom. Touch the desk. Look at the playground. Let your child build a mental map of the space without the added stress of hundreds of other children.
If the school allows it, visit more than once. Each visit makes the environment slightly more familiar, which reduces the novelty response that triggers anxiety. Take photos during the visit and use them to create a [social story](/blog/social-stories-autism-guide) about what school will look like.
**Meet the teacher in advance.** Request a brief meeting with your child's teacher before the first day. Bring a one-page summary of your child: their strengths, their triggers, how they communicate best, what calms them, and what support they need. This is not about handing the teacher a manual. It is about starting the relationship with information rather than incidents.
### Prepare a Sensory Toolkit
Work with your child to assemble a small kit they can keep in their backpack: noise-reducing earplugs or earbuds, a favorite fidget tool, a [chewing tool](/blog/sensory-chewing-why-your-child-chews-everything) if they use one, and a comfort item if the school allows it. Knowing they have their tools available reduces anxiety about the sensory environment. Communicate with the teacher in advance about what your child has and why they need it.
## Moving to a New School Mid-Year
A mid-year school change comes with its own set of challenges. Your child does not have the natural on-ramp of a new school year where everyone is adjusting. They are walking into an established ecosystem where friendships are formed, routines are set, and they are the unknown variable.
### Transfer Documentation Proactively
Do not assume the schools will handle this smoothly. Request your child's complete records from the current school before the transition, including the current IEP or [504 plan](/blog/504-plan-vs-iep-neurodivergent-child), most recent evaluations, progress reports, behavioral plans, and any informal notes about strategies that work. Hand-deliver copies to the new school rather than relying on the transfer process.
If your child has an IEP, the new school must implement it as written until they either adopt it or hold a meeting to develop a new one. Know this. Enforce it. Do not accept "We do things differently here" as a reason to abandon accommodations that are legally required.
### Create a Transition Timeline
Give your child a visual countdown to the change. Use a calendar they can see and interact with. Mark the last day at the current school, the days off in between (if any), and the first day at the new school. Build in specific events they can look forward to, like a goodbye lunch with their current class or a visit to the new school.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) makes this easy. You can create a visual schedule of the transition itself, showing your child each step of the process with personalized AI-generated images. When a child can see what is coming, the uncertainty that fuels anxiety decreases.
### Address the Grief
Leaving a school means leaving behind people, routines, and places your child has grown attached to. Even if the move is positive, your child may grieve what they are losing. Acknowledge it. Saying "You are going to love your new school!" dismisses their feelings. Saying "It makes sense that you feel sad about leaving. We can talk about what you will miss, and we can also talk about what might be good about the new school" validates their experience while keeping the door open for hope.
For children who struggle to articulate their feelings, [emotion check-ins](/blog/tracking-emotions-activities-neurodivergent-children) using visual tools can help them express what they are processing. A feelings chart, a simple thumbs up or down, or [VizyPlan's](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) emotion tracking feature gives them a way to communicate without needing to find the words.
## Switching Classrooms Within the Same School
Sometimes the transition is not a new building but a new classroom, a new teacher, or a new set of classmates. Parents sometimes underestimate how disruptive this can be for a neurodivergent child. The school is familiar, but the micro-environment has shifted, and for a child who relies on predictability, that shift can feel enormous.
### Acknowledge That This Is a Big Deal
Adults may say "It is just a new classroom" or "It is the same school." For your child, it is not "just" anything. Their safe person is gone. The desk arrangement is different. The rules might be slightly different. The tone of voice is different. The schedule is different. Every one of those changes requires adaptation, and adaptation costs energy.
### Build a Bridge Between Old and New
Ask the school if your child can visit the new classroom before the switch. Can they meet the new teacher briefly? Can they see where their desk will be? Can they take a photo of the new classroom to look at before the transition day?
If your child had strategies that worked in the old classroom, communicate those to the new teacher. Write them down. Do not assume the information will be passed along verbally. Bring the same [visual supports](/blog/visual-schedules-for-autism) your child used before and ask the new teacher to incorporate them from day one so there is at least one thread of familiarity.
### Create a New Visual Schedule Immediately
Do not wait to see what the new routine looks like. Get the schedule from the new teacher as soon as possible and build a visual version your child can study and reference. When the daily flow is visible and predictable, the number of surprises drops, and with it, the anxiety.
## What to Do in the First Two Weeks
No matter what type of school transition your child is making, the first two weeks set the tone for everything that follows.
**Lower expectations at home.** Your child is spending massive amounts of energy adapting to the new environment. They may come home exhausted, dysregulated, or operating on empty. This is not the time to add new demands. Protect their [after-school decompression time](/blog/after-school-routine-transitions-neurodivergent-children). Let them stim, rest, and recharge.
**Expect regression.** Skills your child had mastered, [bedtime routines](/blog/bedtime-routine-autism-adhd), morning routines, [emotional regulation](/blog/emotional-regulation-visual-supports), may temporarily slip. This is normal and expected. The brain is allocating resources to processing the new environment, and other systems temporarily lose bandwidth. Do not panic. Gently support the routines without pressure, and they will come back. For a deeper look at this pattern, see our guide on [regression after routine disruption](/blog/regression-after-routine-disruption-autism-adhd).
**Check in daily, but do not interrogate.** Instead of "How was school?" (which is too vague for many neurodivergent children), try specific questions: "Did you eat your snack today?" "Did you go to the playground?" "What was the hardest part?" Or use a visual check-in tool where your child can point to how they felt rather than explaining it in words.
**Communicate with the school proactively.** Send the teacher a brief email after the first week. Ask how your child is adjusting. Share anything you are seeing at home that the school should know about. Establish yourself as a partner early so small issues get addressed before they become big ones.
**Celebrate small wins loudly.** Your child walked into the building without crying? That is a win. They ate lunch in the cafeteria? Win. They told you one thing about their new classroom? Win. The first two weeks are about survival and adaptation, not perfection. [Reward systems](/blog/points-rewards-motivation-neurodivergent) that recognize effort and bravery, not just achievement, build the resilience your child needs to keep going.
## When to Worry vs. When to Wait
Every child's adjustment timeline is different. Some neurodivergent children adapt within a few weeks. Others need a full semester. Research suggests that children with developmental disabilities may need [eight to twelve weeks](/blog/summer-regression-school-to-summer-transition-autism-adhd) to fully adjust to a significant routine change.
**Wait if:** Your child is gradually improving week over week, even slowly. They are eating, sleeping, and engaging in some positive way. They have hard moments but also have moments of connection or enjoyment.
**Worry if:** Your child is regressing significantly after the first month with no improvement. They are refusing to eat at school, having daily meltdowns that are escalating in intensity, showing signs of school refusal, or expressing things like "I hate myself" or "Nobody likes me." These are signals that the current level of support is not sufficient and the school team needs to be involved immediately.
If your child has an IEP, request a meeting to discuss whether the transition plan is adequate and whether additional supports are needed. If they do not have an IEP and are struggling significantly, this may be the time to [request an evaluation](/blog/504-plan-vs-iep-neurodivergent-child).
## You Know Your Child Best
School transitions are hard. They are hard for your child, and they are hard for you. Watching your child walk into a building full of strangers, knowing how much energy it will cost them, knowing they do not yet have a safe person or a familiar routine, is one of the harder parts of this parenting journey.
But preparation matters. The research proves it, and your experience probably confirms it. A child who has practiced the routine, visited the building, met the teacher, studied the visual schedule, and packed their sensory toolkit is a child who walks through that door with more resources than a child who was dropped into the unknown.
You cannot eliminate the challenge. But you can reduce the number of unknowns. And for a brain that thrives on predictability, every unknown you remove is a gift.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual schedules](/blog/visual-schedules-for-autism) for the new school routine, create [social stories](/blog/social-stories-autism-guide) that prepare your child for what is coming, and track their [emotional adjustment](/blog/tracking-emotions-activities-neurodivergent-children) through the transition. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps families of neurodivergent children prepare for every transition with visual routines, social stories, and emotion tracking that turns the unknown into the familiar. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the preparation they deserve.
---
## How to Know If Your Child's IEP Goals Are Actually Right
Published: 2026-04-11 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/are-iep-goals-right-for-your-child
Category: Strategies
Author: Justin Bowman
> A parent guide to evaluating whether your child's IEP goals are truly individualized, appropriately ambitious, and aligned with who your child actually is.
You are sitting in the IEP meeting. The special education teacher reads through a list of goals for the coming year. They sound professional. They have numbers and percentages. They reference things like "given a structured setting" and "as measured by teacher observation." Everyone nods. You sign the paper.
But on the drive home, something nags at you. One of those goals felt off. Maybe it described a skill your child already has. Maybe it focused on something that does not seem like a priority compared to what you see every single day at home. Maybe the language sounded copy-pasted from last year, or from a template, or from another child entirely.
You are not imagining it. Research from Boston University's Wheelock Center for Policy examined IEP goals at scale and found that many goals lack true individualization, with AI-generated goals being adopted without modification in roughly 31% of cases. A landmark study published in the Journal of Early Intervention found that only 2% of IEP objectives for young children with autism had adequate goal measurement descriptions, and 0% included clearly stated criteria and timelines written for individual objectives.
Your instinct that something feels wrong? That instinct is worth listening to.
## Why Goal Quality Matters More Than Most Parents Realize
The goals written into your child's IEP are not just paperwork. They are legally binding commitments that shape what your child is taught, how their progress is measured, and what services they receive every single day. When the goals are wrong, everything downstream suffers.
**Poorly written goals hide a lack of progress.** If a goal says your child will "improve social skills," there is no way to measure whether that happened. The school can report "progress" without your child actually gaining any new skills. A peer-reviewed study in the Journal of Early Intervention found that only 41% of IEP objectives for children with autism were even described in behavioral terms specific enough to measure. That means the majority of goals were written in a way that made accountability nearly impossible.
**Goals that are too easy deny your child growth.** The U.S. Supreme Court addressed this directly in Endrew F. v. Douglas County School District (2017). Drew, a boy with autism, had IEPs that were "substantially similar" year after year with nearly identical goals and minimal progress. The Court ruled unanimously that an IEP must be "reasonably calculated to enable a child to make progress appropriate in light of the child's circumstances" and that the program must be "appropriately ambitious." Chief Justice Roberts wrote that "a student offered an educational program providing merely more than de minimis progress from year to year can hardly be said to have been offered an education at all."
**Goals that do not match your child's actual needs waste everyone's time.** If your child's biggest challenge is [emotional regulation](/blog/emotional-regulation-visual-supports) but their IEP goals focus almost entirely on handwriting, the school is investing time and resources in the wrong place. The research bears this out: a study in the Journal of Early Intervention found that 20% of IEPs for children with autism had no social goals and 15% had no communication goals, despite these being core areas of need for autistic children.
## The Red Flags Every Parent Should Know
You do not need a special education degree to evaluate your child's IEP goals. You need to know what to look for.
### Goals That Sound Generic
If you could swap your child's name out and put any other child's name in without changing a word, the goal is not individualized. Every goal should be tied directly to your child's present levels of performance and reflect their specific strengths, challenges, and circumstances.
A generic goal: "Student will improve reading comprehension skills."
An individualized goal: "Given a grade-level passage of 200 words with accompanying visual supports, Maria will answer four out of five literal comprehension questions correctly across three consecutive sessions, as measured by teacher-created assessments."
The second goal tells you exactly what success looks like for this specific child, under what conditions, and how it will be measured. The first goal could apply to any student in any school in the country.
### Goals Without Baseline Data
Every goal in your child's IEP should connect directly to data in the present levels section. If a goal appears that was not mentioned as a need in the present levels, that is a red flag. Ask the team: "Where in the present levels does it show this is an area of need for my child?" If they cannot point to specific data, the goal may have been pulled from a template rather than built from your child's actual profile.
### Goals That Are Too Easy
If your child met last year's goal within the first two months, this year's goal should be more ambitious. Goals should stretch your child while remaining achievable. The Endrew F. standard requires that goals be "appropriately ambitious in light of the child's circumstances." If the goals feel like your child could meet them without any instruction at all, they are too easy, and the school is not meeting its legal obligation.
### Goals That Never Change
Review the past two or three years of IEPs side by side. Are the goals essentially the same? Are they using the same language, the same benchmarks, the same services? If your child's goals look like carbon copies from year to year, one of two things is happening: either your child is not making progress (which requires a conversation about why and what needs to change) or the school is not updating the goals to reflect growth (which means the IEP is not keeping pace with your child).
### Goals That Focus on Compliance Over Function
This is where neurodiversity-affirming advocacy becomes critical. Some IEP goals are written to make a child look neurotypical rather than to build skills that genuinely improve their quality of life. Julie Roberts, an autistic speech-language pathologist with the Therapist Neurodiversity Collective, has written extensively about how traditional goals often center on what makes adults comfortable rather than what serves the child.
**Red flag goals:**
- "Student will make eye contact when speaking to adults" (forced eye contact can be physically uncomfortable for many autistic people and does not improve communication)
- "Student will sit still for 20 minutes" (many children, especially those with ADHD, regulate better with movement)
- "Student will refrain from stimming during class" ([stimming](/blog/stimming-autism-when-to-support-when-concerned) serves important regulatory functions for many neurodivergent children)
**Better alternatives:**
- "Student will use a preferred communication method to initiate a request with an adult in three out of four opportunities"
- "Student will complete a 20-minute work task using self-selected regulation strategies such as standing, using a fidget tool, or taking a movement break"
- "Student will identify when they need a sensory break and independently access their regulation toolkit in four out of five opportunities"
The difference is not just language. It is philosophy. The first set of goals asks the child to mask. The second set builds genuine skills while honoring who the child actually is.

## How to Evaluate Goals Like a Pro
Here is a framework you can use to evaluate every single goal in your child's IEP. You do not need to be an expert. You need to ask the right questions.
### The SMART Check
Every goal should be:
- **Specific:** Does it name the exact skill your child will work on?
- **Measurable:** Does it include a number, percentage, or frequency that defines success?
- **Achievable:** Is it realistic given where your child is right now, but ambitious enough to represent real growth?
- **Relevant:** Does it address a genuine area of need that matters for your child's daily life, learning, or wellbeing?
- **Time-bound:** Does it include a timeline for when the goal should be met?
If any of these elements are missing, the goal needs revision.
### The "So What?" Test
For every goal, ask yourself: "If my child masters this, will it actually make a meaningful difference in their life?" A goal about maintaining eye contact for three seconds may be measurable, but it fails the "so what" test if it does not improve your child's ability to communicate, learn, or navigate their world.
The best IEP goals target skills that open doors. Communication that helps your child express their needs. [Self-advocacy](/blog/teaching-self-advocacy-skills-neurodivergent-child) that empowers them to ask for what they need. Executive function strategies that help them manage their day. Social skills that lead to genuine connection, not performed compliance.
### The Home-School Match
Compare the goals to what you see at home. Does the IEP focus on areas that are actually challenging for your child? Sometimes schools prioritize goals that address classroom management concerns rather than the child's most significant developmental needs. If the IEP is heavy on behavioral compliance goals but light on communication, emotional regulation, or academic support, push back.
Your perspective matters. You see your child in contexts the school never will. You know what they can do independently at home, what they struggle with on weekends, what skills would make the biggest difference for your family. That knowledge is not anecdotal. It is data.
## What to Do When Goals Are Not Right
You have more power than you think.
### Before the Meeting
**Review the draft IEP in advance.** You have the right to receive the proposed IEP before the meeting. Read every goal carefully. Mark anything that feels generic, too easy, missing measurement criteria, or focused on compliance rather than function. Write your questions down.
**Bring your own data.** Document what you observe at home. If you use [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) to [track your child's routines, emotions, and daily patterns](/blog/tracking-emotions-activities-neurodivergent-children), bring that information. When you can show the team a month of data on your child's morning routine or emotional regulation patterns, you shift the conversation from opinions to evidence.
**Know the Endrew F. standard.** If anyone at the table suggests that minimal progress is acceptable, you can cite the Supreme Court: your child's educational program must be "appropriately ambitious in light of his circumstances." This is not an obscure legal argument. It is the law of the land.
### During the Meeting
**Ask to see the data behind every goal.** When a goal is proposed, ask: "What data from the present levels supports this goal? How was this specific target chosen? What data collection method will be used to measure progress?" These questions are not confrontational. They are the questions every IEP team should be prepared to answer.
**Challenge vague language.** If a goal says "improve" or "increase" without specifying from what baseline to what target, ask for specifics. "Improve reading fluency" becomes meaningful only when it says "from 45 words per minute to 70 words per minute on grade-level passages."
**Propose alternatives.** You are an equal member of the IEP team under IDEA. If a goal does not feel right, you can suggest a different one. Bring written goal suggestions if you have them. If you want a goal to be more ambitious, say so. If you want a goal reframed to be neurodiversity-affirming, explain what that means and why it matters.
**Do not sign on the spot.** You are never required to sign the IEP at the meeting. Take it home. Review it with your child's private therapist, your partner, an advocate, or anyone who knows your child well. Come back with informed feedback. For a full breakdown of your rights in IEP meetings, read our guide on [everything you need to know before the next IEP meeting](/blog/iep-meeting-preparation-guide-parents).
### After the Meeting
**Request Prior Written Notice if you disagree.** If the school refuses to change a goal you believe is inappropriate, ask for Prior Written Notice. This forces the school to put in writing what they are proposing, why they are proposing it, what data supports it, and what alternatives were considered and rejected. This document becomes critical if you need to escalate.
**Monitor progress reports.** When progress reports arrive, read them against the goals. Is the school collecting data the way the IEP specifies? Is progress being reported in measurable terms, or in vague language like "making adequate progress"? If the data is not matching what you see at home, request a meeting to discuss.
**Request an IEP revision at any time.** You do not have to wait for the annual review. If goals are not working, if your child has already met a goal and needs a new one, or if circumstances have changed, you can request a meeting at any time by putting it in writing.
## Building a Year-Round Advocacy System
The parents who are most effective at IEP advocacy are the ones who prepare all year, not just the week before the meeting.
**Track patterns at home consistently.** Use tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) to monitor your child's [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children), routine completion, and behavioral trends over time. When you walk into an IEP meeting with three months of data showing that your child's afternoon meltdowns correlate with a lack of sensory breaks at school, you have something the team cannot dismiss.
**Keep a communication log.** Save every email with the school. Document phone conversations with a follow-up email: "Just wanted to confirm what we discussed today..." This paper trail matters if you ever need to file a complaint or request mediation.
**Connect with your state's Parent Training and Information Center (PTI).** Every state has a federally funded PTI that provides free guidance on special education rights and advocacy strategies. These organizations can help you understand the legal standards, review your child's IEP, and even attend meetings with you.
**Talk to your child's private providers.** If your child sees a [therapist](/blog/finding-right-therapist-neurodivergent-child), ask them to review the IEP goals. Outside professionals can offer perspective on whether the goals align with your child's clinical profile and developmental trajectory. They can also write letters supporting your position if the school pushes back.
## Your Child Deserves Goals That Match Who They Are
The IEP process can feel overwhelming. The jargon, the power dynamics, the pressure to sign and move on. But you know your child in ways no evaluation can capture. You know the difference between a skill they have mastered and one they are still building. You know whether a goal reflects who they actually are or who the school wishes they were.
An IEP that truly serves your child does not just meet a legal standard. It captures their strengths, addresses their real needs, sets ambitious but achievable targets, respects their neurology, and creates a path toward genuine growth. Not growth measured by how well they can sit still or make eye contact. Growth measured by how confidently they can navigate their world.
Trust your instincts. Ask the hard questions. Bring your data. And remember that "appropriately ambitious" is not just a legal phrase. It is what your child deserves.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Track daily routines, monitor [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children), and build the documentation you need to walk into your next IEP meeting with confidence and evidence. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps families of neurodivergent children build visual routines, track progress, and create the data-driven evidence that turns IEP meetings from overwhelming to empowering. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and advocate with confidence.
---
## Summer Regression: How to Protect Your Child's Progress During the School-to-Summer Transition
Published: 2026-04-10
URL: https://vizyplan.com/blog/summer-regression-school-to-summer-transition-autism-adhd
Category: Strategies
Author: Justin Bowman
> Up to 80% of neurodivergent children lose skills over summer break, and recovery can consume the entire fall semester. Here is how to prevent it.
The last day of school is supposed to feel like freedom. For a lot of neurodivergent families, it feels more like standing at the edge of a cliff.
You spent the entire school year building routines. Your child finally learned to transition between activities without a meltdown. The morning routine was working. Homework had a rhythm. Bedtime was predictable. Then June arrives, and the structure that held everything together disappears overnight.
By mid-July, skills that took months to build start slipping away. The independent morning routine? Now you are back to prompting every step. The words your child was using at dinner? Replaced by frustration and shutdowns. And when September rolls around, their teacher spends the first two months just getting them back to where they were in May.
This is not a parenting failure. This is summer regression, and it is one of the most predictable and preventable challenges neurodivergent families face.
## Why Summer Hits Neurodivergent Children Harder
Every child experiences some degree of summer learning loss. Research by Cooper et al. found that students typically lose one to three months of academic progress over summer break. But for children with autism and ADHD, the impact goes far beyond academics.
**The scaffolding disappears.** School provides external structure that compensates for executive function challenges. For children with ADHD, whose prefrontal cortex develops on a different timeline, that school schedule is essentially a [prosthetic for self-regulation](https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2894421/). Remove it, and the child loses both the internal ability and the external support at the same time. As we explored in our post on [regression after routine disruption](/blog/regression-after-routine-disruption-autism-adhd), the skills are not gone. The scaffolding that made them accessible is.
**Uncertainty triggers anxiety.** Research published in the Journal of Autism and Developmental Disorders found that [intolerance of uncertainty mediates the relationship between autism and anxiety](https://link.springer.com/article/10.1007/s10803-014-2077-9). Summer is weeks of open-ended, unstructured time. For a child whose brain craves predictability, that is not relaxation. That is sustained stress.
**Procedural skills degrade without practice.** Many of the skills neurodivergent children build, from social scripts to self-care sequences to [communication routines](/blog/social-stories-autism-guide), are procedural. They live in a part of the brain that requires consistent rehearsal. Without daily practice, those neural pathways weaken. It is like a muscle that atrophies when you stop using it, except rebuilding it takes longer each time.
**The recovery cost is enormous.** Neurotypical students typically recoup summer losses within four to six weeks. Children with disabilities may need [eight to twelve weeks](https://www.parentcenterhub.org/esy/), effectively spending the entire fall semester recovering what was lost over summer. For some children with higher support needs, certain skills may never fully return to pre-summer levels.
## The Numbers Are Sobering
While no single large-scale study pins down exact figures for neurodivergent populations specifically, clinical consensus and smaller studies paint a consistent picture:
- An estimated 60 to 80 percent of autistic children show measurable regression in at least one skill domain over extended breaks of six or more weeks
- Speech and language skills and social skills are the most vulnerable to summer loss
- The regression-recoupment cycle means some children effectively lose half their annual progress every year
- Only 5 to 15 percent of students with IEPs nationally receive Extended School Year (ESY) services, leaving most families to bridge the gap on their own
The landmark court cases Armstrong v. Kline (1979) and Battle v. Commonwealth of Pennsylvania (1980) established that denying year-round services to children who experience significant summer regression violates their right to a Free Appropriate Public Education under IDEA. If your child consistently loses skills over summer, you have legal standing to request ESY services through their [IEP team](/blog/iep-meeting-preparation-guide-parents).
## Start Before the Last Day of School
The most effective strategy is not reactive. It is proactive. Begin preparing two to four weeks before school ends.
### Build a Summer Visual Schedule Now
Do not wait until the first day of summer to figure out what the days will look like. Create a [visual schedule](/blog/visual-schedules-for-autism) that maps out the summer routine before school ends. Let your child see what is coming so the transition is not abrupt.
Your summer schedule does not need to replicate school. It needs anchor points. Pick three to four non-negotiable structure points each day:
- **Wake time** (within 30 to 60 minutes of the school year, per AOTA recommendations)
- **One structured activity block** (therapy practice, learning activity, or skill-building time)
- **Outdoor or physical activity** (supports behavioral regulation and sleep)
- **[Bedtime routine](/blog/bedtime-routine-autism-adhd)** (the single most important routine to protect)
Everything between those anchors can be flexible. The anchors themselves should not move.
### Write a Summer Social Story
Before the last week of school, create a [social story](/blog/social-stories-autism-guide) that explains the transition. Cover what will change, what will stay the same, and what summer will look like. Include photos of actual summer locations and activities whenever possible.
Children who understand what is coming handle transitions better. Research on cognitive flexibility in autism confirms that [predictability serves as a crucial coping mechanism](https://www.frontiersin.org/journals/psychology/articles/10.3389/fpsyg.2021.731753/full).
### Create a Last Day Ritual
Give the school year a clear ending. A goodbye card for the teacher. A photo with the classroom. A special after-school celebration. Emotional closure reduces the anxiety of ambiguity. Your child needs to understand: this chapter is finished, and the next one has already been planned.
### Shift Gradually
Do not flip the schedule overnight. The American Academy of Pediatrics recommends adjusting bedtime and wake time by fifteen-minute increments over one to two weeks rather than making an abrupt change. Start introducing summer elements alongside the school routine before the school routine disappears entirely.
## Protecting Skills Through the Summer
Once summer starts, your job shifts from preparation to maintenance. You do not need to run a homeschool. You need to preserve the pathways your child built during the school year.
### Keep Therapy Connections Alive
The Marcus Autism Center recommends [maintaining therapy services during breaks](https://www.marcus.org/autism-resources/autism-tips-and-resources/maintaining-skills-over-the-summer) whenever possible. If your child receives speech, OT, or ABA through school, those services likely pause in June. Options include:
- **Private therapy continuation** if insurance and budget allow
- **Telehealth check-ins** with existing providers
- **Home practice packets** requested from therapists before the school year ends
- **Structured practice blocks** of 15 to 30 minutes daily, embedding therapy goals into summer activities
If your child's [ABA hours have been reduced](/blog/aba-therapy-cuts-what-to-do-at-home), summer is a critical time to integrate those strategies into daily routines at home.
### Embed Practice in Real Life
You do not need flashcards and worksheets. You need intention.
- Practice requesting and labeling at the pool or the park
- Work on turn-taking during board games and water play
- Use [first-then boards](/blog/first-then-boards-guide) for summer outings: "First sunscreen, then sprinklers"
- Build [fine motor practice](https://www.aota.org/) into cooking, crafts, and gardening
- Create communication-rich environments by narrating daily activities and asking open-ended questions during natural routines
The American Speech-Language-Hearing Association emphasizes that carryover activities embedded in real contexts are more effective than isolated drills.
### Build a Boredom Box or Choice Board
Unstructured free time is where summer falls apart for many neurodivergent children. Open-ended "go play" instructions can trigger [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies), decision fatigue, or screen time spirals.
A [choice board](/blog/choice-boards-empowering-decisions) with five to eight pre-approved activities gives your child autonomy within boundaries. Visual options might include drawing, building with blocks, water play, reading, a sensory bin, or helping with a household task. The goal is reducing the cognitive load of deciding what to do next.
### Protect Sleep Above All Else
Over [80 percent of autistic individuals](https://psychiatryonline.org/doi/full/10.1176/appi.focus.20230028) experience sleep problems, and research shows that children who sleep fewer hours have [lower overall intelligence, verbal skills, adaptive functioning, and socialization skills](https://www.sciencedirect.com/science/article/abs/pii/S0891422212000686). If only one routine survives the summer intact, make it the bedtime routine.
A well-rested brain recovers faster, regulates emotions better, and holds onto learned skills more effectively. Letting bedtime drift by two hours in July means spending all of August trying to claw it back before school starts.
### Plan for Sensory Challenges Unique to Summer
Summer introduces sensory experiences that do not exist during the school year. Sunscreen texture. Swimsuit discomfort. Heat sensitivity. Fireworks. Bug spray. Sand. The sound of a crowded pool.
Proactively plan for these using gradual desensitization, [sensory accommodations](/blog/sensory-processing-daily-routines), and visual preparation. A child who has practiced putting on sunscreen at home three times before the beach trip handles it differently than a child ambushed by it in the parking lot.
## Maintaining Social Connections
Social skill regression is one of the steepest summer losses for neurodivergent children. School provides daily, structured peer interaction. Summer removes it entirely.
### Schedule Structured Playdates
Do not rely on organic social opportunities. Schedule regular playdates with clear activities, defined start and end times, and visual supports. A playdate with a plan is far more successful than an open-ended "go play together" situation. For more specific strategies, see our guide on [navigating playdates](/blog/navigating-playdates-social-gatherings-neurodivergent-child).
### Explore Inclusive Summer Programs
Many communities offer inclusive camps or summer programs for neurodivergent children. Some allow one-on-one aides or shadows. Research options early, as programs fill quickly, and arrange a pre-summer visit so the environment is familiar before the first day.
### Use Family Time Strategically
Siblings, cousins, and family gatherings are structured practice opportunities. Work on greeting, conversation, cooperative play, and [turn-taking](/blog/teaching-turn-taking-sharing-neurodivergent-children) with familiar people before expecting your child to generalize those skills to less familiar peers.
## Preparing for the Return to School
Summer regression is a cycle. The same strategies that protect skills during summer also make the return to school smoother.
Start shifting back toward the school schedule two weeks before the first day. Reintroduce the [morning routine](/blog/morning-routine-tips-adhd). Visit the school building if possible. Create a social story about the new classroom, the new teacher, the new schedule. For a full breakdown of the back-to-school transition, see our guide on [returning to school after a break](/blog/returning-to-school-after-break-neurodivergent-children).
The children who transition back most smoothly are the ones whose summers kept the anchor routines in place. Their brains never fully lost the scaffolding, so they are not rebuilding from scratch.
## You Are Not Starting Over
If your child has already regressed, or if you are reading this mid-July with a sinking feeling that you missed the window for preparation, hear this: you are not starting over.
The skills your child built during the school year are encoded in their brain. The pathways are weakened, not erased. Rebuilding is faster than building from scratch, especially when you approach it with [visual supports](/blog/visual-schedules-for-autism), consistent routines, and the understanding that regression is a neurological response to environmental change, not a reflection of your child's ability or your parenting.
Every anchor routine you put back in place reconnects a pathway. Every visual schedule you post on the wall reduces uncertainty. Every structured activity block protects a skill that would otherwise continue to fade.
Summer does not have to mean starting over in September.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build summer visual schedules, maintain therapy routines with structured activity blocks, and create social stories that prepare your child for every seasonal transition. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and protect your child's progress this summer.
---
## VizyPlan Sponsors the Autism Superhero 5K at Polar Park
Published: 2026-04-09
URL: https://vizyplan.com/blog/vizyplan-sponsors-autism-superhero-5k-worcester
Category: Announcements
Author: Justin Bowman
> VizyPlan is proud to be a water table sponsor at the 2026 Autism Superhero 5K at Polar Park in Worcester, MA. This cause is personal for us.
Some sponsorships are business decisions. This one is personal.
On Saturday, April 18, my son and I will be at Polar Park in Worcester, Massachusetts, handing out water at the [2026 Autism Superhero 5K](https://www.autismresourcecentral.org/superhero/). [VizyPlan](https://vizyplan.com) is a water table sponsor for this year's race, and honestly, writing that sentence still hits different than any product launch or feature update I have ever announced.
Because this is not a cause we believe in from a distance. This is a cause we live in. Every single day.
## Why This Race Matters to Us
If you have followed the [VizyPlan story](/about), you know that this app exists because my son needed a better way to see his day. He is autistic. The early years were full of laminated pictures taped to walls, bulky binders, and stick-figure drawings that never quite captured his world. [VizyPlan](https://vizyplan.com) was born from that experience, from a dad who needed better tools and decided to build them.
So when the [Autism Resource Center](https://www.autismresourcecentral.org/) puts together an event that brings hundreds of autism families together at a ballpark on a Saturday morning in April, we do not just want to write a check. We want to be there. Pouring water. High-fiving runners. Watching kids in superhero capes cross the finish line. Being part of a community that understands what our family lives every day.
My son will be there with me. And that matters more than any logo on a banner.
## What Is the Autism Superhero 5K?
The Autism Superhero 5K is an annual event organized by the [Autism Resource Center](https://www.autismresourcecentral.org/), a program of Advocates. The Autism Resource Center was founded in 1996 by a group of parents in Central Massachusetts who were looking for information and support after their children's autism diagnoses. Today, the organization serves over 4,000 families across 65 towns in the Worcester region, providing family support, social skills groups, parent training, sibling workshops, adaptive swimming, and much more.
The 5K takes place at [Polar Park](https://www.milb.com/worcester), home of the Worcester Red Sox, on a USATF-certified course. But it is so much more than a race. The event runs from 7:30 AM to 1:00 PM and includes:
- **5K Run/Walk** starting at 10:00 AM
- **1-Mile Walk** for those who prefer a shorter route
- **Kids Fun Run** at 11:30 AM with prizes by age category
- **Superhero meet-and-greet** for the kids
- **Craft stations, games, raffles, and giveaways**
- **Community resource vendor booths** connecting families with local services
- **Ballpark concessions** because it is still a day at the park
The first 200 registrants receive a commemorative t-shirt, and every 5K participant gets a finisher medal. ASL interpreters and other accommodations are available on request.
Registration is open now at [autismresourcecentral.org/5kreg](https://www.autismresourcecentral.org/5kreg/). Pricing starts at just $5 for children 12 and under, $10 for teens, $15 for the 1-mile walk, and $35 for the full 5K. You do not have to be a runner to participate. You do not even have to walk. You can show up, enjoy the vendors, let your kids do the fun run, and be part of something bigger.
## Why Community Matters
Building an app for neurodivergent families is one thing. Being part of the community is another.
Autism families know the difference between companies that market to them and companies that show up for them. We have all seen the brands that slap a puzzle piece on their logo in April and call it awareness. That is not what this is.
[VizyPlan](https://vizyplan.com) exists because an autism dad sat on his living room floor trying to explain tomorrow to a toddler who could not yet speak. Every feature we build comes from lived experience, not market research. And sponsoring a local 5K where autism families come together to celebrate their kids as superheroes is the most natural extension of that mission I can think of.
The [Autism Resource Center](https://www.autismresourcecentral.org/) has been doing this work since 1996. They were founded by parents, just like [VizyPlan](https://vizyplan.com). They serve families in the same community where my son grows up. Supporting their annual event is not a marketing strategy. It is showing up for the people who show up for us.
## Come Find Us at the Water Table
If you are in the Worcester area on April 18, come say hi. We will be the ones at the water table, probably wearing [VizyPlan](https://vizyplan.com) shirts and definitely cheering too loudly for every single finisher.
Bring your kids. Wear a cape. Run, walk, or just hang out. This is a day for our community, and every family that shows up makes it better.
**[Register for the 2026 Autism Superhero 5K](https://www.autismresourcecentral.org/5kreg/)**
And if you cannot make it to Worcester but want to support the Autism Resource Center's mission, you can learn more about their programs and how to get involved at [autismresourcecentral.org](https://www.autismresourcecentral.org/).
## See You at Polar Park
April is Autism Acceptance Month. And there is no better way to mark it than by lacing up, showing up, and standing alongside the families who make this community what it is.
My son and I will see you there.

---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) is a visual routines app built by an autism dad for neurodivergent families. We build tools that help children see their day and navigate it with confidence. And when we are not building, we are out in the community supporting the organizations and events that make life better for families like ours. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and see what [VizyPlan](https://vizyplan.com) can do for your family.
---
## Bedwetting and Autism: What Parents Need to Know
Published: 2026-04-08
URL: https://vizyplan.com/blog/bedwetting-autism-nocturnal-enuresis-guide
Category: Daily Routines
Author: Justin Bowman
> Bedwetting affects up to 30% of autistic children. It is not a behavior problem and it is not their fault. Here is the science behind why it happens and what actually helps.
You strip the sheets for the third time this week. It is 2 AM, your child is standing in the hallway looking confused and upset, and you are trying to stay calm while also calculating how many clean sets of bedding you have left. You have tried limiting drinks after dinner. You have tried waking them up before you go to sleep. You have tried rewards, reminders, and prayers. Nothing seems to stick.
If this is your life right now, here is the first thing you need to hear: this is not your child's fault. And it is not yours either.
Bedwetting, known clinically as nocturnal enuresis, is significantly more common in autistic children than in their neurotypical peers. Research by [Von Gontard et al. (2015)](https://pubmed.ncbi.nlm.nih.gov/26052001/) found nocturnal enuresis in 30% of children with autism compared to 0% in the control group. Other studies estimate prevalence between 20% and 38% in autistic children, compared to roughly 11 to 15% in typically developing kids of the same age.
Those numbers are important because they tell you something essential: your child is not an outlier. This is a known, well-documented part of the autism experience that deserves the same compassion and evidence-based support as any other challenge your family faces.
## Why Autistic Children Are More Likely to Wet the Bed
Understanding the "why" changes everything about how you respond. Bedwetting in autistic children is not about laziness, attention-seeking, or regression. It is driven by real neurological and developmental differences.
### Interoception Differences
Interoception is the sense that tells your brain what is happening inside your body: hunger, thirst, pain, temperature, and the need to use the bathroom. [Research consistently shows](https://pmc.ncbi.nlm.nih.gov/articles/PMC11075678/) that autistic individuals experience interoception differently. Many children with autism genuinely do not feel the sensation of a full bladder, especially during sleep when awareness is already reduced. Their brain is not ignoring the signal. The signal is not arriving clearly enough to wake them up.
This is the same interoception challenge that makes [potty training](/blog/potty-training-autism-adhd-visual-supports) more complex for neurodivergent children. The daytime version of the problem often gets addressed with visual schedules and timed toilet sits. The nighttime version requires different strategies because the child is asleep and cannot consciously respond to prompts.
### Sleep Problems Compound the Issue
Sleep disturbances affect [44 to 83% of autistic children](https://pmc.ncbi.nlm.nih.gov/articles/PMC11046719/), and this is one of the strongest contributing factors to bedwetting. Autistic children often have decreased melatonin levels, altered sleep architecture with reductions in REM sleep, and difficulty maintaining consistent sleep cycles.
When sleep quality is poor, the brain is less likely to register and respond to a full bladder signal. Deep sleep patterns can make it nearly impossible for the child to wake up when they need to go. And irregular sleep schedules disrupt the body's natural production of antidiuretic hormone (ADH), which normally concentrates urine at night so less is produced while sleeping.
If your child struggles with [sleep](/blog/autism-and-sleep-problems-what-actually-helps), addressing that piece of the puzzle may be the single most impactful thing you can do for bedwetting too.
### Constipation: The Hidden Culprit
This one surprises many parents, but constipation is one of the most common and most overlooked causes of bedwetting. When the bowel is full, it pushes directly on the bladder, reducing its capacity and making accidents far more likely. Research published in [PMC](https://pmc.ncbi.nlm.nih.gov/articles/PMC8173284/) shows that properly treating constipation alone can produce an 89% reduction in daytime wetting.
If your child has hard stools, infrequent bowel movements, or complains of stomach pain, talk to your pediatrician before pursuing any other bedwetting intervention. Solving the constipation may solve the bedwetting.
### Sensory Processing and Anxiety
Children who are [hyposensitive (under-responsive)](/blog/sensory-processing-daily-routines) to internal body signals may not receive strong enough bladder cues to wake up. Meanwhile, anxiety and behavioral rigidity, both common in autism, can create patterns of holding urine during the day that lead to overflow at night.
Stressful life events like [routine disruptions](/blog/regression-after-routine-disruption-autism-adhd), school transitions, or family changes can trigger or worsen bedwetting. If your child was dry for months and suddenly starts wetting the bed again, look at what changed in their world.
### Medications Can Play a Role
Some medications commonly prescribed for autistic children can contribute to bedwetting. Risperidone has reported incontinence rates ranging from [3.2% to 65.4%](https://pmc.ncbi.nlm.nih.gov/articles/PMC8173284/) across studies. If your child started or changed medications around the time bedwetting began or worsened, bring this up with their prescribing doctor.
## What Actually Helps
The good news is that effective, evidence-based strategies exist. The key is matching the approach to your child's specific needs and being patient with the process.
### Build a Bulletproof Bedtime Routine
A consistent [bedtime routine](/blog/bedtime-routine-autism-adhd) is the foundation. The same steps, in the same order, at the same time, every night. And critically, the routine must include a final toilet trip as the very last step before lights out.
A [visual schedule](/blog/visual-schedules-for-autism) for the bedtime routine makes this concrete and predictable. When your child can see each step laid out, the routine becomes something they own rather than something being done to them. Include: brush teeth, put on pajamas, use the toilet, get into bed, lights out. Post the visual at their eye level in the bedroom or bathroom.
### Try a Bedwetting Alarm
Bedwetting alarms are the [first-line treatment recommended by both the AAP and NICE guidelines](https://www.nice.org.uk/guidance/cg111). They work by detecting moisture and waking the child at the first sign of wetting, which gradually trains the brain to recognize and respond to a full bladder during sleep. About 50% of children achieve dryness with consistent use, and the long-term success rate is better than medication.
A [published case study](https://www.researchgate.net/publication/257586201_Behavioral_Treatment_of_Bedwetting_in_an_Adolescent_with_Autism) showed that a 12-year-old girl with autism achieved dry nights within three weeks using a urine alarm combined with positive reinforcement.
For autistic children, consider these adaptations:
- **Choose sensory-friendly alarms.** Some children react strongly to loud sounds. Look for alarms that vibrate instead of beeping, or ones that do not attach directly to the body.
- **Prepare with a social story.** Before introducing the alarm, use a social story to explain what it does and why. "This helper tells me when my body needs the toilet at night."
- **Start on a weekend** when disrupted sleep is less consequential.
- **Pair the alarm with calm, positive support.** When it goes off, guide your child gently to the bathroom without frustration.
### Manage Fluids Without Restricting Them
NICE guidelines are clear: do not restrict fluids as a treatment for bedwetting. Children need adequate hydration for overall health, and dehydration can actually worsen constipation, which worsens bedwetting.
Instead, shift the timing. Encourage most fluid intake during the morning and afternoon. Offer a normal amount at dinner but avoid large drinks in the hour before bed. Cut out caffeine and sugary drinks in the evening entirely. If your child uses desmopressin medication, limit fluids to 8 ounces on those nights.
### Reward Effort, Not Dryness
This distinction matters enormously. Your child cannot control what happens while they are asleep. Rewarding dry nights can backfire because it sets up a goal the child has no power to achieve, which creates frustration and shame when they fail.
Instead, reward the things they can control:
- Going to the toilet before bed
- Following the bedtime routine
- Helping with sheets in the morning (matter-of-factly, not as punishment)
- Being brave about trying the alarm
A visual reward chart where your child earns stickers for completing the routine, not for staying dry, builds positive associations with bedtime instead of anxiety.
### Address Sleep Quality
If your child has [trouble sleeping](/blog/autism-and-sleep-problems-what-actually-helps), improving sleep quality may reduce bedwetting as a secondary benefit. Consistent sleep and wake times, a dark and quiet room, limited screens before bed, and melatonin supplementation (with your pediatrician's guidance) can all improve sleep architecture. Better sleep means a brain that is more responsive to internal signals, including the signal of a full bladder.
## What You Should Never Do
The research on this is unequivocal.
### Never Punish Bedwetting
A study by [Al-Zaben and Sehlo (2015)](https://pubmed.ncbi.nlm.nih.gov/25435105/) studied 65 children with bedwetting and found that children who were punished had more wet nights per week, increased depressive symptoms, and lower quality of life. Punishment does not reduce bedwetting. It increases it while simultaneously damaging your child's mental health.
In the United States, approximately 25% of parents still punish their child for bedwetting. The data could not be more clear: punishment creates a downward cycle of shame, lost confidence, and more frequent accidents.
### Never Blame the Child
Both NICE and AAP guidelines emphasize that bedwetting is not the child's fault and not within their conscious control. It is a medical and developmental condition, not a behavior problem. Saying things like "you are too old for this" or "just try harder" is not only unhelpful, it is harmful.
### Do Not Ignore Constipation
If you are pursuing bedwetting treatments without first checking for constipation, you may be solving the wrong problem. A full bowel pressing on the bladder is one of the most treatable causes of nighttime accidents.
## When to See a Doctor
Most bedwetting in young children is developmental and resolves over time. But certain situations warrant medical evaluation.
**See your pediatrician if:**
- Your child is over 7 and still wetting regularly
- Bedwetting returns after six or more months of being dry (secondary enuresis)
- There are signs of urinary tract infection: painful urination, frequent urination, cloudy or strong-smelling urine, fever
- Your child has excessive thirst and frequent daytime urination (possible diabetes)
- Constipation is persistent despite dietary changes
- There is daytime wetting in addition to nighttime wetting
- Your child snores heavily or shows signs of sleep apnea
- Bedwetting began around the time a new medication was started
Your doctor may order a urinalysis to check for infection or diabetes, and may assess for constipation or other underlying conditions. For persistent cases, a referral to a pediatric urologist may be helpful.
## Medications: What to Know
**Desmopressin (DDAVP)** is the most commonly prescribed medication for bedwetting. It is a synthetic version of antidiuretic hormone that reduces urine production at night. It is effective in [25 to 65% of children](https://pmc.ncbi.nlm.nih.gov/articles/PMC8984681/), with the AAP citing 40 to 60% effectiveness.
The important caveat: desmopressin works only while being taken. When you stop, bedwetting typically returns. This makes it most useful for specific situations like sleepovers, school trips, or overnight camps where your child needs reliable dryness for a short period. Alarms produce better long-term results.
If your child takes desmopressin, fluid intake must be limited to 8 ounces on the evenings it is used to avoid a rare but serious complication called hyponatremia (water intoxication). For autistic children with rigid drinking habits or [sensory seeking around food and liquids](/blog/safe-foods-autism-sensory-science-food-refusal), this fluid restriction may require careful planning and visual supports.
## Protecting Your Child's Self-Esteem
Bedwetting carries real emotional weight. Research shows that children who wet the bed have significantly lower self-esteem than those who do not. They may develop depressive symptoms, withdraw from social activities, and avoid sleepovers or overnight camps out of fear of being discovered.
For autistic children who may already navigate social challenges, bedwetting adds another layer of vulnerability. How you handle it at home sets the tone for how your child feels about themselves.
**Normalize it.** Tell your child that lots of kids' bodies are still learning to stay dry at night. Use matter-of-fact language. "Your body made extra pee while you were sleeping. That happens sometimes. Let's get cleaned up."
**Protect their privacy.** Never discuss bedwetting in front of siblings, relatives, or friends unless your child is okay with it. This is private health information.
**Plan for sleepovers.** When your child is ready, discreet pull-ups, waterproof sleeping bag liners, and a quiet conversation with the host parent can make overnight stays possible. Desmopressin can provide an extra layer of confidence for special occasions.
**Separate the child from the problem.** Your child is not "a bed wetter." They are a child whose body is still developing nighttime bladder control. Language matters.
## The Long View
Here is what the research tells us that nobody says enough: bedwetting almost always resolves. The spontaneous resolution rate is approximately 15% per year, meaning that each year, a significant portion of children who wet the bed simply stop. For most children, this is a temporary chapter, not a permanent condition.
Your job during this chapter is to keep the sheets clean, keep your child's confidence intact, and keep pursuing gentle, evidence-based strategies that support their body's development. Check for constipation. Address [sleep problems](/blog/autism-and-sleep-problems-what-actually-helps). Build a consistent [bedtime routine](/blog/bedtime-routine-autism-adhd) with a final toilet trip. Try an alarm when your child is ready. And above all, respond with warmth instead of frustration.
Your child is not choosing this. Their body is still learning. And with the right support, it will get there.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build consistent [bedtime routines](/blog/bedtime-routine-autism-adhd) with visual schedules that include that critical final toilet trip, [track your child's emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) around sleep and nighttime challenges, and create morning routines that handle wet mornings with dignity and structure. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your family the visual tools to navigate bedwetting with calm, consistency, and confidence.
---
## Why Your Child Chews on Everything (And What Actually Helps)
Published: 2026-04-07
URL: https://vizyplan.com/blog/sensory-chewing-why-your-child-chews-everything
Category: Strategies
Author: Justin Bowman
> Your child is not being destructive. Sensory chewing is a neurological need that serves a real purpose. Here is the science behind why children chew and evidence-based strategies that work.
You find the third chewed-through shirt collar this week. The pencils at the homework station look like they survived a beaver attack. Your child's sleeves are permanently damp. And you have lost count of how many times someone has told you to "just make them stop."
Here is what nobody told you: your child is not being destructive. They are not doing this to annoy you. And telling them to stop is not going to help.
Sensory chewing is one of the most common and most misunderstood behaviors in neurodivergent children. It serves a real neurological purpose, and once you understand what that purpose is, everything about your approach changes.
## What Is Actually Happening When Your Child Chews
Your child's jaw is one of the strongest muscles in the human body. When they chew, the proprioceptors in the jaw joint send deep-pressure signals through the trigeminal nerve directly to the brainstem. This input helps regulate the reticular activating system, which governs overall arousal levels. In plain language: chewing sends a powerful calming signal to the brain.
This is the same mechanism behind weighted blankets, bear hugs, and compression clothing. Deep pressure input activates the parasympathetic nervous system, the body's "rest and digest" mode. Research published in *Physiology & Behavior* found that chewing [reduces cortisol levels during acute stress](https://pubmed.ncbi.nlm.nih.gov/19268676/) and alleviates negative mood. A review in the *Journal of Clinical Trials and Research* confirmed that regular chewing is associated with [lower anxiety, improved mood, and reduced occupational stress](https://pmc.ncbi.nlm.nih.gov/articles/PMC6410656/).
Your child is not chewing to be defiant. Their nervous system is using the most powerful tool it has to regulate itself.
## Why Neurodivergent Children Chew More
Sensory processing differences are a core feature of autism, significant enough to be included in the DSM-5 diagnostic criteria in 2013. A landmark study by [Tomchek and Dunn (2007)](https://pubmed.ncbi.nlm.nih.gov/17436841/) found that 95% of children with autism demonstrated some degree of sensory processing dysfunction, with the greatest differences in the underresponsive/seeks sensation category. [Leekam et al. (2007)](https://pubmed.ncbi.nlm.nih.gov/17075691/) found sensory abnormalities in over 90% of autistic individuals across all sensory domains, including oral and gustatory processing.
Using Winnie Dunn's Sensory Processing Framework, children who chew on everything typically fall into the "sensory seeker" category. They have high neurological thresholds, meaning their brains need more input to reach an optimal state of arousal. Chewing provides that input efficiently and immediately.
Children with ADHD also show significantly higher rates of sensory seeking behaviors compared to neurotypical peers. The pencil chewing, nail biting, and collar mouthing you see during homework are often the brain's attempt to maintain alertness and concentration. Research has shown that the rhythmic motion of chewing can [improve sustained attention and focus](https://pubmed.ncbi.nlm.nih.gov/22017963/).
The chewing often increases during specific situations:
- **Transitions** between activities, which are already [high-anxiety moments for neurodivergent children](/blog/transition-strategies-autism)
- **Homework or seated tasks** that require sustained concentration
- **Overstimulating environments** like crowded classrooms or loud gatherings
- **Understimulating environments** where the brain needs something to stay engaged
- **Periods of stress or anxiety**, including new environments or changes in [routine](/blog/regression-after-routine-disruption-autism-adhd)
## The Difference Between Sensory Chewing and a Safety Concern
Most sensory chewing is healthy self-regulation. But there are situations where the behavior warrants professional evaluation.
**Typical sensory chewing** looks like chewing on shirt collars, pencils, sleeves, or safe toys. It tends to increase during stress or concentration but remains manageable. The child can be redirected to appropriate alternatives, and the chewing serves a clear calming or focusing function.
**Pica is different.** Pica involves the compulsive ingestion of non-food items like paint chips, dirt, paper, or fabric. Research published in [PMC](https://pmc.ncbi.nlm.nih.gov/articles/PMC9188765/) found that pica affects 23.2% of children with autism compared to just 3.5% of the general population. If your child is swallowing non-food materials, not just mouthing or chewing them, consult your pediatrician. Pica can indicate nutritional deficiencies (iron and zinc are common), and it carries risks including gastrointestinal blockages and toxicity.
**Seek evaluation if you notice:**
- Biting fingers, hands, or lips hard enough to cause wounds or bleeding
- Chewing off and swallowing pieces of objects (choking hazard)
- Cracking or wearing down teeth from chewing hard materials
- Behavior escalating in intensity and interfering with daily functioning
- Significant social difficulties at school related to the chewing
For the majority of children, though, sensory chewing is not dangerous. It is communication. Your child's body is telling you what their nervous system needs.
## What Actually Helps: Safe Alternatives That Work
The goal is never to eliminate chewing. As occupational therapist Kim Griffin explains, "Once you recognise the symptom and its triggers, and find alternative safe self-regulation strategies that work for them, it does not take long for behaviour to change." The goal is to redirect chewing toward safe, appropriate outlets.
### Chew Tools and Chewelry
Commercial chew tools are designed specifically for this purpose. Companies like ARK Therapeutic make chew tubes, pendants, and pencil toppers in different resistance levels (soft, medium, firm) to match your child's bite strength. Chewable jewelry, often called "chewelry," offers discreet options for school-age children who want something less noticeable.
When choosing chew tools, look for:
- **FDA-compliant, food-grade or medical-grade silicone**
- **BPA-free, phthalate-free, PVC-free, and lead-free materials**
- **Breakaway clasps** on necklaces for safety
- **The right resistance level** for your child's bite (start soft and work up)
- **Regular inspection** for damage, and replace when worn
ARK Therapeutic puts it well: rather than eliminating chewing behavior, the goal is to redirect it toward "something that is designed specifically for the need to chew that is comfortable, durable, and safe."
### Food-Based Oral Input
Strategic food choices can provide the sensory input your child's brain is seeking:
- **Crunchy foods**: Raw carrots, celery, apples, pretzels, dried banana chips
- **Chewy foods**: Dried mango, beef jerky, bagels, fruit leather
- **Resistive drinking**: Thick smoothies through a straw, applesauce pouches (the sucking motion provides organizing oral input)
- **Cold foods**: Frozen fruit bars, ice cubes, frozen yogurt tubes (cold adds alerting sensory input)
- **Strong flavors**: Sour or spicy foods provide additional alerting input for children who seek intense sensory experiences
If your child is also a [selective eater](/blog/safe-foods-autism-sensory-science-food-refusal), work within their accepted foods. A child who only eats five foods can still get oral sensory input from crunchy crackers or chewy dried fruit if those fall within their comfort zone.
### Other Oral Motor Strategies
- **Blowing activities**: Bubbles, whistles, kazoos, party blowers, or blowing cotton balls across a table
- **Water bottles with bite valves**: CamelBak-style bottles provide resistive oral input while keeping your child hydrated
- **Vibration**: Electric toothbrushes provide oral sensory input during the [brushing routine](/blog/brushing-teeth-autism-adhd-sensory-strategies)
- **Sugar-free gum**: One of the simplest and most socially acceptable options for older children
## Building Chewing Into the Routine Instead of Fighting It
This is where the shift from reactive to proactive makes all the difference.
Instead of waiting for your child to start gnawing on their sleeve and then redirecting them (reactive), build oral sensory input into their daily schedule before the need becomes urgent (proactive). Occupational therapists call this a "sensory diet," a term coined by Patricia Wilbarger to describe a planned schedule of sensory activities throughout the day.
**Schedule oral input at predictable times:**
- Crunchy or chewy snack before homework or seated tasks
- Chew tool available during [car rides](/blog/road-trips-long-drives-autism-adhd) or waiting rooms
- Resistive drinking (smoothie through a straw) at breakfast
- Gum or chewy snack before [transitions](/blog/transition-strategies-autism) that you know are difficult
**Use visual supports to make it predictable.** A [visual schedule](/blog/visual-schedules-for-autism) that includes "sensory snack time" or "chew break" normalizes the behavior and gives your child a clear expectation for when oral input is coming. When children know the chew break is built into the schedule, the anxiety that drives additional chewing often decreases.
**Create a choice board for chewing alternatives.** A simple visual card showing options, chew necklace, crunchy snack, drink water, blow bubbles, empowers your child to self-select the strategy that matches what their body needs in the moment. This builds [self-advocacy skills](/blog/teaching-self-advocacy-neurodivergent-children) that serve them well beyond childhood.
**Use first-then boards for motivation.** "First math worksheet, then chew break." The visual format makes the expectation and reward clear, connecting the sensory activity to task completion without making it feel like a punishment.
## What to Tell Teachers and Caregivers
Chewing behaviors in the classroom are often misunderstood. Teachers may see a child chewing on their collar and interpret it as a behavioral problem or a lack of self-control. Reframing the conversation changes everything.
**Share the science.** Most educators are receptive when they understand that chewing is a neurological regulation strategy, not a discipline issue. The 95% statistic from Tomchek and Dunn is powerful context. So is the research showing that chewing can actually improve focus and attention.
**Propose a plan.** A chew tool in the pencil case, a crunchy snack during independent work time, and a water bottle with a bite valve at the desk cost nothing and disrupt nothing. Frame these as accommodations that improve focus, not special treatment.
**Include it in the IEP or 504.** If your child has an [IEP](/blog/iep-meeting-preparation-guide-parents) or 504 plan, sensory accommodations including access to chew tools can and should be documented. This protects your child's right to use these tools and ensures consistency across settings.
## When to Involve an Occupational Therapist
An OT can be invaluable if your child's chewing is:
- Intense enough to damage clothing, furniture, or objects regularly
- Interfering with social relationships
- Not responsive to the strategies you have tried at home
- Accompanied by other [sensory processing challenges](/blog/sensory-processing-daily-routines) that affect daily life
OTs use standardized assessments like the Sensory Profile-2 to understand your child's specific sensory needs. They determine whether your child is sensory seeking, sensory avoiding, or has oral motor weakness, each of which requires a different approach.
The American Occupational Therapy Association (AOTA) recognizes sensory integration as an [evidence-based area of practice](https://research.aota.org/ajot/article/76/Supplement_1/7610510189p1/23413/A-Systematic-Review-of-Sensory-Interventions-for), with systematic reviews confirming that sensory interventions "appear to be effective when addressing attention and self-regulation for children with autism." An OT will create an individualized sensory diet tailored to your child's specific needs, not a one-size-fits-all approach.
## Reframing the Narrative
The hardest part of sensory chewing for most parents is not the chewed-up shirts. It is the judgment. The looks from other parents. The teacher's concerned email. The internal voice wondering if you are doing something wrong.
You are not doing anything wrong. And your child is not doing anything wrong either.
Chewing is not a bad habit. It is not a phase they will grow out of if you just discipline them enough. It is a neurological need, as real as the need for [sleep](/blog/autism-and-sleep-problems-what-actually-helps) or food or movement. When you reframe chewing from "problem behavior" to "communication about what my child's nervous system needs," everything about your response shifts.
Instead of "stop chewing on that," you say "let me get you something safe to chew on." Instead of "why do you always destroy your shirts," you think "his brain needs more input right now, let me offer a crunchy snack." Instead of fighting the behavior, you work with it.
Your child's brain is not broken. It is wired to need more proprioceptive input than most. Once you provide that input in safe, structured, predictable ways, the shirt chewing, the pencil destruction, and the sleeve soaking will decrease. Not because you forced it to stop, but because you gave their nervous system what it was asking for all along.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build sensory breaks and chew time directly into your child's [visual daily routine](/blog/visual-schedules-for-autism), [track emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) to identify when oral sensory needs peak, and create choice boards that empower your child to self-select the regulation strategy their body needs. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and turn sensory chewing from a daily battle into a structured part of your child's success.
---
## Regression After Routine Disruption: Why Your Child Lost Skills and How to Rebuild
Published: 2026-04-06
URL: https://vizyplan.com/blog/regression-after-routine-disruption-autism-adhd
Category: Strategies
Author: Justin Bowman
> Nearly 63% of parents report behavioral regression when routines break down. The neuroscience behind why it happens, what it actually means, and how to bring your child back.
Your child was doing so well. They were following their morning routine independently. They were using their words at the dinner table. They were sleeping through the night. Then something changed. Maybe it was a vacation. Maybe grandma visited for two weeks and the whole schedule went sideways. Maybe you moved. Maybe they got sick for ten days and the routine just... stopped.
And now it feels like you are starting over.
The independent morning routine? Gone. The words at dinner? Replaced by pointing and whining. The sleep? Do not even ask. Skills that took months to build seem to have evaporated in a matter of days, and you are standing in your kitchen at 7:15 AM wondering if all that progress was ever real in the first place.
It was real. And here is the part that most articles skip over: your child did not lose those skills. Their brain lost the scaffolding that made those skills accessible. That distinction changes everything about how you respond.
## What Regression Actually Is (And What It Is Not)
Let us get the science straight first, because the word "regression" carries enormous weight for parents of neurodivergent children, and most of the time it is used imprecisely.
There are two fundamentally different types of regression. **Developmental regression** is the loss of previously acquired skills as part of the autism presentation itself, typically appearing between 15 and 30 months of age. This affects roughly [20 to 32% of autistic children](https://www.thetransmitter.org/spectrum/regression-marks-one-five-autism-cases-large-study-finds/) and is a distinct neurological phenomenon.
What you are probably dealing with right now is **situational skill loss**: a temporary setback triggered by stress, illness, routine disruption, or environmental change. These are different things with different causes, different trajectories, and different prognoses. Situational skill loss is [typically recoverable with support](https://www.healthline.com/health/autism/what-is-regression-in-autism) once the triggering factor is addressed.
The COVID-19 pandemic gave researchers an unintentional but massive dataset on exactly this phenomenon. When routines worldwide were disrupted overnight, [62.77% of parents reported](https://www.jaacapopen.org/article/S2949-7329(24)00029-2/fulltext) that their autistic children were regressing behaviorally. Over [51% of more than 1,000 children with autism](https://link.springer.com/article/10.1007/s40489-022-00344-4) experienced behavioral changes including increased anxiety, irritability, and hyperactivity during lockdowns.
But here is the finding that matters most: children who [maintained routines during the pandemic](https://www.frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2020.561882/full) had significantly higher adaptability skills and lower anxiety levels than those whose routines were disrupted. The variable was not the pandemic itself. It was whether the routine survived.
## The Neuroscience: Why Your Child's Brain Needs the Routine
Understanding why disruption causes regression requires understanding how your child's brain processes the world differently.
### The Predictability Problem
A growing body of research frames the autistic brain as a [prediction machine](https://pmc.ncbi.nlm.nih.gov/articles/PMC8043993/) that processes prediction errors differently than neurotypical brains. When something unexpected happens, it generates a disproportionately strong error signal. For most people, a changed schedule is a minor adjustment. For your child, it can feel like the ground shifting beneath them.
This connects directly to what researchers call **intolerance of uncertainty**. A [meta-analysis of 10 studies](https://pmc.ncbi.nlm.nih.gov/articles/PMC7539603/) found a strong correlation (r = 0.62) between intolerance of uncertainty and anxiety in autistic individuals. That means uncertainty accounts for roughly 38% of anxiety in this population. Routines are not a preference. They are a coping mechanism that compensates for a brain that finds unpredictability genuinely threatening.
When you remove the routine, you remove the coping mechanism. And the brain redirects its resources from higher-order skills like language, social engagement, and executive function toward managing the anxiety that floods in.
### The Executive Function Gap
Children with ADHD operate with a [2 to 3 year executive function delay](https://www.additudemag.com/executive-function-adhd-kids-lagging-skills/). A seven-year-old may be functioning at the executive level of a four or five-year-old. Executive function covers planning, cognitive flexibility, and self-monitoring, which are the exact skills needed to adapt when routines change.
When a routine is in place, it acts as an external executive function system. The [visual schedule](/blog/visual-schedules-for-autism) tells your child what comes next so their brain does not have to hold that information. The predictable sequence means they do not need to plan. The familiar environment means they do not need to constantly monitor for threats.
Remove all of that, and you are asking a brain with limited executive function resources to suddenly generate its own plan, adapt to new circumstances, and monitor an unfamiliar environment, all at once. The system gets overwhelmed. Skills that were accessible with scaffolding become inaccessible without it.
### The Amygdala Connection
Research shows [significantly weakened connectivity](https://www.sciencedirect.com/science/article/pii/S1750946721001884) between the prefrontal cortex and the amygdala in children with autism. This feedback loop is critical for emotional regulation. In neurotypical brains, the prefrontal cortex helps calm the amygdala after an initial stress response. In autistic brains, this calming signal is weaker.
The result is that the amygdala, the brain's threat detection center, can remain [highly activated even after repeated exposure](https://www.simplypsychology.org/autism-changes-in-routine.html) to a situation. Your child is not choosing to be inflexible. Their brain is genuinely stuck in a sustained stress response when the environment becomes unpredictable. And a brain in survival mode does not have bandwidth for the complex tasks that were previously mastered.
## What Triggers Regression
Understanding the triggers helps you anticipate and prepare, rather than scramble to respond after the fact.
### Summer Break and Extended School Breaks
This is the most common and most predictable trigger. Research shows [70 to 78% of elementary students](https://www.blnautism.com/understanding-summer-learning-regression-in-children-with-autism-how-summer-intensives-can-help/) experience a decline in math skills over summer, with many losing 2 to 3 months of reading and math progress. For neurodivergent children, the loss extends far beyond academics. Without the structure of school, children may need weeks to regain skills once routines resume.
This is why Extended School Year services exist under IDEA. The [primary purpose of ESY](https://washingtonautismalliance.org/extended-school-year-services/) is specifically to prevent significant regression of already-learned skills during school breaks. If your child's IEP team has not discussed ESY eligibility, bring it up at your [next IEP meeting](/blog/iep-meeting-preparation-guide-parents).
### Vacations and Travel
[Family travel](/blog/travel-vacation-tips-autism-adhd) eliminates nearly every familiar anchor: different beds, different mealtimes, different everything. The sensory environment is unpredictable, transition demands increase dramatically, and sleep disruption compounds everything. A week-long vacation can undo months of progress if the routine is not preserved in some form.
### Illness
When your child is sick, routines collapse. They may stay home from school, sleep at odd hours, eat differently, and lose access to their therapy schedule. The illness itself adds physical stress that taxes an already-stretched nervous system. Over [80% of autistic individuals](https://psychiatryonline.org/doi/full/10.1176/appi.focus.20230028) already experience sleep problems. Add illness-related sleep disruption and you have a perfect storm for regression.
### Family Changes
Moving homes, a parent starting a new job, a new sibling arriving, divorce, the loss of a caregiver, or a change in service providers all constitute [significant routine disruption](https://autismnj.org/article/regression/). These events combine the loss of predictability with emotional stress, making regression more severe and recovery slower.
### The Transition Itself
Up to [80% of children with autism](https://www.skillpointtherapy.com/autism-manage-transitions/) experience anxiety around transitions. Any transition, between activities, between environments, between caregivers, requires cognitive effort that depletes limited resources. When transitions multiply during a disrupted period, the cumulative demand can exceed your child's capacity.
## Autistic Burnout: When Regression Goes Deeper
Sometimes what looks like regression is actually something more pervasive. Researchers define [autistic burnout](https://pmc.ncbi.nlm.nih.gov/articles/PMC7313636/) as a syndrome resulting from chronic life stress and a mismatch between expectations and abilities without adequate supports. It is characterized by exhaustion, loss of function, and reduced tolerance to stimulus, typically lasting three or more months.
In children, burnout is frequently [mislabeled as behavioral issues](https://www.autism.org.uk/advice-and-guidance/professional-practice/autistic-burnout) or oppositional defiance. A child in burnout may show sudden school refusal, sharp academic decline, or loss of milestones like [toilet training](/blog/potty-training-autism-adhd-visual-supports) or speech.
The skill loss in burnout is typically temporary. The brain lacks energy to power higher-order functions like social scripting, complex planning, or verbal speech. But recovery timelines vary significantly. Some children bounce back in weeks with support. Others need months.
If your child's regression has persisted beyond what feels proportional to the triggering event, and if it is accompanied by pervasive exhaustion and withdrawal, talk to their care team about the possibility of burnout. The intervention for burnout is different from the intervention for situational skill loss: it requires reducing demands, not increasing structure.
## How to Respond When Regression Happens
Your instinct might be to immediately ramp up practice, drills, and intensity. Resist that instinct. A brain in stress mode does not learn. It survives.
### Step One: Restore the Routine First
Before you try to rebuild skills, rebuild the structure. Get the daily schedule back. Restore predictable mealtimes, [bedtimes](/blog/autism-and-sleep-problems-what-actually-helps), and transitions. Use the same [visual schedule](/blog/visual-schedules-for-autism) your child was using before the disruption, or create a new one if the old one does not apply.
Research consistently shows that [visual schedules are one of 28 evidence-based practices](https://asatonline.org/for-parents/learn-more-about-specific-treatments/activity-schedules/) for autism. They reduce latency to initiate activities, decrease tantrums during transitions, and enhance social skills. They transform abstract time concepts into concrete images, giving your child a roadmap that their brain does not have to generate on its own.
The routine is the scaffolding. Rebuild the scaffolding first and the skills will have something to stand on again.
### Step Two: Drop Back Without Shame
If your child was independently following a five-step morning routine and now cannot get past step two, meet them where they are. Go back to providing full support for all five steps. This is not starting over. It is providing temporary scaffolding while their nervous system recovers.
Think of it like physical therapy after an injury. You do not jump back to running. You walk first. Then you jog. Then you run. The muscles remember what to do. They just need the gradual reload.
### Step Three: Reintroduce Skills Gradually
Behavioral analysts recommend [revisiting original teaching methods](https://www.daytasticaba.com/handling-regression-in-skills-aba-strategies-for-families) and breaking skills back down into smaller components. If your child was completing their [morning routine](/blog/morning-routine-tips-adhd) independently, start by re-establishing just the first step independently and prompting the rest. Once the first step is solid again, fade prompts on the second step.
The rebuild is almost always faster than the original learning. The neural pathways are there. They are just temporarily less accessible. With consistent routine and graduated support, most children recover situational skill loss within days to weeks, not the months it took originally.
### Step Four: Track What You See
Document the regression and the recovery. Use [emotion tracking](/blog/tracking-emotions-activities-neurodivergent-children) to identify patterns: is the regression worse in the morning? After specific activities? In certain environments? Data turns overwhelming feelings into manageable observations.
This documentation also matters for your child's care team. When you can show a therapist or [IEP team](/blog/iep-meeting-preparation-guide-parents) that every summer break is followed by three weeks of regression, you have evidence for requesting ESY services or modified transition plans.
### Step Five: Protect Sleep
Over [80% of autistic individuals](https://psychiatryonline.org/doi/full/10.1176/appi.focus.20230028) experience sleep problems, and research shows that children who sleep fewer hours have [lower overall intelligence, verbal skills, adaptive functioning, and socialization skills](https://www.sciencedirect.com/science/article/abs/pii/S0891422212000686). Sleep is the foundation that everything else rests on.
During and after a disruption, prioritize the [bedtime routine](/blog/bedtime-routine-autism-adhd) above all other routines. If only one thing can stay consistent, make it sleep. A well-rested brain recovers faster, regulates better, and relearns more efficiently.
## Preventing Regression Before It Happens
You cannot avoid all disruption. Life happens. But you can reduce the impact.
### Maintain Anchor Routines During Disruption
Even during vacations, moves, or illness, keep two or three anchor routines intact. The [morning routine](/blog/morning-routine-tips-adhd) and bedtime routine are the most important. These bookend routines tell your child's brain that the world is still predictable, even when the middle of the day is different.
### Prepare Your Child Visually
Before any anticipated disruption, talk about what will change and what will stay the same. Use social stories or [visual supports](/blog/visual-schedules-for-autism) that show the upcoming changes alongside the familiar elements that will remain. Research on intolerance of uncertainty confirms that [predictability serves as a crucial coping mechanism](https://www.frontiersin.org/journals/psychology/articles/10.3389/fpsyg.2021.731753/full). Give your child as much predictability as possible, even during unpredictable times.
### Maintain Therapy Continuity When Possible
The Marcus Autism Center recommends [maintaining therapy services](https://www.marcus.org/autism-resources/autism-tips-and-resources/maintaining-skills-over-the-summer) during breaks whenever possible. If in-person sessions are not available, ask providers about telehealth options or home programs that maintain the therapeutic routine.
If your child's [ABA hours have been cut](/blog/aba-therapy-cuts-what-to-do-at-home), integrating therapeutic strategies into daily routines at home becomes even more important. Consistency across environments, even at a lower intensity, protects skills better than intermittent high-intensity sessions.
### Build Flexibility Gradually
This sounds counterintuitive, but the most disruption-resistant children are the ones who have been gently exposed to small, safe variations over time. Change one element of the routine occasionally. Eat breakfast in a different spot. Take a different route to school. Introduce small, manageable novelty within a predictable framework so that your child's brain learns that change does not always mean threat.
## The Emotional Toll on You
We need to talk about this, because it is real and it matters.
Watching your child lose skills is one of the hardest experiences in parenting. Research confirms that parents of autistic children report [higher levels of parenting stress than parents of children with any other disability](https://www.frontiersin.org/journals/psychology/articles/10.3389/fpsyg.2019.00464/full). And that stress is not just emotional. Chronic parenting stress leads to [elevated cortisol levels](https://lighthouseautismcenter.com/blog/how-to-reduce-stress-in-parents-with-autistic-children/) that increase vulnerability to cardiovascular and immune system issues.
Regression triggers something primal in parents. It activates the fear that progress is not permanent. That the good days were a fluke. That nothing you are doing matters. Those feelings are understandable. They are also wrong.
Research on the [spillover hypothesis](https://www.nature.com/articles/s41380-021-01433-2) shows that parental stress and anxiety can worsen children's behavioral problems, creating a negative feedback loop. Your stress becomes their stress, which becomes more regression, which becomes more of your stress. Breaking this cycle is not selfish. It is strategic.
**Reframe the narrative.** Your child did not "lose everything." Their brain is temporarily overwhelmed. The skills are encoded. The neural pathways exist. What disappeared is the external support system that made those pathways accessible.
**Use problem-focused coping.** Research shows that [active coping, planning, and seeking support](https://www.frontiersin.org/journals/psychology/articles/10.3389/fpsyg.2019.00464/full) significantly reduce maternal stress and buffer against the impact of high-symptom periods. Do not sit with the fear. Make a plan. Rebuild the schedule. Contact the therapist. Take one concrete step.
**Ask for help.** This is not a failure. This is parenting a child with a neurological difference that requires more structure, more consistency, and more support than most people understand. You were not designed to do this alone, and you do not have to.
## The Skills Are Still There
Here is what I want you to hold onto when you are watching your child struggle with something they could do perfectly two weeks ago.
A study of [1,892 autistic youth](https://pmc.ncbi.nlm.nih.gov/articles/PMC10843390/) found that 98% displayed at least one insistence on sameness behavior. This is not a quirk. It is a fundamental feature of how the autistic brain manages a world that feels inherently unpredictable. Routine is the bridge between what your child's brain can do and what they can actually access in the moment.
When you rebuild that bridge, the skills that seemed lost will reappear. Maybe not all at once. Maybe not in the same order they were learned. But the foundation is there. Your child's brain has not forgotten how to brush their teeth, follow a schedule, or use their words. It has temporarily lost the environmental support that made those things possible.
Your job is not to reteach everything from scratch. Your job is to rebuild the scaffolding, be patient while their nervous system recalibrates, and trust the process. You have done this before. You can do it again.
And this time, you know something you did not know the first time: it works.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build and maintain the visual routines that protect your child's skills through disruption, [track emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) before and after transitions, and rebuild structure quickly when life throws your schedule off course. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the scaffolding their brain needs to keep moving forward.
---
## Autism and the Holidays: Surviving Family Gatherings
Published: 2026-04-05
URL: https://vizyplan.com/blog/autism-holidays-family-gatherings-overstimulation
Category: Strategies
Author: Justin Bowman
> Almost 80% of autism parents say stigma makes holidays harder. Learn how to navigate overstimulation, relatives who do not understand, and the expectations that follow your family to every gathering.
The group text arrives three weeks before the holiday. Your sister is hosting this year. Twenty-two people. A potluck. The cousins will be running around. There will be music. Someone will bring a dog. Dinner is at four but people start arriving at noon. It will be loud and chaotic and wonderful, everyone says.
You read the text and your stomach tightens. Not because you do not love your family. Because you are already calculating. How many hours can your child last? Where is the nearest quiet room? Will there be food they will eat? What happens when Aunt Linda tries to hug them and they pull away? What happens when your father-in-law asks, again, if they have "grown out of it yet"? What happens when your child melts down in front of twenty-two people and you feel every eye in the room land on you?
Almost 80% of parents of autistic children report that stigma has been extremely, very, or somewhat difficult in their lives, according to research from the Kennedy Krieger Institute. That statistic does not live in a vacuum. It lives in the dining room at Thanksgiving, the living room on Christmas morning, the backyard at the Fourth of July barbecue. It lives in every family gathering where your child's neurology meets the expectations of people who love you but do not understand your daily reality.
This article is not about decorating tips or gift-giving strategies. Those are covered in our guide to [preparing your neurodivergent child for holidays and special events](/blog/holiday-special-events-autism-adhd). This is about the harder stuff: the overstimulation your child cannot control, the relatives who think they know better, the guilt you carry when you leave early, and the exhaustion that follows you home.
## Why Family Gatherings Are a Perfect Storm
Your child's daily environment has been carefully engineered. The lighting, the noise level, the schedule, the food, the people. You have spent months or years figuring out what works and building a world that accommodates their nervous system. A family gathering dismantles all of it in a single afternoon.
### Sensory Environments You Cannot Control
At home, you control the volume. At Grandma's house, the TV is blaring football while six conversations happen simultaneously, children shriek in the other room, someone is blending something in the kitchen, and the house smells like a combination of every dish twenty-two people decided to bring.
Research confirms what you already know: lights, unusual noises, crowds, smells, unfamiliar places, and unfamiliar people can all bewilder and overwhelm children with autism. A study published in PMC found that parents consistently link their children's most challenging behaviors to [sensory overload](/blog/sensory-processing-daily-routines), with meltdowns representing intense, involuntary responses to overwhelming situations rather than willful displays of bad behavior.
The key word is involuntary. Your child is not choosing to fall apart. Their nervous system is responding to input that exceeds its processing capacity. It is a neurological event, not a behavioral choice. And it is happening in front of an audience that often cannot tell the difference.
### Social Demands That Exceed Capacity
Family gatherings come with social expectations that are unspoken but enforced. Make eye contact with relatives. Accept hugs and kisses from people you see twice a year. Answer questions about school. Say thank you. Sit at the table. Use a fork. Smile for the camera. Participate in group prayer. Open gifts with appropriate enthusiasm.
Each of these demands requires social processing, sensory tolerance, and emotional regulation. For an autistic child, each one costs energy. Stacked together across four or five hours, they create an impossible debt that the child's nervous system will eventually collect, usually in the form of a meltdown, shutdown, or flight response.
### Routine Disruption Multiplies Everything
Holiday gatherings do not just change one thing. They change everything. Wake time is different. The drive to the gathering is different. The food is different. The people are different. The environment is different. The schedule is unpredictable. There is no visual routine. There are no familiar anchors. Every element of the day that your child normally relies on for stability has been removed simultaneously.
Research on [transition strategies for autistic children](/blog/transition-strategies-autism) consistently shows that routine disruption is one of the strongest predictors of behavioral escalation. A holiday gathering is not one transition. It is a series of transitions across an entire day, with no recovery time between them.
## The Relatives Problem
Here is the part of holidays that no sensory kit can fix. The people who love you the most can also hurt your family the most, not through malice but through ignorance, outdated beliefs, and the gap between what they think autism looks like and what it actually looks like in your child.
### The Comments
You know them by heart because you hear versions of them at every gathering:
- "He seems fine to me." (Because you have spent three hours managing the environment to prevent a meltdown.)
- "Have you tried being more firm?" (Because your parenting must be the problem.)
- "She just needs more socialization." (Because clearly forcing a child into overwhelming situations will fix a neurological condition.)
- "We didn't have all this autism stuff when I was growing up." (Because undiagnosed children who suffered in silence apparently did not count.)
- "He'll grow out of it." (Because autism is a phase, like a preference for dinosaur nuggets.)
- "You are too easy on her." (Because accommodating a disability is apparently the same as spoiling.)
Research from the Kennedy Krieger Institute's Interactive Autism Network found that families consistently report that a lack of understanding by people outside of close family creates significant barriers to inclusion. The tension typically stems from generational differences, misunderstanding, or discomfort with the diagnosis itself.
These comments land differently at a holiday gathering than they do in a text message. In a crowded room full of family, every comment has an audience. Your response becomes a performance. And your child, who may be processing language on a delay, may be absorbing every word even when adults assume they are not listening.
### The Unsolicited Advice
Extended family members often believe their experience with children, or their memory of you as a child, qualifies them to advise you on autism parenting. Research shows that while often well-intended, casual suggestions can invalidate the effort and research parents have already invested. Autism parenting requires advocacy, appointments, insurance navigation, therapy coordination, and daily implementation of evidence-based strategies. When someone offers a simple fix at the dinner table, it dismisses the complexity of what you manage every day.
The advice is hardest to absorb when it comes from people whose opinion you once valued. Your mother. Your favorite uncle. The sibling you always looked up to. Their words carry emotional weight that a stranger's judgment does not.
### The Physical Expectations
People expect hugs, conversations, eye contact, and smiles for the camera. These expectations can pressure autistic children into masking or dysregulating. When Uncle Dave insists on a hug and your child recoils, the room gets uncomfortable. When your child refuses to look at Grandma while she talks to them, someone mutters about manners. When the group photo requires your child to stand still, smile, and tolerate being touched by several people simultaneously, the resulting refusal or meltdown becomes "the scene" everyone remembers.
Your child's body autonomy is not optional just because it is a holiday.

## Before the Gathering: Preparation That Actually Works
The difference between a manageable gathering and a disastrous one is almost always preparation. Not hope. Not "maybe it will be fine this time." Actual, specific, communicated preparation.
### Talk to the Host
This conversation is not optional. Before the gathering, tell whoever is hosting:
- Your child will need access to a quiet room throughout the event
- You may need to arrive late, leave early, or step out during the gathering
- Here are specific sensory triggers to be aware of (loud music, strong perfumes, barking dogs)
- Please do not insist on physical affection from your child
- If you see your child stimming, please do not comment on it or try to stop it
This is not asking for special treatment. This is communicating accessibility needs. If a family member used a wheelchair, you would confirm the venue was accessible before arriving. Sensory and social accommodations deserve the same respect.
### Build a Visual Preview
Show your child what to expect using pictures and sequences. Whose house are we going to? Here is a photo. Who will be there? Here are their faces. What will happen? We will arrive, say hello, eat food, and then leave. How long will we stay? This many hours, and here is your timer.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build a [visual schedule](/blog/visual-schedules-for-autism) for the gathering day that includes everything from the morning routine through the drive, the event itself, and the recovery time afterward. When your child can see the shape of the day, including when it ends, the unpredictability decreases and their sense of control increases.
### Create a [Social Story](/blog/social-stories-autism-guide)
Build a simple story that walks through the gathering:
"Today we are going to Aunt Sarah's house. There will be many people there. It might be loud. If it is too loud, I can go to the quiet room. I do not have to hug anyone. I can wave hello instead. We will eat food. I can bring my own food if I want to. We will stay for two hours. Then we will go home."
Reviewing this story multiple times before the event embeds the expectations and, critically, the escape options into your child's mental framework.
### Pack the Survival Kit
This should be a bag that goes to every gathering:
- Noise-cancelling headphones or earplugs
- Fidget tools or a comfort item
- Snacks your child will actually eat (enough for the whole event)
- A tablet or device loaded with calming content
- A change of [comfortable clothes](/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children) if the "nice outfit" becomes intolerable
- A visual timer
- Any medication they take on schedule
Do not rely on the host to have what your child needs. Bring your own environment with you.
### Set Your Exit Plan
Before you walk in the door, know how you are leaving. Park where you will not be blocked in. Identify the quickest route out that does not go through the main gathering space. Decide what your code word is with your partner: when one of you says "I think we should head out," the other agrees without negotiation.
Tell your child before you arrive: "If it gets too hard, we will leave. You can tell me or squeeze my hand and we will go." Research confirms that knowing an escape exists often reduces the need to use it. The safety net makes the tightrope walkable.
## During the Gathering: Real-Time Management
### Arrive Late and Leave Early
You do not owe anyone your child's wellbeing in exchange for attendance. Arriving after the initial chaos of greetings settles and leaving before your child hits their limit is not rude. It is strategic. A successful ninety minutes is worth more than a catastrophic four hours.
### Station Yourselves Near the Exit
Choose a spot in the gathering space that is near the door, away from the loudest area, and close to the quiet room. Do not sit in the center of the action. Do not accept the seat that puts your child's back to a hallway where people will walk behind them unexpectedly. Position matters.
### Rotate Breaks Before They Are Needed
Do not wait for signs of [overwhelm](/blog/recognizing-triggers-meltdowns-neurodivergent-children). Build breaks into the gathering proactively. Every thirty to forty-five minutes, take your child to the quiet space for five to ten minutes. Go outside. Walk to the car. Sit in a bathroom. These micro-recoveries prevent the buildup that leads to meltdown.
Research on sensory regulation shows that proactive sensory breaks are significantly more effective than reactive ones. By the time your child is covering their ears and crying, their nervous system has already passed the point of easy recovery. Meltdown recovery can take twenty minutes or more after removing the stressor. Prevention costs five minutes.
### Let Them Stim
Your child may [stim](/blog/stimming-autism-when-to-support-when-concerned) more at a gathering than they do at home. That is their nervous system doing exactly what it needs to do. The rocking, the hand flapping, the humming, the pacing. These are regulation tools, not problems to solve. If a relative comments, a simple "that helps them stay calm" is sufficient. You do not owe a longer explanation at the dinner table.
### Monitor Food Carefully
Holiday meals are sensory minefields. Unfamiliar dishes, strong smells, crowded tables, the expectation to eat what is served. If your child has food selectivity (which research shows affects up to 70% of autistic children), bring their [safe foods](/blog/safe-foods-autism-sensory-science-food-refusal) without apology. A child who eats their own familiar food at the gathering is a child who stays regulated. A child who is hungry because nothing on the table was edible is a child approaching meltdown.
If someone comments on what your child is or is not eating, "Their doctor is aware of their dietary needs" ends the conversation.
### When the Meltdown Happens Anyway
You prepared. You brought the kit. You took breaks. And your child still melted down. Because sometimes, even with every strategy in place, the load exceeds the capacity. Here is what to do:
**Get them out of the room.** Not as punishment. As rescue. Move to the quiet space, outside, or to the car. Remove the sensory input that is overwhelming them.
**Do not try to talk them through it.** During a meltdown, the brain's language processing center is offline. Words add stimulation. Be quiet. Be present. Offer deep pressure if they find that calming. Wait.
**Ignore the audience.** This is the hardest part. You can feel your family watching. Some are worried. Some are judging. Some are whispering. None of that matters right now. Your child matters right now. Deal with the relatives later.
**Do not apologize to the room.** Your child had a neurological event. You would not apologize if they had an asthma attack. You would not apologize if they had a seizure. A meltdown is not a behavior problem. It is a medical reality. Hold your head up and take care of your child.
## After the Gathering: Recovery Is Not Optional
### Plan a Recovery Day
The day after a major gathering should have zero demands. No errands. No playdates. No "since we are already out" additions to the schedule. Return to normal [routines](/blog/visual-schedules-for-autism) as quickly as possible. Familiar structure is the antidote to the disruption your child just experienced.
### Process What Happened
After your child has recovered (not during the drive home, not that evening, but the next day or later), talk through the experience. What was hard? What was okay? Was there a part they liked? What would help next time? This reflection builds self-awareness and gives you data for future gatherings.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you [track your child's emotional states](/blog/tracking-emotions-activities-neurodivergent-children) before and after events, creating a record over time of how specific environments affect them. When you can show a therapist or your partner that every family gathering is followed by two days of emotional dysregulation, you have evidence for setting firmer boundaries.
### Debrief With Your Partner
Talk honestly about what happened. What worked? What did not? Which relatives were supportive and which ones made things harder? What boundaries need to be set before the next gathering? This conversation is easier to have on a calm Tuesday evening than in the car on the way home while both of you are exhausted and your child is still dysregulated in the backseat.
## Setting Boundaries With Family
This is the section most holiday articles avoid because it is uncomfortable. But it is the section that matters most for your long-term wellbeing and your child's.
### You Are Allowed to Say No
You do not have to attend every gathering. You do not have to stay the entire time. You do not have to bring your child if the environment is genuinely harmful to them. Saying no to a gathering is not rejecting your family. It is protecting your child. Those are different things, even when relatives act as though they are the same.
### You Are Allowed to Set Conditions
"We will come, but we need a quiet room available." "We will come, but please do not insist on hugging the kids." "We will come for two hours. Please do not pressure us to stay longer." "We will come, but if Uncle Mark makes comments about our parenting again, we will leave."
These are not demands. They are boundaries. And boundaries are not rude. They are necessary.
### Have the Hard Conversation
If there is a specific family member whose behavior consistently makes gatherings worse for your child, talk to them directly. Not at the gathering. Before it. In private.
"I need to talk to you about something important. When you tell my child to stop flapping his hands, it causes him significant distress. His movement is how his body stays regulated, and asking him to stop is like asking you to hold your breath. I need you to stop commenting on his behaviors at family events. If you have questions about autism, I am happy to answer them privately, but not in front of him and not at a holiday dinner."
This conversation will be uncomfortable. It may cause temporary friction. But your child's nervous system is more important than a relative's comfort with being corrected. For more on navigating [extended family who do not understand](/blog/extended-family-doesnt-understand-neurodivergent-child), our dedicated guide walks through these conversations in detail.
### Redefine What Holidays Mean for Your Family
The holiday you imagined before you had a neurodivergent child and the holiday your family actually needs may be very different. And that is not a loss. It is an evolution.
Maybe your family's best holiday is a quiet morning at home with a predictable routine, a special meal with just the four of you, and a video call with extended family instead of an in-person gathering. Maybe it is a shorter visit with a smaller group. Maybe it is hosting on your terms, in your space, where you control the environment.
A holiday that works for your family is a successful holiday. Period. It does not have to look like anyone else's.
## Your Child Deserves to Be Comfortable in Their Own Family
Here is what gets lost in all the planning, the survival kits, the exit strategies, and the boundary conversations: your child should not have to earn the right to be comfortable around the people who are supposed to love them unconditionally.
Your child should be able to attend a family gathering and be accepted exactly as they are. They should be able to stim without being stared at. They should be able to eat their safe food without commentary. They should be able to skip the hug and still be welcomed. They should be able to leave the room without it being "a thing." They should be able to exist in their family without performing neurotypicality for an audience.
That world does not exist yet for most families. But every boundary you set, every conversation you have, every time you advocate for your child's needs in a room full of people who do not understand, you are building it. One gathering at a time.
Your child will not remember the perfect holiday dinner. They will remember the parent who stood between them and the noise, who packed their favorite snacks, who said "we can leave whenever you need to," and who meant it.
Be that parent. Even when it is hard. Especially when it is hard.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build visual schedules for holiday gatherings, create social stories that prepare your child for what to expect, and track emotional patterns before and after events so you can make informed decisions about future gatherings. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring structure to the chaos so your family can actually enjoy being together.
---
## Glass Children: The Forgotten Siblings in Autism Families
Published: 2026-04-04
URL: https://vizyplan.com/blog/glass-children-siblings-autistic-kids-forgotten
Category: Strategies
Author: Justin Bowman
> A meta-analysis of 52 studies found siblings of disabled children face elevated anxiety and depression. Learn how to see the child you might be looking through.
Your neurotypical child has not complained in a while. They are doing fine in school. They get themselves dressed in the morning. They do not need to be reminded five times to brush their teeth. They eat what you put in front of them without a sensory crisis. They do not have a meltdown when plans change. So you assume they are okay.
And maybe they are. But maybe they stopped telling you when they are not, because they learned a long time ago that there is always something more urgent happening with their sibling. Maybe they have gotten so good at being easy that you forgot they still need you to look at them, really look at them, and ask how they are doing.
Researchers have a name for these children. They call them glass children, because their parents look right through them. Not out of cruelty. Not out of neglect. Out of sheer survival. When one child in the family requires intensive daily support, the child who does not starts to disappear. And by the time anyone notices, the damage may already be shaping who they are becoming.
## What the Research Actually Says
This is not parental guilt dressed up as science. The data is clear and it should get your attention.
A 2012 meta-analysis examining 52 studies on the psychological functioning of siblings of children with chronic illness or disability found that these siblings face measurably negative mental health effects. The most significant finding was that siblings are especially vulnerable to internalizing problems, meaning they suffer quietly. They develop anxiety. They develop depression. And they do not ask for help, because asking for help feels like adding to a family that is already stretched past its limits.
Research published by The Transmitter found that siblings of autistic children fare worse socially and emotionally than siblings of children with intellectual disability or other forms of developmental delay. They are more likely to be withdrawn. They are more likely to have poor social skills. The effect is not just about having a sibling with a disability. There is something specific about the autism experience, the unpredictability of meltdowns, the rigidity around routines, the intensity of sensory needs, that creates unique pressure on the siblings who live alongside it.
A systematic review in the Journal of Community and Applied Social Psychology examined the lived experiences of glass children and found that many reported feeling neglected by their parents, experiencing tumultuous sibling relationships, and having their life trajectories profoundly altered, including their mental health, career choices, and sense of identity. The researchers concluded that many of the negative outcomes were not the direct result of their siblings' conditions, but rather the consequences of insufficient understanding and support.
That distinction matters. The problem is not that your neurodivergent child exists. The problem is that nobody taught the family how to hold space for everyone.
## What Glass Children Actually Experience
The term "glass child" was popularized by Alicia Maples in her 2010 TEDx talk. She described it as the experience of being the sibling who appears fine, who is functioning, who is not the one in crisis, and who therefore becomes invisible to the very people whose attention they need most.
Here is what that looks like from the inside of the child's experience.
### They Learn to Shrink
Glass children learn very early that their needs come second. Not because their parents say so, but because they observe it every single day. The morning routine revolves around getting their sibling through [transitions](/blog/transition-strategies-autism) without a meltdown. Dinnertime is structured around their sibling's safe foods. Weekends are organized around therapy appointments. Vacations are planned (or cancelled) based on what their sibling can tolerate.
None of this is wrong. All of it is necessary. But the neurotypical child absorbs a message that nobody intended to send: your needs are less important because they are less urgent. Over time, they stop expressing needs at all. They become the easy child, the low-maintenance child, the child who never asks for anything, and adults praise them for it, which reinforces the pattern.
### They Carry Emotions They Cannot Name
Your neurotypical child loves their sibling. They also resent their sibling. They feel protective and frustrated. Proud and embarrassed. Worried about the future and angry about the present. These emotions exist simultaneously, and for a child who has been told (explicitly or implicitly) that their sibling "cannot help it," there is nowhere for the negative feelings to go.
Guilt becomes the default emotion. They feel guilty for being angry. Guilty for wishing things were different. Guilty for wanting their parents' attention. Guilty for being the one who does not need help. And that guilt, unprocessed and unnamed, becomes the soil where [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) and depression take root.
### They Become Parentified
Parentification happens when a child takes on adult responsibilities within the family. For siblings of autistic children, this can look like:
- Monitoring their sibling during [meltdowns](/blog/recognizing-triggers-meltdowns-neurodivergent-children) or aggressive episodes
- Translating their sibling's needs to other adults
- Giving up activities, friendships, or opportunities because someone needs to stay with their sibling
- Becoming their sibling's social bridge, explaining their behavior to peers or defending them from bullying
- Managing their own emotions to avoid adding stress to already-stressed parents
- Taking on household responsibilities that exceed their developmental stage
Research on parentification in families with disability found that it predicts emotional distress, substance use, and conduct problems over time. But the research also found something important: when social support exists and the child perceives benefits from their caregiving role, distress levels decrease significantly. Parentification is not inherently destructive. It becomes destructive when it is unacknowledged, unsupported, and unlimited.
### They Worry About the Future
This one surprises many parents. Neurotypical siblings, even young ones, think about what happens when their parents cannot take care of their sibling anymore. They worry about whether they will be expected to become the primary caregiver. They worry about how their sibling's needs will shape their own adult lives, where they can live, what jobs they can take, whether they can have their own families.
These worries are not paranoid. They are realistic. And children who carry them alone, without any adult acknowledging that the future is a legitimate concern, carry a weight that no child should shoulder in silence.

## The Signs You Are Missing
Glass children are expert hiders. They have been practicing invisibility their entire lives. But there are signals, if you know where to look.
### Perfectionism
A child who never makes mistakes is not thriving. They are performing. If your neurotypical child holds themselves to impossibly high standards, ask yourself whether they learned that being perfect is the only way to earn attention that is not crisis-driven.
### Excessive Independence
There is a difference between a child who is developing healthy independence and a child who stopped asking for help because they learned help was not available. If your eight-year-old manages their own [morning routine](/blog/morning-routine-tips-adhd), homework, and emotional regulation without any adult involvement, that is not maturity. That is a child who has given up on being parented.
### Social Withdrawal
Some glass children pull away from friendships because they are embarrassed to invite friends over. They do not want to explain their sibling's behavior. They do not want their friends to see a meltdown. They do not want to be different. Research confirms this pattern: siblings of autistic children are more likely to have poor social skills and be withdrawn, not because of inherent deficits but because of learned avoidance.
### Physical Symptoms
Headaches. Stomach aches. Trouble sleeping. Fatigue. Children who cannot express emotional distress often express it through their bodies. If your neurotypical child has recurring physical complaints with no medical explanation, consider whether their body is carrying what their words cannot.
### Anger That Seems Disproportionate
When the easy child finally explodes, it often seems to come from nowhere. But it has been building for months or years. A small frustration becomes the container for every swallowed feeling, every cancelled plan, every time they sat quietly while their sibling's needs consumed the room. The explosion is not about the trigger. It is about everything the trigger represents.
### Overachievement as Identity
Some glass children pour themselves into academics, sports, or other achievements because it is the only reliable way to get their parents' attention. If the only time your child feels seen is when they bring home an A or win a game, they are building their entire identity on performance. That identity is fragile, and it will eventually crack.
## What Your Neurotypical Child Needs From You
You cannot create more hours in the day. You cannot split yourself into two parents. You cannot make your neurodivergent child's needs smaller. But you can do specific, research-backed things that make a measurable difference for your other child.
### Scheduled, Protected One-on-One Time
This is the single most important intervention. Not "we will do something together when we have time." Scheduled. On the calendar. Predictable. And when something comes up with your other child, you protect this time anyway. Even if it means asking someone else to step in.
Research on [sibling relationships in neurodivergent families](/blog/sibling-relationships-neurodivergent-families) consistently identifies dedicated one-on-one time as the strongest predictor of positive sibling outcomes. But the key word is dedicated. Time that can be cancelled at any moment is not dedicated. It is conditional, and your child knows the difference.
Let them choose the activity. Let them have your undivided attention. Put your phone away. Do not talk about their sibling unless they bring it up. For thirty minutes, let them be the only child in the family.
### Permission to Feel Everything
Tell your child explicitly: "You are allowed to be angry. You are allowed to be frustrated. You are allowed to wish things were different. None of those feelings make you a bad sibling. They make you a human being who is dealing with something hard."
Children need to hear this more than once. They need to hear it repeatedly, because the internal guilt is loud and persistent. Create regular check-ins where you ask open-ended questions: "What has been hard this week?" not "Are you okay?" because "Are you okay?" always gets a yes.
### Age-Appropriate Honesty
Your neurotypical child lives in this family. They see everything. They hear the phone calls with insurance companies. They notice when you have been crying. They watch their sibling struggle. Pretending everything is fine insults their intelligence and tells them their observations are not valid.
Instead, give them truthful information at their developmental level. A five-year-old can understand: "Your sister's brain works differently, and that means she needs extra help with some things. That does not mean you need less. It means our family works harder to make sure everyone gets what they need."
A twelve-year-old can handle more: "I know you have noticed that your brother requires a lot of our energy. That is real, and I am sorry that sometimes it means you get less of us. We are working on that. I want you to tell me when you need more."
### Their Own Support System
You are not the only adult who can support your neurotypical child. In fact, having support outside the family is often more effective because the child does not have to worry about burdening someone who is already stressed.
**Sibshops** are peer support groups specifically designed for siblings of children with special needs. A randomized controlled trial by Jones and colleagues, published in the journal Autism in 2020, found that siblings who participated in support groups showed significant improvements in the quality of their sibling relationship compared to a control group. A larger systematic review found that 70% of sibling intervention studies reported improvements in at least one outcome, with the strongest evidence for gains in self-esteem, social wellbeing, and knowledge about their sibling's condition.
Look for Sibshops or similar programs in your area. If none exist locally, online peer support groups for siblings are increasingly available. Your child does not have to be in crisis to benefit. Connecting with other children who understand their specific experience, without having to explain, is profoundly normalizing.
Consider individual therapy if your child shows signs of anxiety, depression, or chronic stress. A therapist who understands family dynamics around disability can help your child develop language for their emotions, coping strategies for their daily reality, and a sense of identity that is not defined by their role in the family.
### A Role That Is Not Caretaker
Your neurotypical child can help with their sibling. That is reasonable. But help should be age-appropriate, time-limited, voluntary, and acknowledged. The problem is not the helping. The problem is when helping becomes the child's primary function in the family.
If your ten-year-old watches their sibling while you cook dinner, that is a reasonable family contribution. If your ten-year-old is responsible for managing their sibling's [emotional regulation](/blog/emotional-regulation-visual-supports) during meltdowns, that is parentification. If your teenager occasionally stays home to help with their sibling, that is being part of a family. If your teenager has stopped making plans with friends because they assume they will be needed, that is their identity being consumed by a caretaking role.
Draw the line clearly. Tell your child: "Helping is part of being in a family. But it is not your job. You are a kid. Being a kid is your job."
### Celebrations That Are Theirs
When your neurodivergent child reaches a milestone, the family celebrates. And they should. But what milestones are you celebrating for your neurotypical child? If the only achievements that get airtime in your family are the ones that required extraordinary effort to reach, your neurotypical child learns that ordinary accomplishments do not matter.
Celebrate the science project. Celebrate the friendship. Celebrate the soccer goal. Celebrate the kindness they showed someone at school. Celebrate them on their terms, for their things, with the same enthusiasm you bring to their sibling's victories.
## When Your Neurotypical Child Needs Professional Help
Some glass children need more than attentive parenting. Watch for these signs:
- **Persistent sadness or withdrawal** lasting more than two weeks
- **Anxiety symptoms**: excessive worry, physical complaints, sleep disturbance, avoidance of school or social activities
- **Anger or aggression** that is new or escalating
- **Academic decline** in a child who was previously performing well
- **Self-harm or talk of self-harm**, no matter how casual it seems
- **Loss of interest** in activities they used to enjoy
- **Changes in eating or sleeping** patterns
- **Statements of hopelessness**: "Nobody cares," "It does not matter," "Things will never change"
If you see these signs, schedule an appointment with a child therapist. Do not wait for it to get worse. Do not assume it is a phase. Your neurotypical child has been minimizing their pain for a long time. By the time it becomes visible to you, it has been building for longer than you realize.
For guidance on finding the right provider, our guide on [finding a therapist for your neurodivergent child](/blog/finding-right-therapist-neurodivergent-child) includes strategies for evaluating fit and navigating waitlists that apply to any child, not just the one with the diagnosis.
## The Long Game: What Glass Children Become
The research on adult outcomes for siblings of autistic individuals tells a complicated but ultimately hopeful story.
Approximately 75% of adult siblings report that growing up with an autistic brother or sister positively influenced their career choice. They become therapists, teachers, social workers, advocates, nurses, special education professionals. They carry their childhood experience into work that changes other people's lives. The empathy, patience, and flexibility they developed under pressure become professional strengths that their peers cannot match.
But this positive outcome is not guaranteed. It depends on what happened during childhood. Siblings who received adequate support, whose parents acknowledged their experience, who had space to express their full range of emotions, and who were not consumed by a caretaking identity tend to channel their experience into purpose. Siblings who were unseen, unsupported, and overburdened tend to carry their childhood patterns into adulthood in less healthy ways: chronic people-pleasing, difficulty setting boundaries, anxiety in relationships, and a persistent feeling that their own needs are less important than everyone else's.
The difference is not the experience itself. It is whether someone saw them in it.
## Building a Family Where Everyone Is Visible
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was designed for the whole family. Building [visual routines](/blog/visual-schedules-for-autism) for your neurodivergent child creates structure that benefits everyone, including the sibling who has been absorbing the chaos without complaint. When morning routines are visual and predictable, the neurotypical child is not stuck waiting while every transition is negotiated. When [emotional check-ins](/blog/tracking-emotions-activities-neurodivergent-children) are part of the daily routine for one child, adding them for every child normalizes the practice and gives the glass child permission to say how they actually feel.
Create routines that include both children. Give the neurotypical sibling their own visual schedule, their own tracked emotions, their own space in the system. The message is: this family sees all of its members. Everyone's day matters. Everyone's feelings count.
## You Are Not Failing. But You Might Be Missing Something.
If you recognized your family in this article, that recognition is not an indictment. It is information. And it is information you can act on starting today.
Your neurotypical child does not need a perfect parent. They do not need equal time, because equal time is not possible when one child requires more. What they need is to know that you see them. That you think about them even when you are not dealing with a crisis. That their feelings matter even when those feelings are inconvenient. That being easy does not mean being invisible.
Tonight, after the routines are done and the house is quiet, go sit with your other child. Not to fix anything. Not to have a big conversation. Just to be there, fully present, with nothing more urgent pulling you away. Look at them. Really look at them.
They have been waiting for you to do that for a very long time.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build visual routines for every child in the family, track emotional patterns so no one falls through the cracks, and create a daily structure where every member of your household feels seen. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and build a family system that holds space for everyone.
---
## Stimming in Autism: When to Support It and When to Be Concerned
Published: 2026-04-03
URL: https://vizyplan.com/blog/stimming-autism-when-to-support-when-concerned
Category: Strategies
Author: Justin Bowman
> Research shows 88% of autistic children stim regularly. Learn which stims to support, which ones signal concern, and practical strategies for keeping your child safe and regulated.
Your child is flapping their hands again. Maybe they are rocking back and forth while watching their favorite show. Maybe they hum the same three notes on repeat during dinner. Maybe they spin in circles at the park while every other child plays on the swings.
You have watched this happen a hundred times. And every time, the same questions surface: Is this okay? Should I stop it? Is this helping them or hurting them? When do I step in, and when do I step back?
These are not simple questions. And the answers you find online often swing between two extremes. One side says all stimming is beautiful and should never be touched. The other side treats every repetitive behavior as a problem to eliminate. Neither extreme serves your child.
The truth, backed by a growing body of research, is more nuanced. Most stimming is not just okay. It is essential. But some stimming crosses into territory that genuinely warrants concern. Knowing the difference is one of the most important skills you can develop as a parent of a neurodivergent child.
## What Stimming Actually Is
Stimming is short for self-stimulatory behavior. It refers to repetitive movements, sounds, or actions that serve a neurological purpose. Everyone stims to some degree. Tapping your foot during a meeting, twirling your hair while reading, clicking a pen while thinking. These are all stims. The difference with autistic children is that their stims tend to be more visible, more frequent, and more essential to their daily functioning.
Research published in Frontiers in Integrative Neuroscience in 2024 found that stimming helps regulate brain rhythms and improve sensory processing and attention. The movements are not random. They are the brain's way of organizing itself, either through rhythmic motor commands or sensory feedback generated by the movements themselves.
Think of it this way: when your child flaps their hands, their brain is not malfunctioning. It is functioning. The flapping is the regulation, not the problem.
An estimated 88% of autistic individuals engage in at least three different forms of stimming regularly. Among those who stim, 84% report that stimming increases during periods of heightened emotion, both positive and negative, and 67% describe it as their primary strategy for emotional regulation.
## The Seven Types of Stimming
Stimming is not one behavior. It is an entire category of behaviors that span every sensory system in the body. Understanding which type your child uses tells you what their nervous system is seeking.
### Visual Stimming
Your child watches ceiling fans spin for extended periods. They stare at lights, blink rapidly, or flick their fingers in front of their eyes. They turn light switches on and off. They watch the same three seconds of a video over and over.
Visual stims provide predictable, controlled visual input. For a child whose visual processing is easily overwhelmed by a chaotic environment, a single spinning object offers simplicity and predictability.
### Auditory Stimming
They hum constantly. They snap their fingers, click their tongue, or tap objects to hear the sound they make. They repeat the same word or phrase. They listen to the same song on an endless loop.
Auditory stims create predictable sound patterns that can block out unpredictable environmental noise. If the cafeteria overwhelms your child with layered sounds, their humming creates a consistent auditory anchor.
### Tactile Stimming
They rub fabrics between their fingers. They scratch surfaces. They pick at skin or scabs. They run their hands along walls as they walk. They fidget with anything they can reach.
Tactile stims provide grounding through touch. The consistent pressure or texture input helps the brain orient to the body's position and state. This is closely related to why [sensory-friendly clothing choices](/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children) matter so much for neurodivergent children.
### Vestibular Stimming
They spin in circles. They rock back and forth in their chair. They swing for extended periods. They pace the same path repeatedly.
Vestibular stims engage the balance system and provide a rhythmic, organizing input. Rocking, in particular, activates the same neural pathways used in early infant development, which is why it remains soothing across the lifespan.
### Proprioceptive Stimming
They jump repeatedly. They crash into furniture or cushions. They seek tight hugs or squeeze themselves into small spaces. They stomp their feet or clap forcefully.
Proprioceptive stims provide deep pressure input that tells the brain where the body is in space. For children who struggle with [sensory processing](/blog/sensory-processing-daily-routines), this deep input is genuinely calming at a neurological level.
### Vocal Stimming
They repeat words or phrases (echolalia). They make sounds, grunts, or squeals. They clear their throat repeatedly. They script dialogue from shows or movies.
Vocal stimming appears in approximately 53% of autistic individuals, with rates as high as 75% among those with language differences. These vocalizations serve multiple purposes: self-regulation, processing information, expressing emotion, and sometimes pure sensory enjoyment.
### Olfactory Stimming
They smell objects, people, or food before interacting with them. They chew or lick non-food items. They seek out specific scents.
Olfactory stims are often the least understood by parents, but they serve the same regulatory function as every other type. Smell is one of the most direct sensory pathways to the brain's emotional centers, which is why certain scents can be powerfully calming.

## Why Your Child Stims: The Science
Understanding the why behind stimming transforms how you respond to it. Research from the past two years has significantly expanded what we know.
### Emotional Regulation
This is the most well-documented function. When your child is overwhelmed, anxious, frustrated, or overstimulated, stimming helps bring their nervous system back to a manageable state. It works the same way deep breathing works for you, except your child's brain discovered its own version independently.
A 2025 study by Morris and colleagues published in SAGE Journals found that autistic adults identified stimming as serving functions far beyond basic self-regulation. Participants described stimming as essential for processing emotions, managing [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies), and navigating overwhelming situations.
### Sensory Regulation
Your child's brain may process sensory input differently. Too much input in one channel, not enough in another. Stimming creates controlled, predictable sensory input that helps the brain calibrate. A child who rocks is giving their vestibular system consistent input. A child who flaps is giving their proprioceptive system feedback. The brain uses this self-generated input to organize the flood of external information.
### Joy and Excitement
Not all stimming is a response to distress. Many children stim when they are happy, excited, or deeply engaged with something they love. The hand flapping when a favorite character appears on screen, the jumping when a parent comes home, the spinning when music plays. These are expressions of positive emotion through movement, and they deserve celebration, not correction.
### Communication
A 2024 study in Frontiers in Integrative Neuroscience examined "interactive stimming" between non-speaking autistic children and their parents. The researchers found that stimming serves as a powerful mode of communication, and they advocated for a shift from focusing exclusively on speech toward recognizing the foundational role of the body in autistic communication.
When your child increases their rocking as you describe tomorrow's schedule, they may be telling you something. When their hand flapping intensifies around a specific person or activity, that is information. Learning to read your child's stims as communication, not just behavior, opens an entirely new channel of understanding.
### Focus and Cognitive Processing
A 2024 paper in Educational Psychology Review, titled "Stimming as Thinking," argued that stimming is an intrinsic part of adaptive functioning, interaction, and cognitive dynamics. The researchers proposed that when educational environments build from students' own sensorimotor patterns rather than suppressing them, those behaviors can be embraced as genuine mental activity.
In practical terms: your child may think better when they move. The rocking during homework, the fidgeting during reading, the pacing while processing a question. These movements are not distractions from thinking. For many neurodivergent children, they are thinking.
## When Stimming Crosses the Line: Red Flags
Here is where the conversation gets harder. Most stimming should be supported. But not all of it. There are clear situations where stimming becomes a genuine concern, and parents need to know what those look like.
### Self-Injurious Behavior
This is the most serious red flag. A meta-analysis published in the Journal of Autism and Developmental Disorders analyzed data from 14,379 participants across 37 studies and found that approximately 42% of autistic individuals engage in some form of self-injurious behavior. Population-based studies from the CDC place the estimate at 27.7%.
Self-injurious stims include:
- **Head banging** against walls, floors, or hard surfaces
- **Self-biting**, particularly hands, wrists, or arms
- **Hair pulling** (trichotillomania)
- **Skin picking or scratching** that creates wounds
- **Eye poking or pressing**
- **Hitting or slapping** themselves
If your child's stimming is causing tissue damage, bruising, bleeding, hair loss, or calluses, this is not a behavior to accommodate. It is a behavior that needs professional intervention, not because stimming itself is wrong, but because your child's body is being harmed in the process.
Self-injurious behavior often signals that a child's distress has exceeded what their safer stims can manage. It frequently indicates unaddressed pain, sensory overload, communication frustration, or anxiety that has escalated beyond their coping capacity.
### Interfering with Daily Life
A stim that prevents your child from eating meals, sleeping, learning, or participating in activities they want to participate in warrants attention. There is an important distinction here: the question is not whether the stim looks unusual to other people. The question is whether it is preventing your child from doing things that matter to them.
A child who rocks during class but still absorbs the lesson is fine. A child whose rocking has become so intense that they cannot engage with anything else for hours at a time needs support. The threshold is functional impact, not social acceptability.
### Escalating Intensity
When stims that were previously mild become significantly more intense, frequent, or urgent, something has changed. Maybe a new source of stress has entered your child's life. Maybe a sensory environment has shifted. Maybe an underlying medical issue is causing discomfort. [Tracking these patterns](/blog/tracking-emotions-activities-neurodivergent-children) over time helps you identify what changed and when.
Escalating stimming is your child's nervous system raising its voice. It does not mean the stimming itself is the problem. It means the stimming is no longer sufficient to manage whatever is driving it.
### Replacing Communication
For some children, stimming can become the default response to every need, replacing attempts to communicate. If a child who was previously using words, signs, or an AAC device begins relying exclusively on stimming to express hunger, discomfort, or wants, this regression in communication warrants evaluation.
The goal is not to eliminate the stimming but to ensure that stimming and communication coexist. A child should be able to stim and communicate, not have to choose one over the other.
## How to Support Healthy Stimming
Supporting stimming does not mean doing nothing. It means creating an environment where your child's natural regulatory behaviors are welcomed while also building skills and structures that expand their toolkit.
### Create Stim-Friendly Spaces
Designate areas in your home where your child can stim freely without judgment or interruption. A corner with a rocking chair, a mini-trampoline, textured objects, and noise-cancelling headphones gives them a physical space that says "your body's needs are welcome here."
This does not have to be elaborate. A beanbag in the corner of their bedroom with a fidget basket nearby is enough. The message matters more than the setup.
### Join the Stim
Research on interactive stimming shows that when parents participate in their child's stimming, it can strengthen the parent-child bond and open communication channels. If your child is rocking, sit beside them and rock together. If they are humming, hum along. If they are tapping, tap a complementary rhythm.
You are not mocking their behavior. You are entering their world through their preferred sensory language. Many parents report that these moments of shared stimming produce eye contact, smiles, and connection that verbal interaction alone does not achieve.
### Track Patterns to Understand Triggers
Stimming does not happen in a vacuum. It increases and decreases in response to specific environments, emotions, times of day, and social demands. Keeping a record of when stimming intensifies, what type of stim your child uses, and what was happening beforehand reveals patterns that are invisible in the daily chaos.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you track your child's [emotional states](/blog/emotional-regulation-visual-supports) and behavioral patterns visually over time. When you can see that your child's rocking triples after school every day, you have concrete data pointing to the school environment as a sensory stressor. That data is worth more than any guess.
### Teach Self-Advocacy
As your child grows, help them understand and articulate their own stimming needs. "I need to rock right now because I am feeling overwhelmed" is a powerful statement that [builds self-advocacy skills](/blog/teaching-self-advocacy-skills-neurodivergent-child). It transforms stimming from something that happens to them into something they understand and can communicate about.
This language also helps teachers, peers, and other adults understand what they are seeing. A child who can say "I listen better when I fidget" has just given their teacher the information needed to support rather than correct them.
### Build a Sensory Diet
An occupational therapist can help you develop a "sensory diet," a planned schedule of sensory activities throughout the day that proactively meets your child's sensory needs before they escalate to the point of intense stimming. This might include:
- Heavy work activities in the morning (carrying books, pushing a laundry basket)
- Movement breaks between seated activities
- Tactile play during transitions
- Deep pressure input before high-demand situations
- Calming vestibular input before bed
A sensory diet does not replace stimming. It reduces the pressure on stimming to be the only regulatory tool your child has.
## When a Stim Is Harmful: Redirecting Safely
If your child has a stim that is causing physical harm, the goal is never to eliminate the need behind the behavior. The goal is to meet the same need through a safer channel.
### Identify the Sensory Function
Before redirecting, figure out what sensory input the harmful stim provides. A child who bangs their head may be seeking deep proprioceptive input to the skull. A child who bites their hands may be seeking intense oral-tactile pressure. A child who scratches their skin may be seeking sharp tactile stimulation.
Once you know the function, you can offer alternatives that deliver similar input without causing harm.
### Offer Safer Alternatives
- **For head banging**: A vibrating pillow, a weighted hat, gentle head squeezes, or a helmet during acute periods while you work on alternatives
- **For self-biting**: Chewable jewelry (chew necklaces, chew bracelets), vibrating teethers, crunchy or chewy snacks
- **For skin picking**: Textured fidgets, peeling activities (stickers, tape, dried glue on hands), putty or clay
- **For hair pulling**: Textured wigs or doll hair to pull, resistance bands, sensory brushes
- **For hitting self**: Weighted lap pads, compression vests, pillow punching, clapping games
The alternative must genuinely satisfy the same sensory need. If it does not, your child will return to the harmful behavior because their body still needs what the original stim provided.
### Address the Root Cause
Harmful stimming often escalates when something deeper is wrong. Before focusing exclusively on the behavior, investigate whether your child is experiencing:
- **Unaddressed pain or medical issues** (ear infections, dental problems, GI distress are common in autism and often go unreported)
- **Environmental stressors** (a new teacher, a schedule change, [bullying](/blog/navigating-bullying-neurodivergent-children))
- **Communication frustration** (needing something they cannot express)
- **Sleep deprivation** ([sleep challenges](/blog/sleep-challenges-night-waking-neurodivergent-children) dramatically increase self-injurious behavior)
- **Sensory environments** that have changed (new lighting at school, construction noise near home)
Treating the root cause often reduces the harmful behavior more effectively than any behavioral intervention targeting the stim itself.
### Know When to Call for Help
Some situations require professional support. Reach out to your child's pediatrician, occupational therapist, or behavioral specialist if:
- Self-injurious stimming is causing visible physical damage
- The intensity or frequency of harmful stims is increasing over time
- Your child seems distressed or in pain during the stimming
- Stims are preventing sleep, eating, or participation in wanted activities
- You have tried safer alternatives and your child consistently returns to the harmful behavior
- The stimming started suddenly with no obvious trigger
For guidance on [finding the right therapist](/blog/finding-right-therapist-neurodivergent-child) who understands neurodivergent children, our dedicated guide walks you through the evaluation process.
## What to Tell Other People
One of the hardest parts of supporting stimming is managing other people's reactions. The stares at the grocery store. The comments from family members. The teacher who insists your child "sit still and pay attention."
### For Family Members
"This is how their brain regulates itself. It is like deep breathing for you. When they rock or flap, their nervous system is doing exactly what it needs to do. Please do not tell them to stop or draw attention to it. If you want to connect with them, try sitting near them and being calm."
### For Teachers
"My child stims to regulate and focus. Research shows that for many neurodivergent children, movement supports rather than hinders learning. Please allow fidget tools, movement breaks, and stimming that does not disrupt others. If their stimming escalates significantly, it usually means something in the environment is overwhelming them, and a sensory break will help more than a correction."
### For Other Children
"Everyone's body works a little differently. Some people need to move their body to help their brain feel calm. That is what you are seeing. It is not weird or scary. It is just their way."
## Your Child's Body Knows What It Needs
Here is what the research keeps pointing back to: your child's stimming exists for a reason. It is not a malfunction. It is not a behavior problem. It is the nervous system's built-in solution to the challenge of existing in a world that was not designed for the way their brain processes information.
A 2025 study found that stimming is only experienced as negative when it causes self-injury or when other people stigmatize it. That second part is important. Much of the distress around stimming comes not from the behavior itself but from the social response to it.
You cannot control how the world responds to your child. But you can control what happens at home. You can create a space where [their strengths are celebrated](/blog/celebrating-neurodivergent-strengths-children), where their body is trusted, and where the message is clear: you do not need to hold still to be accepted here.
And when a stim is harmful, you can address it from a place of understanding rather than shame. Not "stop doing that" but "I see your body needs something. Let me help you find a safer way to get it."
That is the difference between managing behavior and supporting a whole child. And your child can feel the difference.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you track your child's stimming patterns and emotional states over time, build sensory-friendly visual routines that reduce overwhelm, and share documented patterns with occupational therapists and providers. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the structure and understanding they deserve.
---
## Autism Insurance Denials: How to Fight Back and Win
Published: 2026-04-02
URL: https://vizyplan.com/blog/autism-insurance-denials-prior-authorization-guide
Category: Strategies
Author: Justin Bowman
> Mental health claims are denied 85% more often than medical claims. Learn your rights under parity law, how to appeal step by step, and why families who fight back win almost half the time.
The letter arrived on a Tuesday. Your child's ABA therapy has been denied. Or maybe the hours were cut from 30 to 15. Or the prior authorization was rejected because the documentation was "insufficient." Or your child aged out of coverage at 10 in a state that decided a decade of life was enough support.
You are holding the letter and your stomach is in your throat because you have seen what therapy does for your child. You have watched the progress. You have seen the words emerge, the meltdowns decrease, the independence grow. And someone at a desk in an office building has decided, based on a file they reviewed for minutes, that your child no longer needs what is working.
Here is what the insurance company is counting on: that you will not fight back. Research shows that less than 1% of denied claims are ever appealed. But here is what they do not want you to know: 44% of internal appeals succeed. Families who cite specific legal violations win at rates 3.2 times higher than those who do not. The system is designed to make you give up. This article is designed to make sure you do not.
## The Numbers Behind the Denials
This is not happening just to your family. It is a systemic problem with documented evidence.
Insurance companies denied 20% of all health claims in 2024, according to KFF data analyzing 451 million submitted claims. That is 85 million denied claims. But the numbers are significantly worse for behavioral health. Mental health claims are denied at rates 85% higher than medical claims, despite a federal law that has required equal treatment since 2008.
For ABA therapy specifically, providers report that 15 to 20% of prior authorization requests require appeals before approval. Thirteen percent of children referred for ABA never receive it at all. Of those who do start, less than half remain in treatment at 24 months. The system is leaking families at every stage, and insurance barriers are a primary driver.
When nearly one in four children experiences delays exceeding six months from [diagnosis](/blog/autism-diagnosis-what-to-do-next) to treatment, the consequences are not abstract. Research shows that children who begin ABA between 36 and 47 months show markedly greater symptom reduction than those starting just one year later. Every month of delayed therapy has a measurable developmental cost, and every denied claim pushes that timeline further out.
## The Law Is on Your Side (Even When It Does Not Feel Like It)
Multiple federal and state laws protect your child's right to autism therapy coverage. The problem is not that the laws do not exist. The problem is that insurance companies routinely violate them, betting that families will not know their rights or have the energy to enforce them.
### The Mental Health Parity Act
The Mental Health Parity and Addiction Equity Act, enacted in 2008, requires that financial requirements and treatment limitations for mental health benefits are no more restrictive than those for medical and surgical benefits. In plain language: if your insurance covers 30 visits of physical therapy for a broken leg without prior authorization, it cannot require prior authorization for 30 sessions of ABA therapy for autism.
In 2024, the federal government issued landmark regulations that specifically identified ABA therapy as a "core treatment" for autism. Plans that exclude ABA coverage would be "unlikely to satisfy" the law's requirements. While enforcement of some provisions was paused in May 2025 pending litigation, the core parity requirements from 2013 remain fully in effect.
When the Department of Labor reviewed insurance plans' compliance with parity requirements in 2021, not a single plan met the required standards on initial review. Not one. The insurance industry has known about parity requirements for over fifteen years and has systematically failed to comply. Your denial may be one of those failures.
### All 50 States Mandate Autism Coverage
Every state in the country plus Washington D.C. has enacted legislation requiring insurance companies to cover evidence-based autism treatments including ABA, speech therapy, and occupational therapy. But the details vary enormously.
States like California, Colorado, Massachusetts, and New York have no age caps and no dollar caps. Your child's coverage continues as long as treatment is medically necessary. States like Maine cap coverage at age 10. Hawaii caps annual coverage at $25,000, which does not come close to covering comprehensive ABA therapy. Alabama uses a tiered system: $40,000 for ages 0 to 9, dropping to $20,000 for ages 14 to 18.
Knowing your state's specific mandate is essential because your insurer may be applying restrictions that violate state law. The National Conference of State Legislatures maintains a comprehensive database of autism insurance mandates. Look up yours before you file your appeal.
### Medicaid Has Additional Protections
If your child is on Medicaid, the Early and Periodic Screening, Diagnostic and Treatment provision, known as EPSDT, mandates coverage of all medically necessary services for children under 21. A 2014 CMS bulletin specifically required Medicaid programs to provide ABA therapy. Services must be "sufficient in amount, duration, or scope" to achieve their purpose, and coverage cannot be denied or reduced based solely on diagnosis.
If your child's Medicaid-funded ABA hours are being cut, this is the provision you cite. States are currently [cutting Medicaid ABA rates](/blog/aba-therapy-cuts-what-to-do-at-home) across the country, and EPSDT is the strongest legal tool families have to push back.
## Why Your Claim Was Really Denied
Insurance companies use several categories of denial. Understanding which one applies to your situation determines your appeal strategy.
**"Not medically necessary."** This is the most impactful denial type. The insurer has decided that the treatment is not appropriate or effective for your child. The appeal strategy here is overwhelming clinical documentation: your BCBA's assessment, your pediatrician's letter, progress notes showing measurable improvement, and peer-reviewed research supporting the intervention.
**"Sufficient progress."** This is the catch-22 that infuriates families. Your child has improved, which proves the therapy is working, and the insurer uses that improvement as justification to cut the therapy. No equivalent standard exists for chronic medical conditions. Your cardiologist would never be told to stop treating your heart disease because your cholesterol improved. The appeal strategy here is parity: compare how the insurer treats ongoing medical conditions to how it treats autism.
**Prior authorization denied or expired.** ABA authorizations must be renewed every few months. Each renewal requires updated assessments, progress notes, and justification for continued treatment. If the authorization lapses or the paperwork is incomplete, services are denied. The appeal strategy is documentation: submit everything the insurer asked for, plus additional supporting letters.
**Age or dollar cap reached.** If your state mandates coverage only to age 10 or caps benefits at $25,000, the denial may cite the state limit. But here is the critical point: the federal Mental Health Parity Act can override state caps. If your insurer does not apply similar limits to medical and surgical benefits, the cap may be unenforceable. This is where citing parity violations in your appeal dramatically increases your chances.
**Concurrent therapy denied.** Some insurers deny ABA when your child also receives speech therapy or occupational therapy, claiming the services overlap. They do not. ABA addresses behavioral and social deficits. [Speech therapy](/blog/types-of-therapy-neurodivergent-children) addresses communication. [Occupational therapy](/blog/sensory-processing-daily-routines) addresses sensory and motor skills. Each targets different domains and the research supports concurrent delivery.
## How to Appeal Step by Step
### Step 1: Understand Exactly Why You Were Denied
Request the denial in writing with the specific clinical criteria the insurer used to make the decision. Under federal law, your insurer must provide the reasons for denial and identify the specific plan provisions or medical criteria applied. Do not accept a vague explanation. You need the exact language to build your appeal.
### Step 2: Build Your Documentation Package
This is where most appeals are won or lost. Gather:
- Your child's complete autism diagnosis documentation
- Your BCBA's comprehensive assessment and treatment plan with measurable goals
- Progress notes showing what therapy has achieved and what remains
- Letters from your child's pediatrician, psychologist, speech therapist, or OT supporting continued treatment
- Peer-reviewed research supporting the specific intervention being denied
- Your state's autism insurance mandate with relevant provisions highlighted
- Any evidence of parity violations, instances where the insurer treats medical claims differently than behavioral health claims
### Step 3: File Your Internal Appeal
Submit a written appeal to your insurance company with all supporting documentation. Insurers must respond within 30 days for pre-service appeals and 60 days for post-service appeals. For urgent care, the timeline is 72 hours.
This is the most important tactical decision in your appeal: **cite parity violations, not just medical necessity.** Research on appeal outcomes shows that appeals documenting specific parity violations achieve success rates 3.2 times higher than those focused solely on clinical arguments. Parity-focused appeals achieve 76% approval compared to 24% for clinical-only arguments.
In your appeal letter, explicitly compare how the insurer handles your child's autism treatment to how it handles comparable medical conditions. If your insurer requires prior authorization for ABA but not for physical therapy, that is a parity violation. If it caps ABA hours but not oncology visits, that is a parity violation. If it requires "continued improvement" for behavioral health but not for chronic medical conditions, that is a parity violation.
### Step 4: Request External Review
If your internal appeal is denied, you have the right to an external review by an Independent Review Organization. IROs are staffed by medical professionals with no financial ties to the insurance company. Their decision is binding on the insurer. External reviews overturn insurer decisions 27 to 40% of the time.
### Step 5: File a State Insurance Commissioner Complaint
If your insurer is violating your state's autism mandate, file a complaint with your state's Department of Insurance. The commissioner can investigate and compel compliance. This is particularly effective because it creates regulatory pressure beyond the individual claim.
### Step 6: Contact Your State's Protection and Advocacy Office
Every state has a federally funded Protection and Advocacy organization that provides free legal services for disability-related issues, including insurance denials. These offices handle cases exactly like yours. Find your state's P&A through the National Disability Rights Network.
## The Financial Reality Nobody Wants to Talk About
ABA therapy without insurance costs $62,400 to $249,600 per year depending on intensity. Speech therapy runs $100 to $250 per hour. Occupational therapy costs $100 to $200 per hour. Medical expenditures for autistic children are 4.1 to 6.2 times greater than for children without autism.
The research on what this does to families is devastating. Over 40% of families report autism-related costs exceeding 50% of their total household income. Thirty-four percent of caregivers stop working entirely. Mothers' employment rates decline by 6% with a 7-hour weekly reduction in work hours. Nearly 44% of mothers are unemployed specifically due to childcare demands. Families report depleting savings, emptying retirement accounts, and filing for bankruptcy.
When an insurance company denies your child's therapy claim, they are not making a medical decision. They are making a financial decision with medical consequences. And the financial devastation that follows lands entirely on your family.
This is why [tracking your child's progress](/blog/tracking-emotions-activities-neurodivergent-children) matters for more than therapeutic reasons. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you track emotions, behaviors, and daily activities over time, giving you documented data that supports medical necessity arguments in appeal letters. When you can show an insurer specific patterns of improvement tied to therapy and regression during gaps, that data strengthens your case.
## What You Can Do Right Now
If your child's therapy has been denied or reduced:
- **Do not accept the denial as final.** Less than 1% of families appeal, but 44% of those who do win. The odds are dramatically better than the insurance company wants you to believe.
- **Request the denial in writing immediately.** You need the specific reasons and clinical criteria to build your appeal.
- **Contact your child's treatment team.** Ask your BCBA, pediatrician, and any other providers to write supporting letters. Appeals with provider advocacy letters achieve 64% approval versus 29% without.
- **Look up your state's autism mandate.** Know your specific rights, including age limits, dollar caps, and covered services. The National Conference of State Legislatures has a comprehensive database.
- **Cite parity violations in your appeal.** This single strategy triples your success rate. Compare how your insurer treats autism claims to medical claims.
- **Contact your state's Protection and Advocacy office.** Free legal services exist specifically for situations like yours.
- **Document everything.** Keep records of every call, letter, email, and decision. Note the name of every representative you speak with and the date and time of every conversation.
- **File your appeal before the deadline.** Internal appeals typically have a 180-day deadline from the date of denial. Do not let it pass.
## While You Fight: Bridging the Gap
Appeals take time. While you wait, your child's development does not pause. If therapy hours have been reduced or eliminated, research shows that [parent-implemented strategies](/blog/aba-therapy-cuts-what-to-do-at-home) can maintain progress. [Visual routines](/blog/visual-schedules-for-autism), [social stories](/blog/social-stories-autism-guide), [choice boards](/blog/choice-boards-empowering-decisions), and structured daily schedules are evidence-based interventions you can implement at home.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built for exactly this situation. When professional services are disrupted, visual supports and structured routines become the scaffolding that holds your child's progress in place while you fight to get their therapy restored.
Explore school-based services through your child's [IEP](/blog/504-plan-vs-iep-neurodivergent-child), which are free and cannot be denied based on insurance status. Look into university ABA clinics, which often offer reduced-rate services. Consider telehealth options, which achieve similar outcomes at lower cost.
## You Are Not Powerless
The insurance system is designed to exhaust you into compliance. The paperwork is overwhelming by design. The denials are automated. The appeals process is complex enough that most families give up before they start.
But the numbers tell a different story. Forty-four percent of internal appeals succeed. Up to 80% win when families complete the full appeal process. Parity-focused appeals win at three times the rate of clinical-only arguments. Free legal help exists in every state.
Your child's insurer is betting that you are too tired, too busy, too overwhelmed to fight. Prove them wrong. The therapy that is changing your child's life is worth the fight to keep it.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you track your child's progress with data that strengthens insurance appeals, build visual routines that bridge therapy gaps, and maintain the structure your child needs when services are disrupted. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and fight for your child's care with the right tools behind you.
---
## Sensory Processing and Clothing: The Invisible Daily Battle
Published: 2026-04-01
URL: https://vizyplan.com/blog/sensory-processing-clothing-autism-daily-battle
Category: Strategies
Author: Justin Bowman
> Up to 95% of autistic children have sensory differences. Learn why their brain cannot tune out clothing the way yours does and what the neuroscience says actually helps.
It is 7:15 AM on a school day. Your child is standing in the middle of their bedroom in underwear, screaming. The shirt you laid out has a tag. You cut the tag. Now there is a bumpy residue where the tag was. You find a different shirt. The seams feel wrong. A third shirt is the wrong color and they will not wear it. The socks have a line across the toes. The pants are too tight at the waist. The jacket is too stiff.
It is now 7:42 AM. The bus comes in eight minutes. Your child is still in underwear and you are both crying.
If you live some version of this morning, you are not alone. Research shows that up to 95% of parents report sensory processing differences in their autistic children, and clothing is one of the most consistent battlegrounds. A 2025 study found that 73.2% of autistic adults regularly avoid certain clothing types, 55.8% cut labels from their clothes, and 46.5% avoid garments where seams contact their skin.
Your child is not being dramatic. Their brain is processing the physical sensation of clothing in a fundamentally different way than yours does, and understanding that neuroscience changes everything about how you approach the problem.
## Why Your Brain Ignores Clothing and Theirs Cannot
Put on a shirt right now and pay attention to how it feels against your skin. You can feel the fabric, the seams, the weight of it on your shoulders. Now stop thinking about it. Within a minute or two, the sensation fades from your awareness entirely. Your brain has decided the shirt is not a threat, and it stops sending you information about it.
This process is called neural habituation, and it is one of the most basic functions of the sensory system. Your brain learns that repeated, non-threatening stimuli do not need your attention, so it filters them out. It is why you stop hearing the hum of an air conditioner after a few minutes. It is why you do not constantly feel the chair you are sitting in.
In autistic children, this process is impaired. Research published in Developmental Cognitive Neuroscience found that autistic children demonstrate reduced GABA levels in the somatosensory cortex, the brain region that processes touch. GABA is the neurotransmitter responsible for inhibiting neural activity, for telling the brain "you can stop paying attention to this now." With less GABA available, the brain keeps responding to the sensation of clothing against skin all day long.
A separate study published in Translational Psychiatry found that thalamic GABA levels are significantly correlated with sensory over-responsivity severity. The thalamus is the brain's sensory gatekeeper. It decides which sensory information gets passed along to higher brain regions for conscious processing and which gets filtered out. In autism, lower GABA in the thalamus means the gate stays open. Every seam, every tag, every fold of fabric keeps getting flagged as something that requires attention.
This is not a preference. It is not a phase. It is a measurable neurochemical difference in how the brain processes tactile input. When your child says the shirt hurts, their brain is literally not doing the thing that would make the shirt stop hurting.
## What Clothing Actually Feels Like to Your Child
Autistic adults in a 2025 study published in the journal Autism described the sensation of disliked fabrics as feeling like "needles picking" or "ants crawling" on their skin. One participant described trying on clothes as "the worst because it feels like bugs are all over my skin." Another said they feel "trapped in my safe clothes and would feel silly trying anything else now."
These descriptions are not exaggerations. They are the lived experience of a nervous system that processes touch through a different neurological pathway.
### The Sensory Modalities at Play
Research has identified specific sensory channels that drive clothing distress:
**Texture is the dominant factor.** A study comparing autistic and neurotypical children found that 64% of autistic children showed atypical oral and tactile sensory sensitivity, compared to just 7% of typically developing peers. Children with tactile hypersensitivity refused significantly more [sensory input](/blog/sensory-processing-daily-routines) across all domains, and fabric texture was the most consistent predictor of clothing acceptance or rejection.
**Fabric preferences are measurable.** A controlled study had participants handle and evaluate different fabrics. Ninety percent disliked hessian and spandex. Seventy percent disliked polyester. Sixty percent disliked wool. On the preferred side, 70% liked satin for its softness and smoothness, and 60% liked cotton for its neutral, comfortable quality.
**Tightness and compression cut both ways.** Nearly half of autistic adults avoid constricting clothing because it creates feelings of suffocation. But some autistic individuals, particularly those who are hyposensitive to touch, actively seek tight clothing because it provides proprioceptive feedback that helps them feel where their body is in space. Temple Grandin, who described stiffening and pulling away from light touch, simultaneously craved deep pressure so intensely that she built a squeeze machine at age 18. This is why one child refuses anything with an elastic waistband while another insists on wearing compression shirts under their clothes.
**Body regions vary in sensitivity.** Research shows the upper body, particularly the shoulders, arms, and neck area, tends to be more sensitive than lower extremities. The neck is especially reactive due to its high concentration of sensory nerve endings. This explains why tags at the neckline cause disproportionate distress compared to seams in less sensitive areas.
## The Real Triggers: A Research-Backed List
Understanding exactly what triggers your child helps you solve problems instead of guessing. Based on the research:
**Tags and labels.** Over half of autistic adults routinely cut labels from clothes. Even after cutting, the residual material can worsen irritation. Look for tagless clothing or garments with printed labels rather than sewn-in ones.
**Seams.** Nearly half avoid seams contacting skin. Sock seams across the toes are one of the most common meltdown triggers in the research literature. Flat seams or fully seamless designs significantly reduce distress.
**Elastic waistbands.** Tight elastic creates constant pressure that the brain cannot filter out. Drawstring or adjustable waistbands provide a looser fit without the continuous squeeze.
**Fabric type.** Synthetic fabrics like polyester and spandex are overwhelmingly rejected. Natural fibers like cotton, bamboo, and satin are generally preferred. The key variable is predictability: the fabric needs to feel the same way every time.
**Temperature mismatch.** Autistic individuals may have difficulty regulating body temperature and can become hot or cold much faster than expected. Clothing that traps heat or fails to insulate adequately adds another layer of sensory distress.
**Decorative elements.** Sequins, embroidery, sparkly fibers, and printed designs that create texture differences across the garment all add unpredictable sensory input.
## Beyond the Morning: How Clothing Sensitivity Ripples Through Everything
The clothing battle does not end when your child finally gets dressed. It continues all day, consuming cognitive resources that could be directed toward learning, socializing, and emotional regulation.
### School and Academic Impact
If your child spends the entire school day with part of their brain monitoring the uncomfortable sensation of their shirt seam against their shoulder, that is cognitive bandwidth unavailable for paying attention to the teacher, processing language, managing social interactions, or [regulating emotions](/blog/emotional-regulation-visual-supports). Research confirms that sensory experiences compromise the ability to concentrate in a classroom. Some children refuse to attend school entirely when their clothing is intolerable.
If your child's clothing sensitivity significantly impacts their school performance, write sensory accommodations into their [IEP or 504 plan](/blog/504-plan-vs-iep-neurodivergent-child). Allowing flexible dress code options, keeping backup sensory-friendly clothing at school, and permitting your child to remove uncomfortable layers are reasonable accommodations that cost nothing and can transform the school day.
### Social Participation and Self-Expression
Formal events, school uniforms, swimwear, and seasonal clothing all force autistic children into fabrics and fits that their nervous system rejects. One autistic adult in the 2025 Autism study described the impact: "Sometimes at formal events if my clothes are very uncomfortable, I am extra anxious and self conscious."
For older children and teenagers, the impact extends to identity. A 2025 study found a significant negative relationship between tactile hypersensitivity and self-esteem, moderated by appearance dissatisfaction. Autistic adults reported more negative appearance evaluations than both the general population and adults with visible appearance differences. One participant captured the bind perfectly: "Being non-binary, I would love to explore fashion more, but I can not because the clothes I want to wear make me have a meltdown."
Fashion is how children and adults express identity. When sensory barriers restrict clothing choices to a handful of safe items, the loss is not just physical comfort. It is self-expression.
### The Financial and Emotional Toll on Parents
Sensory-friendly clothing costs more than standard children's clothing. When your child finds one acceptable pair of pants, you buy five pairs because you know the manufacturer might change the fabric or discontinue the line. When [shopping](/blog/grocery-store-strategies-errands-neurodivergent-child) for clothes requires your child to physically handle every item before purchase, online shopping becomes a cycle of ordering and returning. When one parent has to leave work because the school called to say your child stripped off their uniform and will not put it back on, the financial impact compounds.
And then there is the judgment. "Just make them wear it" from relatives who do not understand. "They are being dramatic" from teachers who have never felt a fabric like needles against their skin. The isolation and blame that parents of autistic children face is well documented, and clothing battles are one of the most visible and least understood triggers.
## What Actually Helps: Evidence-Based Strategies
### Build a Sensory-Friendly Wardrobe Strategically
Eliminating seemingly minor irritants, tags, seams, rough fabrics, tight elastic, reduced [dressing-related](/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children) meltdowns by up to 65% in observed participants. That is a significant reduction from changes that cost relatively little.
Start with what your child already tolerates and look for more of the same. If they live in one specific cotton t-shirt, find identical or near-identical options. If seamless socks are the only socks that work, stock up. If elastic waistbands are a trigger, switch everything to drawstring or adjustable waist.
Key features to look for: tagless or printed labels, flat seams or seamless construction, soft natural fabrics like cotton or bamboo, elastic-free or adjustable waistbands, no decorative textures, and compression options for children who seek proprioceptive input.
### Use Deep Pressure to Regulate Before Dressing
A 2025 systematic review found strong evidence that deep pressure tactile input improves functional outcomes for autistic children. Temple Grandin's own research showed that 15 minutes of deep pressure reduced anxiety for 45 to 60 minutes. If your child's morning clothing battle happens because their nervous system is already dysregulated from waking up, a few minutes of deep pressure activities before getting dressed can shift their baseline enough that clothing becomes tolerable.
This might look like a tight hug, rolling up in a blanket, wearing a compression garment briefly, or doing "heavy work" activities like pushing against a wall or carrying a heavy object. The goal is to activate the proprioceptive system, which has a calming effect on the tactile system.
### Give Your Child Choices and Control
Let your child participate in selecting their own clothing. When a child chooses their outfit from pre-approved sensory-friendly options, the act of choosing provides a sense of control that reduces [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) and resistance. [Choice boards](/blog/choice-boards-empowering-decisions) with photos of acceptable outfits can make this process visual and concrete.
For children with [demand avoidance profiles](/blog/demand-avoidance-pda-profile-autism-children), being told what to wear triggers the same avoidance response as any other demand. Presenting options instead of instructions changes the dynamic entirely.
### Create a Visual Getting-Dressed Routine
A predictable, visual sequence for getting dressed removes the decision fatigue and uncertainty that amplify sensory distress. When your child knows exactly what comes next, they can focus their cognitive resources on managing the sensory experience rather than also processing the unpredictability of the routine.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build a personalized [visual dressing routine](/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children) with AI-generated images of your child doing each step in their own bedroom with their own clothes. When the routine is visual and familiar, the morning goes from combat to sequence.
### Introduce New Clothing Gradually
If your child needs to wear something new, whether for a seasonal change, a formal event, or a school uniform, gradual exposure is essential. An occupational therapy approach involves first touching the fabric, then draping it over an arm, then wearing it briefly at home with no pressure, then extending the duration over days or weeks.
Research shows it can take multiple exposures before a new clothing item moves from "threat" to "tolerable." Rushing this process guarantees a meltdown. Planning for it, with weeks of lead time before the event or season change, gives the nervous system time to adapt.
Dr. Stephanie Weber, a psychologist at Cincinnati Children's Hospital, emphasizes that "insistence on routine and resistance to change are particularly common among those who have autism." Seasonal transitions are especially difficult. Build tolerance incrementally rather than expecting your child to switch from summer to winter clothing overnight.
### Know When to Seek Professional Help
If clothing sensitivity is causing daily meltdowns that disrupt your family's ability to function, school refusal, or significant distress for your child, an occupational therapy evaluation is warranted. Ayres Sensory Integration therapy is now classified as an evidence-based intervention for autistic children. A qualified OT can assess your child's specific sensory profile and develop targeted strategies that go beyond general recommendations.
A 2025 systematic review also found strong evidence for caregiver training on sensory strategies. Sometimes the most effective intervention is not treating the child directly but teaching you how to respond to and accommodate their sensory needs in ways that reduce distress for everyone.
## What Your Child Needs You to Know
Your child is not choosing to be difficult about clothing. Their brain is doing something measurably different with the sensory information it receives. Where your brain filters out the feeling of fabric within minutes, theirs keeps processing it all day. Where a tag feels like a minor annoyance to you, their brain registers it as something that demands constant attention, like a pebble in your shoe that you cannot remove.
The morning battle is not about control or defiance. It is about a nervous system that is overwhelmed before the day even starts. And the fact that you are standing in that bedroom at 7:15 AM, trying shirt after shirt, cutting tags and checking seams, is not a sign that you are doing something wrong. It is a sign that you are doing exactly what your child needs: taking their experience seriously even when the world tells you to just make them wear it.
Every time you honor what their body is telling them, you teach them that their sensory experience is valid. That lesson matters more than any shirt.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build visual dressing routines with personalized images, track sensory patterns that reveal your child's triggers, and create the predictable morning structure that turns clothing battles into manageable sequences. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring calm to the hardest part of your morning.
---
## Why Social Stories Fall Apart Between Sessions
Published: 2026-03-31 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/why-social-stories-fall-apart-between-sessions
Category: Strategies
Author: Justin Bowman
> Social stories work in therapy but fall apart at home. Research shows why the session-to-home gap exists and what SLPs, parents, and families can do to close it.
The social story worked perfectly in the therapy room. Your child's SLP read it three times. Your child answered the comprehension questions. They even acted out the scenario with a stuffed animal. Everyone felt great about the progress.
Then you got home. You tried to read the story before the situation it was supposed to prepare your child for, and they would not sit still. Or they sat still but the story did not seem to connect to anything real. Or you could not find the printed pages because they were somewhere between the car seat and the recycling bin. Or, honestly, you forgot about it entirely because dinner needed to happen and homework was not done and there were three other things on the list before bedtime.
Two weeks later, the SLP asks how the social story is going at home. You feel guilty. You say "good" and change the subject.
If this is your experience, you are not the exception. You are the rule. And the problem is not you. The problem is that social stories were designed for therapy rooms, not for the messy, unpredictable, overwhelming reality of daily life with a neurodivergent child.
## What the Research Actually Says About Social Stories
Social stories, developed by Carol Gray in 1991, are one of the most widely used interventions for autistic children. Speech-language pathologists use them to target [social communication](/blog/social-stories-autism-guide), which sits squarely within their professional scope. The stories describe social situations using specific sentence types: descriptive sentences that explain what is happening, perspective sentences that describe how people feel, and directive sentences that suggest appropriate responses.
They sound like they should work perfectly. And in controlled settings, with trained professionals delivering them immediately before the target situation, they often do. A 2024 scoping review of 56 studies found that 66% reported positive effects, particularly for aggressive behaviors, following directions, self-care, and emotion identification.
But here is what those optimistic numbers hide. The largest randomized controlled trial of social stories ever conducted, the ASSSIST-2 study published in 2025, tested the intervention with 249 autistic children across 87 schools. The primary outcome measure showed no statistically significant effect. Children who attended at least six sessions did show improvement, but the global measure of social skills did not change in a meaningful way.
The Association for Science in Autism Treatment summarized the research bluntly: "Professionals should present Social Stories as having limited scientific support." And the What Works Clearinghouse found that only 5% of social story studies provided strong evidence of a causal relationship between the intervention and the outcome.
This does not mean social stories are useless. It means the way they are typically created and delivered is failing to produce the results families expect.
## The Generalization Problem Is Massive
Here is the core issue that explains why social stories work in the therapy room and fall apart everywhere else. Autistic children often have specific difficulty generalizing learned skills to new settings. A foundational study by Rincover and Koegel found that nearly half of autistic children who learned new behaviors in a treatment room failed to transfer those skills to a different setting.
Nearly half. And that was the finding that launched decades of research into why.
A systematic review examining whether intervention gains transfer to daily life found that only 32% of eligible trials even measured generalization properly. Of the studies that did measure it, generalization was inconsistent. Skills transferred in some contexts but not others, for some children but not all. The researchers noted that many intervention studies rely on what they called a "train and hope" strategy, teaching skills in one setting and hoping they appear elsewhere without explicitly planning for transfer.
For social stories specifically, research found something even more telling. The strongest improvements in behavior occurred on days when social stories were used immediately before the target situation. This suggests social stories function more like prompts or reminders than lasting skill-builders. If the story is not available at the moment it is needed, the behavioral improvement often disappears.
This has enormous implications for how social stories are used at home. Reading a social story at bedtime about what will happen at the grocery store tomorrow is not the same as reading it in the car on the way to the grocery store. The timing matters, and the gap between therapy sessions and real life is where the timing falls apart.
## Why the Therapy-to-Home Gap Exists
Your child's SLP creates beautiful, thoughtful social stories during sessions. They know the research. They follow Carol Gray's criteria (though only 41% of practitioners actually do, according to a 2024 scoping review). They read the story with your child in a quiet, controlled environment with no distractions, no siblings, no dinner burning on the stove.
Then they send the story home with you. And that is where the system breaks down.
### Parents Are Overwhelmed
Research on parent-implemented interventions for autistic children documents exactly why carry-over fails. Parents of autistic children experience heightened stress and mental health challenges. Learning new intervention strategies requires 2 to 48 hours of training, and daily implementation adds 30 minutes to 20 hours per week of additional work. The perception of treatment burden directly predicts whether parents follow through.
You are not failing to implement the social story because you do not care. You are failing because you are already stretched beyond capacity, and adding one more thing to the pile sometimes feels impossible. The research validates this: introducing interventions decreased parent stress in some studies but actually increased it in others. Your SLP handing you a social story and saying "read this every day" without acknowledging the reality of your daily life is a setup for guilt, not success.
### The Stories Are Not Personalized
Here is something that might surprise you: most social stories used in practice are not truly personalized. They use generic clip art or stock images rather than photos of your child, your home, your school, your grocery store. Research shows this matters enormously.
A direct comparison study found that personalized social narratives were more effective than generic ones for all three participants tested. The researchers explained why: "photos and symbols from a person's real life may be easier to relate with compared to generic images." When your child sees a cartoon character going to the dentist, they have to abstract that image and map it onto their own experience. When they see themselves at their actual dentist's office, the connection is immediate and concrete.
Yet most social stories your SLP sends home feature generic illustrations because creating personalized visual content takes time most clinicians do not have.
### Paper Stories Cannot Be There When Needed
Remember the research finding that social stories work best when used immediately before the target situation? Now think about what paper-based social stories mean in practice. You need to remember to bring the printed pages. You need to find them. You need to read them in the car, at the doctor's office, in the grocery store parking lot, wherever the relevant situation is about to happen. You need them to survive being stuffed in a bag, dropped in a puddle, and torn by a sibling.
This is not a minor logistical issue. It is a fundamental design flaw. The most effective moment to use a social story is the exact moment when parents are most harried, most distracted, and least likely to have a stack of printed papers at hand.
### The Stories Go Stale
Your child's situation changes. The routine at school shifts. The doctor's office moves locations. A new sibling arrives. A new teacher starts mid-year. The social story that was created in October may not match your child's reality by December. But who updates it? Your SLP sees your child once or twice a week and may not know the details have changed. You know the details have changed but creating a new story feels like one more thing you cannot get to.
## What Actually Closes the Gap
The research points clearly toward solutions, even if the current system does not make them easy to implement.
### Make Stories Digital and Always Available
Every study comparing digital to paper social stories found digital delivery superior. In one study, 100% of children preferred digital formats. A pilot randomized controlled trial found that five daily digital sessions over just one week produced medium-to-large effect sizes for child understanding, perceived anxiety reduction, and closeness to story goals.
Digital social stories solve the access problem. They are on your phone, which is always with you. They can be pulled up in the car, in the waiting room, in the grocery store aisle, right before the moment they are needed. They do not get lost, torn, or forgotten in the therapy folder.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) includes a guided social story builder that lets you create personalized stories using AI-generated images of your child in their actual environments. Your SLP can help you identify what situations need stories, and you can build and access them on your phone whenever the moment arises.
### Personalize Everything
Generic social stories ask autistic children to do the thing their brain struggles with most: abstract and transfer meaning from one context to another. Personalized stories remove that cognitive demand entirely.
When the social story shows your child at their school, wearing their clothes, sitting in their actual classroom, the bridge between the story and reality is already built. Research confirms this: personalized photos are "concrete and meaningful" and help children understand content better than generic images.
This is where AI-generated imagery is changing the game. Instead of needing a photographer to visit every location and capture every scenario, tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) can generate personalized images that show your child doing each step of a social scenario in settings that match their real life.
### Use Stories at the Point of Need
Stop reading social stories at bedtime for situations that will happen at 10 AM. The research is clear: the strongest effects occur when stories are used immediately before the target situation. This means:
- Read the grocery store story in the parking lot before you go in
- Review the [doctor visit story](/blog/preparing-doctor-dentist-visits-autism-adhd) in the waiting room
- Go through the [birthday party story](/blog/birthday-parties-neurodivergent-children) in the car on the way there
- Look at the classroom story during the morning [transition](/blog/transition-strategies-autism)
Digital access makes this possible. Paper stories make it aspirational. This single change, shifting from "read it sometime today" to "read it right before," may be the highest-impact adjustment you can make.
### Let Your Child Help Build Them
A 2024 study in Frontiers in Digital Health found that consulting with the child during social story development improved outcomes. This makes sense. When a child participates in creating their own story, they have ownership over it. It is not something imposed on them. It is something they made.
For children with [demand avoidance profiles](/blog/demand-avoidance-pda-profile-autism-children), this is especially important. A social story that feels like another adult-directed demand will trigger avoidance. A social story the child helped create feels collaborative and empowering.
### Partner With Your SLP Differently
The current model is: SLP creates story, hands it to parent, hopes it gets used. A better model involves your SLP in a different role.
Ask your SLP to help you identify which situations need social stories rather than creating the stories themselves for use only in sessions. Ask them to coach you on the timing: when should each story be read relative to the situation? Ask them to review stories you have created at home to make sure the language and structure are effective. Ask them to help you build stories that address [emotional regulation](/blog/emotional-regulation-visual-supports) and social communication goals simultaneously.
This shifts the SLP from content creator to consultant, which is actually a more efficient use of their clinical expertise. They know the social communication goals. You know your child's daily life. The best social stories happen when both perspectives combine.
## The Bigger Picture: Why This Matters for Your Child
Social stories are not failing because the concept is wrong. The idea that autistic children benefit from structured, visual preparation for social situations is well-supported. Social stories are failing because the delivery system has not kept up with what the research says about how and when they need to be used.
Your child needs social stories that are personalized to their life, available at the moment of need, updated as their world changes, and consistent enough that the skills actually generalize beyond the therapy room. The gap between the social story your SLP reads during a session and the social story your child needs in the grocery store at 4:30 PM on a Wednesday is not a gap you can close with willpower. It is a systems problem that requires systems solutions.
The research on digital, personalized, parent-accessible social stories is pointing in a clear direction. Children prefer them. Parents become more competent with them. Implementation fidelity improves. And when stories are available at the point of need rather than locked in a therapy folder, the skills they teach have a fighting chance of showing up in real life.
Your child's SLP is doing important work. The social stories they create during sessions have value. But the work does not end when the session does. It begins again every time your child walks into a situation they need preparation for, and the tool that prepares them needs to be in your hand at that moment, not in a folder at home.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build personalized social stories with AI-generated images of your child, access them on your phone at the moment of need, and create the visual preparation that bridges the gap between therapy sessions and real life. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child social stories that work beyond the therapy room.
---
## Safe Foods and Autism: The Sensory Science Behind Food Refusal
Published: 2026-03-30
URL: https://vizyplan.com/blog/safe-foods-autism-sensory-science-food-refusal
Category: Strategies
Author: Justin Bowman
> Your autistic child is not just being picky. Research shows 64% have atypical oral sensory processing. Learn the neuroscience behind safe foods and what actually helps expand eating.
Your child eats five foods. Maybe seven on a good week. Chicken nuggets from one specific brand. Plain pasta with no sauce. White rice. Goldfish crackers. Maybe apple slices if you cut them exactly right. You have tried everything. You have hidden vegetables in smoothies. You have bribed with dessert. You have sat at the table for an hour waiting them out. You have cried in the kitchen after throwing away another untouched plate of food that took you thirty minutes to prepare.
And someone, probably a well-meaning relative, has told you: "They will eat when they are hungry."
They are wrong. And the science explains exactly why.
## This Is Not Picky Eating
The distinction matters because it changes everything about how you respond. Typical picky eating affects 13 to 50% of children and usually resolves by age six. The child might prefer certain foods but will eventually eat something when hungry enough. They might make faces at broccoli but they are not gagging at the sight of it.
Food selectivity in autism is fundamentally different. Research shows it affects 51 to 89% of autistic children, with a meta-analytic mean prevalence of 63.49%. A 2025 study published in Frontiers in Psychiatry tested what actually drives this selectivity and found something critical: food refusal in autistic children is predicted by sensory processing differences, specifically tactile, gustatory, and olfactory sensitivity. It was not predicted by behavioral profile, IQ, or autism severity.
That finding changes the entire conversation. Your child is not refusing food because they are being difficult or because you have given them too many choices or because you are not firm enough. Their nervous system is processing the sensory experience of eating differently than other children's, and foods that feel neutral or pleasant to you may feel genuinely threatening to them.
## What Eating Actually Feels Like for Your Child
Imagine sitting down to a meal where every bite is an unpredictable sensory event. The texture might be slightly different from last time. The smell is stronger than expected. The temperature is wrong. Something in the sauce changed. The foods are touching each other on the plate and the flavors might mix in your mouth.
For neurotypical eaters, these tiny variations go unnoticed. For an autistic child with [sensory processing differences](/blog/sensory-processing-daily-routines), each one registers as a potential threat.
### Texture Is the Biggest Factor
Research consistently identifies texture as the most powerful driver of food acceptance or refusal. A study of oral sensory processing found that 64% of autistic children showed atypical oral sensory sensitivity, compared to only 7% of typically developing children. Children with oral hypersensitivity refused 48.2% of foods offered, versus 33.2% for those with typical sensitivity.
This is why your child might eat crunchy crackers but refuse anything soft and mushy. Or eat smooth yogurt but gag on yogurt with fruit pieces. The texture profile of a food is not a minor detail. It is the primary information their nervous system uses to determine whether something is safe to eat.
### Taste and Smell Amplify Everything
Autistic children are more sensitive to taste and texture than their non-autistic peers. Bitter sensitivity may be heightened, which contributes to the near-universal vegetable refusal that drives parents to despair. Smells that seem mild to you can register as overwhelming or nauseating for your child.
Here is what makes this harder: these sensitivities are not static. They can fluctuate based on stress levels, [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies), fatigue, and overall sensory load. A food your child tolerated yesterday might be rejected today because their nervous system was already maxed out before they sat down at the table.
### Visual Appearance Matters More Than You Think
Mixed foods that look "chaotic" can trigger rejection before the food ever reaches your child's mouth. Color, shape, and presentation all influence acceptance. This is why brand-specific packaging matters so much. The same chicken nugget in a different brand's bag may look different enough to trigger refusal. It is not stubbornness. It is a nervous system that depends on visual predictability to feel safe enough to eat.
## Why Safe Foods Are Not the Problem
Safe foods are the foods your child returns to reliably. The ones that never trigger gagging, anxiety, or refusal. They tend to be predictable in every sensory dimension: same texture, same taste, same smell, same temperature, same appearance every single time.
Common patterns include beige and bland foods like plain pasta, crackers, and bread. Consistent-texture foods like smooth yogurt or crunchy chips, but never mixed textures. Brand-specific foods where even a slight recipe change causes rejection. Temperature-specific preferences where food must be room temperature or exactly warm, never varying.
These foods are not a failure of parenting. They are your child's neurological self-regulation strategy.
When the [sensory processing](/blog/sensory-processing-daily-routines) system is overwhelmed, the brain's threat detection center, the amygdala, becomes hyperactive. New textures feel threatening. Strong smells trigger nausea. Unexpected changes cause immediate rejection. Safe foods bypass all of that. They provide a known, regulated sensory experience that allows your child to actually nourish themselves instead of fighting their own nervous system through every bite.
Removing safe foods without building adequate replacements does not expand your child's diet. It takes away the only foods they can eat without distress. That is not a strategy. That is a crisis.
## When Food Refusal Becomes ARFID
Some autistic children's eating goes beyond selective into a clinical condition called Avoidant/Restrictive Food Intake Disorder, or ARFID. Unlike anorexia or bulimia, ARFID has nothing to do with body image. It is driven by sensory sensitivity, lack of interest in food, or fear of choking or vomiting.
A 2025 meta-analysis examining 21 studies and over 7,400 participants found that 11.41% of autistic individuals meet criteria for ARFID, which is 15 times higher than the rate in the general population. Among ARFID patients with a sensory sensitivity profile specifically, autism prevalence was 21 to 49%.
The difference between selective eating and ARFID comes down to impact. If your child eats fewer than 20 foods, shows significant nutritional deficiencies, loses weight or fails to gain appropriately, experiences anxiety or gagging around new foods, or avoids social eating situations entirely, ask their pediatrician about an ARFID evaluation. This is a diagnosable condition with evidence-based treatments, and naming it opens doors to support that "picky eating" advice never will.
## The Interoception Piece Nobody Talks About
Here is something that makes "they will eat when they are hungry" not just wrong but potentially dangerous for some autistic children. Many autistic individuals have differences in interoception, the sensory system that detects internal body signals like hunger, fullness, thirst, and pain.
A child with interoceptive differences may not feel hungry until their energy has crashed. They may not be able to distinguish hunger from nausea or anxiety. They may feel something uncomfortable in their stomach and interpret it as a reason to avoid food rather than a signal to eat.
Research shows that the brain regions involved in interoception, the insula, brainstem, thalamus, and vagal pathways, show altered connectivity patterns in autistic individuals. This means the "hunger drives eating" assumption that underlies most feeding advice literally does not apply to a child whose brain processes internal signals differently.
If your child's therapist or pediatrician has ever suggested waiting them out, share this information with them. A child who cannot reliably sense hunger will not eat because you removed their safe foods and hoped biology would take over.
## What the Research Says Does Not Work
The most common advice parents receive about food refusal is also the most harmful when the refusal is sensory-based.
**"They will eat when they are hungry."** No. Children with ARFID may literally not eat even when starving. Children with interoceptive differences may not register hunger cues. Hunger does not override sensory overwhelm. This advice, applied to the wrong child, can lead to dangerous weight loss and nutritional crises.
**Forcing or pressuring.** Feeding specialists are unanimous: force-feeding increases resistance to trying new foods. Pressure at mealtimes raises anxiety, which further restricts the foods a child will accept. You cannot incentivize someone past sensory overwhelm.
**Hiding vegetables in food.** If your child discovers hidden food in something they trusted, you have not expanded their diet. You have destroyed the predictability that made their safe food feel safe. They may stop eating that food entirely because they can no longer trust it. The short-term nutritional gain is not worth the long-term trust damage.
**Reward and punishment systems.** Compliance-based feeding approaches may produce short-term results but increase long-term food anxiety. For children with [demand avoidance profiles](/blog/demand-avoidance-pda-profile-autism-children), even well-intentioned reward charts can make eating feel like a demand, triggering the avoidance response you are trying to reduce.
## The Nutritional Reality You Need to Know
Food selectivity in autism has real nutritional consequences that require monitoring, not ignoring. A 2025 study of 241 autistic children found that 36.5% had vitamin D deficiency and 37.7% had suboptimal iron stores. Co-occurring deficiencies were present in 70% of food-selective autistic children.
The most commonly low nutrients include vitamin D, iron, B vitamins including folate and B12, calcium, vitamin A, fiber, and protein. These deficiencies are not minor. Iron deficiency affects cognition and behavior. Vitamin D deficiency impacts bone health and immune function. B vitamin deficiencies affect neurological development.
This does not mean you should panic. It means you should ask your child's pediatrician for comprehensive bloodwork including a complete blood count, iron panel with ferritin, vitamin D levels, and a basic metabolic panel. Many deficiencies can be addressed with targeted supplements while you work on expanding your child's diet through appropriate therapeutic approaches. Knowing what is actually low prevents both over-supplementing and under-treating.
## What Actually Works: Evidence-Based Approaches
The approaches that help autistic children expand their eating share a common philosophy: respect the child's sensory experience, build trust, and move at the child's pace.
### Food Chaining: Building Bridges From Safe Foods
Food chaining starts with what your child already eats and introduces new foods that share sensory properties with their safe foods. The progression is gradual and intentional.
If your child eats a specific brand of chicken nuggets, the chain might progress to a different brand of nuggets, then to frozen chicken strips, then to homemade breaded chicken, then to lightly breaded chicken, then eventually to plain chicken. Each step changes only one sensory variable at a time.
One clinical study showed that selective eaters increased their median accepted foods from 5 to 20.5 after three months of food chaining therapy. That kind of expansion is meaningful for a child who was eating fewer than ten foods.
The key is patience. Research shows it can take an autistic child 20 to 30 exposures to accept a new food. "Exposure" does not mean eating it. It means seeing it on the table, smelling it, touching it, licking it, and eventually tasting it, all without pressure. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) can help you build [visual mealtime routines](/blog/mealtime-strategies-picky-eating-autism-adhd) that include these gradual exposure steps, making the process predictable for your child rather than surprising.
### The SOS Approach: Six Phases of Trust
The Sequential Oral Sensory approach, developed by Dr. Kay Toomey over 35 years of clinical work, takes children through six progressive phases: visual tolerance, interaction with food, smelling, touching, tasting, and finally eating. A 2024 feasibility study found significant improvements in children's tolerance of new foods, utensil use, and stress-coping strategies during mealtimes.
The philosophy behind SOS is "building safe, trusting feeding relationships." The child is never forced. The child sets the pace. The therapist and parent create conditions where trying food feels safe rather than threatening.
### Olfactory Familiarization: Start With Smell
Research shows that repeated exposure to food smells, without any eating involved, can make foods more acceptable. In one study, 68% of children selected foods with familiarized odors over unfamiliar ones. If your child refuses a new food on sight, try having it present at the table for several meals without any expectation that they interact with it. Let the smell become familiar. Familiarity reduces threat.
### Occupational Therapy for Feeding
Occupational therapists address the sensory, motor, and environmental components of eating that other providers may miss. They can evaluate whether your child's food refusal involves oral motor difficulties like chewing or swallowing challenges, sensory processing issues that need specific accommodations, or environmental factors at mealtimes that are contributing to distress.
The best outcomes come from multidisciplinary teams combining OT, speech-language pathology, nutrition, and psychology. If your child's eating is severely restricted, ask for a referral to a feeding clinic rather than trying to manage it with a single provider.
## The Gut Connection That Compounds Everything
Up to 70% of autistic children experience gastrointestinal symptoms including constipation, abdominal pain, diarrhea, and reflux. A 2025 review in Nutrients found that restricted diets alter the gut microbiome, and an altered microbiome can worsen both GI symptoms and autism-related behaviors through the gut-brain axis. This creates a vicious cycle: restricted eating changes the gut, a disrupted gut causes more discomfort, and more discomfort leads to further food restriction.
If your child complains of stomach pain, shows signs of constipation, or seems to have increased behavioral challenges after eating certain foods, a pediatric gastroenterologist can evaluate whether GI issues are contributing to their food refusal. Treating the gut problems can sometimes open the door to expanding the diet.
## Making Mealtimes Less Miserable Right Now
While you pursue professional feeding support, there are changes you can make today that reduce mealtime stress for everyone.
**Always include at least one safe food at every meal.** Your child should never sit down to a table where nothing feels safe. Having their reliable food present reduces anxiety enough that they might actually notice the other foods on the table.
**Reduce the demand quality of mealtimes.** Use indirect language. "The food is here if you want it" feels different from "time to eat your dinner." For children with [demand avoidance](/blog/demand-avoidance-pda-profile-autism-children), even sitting down to eat can feel like a demand. Casual grazing stations where food is available but eating is not required can reduce the pressure entirely.
**Offer choices within acceptable options.** "Would you like the blue plate or the green plate?" gives your child a sense of control without changing what is served. [Choice boards](/blog/choice-boards-empowering-decisions) work well for mealtimes, allowing your child to select from a visual menu of options.
**Address the sensory environment, not just the food.** Bright overhead lights, background noise from the TV, a crowded table, and an uncomfortable chair all add to the sensory load your child is managing before they even look at the food. Dimming lights, reducing noise, and ensuring comfortable seating can make a surprising difference.
**Track patterns.** Document which foods are accepted, which are refused, and what conditions surrounded each meal. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you [track emotions and activities](/blog/tracking-emotions-activities-neurodivergent-children) throughout the day, which can reveal whether mealtime refusal correlates with specific earlier stressors, [transitions](/blog/transition-strategies-autism), or sensory events. The pattern is often more revealing than the individual mealtime.
## What Your Child Needs You to Understand
Your child is not choosing this. They are not manipulating you. They are not being spoiled. Their nervous system is processing the sensory experience of food in a way that makes most eating feel unsafe, unpredictable, or genuinely distressing. The five foods they eat are not a sign of your failure. They are the five foods their brain has determined will not hurt them.
Sixty-four percent of autistic children have atypical oral sensory processing. Fifty-one to 89% have significant food selectivity. Up to 70% have GI issues compounding the problem. Your child is not an outlier. They are navigating a neurological reality that the majority of autistic children share.
The path forward is not force, shame, or waiting them out. It is understanding the sensory science, working with professionals who respect it, building slowly from safe foods outward, and protecting the trust that makes your child willing to try at all.
Every food your child eats today is a food their nervous system has approved. That approval was hard-won. Honor it while you build, slowly and carefully, toward more.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build visual mealtime routines, track food patterns alongside emotions and daily activities, and create the predictable structure that makes eating feel safer for your child. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring calm to your family's hardest meals.
---
## When ABA Therapy Gets Cut: What Parents Can Do at Home
Published: 2026-03-29
URL: https://vizyplan.com/blog/aba-therapy-cuts-what-to-do-at-home
Category: Strategies
Author: Justin Bowman
> ABA therapy is being cut across the country. If your child lost hours or is on a waitlist, here is what the research says you can do at home to maintain progress.
You got the letter. Or maybe it was a phone call. Your child's ABA hours are being reduced. The provider is dropping your insurance. The waitlist is nine months long. Or the session copay just became something your family cannot absorb.
However it happened, you are now standing in the gap between what your child needs and what the system is willing to provide. And the question keeping you up at night is: what happens to my child's progress while we figure this out?
You are not alone in this. Across the country, families are losing access to the therapy their children depend on. And while the crisis is real, so is the research showing that parents can do more at home than most professionals give them credit for.
## What Is Happening to ABA Therapy Right Now
The numbers tell a story that explains why your family might be caught in the middle. State Medicaid spending on ABA therapy has exploded in recent years. North Carolina saw payments jump from $122 million in 2022 to a projected $639 million in 2026. Nebraska experienced a 1,700% spending increase. Indiana saw 2,800%. States that were already stretched thin are now pulling back hard.
At least eight states have implemented or proposed cuts to ABA reimbursement rates, imposed new hour caps, or added prior authorization requirements that slow access to a crawl. Nebraska cut provider payment rates by 28 to 79% depending on the service type and capped ABA at 30 hours per week. Indiana proposed a lifetime allocation of just 4,000 total ABA hours per child. Colorado added prior authorization requirements while auditing $77.8 million in improper ABA payments.
The federal picture is even more concerning. The One Big Beautiful Bill Act, signed into law in 2025, cuts federal Medicaid spending by an estimated $1.02 trillion by 2034. Advocates warn that states facing this loss of funding will cut optional services like home and community-based supports first, the very category that includes many autism services.
Meanwhile, fraud investigations in multiple states have given lawmakers cover to cut spending broadly. Minnesota has 85 open investigations into autism providers. The FBI raided two providers there. Wisconsin uncovered $18.5 million in improper payments. Indiana found over $56 million. The fraud is real, and families who depend on legitimate services are paying the price for providers who abused the system.
At the same time, autism diagnoses continue to rise. The CDC now estimates [1 in 31 children](/blog/1-in-31-autism-diagnosis-rates-daily-life) has autism, up from 1 in 36 just two years ago. More children need services at the exact moment those services are being cut.
## What Happens When Therapy Stops
If you are worried about regression, the worry is justified. The COVID-19 pandemic provided an unintentional study of what happens when therapy services are suddenly disrupted, and the data is sobering.
During pandemic shutdowns, 79% of parents reported their child's therapies were disrupted. Over 60% of children experienced interruptions in ABA therapy that led to halted developmental progress and regression. Parents reported increases in meltdowns (61%), stimming behaviors (65%), aggression toward family members (46%), and toileting regression (26%).
The disruption affected everything: sensory-motor development, cognitive skills, sleep, behavior, and social interactions in approximately half of children with special needs. And recovery took significant time for both children and families to return to previous levels.
This is not meant to frighten you. It is meant to validate what you already suspect: therapy gaps matter, and the instinct to do something at home is exactly right.
## The Research Says Parents Can Do This
Here is what most families are never told: parent-implemented interventions have a strong research base. A meta-analysis of 51 randomized controlled trials involving nearly 3,000 children found that parent-delivered interventions produced a moderately strong effect size of 0.553 across all measured outcomes.
What does that mean in plain language? It means that parents who learned specific strategies and applied them at home achieved meaningful improvements in their children's social skills, communication, and behavior. Not as a replacement for professional therapy, but as a genuine, research-backed complement to it, or a bridge when professional services are unavailable.
The improvements were consistent across domains. Social skills and positive behavior showed an effect size of 0.603. Language and communication showed 0.545. Reduction in challenging behaviors showed 0.519. These are not anecdotal claims. They are peer-reviewed findings from the largest meta-analysis of parent-implemented autism interventions ever conducted.
## Strategies You Can Start Using Today
The approaches that work best at home are not simplified versions of what therapists do in clinical settings. They are naturalistic strategies designed to be woven into the fabric of daily life. Researchers call them Naturalistic Developmental Behavioral Interventions, and they are built on one principle: children learn best when teaching happens within activities they are already motivated to engage in.
### Follow Your Child's Lead
This is the foundation of everything that follows. Instead of setting up structured teaching sessions, watch what your child gravitates toward and use those moments as teaching opportunities.
If your child reaches for a snack, that is a communication opportunity. Instead of handing it over, pause. Wait for them to make eye contact, point, vocalize, or use whatever communication system they have. Then respond immediately. The snack becomes the natural reinforcement for the communication attempt.
If your child is playing with trains, join them on the floor. Imitate what they are doing. Add a small variation. If they line up trains, you line up trains and then gently crash one into the line. Their reaction, whatever it is, becomes the next teaching moment.
### Embed Teaching in Daily Routines
Every routine your family already has contains dozens of natural teaching opportunities. Getting dressed involves sequencing, motor planning, [choice-making](/blog/choice-boards-empowering-decisions), and communication. Mealtime involves requesting, turn-taking, and sensory exploration. Bath time involves following directions, body awareness, and transitions.
The key is identifying one or two skills you want to target and looking for places they naturally fit into what you are already doing. You do not need to add therapy sessions to your day. You need to see the therapy potential in the day you already have.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build [visual routines](/blog/visual-schedules-for-autism) for these daily activities with personalized images of your child doing each step. When your child can see the sequence, they can participate more independently, which creates more natural opportunities for learning and communication.
### Use Visual Supports as Your Backbone
Visual supports are one of 28 evidence-based practices for autism recognized by the National Professional Development Center on ASD. They are effective across age groups from preschoolers through high schoolers, and the research on home-based visual support interventions shows statistically significant improvements in both parent-reported quality of life and parent confidence.
Here is why visual supports matter especially when therapy hours are cut: they provide structure and predictability that your child's therapist was previously providing during sessions. A [visual schedule](/blog/visual-schedules-for-autism) for the morning routine reduces the number of verbal prompts you need to give, which reduces conflict and builds independence. A [first-then board](/blog/first-then-boards-guide) helps your child understand what is expected before they can access a preferred activity. A [social story](/blog/social-stories-autism-guide) prepares them for new situations the way a therapist might have done during session time.
These are not consolation prizes. Visual supports reduce problem behaviors, improve communication, lead to smoother [transitions](/blog/transition-strategies-autism), and help children maintain skills during service disruptions. Research consistently shows that when children know what to expect and what comes next, anxiety decreases and their capacity for learning increases.
### Practice Generalization Across Settings
One of the most important things therapy provides is teaching skills in a way that transfers to other environments. When therapy hours are cut, the risk is not just that new skills stop being taught. It is that existing skills start to narrow because they are only being practiced in one context.
You can counteract this by deliberately practicing skills in different settings. If your child learned to request items during therapy, practice requesting at the grocery store, at the park, and at a relative's house. If they learned to follow a two-step direction, practice that direction in the kitchen, in the bedroom, and outside. Each new setting strengthens the neural pathways that make the skill stick.
Involve other family members too. When multiple people use the same strategies and respond consistently, children generalize faster. This is something therapy sessions, which typically involve one therapist, struggle to replicate.
### Reinforce Attempts, Not Just Perfection
This is where many parents unintentionally create pressure that backfires. When you are anxious about your child losing skills, it is natural to raise the bar for what counts as success. But research on naturalistic interventions emphasizes the opposite: reinforce approximations.
If your child is working on saying "more" and they produce something that sounds vaguely like it, that counts. Respond with enthusiasm and give them what they asked for. If they are working on [taking turns](/blog/teaching-turn-taking-sharing-neurodivergent-children) and they wait for three seconds instead of the full turn, acknowledge the effort. Progress is not linear, and maintaining motivation matters more than achieving perfection on any given day.
### Track Progress So You Can See It
When therapy is consistent, your BCBA tracks data and shows you progress over time. When therapy is reduced, that tracking often disappears, and without it, every hard day feels like proof that everything is falling apart.
Start your own simple tracking. Note which skills your child uses independently, which ones need prompting, and which ones seem to be fading. Track [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) alongside daily activities. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you track emotions and activities throughout the day, giving you data on what is working and what needs attention, the same kind of pattern recognition your therapist was providing.
## Know Your Rights and Fight Back
While you are building support at home, do not give up on getting your child's therapy restored. The law is often on your side, even when it does not feel like it.
### The Parity Law Is Your Strongest Tool
The Mental Health Parity and Addiction Equity Act requires insurance companies to cover behavioral health care, including ABA, at the same level as physical health care. A total ABA exclusion almost certainly violates this law. Autism is the only diagnosis with its own dedicated working group at the federal Employee Benefits Security Administration. That tells you how significant parity enforcement is in this space.
All 50 states plus the District of Columbia have enacted autism insurance mandates requiring coverage for ABA therapy. Despite this, mental health claim denials occur at rates 85% higher than medical claims. The mandates exist. The enforcement is where the fight happens.
### Appeal Strategically
Research on insurance appeals reveals specific strategies that dramatically improve success rates. Appeals that document parity violations, showing that ABA is being restricted more than comparable medical treatments, achieve success rates 3.2 times higher than appeals focusing solely on medical necessity. Appeals that include detailed provider advocacy letters achieve approval rates of 64% compared to 29% with minimal documentation. Citing specific laws achieves success rates 2.1 times higher than appeals without legal references.
If your child's hours were cut or coverage was denied:
- Request the denial in writing with the specific clinical rationale
- Ask your child's provider to write a detailed letter explaining medical necessity
- Document any regression that occurred after services were reduced
- File an internal appeal citing your state's autism insurance mandate and the federal parity law
- If the internal appeal is denied, file an external appeal for independent review
- Contact your state insurance commissioner if you believe the denial violates parity requirements
### Explore Every Alternative
While you appeal, explore every other pathway to services. Early intervention programs for children under three are federally funded and typically free. [School-based services through an IEP](/blog/504-plan-vs-iep-neurodivergent-child) are available at no cost for children three and older. Many universities with behavior analysis programs offer reduced-rate or free ABA services staffed by supervised students. Telehealth ABA has been shown to achieve similar outcomes at lower cost compared to in-home therapy and eliminates geographic barriers.
## A Honest Word About ABA Itself
If you are reading this during a moment when your child's ABA therapy has been cut, you deserve a complete picture. ABA is endorsed by the American Academy of Pediatrics and has the largest evidence base of any autism intervention. It has also evolved significantly from its origins in the 1960s, when early practitioners used methods that would be considered unacceptable today.
Modern ABA is more child-led, play-based, and focused on positive reinforcement than the rigid, compliance-driven approach that still shapes many people's understanding of the field. Naturalistic approaches like Pivotal Response Treatment and the Early Start Denver Model represent how the best practitioners work today.
At the same time, autistic self-advocates have raised important concerns about ABA that deserve your consideration. Some adults who received ABA as children report that the emphasis on appearing neurotypical, suppressing stimming, forcing eye contact, came at a psychological cost. The autistic community has pushed the field toward what many now call neurodiversity-affirming practices that teach functional skills while respecting who the child is.
This matters for what you do at home. The strategies in this article are not about making your child look neurotypical. They are about building communication, independence, and [self-advocacy skills](/blog/teaching-self-advocacy-skills-neurodivergent-child) that serve your child on their terms. When you follow your child's lead, reinforce their attempts, and use visual supports to reduce anxiety, you are already practicing the most progressive version of what the field has to offer.
## What Your Family Needs to Hear
Losing therapy hours is terrifying. The regression data is real and the fear of losing ground keeps parents up at night. But the research on parent-implemented interventions is equally real, and it says something important: you are not helpless.
You are not a replacement for a trained BCBA. Nobody is asking you to be. But you are the person who is with your child during every meal, every bath, every car ride, every bedtime. You see patterns a therapist who visits for a few hours a week will never see. You know what motivates your child better than any assessment can capture.
A meta-analysis of nearly 3,000 children confirmed that when parents learn specific strategies and apply them consistently, children make meaningful progress. Visual supports are evidence-based. Naturalistic teaching works. Structured routines [build independence](/blog/building-independence-visual-supports).
Fight for your child's services. Appeal the denial. Explore every alternative. And while you do, know that what you are doing at home is not just "filling time until therapy comes back." It is research-backed intervention in its own right, delivered by the person who knows your child best.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build visual routines that maintain your child's skills, track emotional and behavioral patterns that reveal what is working, and create the structured consistency your child needs when professional therapy is reduced. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bridge the gap with tools designed for families in exactly this situation.
---
## Demand Avoidance and the PDA Profile: What Parents Need to Know
Published: 2026-03-28
URL: https://vizyplan.com/blog/demand-avoidance-pda-profile-autism-children
Category: Strategies
Author: Justin Bowman
> When your child resists everything, even things they want to do, it may not be defiance. Learn what the PDA profile looks like, why traditional strategies backfire, and what actually helps.
You have tried everything. The visual schedule is on the wall. The timer is set. You used your calmest voice. You offered choices. And your child still will not brush their teeth. Not because they are being defiant. Not because you are doing something wrong. But because the very act of being asked to do something, anything, triggers a wave of panic they cannot control.
You have read the parenting books. You have sat through the therapy sessions. You have tried reward charts, first-then boards, countdowns, and every transition strategy recommended by well-meaning professionals. Some of them worked for a day. Maybe a week. Then your child figured out the system and the whole thing fell apart. Again.
If this sounds like your life, you are not failing. You may be parenting a child with a demand avoidance profile, sometimes called PDA, and it changes everything about how support needs to look.
## What Is PDA and Where Did It Come From
PDA stands for Pathological Demand Avoidance, a term first used in 1983 by Professor Elizabeth Newson, a developmental psychologist at the University of Nottingham. She noticed a group of children who came in for autism assessments but did not quite fit the expected patterns. They were socially aware. They could make eye contact. They were imaginative. But they shared one overwhelming characteristic: an intense, pervasive need to avoid everyday demands.
Newson described these children as having "an obsessional avoidance of the ordinary demands of everyday life" and an overwhelming drive to maintain a sense of control. In 2003, she published her findings in the journal Archives of Disease in Childhood, based on a cohort of 150 children seen over 25 years, arguing that PDA should be recognized as a distinct profile within the autism spectrum.
Today, many families and clinicians use the term PDA profile to describe a pattern of demand avoidance that goes far beyond what you see with typical childhood resistance. Some autistic self-advocates have proposed the alternative name "Pervasive Drive for Autonomy," reframing the same behaviors through a lens of neurodivergent identity rather than pathology.
It is worth noting that PDA is not currently listed as a formal diagnosis in the DSM-5 or ICD-11. In the United Kingdom, where the concept originated, some clinicians diagnose "Autism Spectrum Disorder with a PDA profile." In the United States, awareness is growing through parent advocacy and social media, but formal clinical recognition has been slower to follow. A 2024 scoping review published in Frontiers in Education found only 22 studies on PDA across all research, with 21 originating from the UK. The research base is small, but for families living this every day, the description fits in a way nothing else has.
## How Demand Avoidance Is Different from Defiance
This is the part that changes everything once you understand it. A child who is being defiant is making a conscious choice to resist authority. They know what is expected. They can do it. They are choosing not to, often out of anger, frustration, or a desire to test limits.
A child with a PDA profile is not choosing anything. Their nervous system is responding to a perceived threat. Every demand, no matter how small or how kindly delivered, activates the same fight-or-flight response you would feel if someone told you to jump off a cliff. The demand itself becomes the threat. Not the content of the demand. Not the person making it. The fact that someone expects something of them.
This is why PDA looks so different from what most parents and professionals expect. Your child might be fine playing independently, and then the moment you say "time to eat," a meal they actually want, they spiral. They might beg for a trip to the park and then refuse to put on shoes the instant the outing becomes a plan. They might desperately want to do their homework and sit frozen in front of it, unable to start, because now it is an expectation rather than a choice.
Dr. Cynthia Martin, a clinical psychologist at the Child Mind Institute, explains it this way: "Any external demand that is coming from somebody else, or that the person perceives is coming from another person, that generates a lot of internal discomfort, which leads to the avoidance."
This is fundamentally different from Oppositional Defiant Disorder, or ODD, which is sometimes confused with PDA. ODD involves deliberate resistance, often directed at specific people or authority figures, rooted in anger or frustration. PDA is anxiety-driven and pervasive across all settings, all people, and all types of demands, including ones the child places on themselves. Perhaps the most important clinical distinction: the strategies that work for ODD, structured consequences, firm boundaries, reward-and-punishment systems, actively make PDA worse.
## The Signs That Traditional Strategies Are Not Working
If your child has a PDA profile, you have probably noticed a pattern. Things that "should" work, based on everything you have read about [autism supports](/blog/visual-schedules-for-autism) and behavioral strategies, either fail or backfire.
**Reward charts lose their power fast.** Sticker charts, token systems, and point-based rewards might generate initial enthusiasm. But within days or weeks, the system itself becomes a demand. Earning stars means complying, and compliance is the thing their nervous system is fighting against. Dr. Martin notes: "When we are only taking a heavy behavioral approach, where it is very reward-and-consequence driven, we often see treatment effects that are high initially, but then taper off over time."
**Firm boundaries trigger escalation, not compliance.** Where a neurotypical child might push back and then comply when they see you are serious, a PDA child reads escalation as a bigger threat and responds with bigger avoidance. What started as ignoring becomes arguing, then crying, then a full meltdown. They are not testing you. They are panicking.
**Predictable routines become predictable demands.** One of the most confusing parts of PDA for parents of autistic children is that routine and structure, normally a cornerstone of autism support, can become the enemy. Once a visual schedule becomes "the thing I have to do every morning," it stops being helpful and starts being another source of anxiety.
**Praise feels like pressure.** You would think a child would welcome recognition for doing something well. But for a PDA child, "Great job brushing your teeth!" can register as an expectation to do it again tomorrow. Even positive attention can feel like a demand for repeat performance.
**They avoid things they genuinely want to do.** This is the hallmark that confuses everyone. Your child asks to go swimming. You start getting ready. They refuse to put on a swimsuit. They are not being difficult. The thing they wanted became a series of demands the moment it became a plan, and their nervous system shut it down.
## What Demands Actually Look Like Through a PDA Lens
Most people think of demands as instructions. "Clean your room." "Do your homework." "Eat your vegetables." But for a child with a PDA profile, the category of "demand" is far broader than anyone expects.
**Direct demands** are the obvious ones. "Brush your teeth." "Put on your shoes." "Come to the table." These are the requests most parents try to soften first, and they are often the easiest to work around with alternative strategies.
**Indirect demands** are trickier. Questions can feel like demands because they require a response. "What do you want for lunch?" forces a decision. Compliments can feel like demands because they set expectations. Transitions of any kind create demands because they require shifting from what is happening now to what needs to happen next. Even time itself is a demand. Knowing that something is scheduled for 3:00 PM means having to be ready at 3:00 PM, and that alone can trigger avoidance hours in advance.
**Internal demands** are the ones that catch families off guard the most. Hunger is a demand because it requires action. Needing the bathroom is a demand. Feeling tired is a demand. A child may genuinely want to eat their favorite food and find themselves unable to do it because the wanting has turned into a need, and the need has become a demand they cannot meet. This is not stubbornness. It is a nervous system that treats even self-generated expectations as threats.
## What Actually Helps: Strategies That Work With PDA
The PDA Society in the UK developed a framework called PANDA that captures the core principles of effective support for demand-avoidant children. It stands for Pick battles, Anxiety management, Negotiate and collaborate, Disguise demands, and Adapt flexibly. These are not techniques you apply rigidly. They are a way of thinking about your child that shifts the entire dynamic.
### Pick Your Battles Ruthlessly
Every rule you enforce adds to your child's internal demand load. Ask yourself: does this actually matter right now? If the answer is no, let it go. Your child wearing mismatched socks to school is not worth the meltdown that comes from insisting they change. Eating cereal for dinner is not a nutritional crisis. Doing homework on the floor instead of at a desk is fine.
This is not permissive parenting. It is strategic parenting. You are preserving your child's capacity for the demands that genuinely matter, like safety, hygiene, and getting to school, by removing the weight of demands that do not.
### Lower Anxiety as the First Priority
If your child is already dysregulated, no strategy will work. The first job is always to bring the [emotional temperature](/blog/emotional-regulation-visual-supports) down. Speak slowly. Use a calm, even tone. Keep your body language soft and open. Do not stand over them. Get on their level. Give them space if they need it. Wait. The demand can come later, after the nervous system has calmed.
A 2021 meta-analysis found that 46% of caregivers of autistic children show significant stress levels, with 44.6% reporting anxiety. When your own nervous system is activated, your child's activation increases. [Managing your own regulation](/blog/caregiver-burnout-parents-neurodivergent-children) is not a luxury. It is part of the strategy.
### Use Declarative Language Instead of Commands
This is one of the most powerful shifts you can make. Declarative language shares information or makes observations rather than giving instructions. It invites the child to respond rather than demanding they comply.
Instead of "Put your shoes on," try "I notice it is chilly outside today." Instead of "Brush your teeth," try "The toothbrush is on the counter." Instead of "Time to leave for school," try "I wonder what we need before heading out." Instead of "Come eat dinner," try "Dinner is on the table."
You are still communicating the same information. But you are removing the demand wrapper. The child gets to process the information and choose to respond rather than feeling forced into compliance. This does not work every time. Nothing works every time with PDA. But it works more often than direct commands.
### Disguise and Depersonalize Demands
When a demand does need to happen, make it feel like it is coming from somewhere other than you. Use timers, visual cues, or external rationales. "The schedule says it is time for bath" feels different from "I need you to take a bath." The schedule is the authority, not you. That small shift in perceived source can make the difference between cooperation and collapse.
Humor works surprisingly well. "I bet you cannot get your pajamas on before I count to twenty" turns a demand into a challenge. Roleplay works too. "Your teddy bear needs to show you how to brush teeth tonight" puts the demand on a character instead of the child.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) can serve as that external reference point. When the app shows the next step in a routine rather than a parent giving a verbal instruction, the demand feels less personal. The key is that the child participates in building the routine so it feels collaborative rather than imposed.
### Collaborate, Do Not Dictate
Dr. Ross Greene, developer of the Collaborative and Proactive Solutions model, built his entire approach around one principle: "Kids do well if they can." When children are not meeting expectations, it is because they lack the skills or capacity to do so in that moment, not because they lack motivation.
His approach has three steps. First, empathize: listen to your child's concerns about the situation without judgment. Second, define the problem: share your concern calmly and clearly. Third, invite collaboration: work together on a solution that addresses both concerns. This works well for PDA because it directly honors the child's core need for autonomy and control. You are not imposing a solution. You are building one together.
### Adapt Constantly
Here is the part that exhausts parents: what works today may not work tomorrow. A strategy that successfully got your child through morning routines for two weeks can suddenly become a demand itself once it becomes an expectation. You may need to rotate approaches, change the order of routines, use different language, or take a completely different route to the same outcome.
This is not a failure of the strategy. It is a feature of PDA. Flexibility is not optional. It is the strategy.
## Rethinking Visual Supports for Demand Avoidant Children
If you have tried [visual schedules](/blog/visual-schedules-for-autism) and they did not work, it may not be that visual supports are wrong for your child. It may be that the visual supports were presented as a fixed list of demands rather than a flexible framework.
Traditional visual schedules tell a child "here is what you are doing, in this order, and you need to do all of it." For most autistic children, that predictability is calming. For a PDA child, it is a wall of demands staring them in the face.
Adapted visual supports for PDA look different. They show options rather than requirements. They invite the child to participate in planning. They use "here is what is happening today" language rather than "here is what you need to do." They include choice points where the child selects what comes next. They can be rearranged, modified, or simplified on the fly.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) works well for this approach because routines can be customized, reordered, and updated quickly. When your child helps build their own visual routine using personalized AI-generated images of themselves doing each step, the routine feels like theirs rather than something imposed on them. That sense of ownership can be the difference between avoidance and engagement.
## The Misconceptions That Hurt Families Most
Parents of PDA children face a unique form of isolation. The behavior looks like defiance to outsiders, which means the advice you get from family, friends, and sometimes even professionals centers on being firmer, more consistent, more authoritative. Exactly the approach that makes things worse.
**"They are manipulating you."** PDA behaviors can look strategic. Your child may use distraction, negotiation, excuses, even charm to avoid demands. But these are not manipulation tactics. They are survival strategies. A child drowning does not "manipulate" the water. They do whatever they can to stay afloat. Your child is doing the same with their nervous system.
**"You just need firmer boundaries."** This advice comes from people who have never watched a child unravel because they were asked to put on socks. More pressure does not create more compliance with PDA. It creates more panic, bigger meltdowns, and deeper withdrawal.
**"They will grow out of it."** A 2016 study using the DISCO diagnostic interview found that 44% of individuals with PDA features showed improvement over time. That is encouraging, but it also means more than half carry these traits into adolescence and adulthood. PDA is not a phase.
**"It is bad parenting."** Research consistently shows that demand avoidance is neurologically based. You did not cause this. The fact that you are reading an article like this, trying to understand your child better, is evidence of exactly the opposite.
## When PDA and Other Profiles Overlap
Demand avoidance does not exist in isolation. Many children with PDA profiles also have [co-occurring ADHD](/blog/autism-and-adhd-co-occurring-children), [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies), or [sensory processing differences](/blog/sensory-processing-daily-routines) that compound the challenges.
A child with PDA and ADHD may have even more difficulty with transitions because both their demand sensitivity and their executive function challenges are working against them. A child with PDA and sensory sensitivities may avoid getting dressed not only because getting dressed is a demand but because the clothing itself is intolerable.
Understanding which challenges are demand-related and which stem from other aspects of your child's neurodivergent profile helps you target the right strategies. The demand avoidance piece needs low-demand, autonomy-supporting approaches. The [sensory piece](/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children) needs sensory accommodations. The executive function piece needs scaffolding and visual supports. Most PDA children need all of these working together.
## Finding Professional Support That Understands PDA
Not every therapist or clinician will be familiar with PDA. In the United States especially, the concept is still gaining recognition. When looking for support, ask potential providers directly: "Are you familiar with the PDA profile? How does it change your approach?"
A provider who understands PDA will talk about flexibility, collaboration, and autonomy rather than compliance and consequences. They will not suggest that you "just need to be more consistent" or recommend a rigid behavioral program. They will recognize that [traditional approaches](/blog/types-of-therapy-neurodivergent-children) need significant adaptation for demand-avoidant children.
If your child has been diagnosed with ODD and the recommended treatment is not working, consider seeking an evaluation specifically for autism with a PDA profile. The strategies that help these two presentations are fundamentally different, and using the wrong approach can do more harm than doing nothing at all.
## What This Means for Your Family Right Now
Understanding PDA does not make the daily struggles disappear. Your mornings will still be hard. Transitions will still be challenging. There will still be days when you cannot get your child to do the thing they desperately need to do.
But understanding what is driving the behavior changes how you respond to it. Instead of thinking "my child is fighting me," you start thinking "my child's nervous system is in threat mode." Instead of adding more structure, you look for ways to reduce perceived demands. Instead of feeling like a failure when strategies stop working, you adapt and try something different, knowing that flexibility is the strategy.
One mother in a 2025 study published in Discover Mental Health described the moment she learned about PDA: everything suddenly made sense. Years of confusion, guilt, and strategies that should have worked but did not finally had an explanation. That moment of understanding does not fix the practical challenges. But it changes the emotional landscape of parenting entirely.
Your child is not broken. They are not defiant. They are not choosing to make your life difficult. They have a nervous system that perceives demands as threats, and they need you to be the person who understands that when no one else does.
You are already that person. You are here. You are learning. And that matters more than any strategy in any book.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create flexible visual routines, track patterns that reveal your child's triggers, and build supports that feel collaborative rather than controlling. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and discover what happens when visual supports are built with your child, not just for them.
---
## Autism and Sleep: Why Your Child Cannot Sleep and What Actually Helps
Published: 2026-03-28
URL: https://vizyplan.com/blog/autism-and-sleep-problems-what-actually-helps
Category: Strategies
Author: Justin Bowman
> Up to 80% of autistic children have sleep problems. Learn what the science says about why, what actually works, and what the latest research reveals about melatonin safety.
It is 11:30 PM and your child is still awake. You have done the bath. You have read the books. You have dimmed the lights and played the white noise and laid next to them until your own eyes closed. And they are still staring at the ceiling, wide awake, while you are barely functioning.
You are not imagining how much harder this is than what other families describe. Research confirms that 50 to 80% of autistic children experience significant sleep problems, compared to 20 to 30% of neurotypical children. Some studies put the number even higher, with up to 86% of autistic children experiencing at least one sleep difficulty daily. Your child is not being difficult. Their brain is wired differently when it comes to sleep, and understanding why is the first step toward finding what actually helps.
## The Science Behind Why Autistic Children Struggle With Sleep
Standard sleep advice assumes a brain that produces the right chemicals at the right time, processes sensory input without distress, and transitions smoothly from alertness to rest. The autistic brain often does none of these things in the way sleep advice expects.
### Their Melatonin Works Differently
Melatonin is the hormone that tells your brain it is time to sleep. In autistic children, the system that produces and regulates melatonin operates on a different schedule. Research published in Frontiers in Neurology found that autistic children experience their dim light melatonin onset, the point when the body starts producing sleep-signaling melatonin, approximately one hour and seventeen minutes later than neurotypical children. Their bodies are not receiving the biological signal to feel sleepy at the time you need them in bed.
Some autistic individuals have what researchers describe as a "flat melatonin curve," meaning their bodies never produce the normal nighttime spike of melatonin that triggers drowsiness. This is not a behavioral problem. It is a hormonal difference linked to mutations in genes that regulate melatonin production and metabolism.
### Their Circadian Rhythms Are Shifted
A groundbreaking 2025 Mendelian randomization study published in the journal Autism provided the first genetic evidence that the relationship between sleep and autism runs deeper than anyone expected. Using data from over 85,000 participants, researchers demonstrated that late chronotype, a biological tendency toward later sleep and wake times, has a causal relationship with autism. This is not just correlation. The genetic analysis shows that disrupted sleep patterns are woven into the neurobiology of autism itself.
Mutations in circadian regulatory genes including CLOCK, BMAL1, PER, and CRY have been associated with autism spectrum disorder. Your child's internal clock is not simply running late. It is built differently.
### Sensory Processing Turns Bedrooms Into Battlegrounds
The pillow feels wrong. The sheets are scratchy. The room is too quiet or not quiet enough. A car drove by outside and now they are fully alert again. For children with [sensory processing differences](/blog/sensory-processing-daily-routines), the bedroom itself can be a minefield of sleep-disrupting stimulation.
A scoping review published in the journal Sleep found that tactile sensitivity alone explained 24% of the variance in total sleep disturbance scores among autistic children. Touch hypersensitivity shows the strongest relationship with sleep problems of any sensory domain, more than sound, light, or any other input. This means that for many autistic children, the physical experience of being in bed is the primary barrier to falling asleep.
The relationship works in both directions. Poor sleep worsens sensory processing, and worsened sensory processing makes it harder to sleep. Families can get trapped in a cycle where each bad night makes the next one worse.
### Anxiety Keeps Their Nervous System on High Alert
Anxiety was associated with every type of sleep problem researchers measured: bedtime resistance, sleep-onset delay, reduced sleep duration, sleep anxiety, and night wakings. Children with autism who have both anxiety and sensory over-responsivity are particularly vulnerable to sleep difficulties because their nervous system is in a state of chronic hyperarousal.
When your child lies in bed and cannot turn their brain off, that is not a choice. Their hypothalamic-pituitary-adrenal axis, the body's stress response system, is dysregulated in ways that researchers have found are shared between insomnia and autism. The same neurobiological pathway that contributes to their [anxiety during the day](/blog/managing-anxiety-neurodivergent-children-visual-strategies) keeps their nervous system activated at night.
## What Poor Sleep Does to Your Child (and Your Family)
Understanding the consequences of poor sleep is not meant to add to your worry. It is meant to validate what you already know: sleep matters enormously, and the effects you are seeing in your child and in yourself are real and documented.
### It Worsens Core Autism Traits
A 2024 systematic review examining 26 studies found consistent associations between sleep problems and increased aggression, hyperactivity, emotional dysregulation, and social withdrawal in autistic children. Sleep deprivation does not just make children tired. It worsens the very challenges that define their daily experience.
Here is what surprised researchers most: when parents received sleep education and their children started sleeping better, the improvements extended beyond sleep. Children also showed reduced repetitive behaviors. Sleep intervention may actually address core features of autism, not just the tiredness on top of them.
In a study of over 2,500 children, those getting less than seven hours of sleep had significantly higher severity scores for social communication difficulties and [emotional regulation](/blog/emotional-regulation-visual-supports) challenges. Dr. Dara Manoach, Professor of Psychology at Harvard Medical School, explains that "critical aspects of learning and memory occur during sleep." The brain consolidation that happens during sleep is not optional. It is when the neural connections built during the day get strengthened or pruned, a process essential for attention, memory, and sensory processing.
### It Is Breaking Parents Too
This part rarely gets enough attention. Research shows that caregivers of autistic children average just 6.4 hours of sleep per night, below the recommended minimum of seven hours. Over half, 54.8%, report obtaining insufficient sleep.
The consequences are severe. Parents of autistic children with sleep problems show significantly higher levels of anxiety and depression compared to parents whose autistic children sleep well. A 2023 study found that among caregivers of autistic children, symptoms of excessive fatigue and insomnia co-occurred at a rate of 46%, suggesting that parent sleep deprivation and the child's sleep problems feed each other in a devastating cycle.
Among caregivers surveyed, 41.6% experienced moderate burden and 33.8% experienced high burden. If you feel like you are running on empty and barely holding things together, the research says you are not exaggerating. The toll of chronic sleep deprivation on top of the demands of [neurodivergent parenting](/blog/caregiver-burnout-parents-neurodivergent-children) is measured and documented.
## The Melatonin Question: What Every Parent Needs to Know
If your child has sleep problems, someone has probably suggested melatonin. Maybe your pediatrician recommended it. Maybe another parent swore by it. Maybe you bought gummies at the drugstore and hoped for the best. Here is what the latest research says.
### It Can Help, But the Details Matter
Melatonin supplementation does have research support for autistic children. A clinical trial of prolonged-release melatonin found that after 13 weeks, children slept an average of 57.5 minutes longer per night compared to just 9 minutes with placebo. Real-world data shows 86% improvement in sleep onset and 54% improvement in sleep duration.
The most effective dosing range appears to be 1 to 5 milligrams, administered 30 minutes before the desired bedtime. A randomized controlled trial found that combining melatonin with cognitive behavioral therapy produced greater improvements than either approach alone. Dr. Beth Malow, a sleep neurologist at Vanderbilt University, emphasizes that melatonin works best when combined with behavioral strategies, not as a standalone solution.
### But There Are Serious Safety Concerns
A 2025 systematic review published in JAMA Network Open revealed alarming findings. The FDA tested 110 melatonin products marketed for children and found that actual melatonin content ranged from 0% to 667% of what was listed on the label. That means some products contain no melatonin at all while others contain nearly seven times the stated dose.
The consequences are showing up in emergency rooms. Melatonin poisoning cases in children rose from zero in 2000-2001 to over 10,500 by 2017-2021, representing 63% of all pediatric supplement poisonings during that period. Emergency department visits for melatonin exposure doubled between 2019 and 2022. Child-friendly gummy formulations accounted for nearly half of accidental ingestion cases.
Because the FDA classifies melatonin as a dietary supplement rather than a drug, there are no standardized manufacturing requirements, no required dosing accuracy, and no oversight of what actually ends up in the bottle. Another troubling finding: 40 to 50% of children prescribed melatonin continued using it for two to three years, exceeding the recommended one to two year duration.
This does not mean melatonin is never appropriate. It means that if you use it, purchase pharmaceutical-grade products when possible, start with the lowest effective dose, and work with your child's doctor rather than guessing.
## What the Research Says Actually Works
The American Academy of Neurology and leading sleep researchers agree: behavioral interventions should be the first approach before medication. A 2025 meta-analysis published in the journal Autism confirmed that behavioral and psychological interventions, physical activity, and somatosensory sleep interventions all significantly improve sleep in autistic children.
### Build a Predictable Wind-Down Routine
A study using an ABAB reversal design found that visual bedtime schedules showed positive treatment effects with increased routine compliance that maintained over time. The routine itself matters less than its consistency. Twenty to thirty minutes of calming, predictable steps signals to your child's brain that sleep is approaching.
The key is making the routine visible. When your child can see what comes next, [anxiety about bedtime](/blog/bedtime-routine-autism-adhd) decreases because the uncertainty disappears. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build a visual bedtime routine with personalized images of your child doing each step, which makes the routine feel familiar and concrete rather than abstract.
### Address Sensory Needs Before They Derail Sleep
Since tactile sensitivity is the strongest sensory predictor of sleep problems, start there. Experiment with different sheets, pajama fabrics, and blanket weights. Some children need compression, like a fitted sheet pulled tight or a compression sleep garment. Others need less contact, preferring loose clothing and lightweight covers.
Room environment matters enormously. Temperature, lighting, and sound all contribute to whether the bedroom supports sleep or fights it. Some children sleep better with white noise or a fan. Others need complete silence. Blackout curtains help light-sensitive children, while a dim nightlight may reduce sleep anxiety for others.
About weighted blankets: despite their popularity, a randomized controlled trial found no significant objective improvement in sleep quality for autistic children using weighted blankets. Subjective reports from families were more positive, with some noting improved morning mood and faster sleep onset. They may help your child feel calmer, but they are not a research-backed sleep solution on their own.
### Cut Screens Before Bed (But Do Not Eliminate Them Entirely)
Blue light from screens disrupts circadian rhythms, and research shows this effect is particularly significant for autistic children given their existing sensory processing differences. Studies consistently find that total screen time, pre-bedtime use, gaming, and social media all correlate with poorer sleep quality in autistic individuals.
The recommendation from sleep specialists: end screen time at least one hour before bed. But researchers also note that for neurodivergent children, [screens can serve important functions](/blog/screen-time-management-autism-adhd) including social connection, anxiety reduction, and learning. The issue is specifically pre-bedtime use and blue light exposure, not screens during the rest of the day. Charge devices outside the bedroom overnight.
### Get Moving During the Day
A meta-analysis of randomized controlled trials found that regular exercise improves sleep quality, reduces how long it takes to fall asleep, and improves sleep efficiency in autistic individuals. Daytime physical activity and outdoor time with natural sunlight exposure help regulate the circadian rhythm that is often shifted in autistic children.
Avoid vigorous activity within an hour of bedtime, but do not underestimate how much difference a physically active day makes for a physically restless night.
### Track What Is Actually Happening
One of the most powerful things you can do is start tracking your child's sleep patterns alongside their daytime activities, [emotions](/blog/tracking-emotions-activities-neurodivergent-children), and sensory exposures. What you think is causing the sleep problems may not match what the data reveals.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you track your child's emotions and activities throughout the day, revealing patterns that connect daytime experiences to nighttime sleep quality. Maybe the days with afternoon meltdowns are also the nights with the worst sleep. Maybe certain foods, activities, or transitions consistently precede difficult nights. Without data, you are guessing. With data, you are making informed decisions.
### Consider Professional Sleep Support
If behavioral strategies alone are not enough, cognitive behavioral therapy adapted for insomnia in autistic children shows remarkable promise. A pilot study found that after eight sessions of CBT, 85% of autistic children no longer met criteria for insomnia one month after treatment ended. That is a striking success rate for a non-medication approach.
When seeking professional help, look for providers familiar with autism-specific sleep challenges. A general pediatric sleep specialist who does not understand sensory processing or anxiety in autism may default to strategies that do not account for your child's neurology. Ask specifically about their experience with neurodivergent children.
## The Nutritional Factors Nobody Mentions
Research has identified several nutritional connections to sleep that are particularly relevant for autistic children, many of whom have [selective eating patterns](/blog/picky-eating-autism-spectrum-food-selectivity).
Iron supplementation showed significant improvement in nighttime restlessness at 6 milligrams per kilogram per day in research studies. This is especially relevant for autistic children with restricted diets who may not get adequate iron from food. A simple blood test can determine whether your child's iron levels are contributing to their restless sleep.
Tryptophan and 5-HTP supplementation showed 84% improvement in parasomnia symptoms, including nightmares and night terrors, in a study of 165 children. This is relevant because tryptophan metabolism is known to be dysregulated in autism.
These are not miracle supplements. But if your child has selective eating and persistent sleep problems, discussing nutritional assessment with their pediatrician is worth the conversation.
## Why This Problem Does Not Go Away on Its Own
Unlike neurotypical children, who tend to outgrow sleep difficulties, sleep problems in autism are persistent. Research shows they are less likely to improve with age without intervention. The biological underpinnings, melatonin differences, circadian gene mutations, sensory processing challenges, do not resolve on their own.
This is not meant to discourage you. It is meant to encourage you to take sleep seriously as a treatable medical issue rather than a phase your child will grow out of. Dr. Beth Malow states plainly: "Sleep issues are highly treatable" when evidence-based approaches are applied.
The good news is that treating sleep problems has cascading benefits. Better sleep improves behavior, emotional regulation, learning, social communication, and reduces repetitive behaviors. Better child sleep improves parent sleep, which improves parent mental health, which improves the entire family dynamic.
## Where to Start Tonight
You do not need to overhaul everything at once. Start with what the research says has the most impact:
- **Address tactile sensitivity in the bedroom.** Experiment with pajamas, sheets, and blankets until you find what your child's skin can tolerate. This single change addresses the strongest sensory predictor of sleep problems.
- **Create a visible wind-down routine.** Twenty to thirty minutes, same steps every night, posted where your child can see it. Reduce demands and stimulation during this window.
- **Cut screens one hour before bed.** This is the most evidence-based screen recommendation for sleep.
- **Start tracking.** Document bedtime, wake time, night wakings, and what happened during the day. Patterns will emerge within two to three weeks.
- **Talk to your pediatrician about a full evaluation** including iron levels, sensory assessment, and whether a sleep specialist referral makes sense.
You have been fighting this battle in the dark, sometimes literally, and the exhaustion is real. But the research is clear: sleep problems in autism are treatable, and addressing them improves virtually every other challenge your family faces during the day.
Your child is not choosing to keep you up all night. Their brain is working against them, and now you know why. That knowledge is the foundation for every strategy that follows.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build visual bedtime routines, track sleep patterns alongside daily emotions and activities, and identify the triggers that are stealing your child's rest. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring science-backed structure to your family's hardest hours.
---
## How to Find Trustworthy Autism Resources Online When TikTok Gets It Wrong
Published: 2026-03-27
URL: https://vizyplan.com/blog/trustworthy-autism-resources-online-tiktok-misinformation
Category: Strategies
Author: Justin Bowman
> Research shows 41% of autism content on TikTok is inaccurate. Learn how to spot misinformation, evaluate online advice, and find evidence-based resources you can actually trust.
You are scrolling at midnight again. Your child was just diagnosed, or maybe you have been living this life for years but something new came up that you do not know how to handle. So you open TikTok. Or Instagram. Or you fall into a Facebook group where someone swears that a supplement changed everything for their kid.
Within ten minutes you have watched a video claiming a specific diet cures autism, another one listing "signs your therapist is gaslighting you," and a third promoting a detox spray that supposedly removes toxins causing your child's behaviors. The videos are confident. The comments are full of parents saying "this changed our lives." And you are left wondering whether you have been doing everything wrong.
You are not the only parent in this position. And the confusion you feel is not a personal failing. It is the predictable result of platforms that reward confidence over accuracy and engagement over evidence.
## The Scale of Autism Misinformation Online
The numbers are worse than most parents realize.
A 2023 study from Drexel University's A.J. Drexel Autism Institute examined the top 133 informational TikTok videos about autism. These videos had a combined reach of 198.7 million views and 25.2 million likes. Of those videos, only 27 percent were classified as accurate. Forty-one percent were inaccurate. The remaining 32 percent were overgeneralized, meaning they took a kernel of truth and stretched it beyond what the evidence supports.
The most alarming finding was this: there was no significant difference in engagement between accurate and inaccurate videos. A video spreading false information about autism gets just as many likes, shares, and comments as one sharing real, evidence-based guidance. The algorithm does not care about accuracy. It cares about watch time.
A 2026 cross-platform analysis found that TikTok had the highest misinformation rate for autism content at 41 percent, compared to 22 percent on YouTube and just under 15 percent on Facebook. Neurodivergence content, including autism and ADHD, contained higher levels of misinformation than any other mental health topic studied.
And when CBC Marketplace analyzed 100 TikTok videos specifically about autism treatments, they found that approximately 80 percent featured treatments or cures that are not supported by science. Those videos had accumulated over 75 million views. The creators were often not medical professionals. They were parents sharing personal experiences, influencers promoting products, or self-proclaimed experts with no clinical credentials.
## Why Social Media Misinformation Is So Convincing
Understanding why this content feels trustworthy helps you build defenses against it.
**Personal stories are powerful.** When a parent looks into the camera and says "this supplement changed my child's life," it hits differently than reading a clinical study. Our brains are wired to trust narratives, especially emotional ones from people who look like us and share our struggles. But a single family's experience, however genuine, is not evidence that something works. It is an anecdote. And anecdotes are where most misinformation takes root.
**The algorithm creates echo chambers.** TikTok's recommendation system learns what keeps you watching. If you engage with one video about an alternative autism treatment, the algorithm serves you ten more. Within days, your entire feed can become a curated reality where a fringe idea looks like mainstream consensus. You are not seeing the full picture. You are seeing what the algorithm calculated would keep you scrolling.
**Credentials are easy to fake or misrepresent.** Someone calling themselves a "holistic autism specialist" or "neurodivergent coach" may have no clinical training whatsoever. There is no credentialing body for most of these titles. A real Board Certified Behavior Analyst (BCBA), licensed psychologist, speech-language pathologist, or occupational therapist has years of supervised clinical education. The person on TikTok with 500,000 followers may have a ring light and strong opinions.
**Desperation is a vulnerability.** Parents of neurodivergent children are often exhausted, overwhelmed, and searching for anything that might help. That emotional state makes people more susceptible to promises of quick fixes or simple solutions. Misinformation marketers know this. They use emotional appeals, urgency, and the language of hope to sell products and ideas that have no scientific backing.
## The Real Dangers of Bad Autism Advice
This is not just about being wrong on the internet. Bad information leads to real harm.
**Dangerous treatments get promoted as cures.** Chelation therapy, which claims to remove heavy metals from the blood and "cure" autism, has been promoted widely on social media despite having no evidence of effectiveness for autism. In 2005, a five-year-old boy died after receiving chelation therapy. More recently, "autism detox" products containing zeolite, a mineral compound sold as sprays, tinctures, and powders, have gone viral on TikTok with claims of curing autism. The Association for Science in Autism Treatment (ASAT) has warned that these products have no published data supporting their use and carry real health risks.
**Families delay evidence-based interventions.** When parents spend months pursuing an unproven treatment they discovered on social media, their child is not receiving the therapies that research has actually validated. Early intervention matters. Every month counts during critical developmental windows. Time spent chasing a TikTok miracle is time not spent on approaches that decades of research support.
**It fuels stigma and misunderstanding.** A 2025 study published in the Journal of Autism and Developmental Disorders found that 88.5 percent of autism-related TikTok content contained stigmatizing messages. When the most-watched autism content frames it as something to be cured, fixed, or feared, it shapes how the broader public views your child. That affects everything from school inclusion to neighborhood acceptance to how extended family members respond.
**It undermines trust in real professionals.** After watching enough social media content claiming that therapists are "masking your child" or that [ABA is always harmful](/blog/types-of-therapy-neurodivergent-children), parents may approach their child's actual care team with suspicion rather than partnership. The nuanced reality, that some therapy approaches work better for some children than others and that good practitioners continuously adapt, gets lost in the black-and-white framing that social media rewards.
## Red Flags That Should Make You Pause
Not every piece of autism content online is bad. But these warning signs should trigger your skepticism immediately.
**Anyone claiming to cure autism.** There is no cure for autism. Autism is a neurological difference, not a disease. Any product, protocol, or program that promises to cure, reverse, or eliminate autism is not telling the truth. Full stop.
**Results that sound too good to be true.** "My nonverbal child started speaking sentences after three days on this supplement." "This one technique eliminated all meltdowns." Real progress with neurodivergent children is gradual, inconsistent, and deeply individual. Dramatic overnight transformations should be met with extreme skepticism.
**No peer-reviewed research cited.** Credible information about autism treatment comes from studies published in peer-reviewed journals, meaning other researchers evaluated the methodology and findings before publication. If someone is making treatment claims without citing published research, you are hearing their opinion, not established science.
**The source cannot be corroborated.** If a claim appears on a single blog, social media account, or website and you cannot find it discussed anywhere else, including by established research or medical organizations, that is a significant red flag. Legitimate findings are replicated, discussed, and built upon by multiple independent sources.
**Aggressive emotional marketing.** Watch for language designed to trigger fear or guilt: "doctors do not want you to know this," "the one thing you are doing that makes autism worse," "I wish someone had told me sooner." These phrases are marketing techniques, not health information.
**The creator is selling something.** Does the video end with a link to purchase a supplement, course, or program? Financial incentive does not automatically make information wrong, but it should make you more cautious. Ask yourself whether the information would be different if there was no product attached to it.
## Where to Find Information You Can Trust
Building a personal library of reliable sources is one of the most protective things you can do as a parent.
### Federal and Research Organizations
**The National Institute of Child Health and Human Development (NICHD)** researches autism causes, early signs, and intervention approaches. Their website provides parent-friendly summaries of current research without the spin.
**The Interagency Autism Coordinating Committee (IACC)** coordinates autism research and services across federal agencies and maintains a comprehensive directory of vetted organizations and resources.
**The Centers for Disease Control and Prevention (CDC)** offers developmental milestone tracking, screening information, and intervention guidance based on the latest research.
### Science-Based Nonprofits
**The Association for Science in Autism Treatment (ASAT)** is one of the most valuable resources most parents have never heard of. They have evaluated over 400 purported autism treatments and provide evidence-based ratings for each one. Before you try anything you found online, search the ASAT website first. Their resources are free, backed by organizations like Johns Hopkins School of Education and the Behavior Analyst Certification Board, and written for families.
**The Organization for Autism Research (OAR)** is parent-led and science-based. Founded and run by parents and grandparents of autistic individuals, they fund research and translate findings into practical resources families can actually use.
**The Autism Science Foundation** focuses exclusively on funding and communicating autism research, providing a reliable filter between complex studies and family-friendly information.
### Professional Associations
**The American Speech-Language-Hearing Association (ASHA)** provides resources on communication development and therapy approaches backed by clinical evidence.
**The American Occupational Therapy Association (AOTA)** offers guidance on sensory processing, daily living skills, and practical strategies supported by occupational therapy research.
**The American Academy of Pediatrics (AAP)** publishes clinical guidelines on autism screening, diagnosis, and treatment that reflect the current medical consensus.
### Evaluating Your Child's Own Providers
The most trustworthy source of guidance for your specific child is a qualified professional who knows them. Licensed psychologists, BCBAs, speech-language pathologists, and occupational therapists have completed years of supervised education and clinical training. When you have questions about something you saw online, bring it to your child's providers. A good clinician will not dismiss your question. They will help you evaluate the claim using the evidence that actually exists.
If you are still searching for the right [therapist for your child](/blog/finding-right-therapist-neurodivergent-child), prioritize providers who explain their reasoning, cite evidence, and welcome your questions rather than those who promise guaranteed outcomes.
## How to Evaluate Autism Content in Real Time
You do not need a research degree to vet information. Use this quick checklist when you encounter autism advice online.
**Check the creator's credentials.** Are they a licensed professional in a relevant field? Can you verify their license? A real BCBA, SLP, OT, or psychologist will typically list their credentials and license number. If there are no verifiable credentials, weight the information accordingly.
**Look for the research.** Does the post or video cite specific studies? Can you find those studies on PubMed, Google Scholar, or the ASAT treatment database? If there is no research cited, or if the cited research does not actually say what the creator claims, that is your answer.
**Check if healthcare professionals made it.** The Drexel study found that TikTok videos created by healthcare professionals were significantly more likely to contain accurate information. Content from clinicians is not automatically perfect, but it is a better starting point than content from someone with no clinical background.
**Search for the claim on trusted sites.** Take the specific claim, such as "zeolite treats autism" or "casein-free diet reverses autism symptoms," and search for it on ASAT, NICHD, or the AAP website. If trusted organizations have not validated the claim, or actively warn against it, that tells you what you need to know.
**Wait before acting.** The most protective habit you can build is pausing before implementing anything you learned from social media. Give yourself 48 hours. Use that time to research the claim through the sources listed above. Talk to your child's [care team](/blog/provider-collaboration-iep-preparation). The urgency you feel after watching a compelling video is manufactured by the platform. Real evidence-based approaches will still be valid in two days.
## Social Media Is Not All Bad
It is important to acknowledge that social media also provides genuine value for many autism families.
The #ActuallyAutistic community on TikTok and Instagram has given autistic adults a platform to share their lived experiences in ways that help parents understand their children's inner worlds. Hearing an autistic adult explain what sensory overload actually feels like, or why transitions are so hard, or what it means when your child [stims](/blog/sensory-processing-daily-routines), can be profoundly helpful. Lived experience is not the same as clinical evidence, but it is valuable context that clinical research alone cannot provide.
Online parent communities offer emotional support that is genuinely hard to find elsewhere. When you are up at 2 AM after a brutal day and you need someone who understands without explanation, a Facebook group of parents living the same reality can be a lifeline. The [isolation of raising a neurodivergent child](/blog/losing-friends-raising-autistic-child) is real, and online community helps.
The key is learning to separate community support and lived experience from medical and treatment advice. A parent sharing that weighted blankets helped their child sleep is a helpful data point worth discussing with your OT. That same parent claiming weighted blankets cure autism is misinformation. The line matters.
## Building Your Information Filter
Over time, you can train yourself to navigate online autism content with confidence. Here is how.
**Curate your feed intentionally.** Follow accounts run by licensed professionals who cite their sources. Follow autistic self-advocates whose perspectives broaden your understanding. Unfollow or mute accounts that consistently promote unproven treatments or use fear-based marketing. Your algorithm reflects your behavior, so teach it what you actually want to see.
**Create a trusted source list.** Bookmark the organizations listed in this post. When you encounter a new claim, make it a habit to check those sources before you change anything about your child's care. Over time, this becomes second nature.
**Talk to other parents with a critical lens.** Parent communities are invaluable for emotional support, practical tips, and the kind of "been there" wisdom that professionals sometimes lack. But when another parent recommends a treatment or approach, apply the same evaluation framework you would use for a TikTok video. Ask what evidence supports it. Check the trusted sources. And remember that what worked for one child may not work for yours because every neurodivergent child is genuinely different.
**Keep your child's providers in the loop.** When you find something interesting online, bring it to your next therapy session or [IEP meeting](/blog/iep-meeting-preparation-guide-parents). Your child's BCBA, therapist, or pediatrician can help you evaluate whether it has merit for your specific child. This turns social media from a source of anxiety into a conversation starter.
**Document what actually works.** The best defense against misinformation is having your own data. When you [track your child's routines, emotions, and progress](/blog/tracking-emotions-activities-neurodivergent-children) over time, you build an evidence base that is specific to your child. You stop needing a stranger's anecdote to feel confident because you have your own information telling you what is actually making a difference.
## You Are Already Doing the Hard Part
The fact that you are reading this post, that you are trying to find trustworthy information, that you are questioning what you see online rather than blindly following it, means you are already doing the most important thing. You are thinking critically about what your child needs.
Your child does not need a parent who has read every study ever published. They need a parent who knows where to look when questions come up, who can tell the difference between a sales pitch and real guidance, and who trusts their own observations enough to bring them to the professionals who know their child best.
The information is out there. The good kind. You just have to know where to find it.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build evidence-based visual routines, track your child's progress with real data, and stay grounded in what actually works for your family. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and replace the noise with tools designed by a parent who gets it.
---
## Everything You Need to Know Before the Next IEP Meeting
Published: 2026-03-26 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/iep-meeting-preparation-guide-parents
Category: Strategies
Author: Justin Bowman
> A parent guide to IEP meeting preparation, from understanding the documents to knowing your rights and walking in with confidence.
You are sitting in a conference room surrounded by six people with clipboards. The special education teacher is using acronyms you have never heard before. The school psychologist is reading from a document you were emailed at 10 PM last night. Someone mentions "present levels" and you nod like you understand, but inside you are wondering what that even means. Then they slide a piece of paper across the table and ask you to sign.
You are not alone. Research shows that parents spoke in only about 14 percent of all intervals during IEP meetings, while professionals spoke in the remaining 86 percent. A separate study found that 33 percent of parents reported feeling confused during IEP meetings, leading them to withdraw from discussions entirely.
This does not have to be your experience. The Individualized Education Program meeting is supposed to be a collaboration, and under federal law, you are an equal member of the team. The difference between feeling steamrolled and feeling prepared comes down to what you do before you walk through that door.
## What an IEP Meeting Actually Is (and Is Not)
An IEP meeting is a federally mandated meeting under the Individuals with Disabilities Education Act (IDEA) where a team of people, including you, develops or reviews your child's educational plan. It is not a parent-teacher conference. It is not a progress update you passively receive. It is a decision-making meeting where your input carries the same legal weight as every other team member's.
The IEP team typically includes you (the parent or guardian), a general education teacher, a special education teacher, a school psychologist or diagnostician, a school administrator who can commit resources, and related service providers like speech therapists or occupational therapists. Your child can also attend when appropriate, and you have the right to bring anyone you choose, an advocate, an attorney, a friend, a family member, or any other person with knowledge or expertise about your child.
Understanding this matters because many parents walk into these meetings believing their role is to listen and agree. It is not. Your role is to participate, question, and make sure the plan reflects what your child actually needs.
If you are unsure whether your child should have an IEP or a [504 plan](/blog/504-plan-vs-iep-neurodivergent-child), start there first. The two serve different purposes and offer different levels of support.
## Before the Meeting: Your Preparation Checklist
The single most important thing you can do is prepare. Parents who come to IEP meetings with organized documentation and clear priorities report feeling significantly more confident and having more productive conversations with the school team.
**Request the draft IEP in advance.** You have the right to see the proposed IEP before the meeting. Schools will sometimes present a finished document at the meeting and ask you to sign it. That is not how the process is supposed to work. Call or email the special education coordinator at least a week before the meeting and ask for the draft. If the school says it is not ready, ask for whatever documents will be discussed.
**Review the current IEP line by line.** Mark anything that was not fully implemented this year. Note goals your child met, goals they did not meet, and goals that no longer seem relevant. Write down questions next to anything you do not understand.
**Gather your own data.** This is where most parents have an advantage they do not realize. You see your child in contexts the school never will. Bring documentation of what you observe at home: behavioral patterns, skill development, challenges that persist outside school hours, and strategies that work in your household. If you use [visual schedules](/blog/visual-schedules-for-autism) or routine tracking tools at home, bring that data. It tells a story that school data alone cannot.

**Write a parent concern letter.** This does not need to be long or formal. A one-page letter that describes your child's strengths, your concerns, and what you want the team to focus on gives you a written record and ensures your priorities are on the table from the start. Hand a copy to every team member at the meeting.
**Prepare your questions in advance.** Write them down. In the moment, when six professionals are talking and acronyms are flying, you will forget. Having a written list means you will not leave the meeting wishing you had asked something important.
**Bring a support person.** Research on parent participation in IEP meetings consistently shows that parents who bring an advocate, knowledgeable friend, or family member feel more empowered and participate more actively. Your support person can take notes, remind you of points you wanted to raise, and provide emotional grounding when the conversation gets difficult.
## Understanding the IEP Document
The IEP can feel like it is written in another language. But every section serves a purpose, and understanding the key parts gives you the ability to evaluate whether the plan actually meets your child's needs.
### Present Levels (PLAAFP)
The Present Levels of Academic Achievement and Functional Performance, often called the PLAAFP or "present levels," is the foundation of the entire IEP. This section describes how your child is performing right now, not just academically, but in communication, social skills, motor skills, behavior, and daily living skills.
This section should reflect your child's actual abilities, not a sanitized version of them. If the present levels say your child "sometimes struggles with transitions" but you know your child has a meltdown every single time a preferred activity ends, that discrepancy matters. The present levels drive the goals, and if the present levels are inaccurate, the goals will be too.
**What to look for:** Does this match what you see at home? Does it include strengths, not just deficits? Does it describe how the disability affects your child's participation in general education? If not, raise it.
### Annual Goals
Each IEP goal should be specific, measurable, attainable, relevant, and time-bound. That sounds like corporate jargon, but it matters in practice. A goal that says "Johnny will improve his social skills" is not measurable. Nobody can track progress toward "improving" something undefined.
A better goal looks like this: "Given a structured small-group activity with visual supports, Johnny will initiate a conversational exchange with a peer for at least three turns in 4 out of 5 opportunities, as measured by teacher observation data."
The difference is that the second goal tells you exactly what success looks like, under what conditions it will be measured, and how often it needs to happen. You can track that. You can hold the school accountable to it.
**Ask these questions about every goal:** How will progress be measured? How often will data be collected? How often will I receive progress reports? What happens if my child is not making progress toward this goal?
### Services and Accommodations
This section specifies what your child will receive: speech therapy minutes, occupational therapy, specialized instruction, behavioral support, and the accommodations that will be in place throughout the school day.
Pay attention to the numbers. "Speech therapy" means nothing without frequency and duration. Is it 30 minutes once a week? Twice a week? In a group or individually? The specifics matter because they are legally binding once the IEP is signed.
Accommodations are the changes to the learning environment or how material is presented. Extended time on tests, preferential seating, visual schedules in the classroom, movement breaks, reduced homework volume, noise-canceling headphones. If your child needs something specific to access their education, it should be written into the IEP. Verbal promises from teachers are not enforceable. Written accommodations are.
## Your Rights: What the School May Not Tell You
IDEA gives parents significant rights that many families do not know about. Schools are required to provide you with a copy of your procedural safeguards at least once a year, but that document is often 20 pages of legal language that nobody reads. Here is what you actually need to know.
**You do not have to sign at the meeting.** This might be the single most important thing in this article. You can take the IEP home, review it, consult with someone you trust, and sign it later. You can also sign parts of the IEP you agree with and disagree with others. Signing does not have to be all or nothing.
**You have the right to Prior Written Notice.** Whenever the school proposes to change, or refuses to change, your child's identification, evaluation, placement, or services, they must give you written notice explaining what they are doing and why. If you request a service and the school says no, ask for Prior Written Notice. It forces the school to put their reasoning in writing, which creates an important paper trail.
**You can request an Independent Educational Evaluation.** If you disagree with the school's evaluation of your child, you have the right to request an Independent Educational Evaluation (IEE) at public expense. The school must either agree to pay for it or file for a due process hearing to prove their evaluation was appropriate. This is a powerful tool when you believe the school's testing does not accurately reflect your child's needs.
**You can invite anyone to the meeting.** There is no limit on who you can bring. An advocate, attorney, private therapist, behavior analyst, or anyone else with knowledge of your child can attend. You do not need the school's permission.
**You can record the meeting.** Laws vary by state, but in many states you can audio record IEP meetings. Check your state's recording consent laws and notify the school in advance if required. A recording protects everyone and ensures nothing is lost in memory.
## Questions That Change the Conversation
The right questions shift the dynamic from parents receiving information to parents driving the conversation. Here are the ones that matter most.
**"Can you show me the data?"** When someone says your child is "making progress" or "struggling with" something, ask to see the actual data. How was it collected? How often? Over what time period? Data-driven conversations are productive. Opinion-based conversations go in circles.
**"What does my child's day actually look like?"** You might be surprised by the answer. Understanding when your child receives services, where they spend their time, who they interact with, and what supports are (or are not) in place throughout the day gives you critical context for evaluating whether the IEP is working.
**"What will happen if my child does not meet this goal?"** This question reveals whether the team has a plan beyond writing the goal and hoping for the best. If there is no answer, that is a red flag.
**"How will this be communicated to every adult who works with my child?"** An IEP is only as good as its implementation. If the classroom teacher does not know about the accommodations, they will not be provided. Ask specifically how the plan will be shared with every teacher, aide, and substitute who interacts with your child.
**"Can I have that in writing?"** If someone makes a verbal commitment during the meeting, a promise to try a new strategy, a plan to increase services next quarter, a suggestion about placement, ask for it to be added to the IEP or documented in the meeting notes. Verbal agreements are not enforceable.
## When You Disagree
Disagreement is normal. In fact, CADRE's 2024 report on dispute resolution trends showed that written state complaints rose 32 percent over the previous year, and mediation requests reached a decade-high of nearly 12,000. You are not being difficult by pushing back. You are doing your job as a member of the team.
**Start with questions, not accusations.** Instead of "You are not giving my child enough speech therapy," try "Can you walk me through how the current speech therapy minutes were determined? I am seeing challenges at home that make me think we might need to revisit the frequency." The information you get from that question will tell you whether the school has a rationale or whether they are basing services on what is available rather than what your child needs.
**Document everything.** Send a follow-up email after the meeting summarizing what was discussed, what was agreed upon, and any outstanding questions. This creates a paper trail that matters if disagreements escalate.
**Know your dispute resolution options.** If informal conversations do not resolve the issue, you have formal options: mediation (voluntary for both parties), state complaints (filed with your state education agency), and due process hearings (a more formal legal proceeding). Many disagreements are resolved through facilitated IEP meetings or mediation before reaching due process. Your state's Parent Training and Information Center can help you understand your options and connect you with free or low-cost advocacy support.
**Consider an advocate.** Parent advocates, many of whom are parents of children with disabilities themselves, can attend meetings with you, help you understand your rights, and speak on your behalf when you feel overwhelmed. Many organizations provide advocacy services for free or on a sliding scale.
## Preparing Your Child
Depending on your child's age and communication abilities, involving them in IEP preparation can be powerful. Research from the IRIS Center at Vanderbilt University shows that student involvement in the IEP process is associated with increased [self-advocacy skills](/blog/teaching-self-advocacy-skills-neurodivergent-child), self-determination, and engagement with their own education.
For younger children, this might mean asking them what they like about school, what is hard, and what would help them. For older children and teenagers, it might mean attending part of the meeting, presenting their own perspective, or even leading portions of the discussion.
Visual tools can help here. Creating a simple [visual routine](/blog/visual-schedules-for-autism) that shows your child what the meeting will look like, who will be there, and what will happen can reduce anxiety about the process itself. [Social stories](/blog/social-stories-autism-guide) about IEP meetings can help children understand why the meeting is happening and that the adults are there to help them succeed.
If your child is approaching the [transition to adulthood](/blog/autism-services-cliff-after-high-school), their involvement becomes even more critical. Transition planning should begin by age 16 (earlier in some states), and the student's preferences, interests, and goals for life after high school should drive those conversations.
## Building a System That Works Year-Round
The most effective IEP preparation does not happen the week before the meeting. It happens all year.
**Keep a running log.** When your child has a great day, write it down. When something goes wrong at school, write it down. When you email the teacher about an accommodation that is not being implemented, save that email. When the school sends home a progress report, file it. This ongoing documentation becomes the evidence base that makes your IEP meetings productive.
**Track patterns and progress at home.** Tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) allow you to [track your child's emotions, activities, and behavioral patterns](/blog/tracking-emotions-activities-neurodivergent-children) over time, giving you concrete data to share with the school team. When you can show a chart of your child's morning routine success rate over the past three months, you are bringing evidence, not opinions. That changes the conversation.
**Communicate regularly.** Do not wait for the annual IEP meeting to raise concerns. If something is not working, email the special education teacher or case manager. If your child is struggling with a new skill, share that information. If a strategy from the IEP is working well at school and you want to [build consistency at home](/blog/provider-collaboration-iep-preparation), ask the team how to do that. Ongoing communication builds the kind of relationship where annual meetings are productive rather than adversarial.
**Review progress reports carefully.** Schools are required to send progress reports on IEP goals at least as often as they send report cards to general education students. Read them. Compare the data to what you are seeing at home. If the school says your child is making "sufficient progress" but you are seeing the opposite, that disconnect needs to be addressed before the next annual meeting.
## You Belong at That Table
The IEP process can feel intimidating. The professional jargon, the power dynamics, the sheer number of people in the room, all of it can make parents feel like guests in someone else's meeting.
But it is your meeting too. No one knows your child the way you do. No one sees what you see at 6 AM when the morning routine falls apart, or at 8 PM when homework is still not done, or on Saturday when the skills from therapy do not carry over into real life. That knowledge is not less valuable than a test score or an observation checklist. It is the context that makes everything else meaningful.
You do not need to be a special education expert to advocate effectively. You need to be prepared, informed, and willing to ask questions until you understand. The school team has training and credentials. You have something they do not: the full picture of your child's life.
Walk in knowing your rights. Walk in with your data. Walk in with your questions written down and a support person beside you. And when they slide that piece of paper across the table, remember that you do not have to sign it today.
Your child's education plan should reflect your child. Not the one the district has a template for. Yours.
---
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that document your child's daily progress, [track behavioral and emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) that give you concrete data for IEP meetings, create [social stories](/blog/social-stories-autism-guide) that prepare your child for school meetings and transitions, and share consistent schedules with every provider on your child's team. Just $6.99/month after your trial, no credit card required upfront.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps families of neurodivergent children build Visual Routines and Planning tools that bring structure, confidence, and data to every part of your child's day, including the IEP table. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and walk into your next meeting prepared.
---
## How AI Is Changing Daily Life for Families of Autistic Children
Published: 2026-03-24
URL: https://vizyplan.com/blog/ai-changing-daily-life-autism-families
Category: Technology
Author: Justin Bowman
> From visual schedules to emotion recognition and smarter IEPs, artificial intelligence is quietly reshaping how families support autistic children every day.
You are standing in the cereal aisle trying to get through the grocery list while your child is on the verge of a meltdown. You already showed them the visual schedule this morning, but the generic clip art did not look anything like your actual grocery store. The social story you printed from a website showed a different child in a different place doing different things. And the gap between those stock images and your child's real life made the whole preparation feel pointless.
Now imagine a version of that morning where the visual schedule showed your child, in your grocery store, putting the items you actually buy into a cart that looks like the one they will push. That is not a hypothetical. That is what artificial intelligence is making possible right now for families raising autistic children.
AI is not coming to autism support. It is already here. And it is showing up in places you might not expect.
## The Numbers Behind the Shift
Before we look at how AI is changing daily life, it helps to understand the scale of what families are navigating.
The CDC's most recent data shows that [1 in 31 children](/blog/1-in-31-autism-diagnosis-rates-daily-life) in the United States is now identified with autism spectrum disorder. That is 3.2 percent of all children, up from 1 in 36 just two years ago. Among boys, the rate is 1 in 20. In some states, it is even higher.
These are not small numbers. They represent millions of families who need tools, support, and systems that actually work for their daily lives. And traditional approaches, while valuable, have not been able to scale to meet that demand.
That is where AI comes in. Not as a replacement for therapists, teachers, or parents, but as a tool that multiplies the reach and personalization of support that already works.
**A survey of 611 families** published in ScienceDirect found that families of autistic children use technology more frequently and across more domains than the general population. Sixty-five percent of autistic children and 57 percent of their families reported that technology had a positive impact on their quality of life. The autism group also showed greater benefits in social, motor, language, and emotion regulation skills from technology use compared to the broader community.
## Visual Schedules Got Smarter
If you have been in the autism parenting world for more than a week, someone has told you about visual schedules. And they were right to. The National Clearinghouse on Autism Evidence and Practice recognizes visual schedules as one of only 28 evidence-based practices for supporting individuals with autism. A pilot study found that 88 percent of staff and 78 percent of caregivers reported that picture schedules decreased anxious behaviors in children.
The evidence is clear. Visual schedules work. The problem has always been making them personal enough to actually connect with your specific child.
**This is where AI changes the equation.** Traditional visual supports rely on stock images, clip art, or photos you take and print yourself. AI-powered tools can now generate custom images that match your child's appearance, your home environment, and the specific steps in your family's actual routines. When a child sees themselves in the visual, not a generic cartoon, engagement increases because the connection between the image and real life is immediate.
We built [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) around exactly this idea. Using AI-generated images, families can create [visual routines](/blog/visual-schedules-for-autism) that look like their child's real life, not someone else's. The result is visual supports that children actually look at, follow, and feel connected to.
This is not a niche idea. Alibaba launched an AI-powered tool in 2024 that has been used by over 50,000 people to create picture books for children with autism, generating audio-enhanced visual stories from simple prompts. The demand for personalized, AI-generated visual content for autism support is growing globally.

## Communication Tools That Learn and Adapt
For many autistic children, communication is the central challenge of daily life. Whether your child uses spoken language, sign language, picture exchange, or a speech-generating device, the tools available have changed dramatically in the last few years.
**AI-powered augmentative and alternative communication (AAC) apps** now use predictive language modeling that learns from your child's communication patterns. Instead of scrolling through hundreds of symbols to find the right word, the system learns which words your child uses most in specific contexts and brings them forward. Research on one such system showed a roughly 30 percent reduction in message construction time, which can make the difference between a child communicating their needs and giving up in frustration.
These tools can now recognize not just words but gestures, breathing patterns, and eye movements to predict communicative intent. For children who communicate through non-traditional means, AI is opening doors that did not exist five years ago.
**The American Speech-Language-Hearing Association (ASHA) confirms** that AAC devices do not slow down speech development. They actually support the production of speech and are used alongside verbal communication, not instead of it. If you have been hesitant about AAC because someone told you it would prevent your child from talking, the research says otherwise.
A tablet-based program called EMooly, which integrates generative AI and augmented reality, was tested in a controlled study with 24 autistic children. The results showed significant improvements in emotion recognition skills, a critical building block for social communication. This matters because understanding emotions in others is one of the skills that families tell us they wish they could support more effectively at home.
## Emotion Recognition and Behavior Tracking
One of the most exhausting parts of parenting an autistic child is trying to figure out what triggered a meltdown when your child cannot tell you. Was it the noise? The change in routine? Something that happened at school three hours ago? The detective work is relentless.
AI is starting to help with that detective work in meaningful ways.
**Emotion recognition technology** using camera-based facial expression analysis and audio pattern detection has reached 90 percent accuracy in research settings. One system achieved real-time detection of seven distinct emotions, and adults with autism were able to adapt to the system in approximately 19 minutes.
For families, this has practical implications. [Tracking your child's emotions and behaviors](/blog/tracking-emotions-activities-neurodivergent-children) over time can reveal patterns that are invisible in the moment. AI-powered tracking tools are starting to analyze these patterns automatically, identifying connections between environmental triggers and behavioral responses that would take a human observer weeks or months to notice.
In the therapy world, AI-driven analytics in ABA software can now flag when a child is at risk of plateauing or regressing, allowing therapists to adjust strategies before progress stalls. A 12-month observational study of 43 children published in JMIR Neurotechnology found that an AI-based therapy platform was an effective supplement for enhancing therapeutic outcomes across cognitive, social, and developmental domains.
This does not replace the therapist. It gives the therapist better data, faster.
## Smarter IEPs and Classroom Support
If you have ever sat through an IEP meeting feeling like the goals were too vague, too generic, or completely disconnected from what your child actually needs at home, you are not alone. IEP quality for students with autism varies significantly, and many plans do not adequately prepare students for real-world skills.
AI is changing how [IEPs](/blog/504-plan-vs-iep-neurodivergent-child) are developed and tracked. Platforms like Expert IEP and EZducate use machine learning to align activities with specific IEP goals, track behavioral patterns, and integrate therapy homework into the school day. Research has found that ChatGPT-assisted IEP goal setting produces goals that are higher quality, more personalized, and more comprehensive across developmental domains.
**A 2025 systematic review** confirmed that AI-powered adaptive learning systems significantly enhance accessibility and social-emotional development for students with autism, ADHD, and dyslexia. These platforms adjust content, pacing, and delivery in real time based on how a student interacts with the material. For a child who needs more repetition on one concept but can skip ahead on another, this kind of personalization was previously impossible without one-on-one instruction.
AI is also showing up in pre-employment transition services, helping autistic youth build career readiness skills before they face the [services cliff after high school](/blog/autism-services-cliff-after-high-school). This is especially important given that employment rates for autistic adults remain far below those of the general population.
## Your Home Is Getting Smarter Too
Some of the most practical AI applications for autism families are the simplest ones.
**Voice assistants** can send reminders for daily tasks, prompt routine steps, and help children manage their own schedules with simple voice commands. For a child who struggles with the multi-step process of getting ready in the morning, a smart speaker that walks them through each step, brush teeth, get dressed, pack backpack, can build [independence](/blog/building-independence-neurodivergent-children) without requiring a parent to stand over them repeating instructions.
**Smart lighting systems** with customizable brightness and color temperature are becoming a key accommodation for families managing [sensory sensitivities](/blog/sensory-processing-disorder-daily-routines). Adjustable LED lights that minimize glare and flickering, which are particularly disruptive for individuals with sensory differences, can reduce the environmental triggers that contribute to meltdowns.
Smart thermostats, white noise machines, and programmable environments all serve the same purpose: creating predictable, controllable spaces that reduce anxiety. For families where a change in the room's lighting or temperature can cascade into a difficult afternoon, these tools offer meaningful relief.
## AI in Diagnosis: Earlier Answers for Families
One of the most significant developments is happening before families even begin building daily routines.
**Cognoa's Canvas Dx** became the first FDA-authorized AI-based diagnostic aid for autism, designed to help diagnose or rule out autism in children ages 18 months to 6 years. Instead of waiting months or years for a specialist evaluation, the system analyzes caregiver questionnaires, physician observations, and video of the child to provide faster answers.
A separate tool from Duke University, SenseToKnow, correctly detects autism 88 percent of the time using a digital screening app. For families who are navigating the often agonizing wait for a formal [diagnosis](/blog/autism-diagnosis-what-to-do-next), AI-powered screening tools can provide earlier indicators that allow parents to begin support sooner rather than later.
Earlier identification means earlier intervention. And the research on early intervention is unambiguous: starting support before age three is associated with significantly better outcomes in communication, daily living skills, and social engagement.
## What AI Cannot Do
Honesty matters here. AI is a tool, not a savior. And it comes with real limitations that every family should understand.
**AI does not replace human connection.** No app, algorithm, or smart device substitutes for the relationship between a child and their therapist, teacher, or parent. The most effective autism interventions are relational. AI can enhance those relationships by providing better tools, better data, and more personalized support, but it cannot replace the human being delivering the care.
**Privacy deserves serious attention.** Stanford's 2025 AI Index Report found that AI-related data privacy risks surged 56 percent. When AI tools collect data about your child's behavior, communication patterns, or daily routines, that data needs to be protected. Before adopting any AI-powered tool, understand how your child's data is stored, who has access to it, and whether it can be deleted.
**Screen time still matters.** The American Academy of Pediatrics now focuses more on content quality than strict time limits, but the principle holds: technology should supplement face-to-face interaction, not replace it. For families using AI-powered visual supports, [first-then boards](/blog/first-then-boards-guide), or [social stories](/blog/social-stories-autism-guide), the goal is to use the tool to prepare for real-world situations, then put the device down and live them.
**AI bias is a real concern.** If an AI system was trained primarily on data from one demographic, it may not work equally well for all children. Families and providers should watch for tools that do not reflect their child's background, culture, or communication style.
The American Occupational Therapy Association has cautioned against technology designed to "normalize" autistic behaviors, noting that support should focus on autonomy and quality of life rather than enforcing neurotypical standards. This is an important distinction. The best AI tools meet your child where they are, rather than trying to make them someone they are not.
## What This Means for Your Family
You do not need to adopt every new technology that appears. You do not need a smart home filled with sensors and cameras. You do not need to turn your parenting into a data science project.
What you can do is pay attention to the tools that solve the specific problems your family faces. If mornings are the hardest part of your day, an AI-powered visual schedule that shows your child their actual routine in images they connect with might make more difference than any other single change. If communication is the barrier, an AAC app with predictive capabilities might unlock conversations you did not think were possible yet. If you are drowning in IEP paperwork, an AI-assisted platform might help you advocate more effectively for your child.
The families who benefit most from AI are not the ones who use the most technology. They are the ones who choose the right tools for their specific challenges and use them consistently.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built by a parent navigating this same journey. We use AI to create the personalized [visual routines](/blog/visual-schedules-for-autism) and [social stories](/blog/social-stories-autism-guide) that research shows make a real difference, because every child deserves to see themselves succeeding in their own day. Not a stock photo child. Not a clip art version of someone else's life. Their life.
The technology is here. The evidence supports it. And your family deserves tools that actually work.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) uses AI-generated images to create personalized visual routines for neurodivergent children. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and see what happens when your child's schedule finally looks like their real life.
---
## The Cliff Nobody Tells You About: Navigating Autism Services After High School
Published: 2026-03-23
URL: https://vizyplan.com/blog/autism-services-cliff-after-high-school
Category: Strategies
Author: Justin Bowman
> When your child with autism graduates high school, most services disappear overnight. Here is what every family needs to know about the services cliff and how to prepare before it hits.
For years, you have built a support system around your child. Speech therapy. Occupational therapy. An IEP with goals reviewed every year. A team of professionals who know your child by name. Then one day, your child walks across a stage, picks up a diploma, and almost everything disappears.
This is the services cliff. And for the roughly 50,000 Americans with autism who turn 18 each year, it is one of the most disorienting transitions a family will ever face.
If your child is still young, you might not be thinking about this yet. But the families on the other side of it will tell you the same thing: they wish someone had told them sooner.
## What the Services Cliff Actually Means
The services cliff describes the dramatic drop in support that happens when autistic individuals age out of the school system, typically between ages 18 and 22 depending on the state. Under federal law, every child with a disability is entitled to a Free Appropriate Public Education through the Individuals with Disabilities Education Act. That word, entitled, is the one that matters most.
**Under IDEA, services come to your child.** The school district is legally obligated to identify, evaluate, and provide support. You do not have to apply. You do not have to prove eligibility. Your child has a right to services, and the school bears the burden of delivering them.
**After graduation, everything flips.** The adult system operates on eligibility, not entitlement. Your child, now a legal adult, must apply for every service, prove they qualify, and often wait months or years to receive support that used to arrive automatically. As one resource guide from PAAutism puts it: "Under IDEA, children are entitled to services. After school, adults must prove eligibility. This is the fundamental shift that creates the services cliff."
That shift is not just philosophical. The numbers tell a devastating story.
## The Numbers Behind the Cliff
Research from Drexel University's A.J. Drexel Autism Institute has documented what happens after graduation in detail that every parent should see.
**Services vanish almost overnight.** Three out of four children on the autism spectrum receive speech therapy during school. After graduation, fewer than one in ten continue receiving it. More than half of autistic adults receive no vocational or life skills services following high school. Approximately 26 percent of young adults on the spectrum receive no services at all.
**Disconnection is the norm, not the exception.** Thirty-seven percent of autistic young adults were completely disconnected during their early twenties, meaning they never got a job or continued education after high school. For comparison, fewer than 8 percent of young adults with other types of disabilities experienced the same disconnection.
**The decline starts before graduation.** Research published in the National Institutes of Health found that with each passing year of high school, students with autism received fewer services. By the time graduation arrives, the cliff has already begun.

## Why Employment Numbers Are So Alarming
The employment picture for autistic adults is one of the starkest indicators of how the system fails after high school.
**Unemployment rates range from 40 to 85 percent** depending on the study and how underemployment is measured. Only about 58 percent of young adults on the spectrum worked for pay at all between high school and their early twenties, far lower than young adults with learning disabilities (90 percent) or even intellectual disabilities (74 percent).
**When autistic adults do find work, it is often part-time and low-wage.** Among those who became employed after vocational rehabilitation services, 80 percent worked part-time with median weekly earnings of just $160. Forty-five percent of employed autistic adults work part-time, compared to 19 percent of the general population.
These are not numbers about capability. They are numbers about a system that does not bridge the gap between the structured support of school and the unstructured demands of adulthood. Many autistic adults want to work. Research shows 60 to 70 percent report wanting gainful employment. The infrastructure to get them there is what falls short.
## Independent Living and the Reality Families Face
The housing picture is equally sobering. Eighty-seven percent of adults on the autism spectrum live with their parents or guardians after high school. Only 5 to 21 percent have ever lived independently.
For many families, this is not a choice. It is the result of a system with waiting lists measured in years and support options that are nearly impossible to navigate without help. The first two years after graduation are especially critical. Research shows this period has the highest rates of complete disengagement from services, employment, and education.
If you are the parent of a younger child and this feels far away, consider this: the average wait time for autism-specific Medicaid waivers is 63 months. That is more than five years. Approximately 607,000 people are currently on waiting lists for home and community-based waiver services. Starting early is not being anxious. It is being strategic.
## Healthcare Falls Through the Cracks Too
One area that rarely gets discussed is the healthcare transition. When your child ages out of pediatric care, finding adult providers who understand autism can feel impossible.
**Less than 9 percent of autistic adolescents** receive recommended guidance on transitioning from pediatric to adult healthcare. Only 14 percent of youth with autism talked with their pediatricians about switching to an adult care doctor. Almost two-thirds of adult physicians received no training in the care of adults with autism.
The result is predictable. As youth with autism leave pediatric care, scheduled outpatient visits decline while emergency service use increases. Families who spent years building relationships with understanding pediatricians are suddenly starting over with doctors who may have little experience with autism.
## What You Can Do Starting Now
The most important thing to understand about the services cliff is that preparation is the single best tool you have. The families who fare best on the other side are the ones who started planning years before graduation.
### If Your Child Is 14 or Younger
This is earlier than most parents think about transition, but it is exactly when preparation should begin.
**Push for strong transition goals in the IEP.** Federal law requires transition planning by age 16, and some states require it by 14. Do not wait for the school to bring it up. Request that [IEP meetings](/blog/504-plan-vs-iep-neurodivergent-child) include specific, measurable postsecondary goals related to employment, education, and independent living.
**Build independent living skills into daily life.** Cooking, laundry, hygiene routines, money management, and using transportation are all skills that can be practiced for years before they are needed. [Visual schedules](/blog/visual-schedules-for-autism) break complex tasks into steps your child can follow independently. [First-then boards](/blog/first-then-boards-guide) help motivate practice of less-preferred skills. These are not just classroom tools. They are life tools.
**Apply for the Medicaid waiver waitlist.** With average wait times exceeding five years, getting on the list now is critical even if your child does not need services yet. Contact your state's developmental disabilities agency to understand what waivers are available and how to apply. We covered financial resources in detail in our guide to [autism funding and programs](/blog/autism-funding-programs-financial-support-families).
**Teach self-advocacy.** In the adult world, your child will need to explain their needs, request accommodations, and navigate systems that are not designed for them. Start by including your child in IEP meetings. Let them practice asking for what they need in low-stakes situations. Self-advocacy is a skill that develops over time, not something that appears at 18.
### Ages 16 to 18: The Critical Window
**Apply for SSI.** At age 18, Supplemental Security Income no longer considers parental income when determining financial eligibility. This is a significant shift that makes many young adults newly eligible. The current maximum SSI benefit is $943 per month.
**Open an ABLE account.** The Achieving a Better Life Experience Act allows individuals with disabilities to save up to $19,000 per year in tax-advantaged accounts without losing eligibility for SSI or Medicaid. Starting in 2026, the eligibility age expands from 26 to 46. Qualified expenses include education, housing, transportation, employment support, assistive technology, and healthcare.
**Connect with Vocational Rehabilitation.** Every state runs a VR program that provides career counseling, job training, placement assistance, and supported employment. Referrals can happen before graduation. Do not wait until your child is unemployed to make this connection.
**Research guardianship alternatives.** When your child turns 18, they become a legal adult regardless of their disability. You will need to decide whether to pursue guardianship, power of attorney, or supported decision-making. Supported decision-making is increasingly recommended because it preserves the individual's legal rights while creating a network of trusted people to help with decisions. Explore the options now so you are not making this choice under pressure.
**Plan the healthcare transition.** Start looking for adult providers who have experience with autism. Ask your current pediatrician for referrals. Request that your child's medical records, therapy history, and [diagnosis documentation](/blog/autism-diagnosis-what-to-do-next) are organized and accessible.
### Before Graduation
**Request a Summary of Performance.** This document from the school summarizes your child's disability, accommodations, and supports. You will need it when applying for adult services.
**Secure all educational and medical records.** Gather IEP documents, evaluations, therapy notes, and medical records. Adult service providers will want this documentation, and getting it after your child leaves the school system becomes significantly harder.
**Request a comprehensive evaluation.** Schools are required to provide one before a student ages out. This evaluation can serve as documentation for adult service applications and establish a baseline for future needs.
## Understanding Your Financial Options
Financial planning is one of the areas where early action pays the most dividends. Several programs exist specifically for individuals with disabilities, but navigating them requires understanding how they interact.
**ABLE accounts** allow tax-free savings for disability-related expenses without jeopardizing means-tested benefits. The 2026 contribution limit is $19,000 per year, and families can roll over funds from 529 education savings plans into ABLE accounts.
**Special needs trusts** can hold assets without affecting SSI eligibility. Unlike ABLE accounts, there is no annual contribution limit, making them useful for larger inheritances or settlements.
**SSI and SSDI** serve different purposes. SSI is need-based and does not require work history. SSDI is available through the Disabled Adult Child benefit, which allows adults disabled before age 22 to receive benefits based on a parent's Social Security record.
A special needs financial planner can help you understand how these programs work together for your family's specific situation.
## The Caregiver Side of the Cliff
The services cliff does not just affect the autistic individual. It reshapes the entire family.
Research shows that 45 percent of autism caregivers experience depressive symptoms. Caregivers have 3.6 times higher odds of chronic stress compared to non-autism caregivers. Nearly three-quarters of primary caregivers are female, and the majority are mothers who often reduce or leave employment to fill the gaps that disappear after graduation.
One parent described the transition this way: "After school ends, we will become his teachers 365 days a year without any breaks for the rest of our lives. It is wholly our responsibility to try to make him able to care for himself as best we can before we die. Many of the autism parents we know refer to this moment in our collective lives as the cliff."
If you are feeling the weight of this, you are not alone. [Caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children) is a predictable consequence of sustained stress without adequate support. Taking care of yourself is not optional. It is part of taking care of your child.
## The System Is Broken, But You Are Not Powerless
Let us be honest about what this article describes. It describes a system that works reasonably well for children and then largely abandons them and their families at 18. It describes waiting lists that last longer than high school itself. It describes a shift from entitlement to eligibility that leaves families scrambling during one of the most vulnerable periods of their child's life.
That is the reality. And pretending otherwise does not help anyone.
But here is the other reality. Families who start early, who understand the system before they need it, who build skills and connections and financial plans years before graduation, those families navigate the cliff with more stability. Not because the system works for them, but because they prepared for a system that does not.
You are reading this article. That already puts you ahead of most families, many of whom do not learn about the services cliff until they are standing at the edge of it.
## Where to Start Today
If this article has you feeling overwhelmed, start with one action. Just one.
If your child is under 14, bring up [transition planning](/blog/transition-strategies-autism) at the next IEP meeting. If your child is 14 to 17, contact your state's developmental disabilities agency and ask about waiver waitlists. If your child is 17 or older, apply for SSI and connect with your state's Vocational Rehabilitation office.
The cliff is real. But you do not have to face it unprepared.
---
[VizyPlan](https://vizyplan.com) helps families build the visual routines and independent living skills that matter most during the transition to adulthood. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child tools for independence that grow with them.
---
## What the RFK Jr. Autism Debate Means for Families Like Ours
Published: 2026-03-22
URL: https://vizyplan.com/blog/rfk-jr-autism-debate-families
Category: Strategies
Author: Justin Bowman
> Autism is at the center of a national debate. Here is what actually matters for your family right now, no matter where you stand.
You have seen the headlines. Autism is at the center of a national conversation unlike anything in recent memory. Promises of new research. Debates about causes. Funding changes that could reshape the services your family relies on. It is a lot to take in, especially when you are already navigating the daily realities of raising a neurodivergent child.
No matter where you fall on the political spectrum, one thing is true: your child still needs support today. And the noise coming from Washington can make it hard to figure out what actually matters for your family right now.
Let us cut through it.
## What Is Happening Right Now
Since taking the role of HHS Secretary, Robert F. Kennedy Jr. has placed autism at the center of federal health policy in ways that have drawn both praise and criticism.
In April 2025, the administration announced a large-scale research initiative to explore environmental causes of autism, including food additives, pesticides, medications, and prenatal factors. Kennedy pledged to have preliminary answers by September 2025, a timeline later pushed to March 2026.
The initiative drew national attention. It also drew controversy. A proposed national autism registry was introduced and then withdrawn after more than 80 organizations raised privacy concerns. NIH spending on autism-related research fell 26 percent in the first four months of 2025, dropping from $147 million to $116 million. The Interagency Autism Coordinating Committee was overhauled with entirely new members, some of whom hold views that diverge from established scientific consensus.
In response, leading autism researchers formed an independent panel called the Independent Autism Coordinating Committee, which held its first meeting on March 19, 2026.
Meanwhile, Congress approved nearly $1 trillion in Medicaid cuts over the next decade. For many families raising autistic children, Medicaid is the primary payer for therapy services.

## Where Parents Stand
This is where it gets personal. And this is where honesty matters most: parents are not a monolith. Families in the autism community hold a wide range of views, and all of them come from a place of love for their children.
**Some parents welcome the attention.** A KFF/Washington Post survey from October 2025 found that roughly 4 in 10 American parents identify with the "Make America Healthy Again" movement. Many of these parents feel that rising autism rates have not been taken seriously enough and that environmental factors deserve more investigation. They appreciate that someone in a position of power is treating autism as a national priority, and they want research into questions they feel have been dismissed.
**Other parents are deeply concerned.** Advocacy organizations including the Autism Society of America, the Autistic Self Advocacy Network, and the Autism Science Foundation have raised alarms about research funding cuts, the framing of autism as something to be "prevented," and the appointment of advisory panel members whose views conflict with the existing body of research. Many autistic adults and their families worry that the current direction could set back decades of progress on acceptance and inclusion.
**And many parents are simply exhausted.** They are not tracking the politics. They are tracking therapy waitlists, [IEP meetings](/blog/504-plan-vs-iep-neurodivergent-child), and how many meltdowns happened before 9 AM. For these families, the debate in Washington feels disconnected from what they actually need: shorter waitlists, affordable services, and tools that help their child get through the day.
All three of these perspectives are valid. All three exist in the same community. And the truth is, you do not have to pick a side to take care of your child.
## What Science Tells Us About Autism's Causes
The scientific picture is complex, and being honest about that complexity is important.
Research consistently shows that autism is 60 to 90 percent heritable. Genetics are the primary contributing factor, with hundreds of genes implicated across large-scale studies. A major 2025 study from Princeton identified biologically distinct subtypes of autism with different genetic backgrounds, suggesting that autism may not be a single condition but several related ones with different underlying biology.
At the same time, researchers acknowledge that some portion of the increase in prevalence may reflect genuine growth, and environmental factors during pregnancy and early development continue to be studied. A Danish study found that 60 percent of the rise in autism diagnoses among children born between 1980 and 1991 was explained by changes in diagnostic criteria and reporting practices. The remaining portion is still being investigated.
The CDC now identifies [1 in 31 children](/blog/1-in-31-autism-diagnosis-rates-daily-life) as having autism spectrum disorder. Most experts attribute the rising numbers primarily to broadened diagnostic criteria, improved screening, greater awareness, and better access for underserved communities. But the scientific community supports continued research into all contributing factors, including genetic, environmental, and prenatal influences.
What researchers broadly agree on is that the debate about causes should not delay the support that children and families need right now.
## What Actually Matters for Your Family
Regardless of where you stand on the political debate, here is what directly affects your daily life.
### Medicaid Funding Is the Biggest Immediate Concern
Nearly $1 trillion in Medicaid cuts were approved by Congress, set to take effect at the end of 2026. Medicaid is the primary payer for autism services for many families, covering therapies that private insurance often limits or excludes entirely.
Several states are already pulling back. North Carolina attempted a 10 percent rate cut for ABA providers. Nebraska cut provider payments by nearly 50 percent. Additional cuts are being considered in Colorado and Indiana. ABA therapy without insurance runs $120 to $150 per hour, and the estimated lifetime cost of raising a child with autism ranges from $1.4 to $2.4 million.
If your child receives therapy through Medicaid, now is the time to understand your state's specific plans. Contact your state representative. Reach out to organizations like Autism Speaks or your state's Autism Society chapter for advocacy toolkits. This is not a partisan issue. Families across the political spectrum rely on these services. We covered financial resources in detail in our guide to [autism funding and programs](/blog/autism-funding-programs-financial-support-families).
### Research Funding Has Been Reduced
NIH autism research funding dropped 26 percent in early 2025. The Department of Defense, which previously directed $15 million annually toward autism research, did not include autism among its funded programs. More than 50 autism-related studies lost funding, and over half of surveyed researchers reported that they or colleagues in their lab could lose their jobs.
Whether you believe the administration's research priorities are moving in the right direction or the wrong one, the reduction in overall funding is a measurable reality. Less research means slower progress on the questions all families share: What supports work best? How do we identify autism earlier? What interventions lead to the strongest outcomes?
### Special Education Services Face Uncertainty
IDEA funding, which supports special education services in public schools, faces potential restructuring. Medicaid reimbursements that schools depend on for speech therapy, counseling, and occupational therapy are also at risk. If your child has an [IEP or 504 plan](/blog/504-plan-vs-iep-neurodivergent-child), staying connected with your school district about how federal changes might affect local services is important.
### Early Intervention Remains the Strongest Evidence We Have
Here is the one thing every researcher, every advocacy organization, and every clinician agrees on, regardless of their position in the broader debate: early intervention works.
A systematic review of multiple studies found that early intensive behavioral interventions before age three are associated with IQ improvements of 9 to 15 points and significant gains in communication and daily living skills. The National Clearinghouse on Autism Evidence and Practice recognizes 28 evidence-based practices for autism, including visual schedules, structured routines, [social stories](/blog/social-stories-autism-guide), and reinforcement systems.
The political debate about what causes autism may take years to resolve. The evidence about what helps autistic children thrive is already here.
## What You Can Do Right Now
You do not have to wait for Washington to act. Here is what is within your control today.
**Build structure at home.** [Visual schedules](/blog/visual-schedules-for-autism) reduce anxiety and increase independence for neurodivergent children. [First-then boards](/blog/first-then-boards-guide) help with transitions. [Social stories](/blog/social-stories-autism-guide) prepare your child for new or challenging situations. These are not just nice-to-have tools. They are evidence-based practices supported by decades of research.
**Track patterns.** [Monitoring your child's emotions and behaviors](/blog/tracking-emotions-activities-neurodivergent-children) gives you data to bring to therapy sessions, school meetings, and medical appointments. Pattern tracking turns "I feel like things are getting harder" into "Here is exactly what is happening and when."
**Advocate locally.** Your child's school, your state legislature, and your insurance company are the decision-makers who most directly affect your family. Know your rights under IDEA. Attend school board meetings. Call your state representative about Medicaid funding. The most effective advocacy happens close to home.
**Protect your own wellbeing.** Research shows that 45 percent of autism caregivers experience depressive symptoms. One in five is at risk for burnout. [Caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children) is not a sign of weakness. It is a predictable consequence of sustained stress without adequate support. Getting help for yourself is getting help for your child.
**Stay informed, but set boundaries.** The news cycle around autism is intense right now. It is okay to limit your media consumption. It is okay to step away from social media threads that leave you feeling worse instead of better. Stay informed about the policy changes that directly affect your family, but do not let the broader debate consume the energy you need for your child.
**Connect with other families.** Whether through local support groups, online communities, or the parent sitting next to you in the therapy waiting room, connection matters. Isolation is one of the most common experiences parents report after an [autism diagnosis](/blog/autism-diagnosis-what-to-do-next), and it does not have to stay that way.
## The Debate Does Not Define Your Family
Autism is in the headlines for many reasons right now. Some of those reasons could lead to positive change. Some could make things harder. Most families will not know the full impact for years.
But here is what we do know. Your child is the same child they were before the debate started. They still light up at the things that bring them joy. They still need the same patience, structure, and love they needed yesterday. And the tools that help them, the visual supports, the predictable routines, the patient repetition of skills, those do not change with election cycles or policy shifts.
[One in 31 children](/blog/1-in-31-autism-diagnosis-rates-daily-life) is now identified with autism. That number represents millions of families who are showing up every single day. You are part of that community. And you and the parent who disagrees with you politically have far more in common than you might think. You both stayed up too late last night. You both worry about the future. And you both want the absolute best for your child.
Start there.
---
[VizyPlan](https://vizyplan.com) helps you build the daily structure and visual supports that research shows make a real difference for neurodivergent children. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child evidence-based tools today, because your family does not have to wait for Washington to act.
---
## 1 in 31: What the New Autism Numbers Mean for Your Family
Published: 2026-03-21
URL: https://vizyplan.com/blog/1-in-31-autism-diagnosis-rates-daily-life
Category: Strategies
Author: Justin Bowman
> The CDC now reports 1 in 31 children has autism. What is driving the increase, what it means for services and schools, and what families should do right now.
The number landed in April 2025 and it has been circulating ever since. One in 31. According to the CDC's Autism and Developmental Disabilities Monitoring Network, 1 in 31 eight-year-old children in the United States is now identified with autism spectrum disorder. That is 3.2 percent of all children in this age group, up from 1 in 36 just two years earlier.
If your child is one of them, or if you are waiting on an evaluation and wondering whether the wait will ever end, this number is not abstract. It is your morning. It is your IEP meeting. It is the therapist waitlist you have been on for months. Let us talk about what these numbers actually mean for families living this every day.
## How We Got from 1 in 150 to 1 in 31
When the CDC began tracking autism prevalence in 2000, the rate was 1 in 150. In 2010 it was 1 in 68. By 2018 it had climbed to 1 in 44. Two years ago it was 1 in 36. Now it is 1 in 31. The current rate is 4.8 times higher than when surveillance began 22 years ago.
These numbers come from the ADDM Network, which reviewed medical and educational records of eight-year-old children across 16 sites in 14 states plus Puerto Rico. This is not a parent survey or a physician estimate. It is a records-based surveillance system, and the 2022 report is the largest the CDC has ever published.
The question everyone asks is the obvious one: are more children actually autistic, or are we just better at finding them?
## Why the Numbers Keep Rising
The honest answer is that both factors are at work, but detection accounts for the majority of the increase.
**Screening has improved dramatically.** Pediatricians now routinely screen for autism at 18 and 24 months. Programs like California's "Get SET Early" model trained hundreds of doctors to identify and refer children earlier. California now has the highest identified prevalence in the country at 1 in 19, not because California has more autistic children, but because California finds them.
**Diagnostic criteria are broader.** When the DSM-5 was published in 2013, it consolidated Asperger's Syndrome, PDD-NOS, and classic autism into a single Autism Spectrum Disorder diagnosis. Children who previously fell into separate categories or received no diagnosis at all now appear under one umbrella.
**Awareness has reduced stigma.** Parents are more willing to seek evaluations. Teachers are more likely to recognize signs. The cultural conversation around neurodivergence has shifted enough that families pursue answers instead of waiting and hoping.
**Underserved communities are finally being reached.** For the first time in the history of the ADDM Network, non-white children are identified at higher rates than white children. Black children are now diagnosed at a rate of 1 in 27. Asian and Pacific Islander children at 1 in 26. This is not because autism suddenly became more common in these communities. It reflects the closing of a diagnostic gap that left generations of children without the support they needed.
Dr. Zachary Warren, lead author of the MMWR report and executive director of Vanderbilt Kennedy Center's TRIAD program, put it this way: "The most striking piece of this is how unbelievably common presentations of autism are."
Dr. Alex Kolevzon, director of Mount Sinai's Seaver Autism Center, offered important perspective: "Parents should not panic. We are not seeing an epidemic with autism."
The Autism Society of America was direct: "This rise in prevalence does not signal an 'epidemic.' It reflects diagnostic progress."
## The Gender Gap Is Still Wide
Boys are diagnosed at a rate of 1 in 20. Girls at 1 in 70. That 3.4-to-1 ratio has held relatively steady across years of data, but researchers widely agree that [girls are still significantly underdiagnosed](/blog/signs-autism-adhd-girls-underdiagnosis).
Girls with autism are more likely to mask their symptoms, mimicking social behavior they observe in peers and camouflaging their struggles until the cognitive and emotional cost becomes unsustainable. Many girls do not receive a diagnosis until adolescence or adulthood, long after the window for early intervention has closed.
If you have a daughter who seems to be struggling socially but "holds it together" at school and falls apart at home, the new prevalence data reinforces what many parents already suspect: [the signs in girls look different](/blog/signs-autism-adhd-girls-underdiagnosis), and the diagnostic system has not fully caught up.
## Where You Live Changes Everything
The geographic variation in the CDC data is staggering. A 5.5 times difference separates the highest and lowest sites.
California identifies autism at a rate of 1 in 19. Texas (Laredo) identifies it at 1 in 103. The same child who would receive a diagnosis, services, and school support in one state might go entirely unidentified in another.
The CDC was clear about what drives this gap: "Differences in ASD prevalence are likely due to differences in evaluation and testing practices." It is not that some states have more autistic children. It is that some states are looking and others are not.
This matters enormously for families. If you live in a state with lower identification rates, the burden of advocacy falls harder on you. Knowing the national data gives you evidence to push for evaluations, services, and accommodations that your local system might not be offering proactively.
## The Service Gap That Keeps Getting Wider
Here is where the story stops being about statistics and starts being about daily life.
The average wait from a parent's first concern to a completed autism evaluation is three years. Sixty-one percent of diagnostic centers have wait times longer than four months. Fifteen percent have waits over a year or have closed their waitlists entirely.
Once you have a diagnosis, the waiting continues. Seventy-five percent of caregivers report spending time on a waitlist for ABA therapy, with an average wait of 5.7 months. Out-of-pocket ABA costs run $150 to $200 per hour without insurance coverage.
Meanwhile, schools are absorbing the impact. In the 2022-23 school year, 7.5 million students received special education services under IDEA, and autism alone accounted for 40 percent of the total increase in special education enrollment. Schools are scrambling for speech therapists, occupational therapists, and behavior specialists who are in desperately short supply.
Sixty-nine percent of specialists cite workforce shortages as the primary barrier to timely evaluations. The children are being identified. The systems built to serve them have not kept pace.
## What This Means for Your Child Right Now
If your child has already been [diagnosed](/blog/autism-diagnosis-what-to-do-next), these numbers validate what you have been living. The classroom is more crowded with need. The therapist has a longer waitlist. The school district is stretched thinner. None of that is your fault, and none of it reduces your child's right to appropriate services.
If you are waiting for an evaluation, do not let the wait be idle time. Early intervention produces the strongest outcomes when it begins before age three, during a period of heightened brain plasticity. Research shows early intensive behavioral interventions are associated with IQ gains of 9 to 15 points and significant language improvements.
Here is what you can do while you wait.
**Document everything.** Keep a log of behaviors, milestones, and concerns. This becomes valuable evidence at the evaluation and at future [IEP meetings](/blog/collaborating-providers-iep-visual-tools). Track [emotional and behavioral patterns](/blog/tracking-emotions-activities-neurodivergent-children) so you walk in with data, not just observations.
**Start building visual structure at home.** You do not need a diagnosis to begin using [visual schedules](/blog/visual-schedules-for-autism), [first-then boards](/blog/first-then-boards-guide), and [social stories](/blog/social-stories-autism-guide). These evidence-based strategies help all children, and they are especially effective for children who struggle with transitions, routines, and [emotional regulation](/blog/emotional-regulation-visual-supports).
**Learn your rights.** Under IDEA, children suspected of having a disability are entitled to evaluation by the school district regardless of whether they have a medical diagnosis. You do not have to wait for a clinical evaluation to request a school-based assessment. A [504 plan or IEP](/blog/504-plan-vs-iep-neurodivergent-child) can begin while you are still on the diagnostic waitlist.
**Explore [funding and programs](/blog/autism-funding-programs-financial-support-families).** Medicaid's EPSDT program, SSI, state grants, and insurance mandates exist in all 50 states. Many families leave thousands of dollars on the table because they do not know what is available.
**Find [the right therapist](/blog/finding-right-therapist-neurodivergent-child).** Not every provider is the right fit. Ask about their experience, approach, and whether they work collaboratively with families. The relationship matters as much as the credential.
## The Diagnostic Disparity That Still Exists
The median age of autism diagnosis is 47 months, just under four years old. Only half of children are diagnosed by age three. That means half of all autistic children are missing the most critical window for early intervention.
The disparities are not random. Higher-income families are significantly more likely to receive early intervention before age two. Lower-income families face additional barriers navigating complex systems with fewer resources and less flexibility.
Children from non-white families, despite now being identified at higher rates overall, are still disproportionately diagnosed only when co-occurring intellectual disability is present. Black children diagnosed with ASD have a 78.9 percent rate of co-occurring intellectual disability or borderline scores, compared to 55.6 percent for white children. This suggests that non-white children with ASD who do not have intellectual disability are still being missed.
The numbers are improving. But "improving" and "equitable" are not the same thing.
## What These Numbers Do Not Mean
These numbers do not mean your child's autism was caused by something you did. Research consistently shows that up to 90 percent of autism is linked to genetic traits, with hundreds if not thousands of neurogenetic factors at play.
They do not mean that autism is a disease that needs to be cured or prevented. The Autism Society of America stated clearly: "Claiming that Autism is 'preventable' is not science based, and places unnecessary blame on people, parents, and families."
And they do not mean that your child's future is determined by a statistic. Prevalence data tells us how many children are identified. It says nothing about who those children will become, what they will accomplish, or how much joy they will bring to the people around them.
## What These Numbers Do Mean
They mean your child is not rare. They mean the family sitting next to you in the waiting room is not unusual. They mean that one in every classroom of 31 children is navigating the same invisible challenges your child faces every day.
They mean we need more therapists, more funding, shorter waitlists, and school systems that are resourced to meet the actual demand. They mean that early screening works, that reaching underserved communities matters, and that every child deserves a path to [diagnosis](/blog/telling-child-about-autism-adhd-diagnosis) and support regardless of zip code or income.
And for you, right now, sitting in a kitchen that still has this morning's [breakfast battle](/blog/mealtime-strategies-picky-eating-autism-adhd) on the table and tonight's [bedtime routine](/blog/bedtime-routine-autism-adhd) already on your mind, they mean one thing above all: you are not alone. Not even close.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual schedules](/blog/visual-schedules-for-autism) that bring structure to your child's day while you wait for services, use [first-then boards](/blog/first-then-boards-guide) to reduce transition meltdowns, track [emotional and behavioral patterns](/blog/tracking-emotions-activities-neurodivergent-children) to bring real data to evaluations and IEP meetings, and create [social stories](/blog/social-stories-autism-guide) that prepare your child for new experiences. Just $6.99/month after your trial, no credit card required upfront.
---
## Neurodivergent Children and Pets: What the Research Actually Shows
Published: 2026-03-20
URL: https://vizyplan.com/blog/neurodivergent-children-and-pets-therapeutic-benefits
Category: Strategies
Author: Justin Bowman
> Research-backed benefits of pets for children with autism and ADHD, which animals work best, and how to introduce a pet using visual supports and gradual exposure.
Your child does not make eye contact with the new neighbor. She will not answer questions from the cashier at the grocery store. She melts down when plans change and retreats to her room when guests come over. But when she sits on the floor next to the family dog, something shifts. She talks to him. She rests her head against his side. She tells him about her day in full sentences that she would never offer a person.
If you have seen this happen, you are not imagining it. Research confirms what parents of neurodivergent children have noticed for years: animals reach children in ways that people sometimes cannot.
## The Science Behind the Bond
The research on animals and neurodivergent children is not anecdotal. It is measurable.
A 2010 study published in *Psychoneuroendocrinology* tracked cortisol levels in 42 children with autism before, during, and after living with a service dog. The cortisol awakening response, a biological marker for stress, dropped from a 58 percent morning spike to just 10 percent when the dog was present. When the dog was temporarily removed, cortisol jumped back to 48 percent. That is not a placebo effect. That is physiology.
Research from the National Institute of Child Health and Human Development found that children had significantly higher levels of oxytocin when playing with the family dog compared to playing alone with toys. Oxytocin is the hormone linked to bonding, trust, and emotional regulation. For children with autism, whose oxytocin systems may function differently, the simple act of petting a dog can activate calming pathways that social interaction alone does not reach.
A systematic review published in *Frontiers in Veterinary Science* in 2024 analyzed the full body of animal-assisted therapy research for autism and found consistent improvements across multiple domains: quality of life, communication, social development, cognitive skills, and anxiety reduction. Across 22 studies reviewed in a separate analysis, increased social interaction was significant in every single one.
## How Pets Help with Social Skills
One of the most consistent findings in the research is that animals serve as what researchers call a "social lubricant." Children who struggle to connect with peers will often engage freely in the presence of an animal.
Marguerite O'Haire, a researcher at Purdue University, studied what happened when guinea pigs were placed in classrooms with autistic children for eight weeks across 14 Australian schools. The children became significantly more talkative and cheerful. They were more likely to look at faces, make physical contact with peers, and respond to social approaches from classmates. The guinea pig gave them a shared focus, something to talk about that felt safe and predictable.
Gretchen Carlisle at the University of Missouri put it simply: "For children with autism who struggle with communication, having something to talk about and share about that is in common with their peers is very important, and animals can fill that role."
This matters beyond therapy sessions. When your child walks the family dog through the neighborhood, other children approach. They ask the dog's name. They want to pet it. These are organic social interactions that require no coaching, no social skills group, and no script. The dog creates the bridge.
## Emotional Regulation and Stress Reduction
[Emotional regulation](/blog/emotional-regulation-visual-supports) is one of the biggest daily challenges for neurodivergent families. Research consistently shows that pets help.
Families who acquired a dog saw significant reductions on the Parenting Stress Index, with 20 percent of parents moving from clinically high stress to normal levels. OCD-related anxiety scores showed a 26 percent greater decrease in families with pets compared to those without. Children reported feeling calmer, having fewer [meltdowns](/blog/recognizing-triggers-meltdowns-neurodivergent-children), and sleeping better with a pet in the home.
The mechanism is partly biological and partly relational. Stroking a dog or cat activates the parasympathetic nervous system, which lowers heart rate and reduces muscle tension. But there is also the unconditional nature of the relationship. A 2022 study published in the *Journal of Autism and Developmental Disorders* found that autistic individuals described their pets as companions who "ask no questions and pass no criticism." For children who spend their days navigating social expectations they do not fully understand, that acceptance is not trivial.
## Sensory Benefits That Might Surprise You
Many neurodivergent children seek [sensory input](/blog/sensory-processing-daily-routines) throughout the day. Pets provide it naturally.
A large dog lying against a child provides deep pressure therapy, the same calming input that weighted blankets deliver. Temple Grandin, the renowned autistic researcher and animal behavior expert, demonstrated decades ago that deep touch pressure calms the nervous system. A 70-pound Labrador draped across a child's lap delivers that pressure in a warm, breathing, responsive form that no blanket can replicate.
Cats offer a different sensory profile. Their purring produces low-frequency vibrations that many children find deeply soothing. The rhythmic nature of a cat's purr can function as a sensory regulation tool, providing consistent, predictable input that helps a child's nervous system settle.
Even fish can serve a sensory role. The rhythmic movement of fish in an aquarium and the gentle sound of water provide visual and auditory regulation for children who are easily overwhelmed by unpredictable sensory environments. For children with significant sensory sensitivities who cannot tolerate fur, noise, or sudden movement, an aquarium is a meaningful starting point.
## Which Animals Work Best
Not every pet is the right fit for every child. The research points to clear strengths for different animals.
**Dogs** are the most studied and offer the broadest range of benefits: social facilitation, deep pressure, emotional bonding, and routine structure through daily walks and feeding schedules. Trained service dogs can also provide safety benefits for children who [elope or wander](/blog/elopement-wandering-autism-prevention-safety). The tradeoff is that dogs are loud, active, and require significant daily commitment.
**Cats** may be preferred by some autistic children because cats naturally avert their gaze quickly. For children who find sustained eye contact uncomfortable, a cat's communication style can feel less intrusive. Cats are also lower-maintenance and their calm, independent nature suits families who need a less demanding companion.
**Guinea pigs** are backed by strong research as effective companions in structured settings. O'Haire's classroom studies specifically validated their impact. They are active during the day, generally enjoy being held, rarely bite, and are small enough for a child to manage independently. They can be an excellent low-pressure first pet.
**Rabbits** offer a safe, non-threatening presence with soft fur that provides pleasant tactile input. They are a good option for children who are afraid of dogs.
**Fish** require the least interaction but still provide visual sensory regulation and teach basic responsibility through feeding schedules. They are ideal for families who want to introduce the concept of pet care without the complexity of a furry animal.
**Horses** deserve mention because the research on equine-assisted therapy is compelling. A randomized controlled trial found that 10 weeks of therapeutic horseback riding produced significant improvements in irritability, hyperactivity, social skills, and word fluency. Children who continued for a full year showed lasting gains in behavior, academic performance, and communication. Equine therapy is typically accessed through programs rather than pet ownership, but many [grants and funding sources](/blog/autism-funding-programs-financial-support-families) cover it.
## Building Routines and Responsibility Through Pet Care
For children with ADHD, executive function challenges make daily structure difficult. Pets create what researchers describe as non-negotiable time anchors. The dog needs to be fed at 7:00 AM. The cat's litter box needs to be cleaned after school. The fish need food before bedtime. These tasks are concrete, visual, and immediate in their consequences, which makes them easier to internalize than abstract expectations like "clean your room."
Giving your child specific, age-appropriate pet care jobs builds [independence](/blog/building-independence-visual-supports) and self-confidence. A [visual schedule](/blog/visual-schedules-for-autism) showing who is responsible for which pet chores turns vague expectations into clear steps. A [first-then board](/blog/first-then-boards-guide) that shows "First feed the dog, then breakfast" creates a predictable sequence that an ADHD brain can follow without repeated verbal reminders.
The routine benefits extend to the whole family. Parents of children with autism who acquired a pet dog reported significantly improved family functioning. The shared responsibility creates connection points and natural opportunities for cooperation.
## How to Introduce a Pet to Your Neurodivergent Child
Preparation matters more than the day itself. Here is what the research and clinical practice recommend.
**Start with exposure, not ownership.** Visit friends who have pets. Spend time at petting zoos. Watch videos of the specific breed or type of animal you are considering. Gauge your child's sensory responses: does the barking bother them? Do they reach for the fur or pull away? These observations will guide your decision.
**Use social stories before the pet arrives.** Create a simple story that covers what to expect: "Our new cat will live in our house. She might hide at first. That is okay. We will use gentle hands and quiet voices." [Social stories](/blog/social-stories-autism-guide) reduce anxiety by making the unfamiliar feel predictable.
**Create visual supports for pet interactions.** Visual cue cards for "gentle hands," "quiet voice near the pet," and "when the pet walks away, let them go" give your child clear behavioral expectations they can reference in the moment.
**Build a visual pet care schedule.** Before the pet arrives, walk through the daily routine together. Morning feeding, after-school play time, evening walk, bedtime check. Making the routine visible and predictable helps your child feel ownership and competence from day one.
**Set up the environment thoughtfully.** Designate a safe space for the pet that is separate from your child's [calm-down area](/blog/happy-place-mindfulness-neurodivergent-children). Establish pet-free zones if your child needs spaces that are entirely predictable. Remove or secure items that could be knocked over during initial excitement.
**Let your child set the pace.** Never force interaction. Short, supervised sessions that end on a positive note are more effective than prolonged exposure. If your child retreats, let them. The animal will still be there when they are ready.
## Challenges to Consider Honestly
Pets are not a treatment for autism or ADHD. They should not be acquired with the sole goal of addressing symptoms. That framing sets up both the child and the animal for failure.
Nearly 20 percent of families who owned dogs reported that their child experienced sensory hypersensitivity related to the animal. Loud barking, sudden movements, and strong smells can cause [sensory overload](/blog/sensory-processing-daily-routines). A large, energetic dog might overwhelm a child while a quiet cat or small guinea pig would thrive in the same household.
Some children develop intense attachment to their pet that manifests as separation anxiety or excessive worry about the animal's health. When a pet rejects affection or does not want to play, this can cause emotional distress that neurodivergent children may struggle to process.
Time and cost are real factors. Parents often absorb the majority of pet care regardless of the child's age. Be honest about your family's capacity before adding another living being to the household.
And consider the animal's welfare. Pets living with [children who have intense behavioral patterns](/blog/aggressive-behavior-autism-biting-hitting-strategies) need their own safe spaces, patience during adjustment, and an owner who will advocate for their needs alongside the child's.
## The Bottom Line
The research is clear that animals can provide measurable benefits for neurodivergent children across social skills, emotional regulation, sensory processing, and daily routine building. But the key word is "can." The right animal in the right environment with the right preparation creates something powerful. The wrong match creates stress for everyone, pet included.
Start with honest assessment. Consider your child's sensory profile, your family's daily capacity, and the level of preparation you can invest before the animal arrives. Use visual supports, social stories, and gradual exposure to set everyone up for success.
When it works, the bond between a neurodivergent child and their pet is one of the most genuine, uncomplicated relationships they will experience. No judgment. No social scripts. No expectation to perform. Just connection, on their terms.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual schedules](/blog/visual-schedules-for-autism) for pet care routines that teach responsibility and independence, create [social stories](/blog/social-stories-autism-guide) to prepare your child before a new pet arrives, track [emotional and behavioral patterns](/blog/tracking-emotions-activities-neurodivergent-children) to see how your child responds to animal interaction over time, and use [first-then boards](/blog/first-then-boards-guide) to build predictable sequences around daily pet care. Just $6.99/month after your trial, no credit card required upfront.
---
## Autism Funding and Programs: Where to Start When the Bills Stack Up
Published: 2026-03-19
URL: https://vizyplan.com/blog/autism-funding-programs-financial-support-families
Category: Strategies
Author: Justin Bowman
> A parent guide to funding autism therapy and services. Federal programs, grants, insurance mandates, tax benefits, and lesser-known resources that can save your family thousands.
You opened the explanation of benefits letter from your insurance company. The one that arrived three weeks after your child started speech therapy. You already knew the number would be bad. You did not know it would make your hands shake.
Forty-five minutes of speech therapy. Billed at one hundred and seventy-five dollars. Insurance covered eighteen. You owe one hundred and fifty-seven dollars. For one session. Your child needs two sessions a week. And that is just speech. The behavioral therapy your pediatrician recommended runs one hundred and fifty dollars an hour, and your child needs ten to twenty hours a week. You have not even looked into occupational therapy yet.
You sit at the kitchen table and do math you never wanted to do. The numbers do not work. They are not even close.
If this is where you are right now, you are not alone. According to the Drexel University National Autism Indicators Report, 66 percent of families raising a child with autism experience significant financial hardship. Research published in Pediatrics found that families of children with autism earn an average of $17,763 less per year than families of children with no health limitations, largely because mothers of autistic children earn 56 percent less than their peers. And a study in the National Institutes of Health database found that families with autistic adolescents are nearly twice as likely to declare bankruptcy compared to families without.
The financial weight is real. But here is what nobody told you at the diagnostic appointment: there is money out there. Federal programs, state services, nonprofit grants, tax strategies, and resources that most families never learn about because no one hands you a roadmap when your child is [diagnosed](/blog/child-autism-diagnosis-what-comes-next). This is that roadmap.
## The Program That Covers More Than You Think: Medicaid and EPSDT
Medicaid is the single largest funder of autism services in the United States, and most families do not realize their child may qualify even if they have private insurance or earn a moderate income.
**Start with EPSDT.** The Early and Periodic Screening, Diagnostic, and Treatment benefit is a federal requirement within Medicaid for children under twenty-one. Under EPSDT, states must cover all medically necessary services to diagnose and treat a child's condition, even if those services are not part of the state's standard Medicaid plan. This is a powerful and chronically underutilized protection. If your child's doctor says ABA therapy, speech therapy, or occupational therapy is medically necessary, Medicaid must cover it under EPSDT. Period.
**Eligibility is broader than you think.** Children can qualify for Medicaid through household income, through disability-based SSI eligibility, or through state Home and Community-Based Services waiver programs. In many states, a child who receives SSI is automatically eligible for Medicaid regardless of what the parents earn. Do not assume your family makes too much. The income limits vary by state, and many families are surprised to discover they qualify.
**The scale tells the story.** North Carolina's Medicaid autism services alone cost an estimated $639 million in fiscal year 2026, a 425 percent increase from 2022. That growth reflects both rising diagnoses and expanding coverage. The money is being spent because the services work. Your child deserves access to them.
## Supplemental Security Income: Monthly Cash for Your Child
SSI is a federal program that provides monthly cash payments to children with disabilities from families with limited income. For 2026, the maximum benefit is $994 per month.
**Eligibility requires three things.** Your child must be under eighteen, must have a medically determinable condition causing "marked and severe functional limitations" expected to last at least twelve months, and your household income must fall below the threshold. Parents' income is "deemed" to the child, which means higher-earning families may not qualify. But the threshold is more generous than many families expect, especially for larger households.
**The Medicaid connection is critical.** In most states, SSI approval automatically qualifies your child for Medicaid. This means one application can unlock two programs: monthly cash and comprehensive health coverage including therapy services under EPSDT. Apply at your local Social Security office, and bring your child's diagnostic paperwork, medical records, and your financial information.
## Your Child's Right to Free Services: IDEA and the School System
The Individuals with Disabilities Education Act guarantees your child access to a free appropriate public education, including specialized services, at no cost to your family.
### Part C: Early Intervention (Birth to Age 3)
If your child is under three, contact your state's Early Intervention program immediately. You can self-refer. No doctor's note is required. Services may include speech-language pathology, occupational therapy, physical therapy, behavioral supports, assistive technology, and family training. Part C received $540 million in federal funding for fiscal year 2025, and every state runs its own program. These services are provided in your home or community at no cost or minimal cost to the family.
### Part B: School-Based Services (Ages 3 to 21)
Once your child turns three, they may qualify for an Individualized Education Program through your local school district. Request a special education evaluation in writing. The school must evaluate your child at no cost and, if they qualify, develop an IEP that may include specialized instruction, speech therapy, occupational therapy, behavioral supports, and assistive technology. If assistive technology is written into your child's [IEP](/blog/504-plan-vs-iep-which-one-does-your-child-need), the school district must provide it free of charge. This includes communication devices, specialized software, and tools your child needs to access their education.
## Insurance Coverage: All 50 States Have Autism Mandates
This is a fact that shocks most parents. All fifty states and the District of Columbia have enacted autism insurance mandates requiring some level of coverage for autism therapies, including Applied Behavior Analysis. As recently as 2001, no state had such a mandate. The landscape has changed dramatically.
**But coverage varies wildly.** Some states have robust mandates with no age limits or dollar caps. Others impose significant restrictions. Florida, for example, caps ABA coverage at $36,000 per year with a $200,000 lifetime maximum. Your state's mandate may cover unlimited therapy through adulthood or may phase out when your child turns twelve. Look up your specific state at the National Conference of State Legislatures.
**Self-funded ERISA plans are the exception.** If your employer self-funds its health plan rather than purchasing insurance from a carrier, state mandates generally do not apply. However, the federal Mental Health Parity and Addiction Equity Act requires that mental health conditions including autism be treated comparably to physical health conditions in terms of coverage limits, visit caps, and copays. If your plan covers forty physical therapy visits per year, it cannot cap ABA at twenty.
**Questions to ask your insurance company today:**
- Does my plan cover ABA therapy, speech therapy, and occupational therapy for autism?
- Is there an age limit or annual dollar cap on coverage?
- Do I need a referral or prior authorization?
- Which providers in my area are in-network for autism services?
- Is my plan self-funded or fully insured, and what state or federal mandates apply?
## Grants You Can Apply for Right Now
Several nonprofit organizations offer direct financial assistance to families of children with autism. These are not loans. They are grants.
**ACT Today (Autism Care and Treatment Today)** provides grants of $100 to $5,000 for families earning under $100,000 per year. Funds cover ABA therapy, speech therapy, occupational therapy, medications, home safety devices, and sensory equipment. Their SOS fund specifically covers GPS trackers and fencing for children who [wander](/blog/elopement-wandering-autism-parent-safety-guide).
**Autism Speaks** offers two grant programs. The Autism Cares Grant provides up to $500 through their Autism Response Team. Their Community Grants provide up to $5,000 for therapy, camp, and equipment based on financial need. Call the Autism Response Team at 888-288-4762 to start the process.
**The National Autism Association Helping Hand Program** provides a one-time $1,000 grant to families in dire financial need with a net household income under $50,000 per year. Their Give a Voice program provides communication devices and software to nonverbal or minimally verbal children with autism.
**UnitedHealthcare Children's Foundation** offers grants for medical expenses not fully reimbursed by insurance. Applications are accepted year-round with no specific deadline. You do not need to be a UnitedHealthcare member to apply.
**The Special Angels Foundation** provides up to $2,500 for equipment and up to $1,500 for therapy services. **The Flutie Foundation** has granted over $900,000 since 2012 for assistive technology programs for individuals with autism.
These grants will not pay for everything. But a $5,000 grant covers more than a month of therapy that would otherwise come out of your pocket. Apply to multiple organizations simultaneously. There is no rule against receiving grants from more than one source.
## Tax Strategies Most Families Miss
The tax code contains several provisions that can significantly reduce the financial burden of raising a child with autism. Most families do not take full advantage of them because no one explains these at diagnosis either.
### Medical Expense Deductions
You can deduct unreimbursed medical expenses that exceed 7.5 percent of your Adjusted Gross Income on Schedule A. Eligible expenses include diagnostic evaluations, ABA therapy, speech therapy, occupational therapy, physical therapy, prescribed medications, specialized equipment, therapeutic diets if medically prescribed, and transportation to medical appointments at twenty-one cents per mile. If your family earns $80,000 and your unreimbursed therapy costs total $12,000, you can deduct $6,000 (the amount exceeding 7.5 percent of your income). Keep every receipt.
### ABLE Accounts: Tax-Free Savings That Do Not Kill Benefits
ABLE accounts are one of the best-kept secrets in disability planning. These tax-advantaged savings accounts allow families to save up to $20,000 per year (2026 limit) for disability-related expenses without affecting SSI or Medicaid eligibility. Up to $100,000 in ABLE savings is completely disregarded for SSI purposes.
**Money grows tax-free and withdrawals are tax-free** when used for qualified expenses including housing, education, healthcare, transportation, and assistive technology. A major 2026 change expanded eligibility from disability onset before age twenty-six to before age forty-six, opening the door to approximately six million more Americans.
If your child receives SSI or Medicaid, an ABLE account lets you save for their future without jeopardizing the benefits they depend on today. Open one through your state's ABLE program or any state that accepts out-of-state residents.
## Medicaid Waivers: The Waitlist You Need to Join Now
Home and Community-Based Services waivers are state-administered Medicaid programs that provide services beyond standard Medicaid, specifically designed to support individuals with disabilities in their homes rather than in institutions. Approximately 257 HCBS waiver programs are active across the country, and many states offer autism-specific waivers.
**Services can include respite care, behavioral supports, personal care, habilitation, and therapeutic services delivered in your home.** Research shows that these waivers significantly reduced the likelihood that a parent had to stop working to care for their child.
**The catch is the waitlist.** Many states have multi-year waiting lists for waiver services. Some families wait five to seven years. This means you need to apply as early as possible, even if your child does not need waiver services today. Getting on the list now protects your child's access to services years from now. Contact your state's Department of Developmental Disabilities to apply.
## Programs You Have Probably Never Heard Of
### Respite Care Funding
[Caregiver burnout](/blog/caregiver-burnout-neurodivergent-parent) is a clinical reality for families raising children with autism. The ARCH National Respite Network, funded by the federal Administration for Community Living, helps families find and fund local respite services. The Lifespan Respite Care Act provides federal funding to states for coordinated respite programs. Most Medicaid HCBS waivers include respite care as a covered service. You are allowed to take a break. And there may be money to help you do it.
### Assistive Technology Programs
Every state has a federally funded Assistive Technology program under the Assistive Technology Act of 2004. These programs provide device demonstrations, short-term device loans, and sometimes low-interest loans for purchasing assistive technology including iPads loaded with communication apps, specialized software, and adaptive equipment. If your child uses a device to communicate or manage their [daily routines](/blog/visual-schedules-for-autism), these programs can help fund it.
### Camp and Recreation Scholarships
The Autism Spectrum Disorder Foundation provides partial and full scholarships for social skills camps, equine therapy camps, and aquatic therapy camps. Autism Speaks Community Grants fund summer camp attendance up to $5,000. Ben's Fund provides up to $1,000 per year per child toward summer camp or enrichment classes. Your child deserves to play, explore, and connect with peers in environments designed for their needs.
## Where to Start: Your First Five Steps
If you are overwhelmed by all of this, here is where to begin. Take these five steps this week.
**Step one: Call your state's Early Intervention program or school district.** For children under three, contact Early Intervention. For children three and older, request a special education evaluation from your school district in writing. These services are free.
**Step two: Apply for Medicaid and SSI.** Visit your local Social Security office with your child's diagnostic paperwork. One application can unlock monthly cash and comprehensive therapy coverage.
**Step three: Review your health insurance.** Call the number on the back of your card and ask the five questions listed above. Know exactly what your plan covers before you start services.
**Step four: Apply for at least two grants.** ACT Today and Autism Speaks are good starting points. Applications take thirty minutes and could put thousands of dollars toward your child's therapy.
**Step five: Open an ABLE account.** Even if you can only contribute fifty dollars a month, start building a tax-free safety net for your child's future that will not threaten their benefits.
You do not have to do everything at once. You do not have to understand every program before you take the first step. The system is complicated and frustrating and sometimes feels designed to keep families out. But the money and the services exist. And your child has a right to access them.
## You Are Already Doing the Hard Part
The hardest part of navigating autism funding is not filling out the applications. It is sitting at that kitchen table, looking at the numbers, and deciding to keep going anyway. It is choosing to fight through bureaucratic phone trees and confusing eligibility rules and rejection letters because your child needs what is on the other side.
Sixty-six percent of families in your position are struggling financially. That means you are not failing. You are facing a system that was not built for you. But the programs exist, the grants are real, and the tax benefits add up. Every dollar you reclaim is a dollar that goes toward helping your child thrive.
You did not sign up for this part of the journey. But you are here, doing the research, reading the fine print, and showing up for your child in ways that no one will ever fully see. That matters more than any dollar amount.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual schedules](/blog/visual-schedules-for-autism) to organize your child's therapy appointments and daily routines, use [first-then boards](/blog/first-then-boards-guide) to prepare them for transitions between activities, track [emotional and behavioral patterns](/blog/tracking-emotions-activities-neurodivergent-children) to share with therapists and school teams, and collaborate with providers during [IEP meetings](/blog/collaborating-providers-iep-visual-tools) with tools that bridge home and school. Just $6.99/month after your trial, no credit card required upfront.
---
## Why Your Neurodivergent Child Melts Down When the Screen Turns Off
Published: 2026-03-18
URL: https://vizyplan.com/blog/screen-time-meltdowns-turning-off-devices-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> The neuroscience behind screen time meltdowns in neurodivergent children, and practical strategies to make turning off the tablet less explosive for everyone.
The timer goes off. You take a breath and say the words you have been dreading for the last ten minutes. "Okay, time to turn it off."
And then it happens. The screaming. The throwing. The full-body collapse onto the floor. Maybe they grab the tablet tighter and run. Maybe they go completely rigid and refuse to move. Maybe they say things that cut deep because they know exactly which words will make you hand the device back.
You have tried countdowns. You have tried warnings. You have tried being firm, being gentle, bribing, and ignoring. Nothing works consistently, and you are starting to wonder if something is genuinely wrong or if you have just created a monster with the iPad.
Here is what nobody tells you: your child is not choosing to melt down. Their brain is experiencing something close to a withdrawal response, and for neurodivergent children, the intensity of that response is amplified by the very wiring that makes them who they are.
## What Is Actually Happening in Your Child's Brain
Understanding the neuroscience does not make the meltdowns disappear, but it changes how you respond to them. And that changes everything.
**Screens deliver dopamine with ruthless efficiency.** Every swipe, every level completed, every new video that auto-plays delivers a small burst of dopamine, the brain's reward chemical. For children with ADHD, whose brains already have lower baseline dopamine levels, screens provide something their neurology is desperately seeking. Research from the Jacob's Ladder Group confirms that digital media creates a cycle of dopamine stimulation that the developing brain becomes dependent on for maintaining a sense of engagement and pleasure.
**The crash is neurochemical, not behavioral.** When the screen turns off, dopamine drops abruptly. For a neurotypical child, this is uncomfortable. For a neurodivergent child with an already-depleted dopamine system, it is a neurochemical crash. The irritability, aggression, and emotional explosion your child displays is not defiance. It is their nervous system responding to a sudden chemical shift it cannot regulate.
**The prefrontal cortex cannot do its job.** The prefrontal cortex handles impulition control, cognitive flexibility, and the ability to shift attention from one task to another. In children, this region is still developing. In neurodivergent children, it may be developing on a different timeline entirely. A 2023 study published in the journal NeuroImage found that daily screen use was associated with reduced functioning in the inhibitory control network in preadolescent children. The very brain region your child needs to stop using a screen is the region most compromised by screen use itself.
**The reward system overpowers the control system.** Neuroscience describes a "dual systems" model in developing brains: the reward and emotional system matures faster than the cognitive control system. Screens activate the reward system at full intensity. When you ask your child to stop, you are asking the weaker system to override the stronger one. For many neurodivergent children, this is not a matter of willpower. It is a matter of brain architecture.
**The transition itself is the hardest part.** Children who struggle with [transitions in general](/blog/staying-regulated-during-transitions) will struggle hardest with this one because they are transitioning away from the most neurologically rewarding activity in their environment. Research on visual activity schedules published in PMC found that structured transition supports significantly reduced problem behaviors and latency to initiate new activities in children with ADHD. The transition, not the screen time itself, is where the intervention needs to happen.
## Why "Just Take It Away" Makes Everything Worse
If you have ever grabbed the tablet out of your child's hands in frustration, you already know how this goes. The meltdown escalates to a level that makes you regret everything. There is a reason this approach backfires every time.
**Abrupt removal triggers a threat response.** Your child's nervous system is in a state of high engagement. Suddenly removing the source of that engagement activates the fight-or-flight system. You are not just taking a device. You are, from your child's neurological perspective, creating a threat. The screaming, hitting, or running that follows is not calculated. It is a survival response.
**It damages trust for future transitions.** When devices are removed without warning, children learn that screen time can end unpredictably at any moment. This creates anticipatory anxiety during screen time, which paradoxically makes them cling harder to devices and fight more aggressively to keep them. You wanted to solve the problem. You just made it worse for next time.
**It confirms that screens are the only good thing.** When the moment of device removal becomes the most intense, negative interaction of the day, it reinforces the idea that everything good lives inside the screen and everything outside the screen involves conflict. The contrast deepens the dependency.
## The Screen-to-Calm Cycle That Traps Families
A study published in JAMA Pediatrics found that children aged two to five who were regularly given devices to manage their meltdowns became significantly less capable of [regulating their emotions](/blog/emotional-regulation-visual-supports) independently than children who were not offered screens to calm down.
This creates a devastating cycle. Your child melts down. You hand them the tablet because nothing else works. The tablet calms them because it floods their system with dopamine. Twenty minutes later, you need to take it back. The meltdown returns, now worse because their system was just artificially regulated and crashed again. So you hand it back. And the cycle tightens.
Breaking this cycle does not mean eliminating screens. It means changing the architecture around how screen time starts, progresses, and ends.
## Strategies That Actually Work
### Before Screen Time Begins
**Define the ending before the beginning.** Before your child touches the device, the end point should be established, visible, and agreed upon. "You have until this timer finishes" or "You can watch two episodes" sets the boundary when [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) is low and cooperation is high. Use a [visual schedule](/blog/visual-schedules-for-autism) that shows screen time as one block in a sequence of activities, not an open-ended event.
**Make the next activity visible and appealing.** One of the most effective strategies from occupational therapy research is having the post-screen activity ready and enticing before screen time begins. A [first-then board](/blog/first-then-boards-guide) that shows "First tablet, then trampoline" or "First show, then snack" gives your child something to transition toward, not just something to transition away from.
**Choose content with natural stopping points.** A show with clear episodes is easier to end than an endless scrolling app. A game with levels has built-in pauses. An open-ended sandbox game like Minecraft has no natural ending, which makes it one of the hardest to transition away from. Match the content to your child's transition ability.
**Front-load regulation.** If your child arrives at screen time already dysregulated, the crash when it ends will be worse. Heavy work, movement, or [sensory input](/blog/sensory-processing-daily-routines) before screen time builds a regulatory foundation that makes the transition less explosive. Ten minutes of jumping on a trampoline before twenty minutes of tablet creates a completely different neurological starting point than going straight from one screen session to the next.
### During Screen Time
**Use graduated warnings that are visible, not just verbal.** The Child Mind Institute recommends multiple warnings at ten minutes, five minutes, two minutes, and one minute. But for neurodivergent children, verbal warnings often do not register because their attention is fully absorbed. Use a visual timer they can see, a physical timer placed next to the device, or a timer app that runs on the screen itself. Making the countdown visible leverages their visual processing strengths instead of relying on auditory processing during a moment of hyperfocus.
**Get connection before giving direction.** For children with ADHD especially, ensure you have their attention before delivering the transition warning. Sit next to them. Make eye contact if they are comfortable with that. Put a gentle hand on their shoulder. Say their name and wait for acknowledgment before saying "five more minutes." A direction delivered to a hyperfocused brain that has not shifted attention is a direction that was never received.
**Acknowledge what they are doing.** "That level looks really cool" or "I can see you are right in the middle of something important" validates their experience before introducing the unwelcome news that it is ending. Children who feel understood resist less than children who feel dismissed.
### The Transition Moment
**Use a sensory bridge.** The moment the screen turns off, your child's sensory system loses its primary input. Having a replacement ready prevents the void that triggers the crash. For some children, this is a crunchy snack. For others, it is a fidget toy, a weighted blanket, or a specific song that signals transition. Occupational therapists call this a "sensory bridge" because it carries regulation across the gap between activities.
**Offer a specific choice, not an open question.** "Do you want to play outside or build with LEGOs?" is infinitely more effective than "What do you want to do now?" Open-ended questions require executive function your child does not have in this moment. Two concrete [choices](/blog/choice-boards-empowering-decisions) reduce cognitive demand while preserving autonomy.
**Allow a transition buffer.** Not every child can go from screen to next activity immediately. Some need two to three minutes of doing nothing, lying on the couch, staring at the ceiling, decompressing. This is not laziness. It is their nervous system recalibrating. If your child needs a few minutes of blank space after screens, build it into the schedule instead of fighting it.
**Name what is happening without judgment.** "Your brain is adjusting. Screens give your brain a lot of energy, and when they stop, your brain needs a minute to reset. That is normal." This kind of narration, delivered calmly and factually, teaches [self-awareness](/blog/tracking-emotions-activities-neurodivergent-children) over time. Children who understand what is happening in their bodies manage it better than children who experience the same sensations without context.
### After the Meltdown (Because It Will Still Happen)
**Do not punish the meltdown.** Your child did not choose to lose control. Punishing a neurological response teaches them that their brain's wiring is wrong, not that a skill needs building. Stay calm, keep them safe, and wait for the storm to pass.
**Do not give the device back.** This is where the cycle breaks or reinforces. If the meltdown results in getting the screen back, you have taught your child's brain that meltdowns are effective. Hold the boundary kindly. "I know this is hard. Screen time is done for now. I am here when you are ready."
**Debrief when calm.** Later, not during the meltdown, talk about what happened. "Your brain had a hard time when the tablet turned off. That happens sometimes. Next time, what might help?" This collaborative approach builds problem-solving skills and gives your child agency in creating their own [regulation strategies](/blog/emotional-regulation-visual-supports).
**Track patterns.** Which apps trigger the worst meltdowns? What time of day is hardest? How long can your child use a screen before the transition becomes unmanageable? [Tracking these patterns](/blog/tracking-emotions-activities-neurodivergent-children) turns a recurring crisis into data you can use to prevent the next one.
## When Screen Time Meltdowns Signal Something Bigger
Some level of protest when screens end is developmentally normal for all children. But certain patterns warrant professional support.
**The meltdowns are getting more intense over time, not less.** If your strategies are consistent and the explosions are still escalating, something else may be driving the behavior. An occupational therapist or behavioral specialist can assess whether [sensory needs](/blog/sensory-processing-daily-routines), anxiety, or demand avoidance is amplifying the screen dependency.
**Your child cannot engage in any non-screen activity.** If every offline option is met with refusal, distress, or complete disinterest, the screen may be masking unmet needs rather than just providing entertainment. Professional support can help identify what those needs are and how to meet them without total dependence on devices.
**Screen time is the only tool that prevents meltdowns.** If you have reached a point where handing over the device is the only way to prevent or stop a meltdown throughout the day, you are in a cycle that is difficult to break without outside help. This is not a parenting failure. It is a sign that your child's regulatory system needs more support than one strategy can provide.
**Aggression during device removal is escalating.** Throwing things, hitting, self-harm, or property destruction during screen transitions is your child's nervous system in crisis. A professional who understands both neurodevelopment and [behavioral strategies](/blog/recognizing-triggers-meltdowns-neurodivergent-children) can create a specific plan for your child.
## You Are Not a Bad Parent for Using Screens
Before we go any further, let us be clear about something. You are not a bad parent for letting your child use screens. You are not a bad parent for using the iPad as a babysitter during dinner prep. You are not a bad parent for handing over the tablet on a hard day because you needed fifteen minutes to breathe.
Screens are a tool. Like any tool, they can be used intentionally or reactively. The fact that you are reading this article means you are trying to move from reactive to intentional, and that is the entire goal.
Research published in JAMA Pediatrics found that toddlers who spent 75 or more minutes daily on tablets were significantly more likely to have angry outbursts a year later. But the researchers were careful to note that the issue is not screens existing in a child's life. It is screens being used as the primary regulation strategy without other tools alongside them.
Your child's relationship with screens can improve. The meltdowns can become less frequent and less intense. But it starts with understanding that the explosion when the screen turns off is not about the screen. It is about a brain that needs help building the skills to handle the transition. And building those skills is something you and your child can do together, one transition at a time.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual schedules](/blog/visual-schedules-for-autism) that show your child exactly when screen time starts and ends, create [first-then boards](/blog/first-then-boards-guide) that make the next activity visible and motivating, track [behavioral patterns](/blog/tracking-emotions-activities-neurodivergent-children) to identify which screen situations trigger the worst meltdowns, and use [transition supports](/blog/staying-regulated-during-transitions) that help your child's brain bridge the gap between screens and real life. Just $6.99/month after your trial, no credit card required upfront.
---
## Birthday Parties and Your Neurodivergent Child: Attending, Hosting, and Surviving It All
Published: 2026-03-17 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/birthday-parties-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Evidence-based strategies for helping neurodivergent children navigate birthday parties, whether you are attending someone else's celebration or hosting your own sensory-friendly event.
There is a specific kind of dread that settles in when a birthday party invitation arrives. Not for you. For your child. The one who took forty-five minutes to recover from the last party. The one who stood by the wall while everyone else played musical chairs. The one who melted down in the car before you even got inside.
Birthday parties are supposed to be fun. For neurodivergent children, they are often a collision of every challenge rolled into one event: unpredictable environments, sensory overload, social expectations, schedule disruptions, unfamiliar food, and the pressure to perform happiness on command. Research from the Interactive Autism Network found that more than 65 percent of autistic children are sometimes or often excluded from social activities by peers, and 34 percent have no friends outside their own family. Birthday parties sit at the intersection of all of this.
But your child deserves to celebrate and be celebrated. Whether you are attending someone else's party or hosting your own, the right preparation can transform these events from something you survive into something your child actually enjoys.
## Why Birthday Parties Are So Hard
Before diving into strategies, it helps to understand what makes birthday parties uniquely challenging for neurodivergent children.
**The sensory environment is extreme.** Balloons popping, children screaming, music blasting, fluorescent lights in a bounce house facility, the smell of pizza mixed with frosting, glitter and confetti everywhere. Birthday parties assault every sensory channel simultaneously. For a child with [sensory processing differences](/blog/sensory-processing-daily-routines), this is not just uncomfortable. It is physically painful.
**The schedule is unpredictable.** Even when there is a plan, birthday parties rarely follow it. Games run long. Cake comes early. Someone has an accident and everything stops. Children who rely on [predictable routines](/blog/visual-schedules-for-autism) to feel safe are suddenly untethered in an environment where anything can happen at any time.
**Social demands are high and unstructured.** Unlike school, where social expectations are somewhat predictable, birthday parties require constant social navigation with minimal structure. When do I give the gift? Do I have to play the game? What if I do not know anyone? What if someone talks to me and I do not know what to say? For children who struggle with [social situations](/blog/navigating-playdates-social-gatherings-neurodivergent-child), this is exhausting.
**Food is often a problem.** Party food rarely accommodates [picky eaters](/blog/mealtime-strategies-picky-eating-autism-adhd). The cake might have a texture your child cannot tolerate. The pizza might be from an unfamiliar restaurant. And the pressure to eat what everyone else is eating adds another layer of social stress.
**Emotional regulation is tested constantly.** Not winning a game. Waiting for a turn. The birthday child opening gifts that your child wants. Singing a song your child finds overwhelming. Every few minutes, something happens that requires [emotional regulation](/blog/emotional-regulation-visual-supports) your child may not have the bandwidth for after the sensory onslaught.
## Part One: Attending Someone Else's Birthday Party
### Before the Party
**Create a social story specific to this party.** Generic party social stories help, but personalized ones work better. Include the name of the birthday child, what the venue looks like (search online for photos), what activities are planned (ask the host), and what your child can do if they feel overwhelmed. [Social stories](/blog/social-stories-autism-guide) reduce anxiety by replacing the unknown with the known.
**Do a drive-by or virtual visit of the venue.** If the party is at a venue your child has never been to, drive past it a few days before. If it is a business, look up photos online together. Knowing what the building looks like from the outside and inside removes one more unknown variable.
**Build a visual schedule of the party.** Map out the expected sequence: arrive, say happy birthday, play games, eat food, watch presents being opened, say goodbye, go home. Even if the real schedule shifts, having a mental framework gives your child something to hold onto. Use [visual supports](/blog/visual-schedules-for-autism) your child already trusts from their daily routine.
**Pack a sensory survival kit.** Noise-canceling headphones or earplugs. A favorite fidget toy. A chewy necklace if your child uses oral sensory input to regulate. Sunglasses for bright venues. A familiar snack in case the party food does not work. A small comfort item. This kit is not a luxury. It is equipment.
**Talk to the host ahead of time.** This can feel vulnerable, but it makes a significant difference. Ask if there is a quiet room or space available if your child needs a break. Ask about the activities planned so you can prepare your child. Let them know about any food needs. Most parents are happy to accommodate when they know what helps.
**Practice the hard parts.** If your child struggles with "Happy Birthday" being sung (many sensory-sensitive children find group singing overwhelming), practice at home with decreasing volume. If gift-giving is confusing, practice handing a gift to a stuffed animal and saying "Happy Birthday." Rehearsal reduces the cognitive load during the actual event.
**Set an exit time before you go.** Decide with your child how long you will stay. Having a defined end point reduces [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) because your child knows this is not an open-ended commitment. "We will stay for one hour. After cake, we will go home." Put it in the visual schedule.
### During the Party
**Arrive a few minutes early.** Getting there before the crowd allows your child to acclimate to the environment without the added stimulus of twenty children arriving at once. They can explore the space, find the bathroom, identify a quiet corner, and adjust while things are still calm.
**Stay close but do not hover.** Your child needs to know you are available without feeling watched. Position yourself where they can make eye contact with you from across the room. Establish a signal, a hand gesture or a specific word, that means "I need a break" so they can communicate their needs without drawing attention.
**Give permission to opt out of activities.** Your child does not have to play every game, eat every food, or participate in every moment. Watching from the side is legitimate participation. Sitting at the table while others play is fine. The goal is positive exposure, not forced performance.
**Watch for early warning signs.** You know your child's [escalation patterns](/blog/recognizing-triggers-meltdowns-neurodivergent-children). Increased stimming, covering ears, becoming very still, withdrawing to a corner, becoming unusually loud or physical. When you see these signs, intervene early. A five-minute break in the hallway can prevent a full meltdown.
**Use breaks strategically.** Before your child hits their limit, suggest a break. "Let's go get some water" or "Want to check on the car with me?" Frame breaks as normal, not as a consequence of struggling. Some children do better with scheduled breaks: attend for twenty minutes, take a five-minute break, return for twenty more.
**Leave while things are still good.** This is the hardest advice to follow because it feels counterintuitive. But leaving after a successful forty-five minutes is far better than staying until a meltdown forces a tearful exit. End on a high note. Your child will remember the party as a positive experience, and that positive memory makes the next party less frightening.
### After the Party
**Decompress intentionally.** Your child's nervous system has been running in overdrive. After the party, provide whatever sensory input helps them [regulate](/blog/staying-regulated-during-transitions). For some children that is deep pressure (a weighted blanket, tight hugs). For others it is quiet time alone. For others it is movement (jumping, swinging). Do not rush to the next activity. Let recovery happen.
**Celebrate what went well.** "You said happy birthday to Marcus. You tried the pizza even though it was new. You told me when you needed a break." Specific praise reinforces the skills your child used, even if the party was not perfect. Especially if the party was not perfect.
**Write it down for next time.** What worked? What did you wish you had done differently? How long did your child last before signs of stress appeared? What sensory input helped during recovery? This data is invaluable for [tracking patterns](/blog/tracking-emotions-activities-neurodivergent-children) and preparing for the next event.
## Part Two: Hosting a Birthday Party for Your Neurodivergent Child
Hosting gives you something attending does not: control. You choose the venue, the guest list, the activities, the food, the schedule, and the sensory environment. Use that control strategically.
### Planning the Guest List
**Smaller is almost always better.** Three or four close friends create a manageable social environment. Fifteen classmates create chaos. Ask your child who they actually want there, not who they think they should invite. If the answer is two people, honor that. A party of three can be the best party your child has ever had.
**Consider the mix of guests.** If your child has neurodivergent friends who share similar needs, invite them. If your child has neurotypical friends who are patient and kind, invite them too. Avoid inviting children who are likely to be overstimulating or unkind, regardless of social obligation.
**Communicate with parents of guests.** Let other parents know the party will be sensory-friendly. Describe the environment, activities, and food options. If other neurodivergent children are attending, their parents will appreciate knowing accommodations are built in. This also sets expectations so no one is surprised by a quieter, calmer celebration.
### Choosing the Right Environment
**Home is often the best venue.** Your child already feels safe there. The sensory environment is familiar. There is a bedroom to retreat to if needed. You control the lighting, the noise level, and the layout. If your home feels too small, a backyard or a familiar park works well too.
**If you choose an outside venue, visit first.** Go at the same time of day the party will happen. How loud is it? How bright? Where are the bathrooms? Is there a quieter area? What does it smell like? These details matter.
**Create zones within the party space.** A main activity zone. A quieter zone with coloring books, puzzles, or sensory toys for children who need a break. A food zone separate from the loud activities. Giving children options about where to be reduces pressure and prevents overstimulation.
### Designing Sensory-Friendly Activities
**Structure activities but allow opt-outs.** Unstructured free play is actually harder for many neurodivergent children than organized activities. Plan a loose schedule of activities, but make participation voluntary. Post a [visual schedule](/blog/visual-schedules-for-autism) of the party events where all children can see it.
**Choose activities with built-in regulation.** Arts and crafts provide calming focus. Sensory bins with kinetic sand, water beads, or playdough engage tactile seekers. A bubble station works for almost every child. [Nature-based activities](/blog/nature-play-outdoor-activities-neurodivergent-children) like a scavenger hunt in the backyard provide movement and space.
**Avoid elimination games.** Musical chairs, hot potato, and similar games where children are "out" create social stress and highlight failure publicly. Instead, choose cooperative games where everyone participates throughout. A group art project, a treasure hunt with clues, or building something together keeps everyone included.
**Plan for the birthday song.** This moment causes more meltdowns than almost any other party element. The sudden group singing, the focused attention, the expectation of a specific response. Prepare your child for when it will happen. Consider alternatives: singing softly, letting your child wear headphones during the song, or replacing the song with a fun countdown to blowing out candles.
**Think carefully about balloons.** Many neurodivergent children are terrified of balloons popping. If your child loves balloons, use them. If not, skip them entirely or use bubble decorations instead. If guests bring balloon bouquets, have a plan for keeping them secured and away from areas where they might pop unexpectedly.
### Managing Food
**Serve familiar foods alongside party foods.** Your child's safe foods should be on the table alongside the pizza and cake. If chicken nuggets from a specific brand are what your child eats, serve them without apology. Other children will eat them too.
**Accommodate dietary needs broadly.** Many neurodivergent children have food sensitivities or restrictions. Having gluten-free, dairy-free, or dye-free options available is thoughtful and increasingly common. Label foods clearly so parents of guests with allergies can make informed choices.
**Do not force cake participation.** If your child does not want to eat cake, that is fine. If they want to eat only cake, that is also fine. A birthday party is not the day to enforce [mealtime expectations](/blog/mealtime-strategies-picky-eating-autism-adhd). Reduce the food pressure to zero.
**Serve food at a predictable time.** Put "snack time" or "pizza time" on the visual schedule. Children who struggle with [transitions](/blog/staying-regulated-during-transitions) do better when they know food is coming and when it will happen.
### The Gift Opening Question
This is where opinions diverge sharply, and both approaches are valid.
**Option A: Open gifts at the party.** If your child enjoys opening gifts and can handle the social attention, go for it. Prepare them for the possibility that they might receive duplicates or things they already have. Practice saying "thank you" regardless of the gift. Use a [social story](/blog/social-stories-autism-guide) to map out the sequence: someone hands you a gift, you open it, you say thank you, you move to the next one.
**Option B: Open gifts after guests leave.** This removes the social performance pressure entirely. Your child can react authentically to each gift without an audience. It also eliminates the challenge of other children becoming upset about gifts they want. You can simply say "we open gifts as a family after the party" and no one will question it.
### Building in Regulation Breaks
**Schedule breaks into the party timeline.** After every twenty to thirty minutes of group activity, build in five to ten minutes of free choice time where children can move between zones, get a snack, or decompress. This benefits every child, not just neurodivergent ones.
**Have your child's regulation tools accessible.** Weighted lap pad, noise-canceling headphones, a swing if you have one, a [calm-down space](/blog/happy-place-mindfulness-neurodivergent-children) they can access independently. Do not wait for your child to ask. Offer proactively: "Want to take a break in your room for a few minutes?"
**Assign a trusted adult to your child.** If you are managing the party, you cannot simultaneously monitor your child's regulation. Have a co-parent, grandparent, or trusted friend whose sole job is watching for your child's cues and facilitating breaks when needed.
## When the Invitation Does Not Come
Sometimes the hardest part of birthday parties is not attending them. It is not being invited.
Research from Kennedy Krieger Institute found that 32 percent of parents of autistic children reported being excluded from social events themselves. The exclusion often starts with their child: when invitations stop coming, so does the family's connection to the broader community. This kind of [social isolation](/blog/losing-friends-raising-autistic-child) compounds over time.
If your child notices they were not invited, be honest in an age-appropriate way. "Not everyone's parties are the right fit for everyone" is truthful without being hurtful. Then redirect: "What kind of celebration would you enjoy?" Host a small gathering on your terms. A movie night with one friend. A trip to a favorite place. Celebrating does not require a traditional party.
If the exclusion is persistent and your child is aware of it, this becomes an opportunity to practice [self-advocacy](/blog/teaching-self-advocacy-skills-neurodivergent-child). Help your child understand that their worth is not measured by party invitations. Connect them with communities where they are welcomed and valued. Focus on [their strengths](/blog/celebrating-neurodivergent-strengths-children) and the friendships that do exist, even if they look different from what other families have.
## A Note for the Host Parents of Neurotypical Children
If you are reading this because a neurodivergent child is attending your child's party, thank you. Here is what helps:
- Ask the parent what their child needs. They will tell you.
- Have a quiet space available for breaks.
- Do not insist every child participate in every activity.
- Keep the music at a reasonable volume.
- Let the parent stay if they want to. Do not assume they are helicoptering. They are providing necessary support.
- If a child has a meltdown, do not stare. Do not offer advice. Just give the parent space to help their child, and carry on with the party.
Your willingness to include a neurodivergent child teaches your own child something no classroom lesson can: that kindness means making room for people who experience the world differently.
## It Gets Easier
The first birthday party is often the worst. Every party after that benefits from what you learned at the one before. Your sensory kit gets more refined. Your social stories get more specific. Your exit strategy gets smoother. Your child develops coping skills they did not have last year. And slowly, birthday parties shift from something you dread to something you prepare for and sometimes, on the best days, enjoy.
Your child may never be the kid running through the bounce house with reckless joy. But they might be the child who sits at the craft table, deeply focused, making something beautiful. They might be the one who connects with one quiet friend in the corner while everyone else runs past. They might be the birthday kid who blows out candles with headphones on and a grin on their face. That counts. All of it counts.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [social stories](/blog/social-stories-autism-guide) to prepare your child for upcoming parties, create [visual schedules](/blog/visual-schedules-for-autism) for hosting your own celebration, track [sensory patterns](/blog/tracking-emotions-activities-neurodivergent-children) so you know what your child needs before and after events, and use [emotional regulation tools](/blog/emotional-regulation-visual-supports) to help them stay regulated through it all. Just $6.99/month after your trial, no credit card required upfront.
---
## Dating as a Single Mom of an Autistic Child: What No One Talks About
Published: 2026-03-16
URL: https://vizyplan.com/blog/single-mom-dating-autistic-child
Category: Strategies
Author: Justin Bowman
> The real reasons dating feels impossible when you are raising an autistic child alone, and the research-backed strategies that help you find connection without guilt.
You finally have a night to yourself. The sitter is booked. You put on something that is not covered in sensory-safe laundry detergent residue. You check your phone, and there is a message from someone who seems genuinely interesting.
And then the guilt hits like a wave.
Should you be doing this? Is it fair to your child? What happens when you have to explain the meltdowns, the rigid routines, the therapy schedule that runs your entire week? What if this person cannot handle it? What if they can, and then your child falls apart because someone new is in their world?
If this sounds familiar, you are not alone. And you are not selfish for wanting connection. You are human.
## Why Dating Feels Different When You Are Raising an Autistic Child
Every single parent faces hurdles when it comes to dating. But parenting an autistic child adds layers that most people never consider.
**The logistics are overwhelming.** Finding a sitter is not just about availability. It is about finding someone who understands your child's communication style, sensory needs, and behavioral patterns. A 2010 study in the Journal of Autism and Developmental Disorders found that mothers of children with autism spend at least two additional hours per day on caregiving compared to other mothers, and they are twice as likely to report chronic fatigue. That does not leave a lot of energy for romance.
**The guilt is constant.** Research published in Current Psychology found that guilt and shame together explain 23% of the variance in parental stress among parents of autistic children. For single moms, this guilt compounds: you are already doing everything alone, and taking time for yourself can feel like you are taking something away from your child. The same study found that self-forgiveness was the single strongest predictor of lower stress, but forgiving yourself is hard when the world tells you that good mothers sacrifice everything.
**The social isolation runs deep.** According to research from Kennedy Krieger Institute, 40% of parents of autistic children isolate themselves from friends and family because of their child's behaviors, and an additional 32% report being actively excluded by others. If you are already struggling to maintain basic friendships, the idea of putting yourself out there romantically can feel impossible.
**The stigma is real.** Studies on courtesy stigma, the social penalty people face for being associated with a stigmatized condition, show that many parents of autistic children internalize negative attitudes about their child's diagnosis. Some parents have reported explicitly that they avoid dating because they do not want to disclose that they have a child with autism. That kind of internalized shame is not a personal failing. It is a predictable response to a culture that still misunderstands neurodivergence.
## The Disclosure Question: When Do You Tell Them?
This is the question that keeps single moms of autistic children up at night. And research confirms it is not straightforward.
A 2025 study published in PMC examining disclosure patterns in dating found that a majority of individuals intentionally withheld information about disability or mental health conditions from dating profiles. Participants used a range of strategies: some disclosed spontaneously, some waited for the right moment, some let circumstances reveal the information naturally, and some avoided disclosure entirely.
Here is the thing: there is no perfect timing. But there are approaches that tend to work better than others.
**Lead with your child, not the diagnosis.** You do not owe anyone a medical history on a first date. Mention that you have a child. Share what makes them amazing. The diagnosis can come when trust has been established and you feel safe, not because you owe an explanation but because you are inviting someone into your real life.
**Pay attention to how they respond to the basics.** Before you ever mention autism, watch how your date responds to the fact that you have a child at all. Do they ask questions? Do they respect your schedule? Do they understand when you need to cut a night short? How someone handles the simple reality of dating a parent tells you a lot about how they will handle the complex parts.
**Normalize it.** When the time feels right, share your child's diagnosis the way you would share any other important fact about your family. Not as a warning, not as an apology, not as a test. Just as information. The right person will ask questions because they are curious, not because they are calculating an exit strategy.
**Know your dealbreakers.** If someone reacts to your child's diagnosis with discomfort, dismissal, or unsolicited advice about how to "fix" your child, that is information. It is painful, but it is valuable. You are not screening for perfection. You are screening for the ability to show up for your actual life.
## How Dating Affects Your Autistic Child
One of the biggest fears single moms carry is that dating will destabilize their child. And the research says this fear is not unfounded, but it is manageable.
**Transitions are genuinely harder for autistic children.** Research from Indiana University's Resource Center for Autism confirms that the autistic brain processes uncertainty and prediction differently than the neurotypical brain. Routine disruptions can trigger verbal outbursts, aggression, self-injury, or complete shutdown. A new person in the household, even occasionally, represents a significant transition.
**But transitions can be prepared for.** The same research emphasizes that visual supports and advance notice significantly reduce transition-related distress. This is not about keeping your child in a bubble. It is about giving them the tools to handle change at their own pace.
If you have been through a divorce or separation, you may already be navigating [two-household routines](/blog/divorce-two-household-routines-neurodivergent-children). The skills you have built there, creating visual schedules, using social stories, preparing your child for changes in advance, apply directly to introducing a new person into your life.
**Practical strategies for protecting your child's stability:**
- Do not introduce a new partner until the relationship is serious and stable. Your child does not need to bond with someone who may leave.
- Use [social stories](/blog/social-stories-autism-guide) to prepare your child for meeting a new person. Walk through what will happen, where, and for how long.
- Keep routines intact. Date nights should not disrupt bedtime, meal schedules, or [morning routines](/blog/morning-routine-tips-adhd) your child depends on.
- Let your child set the pace for interaction. Do not force connection. Some autistic children warm up quickly. Others need weeks or months. Both are okay.
- Build [visual schedules](/blog/visual-schedules-for-autism) that include any changes to the usual routine so your child can see what is coming and feel prepared rather than blindsided.
## The Burnout Factor: You Cannot Pour From an Empty Cup
Let us talk about why dating is not just a "nice to have" for single moms of autistic children. It is genuinely important for your wellbeing.
A 2024 meta-analysis found a 45% global prevalence of depression among caregivers of autistic children. A separate study in The Lancet's eClinicalMedicine found that anxiety rates in autism caregivers are nearly double that of the general population, at 12.2% compared to 6.9%. And research from the University of Wisconsin-Madison found that mothers of autistic children show cortisol patterns similar to combat soldiers, reflecting years of chronic, unrelenting stress.
You are running on fumes. And [caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children) does not just affect you. It affects your child, your patience, your ability to show up the way you want to every day.
Human connection, romantic or otherwise, is protective. Research consistently shows that social support buffers against the mental health impacts of caregiving stress. Dating is not a luxury. It is a form of self-care that makes you a better parent, not a worse one.
## What to Look for in a Partner
Not everyone is equipped to step into the life of a family navigating autism. That is not a judgment. It is a fact. Here is what matters most.
**Flexibility over perfection.** Your life does not follow a predictable script. Dates will be cancelled. Plans will change. You need someone who can adapt without resentment.
**Curiosity over pity.** The right partner will want to learn about your child's world, not out of obligation, but because they are genuinely interested. They will ask what sensory-friendly means. They will want to know your child's favorite things. They will learn the difference between a meltdown and a tantrum without being told twice.
**Patience that goes beyond words.** It is easy to say "I understand" on a second date. It is harder to mean it six months later when your child is having a rough week and you have cancelled three plans in a row. Look for consistency, not grand gestures.
**Respect for your child's needs over convenience.** A partner who suggests skipping your child's [bedtime routine](/blog/bedtime-routine-autism-adhd) so you can stay out later is telling you something important. A partner who says "go handle bedtime, I will be here when you are done" is telling you something important too.
**Willingness to learn.** Your partner does not need to be an autism expert. But they need to be willing to read the articles you send, ask questions when they do not understand, and accept that some things about your family will never look like what they expected.
## Letting Go of the Guilt
This is the hardest part. And it is worth saying directly.
You are allowed to want love. You are allowed to want someone who sees you as more than a caregiver, more than a therapist, more than a schedule manager. You are allowed to want to be held, to laugh at something that has nothing to do with IEP meetings, to feel like a person and not just a parent.
Your child needs a mother who is whole. Not perfect, not selfless to the point of emptiness, but whole. Research on self-forgiveness in autism parenting found that the parents who could extend grace to themselves had significantly lower stress levels than those who carried the weight of guilt for every moment they spent on their own needs.
You are modeling something powerful for your child. You are showing them that people who love them also deserve to be loved. That taking care of yourself is not the same as abandoning them. That the world is big enough for both of your needs.
## Building a Life That Includes You
If you are a single mom of an autistic child who has been thinking about dating but feels paralyzed by logistics, guilt, or fear, here is where to start.
**Get your support system in place first.** Before you start dating, make sure your child's routine is solid and your support network, even a small one, is reliable. If you are working through [losing friendships](/blog/losing-friends-raising-autistic-child) or [managing everything alone](/blog/stay-at-home-mom-autistic-child), shore up those foundations first.
**Invest in respite care.** Research from JADD found that just one additional hour of weekly respite care was associated with a significant increase in relationship quality, mediated through reduced daily stress. Even a few hours of reliable help per week can create the space you need to have a life outside of caregiving.
**Use technology to hold the routine.** Tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) let you build [visual routines](/blog/visual-schedules-for-autism) your child can follow even when you are not physically present. A sitter, a grandparent, or a new partner can follow the same visual schedule your child already knows and trusts. That consistency reduces anxiety for your child and guilt for you.
**Date at your own pace.** There is no timeline for when you should be "ready." If you want to start with casual coffee dates during school hours, that counts. If you want to try a dating app after bedtime, that counts too. Your path does not have to look like anyone else's.
**Stop waiting for permission.** No one is going to tell you it is okay. Not the internet, not your mother-in-law, not the other moms at therapy drop-off. You have to give yourself permission. And you deserve it.
## You Deserve More Than Survival Mode
Being a single mom of an autistic child is one of the hardest things a person can do. The research backs it up: the stress, the isolation, the burnout, the guilt. It is relentless.
But you are more than a caregiver. You are a person who deserves connection, partnership, and joy. Not someday when things calm down, because if you are [parenting a neurodivergent child](/blog/working-parent-neurodivergent-child), things may never look calm in the way other people define it. Right now. In the middle of the beautiful, chaotic, exhausting life you are already living.
The right person will not ask you to choose between them and your child. They will pull up a chair and help you build the life you both deserve.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) your child can follow with any caregiver, create [social stories](/blog/social-stories-autism-guide) that prepare them for meeting new people, track [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) so you know what your child needs before a transition, and share schedules across households and caregivers from one place. Just $6.99/month after your trial, no credit card required upfront.
---
## Losing Friends While Raising an Autistic Child: Why It Happens and What Helps
Published: 2026-03-15
URL: https://vizyplan.com/blog/losing-friends-raising-autistic-child
Category: Strategies
Author: Justin Bowman
> 40% of autism parents pull away from friends after diagnosis. Why friendships fade, what research says about the toll of isolation, and practical ways to rebuild your circle.
You used to have a group text that never stopped buzzing. Friday night dinners. Weekend playdates. A friend you could call when the whole day fell apart. Then your child was diagnosed, and slowly, quietly, the invitations stopped coming. The calls got shorter. The group chat went silent. And one day you realized that most of the people you once considered close friends had become strangers.
If this sounds familiar, you are not imagining things. Research from the Kennedy Krieger Institute found that 40% of parents of autistic children have pulled away from friends and family because of their child's behaviors. Another 32% report being actively excluded by others. This is not a personal failure. It is one of the most common and least discussed consequences of raising a neurodivergent child.
## Why Friendships Fall Apart After a Diagnosis
The reasons are layered, and none of them are your fault.
**Your schedule becomes unpredictable.** Therapy appointments, school meetings, meltdown recovery days, and the constant energy required to manage sensory needs leave little room for spontaneous plans. When you cancel three times in a row, even the most understanding friends stop asking. And the guilt of saying no, again, makes it easier to just stop trying altogether.
**Other parents do not understand your reality.** When your child has a meltdown at a birthday party, it is not the same as a neurotypical tantrum. But to the parent hosting the party, it looks identical. And when their best advice is "just be more firm" or "have you tried taking away screen time," the gap between your worlds becomes almost impossible to bridge.
**Judgment replaces empathy.** A Kennedy Krieger study found that 95% of parents feel shame when their autistic child has a public meltdown. That shame becomes a wall. You stop going to the park, the restaurant, the neighborhood gathering. Not because your child cannot handle it, but because you are exhausted from the stares and the whispered comments.
**The mental load is invisible.** The hours you spend researching therapies, decoding IEP documents, building [visual schedules](/blog/visual-schedules-for-autism), managing insurance appeals, and lying awake wondering if you are doing enough. Friends who do not share this experience often cannot see the weight you carry, and asking them to understand feels like one more task on a list that never ends. If you are also [balancing a career](/blog/working-parent-neurodivergent-child), the exhaustion doubles.
**You start pre-filtering yourself out.** After enough disappointing experiences, many parents begin declining invitations before anyone has a chance to exclude them. This self-protective instinct makes sense, but it accelerates the isolation cycle. You tell yourself it is easier to stay home, and before long, you have stopped getting invited at all.
**Some people simply leave.** This is the hardest truth. Some friendships do not survive because the other person lacks the capacity or willingness to show up for something they do not understand. That loss is real, and it deserves to be grieved.
## The Stigma Nobody Warns You About
Stigma plays a larger role than most people realize. Research published by the Kennedy Krieger Institute found that 80% of autism parents say stigma has been extremely, very, or somewhat difficult in their lives. It shows up in ways that accumulate quietly over time:
- A family member who insists your child "just needs more discipline"
- A friend who stops inviting you to group gatherings because your child "makes things difficult"
- A neighbor who looks away when you walk by after a public meltdown
- Other parents at school who avoid sitting near you at pickup
- Comments framed as concern that are really criticism in disguise
A 2024 study published in the journal Autism found that external responses to autism directly damage family social relationships and well-being. The researchers described it as families being "made to feel different," and the effects ripple outward from the child to every corner of the family's social world.
When you are constantly bracing for judgment, even safe spaces start to feel unsafe. That hypervigilance is exhausting. And it makes the idea of showing up to another school event or neighborhood barbecue feel like a risk you simply cannot afford to take.
## What Isolation Does to Your Health and Your Parenting
Social isolation is not just emotionally painful. It is actively harmful.
Research consistently shows that parents of autistic children face elevated rates of anxiety, depression, and burnout compared to parents of children with other disabilities. A study published in Molecular Psychiatry identified what researchers call a "spillover effect": high parental stress worsens a child's autism-related behaviors, which in turn increases parental stress even further. The cycle deepens isolation at every turn.
Mothers are disproportionately affected. Studies show they report lower quality of life, reduced social support, and higher psychological distress than fathers in the same household. But fathers are not immune. A 2024 study in the journal Family Process found that fathers of autistic children are significantly vulnerable to loneliness, challenging the assumption that social isolation is primarily a maternal experience.
The ripple effects do not stop with the parent. Research shows that parental stress and isolation can affect sibling relationships, contribute to marital tension, and reduce a parent's ability to engage consistently with their autistic child's [therapy and routines](/blog/autism-diagnosis-what-to-do-next). Losing your support system does not just hurt emotionally. It undermines the foundation your entire family depends on.
## The Silver Lining Nobody Talks About
Here is something the research reveals that might surprise you: while the number of friendships decreases, the quality of those that survive often improves significantly.
Raising an autistic child has a way of filtering your social circle. The people who cannot handle complexity or discomfort quietly disappear. But the people who stay, the ones who text you after a hard therapy session, who bring dinner without being asked, who sit with your child at a party without judgment, those friendships become deeper and more meaningful than anything you had before.
Researchers have described this as a "friendship filter." The relationships that survive the upheaval of a diagnosis tend to be grounded in genuine empathy, honesty, and the kind of loyalty that only shows up when life gets hard. Superficial friendships fall away, and what remains is real.
This does not make the losses hurt less. But it does mean that the friendships you build from this point forward are built on something solid.

## How to Rebuild Your Circle
Rebuilding a social life while parenting an autistic child takes intentionality. But the research points to strategies that genuinely work.
**Find other autism parents.** This is the single most effective step. Research published in the Journal of Autism and Developmental Disorders found that informal social supports, including parent groups and online communities, were rated as more helpful than formal professional services. These are people who understand why you cancelled, who do not need you to explain why the restaurant did not work, and who celebrate the milestones nobody else notices.
**Lower the bar for connection.** Friendship does not require dinner reservations and hours of uninterrupted conversation. A ten-minute voice memo while driving to therapy counts. A text that says "today was brutal" and getting a heart emoji back counts. Connection happens in small, imperfect moments when you stop waiting for the perfect ones.
**Be honest with your existing friends.** Some of your old friendships may be salvageable if you are willing to be direct. Tell them what your life actually looks like now. Tell them what kind of support helps and what does not. Some people will rise to the occasion. Others will not, and that clarity is valuable even when it stings.
**Let friends help in specific ways.** Many people want to help but do not know how. Instead of waiting for an open-ended offer, give them something concrete: "Could you pick up groceries on Thursday?" or "Can you sit with the kids for an hour Saturday morning?" Specific asks are easier for people to say yes to, and they create a pattern of support that strengthens the relationship over time.
**Invest in respite care.** Research from the Autism Research Institute identifies respite care as one of the most promising strategies for reducing caregiver burden and enabling social participation. Even a few hours of reliable help each week can create the space you need for the relationships that sustain you.
**Protect your own mental health.** A systematic review found that mindfulness-based stress reduction programs show the strongest evidence for reducing parenting stress among autism caregivers. When your own mental health is stabilized, you have more energy and emotional capacity for the connections that keep you grounded.
**Use online communities as a bridge.** Research confirms that remote support, telehealth groups, and social media communities reduce the logistical barriers that keep parents isolated. You do not have to leave your house to find people who understand your life. Facebook groups, Reddit communities, and platforms built for autism families can become genuine lifelines.
**Create structure that gives you breathing room.** Tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) help you build [visual routines](/blog/visual-schedules-for-autism) that give your child more independence and predictability throughout the day. When daily structure runs more smoothly, you reclaim time and mental energy for the relationships and self-care that keep you whole.
**Reconnect without pressure.** If there is an old friend you miss, reach out without expectations. A simple "I have been thinking about you" text carries no obligation. Not every friendship can be rebuilt, but some people are just waiting for permission to re-enter your life.
## You Are Not Alone in Feeling Alone
If you have watched your friend group shrink since your child's diagnosis, know this: it is not because something is wrong with you. It is because the world has not yet caught up to what neurodivergent families actually need from their communities.
The friends you have lost are not a reflection of your worth as a parent or as a person. They are a reflection of how poorly our culture understands autism and the families navigating it every single day.
The friends you will find, the ones who get it, who show up even when things are messy, who stay when it would be easier to leave, will change everything. And the parent community that surrounds neurodivergent families is one of the strongest, most compassionate communities you will ever be part of.
You just have to let yourself in.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that bring structure and calm to your family's day, create [social stories](/blog/social-stories-autism-guide) that prepare your child for outings and social situations, track [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) so you can identify what is working and what needs adjusting, and share schedules with every caregiver in your child's life from one place. Just $6.99/month after your trial, no credit card required upfront.
---
## Picky Eating and Autism: Why Your Child Is Not Just Being Difficult
Published: 2026-03-14
URL: https://vizyplan.com/blog/picky-eating-autism-spectrum-food-selectivity
Category: Strategies
Author: Justin Bowman
> Research shows 63% of autistic children have significant food selectivity. Why it happens, what actually helps, what makes it worse, and when picky eating crosses into something that needs professional support.
You made chicken nuggets. The same chicken nuggets you always buy, from the same brand, in the same bag. But something is wrong. Maybe the breading looks slightly different. Maybe the shape is off. Maybe the oven cooked them four degrees warmer than usual and the texture changed in a way you cannot detect but your child absolutely can. They will not touch them. Dinner is over before it started, and you are standing in the kitchen wondering how a food your child ate happily yesterday has become the enemy today.
This is not a phase. This is not your child being difficult, manipulative, or spoiled. And the advice you are getting from well-meaning relatives, "just make them eat it" or "they will eat when they are hungry," is not just unhelpful. For an autistic child, it can be actively harmful.
Food selectivity in autism is one of the most misunderstood aspects of the diagnosis. It looks like stubbornness from the outside. From the inside, your child's nervous system is doing exactly what it is designed to do: rejecting input that feels unsafe. Understanding why that happens, and what actually works to expand their diet over time, changes everything.
## How Common This Really Is
If your child eats the same five foods on rotation and refuses everything else, you are not alone. A 2025 meta-analysis published in Research in Autism Spectrum Disorders found a mean prevalence of **63.5 percent** food selectivity in autistic individuals, with individual studies ranging from 46 to 89 percent depending on how selectivity was measured.
The numbers are stark when compared to neurotypical peers. Bandini and colleagues at USC and UMass studied 53 autistic children alongside 58 typically developing children and found that autistic children **refused 41.7 percent of foods** offered, compared to 18.9 percent for neurotypical children. Schreck and colleagues found that autistic children ate roughly **half the number of foods in each food group** compared to controls. Cornish found that **59 percent of autistic children ate fewer than 20 different foods**.
This is not garden-variety pickiness. A study by Dominick and colleagues found that over three-quarters of autistic children showed atypical eating behavior, compared to only 16 percent of children with language disorders alone. The eating challenges are specific to autism, not just a byproduct of developmental delay.
And the rate at which autism and ARFID (Avoidant Restrictive Food Intake Disorder) co-occur is striking. A 2025 meta-analysis by Sader and colleagues at the University of Aberdeen analyzed 21 studies with 7,442 participants and found that autism prevalence in ARFID populations was **15 times higher** than in the general population. Among all eating disorders associated with autism, ARFID had the highest prevalence at 28 percent.
## Why Your Autistic Child Is a "Picky Eater"
The word "picky" minimizes what is actually happening. Your child is not choosing to be difficult about food. Multiple neurological systems are converging to make eating genuinely challenging in ways that neurotypical children and adults simply do not experience.
### Sensory Processing Is the Primary Driver
Over **90 percent of autistic children have sensory abnormalities across multiple domains**, according to research by Leekam. When it comes to food, those abnormalities intersect with every bite.
Williams and colleagues surveyed 100 parents and found the sensory factors driving food refusal:
- **Texture: 69 percent** of parents identified this as a factor
- **Appearance: 58 percent**
- **Taste: 45 percent**
- **Smell: 36 percent**
- **Temperature: 22 percent**
Schmitt and colleagues found that **70 percent of autistic boys chose food based on texture**, compared to only 11 percent of controls. A separate study found that **78 percent showed marked selectivity for food texture** and 53 percent discriminated based on color.
This is why your child can tell the difference between two brands of the same cracker. Their sensory system is processing information at a level of detail that most people's brains filter out. A slight change in texture, a different shade of yellow on a cheese slice, a brand substitution that you thought was identical, registers as an entirely different food to your child's nervous system.
### The Need for Sameness
Autism involves a strong drive toward predictability and routine. At mealtimes, this means the same foods, prepared the same way, served in the same dish, at the same temperature, from the same brand. Any deviation, even one you cannot detect, can trigger refusal. This is not about preference. It is about a nervous system that interprets unpredictability as threat.
### Interoception Differences
Interoception is the ability to sense what is happening inside your body: hunger, fullness, thirst, discomfort. Research by DuBois and colleagues has documented that autistic individuals frequently have atypical interoception, meaning they may not connect the physical sensation of an empty stomach with the concept of being hungry. Occupational therapist and interoception researcher Kelly Mahler has documented that these differences lead to irregular eating patterns and difficulty self-regulating food intake.
Your child may genuinely not feel hungry at mealtimes. Or they may not recognize fullness until they have overeaten. This is a neurological difference, not a behavioral choice.
### Oral Motor Challenges
Some autistic children have difficulty with the physical mechanics of eating. Chewing certain textures requires motor planning and oral coordination that may be underdeveloped. A systematic review found significant oral sensory challenges in autistic children and adolescents, with higher oral sensory scores associated with greater feeding problems. If a food is difficult to chew or swallow, the child learns to avoid it, and that avoidance looks like pickiness from the outside.
### Anxiety and Food Neophobia
Food neophobia, the fear of new foods, is significantly elevated in autistic children. Qian Lin and colleagues studied 160 children with ASD and found higher food neophobia scores compared to typically developing peers. But here is the critical finding from that study: **caregiver pressure to eat was positively associated with higher food neophobia**. The more parents pushed, the more anxious children became about food, and the fewer foods they were willing to try. Pressure creates the opposite of what you want.

## When Picky Eating Becomes Something More Serious
There is a meaningful clinical distinction between a picky eater and what feeding specialists call a "problem feeder." Dr. Kay Toomey, developer of the SOS Approach to Feeding, defines the difference:
- **A picky eater** typically accepts 30 or more foods. They may go through phases of refusing certain foods but will usually return to them. They can tolerate new foods being placed on their plate, even if they do not eat them.
- **A problem feeder** accepts fewer than 20 foods. Their diet continues to shrink over time rather than expand. They may cry, gag, or have a meltdown when new foods are presented. They refuse entire food categories.
ARFID is the clinical diagnosis that applies when food restriction leads to one or more of these outcomes: significant weight loss or failure to gain weight, nutritional deficiency, dependence on supplements or tube feeding, or significant interference with social functioning. Unlike anorexia, ARFID is not driven by body image concerns. In autistic children, the most common presentation is **sensory-based avoidance**, which was found in 21 to 49 percent of cases in the Sader meta-analysis.
### Red Flags That Need Professional Attention
Watch for these signs that your child's eating has moved beyond typical selectivity:
- They eat fewer than 20 foods, and the number is shrinking
- They have lost weight or are not gaining weight appropriately
- They refuse entire food groups, especially all fruits and vegetables
- They gag, vomit, or show extreme distress when new foods are introduced
- [Mealtimes](/blog/mealtime-strategies-picky-eating-autism-adhd) consistently end in meltdowns for the child or the parent or both
- They show signs of nutritional deficiency: fatigue, frequent illness, brittle hair or nails, poor growth
- They eat non-food items (pica)
- Their diet consists almost entirely of one type of food, such as only processed carbohydrates
If any of these apply, your child needs a professional feeding evaluation, not more time to "grow out of it."
## The Nutritional Reality
The restricted diets common in autistic children carry real nutritional consequences. A research review of 63 published articles found severe nutrient deficiencies in individuals with autism due to restricted eating.
The most commonly reported deficiencies:
- **Vitamin D** is the most frequent, with one study of 1,529 autistic patients finding deficiency or insufficiency in approximately **95 percent**
- **Vitamin A** deficiency was found in 24 percent of cases
- **B-vitamins** in 18 percent
- **Calcium** in nearly 11 percent
- **Iron** in nearly 10 percent
What makes this more concerning is that deficiencies rarely occur alone. Approximately **70 percent of cases showed two or more co-occurring deficiencies**. All cases of calcium deficiency were accompanied by vitamin D deficiency. 75 percent of iron-deficient cases had concurrent vitamin C deficiency.
Research across six countries found that autistic children displayed nearly identical dietary patterns regardless of culture: processed carbohydrates with minimal vegetables. The sensory-driven food choices transcend cultural food norms entirely.
If your child's diet is limited, talk to your pediatrician about bloodwork and consider a consultation with a registered dietitian who has experience with autism. A targeted supplement plan is far more effective than guessing.
## What Actually Works
Expanding an autistic child's diet is possible, but it requires approaches designed for how their brain processes food. Generic "picky eater" advice does not apply here.
### Food Chaining
Developed by Cheri Fraker, Dr. Mark Fishbein, and Sibyl Cox, food chaining is a systematic method that links new foods to foods your child already accepts by sharing a sensory property. If your child eats Goldfish crackers, the chain might move to a different cheese cracker, then to cheese on bread, then to grilled cheese. Each step changes one property while keeping the rest familiar.
The principle is simple: instead of asking your child to jump from "eats five foods" to "eats a balanced meal," you build bridges between what they accept and what you want to introduce. Each bridge is small enough that it does not trigger the sensory alarm system.
### The Exposure Hierarchy (Without Pressure)
The most commonly used approach in feeding therapy, employed in 66.7 percent of reviewed studies, is systematic desensitization. It follows a developmental progression:
1. **Tolerate** the food being in the room 2. **Tolerate** the food being on the table 3. **Tolerate** the food being on their plate 4. **Interact** with the food (push it with a fork, poke it) 5. **Smell** the food 6. **Touch** the food with their hands 7. **Taste** the food (a lick, then a small bite) 8. **Eat** the food
This hierarchy must be implemented with **zero pressure**. The child advances at their own pace. Some children will move through steps quickly. Others will spend weeks at "tolerate on the plate." Both are fine. All reviewed studies confirmed improvement in food acceptance using this approach.
### The SOS Approach to Feeding
Dr. Kay Toomey's SOS (Sequential Oral Sensory) approach is a play-based, 12-week program that moves children through six phases: visual tolerance, interaction, smell, touch, taste, and eating. It treats food refusal as a sensory and developmental challenge rather than a behavioral problem.
The SOS approach does not use force, pressure, or reward systems tied to eating. Instead, it uses food play and exploration to reduce the anxiety and sensory defensiveness around new foods. A 2025 feasibility study by Schoen and colleagues at the STAR Institute developed the first documented fidelity measure for the SOS approach, suggesting growing research interest in validating what clinicians have been using for years.
### Visual Supports at Mealtimes
[Visual supports](/blog/visual-schedules-for-autism) reduce unpredictability, and unpredictability is the enemy of food acceptance.
- **Visual menus** showing what will be served let your child prepare mentally before the meal arrives. No surprises.
- **[First-then boards](/blog/first-then-boards-guide):** "First one bite of carrot, then macaroni." The visual makes the expectation concrete and the reward visible.
- **[Choice boards](/blog/choice-boards-empowering-decisions):** Offering two or three acceptable options gives your child control. Control reduces anxiety. Less anxiety means more willingness to engage with food.
- **[Visual timers](/blog/visual-timers-time-management-neurodivergent-children)** showing how long the child needs to stay at the table eliminate the open-ended dread of "when does this end?"
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build mealtime routines with [AI-generated images personalized to your child](/blog/ai-generated-images-visual-supports), so the visual sequence shows their actual plate, their actual kitchen, their actual foods. That specificity matters when your child depends on sameness for safety.
### Sensory Strategies Beyond the Plate
An occupational therapist can help you understand your child's specific sensory profile and how it relates to food. General strategies that many families find helpful:
- **Reduce sensory load during meals.** Turn off the TV. Lower the lights if they are harsh. Minimize competing smells from cooking other foods. The less sensory input your child has to process, the more capacity they have for the food itself.
- **Same plate, same utensils, same spot.** Consistency in the mealtime environment frees up processing capacity for the food, which is where the change is happening.
- **Temperature matters.** Some autistic children insist on room-temperature food. If your child rejects foods that are hot or cold, try serving everything at room temperature and see if acceptance improves.
- **Separate everything.** Many children become distressed when foods touch. Divided plates or separate small bowls eliminate this trigger entirely.
## What Makes It Worse
This matters as much as what helps. Several well-intentioned approaches are actively counterproductive for autistic children with food selectivity.
### Forcing or Pressuring Children to Eat
Research by Galloway and colleagues found that children consumed **significantly more food when they were not pressured to eat** and made fewer negative comments about food. Qian Lin and colleagues found that caregiver pressure to eat was directly associated with **increased food neophobia** in autistic children, which in turn negatively impacted dietary quality.
Pressure creates a vicious cycle: you push, the child becomes more anxious about food, they accept fewer foods, you push harder. The research is clear. Pressure does not work. It makes things worse.
### Hiding Vegetables in Accepted Foods
This seems logical but backfires. When an autistic child detects a change in their safe food, whether it is a blended vegetable or a different ingredient, they do not just reject the new version. They may become **suspicious of the safe food itself** and stop eating it entirely. You have not expanded their diet. You have shrunk it. Feeding specialists consistently recommend against hiding foods because it undermines the trust that is essential for eventual food expansion.
### "They Will Eat When They Are Hungry"
This is the single most dangerous piece of advice for parents of autistic children with food selectivity. It is **wrong for this population.** The Kennedy Krieger Institute documents a case where a health professional suggested withholding preferred foods and the child ended up hospitalized for dehydration rather than eating non-preferred foods.
Here is why the "hungry enough" myth fails for autistic children:
- **Sensory aversions are not motivational problems.** A child will not eat food that causes sensory distress even when starving. The aversion is neurological, not willful.
- **Interoception differences mean many autistic children cannot accurately recognize hunger signals.** They may be hungry without knowing it, or the sensation of hunger may not connect to "I should eat."
- **Rigidity overrides hunger.** The need for sameness in autism is stronger than the hunger drive in many children.
Feeding specialists make this critical distinction: while typically developing picky eaters will not starve themselves, **problem feeders might.** Do not withhold preferred foods from an autistic child hoping that hunger will force compliance. It will not. It will cause distress, weight loss, and a breakdown of trust.
### Punishment, Bribery, and Forced Bites
Using consequences for not eating, bribing with dessert, or requiring a set number of bites before the child can leave the table all frame eating as a power struggle. For an autistic child whose food refusal is driven by genuine sensory distress, these approaches are the equivalent of punishing someone for flinching when something hurts. The behavior is not under their conscious control, and punishing it creates trauma around mealtimes that can persist for years.
## Building a Better Mealtime, Step by Step
You are not going to transform your child's diet overnight. But you can start building the conditions that make food expansion possible.
**Week 1:** Track what your child currently eats. Write down every food, every brand, every preparation method. This is your baseline. You might have more to work with than you think, or you might confirm that professional help is needed.
**Week 2:** Identify sensory patterns. Are the accepted foods all the same texture (crunchy, smooth, chewy)? Same color? Same temperature? Same brand? These patterns tell you which sensory properties feel safe and give you a starting point for food chaining.
**Week 3:** Build a [mealtime visual routine](/blog/mealtime-strategies-picky-eating-autism-adhd). Show what happens at mealtimes: wash hands, sit down, eat from plate, ask to be done. Predictability reduces the anxiety that fuels food refusal.
**Week 4:** Place one new food on your child's plate alongside their safe foods, with zero expectation. Do not comment on it. Do not ask them to try it. Just have it there. Do this every day. You are beginning the exposure hierarchy at step one: tolerate on plate.
**Ongoing:** Continue daily no-pressure exposure. When your child interacts with the new food in any way, touching it, sniffing it, licking it, acknowledge it without making a big deal. "You touched the broccoli" is fine. "Great job! Can you take a bite?" is pressure. Let the progression happen naturally.
## When to Call for Help
If your child eats fewer than 20 foods, is losing weight, has documented deficiencies, or if mealtimes are a source of chronic family distress, you need a professional team. Feeding challenges in autism often require multiple specialists working together:
- **Pediatrician:** Rule out medical causes, order bloodwork, monitor growth
- **Occupational therapist:** Address [sensory processing](/blog/sensory-processing-daily-routines) and oral motor challenges
- **Speech-language pathologist:** Evaluate swallowing safety and oral coordination
- **Registered dietitian:** Assess nutritional adequacy and plan supplementation
- **Feeding therapist:** Specialized intervention using SOS, food chaining, or behavioral approaches
- **Pediatric gastroenterologist:** If GI issues, reflux, or food allergies are suspected
Ask your child's [therapists](/blog/finding-right-therapist-neurodivergent-child) for feeding specialist recommendations. Word of mouth from other autism parents is often the most reliable way to find someone who understands the intersection of autism and food.
## Your Child Is Not Broken
Your child is not being difficult. They are not spoiled. They are not going to be ruined by eating chicken nuggets every day for a year. Their nervous system is doing its job, filtering the world through a sensory lens that is more sensitive, more detailed, and less forgiving of variation than most people's.
The goal is not to make your child eat "normally." The goal is to build enough flexibility and nutritional adequacy that food is not a source of suffering for them or for you. Some autistic adults eat a limited diet their entire lives and are perfectly healthy and happy. Others expand significantly with the right support at the right time.
Meet your child where they are. Feed them what they will eat today, without guilt. And then, slowly, with patience and without pressure, build the bridges that help them try something new when they are ready.
You are not failing at feeding your child. You are parenting a child whose relationship with food is fundamentally different from what the world expects, and you are showing up every single meal to figure it out. That is not failure. That is love doing its hardest, quietest work.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual mealtime routines](/blog/mealtime-strategies-picky-eating-autism-adhd) that reduce anxiety around food, create [choice boards](/blog/choice-boards-empowering-decisions) that give your child control over what they eat, use [first-then boards](/blog/first-then-boards-guide) to pair new foods with preferred ones, and track [patterns](/blog/tracking-emotions-activities-neurodivergent-children) to identify which sensory properties your child accepts so you can build food chains from there. Just $6.99/month after your trial, no credit card required upfront.
---
## Your Child Got an Autism Diagnosis: What Comes Next
Published: 2026-03-13
URL: https://vizyplan.com/blog/autism-diagnosis-what-to-do-next
Category: Strategies
Author: Justin Bowman
> The diagnosis changes everything and nothing at the same time. A research-backed guide to the emotions, the providers, the insurance, the support systems, and the first steps that actually matter after your child is diagnosed with autism.
The paper is in your hands. Or maybe it was an email, a phone call, a conversation across a desk with a psychologist who said the words you had been bracing for or the words you never expected. Your child has autism.
And now you are sitting in your car, or standing in your kitchen, or lying awake at 2 AM with a phone full of browser tabs, and the only question in your head is: what do I do now?
The answer is not simple. It is not a single phone call or a single appointment. It is a series of steps that will unfold over weeks and months, and the order matters less than the fact that you start. This guide walks you through the emotions, the providers, the systems, and the support that will carry your family through this transition, one decision at a time.
## The Emotions Are Part of This
Before you make a single phone call, before you google a single therapy, you need to know this: what you are feeling right now is normal. All of it. The relief of finally having an answer. The grief of a future you had imagined shifting. The anger at yourself for not seeing it sooner, or at the doctor who told you to wait. The guilt. The fear. The strange numbness that comes when your brain has too much to process at once.
Research tells us that **33 percent of parents of autistic children experience clinically significant anxiety** and **31 percent experience depressive symptoms**, according to a meta-analysis by Schnabel and colleagues published in Frontiers in Psychology. Mothers are disproportionately affected, with depression scores that often exceed clinical thresholds requiring monitoring.
What the studies call "cyclical grieving" means the grief does not follow a straight line. You will reach acceptance, feel steady, and then watch your child's same-age peers hit a milestone your child has not reached, and the sadness will return like it never left. Researcher Simon Olshansky described this as "chronic sorrow," an enduring grief that resurfaces at developmental milestones, school transitions, and social situations where the gap between your child and their peers becomes visible.
This is not weakness. This is the natural response of a parent whose love for their child is colliding with uncertainty about the future. Give yourself permission to feel it without rushing past it. Parents who leap directly into "fix-it mode" without processing the emotional weight of the diagnosis are more vulnerable to [burnout](/blog/caregiver-burnout-parents-neurodivergent-children), decision fatigue, and poor choices made from desperation rather than clarity.
You do not need to have it together right now. You just need to keep going.
## Understanding What the Diagnosis Means (and What It Does Not)
An autism diagnosis is an explanation, not a sentence. It does not change who your child was yesterday. It does not define their ceiling. It gives you a framework for understanding how their brain processes the world, so you can support them more effectively.
Autism is now diagnosed in **1 in 31 children** in the United States, according to the CDC's most recent data from 2025. The median age of earliest diagnosis is approximately 4 years old, meaning many children are diagnosed well into their preschool or early school years. If your child was diagnosed later, you have not missed some critical deadline. You are starting exactly where you need to start.
What the diagnosis tells you:
- **Your child's brain processes sensory information, social cues, and communication differently.** Not worse. Differently. Understanding these differences is the key to everything that follows.
- **Many of the things that have been hard, the meltdowns, the rigidity, the [sensory sensitivities](/blog/sensory-processing-daily-routines), the social struggles, now have context.** That context changes how you respond to them.
- **Your child qualifies for services and supports** that were not available without a diagnosis. Insurance coverage, school accommodations, therapeutic interventions, and community resources all open up.
What it does not tell you:
- **It does not predict your child's future.** The autism spectrum is vast. Some autistic adults live independently, have careers and families. Others need lifelong support. Where your child lands depends on many factors, and it is too early to know.
- **It does not mean something went wrong.** Autism is neurodevelopmental, not caused by parenting choices, vaccines, or anything you did or did not do.
## The Providers You Need (and How to Choose Them)
This is where most parents feel the most overwhelmed. The diagnosis report may include a list of recommended therapies that reads like a full-time job. Here is what you need to know about each, who to call first, and how to tell a good provider from a bad one.
### Speech-Language Pathologist (SLP)
If your child has any communication differences, whether they are nonverbal, have limited language, struggle with social conversation, or have difficulty understanding what others say, a speech-language pathologist is typically the first provider to establish.
SLPs work on receptive language (understanding), expressive language (communicating), social pragmatic communication (the back-and-forth of conversation), and alternative communication methods like [AAC devices or picture exchange systems](/blog/choice-boards-empowering-decisions) for children who need them.
**How to find one:** Ask your pediatrician for a referral, contact your insurance company for in-network providers, or search the ASHA (American Speech-Language-Hearing Association) ProFind directory. Look for SLPs with specific experience in autism, not just pediatric speech therapy in general.
### Occupational Therapist (OT)
An occupational therapist addresses the daily living skills and sensory processing differences that affect your child's ability to function. This includes [fine motor skills](/blog/fine-motor-skills-handwriting-neurodivergent-children), [self-care routines](/blog/bath-time-hygiene-routines-neurodivergent-children) like dressing and eating, [sensory regulation](/blog/sensory-processing-daily-routines), and the ability to participate in age-appropriate activities.
If your child is overwhelmed by certain textures, sounds, or environments, if [getting dressed is a battle](/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children), if [mealtimes are a war zone](/blog/mealtime-strategies-picky-eating-autism-adhd), an OT can help you understand why and build strategies that work.
**How to find one:** Same referral paths as SLP. Look for OTs with sensory integration training and pediatric autism experience. The AOTA (American Occupational Therapy Association) has a provider directory.
### Applied Behavior Analysis (ABA) Therapist
ABA is the most widely researched behavioral intervention for autism. A Board Certified Behavior Analyst (BCBA) designs the treatment plan, and Registered Behavior Technicians (RBTs) typically implement it under BCBA supervision.
This is also the therapy with the most variance in quality. Good ABA is collaborative, play-based, focused on building skills, and works toward making your child more independent. Bad ABA is compliance-driven, suppresses harmless stimming, forces eye contact, and prioritizes making the child "look normal" over actually supporting them.
**Green flags to look for:**
- The BCBA includes you and your child in goal development
- They aim to "work themselves out of a job" with clear discharge criteria
- They use positive reinforcement, not punishment
- They allow and encourage parents to observe sessions
- They explain their approach and timeline transparently
**Red flags to walk away from:**
- Insufficient BCBA supervision (the BCBA should be actively involved, not just signing off)
- Not allowing parents to observe
- Reducing or eliminating harmless self-stimulatory behavior (stimming)
- Recommending 35 to 40 hours per week without discussing family needs
- Using punishment-based procedures
- Cannot articulate when or how your child will transition out of services
**How to find one:** Contact your insurance for covered providers. Autism Speaks maintains a resource directory. Ask other autism parents in your area for recommendations, as word of mouth is often the most reliable indicator of quality.
### Developmental Pediatrician
Your regular pediatrician manages general health. A developmental pediatrician specializes in the medical management of developmental disabilities, including co-occurring conditions like [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies), ADHD, [sleep disorders](/blog/sleep-challenges-night-waking-neurodivergent-children), and gastrointestinal issues that frequently accompany autism. If medication becomes part of the conversation, this is the specialist who manages it.
**Wait times for developmental pediatricians are among the longest.** A CMS survey found that 61 percent of autism centers had wait times longer than four months, and 15 percent reported waits over a year. Call early, even if you are not sure you need this provider yet. Getting on the waitlist now gives you the option later.
### Do Not Schedule Everything at Once
Here is where parents make the most common mistake. They read the diagnosis report, see the list of recommended therapies, and try to schedule everything immediately. Within weeks, the child is in therapy four or five days a week, the parent is spending every free hour in waiting rooms, and the entire family is exhausted.
Research actually challenges the "more is always better" assumption. A 2024 study by Anderson and colleagues found that a moderate-intensity intervention of **5 to 10 hours per week was non-inferior to comprehensive behavioral intervention of 15 or more hours per week** on adaptive behavior outcomes. Parent involvement was identified as potentially more important than raw therapy hours.
Start with one or two providers. Let your child adjust. Let yourself adjust. Then add more as your family finds its rhythm. A recovered, present parent is more valuable to your child than an additional hour of therapy.
## Early Intervention: What the Research Actually Shows
You have probably heard the phrase "early intervention is critical," and it is. But "critical" does not mean "if you miss this window, all is lost." It means that the earlier you start, the more your child's brain can benefit from the support.
The most compelling evidence comes from the **Early Start Denver Model (ESDM)**, developed by researchers Sally Rogers and Geraldine Dawson. In a randomized controlled trial, 48 children diagnosed with autism between 18 and 30 months received either ESDM or standard community services for two years. The ESDM group improved **17.6 IQ standard score points** compared with 7.0 points in the comparison group, with significant gains in language, adaptive behavior, and reduced autism symptom severity. These gains were maintained at a two-year follow-up.
The landmark Lovaas study found that 47 percent of children who received early intensive behavioral intervention achieved normal-range intellectual functioning, with IQ gains 30 points above controls.
But here is the nuance that gets lost: **only 15 percent of preschool-aged autistic children currently receive early intervention services before age 2**, according to Lidstone and colleagues in a 2025 study published in Autism Research. If your child is 3, 4, 5, or older, you have not missed the boat. Intervention at any age produces meaningful gains. The brain retains plasticity well beyond the toddler years. You are starting at exactly the right time, which is now.
## Navigating Insurance and Funding
The financial reality of autism services is daunting. Families with an autistic child face average annual costs of **$60,000** including medical care, therapy, and specialized education. Without insurance, ABA therapy alone can cost $4,800 to $20,000 per month.
The good news: **all 50 states now have autism insurance mandates** requiring coverage for diagnosis and treatment, including ABA therapy. And as of 2022, all 50 states have implemented Medicaid coverage for autism treatment.
Here is how to navigate it:
### Call Your Insurance First
Before scheduling with any provider, call the number on the back of your insurance card and ask:
- What autism-related services are covered under our plan?
- Is ABA therapy covered? How many hours per week?
- Are there age limits or annual dollar caps on autism services?
- Do we need a referral or prior authorization?
- What is our out-of-pocket maximum for these services?
- Can you send me a list of in-network autism providers?
Document everything. Write down the name of the person you spoke with, the date, and what they told you. Insurance companies sometimes give conflicting information, and having a record protects you.
### Part C Early Intervention (Birth to Age 3)
If your child is under 3, contact your state's Part C early intervention program immediately. Part C is a federal program under IDEA that funds early intervention services for infants and toddlers with disabilities. Services are provided through an Individualized Family Service Plan (IFSP) and are often free or on a sliding fee scale.
Every state participates, though services and eligibility criteria vary. Your pediatrician can refer you, or you can contact your state's early intervention office directly. You do not need to wait for the referral. You can self-refer.
### Part B and School Services (Age 3 and Up)
When your child turns 3, they transition from Part C to Part B of IDEA, which provides services through the school district. This transition requires re-evaluation and a new plan, an Individualized Education Program ([IEP](/blog/provider-collaboration-iep-preparation)) rather than an IFSP.
**Critical detail:** transition planning must begin at least 90 days before your child's third birthday. If your child is approaching 3 and you have not heard from your school district, contact them proactively. Under IDEA's Child Find mandate, school districts are legally required to identify and evaluate all children with disabilities, even those not yet enrolled in school.
If your child is already school-aged, you can request a special education evaluation in writing at any time. The school district must respond. You have the right to an evaluation, to participate in all decisions about your child's education, and to a Free Appropriate Public Education (FAPE). If the district's evaluation does not capture your child accurately, you can request an Independent Educational Evaluation at the district's expense. For more on [IEPs versus 504 Plans](/blog/504-plan-vs-iep-neurodivergent-child), we have a detailed guide.
## Finding Your People
The isolation after an autism diagnosis is profound. Your friends with neurotypical children do not understand why you cannot just "get a babysitter." Your family may minimize the diagnosis or offer well-meaning but unhelpful advice. You need people who get it, people who are living it.
Research by Sharma, Govindan, and Kommu found **statistically significant reductions in anxiety and stress** among parents who participated in parent-to-parent support groups. Peer support increases parenting confidence, self-efficacy, and reduces caregiving strain. You are not just venting. You are literally improving your mental health by connecting with other parents who understand.
### Where to Find Support
**National organizations:**
- **Autism Society of America** has local chapters with support groups in most states
- **Autistic Self Advocacy Network (ASAN)** is run by and for autistic individuals and offers valuable perspective on supporting your child's identity
- **Autism Speaks** provides resource guides, toolkits, and insurance navigation help
- **The Arc** offers broader disability advocacy including autism
**Online communities:**
- Facebook groups for autism parents are the most widely used platform for peer support
- Reddit communities (r/AutismParenting) allow detailed discussions
- **A word of caution:** A 2025 scoping review published in JMIR found that misinformation in online health support groups is a significant concern. Not everything you read online is accurate. Stick to evidence-based sources for medical and therapeutic decisions, and use online groups primarily for emotional support and practical tips from lived experience.
**Local connections:**
- Ask your child's providers if they know of local parent groups
- Check your school district for parent advisory committees
- Hospital-affiliated autism programs often run caregiver groups
- Look for local Special Olympics, adaptive sports, or social skills groups where you can meet other families naturally
### Do Not Skip This Step
Parents who try to navigate the post-diagnosis period alone burn out faster, make decisions from a place of isolation, and miss resources they did not know existed. Finding even one other parent who understands your daily reality changes everything. You do not have to attend a formal support group if that is not your style. You just need someone you can text at 10 PM when the meltdown lasted an hour and you are sitting on the bathroom floor wondering if you are doing any of this right.
## The Dr. Google Spiral (and How to Avoid It)
You will google. Everyone googles. At 2 AM, you will find yourself seventeen tabs deep into articles about therapies, diets, supplements, and interventions you have never heard of. Some will be evidence-based. Many will not. Some will be actively harmful.
Here is a filter: **if a treatment promises to "cure" or "recover" your child from autism, walk away.** Autism is a neurological difference, not a disease to be cured. Legitimate interventions aim to build skills, reduce barriers, and improve quality of life, not to make your child "indistinguishable from peers."
Trustworthy sources include the CDC, NICHD (National Institute of Child Health and Human Development), peer-reviewed research, and established organizations like Autism Society and ASAN. Be cautious with social media testimonials, influencer-promoted supplements, and any intervention that has not been evaluated in controlled research.
When you find something that interests you, bring it to your child's providers. A good BCBA, SLP, or developmental pediatrician will give you an honest assessment of whether the evidence supports it.
## What to Do This Week
The full picture is overwhelming. Here is what to do in the next seven days, one step at a time:
**Day 1 to 2:** Let yourself feel whatever you are feeling. Talk to your partner, a friend, or a therapist. Do not make any big decisions yet.
**Day 3:** Call your insurance company. Ask what autism services are covered and request an in-network provider list. If your child is under 3, contact your state's Part C early intervention program.
**Day 4:** Choose one provider to start with. Speech therapy is often the most accessible and has the shortest waitlists. Call and get on the schedule, or on the waitlist.
**Day 5:** Join one online or local support group. Just lurk if you want. Read other parents' stories. You will recognize yourself.
**Day 6:** If your child is 3 or older, write a letter to your school district requesting a special education evaluation. This starts the clock on their legal obligation to respond.
**Day 7:** Start one [visual routine](/blog/visual-schedules-for-autism). Pick the part of the day that causes the most stress, whether that is the [morning](/blog/morning-routine-tips-adhd), [after school](/blog/after-school-routine-transitions-neurodivergent-children), or [bedtime](/blog/bedtime-routine-autism-adhd), and create a simple visual sequence your child can follow. You do not need to overhaul everything. You just need one anchor.
## What Not to Do
Research and clinical experience point to several patterns that hurt more than they help:
- **Do not schedule every therapy immediately.** Start with one or two and build gradually. Overwhelming your child and yourself with a packed therapy schedule leads to [burnout](/blog/caregiver-burnout-parents-neurodivergent-children) and worse outcomes.
- **Do not compare your child to other children**, neurotypical or autistic. Every autistic child has their own profile of strengths and challenges. Comparison triggers the cyclical grief that researchers have documented and serves no constructive purpose.
- **Do not make too many changes at once.** Autistic children depend on predictability. A new therapist, a new diet, a new sensory room, and a new [visual schedule](/blog/visual-schedules-for-autism) all in the same week is a recipe for regression. Introduce one change at a time and give it at least a week before adding another.
- **Do not forget your other children.** [Siblings](/blog/sibling-relationships-neurodivergent-families) feel the shift in attention. They need to know they still matter, that their needs are still seen, and that the family is not defined solely by the diagnosis.
- **Do not forget yourself.** You cannot pour from an empty cup. Therapy for yourself is not a luxury. A parent who is emotionally regulated, informed, and supported is the single most powerful intervention in your child's life.
## Your Child Is Still Your Child
The diagnosis did not change your child. They are the same person they were the day before the evaluation. The same laugh. The same quirks. The same things that make you love them so fiercely it physically hurts sometimes.
What changed is that you now have a map. Not a complete map, not one with every road marked, but enough to see the terrain. You know why the [mornings are hard](/blog/morning-routine-tips-adhd). You know why the [grocery store](/blog/grocery-store-strategies-errands-neurodivergent-child) is a nightmare. You know why [transitions](/blog/transition-strategies-autism) feel impossible. And with that understanding comes the ability to do something about it.
You will make mistakes. You will choose a provider who is not the right fit and have to start over. You will try a strategy that does not work and feel like you wasted time. You will have days where the weight of it all feels like too much to carry.
But you will also have the day your child uses a [visual schedule](/blog/visual-schedules-for-autism) independently for the first time. The day a therapist tells you about progress you had not even noticed. The day another parent in a support group says something that makes you feel less alone than you have felt in months. The day your child does something you were told they might never do.
Those days are coming. They do not erase the hard days, but they remind you that the work you are doing right now, the calls, the research, the routines, the showing up even when you are exhausted, is building something real.
Start with one step. Then take the next one. You have already done the hardest part, which is facing the truth and deciding to move forward. Everything from here is just putting one foot in front of the other.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that bring structure to the chaos of those first months after diagnosis, create [social stories](/blog/social-stories-autism-guide) to help your child understand new experiences like therapy visits and school transitions, track [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) so you and your providers can see what is working, and share schedules with every caregiver and [therapist](/blog/provider-collaboration-iep-preparation) in your child's life from one place. Just $6.99/month after your trial, no credit card required upfront.
---
## When Your Autistic Child Hits, Bites, or Lashes Out: What to Do Instead of Restraining
Published: 2026-03-12
URL: https://vizyplan.com/blog/aggressive-behavior-autism-biting-hitting-strategies
Category: Strategies
Author: Justin Bowman
> Research shows 68% of autistic children display aggression toward caregivers. Evidence-based strategies for understanding why it happens, responding safely in the moment, and building proactive systems that reduce aggressive episodes over time.
Your child just bit you. Hard. You are bleeding, they are screaming, and your other child is crying in the corner. In that moment, your instinct is to grab, hold, restrain, do whatever it takes to make the hitting stop. You are not a bad parent for that instinct. You are a human being whose nervous system just got activated by pain and fear.
But what happens next matters more than that instinct. Because how you respond to aggression shapes whether it escalates or de-escalates, whether it happens more frequently or less, and whether your child learns safer ways to communicate what their body was trying to say.
This is not an article about "managing behavior." It is about understanding what is driving the aggression, responding in ways that keep everyone safe without making things worse, and building the kind of proactive environment where hitting, biting, and lashing out happen less often over time.
## How Common This Actually Is
If your child is aggressive, you are not alone, and this is not a reflection of your parenting. Research by Kanne and Mazurek studying 1,380 children and adolescents with autism found that **68 percent had demonstrated aggression toward a caregiver** and **49 percent toward non-caregivers**. A separate study found that autistic preschoolers were three times more likely to display biting and hitting than non-autistic peers.
These numbers are staggering, yet most parents feel completely isolated when their child becomes aggressive. You do not talk about it at the playground. You do not post about it online. You cancel playdates because you cannot guarantee safety. The shame and secrecy around childhood aggression in autism is one of the biggest barriers to families getting help.
Self-injurious behavior, where a child hurts themselves through head-banging, biting their own hands, or skin-picking, affects an estimated **27 to 30 percent** of autistic children. If your child is hurting themselves in addition to or instead of hurting others, the strategies below still apply, and you should involve a professional as soon as possible.
## Why Your Child Is Aggressive (It Is Not What You Think)
The most important shift you can make is this: **aggression is communication, not defiance.** Your child is not choosing to be violent. Their nervous system is responding to something it cannot handle, and their body is doing the only thing it knows how to do.
Research identifies four primary functions that drive aggressive behavior in autistic children. Understanding which function is behind your child's aggression changes everything about how you respond.
### Escape or Avoidance
Your child hits when asked to do homework. They bite during teeth brushing. They throw things when you turn off the tablet. In each case, the aggression serves a purpose: making the demand go away. And if it works, if you stop the homework or hand back the tablet to end the crisis, the behavior is reinforced. Their brain learns: "Hitting makes hard things stop."
This is the most common function of aggression. It does not mean your child is manipulative. It means they are overwhelmed by demands their nervous system cannot currently process, and they do not have the words or skills to say "this is too hard" or "I need a break."
### Sensory Overload
The grocery store lights are buzzing. The birthday party is too loud. The tag in their shirt has been scratching all morning. Your child's [sensory system](/blog/sensory-processing-daily-routines) has been accumulating input all day, and they have reached the threshold where their body switches into fight mode. The aggression is not about the specific moment. It is about the last straw in a sensory system that has been overloaded for hours.
Research confirms that sensory processing difficulties are significantly associated with aggressive behavior in autistic children. The child who seems to "explode out of nowhere" has usually been building toward that explosion through accumulated sensory stress that adults did not notice.
### Communication Frustration
Your child wants something and cannot tell you. They need help and cannot ask. They are in pain and cannot explain where it hurts. When communication fails and the need is urgent, the body takes over. Aggression becomes the loudest, most effective form of communication available to them.
This is especially common in children with limited verbal language, but it also occurs in verbal children during moments of high emotional arousal when their language skills temporarily go offline. Under stress, the brain prioritizes survival responses over language production.
### Attention or Connection
Some children have learned that aggression is the fastest way to get a parent's full, undivided attention. This is not about being "attention-seeking" in a negative sense. It is about a child whose nervous system is wired to need more co-regulation, more connection, and more engagement than they are currently getting. If the only reliable way to get that attention is through crisis, the brain will create crisis.
## What to Do in the Moment
When your child is actively aggressive, your priority is safety, not teaching. They cannot learn in this state. Their prefrontal cortex, the part of the brain responsible for reasoning, language, and self-control, is offline. You are dealing with a brainstem response, and your job is to bring the intensity down, not to lecture, reason, or consequence.
### Keep Everyone Safe
Move other children out of the room. Remove objects that could cause harm. If your child is hitting you, create physical distance if you can do so safely. Position yourself to the side rather than directly in front, which feels less confrontational to an escalated nervous system.
**Do not physically restrain your child unless there is immediate risk of serious injury.** Physical restraint during a meltdown often escalates the crisis rather than resolving it. Research on restraint in autism shows that it can cause physical harm, psychological trauma, and an increase in the very behaviors it aims to stop. A child who is already in fight mode will fight harder when held down. Their nervous system interprets restraint as a threat, and the aggression intensifies.
If you must intervene physically to prevent serious injury, use the least restrictive approach possible. Block rather than grab. Redirect rather than pin. And as soon as the immediate danger passes, create space.
### Reduce Sensory Input
Stop talking. Lower the lights if possible. Turn off background noise. Remove other people from the room. Every piece of sensory input you can eliminate reduces the load on your child's overwhelmed nervous system.
This is counterintuitive. Your instinct is to explain, comfort, redirect, or lecture. But words are sensory input too. During a meltdown, every sentence you say is another thing their brain has to process while it is already overloaded. Quiet presence is more powerful than any words.
### Wait It Out Safely
Meltdowns have a physiological arc. The stress hormones flooding your child's body will peak and then gradually come down. You cannot speed this up. You can only avoid making it worse.
Stay nearby so your child knows they are not abandoned. Keep your own breathing slow and deliberate. Your regulated nervous system is the most powerful de-escalation tool you have, because children co-regulate off the adults around them. If you are escalated, they will escalate further.
If it is safe to do so, offer a [comfort item](/blog/comfort-items-transitions-neurodivergent-children), a weighted blanket, a favorite stuffed animal, or a chewy sensory tool. Do not force it. Just place it within reach.
### After the Storm
Once the meltdown is over, your child will likely be exhausted, disoriented, or emotionally fragile. This is not the moment for a conversation about their behavior. Their brain is still recovering.
Reconnect first. A hug if they want one. A glass of water. Sitting together quietly. The teaching moment comes later, maybe an hour later, maybe the next day, when their brain is back online and they can actually process what you say.
## Proactive Strategies That Actually Reduce Aggression
The in-the-moment responses above are damage control. The real work happens between episodes, when you build an environment that makes aggression less likely in the first place. Research on antecedent-based interventions shows they successfully decrease challenging behaviors in approximately **67.5 percent** of cases. Prevention is always more effective than reaction.
### Identify and Modify Triggers
Start tracking when aggression happens. Not just what happened immediately before, but the full context: What time of day? How much sleep did they get? What happened at school? Were they hungry? Was the environment loud, crowded, or visually overwhelming? Were demands being placed on them?
Patterns will emerge. Maybe aggression clusters after school when sensory reserves are depleted. Maybe it spikes on mornings when the routine changes. Maybe it always happens during a specific demand like getting dressed or transitioning away from a preferred activity.
Once you know the triggers, you can modify them:
- **Transition warnings.** Use a [visual timer](/blog/visual-timers-time-management-neurodivergent-children) to signal upcoming changes. "Five minutes, then we put the tablet away" with a visual countdown gives the brain time to prepare instead of being ambushed by a demand.
- **Choice-making.** "Do you want to brush teeth first or put on pajamas first?" gives your child a sense of control within necessary routines. When children feel they have some agency, aggression around demands decreases.
- **Demand fading.** If homework consistently triggers aggression, reduce the demand temporarily. Two problems instead of ten. Then gradually increase as tolerance builds. This is not giving in. It is meeting your child where they are and building capacity.
- **Environmental modification.** Reduce [sensory triggers](/blog/recognizing-triggers-meltdowns-neurodivergent-children) proactively. Noise-canceling headphones in loud spaces. Dimmer lighting during homework. A quiet corner designated as a regulation space.
### Teach Replacement Behaviors
This is the single most evidence-based approach to reducing aggression: **Functional Communication Training (FCT)**, developed by researchers Carr and Durand in 1985. The concept is straightforward. If aggression serves a communication function, teach your child a different way to communicate that same message.
If your child hits to escape demands, teach them to hand you a "break" card or say "break please." If they bite when overwhelmed by sensory input, teach them to go to a designated calm-down spot or request headphones. If they throw things when they need attention, teach them to tap your shoulder or use a signal.
The research on FCT is extensive. Over 215 studies demonstrate its effectiveness, with reductions in aggressive behavior often exceeding 90 percent. A randomized controlled trial found a **98 percent reduction** in problem behavior compared to no improvement in a control group. Effects are maintained 18 to 24 months after intervention.
For FCT to work:
- **The replacement must be easier than hitting.** If the alternative requires more effort than the aggression, your child will not use it.
- **The replacement must work every time at first.** When your child uses the break card, honor it immediately. Consistency teaches them the new behavior is reliable.
- **The aggression must stop working.** If hitting still gets the demand removed AND the break card also works, there is no incentive to switch. This part requires professional guidance, because doing it incorrectly can temporarily escalate behavior.
For children with limited verbal language, the [Picture Exchange Communication System (PECS)](/blog/choice-boards-empowering-decisions) offers a structured way to build functional communication. Research shows that as children learn PECS, challenging behaviors often decline by 60 percent or more.
### Build Sensory Regulation Into the Day
Do not wait for your child to become dysregulated. Build regulating activities into their daily routine proactively:
- **Proprioceptive input (heavy work).** Carrying groceries, pushing a laundry basket, wall push-ups, digging in sand, bear walks, jumping on a trampoline. These activities provide deep pressure to muscles and joints, which calms the nervous system. Think of it as charging a battery before it dies, rather than waiting for the crash.
- **Oral motor input.** Chewing crunchy foods (carrots, pretzels), using a chewy sensory tool, drinking thick smoothies through a straw. For children who bite, redirecting the oral sensory need to appropriate outlets can significantly reduce biting incidents.
- **Deep pressure.** Weighted blankets during calm activities, compression clothing, firm (consensual) hugs, rolling in a blanket. Research on deep pressure therapy shows it decreases sympathetic arousal, the fight-or-flight response that drives aggression.
- **Movement breaks.** Scheduled breaks for swinging, climbing, running, or jumping throughout the day prevent the sensory buildup that leads to meltdowns. Do not wait for your child to ask. Build these into the [visual schedule](/blog/visual-schedules-for-autism).
An occupational therapist can assess your child's specific sensory profile and recommend strategies tailored to their needs. What works for one child may overstimulate another.
### Use Visual Supports for Emotion Recognition
Many autistic children struggle with interoception, the ability to recognize what is happening inside their own body. They may not notice rising frustration, increasing sensory discomfort, or physical needs like hunger and thirst until those signals become overwhelming. By then, the meltdown is already in motion.
Visual tools like the **Incredible 5-Point Scale** help children learn to identify early warning signs. The scale uses numbers from 1 (calm) to 5 (crisis) with concrete descriptions of what each level looks and feels like in the body: "My hands are relaxed" versus "My hands are in fists." With practice, children can learn to recognize they are at a level 3 and use a coping strategy before reaching level 5.
[Emotion tracking](/blog/tracking-emotions-activities-neurodivergent-children) also helps parents identify patterns. You might discover that your child is consistently at level 4 by 3 PM, which tells you the after-school transition needs more built-in regulation support.

## What About Deep Pressure Holds?
You may have heard about "therapeutic holds" or deep pressure techniques used during meltdowns. This is a nuanced topic that requires careful distinction.
**Deep pressure as a calming strategy** (weighted blankets, compression vests, firm hugs that the child requests) is different from **physical restraint** (holding a child down or immobilizing them against their will during a behavioral crisis). Research from Temple Grandin's work on deep pressure, including her squeeze machine studies, shows that self-initiated or consensually applied deep pressure can reduce anxiety and calm the nervous system.
However, applying physical pressure to a child who is actively fighting you is restraint, not therapy. The distinction matters:
- **Therapeutic deep pressure** is offered, chosen, and controlled by the child. They can get out whenever they want.
- **Restraint** is imposed on a child who is actively resisting. They cannot get out.
If your child seeks deep pressure during distress, providing it through a weighted blanket, a body sock, or a firm hug they lean into is appropriate. If your child is fighting against being held, you are restraining, not regulating, and you should stop.
Some behavior plans may include approved physical management procedures for children with severe aggression or self-injury. These should **only** be implemented under the direct guidance of a Board Certified Behavior Analyst and with written protocols. They should be a last resort within a comprehensive positive behavior support plan, not a go-to response.
## When to Get Professional Help
Some aggression is a normal part of early childhood, even in neurodivergent development. But there are signs that your family needs professional support:
- **Frequency is increasing.** If aggressive episodes are happening daily or multiple times per day.
- **Intensity is escalating.** The hitting is harder. The biting breaks skin. Objects are being thrown with force.
- **Someone is getting hurt.** You, your child, siblings, or peers are being injured.
- **Your strategies are not working.** You have tried modifying the environment, teaching replacement behaviors, and providing sensory support, and the aggression is not improving.
- **Self-injury is present.** Head-banging, hand-biting, skin-picking, or any self-harming behavior requires professional assessment.
- **Your family is in crisis.** Siblings are afraid. You are afraid. The aggression is affecting your mental health, your marriage, or your ability to function.
### Who to Call
**A Board Certified Behavior Analyst (BCBA)** should be your first call for persistent aggression. A BCBA will conduct a Functional Behavior Assessment to determine exactly why your child's aggression is occurring, then develop a Behavior Intervention Plan with proactive, function-based strategies. Ensure the BCBA uses positive approaches. If the plan relies primarily on punishment or restraint, seek a different provider.
**An Occupational Therapist** can assess whether sensory processing differences are contributing to aggression and create a sensory strategy plan tailored to your child.
**A Speech-Language Pathologist** can evaluate whether communication limitations are driving the behavior and implement augmentative communication supports.
**Your pediatrician** should rule out medical causes. Pain, gastrointestinal discomfort, ear infections, dental problems, and sleep deprivation can all present as increased aggression in children who cannot verbally report pain.
If your child is in immediate danger of harming themselves or others and you cannot safely manage the situation, call 988 (Suicide and Crisis Lifeline) or your local crisis services. You are not failing by asking for emergency help. You are keeping your family safe.
## What to Tell Siblings
If your child's aggression affects siblings, those siblings need support too. Be honest in age-appropriate ways: "Your brother's brain works differently, and sometimes his body does things he does not mean to do when he is overwhelmed. It is never okay for anyone to hurt you, and it is our job as parents to keep you safe."
Create a safety plan with siblings: where to go when their brother or sister is having a crisis (a specific room, a neighbor's house), how to get a parent's attention without escalating the situation, and a clear message that it is not their job to manage the behavior.
Watch for signs that siblings are struggling: anxiety, behavioral changes, reluctance to be around the aggressive child, or expressing fear. Consider [family therapy](/blog/sibling-relationships-neurodivergent-families) that addresses the impact on all family members, not just the child with the diagnosis.
## Taking Care of Yourself
You cannot regulate your child's nervous system if your own is chronically dysregulated. [Caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children) is not a personality flaw. It is the predictable result of living in a sustained state of hypervigilance, never knowing when the next violent episode will happen.
If you are flinching when your child moves suddenly, if you are dreading the sound of their footsteps, if you have bruises you are hiding, you deserve support. Not judgment. Not "have you tried a sticker chart?" Not "all kids go through phases." Real, professional support from people who understand the specific demands of parenting an aggressive autistic child.
Find a therapist who specializes in caregiver support. Join a parent support group where you can speak honestly without fear of judgment. And give yourself permission to grieve the parenting experience you expected while showing up for the one you have.
## Building a Calmer Home, One Step at a Time
Reducing aggression is not a single intervention. It is a layered approach: understanding the function, modifying triggers, teaching replacement skills, building sensory regulation into the day, and knowing when to call for help. No strategy works in isolation, and no strategy works immediately. You are building a new neurological pathway for your child, and that takes time, consistency, and a whole lot of patience with both your child and yourself.
Start with one thing. Track when the aggression happens for one week. Identify the most common trigger. Address that trigger first. Teach one replacement behavior. Build one sensory break into the daily routine. Then add the next layer.
Your child is not their aggression. Underneath the hitting, biting, and throwing is a child whose nervous system is overwhelmed and whose communication tools are not yet sufficient for what they need to express. Your job is to help them build those tools, one at a time, while keeping everyone safe in the process.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) that reduce the demand-related triggers behind most aggression, create [emotion regulation sequences](/blog/emotional-regulation-visual-supports) your child can follow when they feel escalation building, schedule sensory breaks throughout the day so dysregulation does not accumulate, and track [behavioral patterns](/blog/tracking-emotions-activities-neurodivergent-children) to identify triggers you might otherwise miss. Just $6.99/month after your trial, no credit card required upfront.
---
## Working While Raising a Neurodivergent Child: What Nobody Prepares You For
Published: 2026-03-11
URL: https://vizyplan.com/blog/working-parent-neurodivergent-child
Category: Strategies
Author: Justin Bowman
> 55% of parents of autistic children have reduced their hours or quit a job. Here is what working parents of neurodivergent kids actually face and the strategies that help.
Your phone buzzes during a meeting. It is the school. Again.
You excuse yourself, step into the hallway, and answer with the calm voice you have perfected over the years, the one that hides the fact that your heart just dropped into your stomach. Your child had a meltdown. Or bit someone. Or ran out of the classroom. Or is refusing to come back from the bathroom. They need you to come pick them up.
You hang up, walk back into the meeting, and pretend everything is fine while you quietly reorganize your entire afternoon. Cancel the 2 PM call. Message your partner. Text the babysitter. Email the teacher. Apologize to your boss. Again.
If you are a working parent raising a neurodivergent child, you live in two worlds simultaneously. In one, you are a professional trying to keep a career on track. In the other, you are the primary coordinator of a complex web of therapies, school accommodations, behavioral strategies, and medical appointments that would challenge a full-time project manager.
Nobody warned you that parenting a child with autism or ADHD would become a second job. The research confirms what you already know in your bones: you are not imagining how hard this is.
## The Numbers Behind the Struggle
A study by SPARK, the largest autism research study in the United States, found that 55% of parents with an autistic child have either reduced their work hours or quit a job entirely. More than half. That is not a fringe experience. It is the majority.
The financial data is equally stark. Research published in the journal Pediatrics found that mothers of children with autism earn 35% less than mothers of children with other health conditions and 56% less than mothers of children without health limitations. They are 6% less likely to be employed at all and work an average of seven fewer hours per week.
Here is the part that should make every policymaker pay attention: lost employment income accounts for approximately 90% of total family costs associated with autism. Not therapy bills. Not special education costs. Lost wages. The money families never earned because someone had to step back from their career to manage their child's needs.
And that someone is disproportionately the mother. Even in dual-income households, research consistently shows that mothers absorb the career impact. They are the ones who get called first by the school. They are the ones who rearrange their schedules for therapy appointments. They are the ones whose careers stall while their partners' advance.
This is not a parenting problem. It is a structural failure.
## The Phone Call You Are Always Waiting For
Working parents of neurotypical children worry about their kids, too. But there is a specific kind of vigilance that comes with having a neurodivergent child in a system that was not built for them.
You never fully relax at work because part of your brain is always monitoring. Is today going to be a good day at school? Did the substitute teacher read the [IEP](/blog/504-plan-vs-iep-neurodivergent-child)? Did someone change the routine without telling your child? Is the fire drill going to happen today?
A 2024 study published in Disability and Society interviewed 19 families of autistic children and found that school-related challenges directly and significantly impact parental employment. Parents described becoming intensely involved in their child's school life, monitoring progress, advocating for accommodations, attending meetings, and managing crises, all of which compete directly with work obligations.
The study documented a pattern that will feel familiar: school calls about behavior, requests to pick up early, meetings that can only happen during work hours, and the slow erosion of an employer's patience. Several parents described a cycle of school instability leading to employment instability leading to financial instability.
The worst part is the unpredictability. You can prepare for a scheduled IEP meeting. You cannot prepare for the call at 10:30 AM that your child is under a table and will not come out. That kind of unpredictability makes it nearly impossible to commit to the kind of consistent, interruption-free workday that most employers expect.
## Therapy Logistics Are a Second Job
Your child sees an occupational therapist on Tuesdays at 3:15. Speech therapy is Thursday mornings. The behavioral therapist can only do Wednesdays at 4, but that conflicts with the social skills group that meets every other Wednesday. The psychiatrist has a six-month wait, and when you finally get an appointment, it is at 11 AM on a Tuesday.
None of this happens during convenient hours. And none of it coordinates itself.
Research from PMC found that children with autism require intensive healthcare and education services from multiple providers, which demands significant transportation time and general oversight from caregivers. Private insurance frequently limits or does not cover autism-specific therapies, adding financial stress on top of the logistical burden.
For working parents, every appointment represents a negotiation. Can you shift your lunch break? Can your partner leave early? Can the grandparent drive this time? Can you do a telehealth session instead? The mental load of coordinating care across multiple providers, school systems, and insurance companies is exhausting, and it is almost entirely invisible to employers and coworkers.
The cost compounds. Research shows that the elevated expense of raising a child with autism means families need stable income more than ever, but the demands of caregiving make maintaining that income exponentially harder. It is a catch-22 that millions of families navigate every single day.
## The Guilt That Comes From Both Directions
If you are a [stay-at-home parent](/blog/stay-at-home-mom-autistic-child), you may feel guilty about losing your career and identity. If you are a working parent, the guilt hits from both sides.
At work, you feel guilty for being distracted. For leaving early. For the apologetic emails. For the projects you cannot take on because they require travel or evening hours you do not have. For the promotion you did not pursue because you knew the additional responsibilities would break the already fragile balance.
At home, you feel guilty for not being there. For missing the meltdown you could have prevented if you had done pickup instead of your partner. For not being the one to take them to therapy. For being too exhausted at the end of the day to do the sensory play or practice the social skills the therapist recommended. For the screen time that fills the gaps your absence creates.
Research from the Children's Health Council confirms that feeling inadequate, ashamed, and guilty is common among parents of neurodivergent children, and that self-compassion, not trying to do more, is the research-backed antidote. But knowing that does not make it easier when your child cries at drop-off or when your boss asks if you can "be more reliable" with your schedule.
The guilt is compounded by comparison. You see other working parents who seem to manage it all. Their kids go to after-school programs. Their mornings run smoothly. They volunteer for the PTA and make it to every soccer game. What you do not see is that their children are not [melting down after school](/blog/after-school-routine-transitions-neurodivergent-children) from sensory overload. Their mornings do not involve a [45-minute visual routine](/blog/morning-routine-tips-adhd) just to get out the door. The comparison is not fair, but your brain makes it anyway.
## What Your Coworkers and Boss Do Not Understand
You have probably heard some version of these: "All kids have meltdowns." "My nephew has ADHD and he is fine." "Can't you just get a babysitter?" "You seem really distracted lately."
Most people have no frame of reference for what raising a neurodivergent child actually requires. They do not understand that your child cannot go to a standard after-school program because the environment causes [sensory overload](/blog/sensory-processing-daily-routines). They do not know that finding a babysitter who can handle your child's specific needs is nearly impossible and costs twice the standard rate. They have never attended a three-hour IEP meeting where you had to fight for basic accommodations.
A 2024 scoping review by Gore and colleagues published in Autism in Adulthood examined the mental health of autistic working parents and found that the intersection of work demands and caregiving demands creates unique stressors that are rarely acknowledged in workplace policies or culture. Working parents of neurodivergent children experience higher levels of depression, anxiety, and exhaustion compared to other working parents.
You do not need your coworkers to fully understand. But you do need systems in place that do not require their understanding to function.
## Building Systems That Work When You Cannot Be There
Here is where the practical advice begins. The research is clear: what helps working parents of neurodivergent children is not motivational quotes or productivity hacks. It is systems. Specifically, systems that reduce the number of daily decisions, create predictability for your child, and distribute the caregiving load so it does not rest entirely on one person.
### Create Visual Routines That Run Without You
The single most impactful thing you can do as a working parent is build routines your child can follow even when you are not the one guiding them. If your child relies on you to prompt every step of the [morning routine](/blog/morning-routine-tips-adhd), the [after-school transition](/blog/after-school-routine-transitions-neurodivergent-children), or the [bedtime sequence](/blog/bedtime-routine-autism-adhd), then anyone else stepping in is going to struggle.
[Visual schedules](/blog/visual-schedules-for-autism) solve this. When the routine is externalized, posted on a tablet or printed on the wall, any caregiver can follow it. The babysitter knows what comes after dinner. The grandparent knows the exact bedtime sequence. Your partner knows which steps cannot be skipped without consequences.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) is built for exactly this situation. You create the routine once, with [AI-generated images personalized to your child](/blog/ai-generated-images-visual-supports), and every caregiver in your child's life can access it. The routine stays consistent whether you are home or in a meeting across town. No guessing. No improvising. No late-night text threads explaining the steps that were missed.
### Build a Care Team Document
Every person who interacts with your child in your absence needs critical information. Create a single, shared document that includes:
- Your child's daily schedule with visual routine links
- [Sensory triggers](/blog/recognizing-triggers-meltdowns-neurodivergent-children) and what to do about them
- [Calming strategies](/blog/happy-place-mindfulness-neurodivergent-children) that actually work for your child
- Food preferences and restrictions
- Medication schedule and instructions
- Emergency contacts and what constitutes an emergency versus a manageable moment
- What to say (and not say) during a [meltdown](/blog/emotional-regulation-visual-supports)
This document saves time, reduces calls to you during work, and ensures consistency. Update it monthly as your child's needs change.
### Negotiate Flexibility, Not Permission
Research consistently shows that flexible employment is the single most protective factor for working parents of neurodivergent children. If you have not had a direct conversation with your employer about flexibility, consider doing so.
You are not asking for special treatment. You are proposing an arrangement that allows you to do your best work. Frame it in terms of output, not hours. "I am most productive when I can shift my schedule to accommodate occasional midday appointments. I will make up the time and meet all deadlines."
If your employer offers an Employee Assistance Program, use it. If they have a caregiver resource group, join it. If neither exists, you may be the person who starts the conversation.
### Coordinate With Your Partner (if Applicable)
In dual-parent households, the caregiving load often defaults to one person. Research shows this is usually the mother. If that imbalance exists in your family, it is worth addressing directly.
Create a shared calendar for all therapy appointments, school events, and medical visits. Alternate who handles the school pickup calls. Divide the administrative tasks: one parent manages insurance and billing, the other handles school communication. Make the invisible labor visible so it can be divided fairly.
### Use Transition Rituals for Yourself
Your child is not the only one who struggles with [transitions](/blog/staying-regulated-during-transitions). The shift from work mode to parent mode is jarring, especially when you walk through the door and immediately face a child in crisis.
Build a brief transition ritual for yourself. Five minutes in the car before walking in. A specific song. A breathing exercise. Changing your clothes. Something that signals to your nervous system: different mode now. This is not self-indulgence. It is self-regulation. And you need it because your child needs you regulated, not depleted, the moment you walk through the door.
### Accept That Good Enough Is Good Enough
Perfectionism and neurodivergent parenting cannot coexist. You will miss therapy sessions. You will forget to send the [visual schedule](/blog/visual-schedules-for-autism) update to the babysitter. You will have weeks where screen time is the only thing keeping the peace after school. You will turn down the work trip that would have been good for your career because the timing is impossible.
[Caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children) happens when you try to be everything to everyone. The research is clear: self-compassion is more effective than self-improvement for parents in demanding caregiving roles. You are not falling short. You are navigating an impossible set of competing demands with more grace than you give yourself credit for.
## What Actually Helps: A Quick Reference
**At work:**
- Negotiate flexible hours or remote work for appointment days
- Block "buffer time" on your calendar for unexpected school calls
- Keep a go-bag at your desk (car keys, insurance cards, your child's comfort item)
- Find one trusted colleague you can be honest with about your situation
- Set clear boundaries: you are available, not always available
**At home:**
- Build [visual routines](/blog/visual-schedules-for-autism) any caregiver can follow
- Prep the next day's logistics the night before (bags packed, clothes laid out, visual schedule reviewed)
- Use [emotion tracking](/blog/tracking-emotions-activities-neurodivergent-children) to spot patterns that predict hard days
- Create a "handoff sheet" that any caregiver can read in two minutes
- Protect ten minutes of wind-down time between walking in the door and engaging with caregiving
**For your sanity:**
- Connect with other working parents of neurodivergent children (online support groups count)
- Stop comparing your family to families with neurotypical children
- Let go of the activities and obligations that drain you without benefiting your child
- Get your own support, whether therapy, coaching, or a trusted friend who actually gets it
## You Are Not Doing This Wrong
There is a specific kind of loneliness that comes with being a working parent of a neurodivergent child. You do not fit neatly into either world. At work, you are the parent who always has to leave. At the parent support group, you are the one who cannot attend because it is during business hours. At school pickup, you are the one who is never there.
You are not doing this wrong. You are doing something extraordinarily hard with a set of constraints that most people will never understand. The fact that your child is fed, loved, in therapy, and supported at school while you are also earning a living and holding your family together financially is not nothing. It is everything.
Your child does not need a parent who is present every second. They need a parent who builds systems that work, who advocates fiercely, who shows up regulated and connected in the time they have. That is enough. You are enough.
And if today was a hard day, the kind where you answered the school call in the bathroom, or cried in the car at pickup, or felt like you are failing at both work and parenting simultaneously, know this: tomorrow the [visual schedule](/blog/visual-schedules-for-autism) will still be there. The routine will still hold. The systems you built will keep running even when you feel like you cannot.
That is the whole point. You built something that does not depend on you being perfect. And that is the most powerful thing a working parent can do.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build [visual routines](/blog/visual-schedules-for-autism) any caregiver can follow when you are not there, share schedules with babysitters, partners, and grandparents so handoffs are seamless, track [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) to predict and prevent hard days, and coordinate with your child's [therapists and teachers](/blog/provider-collaboration-iep-preparation) from one shared space. Just $6.99/month after your trial, no credit card required upfront.
---
## How to Tell Your Child About Their Autism or ADHD Diagnosis
Published: 2026-03-10
URL: https://vizyplan.com/blog/telling-child-about-autism-adhd-diagnosis
Category: Strategies
Author: Justin Bowman
> Research shows children told about their diagnosis early develop stronger self-identity and better mental health. Here is how to have the conversation at every age.
Your child just received a diagnosis. Maybe it is autism. Maybe it is ADHD. Maybe it is both. The clinician handed you a report, answered your questions, and sent you home with a list of resources. But nobody told you how to tell your child.
Now you are lying awake at night running through scenarios. What if they get upset? What if they think something is wrong with them? What if they are too young to understand? What if telling them makes things worse?
Here is what the research actually says: telling your child about their diagnosis does not make things worse. Not telling them does.
A 2023 participatory study published in the journal Autism found that autistic individuals who learned about their diagnosis at a younger age reported higher quality of life and greater wellbeing in adulthood. A separate study in the Journal of Child Psychology and Psychiatry found that late-diagnosed autistic children showed significantly more mental health and social difficulties across childhood and adolescence compared to those diagnosed and told earlier.
The question is not whether to tell your child. It is how.
## Why Disclosure Matters More Than You Think
The instinct to protect your child from a label is understandable. You worry about stigma. You worry about them limiting themselves. You worry about the weight of a word they might not be ready to carry.
But consider what happens when you do not tell them.
Your child already knows they are different. They notice that transitions are harder for them than for their siblings. They see that making friends does not come as easily. They feel the gap between what teachers expect and what their brain can deliver, and without an explanation, they fill that gap with the only conclusion that makes sense to them: something is wrong with me.
Research published in The Lancet's eClinicalMedicine in 2024 found that one in four autistic adults, and one in three autistic women, reported at least one psychiatric diagnosis obtained before their autism diagnosis that was later perceived as a misdiagnosis. Years of anxiety, depression, and identity confusion rooted in not understanding how their brain actually works.
A meta-analysis published in 2024 in ScienceDirect confirmed that children with ADHD experience moderate impairments in global, academic, and social self-esteem compared to peers without the condition. Children who do not have a framework for understanding why they struggle are more likely to blame themselves, internalizing difficulties as character flaws rather than neurological differences.
The diagnosis gives your child something powerful: an explanation that is not their fault.
## When Is the Right Time?
There is no single perfect moment. But research and clinical experts consistently agree: earlier is better than later.
The University of Washington Autism Center recommends telling your child about their autism diagnosis in words they can understand as soon as the diagnosis is made. The Child Mind Institute echoes this guidance, emphasizing that disclosure should be a series of ongoing conversations rather than a single event.
That does not mean sitting your three-year-old down for a formal discussion about neurodevelopmental conditions. It means beginning to lay the groundwork, in age-appropriate language, from the moment you know.
Think of it like teaching your child about any other aspect of who they are. You do not wait until they are twelve to tell them they have brown eyes. You do not schedule a family meeting to explain that they are left-handed. Their neurodivergence is part of who they are, and integrating that understanding into everyday life, gradually and naturally, is far more effective than a single high-stakes conversation.
## Ages 2 to 5: Planting the Seeds
At this stage, your child does not need the word "autism" or "ADHD" explained in clinical terms. They need to understand their own experience in simple, concrete language.
**Start with what they already know about themselves.** "Your brain notices every sound in the room. That is why the fire alarm at school feels so scary for you. Some brains are extra good at hearing things." This is not a disclosure. It is a description. And it starts teaching your child that their experience is valid and explainable.
**Use characters they know.** Sesame Street's Julia is autistic. If your child watches the show, you can say, "Did you see how Julia needed some quiet time? You need quiet time sometimes too. Julia is autistic, just like you." This normalizes the word before it carries any weight.
**Talk about brains in general.** "Everyone's brain works a little differently. Some people's brains are really good at sitting still. Your brain likes to move. That is just how your brain works." At this age, you are not explaining a diagnosis. You are giving your child vocabulary for their inner experience.
**Keep it positive and matter-of-fact.** No dramatic setup. No serious sit-down talks. Just casual, everyday observations woven into normal life. During bath time, during a walk, during a quiet moment reading together. The goal is for your child to absorb the idea that their brain is different, not broken, as naturally as they absorb everything else.
**Books help enormously at this age.** Picture books about neurodiversity give children mirrors to see themselves in. When a character in a book experiences something your child relates to, it opens a door for conversation.
## Ages 6 to 10: Naming It
School-aged children are more aware. They notice differences. They compare themselves to peers. They hear words like "special needs" or "IEP" in the hallway. And they are asking questions, even if they are not asking them out loud.
This is the stage where the specific words "autism" and "ADHD" typically enter the conversation.
**Lead with strengths.** "You know how your brain can focus on dinosaurs for hours and remember every single fact? That is part of how your brain is wired. There is a word for the way your brain works. It is called autism. It means your brain processes the world differently than some other kids' brains."
**Be honest about the hard parts, too.** "Having ADHD means your brain is really good at creative thinking and noticing interesting things. It also means that sitting still in class and remembering all the steps of a task can be harder for you than it is for some of your classmates. That is not because you are not trying hard enough. It is because your brain works differently."
**Normalize it with numbers.** Children at this age understand scale. "About 1 in every 30 kids has autism. That means there are probably other kids at your school who have it too." Knowing they are not alone matters enormously.
**Explain what the diagnosis means practically.** "The reason you go to Ms. Sarah for occupational therapy is because she helps your brain get better at things that are tricky for you right now, like writing and tying your shoes. Your [IEP at school](/blog/504-plan-vs-iep-neurodivergent-child) is a plan that helps your teachers understand what you need to learn best."
**Address their questions directly.** A 2021 study by Riccio and colleagues published in the journal Autism found that autistic adolescents whose parents voluntarily and openly told them about their diagnosis described themselves and autism more positively. They included strengths in their definitions of autism and viewed it as a neutral difference rather than a disorder. Adolescents whose parents did not tell them, or who found out involuntarily, had more negative self-perceptions.
Your child will ask hard questions. "Why am I different?" "Will I always have this?" "Is something wrong with my brain?" Answer honestly. "Yes, you will always be autistic, and that is okay. It is part of who you are, like having brown eyes or being left-handed. It means some things are harder for you, and it also means some things are easier for you than they are for other people."
**Make it an ongoing conversation.** This is not a one-time talk. It is a thread that runs through your relationship. When your child [struggles with a transition](/blog/staying-regulated-during-transitions), you can say, "Transitions are really hard for your brain. Let us use your [visual schedule](/blog/visual-schedules-for-autism) to see what is coming next." When they succeed at something challenging, "You worked so hard on that, and your brain did it. That took real persistence."
## Ages 11 and Up: Deepening Understanding
Tweens and teenagers need more sophisticated conversations. They are forming their identity. They are acutely aware of social dynamics. And increasingly, they are encountering information about neurodivergence on social media, through friends, or through their own research.
**If your child already suspects or has self-identified.** Many teens today encounter ADHD and autism content on TikTok, Instagram, or YouTube and recognize themselves. If your child comes to you and says, "I think I might have ADHD," take it seriously. This is not a trend. Research from the Child Mind Institute notes that teens doing deep dives on neurodivergence online are often accurately identifying traits they recognize in themselves.
**Discuss the neuroscience.** Older children can handle more detailed explanations. "Your brain has differences in how it processes dopamine, which is a chemical that helps with motivation and attention. That is why things that are boring feel physically painful to you, but things you are interested in can hold your attention for hours. It is not a willpower problem. It is brain chemistry."
**Introduce them to the community.** One of the most significant findings from the research is that connecting with other autistic or ADHD individuals improves mental health outcomes. Let your teen know that there is a large community of neurodivergent people who share their experience, that many successful adults are autistic or have ADHD, and that their diagnosis does not define their ceiling.
**Talk about [self-advocacy](/blog/teaching-self-advocacy-skills-neurodivergent-child).** A teenager who understands their diagnosis can begin to advocate for themselves. "You have the right to ask your teacher for extra time on tests. You can explain to your friends why you need to leave the party early. You get to decide who you tell about your diagnosis and who you do not."
**Address stigma head-on.** Your teenager will encounter people who do not understand neurodivergence. Prepare them for this. "Some people have outdated ideas about what autism means. That is their lack of understanding, not a reflection of who you are. You get to define what your diagnosis means to you."
**Respect their process.** Some teens will be relieved. Some will be angry. Some will go through a period of denial. Some will immediately want to learn everything they can. All of these responses are valid. Research shows that an open and honest approach to disclosure contributes to the development of a coherent self-concept and supports the child in coping with the implications of the diagnosis, both personally and socially.
## What to Say (and What Not to Say)
Getting the words right matters. Here is a quick reference.
**Say this:**
- "Your brain works differently, and that is part of what makes you, you"
- "Autism/ADHD explains why some things are harder for you. It is not your fault"
- "You have strengths that come from how your brain is wired"
- "I am here, and we will figure things out together"
- "You can always ask me questions about this"
- "A lot of people have autism/ADHD, and they live great lives"
**Avoid this:**
- "You are autistic/ADHD" as an identity-defining label they did not choose (let them decide how to frame it)
- "There is something wrong with your brain" (it is different, not broken)
- "You will grow out of it" (they will not, and false hope creates confusion)
- "Do not tell anyone" (shame and secrecy do lasting damage)
- "Everyone is a little autistic/ADHD" (this minimizes their real experience)
- "You are special" without explaining what that means (vague and confusing for literal thinkers)
## How Visual Supports Can Help
For many neurodivergent children, especially those who are visual learners, the conversation about their diagnosis can be supported with visual tools.
**Social stories about diagnosis.** A social story that walks through "what autism means" or "what ADHD means" using pictures and simple language gives your child something to revisit on their own terms. They can read it when they are ready, come back to it with questions, and process the information at their own pace. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you create personalized [social stories](/blog/social-stories-autism-guide) with AI-generated images of your child, making the story feel personal rather than generic.
**[Emotion tracking](/blog/tracking-emotions-activities-neurodivergent-children) after disclosure.** After telling your child about their diagnosis, their emotions may shift over days and weeks. [VizyPlan's](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) emotion tracking helps you spot patterns. Are they more anxious on school days now? Are they processing well but need extra connection at bedtime? Data gives you insight that guesswork cannot.
**Visual routines that reinforce self-understanding.** When your child's daily [visual schedule](/blog/visual-schedules-for-autism) includes a [sensory break](/blog/sensory-processing-daily-routines), you can point to it and say, "This is here because your brain needs breaks to recharge. That is part of how you are wired, and it is a good thing." The schedule itself becomes a natural touchpoint for ongoing conversations about their neurodivergence.
## When Your Child Reacts Negatively
Not every child will respond with relief or curiosity. Some children get angry. Some cry. Some shut down. Some say, "I do not want to be different."
**Validate first.** "It makes sense that you feel upset. This is big news, and it is okay to have feelings about it." Do not rush to fix the emotion or reframe it as positive. Let them feel what they feel.
**Do not take it back.** The temptation to soften the disclosure or to backtrack is strong when your child is distressed. Resist it. Backing away from the truth teaches your child that their diagnosis is something to be ashamed of.
**Give them space and time.** Some children need hours or days or weeks to process. Do not force follow-up conversations. Let your child come to you. Make sure they know the door is open. "Whenever you want to talk about this, I am here."
**Watch for ongoing distress.** If your child's emotional response does not resolve, if they become more withdrawn, more [anxious](/blog/managing-anxiety-neurodivergent-children-visual-strategies), or express feelings of hopelessness, bring in professional support. A [therapist who specializes](/blog/finding-right-therapist-neurodivergent-child) in neurodivergent children can help them process the diagnosis in a safe space.
**Share your own feelings carefully.** Your child may ask, "Are you sad that I have autism?" Be honest but measured. "I was surprised when I first found out, and I wanted to make sure I could help you the best way possible. But I am not sad about who you are. I love exactly who you are."
## Telling Siblings, Family, and Friends
Disclosure is not just between you and your child. There is a wider circle to consider, including [extended family members who may not fully understand](/blog/extended-family-doesnt-understand-neurodivergent-child).
**[Siblings](/blog/sibling-relationships-neurodivergent-families) need age-appropriate explanations.** "Your brother's brain works differently than yours. That is why he gets upset about things that do not bother you, and why he needs more help with some things. It does not mean we love him more. It means he needs different support."
**Let your child decide who else knows.** As they get older, your child should have agency over who learns about their diagnosis. A teenager who does not want their classmates to know has that right. A child who wants to tell their best friend should be supported in doing so.
**Prepare for unhelpful responses.** Extended family may say things like "He does not look autistic" or "She just needs more discipline." You have already navigated this. Now your child might hear it too. Role-play responses with them. "When Grandma says something that does not feel right, you can say, 'My brain works differently, and that is okay.'"
## The Conversation That Never Ends
Telling your child about their diagnosis is not a single event. It is the beginning of an ongoing dialogue that evolves as your child grows.
At five, it sounds like, "Your brain likes to move."
At eight, it sounds like, "You have ADHD. That is why focus is hard sometimes and why you are so creative."
At twelve, it sounds like, "Here is how your brain processes dopamine differently, and here is what that means for school."
At sixteen, it sounds like, "You have the right to [advocate for yourself](/blog/teaching-self-advocacy-skills-neurodivergent-child). You get to decide what accommodations you need and who you tell about your diagnosis."
Each conversation builds on the last. Each one deepens your child's self-understanding. And each one sends the same message: there is nothing wrong with you, I see you, and I am here.
The fact that you are reading this, thinking about how to get this right, already tells your child everything they need to know about you. You are the kind of parent who prepares. Who researches. Who cares enough to find the words.
Your child is lucky to have you. And they deserve to know who they are.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Create personalized [social stories](/blog/social-stories-autism-guide) to help your child understand their diagnosis at their own pace, track [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) as they process the news, build [visual routines](/blog/visual-schedules-for-autism) that reinforce self-understanding every day, and share insights with [therapists and teachers](/blog/provider-collaboration-iep-preparation) so everyone supports your child consistently. Just $6.99/month after your trial, no credit card required upfront.
---
## Puberty and Your Neurodivergent Child: What Parents Actually Need to Know
Published: 2026-03-09
URL: https://vizyplan.com/blog/puberty-neurodivergent-children-autism-adhd-guide
Category: Strategies
Author: Justin Bowman
> Autistic children are nearly twice as likely to start puberty early. Learn how hormonal changes affect sensory processing, emotional regulation, and executive function, and how to prepare your child with visual supports.
Nobody warns you that puberty hits neurodivergent kids differently. You expect the growth spurts, the mood swings, maybe even the awkwardness. What you do not expect is your child melting down because their deodorant smells "wrong," or refusing to wear a bra because the sensation is unbearable, or becoming so overwhelmed by changes in their own body that they stop being able to follow routines they have used for years.
If you are the parent of an autistic or ADHD child approaching puberty, you are probably searching for answers that go beyond the standard "talk to your kids about their changing bodies" advice. Because the standard advice assumes a level of flexibility, social awareness, and sensory tolerance that your child may not have. And it assumes puberty will arrive on a typical timeline, which for many neurodivergent children, it does not.
This guide is what you actually need to know. The research, the practical strategies, and the things other parents wish someone had told them before puberty arrived.
## Puberty Often Arrives Early for Neurodivergent Children
Here is something most pediatricians do not mention at routine checkups: autistic children are significantly more likely to experience precocious puberty, meaning puberty that begins earlier than expected.
A large-scale study analyzing data from over 29,000 children found that autistic children have an adjusted hazard ratio of 1.80 for precocious puberty. That means they are nearly twice as likely to start puberty early compared to neurotypical peers. A separate cohort study of 22,208 children found an even higher hazard ratio of 6.48 in certain populations.
The timing differences are specific and measurable. Research shows that autistic girls tend to begin puberty approximately 9.5 months earlier than neurotypical girls, and autistic boys start roughly 7.5 months earlier. One study found that 58% of autistic females began puberty before age 11.
Why does this matter? Because early puberty means less time to prepare. It means hormonal changes are happening in a younger brain with less developed coping skills. And for children who already struggle with change, unexpected body changes arriving ahead of schedule can be deeply destabilizing.
If your child is autistic and between the ages of 7 and 9, it is worth having a conversation with their pediatrician about monitoring for early puberty signs. Knowing what to look for gives you more time to prepare, and preparation makes an enormous difference for neurodivergent kids.
## How Hormonal Changes Affect the Autistic Brain
Puberty is not just a physical process. It is a neurological event. The surge of gonadotropin-releasing hormone (GnRH), estrogen, and testosterone during puberty changes how the brain processes emotions, sensory input, and social information.
For neurotypical children, these shifts can cause typical teenage moodiness. For autistic children, the effects are amplified in ways that can feel like a regression.
**Sensory processing intensifies.** Many parents report that sensory sensitivities their child had managed for years suddenly become unmanageable during puberty. Textures that were tolerable become intolerable. Smells that went unnoticed become overwhelming. New body sensations (sweating, body odor, breast development, genital changes) add an entirely new category of [sensory input](/blog/sensory-processing-daily-routines) that the child has no experience managing.
**Emotional regulation becomes harder.** Hormonal fluctuations create mood swings in all adolescents, but research from the Lurie Center for Autism at Massachusetts General Hospital notes that these heightened emotional responses appear exaggerated in autistic children compared to their neurotypical peers. The consequences are more difficult to moderate because autistic children may have trouble understanding what is happening to them or why they feel so different.
**Anxiety increases.** For a child whose nervous system depends on predictability, puberty is the ultimate uninvited change. Their body is transforming without their permission. Their emotions are unpredictable. Their social landscape is shifting as peers develop romantic interests and more complex social dynamics. All of this [fuels anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) in children who may already have significant anxiety.
**Executive function takes a hit.** If your child has ADHD (or co-occurring autism and ADHD), puberty brings an additional challenge. Research published in Frontiers in Global Women's Health shows that estrogen directly influences dopamine activity. When estrogen levels are high, dopamine activity improves, supporting better attention and cognitive function. When estrogen drops (as it does cyclically after menstruation begins), dopamine activity decreases, and executive function suffers. For girls with ADHD, this creates a monthly cycle where their ability to focus, organize, and regulate their behavior fluctuates in ways that can be confusing for everyone.
## The ADHD and Puberty Connection
ADHD and puberty deserve their own conversation because the interaction between hormones and the ADHD brain is significant and often overlooked.
**Girls with ADHD are frequently diagnosed during puberty.** Many girls with ADHD fly under the radar during childhood because their symptoms present as inattention rather than hyperactivity. When puberty arrives and hormonal fluctuations amplify executive function challenges, symptoms that were manageable become disruptive enough to trigger evaluation. If your [daughter is showing new struggles](/blog/signs-autism-adhd-girls-underdiagnosis) with organization, focus, or emotional regulation during puberty, ADHD assessment is worth considering.
**The estrogen-dopamine cycle creates predictable patterns.** After a girl begins menstruating, her estrogen levels rise and fall each month. During the luteal phase (the two weeks before a period), estrogen drops significantly. For girls with ADHD, this drop corresponds with decreased dopamine activity, meaning worse attention, more impulsivity, greater emotional reactivity, and increased difficulty with tasks that require sustained mental effort. Some researchers describe this as "cyclical ADHD symptoms" because the severity of symptoms changes predictably with the menstrual cycle.
**Boys with ADHD face different hormonal challenges.** Testosterone increases during puberty can amplify impulsivity, risk-taking behavior, and emotional intensity. Boys who were managing their ADHD with existing strategies may find that those strategies stop working as their hormonal landscape changes.
**Medication effectiveness may shift.** Hormonal changes can affect how ADHD medications work. If your child's medication seems less effective during puberty, discuss this with their prescriber. Dosage adjustments or timing changes may be needed.
Understanding these patterns is empowering because it means the changes you are seeing are not random, they are not your child's fault, and they are not permanent. They are the predictable result of hormones interacting with a neurodivergent brain, and there are strategies that help.
## Preparing Your Child Before Puberty Begins
The single most important thing you can do is start preparing your child before physical changes begin. For neurodivergent children, surprises are the enemy. Knowledge is safety.
**Start early, ideally ages 8 to 10.** Given that many neurodivergent children experience early puberty onset, beginning conversations at age 8 is not premature. You are not trying to cover everything at once. You are planting seeds that will grow into understanding over time.
**Use real words, not euphemisms.** Autistic children in particular are literal thinkers. Calling a period "your monthly visitor" or breasts "chest development" creates confusion. Use the actual anatomical terms: penis, vagina, breasts, pubic hair, menstruation, erection, ejaculation. Clear language reduces anxiety because the child knows exactly what you are talking about.
**Create a [social story](/blog/social-stories-autism-guide) about puberty.** Social stories are one of the most effective tools for preparing autistic children for new experiences. A puberty social story should be personalized to your child's gender, body, and specific concerns. It should explain what will change, why it is happening, that it happens to everyone, and that the changes are normal and healthy. Social stories should be read repeatedly over weeks and months, not just once.
**Use visual supports.** Picture cards showing the stages of puberty (appropriate, simple illustrations) help children understand what to expect. A visual timeline showing when different changes typically happen gives their brain a framework for processing what is coming. Visual schedules for new hygiene routines (applying deodorant, shaving, managing periods) provide the step-by-step structure that neurodivergent children thrive with.
**Address their specific concerns.** Ask your child what they are worried about or curious about. Some children fixate on a single aspect of puberty (body hair, voice changes, acne) and need extra support understanding that one thing. Others are anxious about the social implications (locker rooms, body comparison, dating). Meeting your child where their anxiety actually lives is more effective than covering every topic equally.
**Build in repetition.** Neurotypical children may absorb puberty information from a single conversation supplemented by peer discussion and media. Neurodivergent children need more time, more repetition, and more concrete examples. Plan to revisit puberty topics regularly over months and years, not in one uncomfortable "talk."
## Managing New Hygiene Routines
Puberty introduces several new hygiene requirements that can be genuinely challenging for children with sensory sensitivities and executive function differences.
**Deodorant and body odor.** Your child may not notice their own body odor (interoception challenges) or may be overwhelmed by the smell of deodorant products. Finding the right product often takes trial and error. Unscented options work for some children. Others prefer a specific scent they have chosen themselves. The physical sensation of applying deodorant (wet roll-ons, sticky gels, dry powders) varies significantly between products, and sensory preference matters. Add deodorant application to their existing [morning visual routine](/blog/morning-routine-tips-adhd) so it becomes automatic rather than something they need to remember independently.
**Skin care and acne.** Hormonal acne is common during puberty and can be particularly distressing for children who are already self-conscious or who have tactile sensitivity on their face. A simple, consistent skin care routine with a gentle cleanser works better than a complex multi-step regimen. Make it visual: face wash, rinse, pat dry. Three steps. Posted by the bathroom sink.
**Shaving.** When body or facial hair becomes something your child wants to address, introduce shaving gradually. Electric razors are often better for sensory-sensitive children because they reduce the risk of cuts and the uncomfortable sensation of a blade on skin. Practice on less sensitive areas first. Create a visual guide for the process.
**Bra and undergarment changes.** For children who develop breasts, finding comfortable bras or alternatives can be a significant sensory challenge. Seamless, tagless sports bras or bralettes with soft fabric are often more tolerable than traditional bras. Some children prefer compression-style tops. Others refuse bras entirely, and that is okay for as long as it is comfortable for them. This connects directly to broader [clothing and sensory strategies](/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children) you may already use.
**Menstrual hygiene.** This deserves detailed attention because it is one of the most challenging puberty-related changes for autistic girls and nonbinary children who menstruate.
## Supporting Your Child Through Menstruation
Research published in a qualitative systematic review documented that menstruation has a significant negative impact on autistic individuals' daily lives. The sensory challenges are real and specific: the sensation of blood, the smell, the texture of pads and tampons, the physical discomfort of cramps, and the disruption to routines when periods arrive unpredictably.
**Introduce menstrual products before the first period.** Let your child see, touch, and practice with pads (applying them to underwear, removing and wrapping them for disposal) before they need to use one in a stressful moment. Familiarity reduces panic.
**Explore different product types based on sensory needs.** Pads, tampons, period underwear, and menstrual cups each have different sensory profiles. Pads may feel bulky and wet. Tampons require internal insertion that some children find intolerable. Period underwear eliminates the need for separate products and often feels most like regular underwear. Menstrual cups require comfort with insertion but eliminate the wet sensation. There is no single right answer. Let your child's sensory preferences guide the choice.
**Create a visual period routine.** Break the process into clear steps: go to bathroom, remove used pad, wrap in toilet paper, place in trash, clean up, apply new pad, wash hands. Post this sequence in the bathroom. Having the steps visible reduces cognitive load during a time when your child may be uncomfortable, in pain, or emotionally dysregulated.
**Help track the cycle.** Use a simple calendar or app to track periods so your child (and you) can anticipate when the next one is coming. Predictability reduces anxiety. Knowing that a period is likely to arrive within a certain window helps your child prepare mentally and practically (carrying supplies, wearing preferred clothing).
**Prepare a period kit.** A small pouch with pads or preferred products, a change of underwear, pain relief medication (if appropriate), and a comfort item gives your child everything they need in one place. Keep one at home, one in their school bag, and one anywhere they spend regular time.
**Establish a trusted contact at school.** Identify one person at school (a nurse, counselor, or teacher) your child feels comfortable approaching if their period starts unexpectedly. Practice the script: "I need to go to the bathroom. I started my period." Having the words ready removes a communication barrier during a stressful moment.
**Acknowledge the sensory reality.** A study on menstrual hygiene skills training for adolescents with autism found that structured training significantly improved hygiene skills. But the training worked best when it was paired with acknowledgment that the sensory experience is genuinely difficult. Saying "I know this feels uncomfortable and that is okay" validates your child's experience while still teaching the necessary skills.
## Emotional Regulation During Puberty
If your child already struggles with [emotional regulation](/blog/emotional-regulation-visual-supports), puberty is likely to make it harder before it gets better. Understanding why helps both you and your child.
**Name what is happening.** Autistic children often struggle to connect internal feelings with external causes. Saying "You might be feeling more irritable this week because your hormones are changing, and that is completely normal" gives them a framework for understanding their experience. Without this explanation, they may internalize the intensity as something wrong with them.
**Expand the feelings vocabulary.** Puberty introduces emotional nuances that your child may not have words for: embarrassment about their body, confusing feelings of attraction, jealousy, self-consciousness, loneliness in a crowd. [Tracking emotions](/blog/tracking-emotions-activities-neurodivergent-children) with more specific labels helps your child communicate what they are experiencing rather than expressing everything as anger or shutdown.
**Expect temporary regression.** It is common for neurodivergent children to lose skills during puberty that they had previously mastered. A child who was dressing independently may need support again. A child who managed transitions smoothly may start having meltdowns at transition points. This is not permanent. It is the brain reallocating resources to process massive hormonal and physical changes. Respond with patience and scaffolding, not punishment.
**Teach coping strategies proactively.** Cognitive behavioral therapy (CBT) approaches are particularly effective for managing the anxiety and mood swings that intensify during adolescence. Deep breathing exercises, sensory regulation tools (weighted blankets, noise-canceling headphones, fidgets), and designated calm-down spaces should be established before puberty hits peak intensity. A [mindfulness routine](/blog/happy-place-mindfulness-neurodivergent-children) practiced daily gives your child a tool they can reach for when emotions feel overwhelming.
**Monitor for mental health changes.** Puberty increases the risk of depression and anxiety in all adolescents, and neurodivergent children are already at higher baseline risk. If you notice persistent sadness, withdrawal from preferred activities, changes in sleep or appetite, or expressions of hopelessness, seek professional support promptly. These are not "just puberty" and deserve clinical attention.
## Navigating Social Changes
Puberty transforms the social landscape in ways that can leave neurodivergent children increasingly isolated from their peers.
**Peer interests shift rapidly.** Neurotypical pre-teens and teenagers become preoccupied with appearance, romantic relationships, social status, and increasingly complex social dynamics. Autistic children who already struggle to read social cues may find themselves even further from understanding what their peers are talking about or interested in.
**Body comparison becomes constant.** Locker rooms, PE classes, and social media expose children to body comparison that can be particularly distressing for those who are developing at a different pace or who have heightened sensitivity to perceived differences.
**The need for [self-advocacy](/blog/teaching-self-advocacy-skills-neurodivergent-child) increases.** As your child's body changes, they need to be able to communicate boundaries, ask for help with hygiene needs, and advocate for accommodations (privacy for changing, access to a bathroom during class for period management, sensory breaks when overwhelmed by body-related sensory input).
**Social stories can address specific scenarios.** Create stories about what to do when someone comments on your body, how to handle seeing peers change in the locker room, what "having a crush" means, and how to navigate conversations about dating when you are not interested or not ready.
## Teaching Consent and Body Autonomy
This is one of the most critical and most overlooked aspects of puberty education for neurodivergent children.
**Start with their own body autonomy.** Teach your child that their body belongs to them. No one has the right to touch them without permission. They do not have to hug, kiss, or allow physical contact from anyone, including family members, if they do not want to. This foundation protects them and builds a framework for understanding consent more broadly.
**Teach the difference between public and private.** Autistic children may not intuitively understand that certain body parts and behaviors are private. Explicit instruction about what is appropriate in public versus private spaces prevents social problems and keeps your child safe. Use visual supports that clearly categorize: bathroom activities are private, changing clothes is private, touching private body parts is private.
**Explain consent in concrete terms.** Abstract concepts like "enthusiastic consent" are difficult for literal thinkers. Instead, teach specific rules: always ask before touching someone, if someone says "no" or "stop," you stop immediately, if someone looks uncomfortable (teach what uncomfortable looks like), check in verbally, and your own "no" must always be respected by others.
**Address online safety.** Puberty often coincides with increased interest in social media and online communication. Neurodivergent children may be more vulnerable to manipulation because they tend to take statements at face value and may not recognize predatory patterns. Clear, specific rules about online interactions, taught with visual supports and social stories, provide protection.
## Supporting Your Child Through Puberty with Co-Occurring Conditions
Many neurodivergent children have [co-occurring autism and ADHD](/blog/autism-and-adhd-co-occurring-children), which means puberty affects them through multiple pathways simultaneously. The sensory amplification of autism combines with the executive function disruption of ADHD under hormonal influence, creating a particularly intense experience.
**Coordinate with all providers.** If your child sees a therapist, psychiatrist, and pediatrician, make sure each provider knows puberty has begun. Medication dosages may need adjustment. Therapy goals may need to shift to address body image, social changes, or emotional regulation. And the pediatrician should monitor physical development to identify any concerns early.
**Reassess accommodations at school.** An IEP or [504 plan](/blog/504-plan-vs-iep-neurodivergent-child) that worked in elementary school may need updating for the puberty-related challenges of middle school. Consider adding accommodations for: bathroom access (period management, hygiene needs), a private space for changing (PE), sensory breaks during high-stimulation days, and schedule flexibility during particularly difficult hormonal periods.
**Take care of yourself.** Supporting a neurodivergent child through puberty is exhausting. It activates your own memories of adolescence, adds new caregiving demands, and requires a level of explicit communication about bodies and emotions that many parents find uncomfortable. [Caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children) is real, and you cannot support your child effectively if you are depleted. Find your own support, whether that is a therapist, a support group for parents of neurodivergent children, or simply another parent who understands.
## What Your Child Needs to Hear
Through all the practical strategies, hygiene routines, and social skills instruction, your child needs to hear these things from you, repeatedly, in clear and simple language:
Your body is changing, and that is normal. Every body goes through this. The changes might feel strange or uncomfortable, and that is okay. You can always ask me questions, and I will give you honest answers. There is nothing wrong with your body. There is nothing wrong with you. I am here, and we will figure this out together.
Puberty is hard for every child. It is harder for neurodivergent children, not because there is something wrong with them, but because their brains process change, sensation, and social information differently. That difference is not a deficit. It is a reason to prepare more carefully, support more intentionally, and trust that your child can navigate this transition with the right tools and the right people beside them.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual hygiene routines for new puberty-related tasks like deodorant, skin care, and period management, create step-by-step sequences your child can follow [independently](/blog/building-independence-visual-supports), track [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) to identify hormonal cycles that affect your child's regulation, and share routines with schools and caregivers so everyone supports your child consistently. Just $6.99/month after your trial, no credit card required upfront.
---
## Elopement and Wandering in Autism: A Parent Safety Guide
Published: 2026-03-08
URL: https://vizyplan.com/blog/elopement-wandering-autism-prevention-safety
Category: Strategies
Author: Justin Bowman
> Nearly half of autistic children attempt to elope. Learn why wandering happens, how to prevent it, and what to do if your child goes missing.
You turned around for ten seconds. Maybe you were paying for groceries. Maybe you were answering a question from your other child. Maybe you were putting your shoes on by the front door. Ten seconds. And when you looked up, your child was gone.
Your heart hit the floor. Your body moved before your brain caught up. You searched the house, the yard, the street, calling their name in a voice that did not sound like yours. Maybe you found them in the neighbor's yard, fascinated by a sprinkler. Maybe a stranger brought them back from two blocks away. Maybe you called 911.
If you are the parent of an autistic child who wanders, you know a fear that most people will never understand. It is not hypothetical. It is not dramatic. It is the specific, recurring terror of knowing your child can and will leave a safe space without warning, without understanding danger, and often without the ability to tell anyone who they are or where they live.
You are not alone in this. And the research confirms that what you are experiencing is one of the most significant safety concerns in autism.
## The Numbers Every Parent Should Know
A landmark study published in Pediatrics by Anderson and colleagues surveyed families of children with autism spectrum disorder and found that 49% of children with ASD attempted to elope at least once after the age of four. That is nearly half. Among those children, 26% were missing long enough to cause serious concern.
The rate peaks between ages four and seven, when 46% of autistic children attempted to elope, a rate four times higher than their neurotypical siblings. But elopement does not disappear after early childhood. It continues through adolescence and, for some individuals, into adulthood.
The dangers are not abstract. Of children who went missing after eloping, 65% were in danger of traffic injury and 24% were in danger of drowning. Among families surveyed, 56% reported elopement as one of the most stressful behaviors they faced as caregivers, and 43% of parents reported sleep difficulties because of the fear that their child might bolt during the night.
These are not edge cases. This is the reality for roughly half of all families raising an autistic child.
## Why Autistic Children Elope
Elopement is not random. It almost always serves a function for the child, even when that function is invisible to the adults around them. Understanding why your child wanders is the single most important step in preventing it.
### Sensory Escape
A 2012 parent survey found that 36% of autistic children who elope do so to escape [sensory overload](/blog/sensory-processing-daily-routines). The grocery store is too loud. The classroom is too bright. The birthday party has too many people, too many sounds, too many smells happening simultaneously. The child does not have the language or the regulatory capacity to say "I need to leave." So their body does it for them. They run.
If your child consistently elopes from environments that are sensory-rich, noise, crowds, fluorescent lighting, strong smells, sensory escape is a likely function. The elopement is not defiance. It is survival.
### Sensory Seeking
On the opposite end of the same spectrum, some children wander toward sensory experiences they find irresistible. Water is the most dangerous of these. Children with autism are drawn to ponds, pools, lakes, and streams with alarming frequency. The visual shimmer, the sound, the feeling of water on skin can create an almost magnetic pull that overrides any awareness of danger.
Other sensory-seeking triggers include trains, highways (the visual pattern of moving cars), playground equipment, animals, and anything that produces a specific sensory input the child craves.
### Communication Barriers
Children with limited verbal communication are at higher risk for elopement. When a child cannot say "I want to go outside" or "I need a break" or "I am scared," their body communicates for them. Bolting becomes a form of expression. The child is not trying to be difficult. They are trying to meet a need they have no other way to articulate.
### Special Interests and Goal-Directed Wandering
Your child may not be running away from something. They may be running toward something. If your child has an intense interest in trains, they may walk toward the train tracks. If they love a specific park, they may navigate there with startling accuracy. If they are fascinated by construction equipment, a nearby building site becomes an irresistible destination.
This kind of elopement is particularly dangerous because it is purposeful and determined. The child is not disoriented. They know exactly where they want to go. They simply have no concept of the dangers between here and there.
### Routine Disruption and Anxiety
Changes to routine significantly increase elopement risk. A new teacher, a vacation, a different route to school, an unexpected visitor. When the predictable structure of the day breaks down, [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) spikes. For some children, that anxiety expresses itself as flight.
If you notice increased elopement attempts during periods of change or transition, anxiety-driven flight is likely at play.
## The Drowning Crisis
This section is difficult to read. It is also essential.
Drowning is the number one cause of accidental death for children with autism. Research published in the American Journal of Public Health found that autistic children are 160 times more likely to drown than neurotypical peers. That is not a typo. One hundred and sixty times.
A study analyzing drowning incidents involving children with ASD found that wandering was the preceding activity in 73.9% of cases. These drownings most commonly occurred in ponds, followed by rivers and lakes, typically during afternoon hours and in bodies of water near the child's home. The average age of victims was 7.7 years.
The data from Florida is particularly alarming. Since January 2021, 130 children with autism have drowned in the state. In 58% of all drownings in Florida involving children age five and older during that period, the child was autistic.
The National Autism Association reports that only 50% of families with autistic children have enrolled their children in formal swimming instruction. Specialized adaptive swimming lessons have been shown in multiple studies to significantly improve water competency. An Ohio State University pilot study found that adaptive swim classes not only improve survival skills but build competency that transfers beyond the water. A randomized controlled trial of the AquOTic program demonstrated significant improvements in water competency scores.
If your child is drawn to water and has not had swimming lessons, this is the single most important safety intervention you can make today. Look for adaptive or one-on-one instruction designed for children with autism, not standard group lessons.
## Building Your Elopement Prevention Plan
Prevention is layered. No single strategy is enough. The most effective approach combines understanding your child's triggers with environmental safeguards, communication supports, and community coordination.
### Step 1: Identify the Function
Before you can prevent elopement, you need to understand why it happens. Keep a log for two to four weeks. Every time your child elopes or attempts to elope, record:
- Where it happened (home, school, store, car)
- What was happening immediately before
- What time of day it was
- What the environment was like (loud, crowded, new, routine)
- Where your child went or tried to go
- What happened when you found them (were they calm, distressed, engaged in something)
Patterns will emerge. Maybe your child always bolts at the grocery store (sensory escape). Maybe they head for the creek behind the neighbor's house every time they are in the backyard (sensory seeking/water attraction). Maybe elopement spikes on days with schedule changes (anxiety). The function determines the intervention.
### Step 2: Secure Your Home
Your home is the most common location from which children with autism elope, accounting for 74% of incidents in the Anderson study.
**Door and window alarms.** These are your first line of defense. Battery-operated alarms that sound when a door or window opens cost under $15 and can be installed in minutes. Place them on every exterior door and any ground-floor window that can be opened.
**Deadbolts above reach.** A standard doorknob lock is not enough. Install deadbolts at the top of exterior doors, above your child's reach. Some families use keyed deadbolts that require a key to open from the inside. Keep keys accessible to adults for fire safety but out of the child's reach.
**Visual stop signs.** Place a large red "STOP" sign on interior side of exterior doors. This visual cue works for some children as a concrete reminder that this door requires permission. It will not stop every child, but for some, the visual boundary is meaningful.
**Fencing and pool barriers.** If you have a yard, fence it. If you have a pool, fence it separately with a self-closing, self-latching gate, even if the yard is already fenced. If you do not have a pool but your neighbor does, discuss the risk with them directly.
**Secure windows.** Window stops or locks that prevent windows from opening more than a few inches are essential for upper floors and any window a child might use as an exit.
### Step 3: Use Technology
GPS tracking devices designed for children with special needs have become significantly more effective in recent years.
**AngelSense** was designed specifically for children with autism. It is sensory-friendly, attaches to clothing with accessories the child cannot remove without help, offers real-time GPS tracking, two-way voice communication, an auto-answer feature, and geofence alerts when your child leaves a designated safe zone. It also has a one-way listen-in feature and an SOS button.
**Jiobit** is a small, discreet tracker with week-long battery life that works indoors and outdoors across 150+ countries. It provides geofence alerts and proximity detection using Bluetooth signal strength.
Families using GPS tracking technology have a 95% success rate in quickly locating children who have eloped, with average recovery times under 30 minutes. A GPS device does not prevent elopement, but it dramatically reduces the time between "my child is gone" and "I know where my child is." In elopement situations, minutes matter.
### Step 4: Build Communication Alternatives
If your child elopes because they cannot communicate a need, giving them another way to express that need can reduce the elopement itself.
Functional Communication Training, or FCT, is the most evidence-based intervention for elopement behavior. Over 215 single-case-design studies support its effectiveness, with reductions in problem behaviors, including elopement, often exceeding 90%. FCT works by identifying what the child is trying to get through elopement and teaching them a different way to get it.
If your child bolts to escape sensory overload, teach them to hand you a "break" card or press a button on a communication device. If they wander toward water because they want to play in it, teach them to request water play. If they run from transitions, use [visual schedules](/blog/visual-schedules-for-autism) and [first-then boards](/blog/first-then-boards-guide) so they can see what is coming and feel some control over the sequence.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) can support this by providing your child with a visual framework for their day. When children can see what comes next, the unpredictability that triggers elopement decreases. When [transitions are visible](/blog/transition-strategies-autism) and expected rather than sudden and surprising, the urge to flee diminishes.
### Step 5: Create a Visual Safety Routine
For children who can process visual information, create a "going outside" routine that includes safety steps:
- Stop at the door
- Find a grown-up
- Hold hands or stay close
- Look for cars
- Stay in the yard (or whatever boundary is appropriate)
Practice this routine daily during calm moments, not only when you are trying to prevent an incident. A study cited by the Autism Research Institute found that elopement attempts decreased by 72% when individualized behavior support plans addressed the specific function of the behavior. Consistency and practice are essential.
### Step 6: Coordinate With Your Community
**Inform your neighbors.** Let the people who live near you know that your child may wander, what they look like, and what to do if they see your child alone. Most neighbors will be grateful you told them and will become additional eyes.
**Contact local law enforcement.** Many police departments have voluntary registries for individuals who are prone to wandering. Registering your child means that if they go missing, responders already have their photo, physical description, communication abilities, places they are drawn to, and known triggers. This information can cut response time dramatically.
**File a safety plan with your child's school.** Schools are the third most common location for elopement (29% of incidents). Every school should have an individualized plan that includes assigned supervision roles, secured exit points, and protocols for what happens if the child leaves the building. If your child's school does not have this, request it in writing.
**ID bracelets and shoe tags.** Your child should always wear identification that includes their name, your phone number, and a note that they have autism and may not respond to verbal questions. Medical alert bracelets, shoe ID tags, and temporary tattoo IDs designed for children with special needs are all options.
## What to Do If Your Child Goes Missing
Despite every prevention measure, elopement can still happen. Having a response plan is just as important as having a prevention plan.
**First 30 seconds: Search water.** If there is any body of water nearby, check it first. Ponds, pools, creeks, drainage ditches, even large puddles or open containers of water. Given that drowning is the leading cause of death following elopement, water must be your first search area. Every time.
**Call 911 immediately.** Do not wait to see if your child comes back. Do not search for more than a few minutes before calling. Tell the dispatcher that your child has autism, may not respond to their name, and is attracted to [specific hazard]. If you have registered with your local police department, mention this.
**Deploy your network.** If you have informed your neighbors, this is when that preparation pays off. Text or call them. More eyes covering more ground in the first minutes is critical.
**Check their favorite spots.** If your child has a known attraction (a specific park, a creek, a neighbor's yard, a particular store), go there or send someone there immediately.
**Use your GPS tracker.** If your child is wearing a tracking device, check it the moment you realize they are gone. Share the location with anyone helping search.
## The Emotional Weight of Elopement
If you are reading this article, you already know the fear. You know the guilt that comes after every close call. You know the exhaustion of constant vigilance. You know what it feels like to be unable to look away, even for a moment, because ten seconds is all it takes.
Anderson's research found that 43% of parents whose autistic children wander reported sleep problems. Not because of nighttime wandering alone, but because of the pervasive, chronic anxiety that comes from knowing your child could be in danger at any moment.
If that describes you, this is important: the fear you carry is proportional to the risk. You are not being overprotective. You are not being paranoid. You are responding appropriately to a genuine safety threat that affects nearly half of all autistic children.
And there are things you can do. Every layer of prevention you add, the alarm on the door, the GPS on the shoe, the swimming lessons, the visual schedule that reduces the anxiety that triggers bolting, every layer reduces the risk. You may never eliminate it entirely. But you can build a safety net that holds.
Your child is not wandering to scare you. They are wandering because their brain is telling them to go, and they do not yet have the tools or the understanding to override that impulse. Building those tools, layer by layer, is how you keep them safe while honoring who they are.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual routines that reduce the unpredictability and anxiety that trigger elopement, create "going outside" safety sequences your child can follow, track [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) to identify when your child is most at risk, and share routines with caregivers and schools so everyone follows the same safety plan. Just $6.99/month after your trial, no credit card required upfront.
---
## When Your Child Has Both Autism and ADHD
Published: 2026-03-07
URL: https://vizyplan.com/blog/autism-and-adhd-co-occurring-children
Category: Strategies
Author: Justin Bowman
> Up to 70% of autistic children also have ADHD. Here is what the dual diagnosis means and how to support a child living with both.
Until 2013, your child could not exist. Not in any diagnostic manual, anyway.
Before the DSM-5 was published, the American Psychiatric Association explicitly prohibited diagnosing a child with both autism spectrum disorder and ADHD. Clinicians had to pick one. If your child showed signs of both, the official guidance was to choose the diagnosis that "better explained" the symptoms and move on.
Millions of children were only half-understood for decades. Their parents knew something did not add up. One diagnosis explained some of the behavior, but not all of it. The supports that worked for one set of symptoms seemed to make the other set worse. And nobody could tell them why.
The DSM-5 changed that. For the first time, a child could officially carry both diagnoses. And what the research has revealed since then has reshaped how we understand neurodivergence entirely.
## The Numbers Are Staggering
This is not a rare combination. According to the Child Mind Institute, between 50 and 70 percent of children diagnosed with autism also meet the criteria for ADHD. From the other direction, 20 to 50 percent of children with ADHD show traits consistent with autism.
A meta-analysis published in Research in Autism Spectrum Disorders found the pooled prevalence of ADHD in autistic children at 38.5% for current diagnosis and 40.2% for lifetime diagnosis. Twin and family studies have identified a genetic overlap between the two conditions of 50 to 72 percent.
The most recent CDC data (2025) reports autism prevalence at 1 in 31 children and ADHD prevalence at approximately 1 in 9. When you overlay those numbers with the co-occurrence rates, you are looking at millions of children navigating both conditions simultaneously.
And yet most of the parenting resources, therapy models, and school supports available were designed for one condition or the other. Not both.
## The Internal Tug-of-War
Here is what makes the dual diagnosis so uniquely challenging: autism and ADHD often pull a child in opposite directions.
**Autism craves predictability.** It wants the same breakfast, the same route to school, the same order of events every evening. Routine is not a preference. It is a neurological need. When the world is predictable, the autistic brain can allocate its resources to other things. When the world is unpredictable, [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) floods the system.
**ADHD craves novelty.** It wants stimulation, variety, something new. The ADHD brain is driven by interest and urgency, not importance or obligation. Routine feels suffocating. Repetition feels like punishment. The brain is constantly scanning for something more engaging than what is happening right now.
Now imagine both of those operating in the same child at the same time.
Your child may desperately need the [morning routine](/blog/morning-routine-tips-adhd) to stay the same every single day but be neurologically incapable of following it without getting distracted, going off-task, or losing interest halfway through. They may have a complete meltdown when plans change and then, twenty minutes later, resist the replacement plan because it is not stimulating enough.
This is not defiance. It is two neurological systems in genuine conflict. And it is exhausting for everyone involved.
## Why One Diagnosis Gets Missed
If your child was diagnosed with ADHD first, you are not alone. ADHD symptoms tend to become noticeable earlier, particularly when school demands increase and a child's inability to sit still, focus, or follow multi-step directions draws attention.
Research published in the Journal of Autism and Developmental Disorders found that children initially diagnosed with ADHD who later received an autism diagnosis experienced an average delay of 1.8 years between the two. For girls, that delay stretches to 2.6 years because girls are more likely to camouflage their autistic traits by imitating peers and following social scripts.
There is also an unmasking phenomenon that catches many families off guard. When ADHD medication effectively manages attention and hyperactivity symptoms, previously hidden autism traits can become more visible. A child who seemed "just" distractible may now show more obvious rigidity, social communication differences, or [sensory sensitivities](/blog/sensory-processing-daily-routines) that were masked by the ADHD noise.
This does not mean the medication caused autism. It means the autism was always there, hidden beneath the louder ADHD symptoms.
### Symptoms That Overlap
Part of the diagnostic challenge is that autism and ADHD share several surface-level symptoms:
- **Difficulty with social interaction:** Autism affects the ability to read social cues. ADHD causes impulsive or inattentive behavior in social settings. Both look like "social difficulty" on the surface, but the underlying reason is completely different.
- **Trouble sustaining attention:** Autism can cause intensely narrow focus on specific interests. ADHD causes broad distractibility. Both look like "attention problems."
- **Emotional dysregulation:** Present in both conditions, but it manifests differently. Autistic meltdowns are often triggered by sensory overload or routine disruption. ADHD-related [emotional outbursts](/blog/emotional-regulation-visual-supports) are often triggered by frustration, boredom, or impulsivity.
- **Executive function deficits:** Planning, organizing, starting tasks, switching between tasks. Both conditions affect these skills, but the dual diagnosis creates what researchers call a "double hit."
- **Repetitive behaviors:** Autism involves stimming and ritualized routines. ADHD involves fidgeting and restlessness. Both can look like "the child can not sit still."
## The Executive Function Double Hit
A 2024 meta-analysis comparing executive function in children with autism only, ADHD only, and both conditions found something important: the dual diagnosis group does not simply experience the challenges of one condition plus the challenges of the other. They get the worst executive function difficulties of both.
Children with co-occurring autism and ADHD share flexibility and planning deficits with the autism-only group. They share response inhibition deficits with the ADHD-only group. And they show more significant impairment across attention, working memory, processing speed, and visuospatial abilities than either single-diagnosis group.
In practical terms, this means your child may:
- Know what they need to do but be unable to start
- Start a task but be unable to sustain attention long enough to finish
- Finish one step of a routine but be unable to [transition](/blog/transition-strategies-autism) to the next without external support
- Understand the plan but be unable to hold it in working memory long enough to execute it
- Want to follow the routine but get derailed by every distraction in the environment
This is not laziness or a lack of motivation. It is a brain that needs more scaffolding than either diagnosis alone would suggest.
## What "Structured Flexibility" Looks Like
Researchers and clinicians working with dual-diagnosis children have landed on a concept that may be the most useful framework for families: structured flexibility.
The idea is straightforward. Your child needs predictable anchors (the autism need) combined with planned novelty and choice (the ADHD need). Neither rigid routine nor wide-open freedom works in isolation. The sweet spot is a framework that is stable enough to reduce anxiety but flexible enough to sustain engagement.
Here is what that looks like in daily life:
### Morning Routine with Built-In Choice
Instead of a rigid step-by-step sequence that your child resists, create a [visual schedule](/blog/visual-schedules-for-autism) with required anchors (breakfast, getting dressed, brushing teeth) but let your child choose the order. A [choice board](/blog/choice-boards-empowering-decisions) within the routine satisfies the ADHD brain's need for autonomy while the overall structure satisfies the autism brain's need for predictability.
### Transition Warnings with Engagement Hooks
Standard transition warnings ("five more minutes") often fail for dual-diagnosis children because the autism brain needs them but the ADHD brain ignores them. Instead, pair the warning with an engagement hook: "In five minutes we are switching to something new. Want to guess what it is?" or use a visual timer that makes the countdown tangible. Our guide on [staying regulated during transitions](/blog/staying-regulated-during-transitions) covers this in depth.
### Homework with Sensory Breaks
A child with both conditions cannot sustain attention on a non-preferred task for extended periods. Build [sensory breaks](/blog/sensory-processing-daily-routines) directly into the [homework routine](/blog/homework-routine-adhd-autism) rather than using them as a reward. Five minutes of work, two minutes of movement, five minutes of work. This is not giving in. It is working with the brain instead of against it.
### Predictable Novelty
This sounds like a contradiction, but it works. Build a "surprise activity" slot into your daily or weekly routine. Your child knows that every Wednesday after school includes a surprise activity. The slot is predictable. The content is novel. Both brains are satisfied.
## Medication: What Parents Need to Know
The conversation about medication for children with co-occurring autism and ADHD is more nuanced than for either condition alone.
Stimulant medications (methylphenidate and amphetamines) remain the first-choice treatment for ADHD symptoms, including in children who also have autism. Up to 52% of autistic children are prescribed stimulants. However, research consistently shows that stimulants tend to be less effective and cause more side effects in children with dual diagnosis compared to children with ADHD alone.
Side effects of particular concern include social withdrawal, increased irritability, sleep disturbance, and appetite changes. Parents should also know that most of the positive-findings studies on stimulants in this population are short-term (one to two weeks), which may not reflect how the medication performs over months or years.
Non-stimulant options like atomoxetine and guanfacine XR have shown promise. Atomoxetine generally has better tolerability in this population, while guanfacine XR has been effective for managing both hyperactivity and the irritability that often accompanies dual diagnosis.
The American Academy of Pediatrics recommends behavioral intervention as the first line for children under six. For children six and older, the strongest evidence supports combining behavioral strategies with medication. If you are weighing these options, our guide on [finding the right therapist](/blog/finding-right-therapist-neurodivergent-child) can help you find a provider who understands the complexity of dual diagnosis.
## The Impact on Your Family
Research confirms what you already feel: the dual diagnosis takes a greater toll on families than either condition alone.
Co-occurring autism and ADHD is associated with lower quality of life and poorer adaptive functioning for the child, and significantly elevated stress, financial burden, and time demands for caregivers. The interventions are more complex. The attention required is more constant. The daily disruptions are more frequent.
If you are experiencing [caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children), you are not imagining it. The research validates that what you are managing is genuinely harder, not because your child is harder to love, but because the support systems around you were not designed for this level of complexity.
## The Strengths Nobody Talks About
Here is something the deficit-focused literature often misses: the combination of autism and ADHD can produce genuinely remarkable cognitive abilities.
Vanderbilt University's Frist Center for Autism and Innovation describes it this way: "When we only look at the contradictions in a dual diagnosis, society risks seeing the individual as fragmented when, in reality, they are more dynamic and have traits that balance and create unique strengths."
The rapid, expansive thinking of ADHD combined with autism's capacity for deep, sustained attention to detail can create unusual problem-solving abilities. These children often connect ideas across domains that others would never link. They notice subtle patterns. They approach problems from angles that no one else considered.
The impulsivity of ADHD can also serve as a counterbalance to autistic rigidity, helping a child step outside their comfort zone in ways they might not otherwise attempt. And the structure-seeking nature of autism can anchor the ADHD brain when it needs grounding.
Your child is not broken. They are not the sum of two deficits. They are a whole person with a brain that works differently, and that difference includes strengths that the world needs.
## Building the Right Support System
Supporting a child with both autism and ADHD requires a team that understands both conditions and how they interact. Here is what to prioritize:
### Get the Full Picture
If your child has one diagnosis and you suspect the other, pursue evaluation. The 1.8-year average delay in dual diagnosis means many children are receiving supports that only address half of their needs. A comprehensive neuropsychological evaluation can identify both conditions and how they present in your specific child.
### Coordinate Across Providers
Your child may have an occupational therapist addressing sensory needs, a behavioral therapist working on social skills, and a prescribing physician managing medication. These providers need to communicate with each other. Use tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) to share visual routines and [track emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) across settings so everyone is working from the same information. Our guide on [collaborating with providers](/blog/provider-collaboration-iep-preparation) can help you structure these conversations.
### Educate the School
Your child may need accommodations that address both conditions. A [504 plan or IEP](/blog/504-plan-vs-iep-neurodivergent-child) should include provisions for both autism-related needs (sensory breaks, visual schedules, reduced transitions) and ADHD-related needs (movement breaks, extended time, preferential seating, chunked assignments). If the school only accommodates one diagnosis, half of your child's needs are going unmet.
### Build Visual Structure at Home
Visual supports are one of the few interventions with a strong evidence base for both autism and ADHD. The National Clearinghouse on Autism Evidence and Practice lists visual schedules as one of 28 evidence-based practices for autism. For ADHD, visual supports externalize working memory, compensating for one of the core deficits of the condition.
A Scottish study of 29 families found that implementing home visual supports led to statistically significant improvement in parent quality of life (p = 0.005). Before the intervention, only 43% of families used visual supports at home. After the intervention, 100% adopted them.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build visual routines that work for both conditions simultaneously: the predictable structure autism needs with the flexibility and engagement ADHD requires. AI-generated images personalized to your child make the routines feel relevant, not generic. And because the routines are digital, they are easy to adjust when something is not working, without starting from scratch.
## Your Child Is Not a Contradiction
The term "AuDHD" has emerged in recent years to describe the experience of living with both autism and ADHD. It is more than a label. It is a recognition that this is not simply one condition layered on top of another. It is a distinct neurological experience with its own challenges, its own logic, and its own strengths.
Your child's brain is not at war with itself, even when it feels that way. It is doing what all brains do: trying to make sense of the world with the wiring it has. Sometimes that wiring creates conflict between the need for order and the need for novelty. Sometimes it creates something extraordinary.
Your job is not to pick a side. It is to build an environment where both parts of your child's brain can get what they need. Structure with room to breathe. Predictability with room to surprise. Routine with room to choose.
That is not impossible. It just takes different tools than most parenting books will give you. And the fact that you are here, reading this, looking for those tools, tells your child everything they need to know about you.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual routines designed for the unique paradox of autism and ADHD, with predictable structure your child can count on and built-in flexibility their brain craves. Track emotional patterns across both conditions, share routines with therapists and teachers so everyone is on the same page, and create the structured flexibility that research says works best for children with dual diagnosis. Just $6.99/month after your trial, no credit card required upfront.
---
## Stay-at-Home Mom with an Autistic Child: What Nobody Tells You
Published: 2026-03-06
URL: https://vizyplan.com/blog/stay-at-home-mom-autistic-child
Category: Strategies
Author: Justin Bowman
> The science behind why stay-at-home moms of autistic children experience combat-level stress, and the practical strategies that actually help.
You love your child fiercely. That was never the question.
The question is why you feel like you are running on empty by 9 AM. Why the sound of your own name being called for the hundredth time makes your chest tighten. Why you scrolled past three "grateful mama" posts this morning and felt absolutely nothing except tired.
If you are a stay-at-home mom raising an autistic or neurodivergent child, your daily reality looks nothing like what parenting blogs and social media would have you believe. And the hardest part is not the meltdowns, the rigid routines, or the sensory landmines scattered through your house. The hardest part is feeling like you are the only one living this life.
You are not. And science has something important to say about what you are going through.
## Your Stress Is Not "Just" Parenting Stress
Here is a finding that might stop you in your tracks: researchers at the University of Wisconsin-Madison discovered that mothers of adolescents and adults with autism show cortisol profiles similar to combat soldiers. Not "elevated stress." Not "above average." The same hormonal pattern found in soldiers returning from war zones and Holocaust survivors who developed PTSD.
This is not a metaphor. It is biology.
The study, published in the Journal of Autism and Developmental Disorders, found that mothers of autistic children provide at least two additional hours of daily childcare compared to other mothers. They are more than twice as likely to experience fatigue every single day. Three times more likely to encounter stressful events daily. And nearly 25% of their days include work interruptions, compared to less than 10% for comparison groups.
Dr. Leann Smith, a developmental psychologist at the Waisman Center, put it this way: "Mothers experience more stressful events and have less time for themselves compared to average American mothers."
When one mother in a related study by Stewart and colleagues was asked to describe her daily experience, she said: "It is like fight or flight 100% of the time."
If that sentence hit you in the gut, it is because you have lived it. The constant vigilance. The scanning for triggers. The inability to ever fully relax because your nervous system has learned that calm does not last.
This is not a personal failing. It is your body responding to a chronically demanding environment exactly the way it was designed to respond.
## The Isolation Nobody Warns You About
The Kennedy Krieger Institute and the Interactive Autism Network surveyed thousands of families and found that 40% of parents of autistic children isolate themselves from friends and family because of their child's behaviors. Another 32% were excluded from social events by others. And 80% said stigma was a significant difficulty in their lives.
For stay-at-home moms, this isolation compounds in ways that working parents may not experience. Research published in PMC found that employed mothers of autistic children showed greater social inclusion than stay-at-home mothers. The workplace, for all its challenges, provides built-in adult interaction, identity beyond caregiving, and a daily reason to leave the house.
When you are home all day with a child who needs constant support, the world shrinks. You stop accepting invitations because the preparation and potential fallout are not worth it. You watch other moms at the playground form friendships while you are three steps behind your child, managing safety and sensory input instead of having a conversation. Playdates that end in meltdowns become playdates you stop scheduling.
One mother in a Greek qualitative study captured it perfectly: "Other people looking at you differently, like we are coming from a different planet."
The isolation is not just emotional. It changes your brain. Chronic social isolation activates the same stress pathways that are already overloaded from caregiving, creating a feedback loop that makes everything harder. You withdraw because you are exhausted, and the withdrawal makes you more exhausted.
## The Grief You Did Not Expect
Nobody handed you a pamphlet about ambiguous loss when your child was diagnosed. But research shows that parents of autistic children experience a specific kind of grief that does not follow the traditional model.
Ambiguous loss, a concept developed by Dr. Pauline Boss, describes a loss with no closure. Your child is here, present, and deeply loved. But the life you imagined, the milestones you expected, the ease you assumed parenting would eventually become, those are gone. And unlike a death, there is no funeral, no community casseroles, no socially accepted period of mourning.
Studies published in the Journal of Autism and Developmental Disorders and Research in Developmental Disabilities found that mothers go through repeated cycles of grief tied to mourning the child and life they had envisioned. One mother in the research said simply: "I miss my old life. When you have a child with autism, your whole life is affected."
This grief resurfaces at predictable moments. When your child's peers hit milestones your child has not reached. When family gatherings highlight the differences. When another birthday passes and you recalibrate your expectations again.
If you have felt this and felt guilty for feeling it, know that it does not mean you love your child any less. It means you are human. Grief and love are not opposites. They often share the same space.
## Your Identity Did Not Disappear. It Got Buried.
Research on maternal stress in autism caregiving has identified something important: stress increases when mothers struggle to know where their own identity ends and their child's begins.
When your entire day revolves around therapy schedules, [sensory needs](/blog/sensory-processing-daily-routines), [mealtime battles](/blog/mealtime-strategies-picky-eating-autism-adhd), and [bedtime routines](/blog/bedtime-routine-autism-adhd), it is easy to lose track of who you were before this became your whole world. The career you paused or left behind. The hobbies that used to make you feel like yourself. The friendships that faded because you could never be available on anyone else's schedule.
The financial data tells part of this story. Research published in PMC found that mothers of children with ASD earn 56% less than mothers of children with no health limitation. Women who leave the workforce to provide full-time caregiving lose an estimated $330,000 in wages and benefits over their lifetimes. And lost employment income accounts for approximately 90% of total family costs associated with ASD.
These are not just numbers. They represent choices that did not feel like choices. They represent a version of you that got set aside, not because you did not matter, but because everything else felt more urgent.
## The Marriage Pressure
You may have heard the statistic that 80% of marriages with an autistic child end in divorce. Take a breath. That number has been scientifically debunked by researchers at Kennedy Krieger Institute and Johns Hopkins University.
The actual data shows divorce rates of approximately 23.5% in families with an autistic child, compared to 13.8% in comparison groups. That is still elevated, but it is nowhere near the catastrophic figure that gets passed around in support groups and social media.
What the research does show is that the risk timeline is different. In most families, divorce risk decreases as children grow older. In ASD families, the risk remains elevated well into the child's adulthood. Nearly 40% of divorces occurred during the first five years after the child's birth, and another 25% happened between ages 10 and 15.
The strain is real. [Navigating two-household routines](/blog/divorce-two-household-routines-neurodivergent-children) after a separation adds layers of complexity for neurodivergent families. But knowing the real numbers can take some of the fear out of the equation.
## What Actually Helps (According to Science, Not Instagram)
Generic "self-care" advice is not going to cut it. You already know that a bubble bath does not fix chronic stress. Research points to strategies that actually move the needle.
### Problem-Focused Coping Over Emotion-Focused Coping
A systematic review published in PMC found that problem-focused coping (45.9% usage rate) and social support (37.8%) were the most effective coping resources for parents of autistic children. Parents who adopt positive, problem-focused strategies report less stress and better well-being than those who rely on emotion-focused coping.
What does this look like in practice? Instead of trying to feel better about a hard situation, you change the situation. You build a [visual schedule](/blog/visual-schedules-for-autism) that reduces morning chaos. You create a [first-then board](/blog/first-then-boards-guide) that cuts transition meltdowns in half. You set up systems so that your day runs on structure instead of willpower.
### Build Routines That Carry the Weight for You
A Scottish study of 29 families found that implementing home visual supports led to statistically significant improvement in parent quality of life (p = 0.005). Before the intervention, only 43% of families used visual supports at home. After, 100% adopted them.
A UK-based study found that consistent, parent-led routines reduced autism-related difficulties by 17% over six years and improved communication skills. Children with established routines have a 47% likelihood of maintaining strong social-emotional health as they grow older.
This is the shift that changes everything: structured routines are not just for your child. They are for you. When the morning has a predictable shape, you are not making 50 micro-decisions before 8 AM. When transitions have a visual cue, you are not bracing for a meltdown at every turn. When your child can follow a routine with some independence, you get minutes back. And those minutes matter.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was designed for exactly this. Build visual routines with AI-generated images your child connects with, track [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) so you can anticipate hard moments instead of reacting to them, and create a structure that holds even on your hardest days.
### Find Your People (And Let Go of Everyone Else)
The research on social support is clear: the size and function of your support network directly predicts your well-being. Informal support from a partner, family, and friends mediates and moderates maternal well-being, reduces stress, and predicts positive changes over time.
But here is what the research does not always say plainly: you may need to build a new network. The mom friends from before the diagnosis may not be able to meet you where you are now. And that is okay.
Look for:
- Online communities specific to autism parenting (Facebook groups, Reddit communities, Discord servers where people understand without explanation)
- Local parent support groups through your child's therapy clinic, school district, or organizations like the Autism Society
- Even one other parent who gets it, someone you can text at 2 PM on a Tuesday when the day has gone sideways
If your [extended family does not understand](/blog/extended-family-doesnt-understand-neurodivergent-child) your child's needs, that is a separate challenge worth addressing directly. But do not wait for them to come around before building your support system.
### Respite Is Not a Luxury
Research shows that parents who receive respite care report less stress and fewer symptoms of anxiety and depression. Single mothers of autistic children specifically report fewer depressive symptoms when using respite services.
But here is the catch: inadequate respite care can actually increase stress rather than reduce it. Quality matters. A respite provider who does not understand your child's triggers, communication style, or sensory needs will leave you more anxious than if you had just stayed home.
Start small. Train a trusted family member on your child's routines using [visual tools they can follow](/blog/building-independence-visual-supports). Share your [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) routines so a provider can step into your structure without guessing. Even two hours of genuine, worry-free time can interrupt the chronic stress cycle.
### Protect Something That Is Just Yours
This is the strategy most stay-at-home moms skip because it feels selfish. It is not selfish. It is survival.
Research on identity and maternal stress shows that maintaining a sense of self outside the caregiving role is protective against [burnout](/blog/caregiver-burnout-parents-neurodivergent-children) and depression. It does not have to be a career. It does not have to be impressive. It just has to be yours.
- A 20-minute walk with headphones after your partner gets home
- A creative project you work on during nap time or after bedtime
- A weekly phone call with a friend who knows you as more than someone's mom
- A class, a book club, a journal, anything that reminds your brain it has interests beyond the next therapy appointment
## The Part Nobody Talks About: You Are Also Growing
The research is not all heavy. Studies on positive contributions in autism caregiving found that parents report meaningful growth from this experience: deeper self-awareness, stronger parent-child bonds, recognition of their own emotional needs, and a shift toward more connected, intentional parenting.
One study found that despite combat-level cortisol, mothers of autistic children reported similar levels of daily positive interactions, volunteer service, and social support compared to comparison groups. You are not defined by your stress. You are simultaneously stressed and strong, exhausted and capable, grieving and growing.
That duality is not a contradiction. It is the truth of your life.
## You Are Not Failing. You Are Fighting.
If you made it to the end of this article, you are looking for help. That alone tells you something about who you are. You are not the mom who gave up. You are the mom who Googled "stay-at-home mom with autistic child" at some point during a hard day because you refuse to stop trying.
The cortisol is real. The isolation is real. The grief and the exhaustion and the loss of identity are all real. But so is your resilience. So is your love. And so is the fact that you show up for your child every single day in a world that was not designed for either of you.
You are not alone. You never were.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual routines that give your day structure without draining your energy, track emotional patterns so you can anticipate meltdowns instead of reacting to them, create shareable schedules that let a respite provider step into your routine seamlessly, and give yourself back the minutes that make the difference between surviving and actually living. Just $6.99/month after your trial, no credit card required upfront.
---
## When a Family Member Dies: Supporting Your Neurodivergent Child Through Grief
Published: 2026-03-05
URL: https://vizyplan.com/blog/grief-loss-death-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Neurodivergent children grieve differently. Learn why grief looks unusual in autistic and ADHD children and how to support them through the loss of a family member.
The phone call comes and your world stops. Someone your child loves has died. In the hours that follow, you are drowning in logistics, grief, and the impossible question every neurodivergent parent faces in crisis: how do I explain this to my child?
Your child processes the world differently on a normal Tuesday. Death is not a normal Tuesday. It is the most abstract, permanent, confusing concept a human being can encounter, and you are about to explain it to a child whose brain thrives on concrete thinking, predictable routines, and the reassurance that things stay the same.
If you are reading this in the middle of that moment, here is what you need to know first: there is no perfect way to do this. But there are ways that work better for neurodivergent children, and they are different from what most grief resources will tell you.
## Why Grief Is Different for Neurodivergent Children
Grief is hard for everyone. For neurodivergent children, it is hard in specific, predictable ways that most bereavement resources do not address.
### Concrete Thinking Meets an Abstract Concept
Death is inherently abstract. The person was here. Now they are not. They are never coming back. For a child who thinks in concrete, literal terms, this concept can be genuinely incomprehensible. Research on theory of mind in autism confirms that understanding invisible, permanent states that cannot be directly observed is one of the core cognitive challenges autistic children face.
Your child may ask "But where did Grandma go?" not because they did not hear you, but because "gone forever" does not compute the way "gone to the store" does. They may ask the same question repeatedly for weeks, not because they forgot the answer, but because their brain keeps trying to make the concept fit into a framework that has no slot for permanent absence.
### Alexithymia Blocks Emotional Expression
Research estimates that approximately **50% of autistic individuals** experience alexithymia, the difficulty identifying, describing, and processing emotions, compared to roughly 5% of the general population. A 2019 meta-analysis by Kinnaird and colleagues confirmed this striking prevalence.
This means your child may be feeling grief intensely while having no language for what is happening inside their body. They might feel a tightness in their chest, a heaviness in their stomach, or an overwhelming urge to scream, but they cannot name that as sadness. Without the ability to identify and express the emotion, grief has nowhere to go. It comes out sideways, through [meltdowns](/blog/recognizing-triggers-meltdowns-neurodivergent-children), regression, behavior changes, or what looks from the outside like not caring at all.
### Routine Disruption Compounds the Loss
When someone in the family dies, routines collapse. People come and go from the house at unusual times. Meals happen at random. Parents are distracted, crying, on the phone. The normal schedule disappears entirely, sometimes for days or weeks.
For a child who depends on [predictable routines](/blog/visual-schedules-for-autism) to feel safe, this is a double loss. They have lost a person they love AND they have lost the structure that helps them navigate the world. Researchers describe this as "loss on loss," where the secondary disruptions (changes to household dynamics, altered schedules, unfamiliar visitors) compound the primary grief in ways that are unique to neurodivergent children.
### Sensory Overwhelm at the Worst Time
Funerals, wakes, and memorial services are [sensory nightmares](/blog/sensory-processing-daily-routines). Crowded rooms full of unfamiliar people. People crying loudly. Hugging from relatives the child barely knows. Unfamiliar clothing that feels wrong. Strong smells from flowers. The echoing acoustics of a church or funeral home. Cold, hard pews. Standing and sitting at unpredictable intervals.
Every one of these sensory challenges exists in an environment where social expectations demand quiet, stillness, and emotional composure. For a neurodivergent child, this is an impossible combination.

## How to Tell Your Child Someone Has Died
The words you use matter enormously, and the rules are different for neurodivergent children.
### Use Literal Language
This is the most important guidance in this entire article. **Do not use euphemisms.** Neurodivergent children, especially autistic children, process language literally. Common phrases that adults use to soften death create genuine confusion and sometimes fear.
**Do not say:**
- "We lost Grandpa." (Your child may want to go find him.)
- "Grandma passed away." (Passed where? Away to where?)
- "Uncle Mike is sleeping now." (Your child may become terrified of going to sleep.)
- "God took her." (Your child may become afraid of God or angry that someone took their person.)
- "She is in a better place." (If it is better, why is everyone crying? Can we visit?)
**Instead say:**
- "Grandpa died. That means his body stopped working and he is not alive anymore."
- "When someone dies, their body does not breathe, eat, sleep, or feel anything anymore. They cannot come back."
- "Grandma's body was very sick and the doctors could not fix it. She died."
The language feels blunt to adult ears. But for a concrete thinker, clarity is kindness. Vague language does not protect your child. It confuses them and forces them to fill in the gaps with their imagination, which is often worse than the truth.
### Expect and Welcome Repeated Questions
Your child may ask "Is Grandpa really dead?" every day for weeks. This is not a sign that they do not understand. This is how concrete thinkers process permanence. Each time they ask, they are testing whether the answer has changed, because in their experience, most things that go away eventually come back.
Answer the same way each time, calmly and consistently. "Yes, Grandpa died. He is not coming back. I know that is sad." Consistency in your answer helps the permanence settle in over time. Getting frustrated or changing your wording signals that the truth might be flexible, which restarts the processing loop.
### Use Visual Supports
[Social stories](/blog/social-stories-autism-guide) are one of the most effective tools for helping neurodivergent children understand complex experiences. A social story about death can include:
- What happened (the person died)
- What that means in concrete terms (their body stopped working)
- What will change (they will not be at Sunday dinners, we will not visit their house anymore)
- What will stay the same (our family still lives here, you still go to school, your routine is still the same)
- What feelings are okay to have (sad, angry, confused, or even nothing at all)
- What the child can do when they feel those feelings
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build personalized social stories with AI-generated images of your child in familiar settings, making the concept feel concrete and connected to their actual life rather than abstract.
## Preparing for the Funeral or Memorial
Not every neurodivergent child should attend a funeral. That is okay. But if you want to give your child the option, preparation is everything.
### Preview Everything Visually
Show your child pictures of the funeral home or church. Explain what will happen in order: we will arrive, we will sit in a room with chairs, people will talk about the person who died, some people will cry, there may be music, and then we will leave. Use a visual sequence they can reference during the service.
If there will be an open casket, explain this concretely: "The person's body will be in a special box called a casket. They will look like they are sleeping, but they are not. Their body stopped working. Some people want to walk up and look at the body. You do not have to do that unless you want to."
### Create a Sensory Survival Kit
Pack everything your child needs to manage the [sensory environment](/blog/sensory-processing-daily-routines):
- Noise-cancelling headphones or earplugs
- A fidget tool or comfort item
- Sunglasses if the lighting is harsh
- Comfortable clothes that look appropriate (negotiate this in advance, not the morning of)
- A snack in case the service is long
- A tablet or book for quiet distraction if needed
### Have an Exit Plan
Before you arrive, identify where you will go if your child needs to leave. A car, an empty hallway, a quiet room. Designate one adult whose sole job is to be your child's support person, someone who can leave the service without disrupting it and take the child somewhere calm.
Tell your child in advance: "If it feels like too much, we can leave. You just tell me or squeeze my hand and we will go outside." Knowing the escape exists often reduces the need to use it.
### Consider Alternatives
If a full funeral service is too overwhelming, your child can participate in grief in other ways:
- Visiting the grave or memorial site later, when it is quiet
- Drawing a picture or writing a letter to the person who died
- Lighting a candle at home
- Looking at photos together and sharing memories
- Planting something in the person's honor
Participation does not have to look traditional to be meaningful.
## Understanding Atypical Grief Responses
This section may be the most important for your own wellbeing as a parent, because neurodivergent grief often looks nothing like what you expect.
### Delayed Grief
Your child may show no visible reaction for days, weeks, or even months after the death. This does not mean they do not care. Autistic children in particular may need extended processing time before the emotional weight arrives. Research on bereavement in autism describes delayed grief as one of the most common and most misunderstood responses.
The grief may surface suddenly and intensely, triggered by something seemingly unrelated: a song, a smell, arriving at a place the person used to be, or a change in routine that was previously anchored by the person who died. When it arrives late, it can catch everyone off guard, including the child.
### Grief Through Behavior, Not Words
A child who cannot name their grief may express it through:
- Increased [meltdowns](/blog/recognizing-triggers-meltdowns-neurodivergent-children) or emotional outbursts
- Regression in previously mastered skills (toileting accidents, loss of independence)
- Changes in sleep patterns or [increased sleep difficulties](/blog/sleep-challenges-night-waking-neurodivergent-children)
- Increased stimming (this is a healthy coping mechanism and should not be discouraged)
- Withdrawal from activities they previously enjoyed
- Physical complaints: stomach aches, headaches, fatigue
- Refusing food or changes in [eating patterns](/blog/mealtime-strategies-picky-eating-autism-adhd)
- Increased rigidity around routines and rules
These are not behavior problems. They are grief expressed through the only channels available to a child who cannot articulate what they feel.
### Seeming "Unaffected"
Some neurodivergent children respond to news of death with apparent indifference. They may return to playing immediately, ask a factual question ("What will happen to their house?"), or change the subject entirely. This can be shocking and painful for grieving family members.
This response does not mean your child lacks empathy or does not care. It may mean they are processing the information cognitively before the emotional response arrives. It may mean they do not yet understand the permanence. It may mean the emotional response is happening internally but they cannot express it externally. Or it may mean they need time.
Do not force a visible grief response. Do not say "Do you not feel sad?" or "Do you understand what happened?" Simply keep the door open: "I feel sad about Grandpa. If you feel sad too, or any other way, you can always tell me."
### Perseverative Questions About Death
Some children will become intensely focused on the mechanics of death. How does a body stop working? What happens to a body underground? Can it happen to other people? Can it happen to you? Can it happen to me?
These questions can feel morbid or upsetting, but they are often your child's way of trying to build a mental model for something they have never encountered. Answer honestly, age-appropriately, and repeatedly. If the questions are causing the child visible distress rather than serving an information-gathering function, gently redirect: "I have answered that question the best I can. Let us do something that helps us feel calm right now."
## Maintaining Routine When Everything Falls Apart
When your family is in crisis, routine feels like the last priority. It is actually the first.
### Keep the Anchors
You cannot maintain a perfect schedule while planning a funeral and processing your own grief. You do not need to. Focus on the anchor points: the predictable moments that bookend your child's day.
- [Morning routine](/blog/morning-routine-tips-adhd) stays the same, even if abbreviated
- Meals happen at approximately the same times
- [Bedtime routine](/blog/bedtime-routine-autism-adhd) stays the same, even if bedtime itself shifts slightly
- School attendance continues if possible (school provides structure and normalcy)
Between the anchors, let the middle be flexible. Your child can handle uncertainty in the gaps if the edges hold.
### Use Visual Schedules to Replace Verbal Explanations
You are exhausted. You are grieving. You do not have the bandwidth to explain the plan for the day seventeen times. A [visual schedule](/blog/visual-schedules-for-autism) does this for you. Post it where your child can see it. Update it as needed. Let the schedule be the authority so you do not have to narrate every transition.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build and adjust visual routines quickly, which matters when your days are unpredictable and your energy is low. A five-minute schedule update on the app can save hours of anxiety for your child and you.
### Prepare for Household Changes
If the person who died was part of your child's regular routine (a grandparent who watched them after school, a parent in a co-parenting arrangement, a sibling), the structural change is enormous. Address this directly:
- "Grandma used to pick you up on Tuesdays. Now Aunt Sarah will pick you up on Tuesdays."
- "Dad is not going to be at dinner anymore. We will still eat dinner at the same time, at the same table."
- Use a [first-then board](/blog/first-then-boards-guide) to show the new arrangement visually.
The more explicitly you name what is changing and what is staying the same, the less your child's brain has to guess, and guessing is where anxiety lives.
## ADHD and Grief: A Different Pattern
While autistic grief tends toward delay and internalization, ADHD grief often shows up differently.
### Intensity and Impulsivity
Children with ADHD may experience grief in sudden, intense waves that arrive without warning and feel disproportionate to the trigger. They may be playing happily one moment and sobbing the next. This emotional intensity is consistent with the [emotional dysregulation](/blog/emotional-regulation-visual-supports) that characterizes ADHD, but it can be alarming during bereavement.
### Difficulty Sustaining Focus on Grief
A child with ADHD may struggle to sit with grief for extended periods. Their brain naturally seeks stimulation and novelty, which means they may cycle rapidly between visible sadness and completely unrelated activities. This is not shallow grief. It is grief filtered through a brain that cannot sustain attention on a single emotional state.
### Impulsive Expression
A child with ADHD may say things about the death that sound inappropriate: "Can I have Grandpa's watch now?" or "Does this mean we do not have to go to his house anymore?" These are not signs of callousness. They are impulsive verbalizations of thoughts that a neurotypical child might think but filter. Respond without judgment: "We can talk about that later. Right now, let us focus on how we are feeling."
## When to Seek Professional Support
Grief is a normal response to loss, and most children, including neurodivergent children, will process it over time without professional intervention. But some signs suggest grief has become complicated and help is needed.
### Watch For
- Grief that intensifies rather than gradually eases after several months
- Persistent refusal to acknowledge the death (different from delayed processing)
- Talk of wanting to die or join the person who died
- Complete withdrawal from all activities and relationships
- Significant regression that does not begin to resolve
- Self-harm or increase in dangerous behaviors
- Persistent sleep disruption beyond the first few weeks
- Inability to function at school or home after the initial crisis period
### Finding the Right Support
Look for a therapist who has experience with both grief and neurodivergent children. Play therapy is particularly effective for younger neurodivergent children processing loss, as it allows grief expression without requiring verbal articulation. For older children, adapted CBT can help with [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) that develops around death and loss.
Research in this area is remarkably scarce. A 2024 systematic review by Bonin and colleagues found that only six studies worldwide met inclusion criteria for grief support specifically for children with autism or intellectual disabilities. This means most therapists are working without a well-established evidence base, making it even more important to find someone who understands your child's neurotype. Our guide on [finding the right therapist](/blog/finding-right-therapist-neurodivergent-child) can help you evaluate potential providers.
## Talking About Your Own Grief
Your child is watching you. This is true always, and it is especially true now.
Many parents try to hide their grief to protect their child. For neurodivergent children, this backfires. Your child can sense that something is wrong. If they cannot see evidence of what is wrong, they may conclude that the wrongness is about them.
Instead, name your feelings in simple, concrete terms:
- "I am crying because I am sad about Grandma. Crying is one way our body shows sadness."
- "I feel tired today because grief makes your body tired. I am going to rest for a little while."
- "I miss Grandpa. Missing someone means you wish they were still here."
This models emotional language for a child who may not have their own. It also normalizes grief as something that happens to everyone, not something to be afraid of.
## You Cannot Grieve Wrong, and Neither Can Your Child
There is no timeline for grief. There is no correct way to feel. Your child may cry for weeks or may never cry at all. They may ask about death constantly or never mention it again. They may seem fine for months and then fall apart when a holiday arrives and the person is not there.
All of it is normal. All of it is grief doing what grief does in a brain that processes the world differently.
Your job is not to make the grief go away. It is to hold the structure steady while the ground shakes. To keep answering the same question with the same patience. To let your child stim and withdraw and rage and go quiet without interpreting any of it as wrong. To show up, even in your own grief, and say "I am here. I am sad too. And we are going to be okay."
That is enough. You are enough. Even now.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build social stories that help your child understand death and funerals with AI-generated visuals they recognize, maintain visual routines during the chaos of family crisis, track emotional patterns as your child processes grief over time, and give your family the predictability that holds everything together when nothing else can. Just $6.99/month after your trial, no credit card required upfront.
---
## Signs of Autism and ADHD in Girls: Why So Many Are Missed
Published: 2026-03-04
URL: https://vizyplan.com/blog/signs-autism-adhd-girls-underdiagnosis
Category: Strategies
Author: Justin Bowman
> Research shows 80% of autistic girls are undiagnosed at 18. Learn why autism and ADHD look different in girls and the signs parents should watch for.
Your daughter is not the child anyone worries about. Her teachers describe her as quiet, maybe a little shy. She has a best friend she shadows everywhere. She gets good grades, mostly. She melts down at home after school, but you figure she is just tired. She has very strong opinions about how her socks feel. She can talk about horses or a specific TV show for forty-five minutes without pausing. She cries easily. She struggles with change. But nobody at school sees a problem.
Here is what the research says you need to hear: **80% of autistic females are still undiagnosed at age 18.** Girls with ADHD are diagnosed an average of five years later than boys. Up to 75% of girls with attention disorders are never identified at all. These are not small gaps. These are entire childhoods spent without the support, understanding, and language your daughter needs to make sense of her own experience.
This is not because your daughter's challenges are not real. It is because the diagnostic system was built by studying boys, and your daughter does not look like a boy with autism or ADHD. She looks like a girl who is trying very, very hard to hold it all together. And she is exhausted.
## The Diagnostic Gap Is Enormous
The numbers tell a story that should make every parent pay attention.
The CDC's 2025 ADDM Network Report found that among 8-year-olds, **3.4 boys are diagnosed with autism for every 1 girl.** For ADHD, the gap is similar: 14.5% of boys carry a diagnosis compared to just 8.0% of girls. But a landmark 2026 Swedish study that tracked 2.7 million children found something striking. By age 20, the male-to-female autism ratio was approaching 1:1. The girls were not less autistic. They were just diagnosed a decade later.
Boys receive an autism diagnosis at a median age of 5. For girls, the median is age 8. For ADHD, boys are typically identified around age 7. Girls wait until age 12. That is five years of struggling without anyone naming the reason. Five years of being told they are too sensitive, too dramatic, too spacey, or not trying hard enough.
A 2025 analysis of over 338,000 patients confirmed that while boys are increasingly diagnosed before age 5, girls still peak in diagnostic rates between ages 15 and 19. That means many girls are not identified until high school, if they are identified at all.
## Why the System Misses Girls
The answer starts in 1943. Leo Kanner described 11 children with autism: 8 boys and 3 girls. Hans Asperger studied only boys. Every subsequent version of the DSM built its diagnostic criteria around these male-dominated observations. The behaviors clinicians were trained to spot, the overt repetitive movements, the obvious social withdrawal, the disruptive hyperactivity, are the way boys typically present. Girls do not.
### Girls Internalize Instead of Externalize
This is the single most important distinction. Autism and ADHD in boys tend to show up as **externalizing behaviors**: hyperactivity, disruption, visible repetitive movements, aggression. Teachers notice. Parents get calls. Referrals happen.
In girls, the same conditions show up as **internalizing behaviors**: [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies), daydreaming, [emotional dysregulation](/blog/emotional-regulation-visual-supports), perfectionism, quiet withdrawal. Nobody calls home about the girl staring out the window. Nobody flags the child who cries in the bathroom at lunch. The girl who follows every rule at school but falls apart the moment she walks through the front door does not trigger a referral because she is not disrupting anyone else's day.
Research confirms this pattern: girls with ADHD are more likely to be diagnosed with anxiety (53% compared to 32% in boys) and depression (29% compared to 14% in boys). Their actual ADHD goes unnamed while the secondary symptoms get all the attention.
### Girls Are Social Chameleons
A 2017 study by Lai and colleagues at Cambridge was the first to quantify camouflaging in autism. They found that autistic women had significantly higher camouflaging scores than autistic men, with a large effect size (Cohen's d = 0.98). This means autistic girls and women are actively, deliberately working to hide their autistic traits in social settings.
What does camouflaging look like in practice?
- **Compensation:** Explicitly learning social rules by observation, preparing conversation topics in advance, studying facial expressions like a foreign language
- **Masking:** Forcing eye contact even when it feels uncomfortable, suppressing the urge to stim, hiding sensory distress behind a smile
- **Assimilation:** Copying the behavior of popular peers, mirroring accents and speech patterns, adopting someone else's personality to fit in
The 2019 Camouflaging Autistic Traits Questionnaire (CAT-Q) by Hull and colleagues confirmed these three dimensions and showed that the gender difference in camouflaging exists only among autistic individuals. Non-autistic men and women mask at similar rates. The difference is specific to autism, driven by the intense social pressure girls face to conform.
### The "Female Autism Phenotype"
Research increasingly describes a distinct female presentation of autism that standard diagnostic tools were not designed to detect.
**Social motivation is different, not absent.** Autistic girls are often socially motivated and genuinely want friendships. This contradicts the stereotype of the child who prefers being alone. But their friendships look different. They tend to have one or two intense relationships rather than a broad social circle. They may shadow a single best friend, imitating that friend's behavior, clothing, and interests to navigate social situations. When that friendship fractures, the fallout can be devastating because the entire social strategy collapses with it.
**Special interests look "normal."** A boy who memorizes train schedules gets flagged. A girl who knows everything about a particular pop star, horse breed, or fictional universe does not, because those interests appear age-appropriate. The difference is not the topic. It is the intensity. Your daughter does not just like horses. She has memorized the lineage of every Kentucky Derby winner since 1990 and cannot stop talking about it even when her listener has clearly lost interest.
**Repetitive behaviors are hidden.** Girls tend to internalize their repetitive behaviors or redirect them into socially acceptable forms. Instead of hand-flapping, she might twirl her hair. Instead of rocking, she might bounce her leg under the desk. The behavior serves the same regulatory function, but it does not look like what the DSM describes.

## What ADHD Looks Like in Girls
ADHD in girls is its own diagnostic blind spot, and it deserves its own section because the missed signs are often different from autism.
### The Inattentive Type Dominates
Girls with ADHD are far more likely to have the inattentive presentation. They are not bouncing off the walls. They are staring out the window. They are doodling in the margins of their math worksheet while the teacher explains fractions. They are reading the same paragraph three times because their mind keeps wandering to something that happened at recess.
The ADDitude research describes these girls as fading "into the background of their classrooms." They experience "internal distractibility," getting swept away by their own thoughts so completely that they miss what is happening right in front of them. From the outside, this looks like daydreaming. From the inside, it feels like your brain has a mind of its own.
### Perfectionism Hides the Struggle
Here is something that confuses parents and clinicians alike: many girls with ADHD get good grades. Not because they find school easy, but because they are working three times harder than everyone else to compensate. They double-check everything. They stay up late rewriting assignments. They are terrified of making mistakes because mistakes feel like proof that something is wrong with them.
This perfectionism is not a personality trait. It is a coping mechanism. And it comes at a cost. The stress of maintaining a "together" exterior while internally struggling to focus, organize, and keep track of everything leads to [burnout](/blog/caregiver-burnout-parents-neurodivergent-children), anxiety, and eventually a crash that everyone around them finds surprising because she always seemed fine.
### Emotional Sensitivity Is Dismissed
Girls with ADHD experience emotions with unusual intensity. They cry at small frustrations. They become overwhelmed by conflict. A harsh tone from a teacher can ruin an entire day. This emotional sensitivity is a core feature of ADHD, but in girls, it gets labeled as "being dramatic" or "too sensitive" rather than recognized as a neurological difference.
Research from 2023 found that emotional dysregulation in girls with ADHD frequently leads to misdiagnosis of mood disorders. The girl gets treated for anxiety or depression while the underlying ADHD remains invisible.
## The Cost of Being Missed
Late or missed diagnosis is not a neutral event. It carries real consequences that compound over time.
### Mental Health Deteriorates
A study in JCPP Advances found that autistic and AuDHD adults experience clinical anxiety at a rate of **47.7%** and depression at **54.1%**, compared to 15.7% and 17.3% in the general population. Among autistic adolescents specifically, 79% experience depression and 54% have an anxiety disorder.
Without a diagnosis, girls internalize the explanation: something is wrong with me. They are too sensitive, too forgetful, too emotional, too weird. "Perceived personal flaws become the reason for academic, social, and emotional struggles, resulting in self-blame and a negative self-image," according to a systematic review in PMC.
### The Eating Disorder Connection
The research here is alarming. Up to **35% of women in inpatient units for anorexia nervosa** are likely autistic, compared to roughly 2% in the general population. Among girls entering partial hospitalization for eating disorders, 10% had a pre-existing autism diagnosis and an additional 12.5% received a new diagnosis during treatment.
Girls with ADHD face **3.6 times the risk** of any eating disorder and **5.6 times the risk** of bulimia nervosa compared to girls without ADHD. The impulsivity, sensory issues around food, and desire for control all converge in dangerous ways when a girl does not understand why she is different.
### Masking Breaks Down
A 2025 systematic review confirmed the long-term consequences of camouflaging: impact on identity formation, delayed diagnosis, depression, anxiety, stress, and suicidal ideation. A separate 2025 study found that camouflaging is strongly associated with anxiety, which in turn is strongly associated with suicidal thoughts in autistic women.
The girl who held it together through elementary school often begins to unravel in middle school, when social complexity increases beyond what mimicry can sustain. Puberty adds sensory challenges (research shows autistic girls start their period an average of 9.5 months earlier than non-autistic peers), hormonal mood shifts layer onto existing emotional dysregulation, and the gap between her internal experience and her external performance becomes unbearable.
### Nearly 80% Are Misdiagnosed First
Research from Durham University found that the majority of women with autism receive at least one incorrect psychiatric diagnosis before autism is identified. Common misdiagnoses include borderline personality disorder, generalized anxiety disorder, bipolar disorder, and eating disorders. Each wrong diagnosis means wrong treatment, wrong medication, and more time lost.
## What to Watch For at Every Age
### Toddlers (Ages 1-3)
- Unusual reactions to sensory input: covering ears, refusing certain textures, distress with [clothing tags](/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children)
- Repetitive play that looks different from peers (lining up toys, organizing by color rather than imaginative play)
- Extreme distress with changes in routine
- [Picky eating](/blog/mealtime-strategies-picky-eating-autism-adhd) tied to texture or appearance rather than taste
- May appear "advanced" verbally but struggles with back-and-forth conversation
- Prefers parallel play over interactive play
**Important note:** Signs in toddler girls are often subtler. A girl who mimics social cues from an early age may already be compensating.
### School-Age (Ages 6-10)
- One or two intense friendships rather than a broad friend group
- Shadows a specific friend, imitating their behavior and interests
- A noticeable "school self" versus "home self," with [meltdowns after school](/blog/after-school-routine-transitions-neurodivergent-children) when the mask comes off
- Interests that look typical in topic but are unusual in intensity and depth
- Difficulty with [transitions](/blog/transition-strategies-autism) between activities
- Sensory sensitivities to [noise](/blog/sensory-processing-daily-routines), light, clothing, or food that persist beyond what is typical
- Daydreaming, losing track of belongings, difficulty following multi-step directions
- Emotional reactions that seem disproportionate to the situation
- Perfectionism and intense self-criticism around schoolwork
### Pre-Teens (Ages 11-13)
This is when many girls hit a wall. Research describes puberty as "a true crossroads, particularly for the female profile of autism."
- Social complexity overwhelms camouflaging abilities and friendships fracture
- Increasing anxiety, depression, or withdrawal that looks like "typical teenage behavior"
- Autistic burnout: chronic exhaustion, loss of previously acquired skills, reduced tolerance to stimulation
- Heightened [sensory overwhelm](/blog/sensory-processing-daily-routines) during menstruation
- Intense emotional reactions to social conflict
- Difficulty maintaining [homework routines](/blog/homework-routine-adhd-autism) and organization despite academic ability
- May begin refusing school or developing physical symptoms (headaches, stomach aches) to avoid overwhelming environments
## What to Do If You See Your Daughter in This Article
### Document Before You Call
Before your next pediatrician appointment, prepare:
- Written examples of specific behaviors across settings (home, school, social)
- Notes on sensory sensitivities, [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children), and social dynamics
- Observations about the gap between her "school self" and "home self"
- Family history of autism, ADHD, anxiety, depression, or learning differences
- Video clips of meltdowns, stimming, or social difficulties if you can capture them naturally
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) can help you track your daughter's emotional patterns and behavioral changes over time, giving you concrete data to bring to appointments rather than relying on memory alone.
### Advocate Firmly at the Pediatrician
Use specific language:
- "I would like a developmental screening for my daughter."
- "I have noticed patterns that concern me and I am requesting a referral to a specialist."
- If concerns are dismissed: "I understand this may not look like the classic presentation, but research shows autism and ADHD present differently in girls. I would like a referral to a specialist who has experience evaluating girls."
### Seek the Right Evaluator
General pediatricians are often not trained in how autism and ADHD present in girls. Request a referral to:
- A developmental pediatrician
- A neuropsychologist with experience in female presentations
- A child psychologist who specifically mentions experience with the female autism phenotype
For a detailed framework on evaluating providers and navigating waitlists, read our guide on [finding the right therapist for your neurodivergent child](/blog/finding-right-therapist-neurodivergent-child).
### If You Are Dismissed, Get a Second Opinion
You know your child. Research explicitly states that parental concerns are one of the most reliable early indicators of developmental differences. A clinician who says "she makes eye contact, so it is not autism" or "she gets good grades, so it is not ADHD" is working from outdated criteria. Find someone who understands the female presentation.
## Supporting Your Daughter Right Now
You do not need a diagnosis to start helping. Whether you are waiting for an evaluation, navigating a waitlist, or still deciding whether to pursue assessment, there are things you can do today.
**Honor the after-school crash.** If your daughter falls apart when she gets home, she is not being difficult. She has been masking all day and has nothing left. Build a [decompression routine](/blog/after-school-routine-transitions-neurodivergent-children) into her afternoon: quiet time, sensory tools, a predictable snack, and zero demands for the first 30 minutes.
**Create visual predictability.** Research confirms that [visual schedules](/blog/visual-schedules-for-autism) reduce anxiety and increase independence for neurodivergent children. Even without a diagnosis, a visual routine for [mornings](/blog/morning-routine-tips-adhd), after school, and [bedtime](/blog/bedtime-routine-autism-adhd) can reduce the cognitive load your daughter carries.
**Name the feelings without judgment.** If she cries over something that seems small, do not tell her she is overreacting. Say "That really upset you. I see that." Validating her emotional experience teaches her that her feelings are real and worth understanding, not symptoms to suppress.
**Protect her energy.** A girl who is masking all day at school does not need a packed schedule of after-school activities. She needs rest. She needs unstructured time in a safe environment where she does not have to perform. Building in [sensory breaks](/blog/sensory-processing-daily-routines) and downtime is not coddling. It is preventing burnout.
**Talk about brains being different.** Even before a formal label exists, you can give your daughter language for her experience. "Your brain notices things other people miss. That is a strength and sometimes it is also really tiring." [Celebrating neurodivergent strengths](/blog/celebrating-neurodivergent-strengths-children) builds the identity foundation she will need regardless of what any evaluation says.
## She Is Not Broken. She Is Working Harder Than Anyone Knows.
Your daughter is not too sensitive. She is not being dramatic. She is not lazy or spacey or "just shy." She is navigating a world that was not designed for the way her brain works, and she has been doing it without a map, without a name for her experience, and without the accommodations that could make everything feel less impossible.
The fact that she has gotten this far by sheer force of will is not evidence that she is fine. It is evidence of how hard she has been working.
Getting your daughter evaluated, named, and supported does not limit her. It frees her. It replaces "what is wrong with me" with "this is how my brain works, and here is what helps." It transforms the internal narrative from personal failure to neurological difference. And it gives both of you a path forward that is built on understanding rather than exhaustion.
Start with what you noticed today. Write it down. Make the call. And trust that the parent who sees what nobody else sees is exactly the advocate her daughter needs.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Track your daughter's emotional patterns and behavioral changes over time with visual check-ins, build decompression routines for after school with AI-generated images she recognizes, create predictable visual schedules that reduce the cognitive load of masking, and share documented patterns with evaluators and therapists. Just $6.99/month after your trial, no credit card required upfront.
---
## Types of Therapy for Neurodivergent Children: What Parents Need to Know
Published: 2026-03-03
URL: https://vizyplan.com/blog/types-of-therapy-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> From occupational therapy to speech therapy to play-based approaches, understanding which therapies help neurodivergent children and what each one actually looks like in practice.
Your child just got diagnosed, and now you are staring at a referral list that reads like alphabet soup. OT. SLP. ABA. CBT. PT. The pediatrician mentioned something about sensory integration, the school wants to discuss social skills groups, and a friend of a friend swears by equine therapy. You want to do everything right. You also have no idea where to start.
This is the moment most parents describe as the second wave. The first wave was the diagnosis itself. The second is realizing that getting the diagnosis was the easy part. Now comes the harder question: what do you actually do with it?
The answer, frustratingly, is "it depends." But it depends in ways that make sense once you understand what each therapy targets, what it looks like in a real session, and which signs in your child point toward which type of support. That is what this guide is for. Not to replace professional evaluation, but to give you the foundation you need to walk into those conversations informed and confident.
## Why So Many Therapies Exist
Neurodivergent children do not all face the same challenges. A child with autism who is nonverbal and struggles with daily living skills has very different needs than a child with ADHD who talks nonstop but cannot sit through a homework assignment. A child who gags at the texture of mashed potatoes needs different support than a child who melts down every time plans change.
The variety of therapy options exists because the neurodivergent experience is not one thing. It is a constellation of strengths and challenges that shows up differently in every child. The goal is not to sign your child up for everything. It is to identify the specific areas where they need support and match those to the right approach.
Research supports this targeted model. The American Academy of Pediatrics recommends individualized therapy plans based on comprehensive assessment, because the intervention that transforms one child's life may be irrelevant to another. With **1 in 36 children** now identified with autism according to the CDC's 2025 Community Report, the therapeutic landscape has expanded significantly to address this range.
## Occupational Therapy: Building the Skills of Everyday Life
Occupational therapy is often the first referral parents receive, and for good reason. OTs work on the skills your child needs to navigate daily life, from getting dressed in the morning to writing their name at school to tolerating the feeling of socks on their feet.
### What a Session Actually Looks Like
OT sessions for young children often look like play, and that is intentional. Your child might swing on a platform swing to work on vestibular processing, squeeze putty to build hand strength, practice buttoning a shirt on a doll before trying it on themselves, or navigate an obstacle course that challenges balance and motor planning. For older children, sessions might focus on handwriting strategies, organizational skills, or sensory regulation techniques they can use independently.
The 2024 AOTA Practice Guidelines, developed through four rounds of consensus with 17 OT experts, identify 20 key treatment components for working with autistic individuals across the lifespan. A 2024 study published in the National Library of Medicine found that occupational therapy "significantly improved the behaviour and daily performance of children with ASD," including measurable gains in communication, socialization, and daily living skills.
### Signs Your Child May Need OT
- Struggles with [fine motor tasks](/blog/fine-motor-skills-handwriting-neurodivergent-children) like holding a pencil, using scissors, or buttoning clothing
- Avoids or is overwhelmed by sensory input: bright lights, loud sounds, certain textures, specific food consistencies
- Has difficulty with self-care routines like [getting dressed](/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children), [brushing teeth](/blog/teeth-brushing-routine-autism-adhd), or [bath time](/blog/bath-time-hygiene-routines-neurodivergent-children)
- Experiences intense [emotional outbursts](/blog/emotional-regulation-visual-supports) and difficulty calming down
- Struggles with balance, coordination, or appears unusually clumsy
- Has trouble paying attention or following multi-step instructions
## Speech-Language Therapy: Far More Than Learning to Talk
When parents hear "speech therapy," they often picture a child learning to pronounce sounds correctly. But speech-language pathology covers an enormous range of communication, and for neurodivergent children, it often has nothing to do with pronunciation at all.
### What a Session Actually Looks Like
For a nonverbal or minimally verbal child, sessions might involve learning to use a picture exchange system (PECS), practicing with a speech-generating device on a tablet, or building functional gestures. For a verbal child with pragmatic language challenges, sessions might involve practicing conversation turn-taking, learning to read facial expressions, understanding sarcasm or implied meaning, or working through [social stories](/blog/social-stories-autism-guide) that model appropriate responses.
The American Speech-Language-Hearing Association (ASHA) identifies evidence-based practices for autism that include functional communication training, augmentative and alternative communication, and naturalistic teaching strategies. A systematic review found a "small but significant effect" favoring pragmatic language interventions for children 18 and younger on the autism spectrum, with the strongest gains in structured social communication.
### Signs Your Child May Need Speech Therapy
- Fewer than 20 words at 18 months or fewer than 50 words by age 2
- Does not respond to their name consistently
- Has difficulty joining or maintaining conversations
- Speech is hard for others to understand
- Frustration that leads to hitting, throwing, or screaming because they cannot express what they need
- Difficulty understanding multi-step directions
- Struggles with social aspects of communication, like knowing when to speak and when to listen
## Applied Behavior Analysis: Understanding the Full Picture
ABA is likely the most frequently recommended and most hotly debated therapy in the autism world. If you have been reading online, you have probably encountered passionate opinions on both sides. You deserve the full picture so you can make an informed decision for your family.
### What Modern ABA Actually Looks Like
ABA at its core uses principles of learning and motivation to teach new skills and reduce behaviors that interfere with safety or quality of life. Modern, neurodiversity-affirming ABA has evolved significantly from the rigid, compliance-focused approach of decades past.
In a good ABA program today, sessions are play-based and follow the child's interests. A therapist might embed learning opportunities within a game your child loves, use natural environment teaching rather than structured table drills, and prioritize functional communication and independence over compliance and eye contact. Naturalistic Developmental Behavioral Interventions (NDBIs) like the Early Start Denver Model embed learning within daily routines and natural play rather than structured repetition.
### The Research and the Controversy
Research shows ABA produces measurable improvements. A 2022 meta-analysis found medium effect sizes for intellectual functioning and adaptive behavior, with greater treatment duration associated with greater improvement.
At the same time, the autistic self-advocacy community has raised serious concerns. A 2018 study found that ABA-exposed participants were 86% more likely to meet PTSD diagnostic criteria, though this study has been criticized for significant methodological limitations. What is clear is that ABA programs vary enormously in quality, and the difference between a neurodiversity-affirming program and a compliance-driven one is the difference between support and harm.
For a detailed framework on evaluating ABA providers, including specific green flags, red flags, and interview questions, read our comprehensive guide on [finding the right therapist for your neurodivergent child](/blog/finding-right-therapist-neurodivergent-child).
### If You Choose ABA, Look For
- Goals focused on communication, independence, and safety rather than making your child appear neurotypical
- A BCBA who directly observes sessions regularly, not just signs paperwork
- Therapists who respect your child's right to say no and to stim
- Child-led, play-based sessions that incorporate your child's interests
- A program willing to reduce hours if your child is thriving rather than defaulting to maximum billable time
## Sensory Integration Therapy: When the World Feels Like Too Much
Sensory integration therapy, formally known as Ayres Sensory Integration (ASI), is a specialized approach typically delivered by occupational therapists that focuses specifically on how the brain processes and responds to sensory information.
### What a Session Actually Looks Like
Sessions take place in sensory-rich environments filled with swings, trampolines, weighted blankets, textured surfaces, and climbing structures. The therapist creates "just right" challenges that push the child slightly beyond their comfort zone while maintaining a sense of safety and control. Your child might swing while catching a ball (combining vestibular and visual-motor input), crawl through a tunnel filled with textured objects, or use a body sock that provides deep pressure while they move.
A 2019 systematic review found that ASI can be considered an evidence-based practice for children with autism ages 4 to 12. The 2025 AOTA systematic review of five randomized controlled trials found "strong evidence" that Ayres Sensory Integration supports autistic children in meeting individualized goals.
### Signs Your Child May Benefit
- Covers their ears in environments that do not bother other children
- Avoids or seeks out specific textures, movements, or sensory experiences with unusual intensity
- Has difficulty with [sensory processing in daily routines](/blog/sensory-processing-daily-routines)
- Seems unable to "filter out" background noise or visual stimulation
- Struggles with motor planning: difficulty learning new physical tasks even after repeated practice
- Appears either constantly under-aroused (sluggish, hard to engage) or over-aroused (anxious, reactive)
## Cognitive Behavioral Therapy: When Anxiety Rides Alongside
Many neurodivergent children experience co-occurring anxiety, and the rates are striking. Research estimates that **40 to 50 percent of autistic children** meet criteria for at least one anxiety disorder. For children with ADHD, the number is similar. When anxiety is present alongside autism or ADHD, it amplifies every other challenge.
### What a Session Actually Looks Like
CBT for neurodivergent children is adapted from standard CBT with visual supports, concrete examples, and modifications for different processing styles. A therapist might use a "worry thermometer" to help a child rate anxiety levels, teach specific [coping strategies](/blog/managing-anxiety-neurodivergent-children-visual-strategies) connected to different anxiety intensities, work through feared situations using graduated exposure, and help a child identify thought patterns that increase anxiety.
In a randomized controlled trial, **69% of autistic adolescents** receiving CBT were classified as treatment responders compared to just 27% in the treatment-as-usual group. CBT has also shown effectiveness for autism combined with OCD, though adaptations specific to the child's processing style are essential.
### When CBT Is the Right Fit
- Your child is approximately age 7 or older (CBT requires some ability to reflect on thoughts and feelings)
- [Anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) is significantly impacting daily functioning, not just occasional worry
- Your child experiences obsessive thoughts or compulsive behaviors
- [Emotional regulation](/blog/emotional-regulation-visual-supports) challenges are driven more by anxious thinking patterns than sensory overload
- Your child can engage in conversation about their internal experience, even if it is difficult
## Play Therapy and DIR/Floortime: Meeting Your Child Where They Are
Play therapy approaches build connection and skills through the child's natural language: play. Rather than teaching skills in structured drills, these methods follow the child's lead and embed developmental goals within interactions the child already enjoys.
### What a Session Actually Looks Like
In DIR/Floortime, developed by Dr. Stanley Greenspan, the therapist or parent literally gets on the floor with the child and enters their world. If your child is lining up cars, the adult joins the line. If your child is spinning, the adult spins alongside them. From that point of connection, the adult gently expands the interaction, adding one more car, introducing a problem to solve, or creating a reason for the child to communicate.
AutPlay Therapy, designed specifically for neurodivergent children ages 3 to 18, celebrates each child's neurological profile rather than trying to change it. Clinical studies show statistically significant improvements in developmental levels compared to baseline, and home-based Floortime has been shown to improve emotive functioning, communication, and daily living skills.
### When Play Therapy Fits Best
- Your child is between ages 3 and 12
- They struggle with social connection and engagement
- They have difficulty with emotional expression and regulation
- Structured therapy environments feel stressful or unproductive for them
- You want an approach that builds relationship first and skills second

## Therapies You Might Not Have Considered
Beyond the most commonly recommended options, several specialized therapies have growing evidence bases for neurodivergent children.
### Feeding Therapy
If your child eats fewer than 20 foods, gags at new textures, or has [mealtime battles](/blog/mealtime-strategies-picky-eating-autism-adhd) that go far beyond typical picky eating, feeding therapy may be the missing piece. Research shows that eating problems affect **51 to 69 percent of autistic children**, five times higher than neurotypical peers.
Feeding therapy typically involves a multidisciplinary team: an OT addressing sensory components, an SLP working on oral-motor skills, a registered dietitian monitoring nutrition, and sometimes a psychologist addressing food-related anxiety. A randomized controlled trial found that behavioral feeding therapy led to significantly increased food acceptance with large effect sizes.
### Music Therapy
Music therapy uses rhythm, melody, and musical interaction to build social, communication, and emotional skills. A meta-analysis of 18 randomized controlled trials involving 1,457 children with autism found improvements in social greeting, joint attention, communication, and peer interactions. It is particularly effective for younger children and those who are minimally verbal, as music often reaches children who are difficult to engage through traditional talk-based approaches.
### Social Skills Groups
If your child understands language and has basic conversation abilities but struggles with the unwritten rules of social interaction, a social skills group may help. A 2025 systematic review found "modest to moderate effectiveness" with effect sizes between 0.28 and 0.60. These groups work best for adolescents and when conducted face-to-face rather than digitally.
### Equine-Assisted Therapy
Working with horses builds social engagement, communication, problem-solving, and daily living skills through an inherently motivating activity. A 2024 systematic review found that equine-assisted therapy "can substantially improve the social and behavioral skills of children with ASD," with particularly notable outcomes for children with Level 1 autism.
## How Visual Supports Tie Everything Together
Here is something every therapist will tell you, regardless of their specialty: the work does not stop when the session ends. The children who make the most progress are the ones whose therapeutic strategies are reinforced consistently at home, at school, and in the community.
This is where [visual supports](/blog/visual-schedules-for-autism) become the connecting thread across all therapy types.
**Visual supports are classified as an evidence-based practice** by the National Professional Development Center on ASD, based on a review of 18 studies. The National Autism Center classifies visual schedules as an "established treatment." Research consistently shows they are most effective when used across settings, which means the same visual structure should appear at home, at school, and in therapy.
If your child's OT is working on [morning routine independence](/blog/morning-routine-tips-adhd), a visual schedule at home reinforces that skill every single day between sessions. If your SLP is building expressive language, visual [first-then boards](/blog/first-then-boards-guide) give your child a tool to practice communication throughout the day. If your child is in ABA working on [transition tolerance](/blog/transition-strategies-autism), a visual routine that previews upcoming changes bridges the gap between clinical sessions and real life.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you build these visual supports using AI-generated images of your child in their actual environments, so the visuals feel personal and recognizable. You can create therapy preparation routines, post-therapy practice schedules, and daily visual plans that reinforce whatever your child's therapy team is working on.
## Insurance and Access: The Practical Reality
Understanding what is covered and what it costs helps you plan strategically.
**All 50 U.S. states** have passed legislation requiring insurance coverage for autism-related therapies, including ABA. The Affordable Care Act requires most individual and small group plans to cover essential health benefits that include many autism therapies. Medicaid's EPSDT benefit covers ABA, speech, occupational, and physical therapy for children under 21 when medically necessary.
However, access remains a challenge. Approximately **30% of children with ASD do not receive any therapeutic services**. Waitlists for ABA average 5.7 months. OT waitlists can stretch up to 2 years in some regions. Speech therapy waitlists average around 6 months.
**What you can do while you wait:**
- Get on multiple waitlists simultaneously and request cancellation list placement
- Ask about telehealth options, which research shows are at least equivalent to in-person services for many therapy types
- Look into your state's early intervention program (IDEA Part C for children under 3)
- Check whether your school district offers related services through an [IEP or 504 Plan](/blog/504-plan-vs-iep-neurodivergent-child)
- Start building visual routines and structure at home, because the research is clear that parent-led interventions produce meaningful gains even before formal therapy begins
## You Do Not Have to Do This Alone
The therapy landscape feels overwhelming because it is overwhelming. There is no single correct path, no one therapy that fixes everything, and no way to know in advance exactly what your child needs. That is not a flaw in the system. It is a reflection of the fact that your child is a complex, unique human being who deserves a plan built specifically for them.
Start with the challenge that disrupts your family's daily life the most. If mornings are a battlefield because getting dressed and eating breakfast takes two hours, an OT evaluation makes sense. If your child cannot tell you when they are hurt or scared, a speech-language evaluation is the priority. If anxiety is so severe that your child cannot leave the house, a psychologist who understands neurodivergent presentations should be your first call.
You do not need to pursue every therapy at once. You do not need to fill every hour of your child's week with appointments. Research actually shows that more therapy hours do not always produce better outcomes. What matters is the right therapy, with the right provider, targeting the right goals, and reinforced consistently at home.
You are already doing the hardest part. You are learning. You are asking questions. You are showing up for your child in a system that was not built for families like yours. That is not nothing. That is everything.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual routines that reinforce therapy goals at home, create preparation schedules for therapy appointments with AI-generated images your child recognizes, track emotional patterns and skill progress across sessions, and share visual data with your child's therapy team so everyone is working from the same plan. Just $6.99/month after your trial, no credit card required upfront.
---
## Eating Out With Your Neurodivergent Child: A Restaurant Survival Guide
Published: 2026-03-02
URL: https://vizyplan.com/blog/eating-out-restaurants-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Restaurants combine every challenge neurodivergent children face into one setting: sensory overload, unfamiliar food, long waits, and social pressure. Research-backed strategies to make dining out possible for your family.
The last time you tried to eat at a restaurant with your child, you lasted eleven minutes. You know because you watched the clock the entire time. The music was too loud. The menu had nothing they would eat. The wait for food felt infinite, and your child was under the table before the appetizers arrived. You paid for food no one touched, carried a screaming child to the car, and sat in the parking lot wondering why you even tried.
You have probably stopped trying. Most families in your situation have. When every restaurant visit ends in a meltdown, a judgment-filled stare from a stranger, or food that goes completely untouched, the logical response is to stop going. And for a while, that works. But it also means your family misses birthday dinners, celebrations with friends, vacations where eating out is unavoidable, and the simple experience of sharing a meal together somewhere that is not your kitchen.
Here is the truth the research supports: dining out with a neurodivergent child is genuinely harder than dining out with a neurotypical child. But it is not impossible. It takes preparation, the right tools, and a willingness to redefine what "success" looks like at a restaurant.
## Why Restaurants Are the Perfect Storm
A restaurant combines nearly every challenge a neurodivergent child faces into a single environment. Understanding why it is so hard is the first step to making it manageable.
### The Sensory Assault
A 2021 scientific review found that **50 to 70 percent of autistic people are hypersensitive to everyday sounds.** A typical busy restaurant operates at 70 to 80 decibels, with clattering dishes, background music, conversations from surrounding tables, and kitchen noise layering on top of each other. For a child whose nervous system is already working overtime to filter [sensory input](/blog/sensory-processing-daily-routines), a restaurant can feel like being trapped inside a noise machine with no off switch.
Research from Frontiers in Psychiatry confirms that autistic children show increased neural resource recruitment in noisy environments, meaning their brains are working significantly harder to process sound than neurotypical peers. Noise-cancelling headphones can reduce surrounding noise by up to 20 decibels, which is often the difference between "I can handle this" and a full meltdown.
But sound is only part of it. Bright overhead lighting, unfamiliar smells from other people's food, the visual chaos of a busy dining room, the texture of an unfamiliar booth seat, the temperature of the air conditioning blowing directly onto their skin. Every sense is being activated simultaneously in an environment your child did not choose and cannot control.
### The Food Problem
Research shows that eating problems affect **51 to 69 percent of autistic children**, which is five times higher than in neurotypical peers. A study published in the Journal of the American Dietetic Association found that food textures are the primary reason for food refusal in autistic children. Some children have food repertoires limited to as few as five foods.
This is not picky eating. For many neurodivergent children, this is a genuine sensory and sometimes medical condition. ARFID (Avoidant Restrictive Food Intake Disorder) co-occurs with autism in an estimated 12.5 to 33.3 percent of cases, according to research reviewed by the Priory Group. Children with ARFID are not being difficult. Their nervous system is rejecting foods that feel unsafe based on texture, smell, temperature, appearance, or even brand.
Now put that child in a restaurant where the menu is unfamiliar, the preparation method is unknown, and the food looks and tastes different from what they eat at home. Even if the restaurant serves chicken nuggets, they are not the same chicken nuggets. The breading is different. The shape is different. The sauce on the side is the wrong color. For a child who depends on food sameness for safety, an unfamiliar restaurant plate can trigger the same fight-or-flight response as any other perceived threat.
### The Waiting Problem
Children with ADHD find waiting excruciating. Research confirms that impulsivity, difficulty staying seated, and restlessness are core features that become especially visible in public settings. The NIMH describes hyperactive-impulsive symptoms as including being unable to stay seated, running or climbing at inappropriate times, and difficulty waiting for their turn.
A restaurant requires waiting at nearly every stage: waiting to be seated, waiting to order, waiting for food, waiting for the check. For a neurotypical child, this is boring. For a child with ADHD, each waiting period is a battle between their brain's need for stimulation and the social expectation to sit still and be quiet. That is a battle they will lose more often than not, and it is not because they are choosing to misbehave.
### The Judgment Factor
Research consistently shows that families of autistic children experience enacted stigma in public settings. Parents worry that their child's behavior is "being attributed to bad parenting, laziness, or lack of motivation," because there is often no visible indicator explaining why the child is struggling. Studies confirm that autism-related stigma negatively impacts family wellbeing, including mental health and social connections.
Many families simply stop eating out to avoid the judgment. That avoidance protects your mental health in the short term, but it also shrinks your family's world over time.

## Before You Go: The Preparation That Changes Everything
The difference between a restaurant meltdown and a manageable meal almost always comes down to what happens before you walk through the door.
### Choose the Right Restaurant
Not all restaurants are created equal for neurodivergent families.
- **Noise level matters most.** Avoid restaurants with hard surfaces, open kitchens, and loud music. Look for places with carpet, booth seating, sound-absorbing materials, and separate dining areas. Some restaurants now offer designated "quiet hours" with reduced music and dimmer lighting.
- **Menu familiarity is critical.** Check the menu online before you go. If your child eats five foods, make sure at least one of them is on the menu, prepared in a way your child will accept. Call ahead and ask if the kitchen can accommodate modifications (plain pasta, unbreaded chicken, specific brands of condiments).
- **Fast service reduces wait time.** For early attempts, consider restaurants where food arrives quickly: fast-casual, counter-service, or family-friendly chains with predictable menus. The goal is not a Michelin-starred experience. The goal is a successful meal outside your home.
- **Time it right.** The Marcus Autism Center specifically recommends visiting during off-peak hours. A Tuesday at 4:30 PM is a fundamentally different sensory experience than a Saturday at 7:00 PM. Less noise, fewer people, faster service, more space.
### Build a Restaurant Social Story
[Social stories](/blog/social-stories-autism-guide) are one of the most evidence-based tools for preparing autistic children for new experiences. Research from the Pennsylvania Autism Self-Advocacy Coalition (PAAutism) and multiple occupational therapy organizations confirm that social stories help children understand restaurant procedures step by step.
Build a simple visual story that walks through the entire sequence:
- "We are going to a restaurant called [name]. Here is a picture of it."
- "We will walk in and wait to be seated. This might take a few minutes."
- "We will sit at a table and look at the menu. I already know what I want to order."
- "We will tell the server what we want. Mom or Dad can order for me if I want."
- "We will wait for our food. I can play with my activity bag while I wait."
- "When the food comes, I will eat. If I do not like it, I have my safe snack."
- "When we are done, we will pay and leave. I did it."
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you create personalized restaurant social stories with AI-generated images that show your child in the actual setting, making the experience concrete and recognizable before you ever leave the house.
### Preview the Menu Together
Do not wait until you are sitting at the table to figure out what your child will eat. That adds decision-making pressure to an already overwhelming environment.
Pull up the menu at home. Let your child look at pictures of the food (many restaurant websites have photos). Decide together what they will order. If nothing on the menu works, plan to bring a safe food from home. The Marcus Autism Center explicitly recommends bringing preferred foods to ensure your child will eat and to minimize disruptive behavior. This is not cheating. This is smart planning.
### Practice at Home
Set up a practice restaurant experience at your kitchen table. Use a printed menu (or make one). Take turns being the server. Practice the sequence: sitting down, looking at the menu, ordering, waiting, eating, and saying thank you. The more familiar the sequence becomes in a safe environment, the less overwhelming it will be in a real one.
Research on graduated exposure for autistic children confirms that systematic desensitization, starting with familiar environments and gradually increasing challenge, is an evidence-based approach to reducing anxiety around new experiences.
## What to Pack: Your Restaurant Survival Kit
Never go to a restaurant empty-handed. Your preparation bag is not optional. It is infrastructure.
### Sensory Tools
- **Noise-cancelling headphones.** Research shows these reduce environmental noise by up to 20 decibels, which can make a busy restaurant tolerable for a sound-sensitive child.
- **Fidget toys or sensory tools.** Whatever helps your child [stay regulated](/blog/emotional-regulation-visual-supports) in other settings will help here too.
- **Sunglasses or a hat with a brim** if your child is sensitive to overhead lighting.
- **A familiar comfort object** that provides grounding.
### Waiting Tools
- **A visual timer.** Research from the Texas SPED Support Autism Toolkit confirms that visual timers reduce anxiety and problem behaviors during waiting periods. Set it when food is ordered so your child can see the time passing rather than experiencing it as endless.
- **A [first-then board](/blog/first-then-boards-guide).** "First we wait, then we eat." "First we eat, then we get dessert." Making the sequence visible gives your child something to hold onto.
- **An activity bag.** Coloring supplies, a small puzzle, a preferred book, or a tablet with headphones. This is not about screen time philosophy. This is about making it through the meal.
### Food Backup
- **Safe snacks from home.** If the restaurant food does not work, your child still eats. Hunger plus sensory overload plus unfamiliar food is a guaranteed meltdown recipe.
- **Familiar utensils or cups** if your child is sensitive to how silverware feels or how a cup's rim touches their lips.
- **Preferred condiments** in small containers. If your child only eats ketchup from a specific brand, bring it.
## During the Meal: Strategies That Actually Work
### Manage the Environment
- **Request a booth** away from the kitchen, bathroom, and entrance. Booths provide physical boundaries that help a child feel contained rather than exposed. The Marcus Autism Center specifically recommends this.
- **Sit near an exit** so you can step outside quickly if your child needs a sensory break without making a scene.
- **Ask for the check when your food arrives.** This is a widely recommended strategy from multiple autism centers. It means the moment your child is done eating, you can leave immediately. No waiting for the server. No extra ten minutes of sitting still while your child is maxed out.
- **Reduce visual clutter** at the table. Move salt shakers, sugar caddies, and table advertisements out of reach if they are distracting or overwhelming.
### Support Your Child Through the Wait
The wait for food is where most restaurant visits fall apart. Your child has been managing sensory input, sitting still, and coping with an unfamiliar environment, and now they have to do all of that while hungry.
- **Set the visual timer** as soon as you order. "Our food will come in about this much time. You can watch the timer."
- **Engage them with the activity bag.** Do not save it as a last resort. Hand it over proactively.
- **Offer specific praise.** "You are doing a great job sitting in your spot and waiting." Research on behavior management confirms that specific positive reinforcement during the desired behavior is more effective than correction after the undesired behavior.
- **Take movement breaks.** If your child needs to move, walk to the bathroom, step outside for thirty seconds, or walk the perimeter of the waiting area. Movement is regulation, not misbehavior.
- **Use the [waiting strategies](/blog/teaching-waiting-patience-neurodivergent-children) you have practiced at home.** If your child has a visual waiting routine, bring it.
### Handle the Food
- **Do not force new foods.** A restaurant is the worst possible environment for food exposure therapy. The goal is for your child to eat something, feel comfortable, and have a positive experience. Expanding food repertoire happens at home in a controlled, low-pressure setting.
- **Let them eat their safe food** without commentary. If they brought crackers from home and that is what they eat while everyone else has pasta, that is a win. They are sitting at a restaurant eating a meal with their family.
- **Modify without apology.** Ask for sauce on the side, plain noodles, bread with nothing on it, a separate plate so foods do not touch. Good restaurants will accommodate. If a server seems annoyed, that is a server problem, not a you problem.
## When It Goes Wrong (Because Sometimes It Will)
Even with perfect preparation, some restaurant visits will not work. That is not failure. That is reality.
### Have an Exit Plan
Before you sit down, decide with your co-parent or partner what the exit signal looks like. Maybe it is a specific word. Maybe it is one parent taking the child outside while the other gets the food boxed up. Whatever it is, agree on it beforehand so you are not negotiating in the middle of a meltdown.
### Do Not Punish the Meltdown
Your child is not melting down because they are being bad. They are melting down because their nervous system is overwhelmed. Punishing a meltdown teaches your child that restaurants are places where they get in trouble, which guarantees they will resist going next time. Instead, calmly leave, validate their experience ("That was really loud in there. I understand"), and try again another day.
### Reframe Success
A successful restaurant visit does not have to mean sitting for a full meal, ordering from the menu, and eating politely for an hour. Success might look like:
- Walking into the restaurant and sitting for five minutes before leaving
- Ordering a drink and staying for ten minutes
- Eating a safe snack from home while the family eats restaurant food
- Making it through the main course before needing to leave
Every positive experience, no matter how short, builds your child's tolerance and confidence. This is graduated exposure in action. Research confirms that systematic, positive exposures over time reduce [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) and increase comfort with new environments.
## Building Toward Longer Meals
Think of restaurant visits as a skill you are building over months, not a test you pass or fail on any single outing.
### The Graduated Exposure Approach
Research on systematic desensitization confirms this approach works for reducing anxiety around new environments:
1. **Week 1-2:** Drive past the restaurant. Talk about it. Look at pictures online. 2. **Week 3-4:** Walk inside the restaurant during off-hours. Look around. Leave. 3. **Week 5-6:** Sit at a table for 5 minutes. Have a drink. Leave. 4. **Week 7-8:** Order one item. Eat quickly. Leave. 5. **Week 9+:** Gradually extend the visit as your child's tolerance builds.
Each step should end positively. If your child gets overwhelmed at step 3, do not push to step 4. Stay at step 3 until it feels comfortable. Then move forward.
### Track What Works
After each restaurant visit, note what went well and what did not. Which seat worked best? What time of day was easiest? Which foods did your child actually eat? What sensory tools helped? [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you track your child's emotions and behaviors across outings, helping you spot patterns that inform your next visit.
### Celebrate Every Win
Your child sat at a restaurant table for twenty minutes and ate crackers from a bag you brought from home while wearing noise-cancelling headphones. That is worth celebrating. Genuinely. Because last month, they would not walk through the door. Progress in neurodivergent parenting does not always look the way the world expects it to look, but it is still progress.
## The Sensory-Friendly Movement Is Growing
The good news is that the restaurant industry is starting to pay attention. Sensory-friendly dining initiatives are expanding across the country:
- Organizations like Autism Eats host sensory-friendly dining events where music is turned off, lights are dimmed, and families eat without judgment.
- Some restaurants now offer "Busy Buddy Sensory Boxes" with earphones and fidget toys for children who need support.
- Staff training programs are helping servers understand how to interact with neurodivergent customers, from speaking in clear and direct language to giving families extra time without hovering.
- The CDC reports that approximately 1 in 31 children are now diagnosed with ASD. The demand for inclusive dining is not niche. It is a growing need that smart restaurants are beginning to address.
You can help this movement by giving feedback. When a restaurant accommodates your family well, tell them. Leave a review mentioning their flexibility. When you find a server who gets it, ask for them by name next time. Building a roster of restaurants that work for your child means you always have a go-to option when your family wants to eat out.
## Your Family Deserves a Seat at the Table
Eating out with a neurodivergent child takes more work than most people will ever understand. It takes planning that starts days before the meal. It takes a bag packed with tools that other families never think about. It takes a willingness to leave a restaurant eleven minutes in and call it a victory because last time it was seven.
But your family deserves to eat at restaurants. Your child deserves the experience of sitting in a booth, picking something from a menu, and watching a server bring food to the table. They deserve birthday dinners and vacation meals and the simple pleasure of not having to eat every single meal at the same kitchen table.
Start small. Pick one restaurant. Build the social story. Pack the bag. Go on a Tuesday at 4:30. Stay for fifteen minutes or stay for an hour. Whatever your child can handle today is enough.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build restaurant social stories with AI-generated visuals your child recognizes, create visual waiting timers and first-then boards for dining out, track what works across restaurant visits to spot patterns, and give your child the preparation that turns stressful meals into family memories. Just $6.99/month after your trial, no credit card required upfront.
---
## Divorce and Two-Household Routines for Neurodivergent Children
Published: 2026-02-27
URL: https://vizyplan.com/blog/divorce-two-household-routines-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Research shows neurodivergent children face unique challenges during divorce, from routine disruption to transition anxiety between homes. Evidence-based strategies for building consistency across two households using visual supports.
You are sitting in your car in the driveway, and your child is in the backseat refusing to unbuckle. It is Sunday evening. The handoff. Again. They were fine ten minutes ago, but the moment you pulled onto this street, the one that leads to their other parent's house, the meltdown started. The screaming. The kicking. The "I want to go home" that splits your heart in two because both houses are supposed to be home now.
This is not a tantrum. This is not defiance. This is a neurodivergent child whose entire nervous system is reacting to a transition that most adults struggle with, and your child is being asked to do it every single week.
If this is your life right now, you need to know something: the research says this is genuinely harder for your family. Not because you are doing it wrong. Because the way divorce typically works was not designed for a child who depends on predictability to feel safe.
## The Numbers Behind the Stress
Divorce rates in families raising neurodivergent children tell a story that most parents already feel in their bones.
Hartley et al. (2010) conducted a landmark longitudinal study of 391 families and found that parents of children with autism have a divorce rate of **23.5%** compared to 13.8% in comparison families. That alone is significant. But the more revealing finding was about timing: in families without autism, divorce risk drops substantially after the child turns eight. In autism families, **the risk stays elevated through adolescence and into adulthood.** The stress does not ease as children grow. It persists.
For ADHD families, the numbers are even more pronounced. A large-scale Danish study by Kvist et al. examined over 172,000 parent couples and found that parents of children diagnosed with ADHD were **75% more likely to divorce** within ten years of the child's birth. Wymbs et al. (2008) at the University of Buffalo found that 22.7% of parents of children with ADHD had divorced by the time the child turned eight, compared to 12.6% in comparison families.
A 2023 literature review published in Children confirmed that ADHD families face a higher divorce risk than ASD families. The researchers believe this is partly because ADHD behavioral challenges tend to emerge later (school age), giving parents less time to adapt, while ASD is typically diagnosed earlier, allowing more time for developing coping strategies and accessing support services.
One thing the research is clear about: the commonly cited statistic that 80% of autism families end in divorce is a myth. Freedman et al. (2013) thoroughly debunked it. The real numbers are concerning enough without inflating them.
And here is what matters most for this conversation: the research consistently shows that "divorce does not appear to be specifically related to a diagnosed pathology of the child, but rather presents itself as a risk factor in certain situations." In other words, the divorce is not your child's fault. It never was.
## Why Divorce Hits Neurodivergent Children Differently
Every child is affected by divorce. But neurodivergent children face a specific set of challenges that amplify the disruption in ways most divorce resources never address.
### Routine Disruption Destabilizes Their Foundation
Insistence on sameness is a core feature of autism in the DSM-5. Research consistently shows that predictable routines serve as a self-regulation strategy for neurodivergent children, reducing anxiety and providing a sense of control in an otherwise overwhelming world. When divorce fractures the daily routine, it does not just inconvenience your child. It removes their primary coping mechanism.
We have data on what happens when routines collapse for autistic children. COVID-19 pandemic research showed that from routine disruption alone (without the added layer of family breakup), **51.9% of autistic children experienced behavioral changes**, 57% showed skill regression, and 61.59% of parents reported increased meltdowns. Now add the emotional weight of divorce on top of that.
### Transitions Between Homes Trigger the Nervous System
Research from Brown University Health confirms that children with ASD are "prone to anxiety, which can impact behavior during times of change or transition." The Indiana University Resource Center for Autism explains that this is driven by "a greater need for predictability, challenges in understanding what activity will be coming next, or difficulty when a pattern of behavior is disrupted."
Every custody handoff is a transition. A big one. Your child is shifting environments, adjusting to different sensory landscapes, recalibrating to potentially different rules and routines, and processing the emotional complexity of leaving one parent to be with the other. For a child who struggles with [transitioning between activities at home](/blog/transition-strategies-autism), moving between two entirely different households is exponentially harder.
### Emotional Processing Takes a Different Path
Children with ADHD "may struggle to manage their emotions, and their parents' divorce might cause them to go through a series of complex emotions causing outbursts or retreat," according to CHADD (Children and Adults with Attention-Deficit/Hyperactivity Disorder). Some children with ADHD fixate on ways they could have prevented the divorce, replaying scenarios endlessly.
Autistic children may react in ways that seem unexpected. Pathfinders for Autism notes that "children with Autism may react in a way that we would deem inappropriate," like laughing, which may reflect relief rather than humor. Some children show no visible reaction initially and then have a delayed response days or weeks later. Do not assume a calm reaction means they are fine. Give space for processing that may not look the way you expect.
## How to Tell Your Neurodivergent Child About the Divorce
The conversation itself requires a different approach than what most divorce guides recommend.
### Use Concrete, Direct Language
Skip the euphemisms. "Mommy and Daddy are going through some changes" is vague and confusing for a concrete thinker. Instead, say exactly what is happening: "Mommy and Daddy are not going to live in the same house anymore. You are going to have two houses. We both love you, and that will never change."
Pathfinders for Autism recommends that "young children may not need information beyond the fact that you and your spouse will be living in different houses." Do not over-explain the reasons for the divorce. That is adult information. Your child needs to know what is changing in their daily life, not why it is changing.
### Focus on What They Care About
Children want to know what is going to happen to their world. Will they still go to the same school? Will they keep their toys? Will the dog come with them? Will they still see Grandma? Address these concrete details directly. For a neurodivergent child, these specific anchors matter more than abstract reassurances about everything being "okay."
### Create a Social Story
[Social stories](/blog/social-stories-autism-guide) are one of the most evidence-based tools for helping autistic children understand new situations. Build a simple story with real photos that walks through the new arrangement:
- "On Monday, Tuesday, and Wednesday, I live at Mommy's house. Mommy's house has my blue room."
- "On Thursday and Friday, I live at Daddy's house. Daddy's house has my toy shelf."
- "On weekends, I go back to Mommy's house. We always follow my schedule."
- "Both houses have my things. Both parents love me."
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you create personalized social stories with AI-generated images that show your child's actual living situations, making the narrative concrete and recognizable rather than generic.
### Prepare for the Unexpected
Your child might have questions you did not anticipate. They might ask the same question repeatedly for weeks. They might seem fine and then melt down at bedtime three days later. They might become more rigid about routines as a way to regain control. All of this is normal processing. Meet them where they are.
Inform your child's therapists, teachers, aides, and other support professionals about the divorce immediately. Behavioral changes at school or in therapy sessions need to be understood in context. Without that information, regression or acting out may be misinterpreted as a new behavioral concern rather than a response to a major life change.
## Choosing a Custody Schedule That Works
Not all custody arrangements are equal when it comes to neurodivergent children. The Children's Hospital of Philadelphia (CHOP) Center for Autism Research provides specific guidance that every co-parenting family should consider.
### Minimize Transitions
CHOP's CAR Autism Roadmap is direct: **alternating nights is not ideal for a child on the autism spectrum** because it involves too many transitions. Every transition is a potential meltdown, a sensory adjustment, and an emotional recalibration. More transitions means more daily stress for your child and for you.
If you share 50/50 custody, research supports longer blocks rather than frequent switches. Trading off every other week, or splitting the week into two blocks (Monday through Thursday with one parent, Friday through Sunday with the other), reduces the total number of transitions your child faces.
### Consider Bird Nesting
Bird nesting is an arrangement where the child stays in one home and the parents rotate in and out. A 2024 study published in ScienceDirect found that "nesting eases the transition to separated family life by preserving the lifestyle to which children are accustomed."
For neurodivergent children, this can be transformative. Your child keeps the same bedroom, the same sensory environment, the same neighborhood sounds, the same route to school. The disruption falls on the adults, who are theoretically more equipped to handle it. If bird nesting is financially or logistically feasible for your family, it eliminates the single biggest source of transition stress.
### Build Transition Rituals
Whatever schedule you choose, create predictable transition rituals that your child can rely on. Research confirms that when transition strategies are used, children with ASD require less time to transition and show more appropriate behavior.
- **A visual countdown.** Three days before a transition, start using a visual countdown. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build countdown routines that show your child exactly how many sleeps until the switch.
- **A consistent handoff routine.** Same time, same place, same sequence. Maybe it is always a hug, then loading the backpack, then waving goodbye from the door. The predictability of the ritual absorbs some of the anxiety of the change.
- **A "landing" routine at each home.** When your child arrives at each house, they follow the same first-fifteen-minutes sequence: put bag in the same spot, check the visual schedule for the evening, have a snack, and settle into a comfort activity. This anchors them in the new environment quickly.
## Building Matching Routines Across Two Homes
This is where the real work happens, and where most families struggle the most. Two households means two sets of rules, two physical environments, two approaches to bedtime, mealtime, and everything in between. Your child needs bridges between these worlds.
### Mirror the Core Routines
You do not need identical homes. You need identical structures. The [morning routine](/blog/morning-routine-tips-adhd) should follow the same sequence at both houses even if the specific bathroom or kitchen is different. The [bedtime routine](/blog/bedtime-routine-autism-adhd) should have the same steps in the same order. Homework time, screen time boundaries, and [meal structures](/blog/mealtime-strategies-picky-eating-autism-adhd) should be as consistent as possible.
This does not mean both parents must agree on every detail. Research from MindNLife UK (2024) suggests focusing on "shared values and limit setting rather than identical rules in each household." The structure matters more than the specifics. If bedtime is 8:00 at one house and 8:30 at the other, that is manageable. If bedtime has four visual steps at one house and no routine at the other, that is a problem.
### Use the Same Visual Schedule System
When both homes use the same visual schedule format, your child carries internal continuity even as the physical environment changes. The schedule becomes the constant.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) is particularly powerful here because both parents can build routines using the same app with the same AI-generated images your child already recognizes. When your child sees the familiar visual steps for their bedtime routine at Dad's house, it activates the same predictability they feel at Mom's house. The app becomes the bridge between two worlds.
### Duplicate Sensory Essentials
Research on comfort objects and autism shows that object attachment serves as a critical self-regulation tool. Many autistic children have intense attachments to specific items that help them cope with transitions and unfamiliar situations. A child whose weighted blanket is at the other house cannot regulate at this house.
Invest in duplicates of the essentials:
- Weighted blanket at both homes
- Same type of noise-cancelling headphones
- Duplicate favorite sensory toys
- Same brand and type of bedding if texture matters
- Same nightlight, same white noise machine
- The same [comfort and regulation tools](/blog/emotional-regulation-visual-supports) available in both spaces
This is not spoiling your child. This is ensuring they have the regulation tools they need regardless of which home they are in.
### Create a Transition Bag
Some items cannot be duplicated: a specific stuffed animal, a favorite shirt, a particular fidget. Designate a "transition bag" that travels with your child between homes. Let your child pack it themselves (with visual checklist support) so they feel ownership over the process. Include:
- Their irreplaceable comfort object
- A family photo from each household
- Their visual schedule (if physical rather than app-based)
- Any sensory tools they currently rely on
- A familiar scent item (same lotion or fabric softener on a small cloth)
## Co-Parenting Communication That Protects Your Child
How you and your co-parent communicate directly impacts your child's adjustment. Research consistently shows that parental conflict is the single strongest predictor of poor child outcomes after divorce, more than the divorce itself.
### Keep It Business-Like
Think of co-parenting communication as a professional collaboration focused on one client: your child. Use email, a shared calendar, or a co-parenting app like OurFamilyWizard or TalkingParents. Keep messages factual, concise, and focused on your child's needs rather than your frustrations with each other.
### Share What Matters
Both parents need to know:
- What happened in therapy this week and any new strategies to practice
- Behavioral changes, meltdowns, or regressions and what triggered them
- What is working in the current routine and what needs adjusting
- Upcoming school events, [IEP meetings](/blog/provider-collaboration-iep-preparation), or medical appointments
- Changes in medication, sleep patterns, or eating habits
- Emotional state at drop-off and pickup
### Never Put Your Child in the Middle
Neurodivergent children are not always able to filter or process the emotional weight of adult conflict. Do not ask your child to relay messages between households. Do not ask how things are "over there." Do not express frustration about the other parent in front of your child. Children with ADHD in particular may absorb and fixate on parental tension, blaming themselves for conflict they cannot control.
## When Your Child Is Struggling
Even with the best planning, some periods will be hard. Watch for signs that your child needs additional support:
- **Increased rigidity.** If your child becomes significantly more inflexible about routines, food, or activities, they may be trying to regain control in a world that feels unpredictable. Rather than fighting the rigidity, add more visual predictability to their day.
- **Regression.** Losing skills they had previously mastered, whether [toileting](/blog/potty-training-autism-adhd-visual-supports), verbal communication, or self-care abilities, is a common response to major stress. This is temporary with consistent support.
- **Sleep disruption.** [Sleep challenges](/blog/sleep-challenges-night-waking-neurodivergent-children) often intensify during periods of transition. Maintaining the exact same bedtime routine at both homes is your strongest tool here.
- **Increased sensory sensitivity.** Stress lowers the threshold for [sensory overwhelm](/blog/sensory-processing-daily-routines). Your child may suddenly struggle with sounds, textures, or environments they previously tolerated.
- **Emotional outbursts at transition times.** If meltdowns consistently happen around custody handoffs, the transition itself needs more support, not less. Add more visual preparation, lengthen the transition ritual, and consider whether the custody schedule needs adjustment.
If these signs persist beyond the initial adjustment period (typically 6 to 12 months), seek support from a therapist who specializes in neurodivergent children and family transitions. Your child may need professional help processing changes they cannot articulate on their own.
## Taking Care of Yourself Through This
You cannot build two stable homes for your child if you are falling apart. Research on [caregiver burnout](/blog/caregiver-burnout-parents-neurodivergent-children) shows that parents of neurodivergent children already carry stress at four times the rate of other parents. Divorce adds an entirely new layer.
Give yourself permission to grieve the family structure you planned. Give yourself permission to feel overwhelmed by the logistics of maintaining consistency across two homes while co-parenting with someone you are separating from. Give yourself permission to not have it all figured out yet.
And then do the next right thing. Build one visual routine. Set up one consistent bedtime. Duplicate one comfort item. Your child does not need perfection. They need predictability, and they need to see that both of their homes are safe places where their needs are understood.
## Start Building the Bridge Today
Your child's world just split in two. Your job, the hardest and most important job, is to build a bridge between those two worlds that your child can cross without falling apart.
Start with one routine. Pick the transition that causes the most stress, whether that is the Sunday evening handoff, the Monday morning adjustment, or the bedtime at the new house, and build a visual sequence your child can follow. Make it concrete. Make it predictable. Make it the same in both homes.
Then build the next one. And the next. One visual step at a time, you are creating the consistency your child depends on, even when the rest of the world is shifting.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build matching visual routines for both households, create social stories that help your child understand their new arrangement, track emotional patterns across transitions, and give your child the predictability they need no matter which home they are in. Just $6.99/month after your trial, no credit card required upfront.
---
## Caring for Your Neurodivergent Child When They Are Sick
Published: 2026-02-26
URL: https://vizyplan.com/blog/caring-for-sick-neurodivergent-child
Category: Daily Routines
Author: Justin Bowman
> Your child is burning up with fever but cannot tell you what hurts. The medicine tastes wrong. The routine is gone. Here is how to care for a sick neurodivergent child when nothing in the parenting playbook applies.
Your child woke up at 2 a.m. crying, but not the way they usually cry. This was different. Guttural. Panicked. You touched their forehead and felt the heat before you even reached for the thermometer. 102.3. Your stomach dropped. Not because a fever is unusual for a kid their age, but because you already knew what was coming. They cannot tell you what hurts. The children's Tylenol tastes "wrong" and they gag every time you try. The thermometer under their tongue triggers a meltdown. And the carefully constructed daily routine that holds their world together just shattered into a thousand pieces on the bedroom floor.
If you are a parent of a neurodivergent child, being sick is not just uncomfortable. It is a full sensory, communication, and regulation crisis layered on top of the illness itself. And the standard parenting advice about fluids, rest, and "call the doctor if it gets worse" was not written for a child who cannot identify where the pain is, refuses every form of medicine, and spirals when the visual schedule on the wall no longer matches what is happening.
You are not overreacting. This is genuinely harder for your family. Research confirms it.
## Why Illness Hits Neurodivergent Children Differently
### They May Not Know They Are Getting Sick
Interoception, sometimes called the body's eighth sense, is the ability to perceive internal signals like hunger, thirst, temperature, and pain. Research shows that many autistic children have significant interoception differences. A 2025 systematic review and meta-analysis in Frontiers in Psychiatry confirmed interoceptive impairments in autistic individuals, meaning your child may not recognize they are getting sick until the fever spikes, the vomiting starts, or the pain becomes severe.
Approximately 50% of autistic individuals also experience alexithymia, the difficulty identifying and describing their own bodily sensations and emotions (Kinnaird, Stewart, & Tchanturia, 2019). A child with alexithymia who has a sore throat may not connect the scratchy feeling to "my throat hurts." They just know something feels wrong and they cannot explain it. That confusion alone can trigger anxiety, which looks like a meltdown, which looks like a behavior problem, when really your child is scared because their body is doing something they do not understand.
### Sensory Processing Makes Every Symptom Worse
Sensory processing differences affect up to 92% of children with autism and are part of the DSM-5 diagnostic criteria. The uncomfortable body sensations of illness, congestion that changes how breathing sounds and feels, a sore throat that alters the texture of swallowing, fever chills that create unpredictable temperature shifts, nausea that introduces a completely unfamiliar internal sensation, are amplified by a nervous system that already struggles to filter and regulate sensory input.
For a child who is already [managing sensory sensitivities](/blog/sensory-processing-daily-routines) on a good day, being sick can feel like every internal alarm system firing at once with no off switch.
### The Routine Is Gone and So Is Their Anchor
Insistence on sameness is a core feature of autism in the DSM-5, and research suggests that predictable routines serve as a self-regulation strategy to reduce anxiety. When illness disrupts the daily schedule, it does not just inconvenience your child. It removes their primary coping mechanism.
COVID-19 pandemic research gave us data on what happens when routines collapse for autistic children: 51.9% experienced behavioral changes including anxiety, irritability, and hyperactivity. 57% showed regression in previously acquired skills. 61.59% of parents reported increased meltdowns. These numbers came from routine disruption alone, without the added burden of physical illness.
Your child is not "being difficult" when they are sick and falling apart. Their body hurts, they cannot explain it, every sensation is amplified, and the structure that normally holds them together is gone. Of course they are melting down.
## The Communication Gap That Scares Every Parent
### They Cannot Tell You What Hurts
This is the part that keeps you up at night. A critical body of research published in Paediatric and Neonatal Pain (Johnson, van Zijl, & Kuyler, 2023) found that autistic children do express pain, but differently than neurotypical children. They may not cry in expected ways, point to the affected area, or seek comfort. Instead, pain often shows up as:
- Increased self-stimulatory behavior or stimming
- Self-injurious behavior like head-banging or biting
- Aggression or irritability that seems disproportionate
- Withdrawal and refusal to engage
- Changes in appetite or sleep
- Loss of previously acquired skills
The dangerous myth that autistic children do not feel pain has been firmly debunked by research (Allely, 2013). They feel everything. They just express it through behavior rather than words.
### What to Watch For
Since your child may not be able to say "my ear hurts" or "my stomach feels bad," you become the interpreter. Watch for:
- **Behavioral changes that do not match the situation:** A sudden increase in meltdowns, aggression, or self-injury that cannot be explained by environmental triggers may indicate pain or illness
- **Touching or guarding a body part:** Repeatedly touching their ear, holding their stomach, or refusing to let you touch a specific area
- **Changes in eating or drinking:** Refusing foods they normally accept, difficulty swallowing, or suddenly refusing to drink
- **Sleep disruption:** Waking at unusual times, difficulty falling asleep, or sleeping significantly more than usual
- **Regression in skills:** Losing [toileting progress](/blog/potty-training-autism-adhd-visual-supports), verbal skills, or self-care abilities during illness
### Build a Communication System Before They Get Sick
Do not wait until your child is feverish and miserable to figure out how to communicate about pain. Build the tools now:
- **Body outline charts:** Print a simple outline of a body and practice having your child point to where something feels different. Do this during calm moments, not just during illness
- **Pain scale visuals:** The Wong-Baker FACES Pain Scale (happy face to crying face) has been validated for use with autistic children. Practice using it regularly so it is familiar when they need it
- **Color-coded feeling cards:** Green means "I feel okay," yellow means "something feels wrong," red means "I feel really bad." Keep these accessible at all times
- **AAC vocabulary:** If your child uses an AAC device, make sure health-related words are programmed and practiced: stomachache, headache, throat hurts, hot, cold, dizzy, nauseous
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build custom visual check-in routines with AI-generated images that match your child's specific communication level, so they have a familiar tool ready when illness strikes.
## The Medicine Battle
Let's talk about the moment every neurodivergent parent dreads: getting medicine into your child.
### Why It Is So Hard
Children with autism and sensory processing differences often have extreme sensitivity to taste, texture, temperature, and smell. Liquid medicine that tastes "fine" to a neurotypical child can be genuinely intolerable. Research from Seattle Children's Autism Center confirms that sensory over-responsivity makes medication administration one of the most challenging aspects of caring for a sick autistic child. Some children also have difficulty with the motor coordination required to swallow on command, and certain textures can trigger a gag reflex.
The data on medication compliance is sobering: less than 46% of children with ADHD were adherent to their regular stimulant medication (Charach et al., 2013). Compliance with unfamiliar sick-day medication is even harder.
### Strategies That Actually Work
- **Chill the medication:** Cold temperatures reduce taste sensitivity. Refrigerate liquid medicines before administering
- **Mix with a strong flavor:** Chocolate pudding, applesauce, or a small amount of juice can mask taste. Check with your pharmacist first to ensure mixing does not affect the medication
- **Ask for alternatives:** Compounding pharmacies can change the flavor, form (liquid to chewable to suppository), or concentration of many medications. Your pediatrician can call this in
- **Use a first-then approach:** "First medicine, then your favorite show" with a [visual first-then board](/blog/first-then-boards-guide) makes the sequence predictable and gives your child something to look forward to
- **Practice when they are well:** Research shows that behavioral training using graduated exposure (starting with small items like sprinkles, working up to pill-sized capsules) achieves 75 to 90% success rates for pill swallowing. Practice this skill during healthy periods
- **Never force:** Coercion leads to increased anxiety, pill aversion, and food selectivity, making future medication compliance even harder
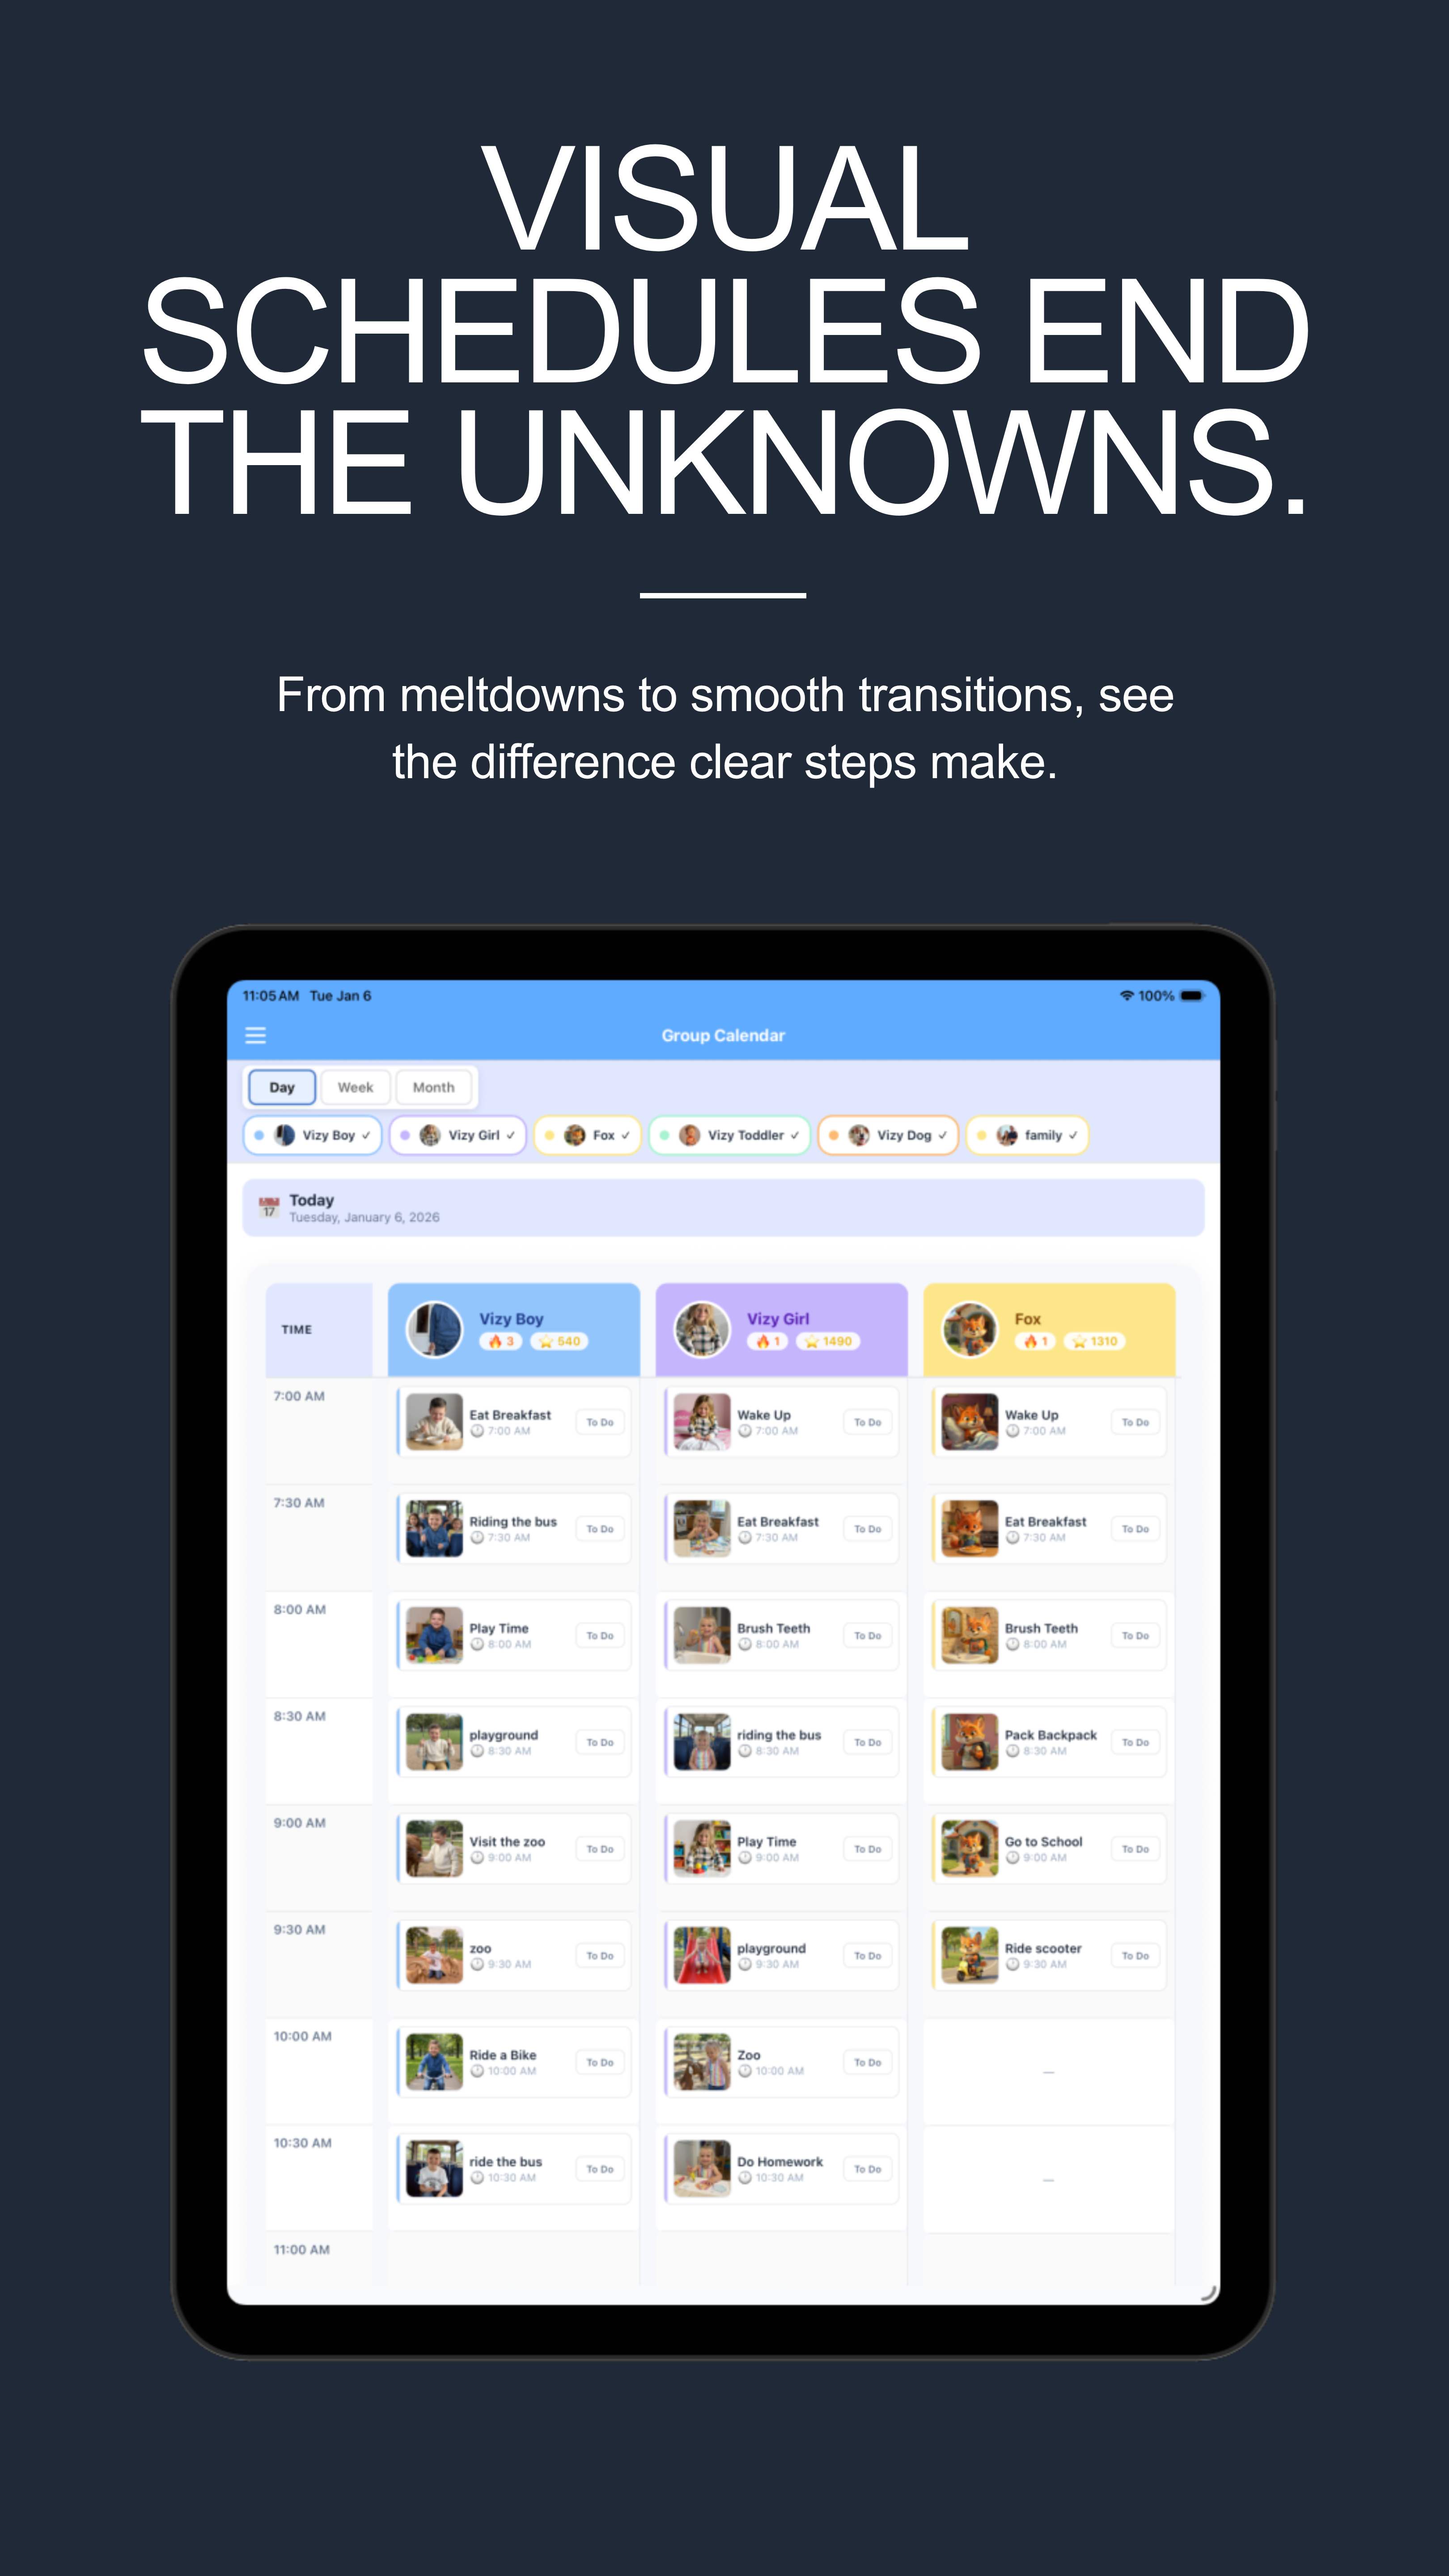
## Building a Sick Day Routine
The best thing you can do when your child is sick is replace the lost routine with a modified one. Not the same routine (they cannot go to school or follow their usual schedule), but a predictable sick-day structure that gives them something to hold onto.
### Create a Sick Day Visual Schedule
Build a simple [visual schedule](/blog/visual-schedules-for-autism) for sick days that includes:
- Wake up and check temperature
- Take medicine
- Drink fluids (offer choices: water, juice, popsicle)
- Rest time (couch with blanket and favorite show)
- Snack (offer safe foods they can tolerate)
- Calm activity (coloring, audiobook, sensory toy)
- Check temperature again
- Medicine
- Bedtime routine (modified but familiar)
Having this posted where your child can see it replaces the anxiety of "I do not know what is happening" with "I can see what comes next." [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) makes it easy to build a modified sick-day routine quickly, using your child's familiar visual format so the schedule feels safe even though the day is different.
### Keep What You Can
Illness does not have to erase everything. Maintain as many familiar elements as possible:
- Same wake and sleep times (adjusted for extra rest)
- Same meals structure (even if the food changes)
- Same [bedtime routine](/blog/bedtime-routine-autism-adhd) elements (shortened if needed)
- Same comfort objects and sensory tools
- Same calm-down strategies from your regular routine
### Modify the Sensory Environment
- Dim the lights if they are sensitive to brightness during illness
- Reduce household noise
- Offer a weighted blanket if they find deep pressure calming
- Allow stimming as a self-regulation strategy without redirecting
- Create a "sick nest" in their preferred space with everything they need within reach
## When to Call the Doctor vs. Go to the ER
This is critical for families where a child cannot verbally describe their symptoms. Because you cannot rely on "tell me where it hurts," you need to monitor observable signs closely.
### Call Your Pediatrician When:
- Fever over 101 that lasts more than 24 hours
- Refusing fluids for more than 6 hours
- Significant behavior change (much more irritable, lethargic, or distressed than a typical sick day)
- Vomiting or diarrhea lasting more than 12 hours
- New onset of self-injurious behavior during illness (this may indicate pain they cannot express)
- Ear pulling, throat guarding, or repeated touching of one body area
### Go to the ER When:
- Fever over 104, or any fever in an infant under 3 months
- Difficulty breathing: fast or labored breathing, nasal flaring, wheezing, chest retractions, or bluish color around lips
- Signs of dehydration: no tears when crying, very little or no urination, extreme sleepiness, dry mouth
- Inconsolable distress that does not respond to any comfort strategy
- Seizure, stiff neck, or rash accompanying fever
- Inability to wake your child or extreme lethargy
**Bring documentation to any medical visit.** Your child's communication style, sensory triggers, what calms them, and a log of symptoms and behavioral changes. Research published in Pediatric Emergency Care emphasizes that healthcare providers need this information to properly assess neurodivergent patients who cannot self-report symptoms. If your child has a [504 plan or IEP](/blog/504-plan-vs-iep-neurodivergent-child), bringing that documentation helps medical staff understand their baseline functioning.
## After the Illness: Getting Back to Normal
### Expect Regression and Do Not Panic
Skills your child had mastered before the illness may temporarily disappear. Toileting accidents, lost verbal skills, refusal to follow previously established routines, increased sensory sensitivity. Research confirms that stressful events and breaks in routine commonly trigger regression in autistic children, but with consistent support, recovery happens. Studies suggest 60% of children recover lost language abilities within 19 months with consistent therapy support.
### Rebuild Gradually
Do not try to snap back to the full routine on day one of recovery. Instead:
- **Day 1-2 of recovery:** Keep the modified sick-day schedule but add one or two regular activities
- **Day 3-4:** Reintroduce the morning and [evening routine](/blog/bedtime-routine-autism-adhd) in full, keep midday flexible
- **Day 5+:** Return to the full schedule with extra sensory breaks built in
- **Week 2:** Remove the extra supports if your child is back to baseline
Use [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) to visually show your child the transition from "sick day schedule" back to "regular schedule" so they can see the familiar routine returning step by step.
### Communicate with School and Therapists
When your child returns to school or therapy, share what happened during the illness: what skills regressed, what behavioral changes you noticed, and what supports helped. This prevents their team from misinterpreting post-illness regression as a new behavioral concern. The [provider collaboration strategies](/blog/provider-collaboration-iep-preparation) you already use for IEP meetings work just as well for post-illness reintegration.
## You Know Your Child Best
Caring for a sick neurodivergent child is exhausting in ways that other parents may never understand. You are not just managing an illness. You are managing an illness inside a body that processes every sensation differently, in a child who cannot tell you what is wrong, while the structure that holds their world together falls apart.
Give yourself permission to do what works, even if it does not look like what the parenting books say. If that means they eat nothing but crackers for three days, that is fine. If the screen time limits go out the window, that is fine. If you sleep on their floor because that is the only way anyone rests, that is fine. Your job during illness is survival and comfort, not optimization.
And when the fever breaks and the color returns to their cheeks and they ask for their favorite breakfast, you will rebuild. One visual schedule step at a time. One familiar routine at a time. Because that is what you do. You hold it all together, even when it feels like it is falling apart.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build sick-day visual schedules in minutes, create pain communication check-ins with AI-generated images your child recognizes, track symptom patterns and behavioral changes across illness and recovery, and transition smoothly back to regular routines. Just $6.99/month after your trial, no credit card required upfront.
---
## Navigating Bullying When Your Child Is Neurodivergent
Published: 2026-02-24
URL: https://vizyplan.com/blog/navigating-bullying-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Your child came home quiet again. No eye contact, no stories about recess. Research shows neurodivergent kids are bullied up to 3 times more often, and the signs look different than you might expect.
Your child climbed into the car after school and did not say a word. No stories about recess. No chatter about their favorite subject. Just silence, a clenched jaw, and eyes fixed on the window. When you asked how their day was, they whispered "fine" in a voice that told you everything was the opposite. Then, fifteen minutes later at home, they exploded. Screaming. Throwing things. Sobbing on the floor over something as small as a sock seam. You knew this was not about the sock. Something happened at school. But when you asked, they could not tell you what.
If this pattern is playing out in your house, you may be watching your neurodivergent child navigate bullying without the words, the social awareness, or the support system to fight back. And the hardest part is that traditional bullying advice ("just tell a teacher" or "ignore them and they will stop") was never designed for kids like yours.
The numbers are staggering. A meta-analysis published in Autism Research found that 44% of youth with autism experience bullying victimization, with 50% facing verbal bullying, 33% physical bullying, and 31% relational bullying (Maiano et al., 2016). A study in JAMA Pediatrics found that 46.3% of adolescents with autism were bullying victims compared to just 10.6% of the general population, making them roughly four times more likely to be targeted (Sterzing et al., 2012). For children with ADHD, a 2024 study using national survey data from over 71,000 youth found that 47% were bullying victims compared to 23% of peers without ADHD (Lebrun-Harris et al., 2024).
Your child is not weak. The system around them was not built to protect how they experience the world.
## Why Neurodivergent Children Are Targeted
Understanding why your child is a target is not about blaming them. It is about recognizing the dynamics so you can disrupt them.
### Social Cue Differences Make Them Vulnerable
Neurodivergent children often process social information differently. They may not recognize sarcasm, detect hidden intentions, or distinguish between friendly teasing and cruelty. Researchers Tony Attwood and Michelle Garnett note that children with autism "may lack the ability to determine if an action or suggestion was deliberate or accidental, whether teasing is friendly or malicious, and the difference between humor and insult." This means a bully can target your child repeatedly, and your child may not even realize it is happening.
### They Often Lack the Peer Protection Network
Bullying thrives on power imbalances. A 2025 systematic review in Frontiers in Psychiatry found that autistic children are perceived as easier targets because they are "often alone and not having a group of friends for protection." When other children move in packs and your child sits alone at lunch reading about dinosaurs, bullies see an opportunity without consequences.
### Masking Does Not Protect Them
Here is something that surprises many parents: research shows that autistic children who demonstrate more social understanding and integration with neurotypical peers are actually at higher risk for bullying, not lower. The effort of [masking their differences](/blog/after-school-routine-transitions-neurodivergent-children) makes them visible enough to be targeted but still different enough to be singled out.
### Their Interests and Behaviors Stand Out
The Kennedy Krieger Institute's Interactive Autism Network survey of nearly 1,200 parents found that autistic students in mainstream settings are "more likely to be ignored, purposely excluded by their peers, victimized for having intense areas of interest, and provoked to exhibit social or emotional responses." That passionate monologue about train schedules that you find endearing? Peers may weaponize it.
## The Types of Bullying You Might Not Recognize
Bullying of neurodivergent children rarely looks like the schoolyard shoving match from movies. It is far more subtle, layered, and deliberately designed to avoid adult detection.
### Fake Friendships and Social Manipulation
This is one of the most devastating forms. A group of kids "befriends" your child, but the friendship is performative. They give instructions that lead to embarrassment. They exploit your child's literal thinking by making promises they never intend to keep. Because your child struggles to read social intentions, they genuinely believe these kids are their friends and defend them even when you suspect something is wrong.
### Provocation Bullying
Peers learn exactly what triggers your child's meltdowns, then deliberately push those buttons. Loud noises near a child with [sensory sensitivities](/blog/sensory-processing-daily-routines). Touching their belongings. Saying the one phrase that causes a visible reaction. When your child melts down, the bully looks innocent and your child gets sent to the office. The ADDitude 2022 survey found that 61% of neurodivergent children had been bullied at school, and a significant portion of that bullying involved deliberate provocation.
### Sensory-Based Targeting
Research shows that sensory processing differences affect 87 to 95% of autistic individuals. Bullies who figure this out may deliberately create sensory overload: banging on desks, spraying strong perfume, flickering lights, or invading personal space. To an outside observer, nothing "happened." To your child, it was an assault on their nervous system.
### Exclusion and Relational Aggression
Being left out of group chats. Whispered conversations that stop when your child approaches. Birthday party invitations that never arrive. The meta-analysis by Maiano et al. found that relational bullying affects roughly one in three autistic youth. This type of bullying leaves no bruises but carves deep wounds in a child who already struggles to build social connections.
### Cyberbullying
The ADDitude survey found that 32% of neurodivergent children experienced bullying through social media and 27% through text messages. Online spaces can be especially dangerous for neurodivergent kids who may not detect tone, sarcasm, or manipulation in written communication.
## The Hidden Signs Your Child Is Being Bullied
Here is what makes bullying detection especially difficult with neurodivergent children: they may not recognize it themselves. Research confirms that neurodivergent children "may not even realize that they are being bullied at first" and "may misunderstand the intentions of their peers." You cannot wait for your child to tell you. You need to watch for the signals.
### The Mask-Then-Crash Pattern
Your child is "fine" at school. Teachers report no issues. But the moment they get in the car or walk through the front door, they fall apart. This behavioral discrepancy between school and home is one of the strongest indicators. Your child is spending every ounce of energy holding it together in an unsafe environment and has nothing left when they reach safety.
### Sudden School Refusal
A study by Ochi et al. (2020) found that bullying was significantly associated with school refusal in both boys and girls with autism. If your child who previously tolerated school suddenly fights going every morning, develops mysterious stomach aches on weekday mornings, or begs to stay home, bullying may be the root cause.
### Regression in Skills
A child who was managing homework independently starts needing constant help. A child who was [building independence](/blog/building-independence-visual-supports) with daily routines suddenly cannot get through their morning checklist. Bullying drains cognitive and emotional resources, and skills that were once automatic start falling apart under the weight of chronic stress.
### Loss of Special Interests
If your child suddenly stops talking about the topic they were obsessed with last week, pay attention. Their special interest may have been mocked or used against them, making it feel unsafe to express joy about the things they love.
### Increased Meltdowns with Invisible Triggers
The meltdown is not about the sock seam, the wrong cup, or the homework assignment. Those are the final straw on a nervous system that has been absorbing social pain all day. When meltdowns increase in frequency and intensity without an obvious environmental change at home, look at what is happening during school hours.
### Physical Symptoms
Unexplained headaches, stomach aches, sleep disruption, and appetite changes. The body keeps score, and chronic stress from bullying manifests physically, especially in children who cannot verbalize what they are experiencing.
## What You Can Do Starting Today
### Build a Reporting System That Works for Your Child
"Just tell a teacher" does not work for a child who cannot identify that bullying is happening, does not know the right words, or fears making the situation worse. Instead, create a visual check-in system. Use a [feelings chart or emotion tracking tool](/blog/tracking-emotions-activities-neurodivergent-children) to help your child communicate their school experience without needing to narrate it. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking features let children identify and log how they felt during different parts of their day, giving you a window into patterns you might otherwise miss.
### Use Social Stories to Build Recognition Skills
[Social stories](/blog/social-stories-autism-guide) are individualized short narratives that help children understand social situations by describing appropriate behavior and providing examples of responses. A 2024 scoping review confirmed their effectiveness for behavior change in autistic children. Create social stories that specifically address:
- The difference between a real friend and someone pretending
- What bullying looks like (not just hitting, but excluding, tricking, and mocking)
- What to do when someone makes you feel bad on purpose
- Safe adults to go to and exactly what to say
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build custom visual stories with AI-generated images that match your child's specific scenarios, so the social stories feel relevant and personal rather than generic.
### Practice with Role-Playing
Research shows that role-playing "provides a safe and controlled environment for practicing interactions." At home, act out scenarios your child might face. Practice responses they can use:
- "I do not want to do that."
- "That is not funny to me."
- "I am going to find my teacher."
- Walking away without responding
Rehearse these until they become automatic. Neurodivergent children often perform better with scripted responses because they do not have to generate language under social pressure.
### Teach Self-Advocacy in Layers
[Self-advocacy](/blog/teaching-self-advocacy-skills-neurodivergent-child) does not start with confronting a bully. It starts with your child being able to say "I need help" to a safe adult. Build skills in stages:
- **Layer 1:** Identify "I feel unsafe" using a visual scale or emotion card
- **Layer 2:** Know who to go to (name specific adults and where to find them)
- **Layer 3:** Use a script: "Someone is being mean to me and I need help"
- **Layer 4:** Self-advocate in an IEP or 504 meeting with parent support
A self-advocacy goal can and should be incorporated into your child's IEP or [504 plan](/blog/504-plan-vs-iep-neurodivergent-child).
### Document Everything
Keep a detailed log of every incident: dates, descriptions, witnesses, what your child reported (or what you observed), and how the school responded. This matters because the ADDitude survey found that only 12% of parents reported the school punished the bullies, and more than 37% said the school never even acknowledged the bullying was happening.
If the school fails to act, a formal letter (sometimes called a Gebser letter) puts the administration on legal notice that they have been informed of the bullying and are now responsible for addressing it.
### Work with Your Child's IEP or 504 Team
Schools are legally required to respond to harassment or bullying of a student with a disability. The PACER Center, a national parent advocacy organization, emphasizes that IEPs and 504 Plans can "help design strategies for bullying prevention that take into consideration the child's disability, their social skills, the environment around them." Push for specific accommodations:
- A designated safe adult your child can go to at any time
- A safe space or quiet room for decompression
- Structured lunch and recess with adult supervision
- Peer education about neurodevelopmental differences
- Regular check-ins between your child and a counselor or social worker
- Anti-bullying measures written explicitly into the IEP
### Push for School-Wide Change
Individual accommodations protect your child, but systemic change protects all neurodivergent students. Research published in Frontiers in Public Health found that anti-bullying programs are most successful when they use multi-component structures that combine social-emotional learning training, parent involvement, and educator workshops.
Ask your school:
- Does the anti-bullying policy specifically address disability-based harassment?
- Have teachers received training to identify bullying of neurodivergent students? (Research shows 69% have not.)
- Are there structured social groups or buddy systems during unstructured times?
- Is there a peer education program that teaches neurotypical students about neurodevelopmental differences?
## Why This Cannot Wait
The long-term impact of bullying on neurodivergent children is more severe than for their neurotypical peers. Lebrun-Harris et al. (2024) found that the increase in anxiety and depression associated with bullying was significantly greater among autistic youth and youth with ADHD compared to non-autistic, non-ADHD youth. The same bullying experience produces a more devastating mental health outcome.
Research from Attwood and Garnett documents that rates of probable PTSD in autistic people range from 32 to 45%, compared to 4 to 4.5% in the general population, and that "among autistic students, social incidents such as ostracizing predict PTSD more strongly than violent events." Bullying is described as "the most common traumatic social experience for autistic individuals."
The stakes are real. Research published in Research in Autism Spectrum Disorders found that autistic youth who were teased were three times more likely to show suicidal behavior. This is not something to "wait and see" about.
And the masking cycle makes it worse. Being bullied drives children to camouflage their autistic traits even harder, which creates additional psychological strain, which makes them more vulnerable, which invites more bullying. Breaking this cycle requires adult intervention.
## You Are Your Child's Best Advocate
If you are reading this because your gut tells you something is wrong at school, trust that instinct. You know your child better than any teacher, administrator, or standardized behavioral checklist. The silence in the car, the meltdowns at home, the regression in skills you worked so hard to build: these are your child's way of telling you they need help, even when they do not have the words.
You do not have to solve this alone. Document what you see. Bring it to the school with specific requests. Connect with other neurodivergent families who understand. And give your child tools to understand, communicate, and protect themselves in a world that was not designed for how they think and feel.
[Managing the anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies) that comes with bullying is a process, not a single conversation. Build it into your daily routine. Check in every day. Make space for the hard feelings. And remind your child, over and over, that who they are is not the problem. How they are being treated is the problem. And you are going to fight like hell to change it.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build social stories that teach your child to recognize unsafe situations, track emotional patterns across the school week to identify when bullying is happening, create self-advocacy scripts with visual supports, and share documentation with your child's school team. Just $6.99/month after your trial, no credit card required upfront.
---
## When Grandparents and Relatives Do Not Understand Your Neurodivergent Child
Published: 2026-02-23
URL: https://vizyplan.com/blog/extended-family-doesnt-understand-neurodivergent-child
Category: Strategies
Author: Justin Bowman
> "He just needs more discipline." Your mother-in-law said it at dinner, again. Here is how to educate extended family, set boundaries without burning bridges, and protect your child when relatives do not get it.
"He just needs more discipline." Your mother-in-law said it at Thanksgiving dinner, loud enough for your child to hear. Your father shook his head and muttered, "There was no autism when I was growing up." Your sister offered helpful advice about how her kids "turned out fine without all these labels." And you sat there, jaw clenched, trying to decide whether to defend your child, educate your family, or simply survive until dessert.
If this scene sounds familiar, you are living one of the loneliest experiences in neurodivergent parenting: loving people who love your child but fundamentally do not understand them. People whose "help" feels like judgment. People whose outdated ideas about behavior, discipline, and diagnosis are slowly eroding your confidence, your patience, and your child's self-image.
You are not overreacting. And you are not alone. A systematic review of 42 studies across 17 countries found that 19 of those studies documented negative attitudes toward autistic individuals from extended family members, including isolation from events, avoidance, and blame directed at parents. This is not a rare family dynamic. It is one of the most common pain points in neurodivergent family life.
## Why They Do Not Get It (And Why It Is Not Entirely Their Fault)
Before we get to the scripts and boundaries, it helps to understand where the disconnect comes from. Not to excuse harmful behavior, but because understanding the root makes your response more effective.
**They grew up in a different world.** Autism was not recognized as a distinct diagnosis until 1980. ADHD was previously labeled "hyperkinetic reaction of childhood." In 1995, roughly 1 in 500 children were diagnosed with autism. Today, the CDC reports approximately 1 in 31 children. This is not because autism is an "epidemic." It reflects broadened diagnostic criteria and increased awareness. But to a grandparent who grew up never hearing these words, it genuinely feels like something new and questionable. People with autism and ADHD in previous generations were often institutionalized, misdiagnosed with intellectual disability, or simply called "odd," "lazy," or "difficult."
**They do not understand invisible disabilities.** The Child Mind Institute identifies three patterns behind family skepticism: they do not understand the diagnosis and dismiss it, they think they know what autism "looks like" and your child does not match their stereotype, or they feel overwhelmed and do not know how to respond. When your child "seems fine" at a family gathering because they are masking, it reinforces the belief that nothing is really wrong.
**They are grieving too.** Autism Speaks describes what grandparents experience as "double grief," mourning both for the grandchild's challenges and for the pain they see their own adult child going through. Common reactions include denial, fear about the future, anger, guilt, confusion, and disappointment. The grandmother who insists your child "will grow out of it" may not be dismissing your experience. She may be trying to protect herself from a reality she is not yet ready to face.
**Cultural factors add complexity.** A systematic review across 17 countries found that in cultures emphasizing family interdependence, there can be both stronger support networks and stronger stigma. In some communities, a diagnosis carries shame that affects the entire family's social standing. In Confucian-influenced cultures, grandparents often hold decision-making authority, and challenging their views risks losing family support entirely.

## The Most Common Things Relatives Say (And What They Actually Mean)
Understanding the belief behind the statement helps you respond to the real issue, not just the words.
**"He just needs more discipline."** What they mean: "I think this is a behavior problem that stricter parenting would solve." What the research says: ADHD is a neurological difference, not a behavior disorder. Punishing a child with ADHD for behaviors rooted in executive function challenges is ineffective and can cause lasting harm. Autistic behaviors like stimming serve a regulatory function and should not be "disciplined away."
**"She will grow out of it."** What they mean: "I am not ready to accept that this is permanent." What the research says: Autism is a lifelong neurodevelopmental condition that begins before birth. ADHD is a brain difference people are born with and have for life. Symptoms may change with intervention, but neither condition is outgrown.
**"You are coddling them."** What they mean: "If you stopped making accommodations, they would learn to cope on their own." What the research says: Accommodations are not weakness. They are the scaffolding that allows neurodivergent children to build skills at their own pace. Removing supports prematurely leads to increased anxiety, behavioral challenges, and loss of trust.
**"There was no autism in my day."** What they mean: "This feels made up or exaggerated." What the research says: Autism has always existed. There is no evidence of an actual change in autism occurrence over the last 70 years, only an increase in knowledge, awareness, and diagnostic capability. In previous generations, these individuals were often hidden away or misdiagnosed.
**"I struggled too, but I turned out OK without any help."** What they mean: "Everyone has challenges. Why does your child need special treatment?" What the research says: Neurodevelopmental differences are not the same as typical childhood struggles. Comparing the two minimizes the genuine neurological challenges your child faces and ignores the decades of research showing that early intervention dramatically improves long-term outcomes.
## How to Have the Conversation
The Child Mind Institute recommends a structured approach to sharing your child's diagnosis with family. This is not a one-time announcement. It is an ongoing conversation.
### Before the Conversation
**Write talking points.** Do not wing it. Write down the two or three most important things you want family members to understand. Keep it focused.
**Practice out loud.** Say your script aloud at least five times before the actual conversation. This reduces the likelihood that emotion will derail your message.
**Never have this discussion in front of the children.** As the Child Mind Institute puts it, "then Aunt Suzie loses face, or the grandparent loses face," and the conversation becomes about ego instead of understanding.
**Choose your timing.** Do not have this conversation at a holiday gathering, during a meltdown, or in front of other family members. Choose a calm, private moment.
### During the Conversation
**Lead with appreciation.** Before anything else, acknowledge how much they mean to your child. "Mom, you know how much Eli loves spending time with you. That relationship is so important to us."
**Focus on observable behaviors.** Point to things they have already noticed rather than leading with the diagnosis label. "You have probably noticed that Eli covers his ears in loud restaurants, or that he gets really upset when plans change unexpectedly. Those things are connected to how his brain processes information."
**Use simple, concrete language.** The Child Mind Institute suggests explaining autism in terms of two main areas: differences in social communication and restricted or repetitive behaviors. For ADHD, focus on strengths alongside challenges: "We learned that Maya has incredible creativity and energy. She also struggles with things like following multi-step instructions and controlling her impulses. That is the ADHD."
**Explain what the diagnosis gives you.** Many family members fear that a label will limit their grandchild. Reframe it: "This diagnosis is not a limitation. It is a roadmap. Now we know why certain things are hard, and we know exactly how to help."
**Invite their involvement.** Rather than just educating, include them. "Would you be open to coming to one of Eli's therapy sessions? The therapist could show you some of the strategies we use." Research shows that grandparents who attend therapy sessions or diagnostic feedback meetings are significantly more likely to accept and support the diagnosis.
## Setting Boundaries Without Burning Bridges
Education is the first step. But when education alone does not change behavior, you need boundaries. The key is being firm enough to protect your child while preserving relationships that matter.
### The "Acknowledge, Boundary, Redirect" Framework
Therapists recommend a three-step approach for common situations:
**Step 1: Acknowledge their concern.** This reduces defensiveness. "I can see that you are worried about how much screen time he gets."
**Step 2: Set a firm but kind boundary.** State your position clearly. "We have worked with his therapist to find a screen time approach that helps him regulate. We need everyone to be consistent with that plan."
**Step 3: Redirect toward something positive.** Move the conversation forward. "What would really help is if you could do a puzzle with him after dinner. He loves that one-on-one time with you."
### Scripts for Common Situations
**When they criticize your parenting approach:** "I know this looks different from how you raised us. We are following guidance from professionals who specialize in how our child's brain works. I need you to trust that we are making informed choices, even when they look unfamiliar."
**When they ignore dietary or sensory accommodations:** "I need you to check with us before giving treats or changing the routine. When his accommodations are not followed, it leads to a meltdown that affects the rest of his day. This is not a preference. It is a need."
**When they compare your child to siblings or cousins:** "Please do not compare the kids. They each have different strengths and challenges. When Eli hears that his cousin did something 'easily' that is hard for him, it affects how he feels about himself."
**When they offer unsolicited advice:** "I appreciate that you care. Right now, we have a [support team](/blog/provider-collaboration-iep-preparation) that is guiding our approach, and consistency is really important. The most helpful thing you can do is follow the strategies we share with you."
**When they refuse to accept the diagnosis:** "I understand this is hard to hear. It was hard for us too. But the diagnosis is real, the professionals who evaluated our child are experts, and the supports we are putting in place are making a measurable difference. I need you to respect that, even if you do not fully understand it yet."
### Non-Negotiable Boundaries
Some boundaries are not up for discussion. Identify yours in advance:
**Physical boundaries:** Respect sensory sensitivities. Do not force hugs, physical contact, or proximity. Maintain safe retreat areas during visits.
**Emotional boundaries:** No criticizing autism-related behaviors in front of the child. No [labeling](/blog/celebrating-neurodivergent-strengths-children) them as "naughty," "weird," or "difficult." No commenting on parenting choices in front of the kids.
**Behavioral boundaries:** No "correcting" stimming. Follow the visual schedule and routine. Respect food accommodations. Check before giving gifts or treats.
## When Family Support Works, It Changes Everything
It is worth fighting for family understanding because the research on what happens when it works is powerful.
A survey of 1,870 grandparents by the Interactive Autism Network found that over 36 percent care for their grandchild at least once a week, 72 percent play some role in treatment decisions, and 90 percent said the experience of navigating the diagnosis together brought them closer to their adult child. In 30 percent of cases, grandparents were the first to notice developmental concerns.
Research consistently demonstrates that extended family support is a significant protective factor for both parents and children. Parents who report higher social support experience lower levels of stress, anxiety, and depression. For children, cohesive family relationships represent key mental health protective factors throughout development.
A psychoeducation study in Stockholm provided 120 grandparents with a six-hour program about autism. Ninety-five percent completed the program, and grandparents significantly increased their knowledge and gained practical skills for supporting both their grandchild and their adult child. Every grandparent benefited equally regardless of gender or whether they were maternal or paternal grandparents. Many grandparents who go through this journey become powerful advocates, educating other family members, writing letters to school districts, and requesting increased support from community resources.
The point is clear: when extended family gets on board, the entire support system becomes stronger. That is worth the uncomfortable conversations.
## Preparing for Holidays and Family Gatherings
Holidays are where all of these dynamics come to a head. The noise, the crowds, the disrupted routine, and the scrutiny of relatives who see your child a few times a year can make gatherings feel impossible.
**Communicate expectations in advance.** Before the event, send a brief message or have a phone call with the host. Share specific needs: "We will need a quiet room available for breaks. Please keep background music low. We will bring food that works for her. We may need to leave early, and we would appreciate no comments about that."
**Create a [visual schedule](/blog/visual-schedules-for-autism) for the gathering.** Show your child what will happen: arrive, say hello, eat, play, quiet break, dessert, go home. Knowing the sequence reduces anxiety for both of you.
**Set a time limit and honor it.** Decide in advance how long you will stay and communicate it. "We will be there from 2 to 4." Leave when you said you would, even if things are going well. Leaving on a positive note is far better than staying until a meltdown forces you out.
**Designate a safe space.** Before you arrive, identify a quiet room where your child can retreat. Stock it with familiar items: headphones, a favorite book, a fidget, a [calming tool](/blog/happy-place-mindfulness-neurodivergent-children). Let your child know it is available and that using it is completely okay.
**Pack familiar food.** Do not rely on the gathering to have foods your child can eat. Bring what works for them. If relatives comment, a simple "this is what works for us" is sufficient.
**Plan recovery time.** The day after a family gathering should be low-demand. [Burnout is real](/blog/caregiver-burnout-parents-neurodivergent-children) after sensory and socially heavy days, for your child and for you.
## When Education Is Not Enough: Knowing When to Step Back
Not every family member will come around. Some will continue to dismiss, criticize, or undermine your parenting no matter how many conversations you have. Knowing when to shift from education to protection is one of the hardest decisions in this journey.
**Watch your child for signs.** If your child becomes withdrawn, anxious, or overly eager to please after visits with certain relatives, pay attention. Stomachaches before family gatherings or silence on the car ride home are signals that should not be ignored.
**Track the pattern.** Ask yourself: after conversations and boundary-setting, is this person showing any progress? Are they reading the resources? Are they trying, even imperfectly? Progress matters more than perfection. But if someone consistently ignores your boundaries and dismisses your child's needs, the relationship is causing more harm than good.
**Use a graduated approach when limiting contact:**
- Supervised visits only, where you are always present to monitor and intervene
- Time-limited contact with clear start and end times
- Reduced frequency of visits
- In serious cases, low contact or no contact
This is not about punishment. It is about protecting your child's emotional safety and your own mental health. You are not obligated to maintain relationships that harm your family, regardless of shared DNA.
If the situation is complex, a family therapist can help you navigate the dynamics without carrying the full emotional weight alone.
## What Your Relatives Can Do Right Now
If you are sharing this article with a family member, here is what they can do today:
- **Ask the parents what would be most helpful.** Do not assume. Ask.
- **Read one resource.** The Autism Speaks Grandparent Guide or CHADD's parent education materials are excellent starting points.
- **Follow the routine.** When you are with the child, follow the same [visual schedule](/blog/visual-schedules-for-autism) and strategies the parents use. Consistency across caregivers makes everything work better. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) makes this simple by letting parents share visual routines and daily schedules with family members, so grandparents and relatives can follow the exact same routine without guessing.
- **Watch your language around the child.** Children hear everything. Comments about their behavior, their diagnosis, or their parents' choices land harder than you think.
- **Show up without judgment.** You do not need to fully understand neurodivergence to be supportive. You just need to trust the parents, follow their lead, and love the child as they are.
## You Are Advocating, Not Apologizing
If you are exhausted from explaining your child to the people who should understand them most, hear this: you are not asking for too much. You are not being "difficult" or "oversensitive." You are [advocating for your child](/blog/teaching-self-advocacy-skills-neurodivergent-child), and that is exactly what good parents do.
The conversations are hard. The boundaries feel uncomfortable. The grief of wanting family support and not getting it is real. But every time you stand up for your child's needs, you are teaching them something profound: that who they are is worth fighting for.
Some family members will come around. Some will surprise you. And some will not change no matter what you do. Your job is not to fix everyone's understanding. Your job is to protect your child, take care of yourself, and build a circle of support that actually supports.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Share visual routines with grandparents and caregivers so everyone follows the same plan, track your child's emotional patterns across different environments, and build the documentation that helps your family team stay on the same page. Just $6.99/month after your trial, no credit card required upfront.
---
## Stuck Inside Again? An OT-Backed Survival Guide for Neurodivergent Families on Bad Weather Days
Published: 2026-02-22
URL: https://vizyplan.com/blog/stuck-inside-bad-weather-activities-neurodivergent-children
Category: Daily Routines
Author: Justin Bowman
> Another snow day. The kids are climbing the walls, screens are the only thing keeping the peace, and you can feel the meltdown building. Here are the OT-approved strategies that actually work when your neurodivergent family is trapped indoors.
The northeast just got buried under another 19 inches of snow. Schools are closed. Roads are impassable. And somewhere in your house, your neurodivergent child is on hour three of being trapped indoors, and you can see the dysregulation building like storm clouds.
Maybe it is not snow where you live. Maybe it is a week of rain, a heat advisory that makes outdoor play dangerous, or a string of bad air quality days. The trigger does not matter. What matters is this: your sensory-seeking child has no outlet, your routine-dependent child has lost their anchor, and you are one sibling argument away from losing yours.
You are not alone. And this is not just cabin fever. For neurodivergent children, being stuck indoors creates a specific set of neurological challenges that require specific solutions. Here is what the research says and what actually works.
## Why Bad Weather Days Are Neurological Emergencies (Not Just Inconveniences)
When neurotypical kids get bored inside, they get restless. When neurodivergent kids lose access to outdoor movement and their daily structure disappears, the impact is neurological.
**Sensory systems lose their primary input source.** Outdoor play naturally provides two types of sensory input that neurodivergent children desperately need: proprioceptive input (the deep pressure and resistance from climbing, jumping, pushing, and pulling) and vestibular input (the balance and spatial awareness from swinging, spinning, and running). Remove those, and you remove the primary way many children regulate their nervous systems. Research shows that sensory processing problems affect 42 to 88 percent of children with autism and approximately 50 to 64 percent of children with ADHD. These are not children who simply prefer being outside. They biologically need the input that outdoor play provides.
**Dopamine production drops.** Physical activity releases both serotonin and dopamine, the same neurotransmitters often deficient in ADHD brains. Through neuromodulatory influences over brain circuits, dopamine and noradrenaline play critical roles in the executive functions that are already impaired in ADHD. When movement stops, the natural dopamine supply that was helping your child focus, regulate, and cope decreases. This is why CHADD has described cabin fever for ADHD children as "torture," and why being stuck inside with little room to move is particularly devastating for hyperactive children.
**Routine disruption creates genuine distress.** A snow day or weather cancellation is, by definition, an unexpected change. For autistic children who rely on predictable routines for emotional safety, unexpected changes feel like the floor dropping out from under them. The distress is not about missing school. It is about losing the structure that makes the world feel manageable.
**Seasonal patterns compound everything.** Research shows that individuals with ADHD traits are more susceptible to seasonal mood variations, with significant associations between ADHD traits and changes in body weight, sleep patterns, and food preferences during winter months. Being stuck inside during an already difficult season amplifies existing challenges.

## The Indoor Sensory Diet: Your Snow Day Blueprint
Occupational therapists use a concept called a "sensory diet," a term coined by OT Patricia Wilbarger, which is a carefully designed, personalized activity plan that provides the sensory input a person needs to stay focused and organized throughout the day. On a bad weather day, you need to intentionally build this diet into the schedule because the outdoor environment is no longer doing it for you.
Think of it as replacing what the playground provides, but inside your house.
### Heavy Work Activities (Proprioceptive Input)
Proprioceptive input occurs when muscles, tendons, and joints receive active input against gravity. This input has a calming, organizing, and regulating effect on the nervous system. When your child is bouncing off the walls, climbing furniture, or getting aggressive with siblings, their body is often seeking this input. Give it to them intentionally.
**Activities that work:**
- Wall push-ups, bear crawls, crab walks, and wheelbarrow walking down the hallway
- Pushing or pulling heavy laundry baskets, furniture, or a wagon loaded with books
- Carrying heavy items like water jugs, stacks of books, or bags of rice from one room to another
- Kneading bread dough, pulling apart therapy putty, or squeezing stress balls
- Building a blanket fort, which involves the heavy lifting, carrying, and draping that provides natural proprioceptive input
- Playing "indoor snowman" by rolling blankets into large balls and stacking them
A meta-analysis of 15 randomized controlled trials found that physical exercise significantly improves attention, executive function, and motor skills in children with ADHD. The optimal session duration was 45 to 60 minutes. You do not need a gym. You need a hallway and some creativity.
### Movement Activities (Vestibular Input)
Vestibular input can either calm children down or alert them depending on the type. Slow, rhythmic movements like rocking have a calming effect. Fast, irregular movements like jumping and spinning cause an excitatory response. Choose based on what your child needs in the moment.
**Calming vestibular activities:**
- Rocking in a rocking chair or therapy swing
- Slow bouncing on a therapy ball
- Gentle swaying while listening to music
**Alerting vestibular activities:**
- Jumping on a mini trampoline
- Dancing to upbeat music
- Somersaults and log rolls on carpet
- Spinning on a sit-and-spin toy or desk chair
**Important safety note:** With spinning, limit to no more than 10 rotations at a time and always spin in both directions. After intense spinning, have your child ground their body by jumping up and down in place with hands on top of their head, pushing down while jumping.
### Tactile Play and Sensory Bins
Sensory bins are containers filled with materials specifically chosen to stimulate the senses. They build comfort with different textures and strengthen fine motor control while providing a calming, focused activity.
**Winter-themed ideas from OT resources:**
- Arctic bins with artificial snow, white rice, or salt and small animal figures
- Hot cocoa sensory bins using instant cocoa powder, brown rice, coffee grounds, and small scoops
- Water beads, kinetic sand, dried pasta, or shaving cream on a tray
- Finger painting with pudding or whipped cream for edible sensory play with younger children
### Indoor Obstacle Courses
Obstacle courses are the gold standard for indoor days because they activate multiple sensory systems simultaneously: tactile, visual, vestibular, and proprioceptive. Research suggests that playful, guided experiences can improve self-regulation skills by up to 40 percent.
**Build one with what you have:**
- Crawl under chairs and tables
- Jump over pillow "lava rocks"
- Balance on a tape line on the floor
- Army crawl through a blanket tunnel
- Toss beanbags or rolled socks into a laundry basket
- End with a crash landing onto a pile of couch cushions
Change the course every few hours to keep it novel. Let your child help design it, which adds executive function practice to the physical benefits.
## Creating a Bad Weather Day Visual Schedule
A [visual schedule](/blog/visual-schedules-for-autism) is your most powerful tool on a stuck-inside day. Without one, the day stretches out as an unstructured void that breeds anxiety for routine-dependent children and chaos for everyone else.
**Build the schedule the night before if you know bad weather is coming.** If it is an unexpected cancellation, create it together first thing in the morning. Include:
- Wake-up routine (keep this consistent even when school is canceled)
- Breakfast
- Active play block (heavy work or obstacle course)
- Quiet creative time (art, building, sensory bins)
- Snack
- Screen time block (defined start and end)
- Movement break (dance party, trampoline, yoga)
- Lunch
- Calm time (weighted blanket, audiobook, quiet play)
- Active play block two
- Free choice time
- Dinner and evening routine
**Leave flexibility gaps.** Build empty spaces between activities so unexpected things can be inserted without the whole structure feeling disrupted. Rigidity in the schedule can cause as much stress as having no schedule at all.
The key insight from OTs is that alternating between high-energy and calming activities throughout the day prevents the buildup of sensory overload that leads to meltdowns. Think of it as a wave pattern: up, down, up, down.
## The Screen Time Strategy (Not a Screen Time Ban)
Here is the truth: on a bad weather day, screens are going to happen. The goal is not elimination. It is intention.
Research from the Child Mind Institute shows that unstructured screen time is consistently associated with worsening ADHD symptoms, particularly inattention and hyperactivity. Children exposed to screens for more than three hours a day show increased language delay, attention deficit, and hyperactivity. But the same research acknowledges that interactive, cognitively engaging digital activities may provide benefits.
**What works:**
- **Define screen time blocks** on the visual schedule with clear start and end times. Use a visual timer so your child can see the countdown rather than being surprised when time is up.
- **Differentiate passive from active screen time.** Watching random YouTube videos is passive. Playing an interactive educational game, video calling a friend, or following along with a kids yoga video is active. Prioritize active.
- **Use screen interests as bridges to hands-on play.** If your child loves a particular show or game, transition screen time into related hands-on activities. Loves dinosaurs on a tablet? Transition to a dinosaur sensory bin. Loves cooking shows? Transition to actually making something in the kitchen.
- **Front-load movement before screens.** A child who has had 30 minutes of heavy work before sitting down for screen time will be more regulated during and after than a child who goes straight from waking up to the iPad.
## When Siblings Are Stuck Together
Confinement amplifies sibling conflict. Two children trapped in the same space with no escape valve and mounting sensory needs is a recipe for battles. Here is how to reduce the friction.
**Create designated spaces.** Even in a small home, each child needs somewhere they can go to be alone. A corner with headphones. A blanket fort. A specific chair that is "theirs." Physical separation is not punishment. It is a sensory strategy.
**Schedule both together time and apart time.** Plan one or two shared activities (building a fort together, a family dance party) and ensure each child also has solo time built into the schedule. Forcing constant togetherness does not build connection. It builds resentment.
**Distribute your attention intentionally.** The number one recommendation from family therapists is to be deliberate about giving each child individual attention during confined days. Even 10 minutes of focused, one-on-one time with each child can dramatically reduce the bids for attention that show up as sibling conflict.
**Equip everyone with [emotional regulation tools](/blog/emotional-regulation-visual-supports).** Deep breathing cards, a calm-down corner, fidgets, and weighted blankets should be accessible to all children, not just the neurodivergent ones. Everyone's regulation is tested on a stuck-inside day.

## Preventing the Meltdown Before It Happens
By the time a meltdown is happening, the window for prevention has closed. The goal is to recognize the early signs and intervene before your child hits the point of no return.
**Watch for the buildup cues:**
- Increasing volume or speed of speech
- Repetitive movements escalating in intensity
- Seeking more and more sensory input (crashing, jumping, spinning) without satisfaction
- Withdrawal or shutting down
- Picking fights with siblings over nothing
- Refusing activities they normally enjoy
**When you see the signs:**
- Offer a [heavy work activity](/blog/sensory-processing-daily-routines) immediately (wall push-ups, carrying something heavy, bear crawls)
- Lower the sensory environment (dim lights, reduce background noise, turn off the TV)
- Offer deep pressure (a firm hug, a weighted blanket, squeezing each limb)
- Use fewer words, not more. Your calm nervous system is more powerful than any script. Co-regulation means your child's mirror neurons pick up on your regulated state and begin to settle their own.
- Move to the [calm-down space](/blog/happy-place-mindfulness-neurodivergent-children) with preferred calming tools
Research shows that deep pressure therapy activates the parasympathetic nervous system, lowering heart rate and reducing anxiety. In studies on weighted blankets, 63 percent of users reported lower anxiety and 78 percent preferred them as a calming tool.
## The Quick-Reference Activity Menu
Print this and stick it on your fridge for the next bad weather day.
**When they need to burn energy:**
- Obstacle course
- Dance party
- Mini trampoline
- Bear crawl races
- Pillow fight (with rules)
- Indoor bowling with water bottles and a rolled-up sock
**When they need to calm down:**
- Weighted blanket time
- Sensory bin play
- Deep breathing with a [visual guide](/blog/emotional-regulation-visual-supports)
- Quiet audiobook in a blanket fort
- Playdough or clay sculpting
- Warm bath with calming scents
**When they need focused engagement:**
- Building with blocks, LEGOs, or magnetic tiles
- Art project with mixed textures
- Cooking or baking together (measuring, stirring, kneading are all heavy work)
- Scavenger hunt with clues around the house
- Sorting or organizing activities (lining up toys by color, building patterns)
**When everyone needs a reset:**
- Family yoga or stretching
- Everyone gets 15 minutes alone in their own space
- Hot cocoa break with a story
- Change the environment (move to a different room, rearrange furniture, open curtains for natural light)
## Building a System That Survives Every Storm
The families who handle bad weather days best are not the ones with the most toys or the biggest houses. They are the ones with a system.
**Create a "stuck inside" visual schedule template** that you can pull out whenever weather hits. Keep it stored with your child's other visual supports so it is ready in minutes, not hours. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you build and save indoor day routines with personalized visuals that your child recognizes and responds to, so the next snow day, rain day, or heat advisory day does not start with panic.
**Stock a sensory activity bin.** Keep a dedicated container with therapy putty, sensory bin fillers, fidgets, a few new coloring books, and a list of heavy work activities. When bad weather hits, pull it out. The novelty of materials they have not seen in a while buys you time and engagement.
**Track what works.** After each stuck-inside day, spend two minutes noting which activities helped and which made things worse. Over time, you build a personalized playbook for your specific child. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) tracks daily routines and [emotional patterns](/blog/tracking-emotions-activities-neurodivergent-children) automatically, so you can look back and see exactly which strategies correlated with calmer days.
**Accept that some days will still be hard.** No amount of preparation makes a full day indoors with a sensory-seeking child easy. But preparation turns impossible into manageable. And manageable is enough.
## You Have More Tools Than You Think
Right now it might feel like you are trapped between a snowstorm and a meltdown with nothing but screens and snacks to get you through. But you have something better: an understanding of what your child's nervous system actually needs.
Every pillow fort is proprioceptive input. Every dance party is vestibular input. Every batch of cookies you bake together is heavy work wrapped in connection. You have been doing sensory activities all along. Now you know why they work and how to be more intentional about it.
The snow will melt. The rain will stop. The heat will break. And when it does, your child will go back outside and get everything their sensory system has been craving. Until then, you have a plan.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build indoor day visual routines, track which sensory strategies work for your child, and have a ready-made plan the next time bad weather keeps your family inside. Just $6.99/month after your trial, no credit card required upfront.
---
## Returning to School After February Break: A Neurodivergent Family Survival Guide
Published: 2026-02-21
URL: https://vizyplan.com/blog/returning-to-school-after-break-neurodivergent-children
Category: Daily Routines
Author: Justin Bowman
> Your child was fine all break. Now school is back and suddenly there are stomachaches, meltdowns, and morning battles. Here is why the return hits neurodivergent kids 47x harder and exactly what to do about it.
February break is over. The pajama days, the flexible wake-up times, the blissful absence of morning rushes. For many families, the return to school feels like flipping a switch from calm to chaos overnight. For families raising neurodivergent children, it can feel more like defusing a bomb.
If your child is melting down at the thought of going back, refusing to get dressed, complaining of stomachaches that mysteriously appear every morning, or clinging to you at drop-off after weeks of independence, you are not imagining how hard this is. The science confirms it.
## Why Vacation-to-School Transitions Hit Neurodivergent Kids Harder
This is not about your child being dramatic or stubborn. There are real neurological reasons why the return to school after a break is uniquely difficult for neurodivergent children.
**Routine disruption registers as a threat.** Autistic children often experience changes in routine not as minor inconveniences but as genuine threats to their sense of safety and security. When the predictable structure of school disappears for a week or two and is replaced by the looser rhythms of home, their nervous system adapts. Switching back is not just annoying. It is destabilizing.
**Executive function takes the biggest hit.** Children with ADHD have executive function skills that lag approximately three years behind their peers, with prefrontal cortex development up to 30 percent behind typical timelines. During school, external scaffolding like bells, teacher direction, visual schedules, and structured transitions compensates for this gap. During break, that scaffolding disappears, and children must rely on the very skills they struggle with most: self-initiating, organizing, and managing time independently.
When school resumes, the executive function "muscle" has been resting. Re-engaging it feels exhausting, and children may appear to have "forgotten" skills they had mastered before the break.
**Sensory systems need time to recalibrate.** After days in the lower-stimulation home environment, walking back into fluorescent-lit hallways, echoing cafeterias, crowded classrooms, and scratchy uniforms can feel overwhelming. Research published in Frontiers in Psychiatry found that 92.7 percent of children experiencing school distress had co-occurring sensory processing difficulties. The sensory assault of school after the relative calm of home is a real neurological challenge, not a behavioral choice.
**Social demands spike overnight.** At home, your child could retreat when overwhelmed, interact on their own terms, and avoid the complex social navigation that school requires. Returning means instant immersion in peer dynamics, group work, unstructured recess, and the constant need to read social cues. For children who find social interaction draining, this is like going from zero to sixty.

## The Numbers Behind School Transition Struggles
Understanding how common these challenges are can help you feel less alone and more confident that your child's reaction is not unusual.
A landmark 2023 study published in Frontiers in Psychiatry surveyed 947 parents of children experiencing school distress and found staggering numbers. Among children with school attendance problems, 92.1 percent were neurodivergent. The study found that 83.4 percent were autistic, 89.4 percent had co-occurring ADHD, and children averaged 3.62 co-occurring neurodivergent conditions. The odds ratio for autistic children experiencing school distress was 46.61, meaning they were nearly 47 times more likely to experience significant school-related distress than neurotypical peers.
Research from the European Education Journal found that school refusal behavior was present in 42.6 percent of autistic students compared to just 7.1 percent of non-autistic students, during a standard 20-day measurement period.
These are not small numbers. If your neurodivergent child struggles with returning to school, they are in the majority of neurodivergent children, not the exception.
## Starting the Transition Before Break Ends
The most effective strategy is not waiting until the morning school resumes. Begin the transition several days before.
**Adjust sleep and wake times gradually.** Sleep is the foundation. If your child has been staying up later and sleeping in during break, begin shifting bedtime and wake time back by 15 minutes every day, starting at least four to five days before school resumes. CHADD recommends making sleep adjustment the first priority because it sets everything else in motion. A child who is sleep-deprived on the first day back starts at a significant disadvantage.
**Re-establish two to three daily anchors.** You do not need to replicate the full school schedule during break. Instead, maintain consistent wake times, mealtimes, and one planned structured activity each day. These anchors keep the internal clock roughly aligned with school time and prevent the complete loss of routine structure.
**Introduce the "Sunday Session."** The evening before school returns, sit down together after dinner and preview the week ahead. Review the schedule visually. Talk through what Monday will look like. This is not a lecture. It is a collaborative conversation that reduces the element of surprise. For older children, let them co-create this preview rather than having it imposed on them.
**Do a practice run.** Wake up at school time, get dressed in school clothes, pack the backpack, and drive to or past the school. You do not have to go inside. The goal is to re-familiarize your child with the full sequence so the first real morning is not the first time they have done it in over a week. Familiarity is a powerful tool for reducing anxiety and giving children a sense of control.
## Visual Supports That Make the Difference
If you have been following this blog, you know that [visual schedules are one of the most evidence-based tools](/blog/visual-schedules-for-autism) for supporting neurodivergent children through daily routines. The return to school is where they truly shine.
**Create a "Back to School" visual countdown.** Starting three to four days before school resumes, use a visual countdown that shows how many days remain. Each day, review what will happen: "Two more home days, then school starts." This removes the surprise element and gives your child time to mentally prepare. Unlike a verbal reminder that disappears as soon as you say it, a visual countdown stays present and available for your child to check whenever anxiety spikes.
**Build a morning routine visual schedule.** The morning of the return is when meltdowns are most likely. A clear, step-by-step visual schedule for the morning, wake up, get dressed, eat breakfast, brush teeth, put on shoes, grab backpack, removes the need for constant verbal prompting that can escalate tension. Post it at your child's eye level and let the schedule do the directing instead of you.
**Use a [social story](/blog/social-stories-autism-guide) about returning to school.** Social stories, developed by Carol Gray in 1990, are an evidence-based intervention particularly effective for autistic children. A back-to-school social story might include: "During the break, I stayed home with my family. Now it is time to go back to school. I might feel happy, nervous, or both. That is okay. My teacher will be there. My classroom will look the same. I know what to do at school." Reading this daily in the days before the return normalizes the mixed emotions and previews the experience.
**Use [first-then boards](/blog/first-then-boards-guide) for the hardest moments.** "First get dressed, then watch one show." "First walk into school, then open your sensory kit." These simple visuals break overwhelming sequences into manageable pairs and give your child something to look forward to on the other side of the hard moment.
## Sensory Preparation: Easing Back Into the School Environment
The [sensory demands of school](/blog/sensory-processing-daily-routines) are one of the biggest barriers to a smooth return. Proactive preparation helps.
**Re-introduce school clothing days before the return.** If your child has been living in soft pajamas and comfortable home clothes, putting on stiff jeans, button shirts, or uniforms on Monday morning adds a sensory battle to an already difficult transition. Start having your child wear school-appropriate clothing at home for a few hours each day during the final days of break. This is not a punishment. Frame it as "practicing" for school.
**Prepare a sensory toolkit for the backpack.** Work with your child to assemble a small kit they can keep in their bag: noise-reducing earplugs or earbuds, a favorite fidget, a chewing tool if they use one, and a comfort item if the school allows it. Knowing they have their tools available reduces anxiety about the sensory environment.
**Use deep pressure before the morning transition.** Before getting dressed and heading out the door, offer deep touch pressure activities: a big squeeze hug, pressing on each limb, rolling a therapy ball over their back, or wearing a compression shirt. Deep pressure activates the parasympathetic nervous system and can reduce the heightened arousal state that makes everything feel more overwhelming.
**Re-familiarize with school sounds.** If your child is sensitive to noise, play sounds typical of a school environment at low volume in the days before the return. Hallway chatter, cafeteria noise, school bells. Gradually increase the volume. This gentle exposure can prevent the shock of full-volume school sounds on day one.
## Age-Specific Strategies
### Toddlers and Preschoolers (Ages 2-5)
Separation anxiety is the primary challenge at this age. The break has reinforced the comfort of being with you, and leaving again can feel like a loss.
- **Practice short separations** in the days before the return. Leave your child with a trusted person for increasing intervals.
- **Create a consistent goodbye ritual** that you will use at drop-off. The same words, the same sequence, every single day. Predictability in the goodbye reduces panic.
- Use **photo-based visual schedules** rather than text. Pictures of their actual classroom, their teacher, their cubby, and their lunchbox make the abstract "going to school" concrete.
- **Role-play the school day** at home. Set up a pretend circle time, pretend snack time, pretend recess. Let your child be the teacher sometimes to give them a sense of control.
### Elementary Age (Ages 6-10)
At this age, the challenge shifts from separation anxiety to re-engaging with academic and social demands.
- **Contact the teacher before school resumes.** A quick email sharing your child's specific challenges after breaks and asking about the first-day plan can help you prepare your child. It also signals to the teacher to watch for signs of struggle.
- **Walk through the school building** if possible before the first day back. Re-familiarize your child with their classroom, locker, cafeteria, and the route between them. Familiarity reduces cognitive load.
- [Social stories](/blog/social-stories-autism-guide) become highly effective at this age. Write one specific to your child's school, teacher, and routine.
- **Build in a decompression period** after school. The first week back is exhausting. Do not schedule activities or homework immediately. Let your child have 30 to 60 minutes of unstructured downtime before any demands.
### Middle School (Ages 11-14)
Social complexity and executive function demands peak during these years.
- **Involve your child in planning the transition.** Adolescents resist having things done to them. Co-create the back-to-school plan together. Ask what they think would help rather than telling them.
- **Remember the executive function lag.** A 12-year-old with ADHD may be functioning at the organizational level of a 9-year-old. Adjust expectations for the first week accordingly. Multiple teachers, locker combinations, class changes, and managing materials across subjects are executive function nightmares after a break.
- **Focus on [self-advocacy skills](/blog/teaching-self-advocacy-skills-neurodivergent-child).** Help your child practice telling teachers "I need a minute" or "Can I take a break?" rather than pushing through until they melt down.
- Use the **"Sunday Session" habit stack**: after a family meal, review the upcoming week together. Attach the planning to an existing routine so it becomes automatic.
## When to Worry: Normal Adjustment vs. School Refusal
Some resistance on the first day or two back is completely normal, even for neurotypical children. Here is how to tell the difference between typical adjustment and something that needs professional attention.
**Normal adjustment looks like:**
- Grumbling, complaining, or dragging feet on the first one to three mornings
- Some clinginess at drop-off that resolves within minutes of entering the classroom
- Tiredness and crankiness after school for the first few days
- Occasional "I do not want to go" statements that respond to encouragement
- Full resolution within one to two weeks
**School refusal warning signs include:**
- Persistent physical complaints like headaches, stomachaches, nausea, or chest pain, especially in the morning, that mysteriously resolve when the child is allowed to stay home
- Panic attacks, severe [anxiety](/blog/managing-anxiety-neurodivergent-children-visual-strategies), or meltdowns specifically triggered by school
- Sleep disruption or nightmares about school
- Behavior that intensifies rather than improves over the first week
- Avoidance behaviors like hiding, refusing to get dressed, or physically clinging to prevent you from leaving
Research from StatPearls and the National Library of Medicine indicates that two to five percent of all school-aged children experience school refusal, with peak vulnerability at ages five to six and ten to eleven. For neurodivergent children, the rates are dramatically higher.
**If your child has not adjusted within two weeks, or if symptoms are escalating rather than resolving, consult your child's pediatrician or therapist.** School refusal is treatable, but early intervention matters. Cognitive behavioral therapy is the primary evidence-based treatment, typically involving 12 to 16 sessions that gradually re-introduce the child to anxiety triggers in manageable steps.

## What to Ask Your Child's School
You are not in this alone. Schools have tools and accommodations that can make the transition smoother, especially if your child has a [504 Plan or IEP](/blog/504-plan-vs-iep-neurodivergent-child).
**Request a gradual re-entry if needed.** Some children benefit from half days or a modified schedule during the first week back. This is a reasonable accommodation that many schools will agree to, especially if it is discussed proactively rather than in crisis mode.
**Ask about the first-day plan.** Good teachers ease students back in with familiar, enjoyable activities rather than jumping straight into demanding academics. Knowing the plan helps you prepare your child and manage expectations.
**Discuss sensory accommodations.** Request that your child have access to their sensory tools from day one. Fidgets, noise-reducing headphones, a weighted lap pad, or access to a calm-down space should not require a meltdown before they are made available.
**Revisit [transition supports](/blog/transition-strategies-autism) in the IEP or 504.** The return from a break is an ideal time to review whether current accommodations are working. Possible additions include advance notice for schedule changes, movement breaks written into the plan, extra time for transitions between activities, a designated safe space, and a reduced homework load during the adjustment period.
**Set up a communication system for the first week.** Ask the teacher to send a brief note or message about how your child's day went. This gives you real-time data to adjust your after-school approach and catch problems early.
## Building Daily Routines That Survive Breaks
The ultimate goal is not just surviving this transition but building routines resilient enough to withstand future disruptions.
**Visual routines create muscle memory.** When a child follows the same visual schedule every school morning for months, the routine becomes automatic. After a break, the visual schedule is still there, serving as an external memory system that re-activates the pattern. Without visual supports, routines live only in working memory, which is exactly the system most affected by breaks.
**Track what works and what does not.** After this transition, document which strategies helped and which did not. What time did your child need to wake up to avoid feeling rushed? Which sensory tools made the biggest difference? Did the social story help? This data is invaluable for the next break. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) makes this tracking effortless with built-in routine monitoring and emotion tracking that captures daily patterns over time, so you are not starting from scratch before every school break.
**Maintain micro-routines during future breaks.** You do not need to replicate the school day during vacation. But keeping two to three anchors, a consistent wake time, a mealtime, and one structured activity, preserves enough routine structure to make the return smoother. Think of it as keeping the engine idling instead of turning it off completely.
**Communicate with teachers before every break return.** A quick email before school resumes saying "Here is what worked last time and here is what we are seeing at home" keeps the school team informed and allows them to prepare accommodations proactively.
## What to Do Right Now
If school starts Monday and you are reading this on Friday or Saturday, here is your action plan:
**Today:**
- Shift bedtime 15 minutes earlier tonight
- Lay out school clothes and have your child try them on briefly
- Create or print a simple [morning routine visual schedule](/blog/morning-routine-tips-adhd)
- Email your child's teacher to let them know about any concerns
**Tomorrow (Sunday):**
- Shift bedtime another 15 minutes earlier
- Do a practice run of the morning routine, full dress rehearsal including the drive
- Read a social story about returning to school
- Have the "Sunday Session" to preview Monday together
- Pack the backpack and sensory toolkit
**Monday morning:**
- Follow the visual schedule, letting it direct the routine instead of your voice
- Offer deep pressure or calming activities before getting dressed
- Keep your own anxiety in check; children read your nervous system
- Use the goodbye ritual at drop-off, keep it brief, warm, and consistent
- Do not linger, even if they cry; a prolonged goodbye often increases distress
- Have a low-demand, comforting after-school plan ready
**All week:**
- Lower expectations for homework and extracurriculars
- Prioritize sleep above everything else
- Offer extra connection time in the evenings
- Check in with the teacher daily
- Track what is working and what needs adjustment in [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) so you have data for the next transition
## You Are Not Failing
If your child is struggling with the return to school, it is not because you let them stay up too late during break. It is not because you were too lenient with screens. It is not because you failed to "prepare" them properly.
Your child's brain processes transitions differently. That is neurology, not a parenting failure. The fact that you are reading this, looking for strategies, and thinking proactively about how to support your child, means you are exactly the parent they need.
Adjustment after breaks is temporary. With the right supports, most children resettle within a few days to two weeks. And with each transition you navigate together, both you and your child build resilience and a toolkit of strategies that make the next one a little easier.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual morning routines, track emotional patterns through school transitions, and keep every strategy that works in one place so the next break return is smoother than this one. Just $6.99/month after your trial, no credit card required upfront.
---
## How to Find the Right Therapist for Your Neurodivergent Child
Published: 2026-02-20
URL: https://vizyplan.com/blog/finding-right-therapist-neurodivergent-child
Category: Strategies
Author: Justin Bowman
> A practical guide to choosing the right OT, SLP, or behavior therapist for your neurodivergent child, including what to look for, what to avoid, questions to ask, and how to know when it is time to switch.
You have the diagnosis. Maybe it is autism, ADHD, or both. Your pediatrician hands you a list of recommended therapists and says something like, "You will want to get on some waitlists." And just like that, you are standing at the beginning of a process that feels overwhelming before it even starts.
Which type of therapy does your child actually need? How do you tell a great therapist from a mediocre one? What questions should you ask? And how do you navigate waitlists that stretch months or even years?
These are not small questions. The therapist your child works with will shape their development, their self-image, and your family's daily life. Getting this right matters. The good news is that you do not need a clinical degree to make an informed choice. You need the right framework.

## Understanding What Each Therapist Does
Before evaluating individual providers, it helps to understand what each type of therapy addresses and when your child might need it.
**Occupational Therapists (OTs)** help children develop skills for daily living. This includes fine motor skills like handwriting and using utensils, sensory processing challenges, self-regulation, dressing, feeding, and play skills. If your child struggles with textures, has difficulty getting dressed independently, melts down in noisy environments, or avoids certain types of touch, an OT is often the first referral. The American Occupational Therapy Association (AOTA) oversees professional standards and continuing education. For more on sensory processing and daily routines, read our guide on [supporting sensory processing needs through daily routines](/blog/sensory-processing-daily-routines).
**Speech-Language Pathologists (SLPs)** work on verbal and non-verbal communication. This goes far beyond "learning to talk." SLPs help children express needs, engage in conversation, understand language, develop social communication skills, and learn to use augmentative and alternative communication (AAC) devices when appropriate. If your child has delayed speech, difficulty following multi-step directions, struggles with social conversation, or is non-speaking, an SLP is essential. The gold-standard credential is ASHA's Certificate of Clinical Competence (CCC-SLP), which requires a master's degree, 1,260 hours of supervised clinical fellowship, and passing the Praxis exam.
**Board Certified Behavior Analysts (BCBAs)** specialize in Applied Behavior Analysis (ABA), focusing on teaching new skills and reducing challenging behaviors through systematic interventions. BCBA certification requires a master's degree plus approximately 1,500 hours of supervised fieldwork and a board exam. However, your child's day-to-day therapy is often delivered by Registered Behavior Technicians (RBTs) who have far less training. Always ask about supervision ratios and how often a BCBA directly observes sessions.
**Physical Therapists (PTs)** address gross motor coordination, balance, muscle tone, and movement planning. Research shows that motor skill difficulty affects up to 83% of children with autism. If your child seems clumsy, avoids playground equipment, has difficulty with stairs, or struggles with ball skills, a PT evaluation is worth pursuing. Studies show individualized physiotherapy programs significantly improve coordination and movement skills, with benefits extending to social participation and educational engagement.
**Developmental-Behavioral Pediatricians** are MDs who complete three additional years of specialty training beyond general pediatrics. They diagnose complex developmental conditions, coordinate care across multiple providers, and can prescribe medication. Waitlists for developmental pediatricians average 9 months to 2 years across the United States.
**Psychologists and Neuropsychologists** conduct comprehensive evaluations, provide cognitive behavioral therapy (CBT), and address co-occurring mental health conditions like anxiety and depression. They perform standardized assessments that help tease apart overlapping conditions, which is particularly valuable when your child's presentation does not fit neatly into one diagnostic category.
## The Waitlist Reality
Before diving into how to evaluate therapists, it is important to understand the access landscape so you can plan strategically.
The numbers are sobering. According to a survey of U.S. autism specialty centers, 61% had diagnostic evaluation wait times longer than 4 months. Twenty-five percent had waitlists exceeding 6 months. Twenty-one percent had waitlists over one year or were closed entirely to new referrals.
For specific therapies, ABA waitlists average 5.7 months. Parents report OT waitlists stretching up to 2 years and speech therapy waitlists of approximately 6 months in many regions.
**What this means practically:**
- Get on multiple waitlists simultaneously. You can always decline when a spot opens if you have already found a good fit.
- Ask to be placed on cancellation lists for earlier openings.
- Consider telehealth options while you wait. A systematic review found that telehealth therapy services were at least equivalent to in-person services for autistic children and their families, particularly for ABA, speech therapy, and parent coaching.
- Look into your state's early intervention program (Part C of IDEA) for children under 3, as these programs often have shorter wait times than private providers.
- Do not wait for a formal diagnosis to request evaluations. Many therapists will evaluate and begin services based on developmental concerns alone.
## What to Look For: Green Flags
Not all therapists are created equal, even among those with the right credentials. Research and clinical best practices point to specific qualities that distinguish effective providers.
**They ask about your child's strengths, not just their deficits.** A therapist who opens the conversation with "What does your child enjoy? What are they good at?" is operating from a strengths-based framework. Research consistently shows that building on existing strengths produces better outcomes than focusing exclusively on remediation.
**They presume competence.** This means assuming your child can learn, think, and understand, even when they cannot yet demonstrate it through typical behaviors. A therapist who talks to your child (not about them as if they are invisible) and adjusts their communication style rather than lowering their expectations is showing this principle in action.
**They involve your child in goal-setting.** Even young children can contribute to identifying what they want to work on. A therapist who asks a 6-year-old, "What is hard for you that you wish was easier?" is building self-awareness and self-advocacy alongside clinical skills. For more on fostering these abilities, read our guide on [teaching self-advocacy skills to your neurodivergent child](/blog/teaching-self-advocacy-skills-neurodivergent-child).
**They use data to track progress.** Good therapists collect systematic data on your child's performance, share it with you regularly, and adjust their approach based on what the data shows. If a therapist cannot tell you, in concrete terms, how your child is progressing toward specific goals, that is a problem.
**They coordinate with your child's other providers and school.** Your child's therapists should communicate with each other and with the school team. A siloed approach, where the OT does not know what the SLP is working on and neither talks to the teacher, wastes everyone's time and limits progress. For a deeper look at provider coordination, see our guide on [collaborating with providers for IEP meetings and therapy](/blog/provider-collaboration-iep-preparation).
**They teach you strategies to use at home.** The most effective therapy extends beyond the session. A therapist who coaches you on how to reinforce skills during daily routines multiplies the impact of every session. Research on parent-mediated interventions shows significant improvements in language development and reduced parenting stress compared to standard community interventions.
**They are transparent about what they do and why.** You should never feel confused about what is happening in your child's sessions. A good therapist explains their methods, welcomes your questions, and adjusts when something is not working.
## What to Watch For: Red Flags
Equally important is knowing when to trust your instincts that something is wrong.
**They insist on eye contact as a therapy goal.** Forcing eye contact is uncomfortable or painful for many autistic individuals. Research from the neurodiversity-affirming therapy community identifies this as a practice rooted in making autistic children appear neurotypical rather than supporting genuine communication.
**They pathologize stimming.** Stimming (self-stimulatory behavior like hand-flapping, rocking, or spinning) serves important regulatory functions. A therapist who treats all stimming as a behavior to eliminate rather than understanding its purpose is operating from an outdated framework. The exception is stimming that causes physical harm, which may need redirection.
**They use a one-size-fits-all approach.** If the therapy plan looks the same for every child on the caseload, it is not individualized. Your child's therapy should reflect their specific profile, interests, sensory needs, and goals.
**They do not honor your child's "no."** Ethical therapists respect autonomy. A child who consistently refuses an activity is communicating something important. The right response is to explore why, not to override their resistance.
**They collect no data or refuse to share progress information.** If you ask how your child is doing and get vague answers like "They are making good progress" without specifics, you have no way to evaluate whether the therapy is actually working.
**They will not coordinate with other providers.** Therapy does not happen in isolation. A provider who refuses to communicate with your child's school, other therapists, or pediatrician is limiting your child's care.
**They make you feel unwelcome in sessions.** You should be able to observe therapy sessions. A therapist who consistently discourages your presence or becomes defensive when you ask questions is not treating you as the equal partner you are in your child's care.
## An Honest Look at the ABA Debate
If your child has been diagnosed with autism, ABA therapy is likely one of the first recommendations you receive. It is also one of the most debated topics in the neurodivergent community, and you deserve a balanced understanding before making decisions.
**What the research shows:** A 2025 meta-analysis in the Review Journal of Autism and Developmental Disorders found that ABA-based interventions showed a large effect size for receptive language skills and moderate effect sizes for adaptive and cognitive skills. A 2022 meta-analysis in BMC Psychiatry found medium effects for intellectual functioning and adaptive behavior. Greater treatment duration and intensity were associated with greater improvements.
**What the criticism says:** The Autistic Self Advocacy Network and many autistic adults argue that traditional ABA focuses too heavily on making autistic children appear "indistinguishable from their peers," which can force harmful masking behaviors. A widely cited 2018 study by Kupferstein in Advances in Autism found that 46% of ABA-exposed respondents met the diagnostic threshold for PTSD, though this study has been criticized for methodological limitations. The U.S. Department of Defense's 2019 report on ABA outcomes for military families found that after one year, 76% of 16,000 participating children showed no measurable change. A 2021 follow-up improved to 57% showing statistically significant improvements.
**Where this leaves you:** Modern, neurodiversity-affirming ABA looks different from the ABA of decades past. The best practitioners use preference assessments, honor the child's choices, incorporate the child's interests, and set goals focused on functional independence and quality of life rather than neurotypical appearance. A 2025 publication in Societies examines how the field is integrating autistic voices into ABA practice.
If you pursue ABA, prioritize providers who:
- Set goals focused on communication, independence, and safety rather than compliance and appearance
- Never use punishment-based techniques
- Respect your child's right to say no and to stim
- Include your child's interests and preferences in every session
- Have a BCBA directly supervising sessions regularly, not just signing off on paperwork
## Questions to Ask When Interviewing Therapists
Treat your first meeting as a mutual interview. You are evaluating them as much as they are assessing your child.
**About their approach:**
- "How do you tailor therapy to each child's individual needs?"
- "What is your experience specifically with children who have autism/ADHD/my child's diagnosis?"
- "How do you incorporate my child's interests into sessions?"
- "How do you handle it when a child refuses an activity?"
- "Are you familiar with the neurodiversity paradigm, and how does it inform your practice?"
**About goals and progress:**
- "How will we set goals together, and will my child be included in that process?"
- "What data do you collect, and how often will you share progress reports with me?"
- "What does a successful outcome look like to you?"
- "How do you decide when to adjust the treatment plan?"
**About qualifications and logistics:**
- "What are your credentials and specialized training?"
- "For ABA: How often does a BCBA directly observe my child's sessions?"
- "Do you coordinate with school teams and other providers?"
- "What insurance do you accept, and what will my out-of-pocket costs be?"
- "Do you have a waitlist, and can I be placed on a cancellation list?"
- "Do you offer telehealth sessions?"
A therapist who welcomes these questions and answers them thoroughly is a good sign. One who becomes defensive or dismissive is telling you something important.
## Navigating Insurance and Costs
Therapy is expensive, and understanding your financial options matters.
**All 50 U.S. states plus D.C. have passed legislation requiring insurance companies to cover ABA therapy for autism.** However, the details vary significantly by state, including age limits, dollar caps, and which therapy types are covered. Check your state's specific mandate through the National Conference of State Legislatures.
**Typical costs without insurance:**
- Intensive ABA therapy: $40,000 to $60,000 per year
- Speech therapy: $100 to $250 per session
- Occupational therapy: $100 to $200 per session
- Families with an autistic child face an average of $4,110 to $6,200 in additional annual medical expenses according to CDC estimates
**Strategies to reduce costs:**
- Verify your insurance covers the specific therapy type and provider before starting
- Ask about sliding scale fees, especially at university-affiliated clinics
- Look into your state's early intervention program (Part C of IDEA) for children under 3, which provides services at no cost or reduced cost
- Check if your school district offers related services through an IEP, as those are provided at no cost to families. For help navigating IEPs, read our guide on [504 Plans vs IEPs](/blog/504-plan-vs-iep-neurodivergent-child)
- Explore nonprofit organizations that offer therapy scholarships or grants
- Consider parent-mediated therapy models. A 2024 study in JMIR Pediatrics found that parent-led ABA can lead to goal achievement and improved clinical outcomes while dramatically reducing costs
## The Case for Starting Early
Research consistently supports earlier intervention, though "early" does not have to mean "intensive."
A 2023 study published in Autism found that toddlers randomized to early social interaction therapy at 18 months showed greater gains in receptive and expressive language than those starting at 27 months. The landmark Early Start Denver Model (ESDM) trial by Dawson et al. showed that children receiving intervention from ages 18 to 30 months gained an average of 17.6 IQ points compared to 7.0 points in the comparison group.
However, only 50% of children with ASD currently receive early intervention services before age 3. Children from higher-income families and non-Hispanic White families are significantly more likely to access early intervention, highlighting a persistent equity gap.
**What this means for you:** If your child is young and you suspect developmental differences, do not wait for a formal diagnosis to seek services. Many early intervention programs and therapists will begin working with your child based on documented developmental concerns. Every month of waiting is a month of missed opportunity during the period when the brain is most responsive to intervention.
If your child is older, do not despair. The brain remains plastic throughout childhood and beyond. Starting therapy at 5, 8, or 12 still produces meaningful improvements. "Earlier is better" does not mean "later is useless."
## How to Know When It Is Working
Progress for neurodivergent children rarely looks like a straight line. Expect cycles of breakthroughs, apparent plateaus, and what may look like setbacks but is often the brain consolidating recent learning.
**Signs therapy is working:**
- Your child is making measurable progress toward specific goals, even if slowly
- Your child shows increased confidence, independence, or willingness to try new things
- Skills practiced in therapy are starting to appear at home and school
- Your child generally enjoys or tolerates sessions (some resistance is normal, consistent dread is not)
- The therapist can show you data demonstrating progress over time
**Signs it might be time to change:**
- No measurable progress toward goals after 3 to 6 months, despite the therapist adjusting their approach
- Your child consistently expresses dread, anxiety, or distress about sessions
- The therapist is not willing to modify strategies based on outcome data
- Communication with you has broken down
- Goals focus on making your child appear neurotypical rather than building functional skills
- You feel dismissed when you raise concerns
Tracking your child's daily patterns outside of therapy sessions helps you evaluate whether gains are generalizing. Tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) let you monitor your child's emotional responses, routine completion, and behavioral patterns over time, giving you concrete evidence to share with therapists and to inform decisions about whether therapy is producing real-world changes.
## Bridging Therapy and Home Life
The most effective therapy happens when strategies are reinforced consistently between sessions. This does not mean turning your home into a clinic. It means building therapeutic goals into the rhythms of daily life.
If your child's OT is working on sensory regulation, you can create a visual routine at home that includes sensory breaks at predictable times. If your SLP is building expressive language, you can practice the same strategies during mealtime conversations or bedtime routines.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps bridge this gap by letting you build personalized visual routines with AI-generated images of your child. When the same structure and visual language appears at home and in therapy, children internalize skills faster and transfer them between settings. You can share routine data with your child's therapy team so everyone is working from the same playbook.
## Where to Start Today
If you are at the beginning of this process:
- **Make a list of your child's biggest daily challenges.** Where do they struggle most? Communication, sensory regulation, motor skills, behavior, daily living skills? This helps you prioritize which therapist to pursue first.
- **Start documenting now.** Track daily patterns, emotional responses, and what strategies help or do not help at home. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) makes this simple with built-in routine tracking and emotion monitoring. This documentation will be invaluable when you meet with potential therapists and when you attend [IEP meetings](/blog/504-plan-vs-iep-neurodivergent-child).
- **Get on waitlists today.** Do not wait until you have "figured everything out." Call multiple providers, get on cancellation lists, and explore telehealth options to start sooner.
- **Trust your instincts.** You know your child better than any professional. A therapist's credentials matter, but so does the feeling you get when you watch them interact with your child. If something feels wrong, it probably is.
Finding the right therapist is not about finding a perfect person. It is about finding someone who sees your child as a whole person, who partners with you as an equal, and who measures success by your child's quality of life, not by how closely they approximate neurotypical behavior.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Track daily routines, monitor emotional patterns, and build the documentation that helps you collaborate effectively with your child's therapy team. Just $6.99/month after your trial, no credit card required upfront.
---
## 504 Plan vs IEP: Which One Does Your Child Need?
Published: 2026-02-19 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/504-plan-vs-iep-neurodivergent-child
Category: Strategies
Author: Justin Bowman
> Understand the real differences between 504 Plans and IEPs, when each is appropriate for children with autism or ADHD, and how to advocate for the right support at school.
Your child just received a diagnosis. Maybe it is autism, ADHD, or both. The school mentions something about a "504" or an "IEP," and suddenly you are navigating a system filled with acronyms, legal language, and meetings that feel high-stakes because they are.
You are not alone. In the 2022-23 school year, 7.5 million students received special education services under IDEA, representing 15% of all public school students, an all-time high according to the National Center for Education Statistics. Meanwhile, the number of students with 504 Plans has nearly quadrupled over the past 15 years. These plans shape your child's daily school experience, and getting the right one matters.
This guide breaks down the real differences between 504 Plans and IEPs, explains when each applies to neurodivergent children, and gives you the tools to advocate confidently at your next school meeting.
## What Is a 504 Plan?
A 504 Plan comes from **Section 504 of the Rehabilitation Act of 1973**, a civil rights law that prohibits discrimination against individuals with disabilities in any program receiving federal funding, including public schools.
The core purpose is **equal access**. If your child has a physical or mental impairment that substantially limits a major life activity (including learning, reading, concentrating, thinking, or communicating), they qualify for accommodations that level the playing field.
A 504 Plan typically includes accommodations like:
- Extended time on tests and assignments
- Preferential seating away from distractions
- Frequent breaks during long tasks
- Modified homework expectations
- Permission to use fidget tools or noise-canceling headphones
- Access to a quiet testing environment
- Copies of class notes or audio recordings of lectures
The key word is **accommodations**. A 504 Plan changes how your child accesses the same curriculum, not what they are taught. The classroom expectations remain the same, but barriers are reduced so your child can meet them.
## What Is an IEP?
An Individualized Education Program comes from the **Individuals with Disabilities Education Act (IDEA)**, a federal funding statute that requires schools to provide a Free Appropriate Public Education (FAPE) to children with disabilities.
An IEP goes significantly further than a 504 Plan. It provides:
- **Specialized instruction** tailored to your child's unique needs
- **Related services** such as speech therapy, occupational therapy, counseling, or behavioral support
- **Modifications** to the curriculum itself (not just how your child accesses it)
- **Measurable annual goals** with regular progress monitoring
- **Transition planning** starting at age 16 for life after high school
- **Extended school year services** if your child regresses during breaks
- **Assistive technology** evaluations and devices
An IEP is a legally binding document. The school must provide everything written in it. If they do not, you have robust due process rights to hold them accountable.
## The Differences That Actually Matter
Understanding the legal nuances helps, but what parents really need to know is how these plans differ in daily practice.
**Eligibility is the first dividing line.** IDEA requires your child to have one of 13 specific disability categories AND need specialized instruction. Section 504 uses a broader definition: any physical or mental impairment that substantially limits a major life activity. A child who does not qualify for an IEP may still qualify for a 504 Plan.
**The level of support is fundamentally different.** A 504 Plan provides accommodations within the general education setting. An IEP can provide specialized instruction, pull-out services, a modified curriculum, and dedicated support staff. If your child needs someone to teach them differently, not just adjust the environment, an IEP is the right tool.
**Legal protections are stronger under an IEP.** IDEA requires written notice before any changes to your child's identification, evaluation, or placement. It gives you the right to request an Independent Educational Evaluation at the school's expense if you disagree with their assessment. It includes a "stay-put" provision that keeps your child in their current placement during disputes. Section 504 offers more limited procedural safeguards.
**Progress monitoring differs dramatically.** An IEP requires measurable annual goals and regular progress reports sent to parents. A 504 Plan has no federal requirement for goals or progress reporting. Without built-in accountability, 504 accommodations can quietly stop being implemented, and you may not know until the next report card.
**The team composition is mandated for IEPs.** An IEP meeting must include at least one general education teacher, one special education teacher, a school psychologist or evaluation specialist, a district representative, and you. A 504 meeting has no mandated attendee list, which sometimes means fewer qualified voices in the room.
## How Autism and ADHD Factor In
The diagnosis your child carries often influences which plan schools recommend, but the decision should be based on need, not diagnosis alone.
**Autism and IEPs.** Autism is one of IDEA's 13 disability categories, which makes IEP eligibility more straightforward. In 2022-23, autism represented 13% of all students in special education, up from 7.8% a decade earlier. Most children with autism who receive formal school support have an IEP because autism typically affects educational performance broadly, across communication, social skills, behavioral regulation, and academics.
However, a medical diagnosis of autism does not automatically qualify your child for an IEP. Research published in PMC found that more than 36% of children with ASD did not receive an autism eligibility classification in special education, often being served under other categories or not at all. The school must determine that autism adversely affects educational performance and that specialized instruction is needed.
**ADHD and the gray area.** ADHD is not a standalone IDEA category. Children with ADHD typically qualify under "Other Health Impairment," though some qualify under Specific Learning Disabilities or Emotional Disturbance. This creates a gray area where schools may push toward a 504 Plan even when an IEP is warranted.
The data is revealing: among students with ADHD who have formal education plans, 42.9% have an IEP while only 13.6% have a 504 Plan, more than a 3-to-1 ratio favoring IEPs (CHADD). Yet research from CHADD also shows that about one in three students with ADHD who would qualify for accommodations receive no formal plan at all.
If your child with ADHD struggles not just with attention but with executive function, emotional regulation, social skills, or academic performance despite accommodations, they likely need the specialized instruction an IEP provides, not just the accommodations of a 504.
## When a 504 Plan Is the Right Choice
A 504 Plan is appropriate when your child:
- Has a disability that substantially limits a major life activity but can succeed in general education with accommodations
- Needs environmental adjustments like extended time, seating changes, or break schedules
- Performs at or near grade level academically but struggles with specific barriers
- Has a condition like anxiety, a medical condition, or mild ADHD that needs accommodations but not specialized instruction
- Was evaluated for an IEP but found ineligible because they do not need specialized instruction
A well-written 504 Plan can be genuinely effective. The problem is not the plan itself but how it is sometimes used: as an easier, less resource-intensive alternative when an IEP is what the child actually needs.
## When an IEP Is the Right Choice
Push for an IEP when your child:
- Needs **specialized instruction**, not just accommodations, to make progress
- Requires **related services** such as speech therapy, occupational therapy, counseling, or behavioral intervention
- Needs **modifications** to the curriculum (reduced assignments, alternate assessments, simplified content)
- Has significant needs that require **measurable goals** and regular progress monitoring
- Has autism, intellectual disability, or significant learning disabilities that affect educational performance
- Is not making adequate progress with a 504 Plan already in place
The U.S. Supreme Court made an important distinction in Endrew F. v. Douglas County (2017): an IEP must be "reasonably calculated to enable a child to make progress appropriate in light of the child's circumstances" and must be "appropriately ambitious." If your child is stagnating, the law is on your side.
## The Evaluation Process
**For an IEP:** Request an evaluation in writing to the school principal or special education coordinator. The school has 60 days (or your state's timeline) to complete a comprehensive evaluation after receiving your consent. They must assess all areas of suspected disability using multiple assessment tools. If eligible, an IEP must be developed within 30 days.
**For a 504 Plan:** The process is less standardized. The school evaluates using information from a variety of sources including grades, teacher reports, medical records, and standardized tests. There is no federally mandated timeline, which means it can move quickly or slowly depending on the school.
**Critical tip:** Always make your request in writing. A verbal request at pickup does not create a paper trail. An email or letter does.
## Common Mistakes Parents Make
Research and advocacy organizations consistently identify several pitfalls.
**Accepting a 504 when an IEP is warranted.** Schools sometimes steer parents toward a 504 Plan because it requires fewer resources and less oversight. If your child needs specialized instruction, accommodations alone will not close the gap. Do not let convenience drive the decision.
**Signing documents at the meeting.** You are not required to agree on the spot. Request time to review proposed plans with your pediatrician, therapist, or an educational advocate. Bring the documents home, read them carefully, and ask questions before signing.
**Not addressing executive function needs.** A peer-reviewed study published in PMC found that while 85% of IEP Present Level statements for students with ADHD described behavioral concerns, less than half had measurable goals targeting those areas. If your child struggles with planning, organization, emotional regulation, or task initiation, those needs belong in the plan.
**Assuming the plan will be automatically implemented.** Plans are only as good as their execution. Check in regularly with teachers. Ask your child how supports are working. Request a mid-year review if something feels off.
**Not updating plans annually.** Your child grows and changes. A strategy that worked in second grade may be irrelevant by fourth grade. Push for plans that evolve with your child's current needs, not carry over the same language year after year.
**Missing assessment bias.** Research shows that girls, children of color, and children from non-English-speaking households are systematically under-identified or misidentified for services. If your child does not fit the stereotypical presentation, you may need to advocate harder for an accurate evaluation.
## How to Advocate Effectively
**Document everything at home.** The strongest IEP meetings start long before the meeting itself. Keep records of your child's daily challenges, the strategies you use at home, and what works or does not work. Tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) can help you track your child's daily routines, emotional patterns, and progress over time, giving you concrete data to bring to school meetings rather than relying on memory alone.
.png)
**Know your rights before walking in.** IDEA mandates that parents are equal members of the IEP team. You are not a guest at this meeting. You are a decision-maker. Resources like Wrightslaw, your state's Parent Training and Information Center (PTI), and organizations like CHADD provide free training on your legal rights.
**Bring outside evaluations.** If your child sees a private therapist, psychologist, or developmental pediatrician, request a written summary of their recommendations. Outside evaluations carry weight in meetings and can highlight needs the school's assessment may have missed.
**Request an Independent Educational Evaluation (IEE) if needed.** Under IDEA, if you disagree with the school's evaluation, you can request an IEE at the school's expense. The school must either fund the evaluation or file for due process to prove their own evaluation was adequate. This is a powerful tool parents often do not know they have.
**Focus on measurable goals.** Vague goals like "improve reading" are hard to enforce. Push for specifics: "By May, the student will read 80 words per minute on grade-level passages with 95% accuracy, as measured by weekly fluency probes." Measurable goals create accountability.
**Use dispute resolution strategically.** If the school is not meeting your child's needs, start with an informal conversation with the special education coordinator. If that fails, request mediation. CADRE data shows that mediation has consistently high agreement rates between families and schools. Save due process hearings as a last resort.
**Involve your child when appropriate.** Research from ERIC found a positive association between student participation in IEP planning and academic outcomes. Even young children can contribute to goal-setting and self-advocacy discussions at a developmentally appropriate level. For more on building these skills, read our guide on [teaching self-advocacy skills to your neurodivergent child](/blog/teaching-self-advocacy-skills-neurodivergent-child).
## Building a Bridge Between Home and School
The most effective education plans do not exist in isolation. They work best when home routines and school supports reinforce each other.
If your child's IEP includes goals around following multi-step directions, you can practice that skill at home using [visual routines in VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) that break daily activities into clear, sequential steps with personalized images of your child. When the same structure appears at home and school, children internalize it faster and transfer skills between settings.
If your child's 504 Plan includes break schedules or emotional regulation accommodations, tracking which strategies work at home helps inform what works at school. When you can tell the team, "We have been tracking his emotional responses for the past month, and here is what we have found," you shift the conversation from opinions to evidence.
For a deeper look at using visual tools in provider meetings, read our guide on [collaborating with providers for IEP meetings and therapy](/blog/provider-collaboration-iep-preparation).
## The Numbers That Should Motivate You
The stakes are real. Students with IEPs are 85% more likely to repeat a grade than peers without disabilities. Students with 504 Plans are 110% more likely (NCLD). Written state complaints about special education services surged to 9,927 in 2023-24, a 79% rise over the 10-year average, according to CADRE.
These numbers reflect a system under strain, but also a system where parents who advocate get results. The families who understand the difference between a 504 and an IEP, who show up prepared with documentation, and who know their legal rights are the ones who secure the supports their children need.
You do not need to be a special education lawyer to be an effective advocate. You need to understand your options, prepare your evidence, and be willing to push when your child's needs are not being met.
## Where to Start Today
If your child does not yet have a formal plan:
- **Request an evaluation in writing** to the school's special education coordinator. Be specific about the areas of concern: academics, behavior, social skills, communication, executive function.
- **Start documenting at home.** Track your child's daily challenges, emotional patterns, and what strategies help. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) makes this simple with built-in routine tracking and emotion monitoring that gives you shareable data for school meetings.
- **Connect with your state's PTI.** Every state has a federally funded Parent Training and Information Center that provides free guidance on special education rights and advocacy strategies.
If your child already has a plan that is not working:
- **Request an IEP or 504 review meeting.** You can request a meeting at any time, not just at the annual review.
- **Bring data.** Report cards, work samples, behavioral logs, and daily routine tracking from tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) help you show the team exactly where supports are falling short.
- **Consider whether the plan type is right.** If your child has a 504 but is not making progress, it may be time to request an IEP evaluation.
Your child deserves a school experience built around their actual needs, not the plan that is easiest for the school to administer. Understanding the difference between a 504 Plan and an IEP is the first step toward making that happen.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Track daily routines, monitor emotional patterns, and build the documentation you need to advocate effectively at your child's next school meeting. Just $6.99/month after your trial, no credit card required upfront.
---
## Caregiver Burnout Is Real: What Every Neurodivergent Parent Needs to Know
Published: 2026-02-18
URL: https://vizyplan.com/blog/caregiver-burnout-parents-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Parents of neurodivergent children experience stress at 4x the rate of other parents. Research-backed strategies to recognize burnout, protect your wellbeing, and build systems that support your whole family.
You love your child fiercely. You show up at every therapy appointment, navigate every meltdown with patience you did not know you had, and spend hours researching strategies that might help. You have become your child's loudest advocate, their safest person, and their daily anchor.
And you are exhausted.
Not the kind of tired that a good night's sleep fixes. The kind that sits in your bones, clouds your thinking, and makes you wonder if you are doing any of this well enough. If this sounds familiar, you are not alone, and what you are feeling has a name: caregiver burnout.
## The Numbers Are Staggering
Research paints a clear picture of just how widespread parental burnout is among families raising neurodivergent children.
A landmark meta-analysis by Hayes and Watson (2013) found that parents of autistic children experience stress at **four times the rate** of parents raising neurotypical children. That is not a small difference. It is a fundamentally different experience of parenting.
Kiami and Goodgold (2017) found that parental stress reaches **clinically significant levels in 77% of parents** of children with autism. When you add ADHD to the mix, stress levels climb even higher. Research shows the combined autism and ADHD group reports the highest parental stress of any diagnostic category.
A 42-country study by Roskam and Mikolajczak (2021) found that parental burnout affects roughly 8.9% of the general population in the United States. Among parents of children with special needs, that number is dramatically higher, with some studies showing more than half of caregivers experiencing measurable caregiver burden.
These are not just statistics. They represent millions of parents running on empty.
## What Caregiver Burnout Actually Looks Like
Researchers Mikolajczak and Roskam at the University of Louvain defined parental burnout as a specific syndrome with three dimensions:
- **Overwhelming exhaustion** tied to your parenting role, not just general tiredness but a deep depletion that does not recover with rest
- **Emotional distancing** from your children, feeling detached, going through the motions, or losing the warmth you used to feel
- **A sense of parental ineffectiveness**, the persistent feeling that nothing you do is enough or that you are failing despite your best efforts
This is not the same as having a bad day or feeling stressed about a difficult week. Burnout is a progressive condition. Roskam and Mikolajczak's longitudinal research (2021) established that it develops gradually, with emotional exhaustion as the entry point. Without intervention, it deepens over time.
## It Is Not Just in Your Head
Here is something that validates what many parents already sense: the stress is physiological, not just psychological.
Research shows that parents of children with autism or ADHD have significantly elevated levels of **cortisol** (the stress hormone) and **C-reactive protein**, a biomarker linked to cardiovascular disease, diabetes, and chronic inflammation. Studies on mothers of adolescents and adults on the autism spectrum found cortisol patterns characteristic of chronic stress, similar to patterns observed in combat veterans and individuals with PTSD.
Your body is keeping score. The constant hypervigilance, the daily problem-solving, the emotional labor of navigating a world not designed for your child, it all registers physically.
## The Ripple Effect on Your Family
Burnout does not stay contained. Research consistently shows that parent wellbeing and child outcomes are deeply interconnected.
**When parents are less stressed, children do better.** Studies on family-mediated interventions found that when caregivers receive support and stress reduction, their children show measurable improvements in social behaviors and emotional regulation.
**The stress-behavior feedback loop is real.** Higher parental stress is associated with increased child behavioral difficulties, which in turn increases parental stress. It becomes a cycle that feeds itself. Breaking that cycle at the parent level creates positive changes for the entire family.
**Relationships feel the strain.** Parents of children with autism face a divorce rate of approximately 23.5%, compared to 13.8% for parents of children without disabilities, according to Hartley et al. (2010). Unlike comparison families where divorce risk decreases as children grow, this elevated risk persists through adolescence and adulthood due to prolonged caregiving demands.
**Work suffers too.** Research indicates that approximately 67% of caregivers find it hard to balance work and caregiving responsibilities, and 27% have had to reduce their work hours.

## Why "Self-Care" Advice Falls Short
You have heard it before. Take a bath. Go for a walk. Practice gratitude. While well-intentioned, generic self-care advice often misses the mark for parents of neurodivergent children.
The challenge is not that you forgot to take care of yourself. The challenge is structural: the sheer volume of daily decisions, the unpredictability, the advocacy burden, the lack of systems designed to support your child's needs. A bubble bath does not fix decision fatigue. A walk does not reduce the cognitive load of managing therapies, IEPs, sensory accommodations, and emotional regulation strategies for another person while managing your own life.
What research actually supports is more targeted than "practice self-care."
## Evidence-Based Strategies That Actually Help
**Mindfulness-Based Stress Reduction (MBSR) works.** A systematic review of 12 randomized controlled trials found that mindfulness-based interventions significantly reduced parental stress, improved awareness, and alleviated anxiety and depression in parents of autistic children. The optimal duration was 5 to 8 weeks of parent-focused practice.
**Acceptance and Commitment Therapy (ACT) shows strong results.** ACT helps parents develop psychological flexibility, accepting difficult thoughts and feelings while committing to values-based action. Research identifies ACT and mindfulness-based approaches as the optimal combination for reducing parental stress and depressive symptoms.
**Parent training reduces burnout measurably.** A specific intervention combining psychoeducation and targeted parenting exercises decreased parental burnout by 37%, reduced neglect behaviors by 35%, and lowered cortisol levels by 36%, while increasing positive emotions by 28% (Mikolajczak et al.).
**Respite care has a real impact.** A study of over 28,000 children and young adults with autism found that each $1,000 increase in spending on respite care during a 60-day period resulted in an 8% decrease in the odds of hospitalization. Respite is not a luxury. It is a health intervention.
**Psychoeducation itself reduces stress.** Parents consistently report that simply receiving accurate, factual information about their child's condition helps decrease feelings of stress and anxiety. Knowledge replaces fear with understanding.
## The Power of Predictability
One of the most consistent findings across the research is that routines serve as a protective factor for both children and parents.
A 2024 systematic review in the Journal of Family Theory and Review found that routines are associated with positive development of children's cognitive skills, executive functioning, and social-emotional skills. More directly relevant: routines have been demonstrated to **reduce stress and anxiety** for children with neurodevelopmental differences.
For children with ADHD specifically, research shows that a higher number of household routines is inversely related to the severity of ADHD symptoms. Household and homework routines predicted fewer externalizing behaviors and fewer internalizing symptoms like depression and anxiety.
But here is the part that matters for burned-out parents: **routines reduce your stress too.**
When daily activities follow a predictable pattern, you make fewer decisions. You spend less mental energy planning what comes next, negotiating transitions, or managing the anxiety that comes from unstructured time. Visual routines externalize the plan so it is not all living inside your head.
This is where tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) become genuinely valuable, not as another thing on your to-do list, but as a way to offload the mental labor of daily planning. When your child can see what comes next in their routine, they need less prompting from you. When transitions are visual and predictable, meltdowns decrease. When the routine is built once and runs daily, you are not reinventing every morning and evening from scratch.
Research on visual schedules confirms they significantly reduce unwanted behaviors during transitions by illustrating what is expected, reducing confusion and anxiety for children and cognitive load for parents.
## Building Your Burnout Recovery Plan
Recovery from caregiver burnout is not about adding more to your plate. It is about building systems that carry some of the weight for you.
**Audit your daily decision load.** Write down every decision you make in a single day related to your child's care. Meals, clothing, transitions, therapies, sensory accommodations, emotional support, scheduling. Seeing the list in full often reveals why you are depleted. Then identify which decisions can be systematized, automated, or delegated.
**Build routines that run without you having to manage them.** Visual schedules that your child can follow independently reduce the number of times you need to prompt, redirect, or negotiate. Every routine your child can navigate on their own is energy returned to you. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you create personalized visual routines with AI-generated images tailored to your child, so routines feel familiar and motivating rather than generic.
**Connect with other parents who understand.** Professional guidelines consistently emphasize the importance of peer support. Other parents of neurodivergent children understand the specific exhaustion, the advocacy battles, the celebration of milestones others might not recognize. This is not optional. It is evidence-based stress reduction.
**Pursue targeted professional support.** If burnout is affecting your daily functioning, seek out a therapist familiar with ACT or MBSR approaches. Many therapists now specialize in supporting caregivers of neurodivergent children. Some offer group formats that are both cost-effective and provide community.
**Use respite care without guilt.** Taking breaks from caregiving is not selfish. The research is unambiguous: respite care reduces anxiety, depression, and stress in caregivers while improving outcomes for children. Whether it is a few hours with a trusted family member or a formal respite program, regular breaks are maintenance, not indulgence.
**Track your child's emotions alongside your own.** [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking feature helps you spot patterns in your child's day, which activities trigger stress and which bring calm. When you can see those patterns clearly, you spend less energy guessing and more energy responding effectively. That shift from reactive to proactive parenting is one of the fastest paths to reducing your own stress.
## You Cannot Pour From an Empty Cup (and That Is Not Just a Cliche)
The research is clear: interventions that reduce parent stress simultaneously improve child behavior, creating a positive cycle that benefits everyone. When you invest in your own wellbeing, you are not taking something away from your child. You are giving them a more present, patient, and effective parent.
Mikolajczak and Roskam's research found that severely burned-out parents reported behaviors they would never engage in when functioning well, including emotional withdrawal, harsh words, and neglect of daily needs. This is not a character failing. It is what happens when human beings are pushed past their capacity without adequate support.
Your burnout is not evidence that you are a bad parent. It is evidence that you are carrying more than any one person should carry alone.
## Start Small, Start Today
You do not need to overhaul your entire life to begin recovering. Start with one change:
- **Build one visual routine** for the most stressful part of your day. Morning chaos? Bedtime battles? After-school transitions? Pick the pain point and create a predictable visual sequence your child can follow. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) makes this simple, with AI-powered image generation and drag-and-drop routine building that takes minutes, not hours.
- **Identify one decision you can eliminate.** Maybe it is laying out clothes the night before. Maybe it is meal prepping on Sunday. Maybe it is setting a visual timer that signals transitions so you do not have to be the one constantly announcing what comes next.
- **Schedule one hour of respite this week.** Not someday. This week. Put it on the calendar and protect it like you would protect a therapy appointment for your child.
The goal is not perfection. The goal is sustainability. You are in this for the long haul, and your child needs you to still be standing, still be present, and still have something left to give.
Download on the App Store
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual routines that reduce daily decision fatigue, track your child's emotions to spot patterns, and create predictability that supports your whole family. Just $6.99/month after your trial, no credit card required upfront.
---
## Celebrating Neurodivergent Strengths in Your Child
Published: 2026-02-17
URL: https://vizyplan.com/blog/celebrating-neurodivergent-strengths-children
Category: Visual Supports
Author: Justin Bowman
> Moving beyond deficit-based thinking to recognize and nurture the special interests, unique perspectives, and remarkable abilities of neurodivergent children.
So much of the conversation around neurodivergence focuses on challenges, deficits, and things that need to be fixed. Therapy goals target weaknesses. School reports highlight what your child cannot do. Well-meaning advice centers on closing gaps between your child and their neurotypical peers. It is easy to internalize this deficit framing until it becomes the lens through which you see your own child.
But here is what that lens misses: your child's brain is not broken. It is different. And that difference comes with genuine, remarkable strengths that deserve recognition, nurturing, and celebration.
The neurodiversity paradigm, which frames neurological differences as natural human variation rather than pathology, has gained significant traction in both research and clinical practice. Studies increasingly recognize that the same neurological wiring that creates challenges in certain contexts produces extraordinary abilities in others. The child who struggles with small talk may have an encyclopedic knowledge of marine biology. The child who cannot sit still may have physical energy and creativity that peers cannot match. The child who has meltdowns at the grocery store may perceive patterns and details that everyone else misses.
This article is not about ignoring challenges. It is about ensuring that strengths get at least as much attention, recognition, and support as the difficulties do.
## The Science of Neurodivergent Strengths
Research on the strengths associated with autism and ADHD is growing and compelling.
**Special interests are a superpower, not a symptom.** Autistic special interests, the deep, passionate, sustained focus on specific topics, have traditionally been viewed as a symptom to be managed. Current research tells a different story. Studies show that special interests reduce anxiety, increase happiness, provide motivation for learning, and build expertise that can translate into academic and professional success. A longitudinal study published in Autism Research found that special interests contribute positively to quality of life and can serve as pathways to meaningful careers and social connections.
**Pattern recognition is enhanced.** Research on perceptual processing in autism has consistently found superior performance on tasks requiring attention to detail and pattern recognition. Autistic individuals often outperform neurotypical peers on visual search tasks, embedded figure tests, and pattern completion exercises. This ability to detect patterns that others miss has real-world applications in fields ranging from mathematics to music to quality assurance.
**ADHD brings creative advantages.** Studies on divergent thinking, the ability to generate multiple novel ideas, have found that individuals with ADHD score significantly higher than neurotypical peers on measures of creative thinking. The same neural differences that make sustained attention to routine tasks difficult appear to enhance the ability to make unusual connections, think outside established frameworks, and generate original solutions.
**Hyperfocus is a valuable asset.** While ADHD is often characterized by attention deficits, hyperfocus, the ability to become deeply absorbed in an engaging task, is an equally defining feature. During hyperfocus, productivity and creative output can be extraordinary. Research suggests that channeling hyperfocus toward areas of strength and interest produces outcomes that exceed what sustained but moderate attention achieves.
**Honesty and authenticity.** Many autistic individuals are recognized for their directness and honesty. In a world that often values social performance over genuine communication, the autistic tendency toward straightforward, authentic expression is a strength that builds trust and clarity in relationships.
**Memory and knowledge depth.** The ability to absorb, retain, and recall detailed information about topics of interest is well-documented in autism research. This deep knowledge, whether about train schedules, historical events, animal species, or video game mechanics, represents genuine intellectual capacity that can be channeled into academic and professional success.
## Identifying Your Child's Specific Strengths
Every neurodivergent child has a unique profile of strengths. Here is how to discover them.
**Observe what captivates them.** What does your child choose to do when they have free time? What topics do they return to repeatedly? What activities produce the most sustained focus and the brightest expressions of joy? These natural inclinations point directly to their strengths.
**Notice what comes easily.** While much attention goes to what is hard, pay equal attention to what your child does effortlessly. Maybe they build complex structures with blocks. Maybe they memorize song lyrics after one listen. Maybe they notice details in pictures that you walk right past. These are not trivial observations. They are data points about how your child's brain excels.
**Ask their teachers and therapists.** Professionals who work with your child see them in different contexts and may notice strengths that are less visible at home. Ask specifically: "What is my child good at? What comes naturally to them? When do they seem most engaged and confident?"
**Let your child tell you.** Ask them what they enjoy, what they feel proud of, and what they wish they could do more of. Their self-perception of their strengths matters enormously. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking can help children identify when they feel confident and happy, building awareness of the activities and contexts that bring out their best.
## Nurturing Strengths Through Daily Routines
Strengths grow when they are exercised regularly and celebrated consistently.
**Build strength-based activities into the visual schedule.** If your child loves drawing, ensure daily drawing time appears on their visual routine. If they are passionate about dinosaurs, include a "dinosaur research" block. When strength-based activities are part of the daily schedule, they are protected from being crowded out by therapy appointments and homework. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual schedule feature makes it easy to include these interest-based activities as valued parts of the day.
**Use special interests as bridges to challenging tasks.** A child who loves space can practice reading with books about planets. Math problems can involve dinosaur counting. Writing assignments can explore their favorite video game characters. When academic content is delivered through the channel of a special interest, engagement and retention improve dramatically.
**Create opportunities for expertise sharing.** Let your child teach you about their special interest. Ask genuine questions. Express authentic wonder at their knowledge. This positions them as the expert, reinforcing their sense of competence and the value of their unique knowledge.
**Connect interests to community.** Clubs, classes, online communities, or local groups related to your child's interests connect them with others who share their passion. A child who struggles in unstructured social settings may thrive in a robotics club or an art class where interaction is organized around a shared interest.
## Reframing the Narrative
How you talk about your child's neurodivergence shapes how they feel about themselves.
**Use strengths-based language.** Instead of "He is obsessed with trains," try "He has an incredible depth of knowledge about trains." Instead of "She cannot sit still," try "She has amazing physical energy." The reframe does not ignore the challenge but leads with the strength.
**Celebrate neurodivergent role models.** Share stories of successful neurodivergent individuals who have leveraged their unique brains in remarkable ways. Knowing that their neurological wiring is shared by scientists, artists, entrepreneurs, and innovators helps children build a positive neurodivergent identity.
**Create a visual strengths board.** A physical or digital board showing your child's strengths, achievements, and proud moments provides a tangible reminder of their capabilities. Update it regularly. Include awards, completed projects, kind acts, and moments of growth. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s reward and tracking features can serve as a digital strengths portfolio, showing your child's progress and achievements over time.
**Separate the child from the challenge.** "You are a creative, energetic kid who sometimes finds it hard to wait" is fundamentally different from "You are an impatient kid." Identity-first language that leads with the person, not the deficit, protects self-concept.
## Supporting Strengths at School
Ensuring your child's strengths are recognized and nurtured at school is an important advocacy role.
**Include strengths in IEP discussions.** IEP meetings tend to focus almost exclusively on deficits and goals for improvement. Bring your child's strengths to the table explicitly. Request that strength-based goals and interest-based accommodations are included alongside remedial objectives.
**Ask for opportunities to showcase expertise.** A child who knows everything about ancient Egypt should have opportunities to present that knowledge, lead a class discussion, or create a project that demonstrates their depth. These moments of competence balance the many moments where school highlights what is difficult.
**Connect strengths to future planning.** As your child grows, help them see how their specific strengths connect to potential career paths, hobbies, and life goals. The child who can identify every bird by its call might become a biologist. The child who builds elaborate worlds in Minecraft might become an architect or game designer. Seeing a future built on their strengths provides powerful motivation.
## The Bigger Picture
Celebrating neurodivergent strengths is not about pretending challenges do not exist. It is about ensuring that your child's self-concept is not built entirely on what is hard for them. Every child deserves to know what they are good at, to feel the confidence that comes from exercising their strengths, and to envision a future where their unique brain is an asset rather than a liability.
When you focus only on closing gaps, you risk communicating to your child that who they are is not good enough. When you equally invest in discovering, nurturing, and celebrating their strengths, you communicate something far more powerful: who you are is remarkable, and the world needs what you bring.
Your neurodivergent child is not a collection of deficits to be remediated. They are a whole person with a unique neurological profile that includes extraordinary strengths alongside genuine challenges. Both deserve your attention. Both shape who they will become.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build daily routines that celebrate your child's strengths, track emotional well-being, and create visual supports that reinforce their confidence and identity. Just $6.99/month after your trial, no credit card required upfront.
---
## Managing Anxiety in Neurodivergent Children
Published: 2026-02-16 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/managing-anxiety-neurodivergent-children-visual-strategies
Category: Strategies
Author: Justin Bowman
> How anxiety shows up differently in autistic and ADHD children, and visual strategies including worry scales, calm-down sequences, and grounding techniques that help.
Your child refuses to walk into school. The teacher calls it defiance. Your child melts down at the birthday party. The other parents call it a tantrum. Your child cannot focus on homework. The report card says "not trying hard enough." But you know something everyone else is missing: your child is not misbehaving. They are terrified.
Anxiety in neurodivergent children hides behind behaviors that look like something else entirely. What presents as defiance is often freeze-mode anxiety. What looks like a meltdown is frequently an anxiety-driven fight response. What appears to be distraction may be a mind racing with worry so loud it drowns everything else out. When we miss the anxiety underneath, we respond to the symptom instead of the cause, and the anxiety grows.
Research paints a striking picture. Studies published in the Journal of the American Academy of Child and Adolescent Psychiatry report that approximately 40% of autistic children meet criteria for at least one anxiety disorder, compared to about 6 to 7% of the general child population. For children with ADHD, the rate is similarly elevated, with estimates ranging from 25 to 50% experiencing clinically significant anxiety. These are not small numbers. Anxiety is one of the most common co-occurring conditions in neurodivergence.
The good news is that visual strategies offer a powerful, accessible approach to anxiety management that works with the neurodivergent brain rather than against it. When anxious thoughts are made visible, when coping strategies have a concrete form, and when the pathway from "anxious" to "calm" is laid out step by step, neurodivergent children gain genuine tools for managing their inner experience.
## How Anxiety Looks Different in Neurodivergent Children
Anxiety in neurodivergent children often does not match the textbook presentation, which means it gets missed or misinterpreted.
**Anxiety can look like rigidity.** An autistic child who insists that everything happen exactly the same way every time may be managing underlying anxiety through control. Sameness is a regulatory strategy. When the routine breaks, the anxiety that sameness was containing floods to the surface and manifests as a meltdown or shutdown.
**Anxiety can look like avoidance.** A child who refuses to go to school, will not try new foods, or resists any new activity may not be "oppositional." They may be avoiding situations that trigger unbearable anxiety. The avoidance is self-protective, not defiant.
**Anxiety can look like aggression.** The fight response in the anxiety cycle can manifest as hitting, throwing, or verbal aggression. For children who cannot articulate "I am terrified right now," the anxiety exits as explosive behavior that gets treated as a disciplinary issue rather than an emotional regulation crisis.
**Anxiety can look like physical symptoms.** Stomachaches, headaches, nausea, and toileting accidents can all be physical manifestations of anxiety. If your child consistently complains of stomach pain before school but feels fine on weekends, anxiety is a likely contributor.
**Anxiety can look like ADHD symptoms.** Racing thoughts, inability to focus, restlessness, and difficulty sitting still are symptoms shared by both anxiety and ADHD. In children who have both conditions, untreated anxiety can amplify ADHD symptoms significantly.
## The Worry Scale: Making Anxiety Visible
One of the most effective visual tools for anxiety management is the worry scale, sometimes called a feelings thermometer.
**How it works.** A visual scale from 1 to 5 (or 1 to 10) with corresponding colors and descriptions helps your child identify and communicate their anxiety level. Level 1 might be "calm and relaxed" (green), level 3 might be "worried, stomach feels funny" (yellow), and level 5 might be "everything feels too much, cannot think" (red).
**Why it works for neurodivergent children.** Many neurodivergent children have difficulty with interoception, the ability to identify internal body states. They may go from "fine" to "complete meltdown" with no apparent middle ground. The worry scale teaches them to recognize the middle stages, where intervention is most effective, before they reach crisis level.
**Build it together.** Let your child choose the colors, the descriptors, and the coping strategies associated with each level. Ownership increases engagement. [VizyPlan](https://vizyplan.com)'s emotion tracking feature provides a built-in framework for this type of emotional check-in, giving your child a consistent visual tool for identifying where they are on the scale throughout the day.
**Use it proactively.** Check in with the worry scale before anxiety-provoking situations, not just during them. "We are going to the dentist in one hour. Where are you on the worry scale right now?" This proactive use catches anxiety early when it is most manageable.
## Visual Calm-Down Sequences
When anxiety escalates, verbal instructions ("Just calm down!") rarely work. Visual sequences provide a concrete path from anxious to regulated.
**Create a step-by-step calm-down routine.** A visual card or poster showing a sequence of calming strategies gives your child something to follow when their thinking brain is offline:
- Take three deep breaths (picture of breathing)
- Squeeze your hands tight, then release (picture of fists)
- Name five things you can see (picture of eyes)
- Name four things you can touch (picture of hands)
- Drink some water (picture of water)
**Personalize the strategies.** Not every calming strategy works for every child. Some children are calmed by deep pressure (a weighted blanket or a tight hug). Others need movement (jumping, running, or rocking). Some need sensory input (cold water on hands, a crunchy snack). Build a calm-down sequence using strategies your child actually responds to. [VizyPlan](https://vizyplan.com)'s visual schedule feature lets you create personalized calm-down routines with images your child recognizes and connects to.
**Practice when calm.** The time to learn a calm-down sequence is NOT during a panic attack. Practice the sequence daily during calm moments so that when anxiety hits, the routine is familiar and automatic. Think of it like a fire drill: you practice when there is no fire so that the response is ready when there is.
**Make calm-down kits portable.** A small bag with a laminated visual calm-down card, a fidget toy, noise-canceling headphones, and a stress ball can travel with your child to school, appointments, and outings. Having the tools available when anxiety strikes, rather than only at home, dramatically increases their usefulness.
## Grounding Techniques Made Visual
Grounding techniques pull attention from anxious thoughts back to the present moment. Visual adaptations make these techniques accessible to neurodivergent children.
**The 5-4-3-2-1 technique with visual prompts.** A card showing: 5 things I see (with eye icon), 4 things I touch (hand icon), 3 things I hear (ear icon), 2 things I smell (nose icon), 1 thing I taste (mouth icon). This sensory grounding exercise redirects attention from internal worry to external reality.
**Breathing exercises with visual guides.** Square breathing (breathe in for 4 counts, hold for 4, breathe out for 4, hold for 4) works well with a visual trace-along square. Flower breathing (breathe in like smelling a flower, breathe out like blowing a pinwheel) uses imagery that makes the abstract concrete.
**Body scan with a visual body map.** A simple outline of a body where your child colors in where they feel the anxiety (tight stomach, tense shoulders, clenched jaw) builds body awareness and makes the abstract feeling of anxiety tangible and addressable.
## Reducing Anxiety Through Predictability
For many neurodivergent children, the most effective anxiety management is prevention through predictability.
**Visual schedules reduce uncertainty.** When your child can see what is happening today, the ambient anxiety of "What is coming next?" decreases. [VizyPlan](https://vizyplan.com)'s daily visual schedule provides this predictable framework, reducing the cognitive load of uncertainty that feeds anxiety.
**Preview new situations with social stories.** Before any new or potentially anxiety-provoking situation, walk through it visually. What will it look like? What will happen? What will your child do if they feel anxious? This preparation converts the terrifying unknown into a somewhat familiar sequence of events.
**Build in transition warnings.** Abrupt changes trigger anxiety. Providing visual countdown warnings before transitions ("Five minutes until we leave," "Two minutes until we leave") gives your child time to prepare psychologically rather than being ambushed by change.
**Create "what if" plans.** For children who worry about what could go wrong, having a visual plan for those scenarios can be profoundly reassuring. "What if the fire alarm goes off at school?" Here is the plan, in pictures, step by step. When the fear has a response plan, it loses much of its power.
Anxiety does not have to control your child's life. With visual tools that make feelings tangible, coping strategies concrete, and daily routines predictable, neurodivergent children develop genuine capacity for managing the worry that comes with experiencing the world differently.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual calm-down routines, track anxiety patterns with emotion tracking, and create the predictable daily structure that reduces anxiety at its source. Just $6.99/month after your trial, no credit card required upfront.
---
## Teaching Safety Awareness to Neurodivergent Children
Published: 2026-02-15
URL: https://vizyplan.com/blog/teaching-safety-awareness-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Evidence-based strategies for teaching safety rules, stranger awareness, road safety, and emergency protocols to children with autism and ADHD using visual supports.
Teaching safety to neurodivergent children keeps parents up at night. The stakes feel impossibly high. You know your child may not recognize danger the way neurotypical peers do. They may run into a parking lot without looking. They may wander away from you in a crowded place. They may trust a stranger without hesitation. They may not know what to do in an emergency.
The statistics reinforce these fears. Research from the National Autism Association reports that wandering, also called elopement, affects nearly half of children with autism, with a significant percentage experiencing potentially life-threatening situations as a result. Children with ADHD face elevated risk of accidental injury due to impulsivity and reduced danger awareness.
The good news is that safety skills can be taught effectively to neurodivergent children. The approach needs to be more visual, more repetitive, more concrete, and more practiced than typical safety instruction, but the outcomes can be genuinely protective. Your child can learn to be safer in the world.
## Why Safety Awareness Is Different
Understanding why standard safety instruction falls short for neurodivergent children helps you teach more effectively.
**Abstract danger is hard to understand.** "Strangers can be dangerous" is an abstract concept. For concrete thinkers, this instruction is confusing: the grocery store cashier is a stranger but is clearly not dangerous. The mail carrier is a stranger but comes to the house every day. Without concrete, specific rules, abstract safety warnings do not translate into protective behavior.
**Impulsivity overrides knowledge.** A child with ADHD may know the rule about looking both ways before crossing the street but be unable to stop themselves from chasing a ball into the road. The gap between knowing a safety rule and being able to follow it in the moment of impulse is a real and dangerous vulnerability.
**Social processing differences affect stranger awareness.** Some autistic children have difficulty reading social cues that signal danger. They may not detect the "off" feeling that neurotypical children get from an unsafe adult. Conversely, some autistic children may be overly trusting because social scripts they have learned ("Be polite to adults") override situational safety awareness.
**Sensory seeking can create danger.** A child drawn to the sensory experience of running water may approach a pool or stream without recognizing the drowning risk. A child who loves the feeling of spinning may climb to dangerous heights for vestibular input. The sensory drive can be stronger than the cognitive understanding of risk.
**Elopement is driven by multiple factors.** Children may wander toward something that interests them (a body of water, a favorite store, a dog), away from something distressing (a sensory trigger, a social demand), or simply due to the impulse to move without a destination in mind. Understanding your child's specific elopement triggers is essential for prevention.
## Visual Safety Rules
Abstract safety rules need to be made concrete and visible.
**Create visual safety rule cards.** Each safety rule gets its own card with a picture and a simple statement:
- "Stop at the curb. Look left. Look right. Walk when clear." (with images of each step)
- "Stay with Mom/Dad in stores." (with an image of child near parent)
- "If lost, find a worker with a name tag." (with an image of a store employee)
- "Do not open the door for anyone when home alone."
**Post rules where they apply.** The road safety card goes near the front door. The kitchen safety rules go in the kitchen. The pool rules go near the swimsuit drawer. Context-specific placement reinforces the association between the rule and the situation.
**Use social stories for complex safety scenarios.** [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social story feature lets you create personalized narratives about safety situations. A story about what to do if your child gets separated from you in a store, complete with AI-generated images showing your child in a familiar store setting, makes the scenario concrete and rehearsable.
## Teaching Road Safety
Road and traffic safety requires specific, repeated instruction.
**Practice at real intersections.** Standing at a crosswalk and physically practicing the sequence, stop, look left, look right, look left again, walk when clear, builds the motor routine alongside the cognitive rule. Verbal instruction alone is insufficient. The body needs to learn the pattern.
**Use visual crossing sequences.** Create a step-by-step visual card your child can reference. Over time, the external visual support becomes internalized as an automatic routine. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual schedule format works well for this type of sequential instruction.
**Teach traffic light meanings with visuals.** Red means stop (picture of a child standing still). Green means go (picture of a child walking). Yellow means wait (picture of a child stopping). These visual associations are more reliable for concrete learners than verbal rules alone.
**Practice in low-stakes environments first.** Empty parking lots, quiet residential streets, and sidewalk paths all provide opportunities to practice road safety without the immediate danger of heavy traffic.
**Address impulsivity directly.** For children with ADHD, add a physical anchor to the road safety routine. "Put your hand on my arm before we cross" or "Touch the crossing button and count to three before stepping off the curb" adds a physical action that interrupts the impulse to dart into the street.
## Stranger Safety for Concrete Thinkers
Reframe "stranger danger" into specific, actionable rules.
**Replace "stranger danger" with a safety network concept.** Instead of teaching your child that all strangers are dangerous (which is confusing and not actually true), build a visual "safety network" showing specific people your child can go to for help: parents, grandparents, teachers, specific neighbors. Anyone not on the network is "someone I do not go with."
**Teach the "check first" rule.** Before going anywhere with anyone, your child checks with a parent first. This simple, concrete rule is easier to follow than evaluating whether someone is safe. Practice the script: "I have to check with my mom/dad first."
**Role-play specific scenarios.** "What do you do if someone you do not know offers you candy?" Practice the response physically: shake head, say "No thank you," walk to a safe person. Repeated rehearsal builds automatic responses that do not require in-the-moment decision-making.
**Teach body autonomy.** "Your body belongs to you. No one touches you in ways that make you uncomfortable. If someone does, tell a safe person." Use visual supports showing the difference between safe touches (high fives, handshakes when you want them) and unsafe touches. Social stories about body boundaries are an effective tool for this sensitive topic.
## Emergency Preparedness
Preparing for emergencies requires specific, practiced routines.
**Teach your child their full name, address, and a parent's phone number.** For non-speaking or minimally speaking children, consider an identification bracelet or a laminated card they carry. Practice reciting this information regularly until it is automatic.
**Create visual fire safety routines.** A step-by-step visual showing: hear the alarm, leave what you are doing, go to the door, feel the door (if hot, use another exit), go to the meeting spot. Practice this as a family regularly, just as schools run fire drills.
**Practice calling emergency services.** Use an old phone to practice dialing the emergency number and stating their name and address. Some children benefit from a visual script posted near the phone.
**Establish a meeting spot.** A specific, visible location outside your home where the family gathers during any emergency. Include this spot in your visual safety rules and reference it regularly.
## Preventing Elopement
For families where wandering is a concern, prevention and preparation are both essential.
**Identify triggers.** Using [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s tracking features, log when and why elopement attempts happen. Is your child drawn to water? Do they run when overwhelmed? Do they wander when they see something interesting through a window? Understanding the trigger informs the prevention.
**Secure the environment.** Door alarms, window locks, fencing, and GPS tracking devices provide physical safeguards while you work on teaching safety awareness. These are not punishments. They are protective measures similar to childproofing a home for a toddler.
**Teach "stop" as a safety command.** Practice responding to the word "stop" as an immediate freeze response. Turn it into a game during calm moments (red light, green light) to build the automatic response that could prevent a dangerous situation.
**Alert neighbors and community.** Let nearby neighbors, local police, and school staff know that your child may wander and provide a description and photo. Many communities have programs specifically designed to support families of children prone to elopement.
Safety awareness is a lifelong learning process for all children, and neurodivergent children may need longer, more intensive instruction with more visual support. But every safety skill learned is a layer of protection that increases your child's ability to navigate the world more safely.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Create visual safety rules, social stories about emergency preparedness, and trackable routines that build your child's safety awareness over time. Just $6.99/month after your trial, no credit card required upfront.
---
## Teaching Household Chores to Neurodivergent Children
Published: 2026-02-14
URL: https://vizyplan.com/blog/teaching-household-chores-neurodivergent-children
Category: Daily Routines
Author: Justin Bowman
> How to build life skills and independence through household chores using visual task analysis, backward chaining, and structured support for neurodivergent children.
Teaching chores to a neurodivergent child can feel like it takes more time and energy than just doing the task yourself. And honestly, in the short term, it does. But the long-term payoff, a child who can independently contribute to their household, who feels capable and included, who builds the executive function skills that transfer to every area of life, makes the investment worthwhile many times over.
Research on independence and life skills in neurodivergent individuals consistently identifies household task completion as one of the strongest predictors of adult independence. Children who learn to complete chores with appropriate support develop executive function skills, self-confidence, and a sense of belonging in the family unit that benefits them throughout their lives.
The good news is that with the right visual supports, appropriate task breakdown, and patient teaching methods, neurodivergent children can learn to complete household chores independently. The approach just needs to match their learning style rather than relying on verbal instructions and the assumption that they will figure it out.
## Why Chores Are Challenging
Understanding the specific barriers helps you choose the right supports.
**Executive function demands are high.** Even a "simple" chore like setting the table requires planning (what items are needed), organization (gathering them from different locations), sequencing (putting them in the right places in the right order), and task monitoring (checking that everything is complete). Each of these executive function components may be an area of difficulty for your child.
**Multi-step tasks overwhelm working memory.** When you say "Go clean your room," you are actually giving an instruction that contains dozens of sub-tasks: pick up clothes, put away toys, make the bed, organize the desk, put books on shelves. For a child with limited working memory, this single instruction is an impossible demand because they cannot hold all the sub-tasks in mind simultaneously.
**Sensory issues affect willingness.** Wet textures in dishwashing, the smell of cleaning products, the feel of dirty laundry, or the noise of a vacuum can all be sensory barriers. A child is not being lazy when they refuse to take out the trash because the bag feels wet and smells bad. Their sensory system is creating a genuine aversion.
**Motivation systems work differently.** Neurotypical children may be motivated by the intrinsic satisfaction of a clean room or the social reward of parental approval. Neurodivergent children, especially those with ADHD, often need more immediate, tangible reinforcement to sustain effort on non-preferred tasks.
## Visual Task Analysis: Breaking Chores Down
The single most effective strategy for teaching chores to neurodivergent children is visual task analysis: breaking a complex task into individual, visible steps.
**Create a visual checklist for each chore.** Instead of "Clean your room," create a checklist with pictures:
- Put dirty clothes in hamper
- Put toys in toy bin
- Put books on shelf
- Straighten bedcovers
- Put shoes in closet
Each step is specific, observable, and checkable. Your child can see what needs to happen and track their own progress through the task. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual schedule feature lets you create personalized chore checklists with images that match your child's actual home, making each step concrete and recognizable.
**Use photos of the finished result.** A picture showing what the made bed looks like, what a properly set table looks like, or what "toys put away" actually means gives your child a concrete target. Abstract standards like "tidy" or "clean enough" are impossible to achieve when you do not know what they look like.
**Post checklists where the chore happens.** The dish-loading checklist goes near the dishwasher. The room-cleaning checklist goes on the bedroom door. The laundry checklist goes in the laundry room. Proximity reduces the cognitive demand of remembering what to do.
## Backward Chaining: Building Confidence
Backward chaining is a teaching method where you complete most of the task and let your child finish the last step. Then gradually, they complete the last two steps, then the last three, and so on.
**Why it works for neurodivergent learners.** Every practice session ends with your child completing the task, which creates a positive association with finishing and builds confidence. They experience success from the very first attempt rather than struggling through an entire complex task.
**Example with making the bed:**
- Week 1: You make the bed entirely except the last step (placing the pillow). Your child places the pillow. Done!
- Week 2: You do everything except the last two steps (pulling up the top blanket and placing the pillow). Your child completes both.
- Week 3: Add another step. Continue until your child completes the entire task independently.
**Apply to any chore.** Backward chaining works for loading the dishwasher, folding laundry, wiping counters, and virtually any multi-step household task. The key is patience. Each step may need many repetitions before it becomes automatic.
## Age-Appropriate Chore Ideas
Match the chore to your child's developmental level and sensory profile, not just their chronological age.
**Foundational skills (developmental age 2-4):**
- Putting toys in a designated bin
- Carrying lightweight items to the table
- Putting clothes in the hamper
- Wiping up small spills with a cloth
- Helping feed pets by pouring measured food
**Building skills (developmental age 4-6):**
- Setting the table with a visual placemat showing where items go
- Sorting laundry by color (a visual sorting activity)
- Wiping surfaces with guidance
- Watering plants with a measured container
- Picking up items from the floor and putting them in designated spots
**Expanding skills (developmental age 6-8):**
- Loading the dishwasher with a visual guide showing where items go
- Folding simple items (towels, washcloths)
- Making their bed with visual reference
- Sweeping with a child-sized broom
- Helping prepare simple snacks
**Growing independence (developmental age 8+):**
- Complete kitchen cleanup routines
- Laundry from start to finish with checklists
- Vacuuming or mopping designated areas
- Organizing personal spaces
- Simple cooking tasks with visual recipes
## Using Reward Systems Effectively
Tangible rewards bridge the gap between effort and motivation.
**Make rewards visual and immediate.** A chore chart where your child places a sticker after completing each task provides instant visual feedback. Accumulated stickers earn a chosen reward. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s built-in reward system lets you connect chore completion directly to points that build toward goals your child has chosen, keeping motivation high.
**Match the reward to the effort.** Simple, quick chores earn small rewards. Bigger, more challenging chores earn bigger rewards. This teaches the real-world connection between effort and compensation.
**Reward effort during the learning phase.** While your child is first learning a chore, reward any participation, even if the result is imperfect. A crookedly made bed is still a made bed. Partially loaded dishwasher still shows effort. Perfectionism in the learning phase kills motivation.
**Fade rewards gradually.** As chores become habitual, you can gradually shift from external rewards to natural consequences. "When the kitchen is clean, we can start movie night" connects the chore to a natural outcome rather than an artificial reward.
## Handling Resistance
Resistance to chores is normal for all children and especially common in neurodivergent children.
**Identify the barrier.** Is it sensory? Executive function? Motivation? Fatigue? Unclear expectations? The intervention depends on the cause. A child resisting dishwashing because the water feels wrong needs gloves. A child resisting because they do not know where things go needs a visual guide. A child resisting because they are exhausted after school needs the chore moved to a different time.
**Offer choices within the structure.** "Do you want to do your chore before or after snack?" or "Would you rather set the table or put away the clean silverware?" Choice provides autonomy within the non-negotiable expectation of contributing.
**Use first-then visually.** "First, put away your laundry. Then, thirty minutes of screen time." The visual first-then board makes the expectation and reward crystal clear.
Chores are more than tasks to check off a list. They are opportunities for your neurodivergent child to develop independence, build executive function, contribute to the family, and grow in confidence. With visual supports, patient teaching, and the right motivation, every child can learn to be a capable contributor to their household.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Create visual chore checklists, track completion with built-in rewards, and build daily routines that include household contributions your child can be proud of. Just $6.99/month after your trial, no credit card required upfront.
---
## Sleep Challenges Beyond Bedtime for Neurodivergent Children
Published: 2026-02-13
URL: https://vizyplan.com/blog/sleep-challenges-night-waking-neurodivergent-children
Category: Daily Routines
Author: Justin Bowman
> Beyond bedtime routines: addressing night waking, sleep anxiety, early morning rising, and other sleep challenges common in children with autism and ADHD.
You have the bedtime routine down. The visual schedule is posted. The weighted blanket is in place. Your child falls asleep at a reasonable hour. And then, at 2 AM, they are wide awake. Or they wake screaming from a nightmare. Or they appear at your bedside for the third time, unable to settle. Or they are up at 4:30 AM, fully alert and ready to start the day while the rest of the household desperately needs more sleep.
Sleep challenges in neurodivergent children extend far beyond the difficulty of falling asleep at bedtime. Research consistently shows that 50 to 80% of children with autism and up to 70% of children with ADHD experience significant sleep disturbances. These are not just bedtime resistance issues. They include night waking, sleep anxiety, nightmares, early morning rising, and fragmented sleep patterns that leave both children and parents exhausted.
The good news is that understanding why these specific sleep challenges occur opens the door to targeted strategies that address the root causes rather than just managing symptoms.
## Why Sleep Is Different for Neurodivergent Brains
The neurology behind sleep difficulties goes deeper than behavioral habits.
**Melatonin production is often atypical.** Research has found that many autistic children produce melatonin on a delayed or irregular schedule compared to neurotypical peers. Studies in the Journal of Clinical Sleep Medicine have shown that autistic children may produce peak melatonin levels later in the evening, making it harder to fall asleep, and may see melatonin levels drop earlier in the morning, leading to premature waking. This is a biological difference, not a behavioral one.
**Circadian rhythm differences are common in ADHD.** Children with ADHD frequently show delayed circadian rhythms, meaning their internal clock is shifted later than typical. Their body wants to fall asleep later and wake later, which conflicts with school schedules and family routines. This mismatch between internal clock and external demands creates chronic sleep debt.
**Arousal regulation affects sleep maintenance.** The ability to transition smoothly between sleep stages and to return to sleep after brief natural awakenings depends on arousal regulation systems that function differently in neurodivergent brains. Where a neurotypical child briefly wakes between sleep cycles and falls back asleep without fully rousing, a neurodivergent child may wake fully and be unable to return to sleep.
**Sensory sensitivities do not stop at night.** The hum of a refrigerator, the feel of sheets, the temperature of the room, shadows on the wall, or a sibling's breathing can all be enough to rouse a sensory-sensitive child. Sensory processing differences that create challenges during the day continue operating during sleep.
**Anxiety peaks at night.** The absence of daytime distractions allows anxious thoughts to dominate. For neurodivergent children prone to anxiety, bedtime and middle-of-the-night waking can trigger worry spirals that make returning to sleep impossible.
## Addressing Night Waking
Night waking is one of the most exhausting sleep challenges because it disrupts everyone in the household.
**Identify the cause before choosing a strategy.** Night waking can stem from sensory triggers, anxiety, hunger, the need for the bathroom, nightmares, or simply an inability to self-soothe back to sleep. The intervention depends entirely on the cause. Track your child's night waking patterns using [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion and activity tracking. Note the time, what preceded the waking, and how your child presents. Patterns usually emerge within one to two weeks.
**Address sensory triggers in the sleep environment.** A white noise machine masks inconsistent nighttime sounds. Blackout curtains eliminate light that can trigger waking. Temperature control (many neurodivergent children sleep better in slightly cooler rooms) reduces discomfort. Weighted blankets provide proprioceptive input that promotes deeper sleep for some children.
**Create a visual "night waking" routine.** If your child wakes at night and comes to find you, having a simple visual posted by their bed showing what to do can build independent re-settling skills. The sequence might include: stay in bed, hug your stuffed animal, take three deep breaths, close your eyes, and try again. Having the steps visible removes the cognitive demand of remembering what to do in a groggy, anxious state.
**Build a gradual independence plan.** If your child currently requires your physical presence to fall back asleep, gradually reduce your involvement over weeks. Start by sitting beside their bed, then move the chair further from the bed, then sit in the doorway, then stay in your room with the door open. Each step is small enough to be tolerable while building the skill of independent re-settling.
## Managing Sleep Anxiety
For many neurodivergent children, the fear of sleeping is the biggest barrier to sleep itself.
**Validate the fear.** "I can see nighttime feels scary for you" is more effective than "There is nothing to be afraid of." Dismissing fear does not reduce it. Validation makes your child feel heard and opens the door to problem-solving.
**Create visual calm-down sequences for nighttime.** A simple visual card by the bed with calming strategies: deep breathing pictures, a body scan instruction, or a progressive muscle relaxation sequence gives your child something to do with the anxiety rather than lying in the dark with it.
**Address specific fears concretely.** If your child is afraid of the dark, experiment with different night light options. If they fear something in the closet, check together and close the door as part of the routine. If they worry about being alone, a two-way monitor with a visual indicator showing that you are nearby provides reassurance.
**Use social stories about nighttime.** A personalized social story about what happens while your child sleeps (the house is safe, the family is nearby, nighttime is for resting bodies) provides cognitive reassurance that reduces anxiety. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social story feature creates these narratives with images your child recognizes, making the reassurance more concrete and personal.
**Consider a worry journal or worry box.** Before bed, have your child draw or write their worries and place them in a designated box. The physical act of externalizing the worry can reduce its power. You can promise to "keep the worries safe" until morning, giving your child cognitive permission to set them aside.
## Early Morning Waking
When your child wakes hours before the alarm and cannot fall back asleep, the entire family suffers.
**Use a visual "okay to wake" system.** A clock that changes color at the acceptable wake time, or a simple sign that flips from "sleep time" to "awake time," gives your child a concrete signal for when it is okay to get up. This removes the ambiguity of "too early" versus "early enough."
**Create an independent morning activity kit.** If your child wakes early and truly cannot fall back asleep, having a designated bin of quiet activities (books, drawing supplies, simple puzzles) they can access independently gives them something to do without requiring your involvement. A visual card can show the rule: "If the clock is still red, choose a quiet activity from the bin."
**Address biological causes.** Early waking can be caused by blood sugar drops, light exposure, room temperature changes at dawn, or melatonin cycles ending too early. Consult with your child's pediatrician about whether melatonin timing adjustments or other interventions might help.
**Adjust bedtime strategically.** Counterintuitively, a later bedtime does not always produce later waking. For some children, being overtired at bedtime leads to restless sleep and earlier waking. For others, shifting bedtime thirty minutes later genuinely helps. Track the data and adjust based on what actually works for your child.
## Supporting the Whole Family
Sleep challenges affect every family member. Protecting everyone's rest is essential.
**Create a family sleep plan.** Discuss and agree on how nighttime disruptions will be handled. Who responds to night waking? How are siblings protected from disruption? What backup plans exist for nights that go badly? Having a plan reduces the stress of in-the-moment decision-making at 3 AM.
**Protect your own sleep.** A parent running on chronic sleep deprivation cannot provide the patient, consistent support their child needs. Take turns with a partner, accept help from family, or adjust expectations for daytime productivity when nights are disrupted. Your rest matters too.
**Communicate with school.** If your child's sleep challenges are affecting their daytime functioning, their teachers need to know. Accommodations like movement breaks, a quiet resting space, or modified expectations on days following poor sleep can prevent the compounding effect of sleep deprivation plus academic demands.
Sleep challenges are among the most physically and emotionally draining aspects of raising a neurodivergent child. They are also among the most responsive to targeted intervention. With the right environmental adjustments, visual supports, and consistent strategies, most families see meaningful improvement over time.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build bedtime and nighttime visual routines, track sleep patterns and emotions, and create calming sequences that help your child navigate the overnight hours. Just $6.99/month after your trial, no credit card required upfront.
---
## Supporting Fine Motor Skills in Neurodivergent Children
Published: 2026-02-12
URL: https://vizyplan.com/blog/fine-motor-skills-handwriting-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Practical strategies for helping neurodivergent children develop fine motor skills and handwriting, including visual guides, adaptive tools, and occupational therapy approaches.
Buttons that will not cooperate. Zippers that defeat small fingers. Handwriting that is illegible even to the child who wrote it. Scissors that seem impossible to control. For neurodivergent children, fine motor tasks that peers handle with relative ease can feel like running a marathon with weights on their hands.
Fine motor difficulties are remarkably common in both autism and ADHD. Research published in developmental psychology journals estimates that up to 80% of autistic children and a significant portion of children with ADHD experience some degree of fine motor delay. These challenges affect far more than handwriting. They impact dressing, eating, hygiene, art projects, science labs, and countless daily activities that require precise hand and finger movements.
The good news is that fine motor skills respond to practice, and the right kind of practice makes all the difference. Understanding why your child struggles and providing targeted, enjoyable activities that build strength and coordination gradually can transform their confidence and independence.
## Why Fine Motor Skills Are Challenging
Multiple neurological factors contribute to fine motor difficulties in neurodivergent children.
**Motor planning (praxis) differences.** Motor planning is the ability to conceptualize, organize, and execute a series of physical movements. Many autistic children experience dyspraxia or motor planning difficulties that make it hard to translate the idea of a movement into the actual physical execution. They know what they want their hands to do but cannot reliably make it happen.
**Muscle tone variations.** Low muscle tone (hypotonia) is common in autism and affects the small muscles of the hands and fingers. With reduced tone, gripping a pencil, squeezing scissors, or manipulating small objects requires more effort and produces more fatigue. The child's hands tire faster than their peers', which looks like laziness or lack of effort but is actually a physical limitation.
**Sensory processing affects motor output.** Fine motor control depends on sensory feedback from the hands, proprioception telling the brain how much force to apply, where the fingers are in space, and how to adjust grip. When sensory processing is atypical, this feedback loop is unreliable. The child may press too hard or too lightly, overshoot or undershoot target positions, and struggle with the fine adjustments that precise motor tasks require.
**Attention and motor control are linked.** Research has demonstrated a strong connection between attentional control and fine motor performance. Children with ADHD often show inconsistent motor output because their attention fluctuates during tasks that require sustained focus. One letter looks fine; the next is illegible. One cut with scissors is straight; the next veers wildly. This inconsistency is not carelessness. It reflects the attentional variability inherent in ADHD.
**Visual-motor integration challenges.** Many fine motor tasks require coordinating what the eyes see with what the hands do. Copying letters from a board, cutting along a line, or threading a bead onto a string all require visual-motor integration that may be weaker in neurodivergent children.
## Building Strength and Coordination
Before expecting precise fine motor output, ensure your child has the foundational strength and coordination to support it.
**Hand strengthening activities:**
- Squeezing play dough, clay, or therapy putty
- Using spray bottles to water plants
- Crumpling newspaper into balls
- Tearing paper into strips for collages
- Opening and closing clothespins
- Squeezing sponges during bath time
**Finger isolation and coordination:**
- Finger painting
- Picking up small objects with tweezers or tongs
- Piano or keyboard play
- Finger games and rhymes
- Peeling stickers off a sheet
- Building with small blocks or LEGO
**Bilateral coordination (using both hands together):**
- Stringing beads
- Lacing cards
- Cutting with scissors (one hand holds paper, one cuts)
- Opening containers
- Tying knots with rope or string
**Core and shoulder stability.** Fine motor skills actually start at the core. A child who cannot stabilize their trunk and shoulder will struggle with hand precision. Encourage activities that build proximal stability: wheelbarrow walks, push-ups against a wall, carrying heavy items, and hanging from monkey bars all strengthen the foundation that supports fine motor control.
## Visual Supports for Fine Motor Tasks
Breaking down motor tasks into visual steps reduces the cognitive load and makes success more achievable.
**Visual task analysis for dressing.** Buttoning, zipping, tying shoes, and snapping closures each involve multiple small steps. A visual sequence showing each step in isolation helps your child focus on one movement at a time rather than feeling overwhelmed by the whole task. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual schedule feature lets you create personalized step-by-step dressing sequences that your child can reference independently.
**Handwriting guides.** Visual cues for letter formation, such as numbered arrows showing stroke order, highlighted start points, and consistent spacing guides, support the motor planning required for handwriting. Many occupational therapists recommend programs that emphasize visual instruction over verbal instruction for neurodivergent learners.
**Model and then practice.** Demonstrate the motor task slowly while your child watches, then have them try. For complex tasks like tying shoes, video modeling (watching a recording of the hand movements) can be more effective than live demonstration because it can be replayed as many times as needed.
## Adaptive Tools That Help
The right tools reduce the physical demands of fine motor tasks.
**Writing tools:**
- Pencil grips that guide finger placement
- Weighted pencils that provide proprioceptive feedback
- Thicker pencils or crayons that are easier to grip
- Slant boards that position the paper at an optimal angle
- Lined paper with raised lines that provide tactile feedback
**Dressing aids:**
- Velcro closures instead of buttons
- Zipper pulls with large handles
- Elastic shoelaces that convert tie shoes to slip-ons
- Button hooks for practicing button skills
**Eating tools:**
- Built-up handle utensils that are easier to grip
- Non-slip mats under plates
- Adaptive cups with handles on both sides
**Remember:** Adaptive tools are not "giving up." They are accommodations that allow your child to participate independently while their motor skills continue developing. There is no shame in using a tool that makes a task possible.
## When to Work With an Occupational Therapist
Occupational therapy (OT) is the gold standard for addressing fine motor challenges in neurodivergent children.
**Consider OT if:**
- Fine motor difficulties significantly impact daily activities
- Your child avoids tasks that require fine motor skills
- Handwriting is consistently illegible or physically painful
- Your child is falling behind peers in self-care skills like dressing or eating
- Motor challenges are affecting self-esteem or social participation
**What OT provides:**
- A comprehensive assessment of motor strengths and challenges
- Individualized treatment plans targeting specific skills
- Therapeutic activities designed to be engaging rather than tedious
- Strategies for home and school that build on therapy gains
- Guidance for parents on how to support motor development daily
**Integrate OT strategies into your visual schedule.** When your occupational therapist recommends home exercises, build them into your child's visual routine. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) makes it easy to add hand-strengthening or coordination activities as steps in the daily schedule, so they become part of the expected routine rather than an extra demand.
## Celebrating Motor Milestones
Fine motor progress is often slow and incremental. Celebrating small wins keeps motivation alive.
**Track progress visually.** A chart showing skills mastered, from "can hold a crayon" to "can write their name" to "can button a shirt," gives your child a visible record of their growth. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s reward system can be set up to celebrate fine motor achievements, providing tangible reinforcement for the hard work these skills require.
**Focus on function, not perfection.** If your child can write legibly enough to be understood, that is success. If they can zip their jacket independently even if it takes longer than peers, that is success. The goal is functional independence, not flawless execution.
**Celebrate effort as much as outcome.** The child who spends ten focused minutes practicing letter formation, even if the letters are still wobbly, is building neural pathways that will eventually produce smoother output. The effort matters as much as the result.
Fine motor challenges are frustrating, but they are not permanent limitations. With targeted practice, the right tools, and patient support, neurodivergent children develop the hand skills they need to write, dress, eat, and create with increasing independence and confidence.

**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual routines that include fine motor practice, create step-by-step dressing sequences, and track your child's growing independence. Just $6.99/month after your trial, no credit card required upfront.
---
## Nature Play for Neurodivergent Children
Published: 2026-02-11
URL: https://vizyplan.com/blog/nature-play-outdoor-activities-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Research shows nature exposure reduces ADHD symptoms and supports sensory regulation in autistic children. Here are practical ways to bring the outdoors into your routine.
There is something about the outdoors that calms neurodivergent brains in ways that indoor environments simply cannot replicate. Maybe you have noticed it yourself: your child who is bouncing off the walls inside becomes focused and calm after thirty minutes at the park. The one who melts down in the grocery store can spend an hour exploring the backyard without a single struggle.
This is not a coincidence. A growing body of research demonstrates that nature exposure has measurable, significant benefits for children with ADHD, autism, and other forms of neurodivergence. The effects go beyond simply "burning off energy." Nature provides a unique sensory environment that actively supports regulation, attention, and emotional well-being.
The good news is that you do not need access to pristine wilderness to benefit. A backyard, a neighborhood park, a patch of grass, or even a window box with soil can provide the sensory input your child's brain is seeking.
## What the Research Shows
The evidence for nature's benefits to neurodivergent children is substantial and growing.
**Nature exposure reduces ADHD symptoms.** Landmark research by Frances Kuo and Andrea Faber Taylor at the University of Illinois found that children with ADHD who played in green outdoor settings showed significantly reduced symptoms compared to those who played indoors or in built outdoor environments. Their studies demonstrated that even a twenty-minute walk in a park improved concentration in children with ADHD to a degree comparable to the effects of common ADHD medications. Follow-up research has consistently replicated these findings.
**Green time outperforms screen time for regulation.** Multiple studies have compared the regulatory effects of nature exposure versus screen time for children with attention difficulties. The results consistently favor nature: outdoor play in natural settings provides more sustained improvements in attention, mood, and self-regulation than equivalent time spent with screens. This does not mean screens are always harmful, but it does suggest that nature should be prioritized when regulation is the goal.
**Sensory input in nature is uniquely regulating.** Unlike the sensory environment of indoor spaces, which tends toward artificial lighting, static temperatures, and repetitive sounds, natural environments provide rich, varied, and gently stimulating sensory input. The feel of grass underfoot, the sound of wind in leaves, the warmth of sunlight on skin, the visual complexity of trees and clouds. This input is varied enough to engage the senses without the overwhelming intensity of urban or indoor environments.
**Nature reduces cortisol levels.** Research on stress hormones in children has found that time in natural settings reduces cortisol levels, the body's primary stress hormone. For neurodivergent children who often operate with elevated baseline stress due to the constant demands of navigating a world not designed for their neurology, this cortisol reduction supports overall regulation and resilience.
## Sensory Benefits of Outdoor Play
Nature provides sensory input that many neurodivergent children actively need.
**Proprioceptive input.** Climbing trees, digging in dirt, pushing through tall grass, carrying sticks and rocks, and navigating uneven terrain all provide deep proprioceptive input that helps regulate the nervous system. Occupational therapists frequently recommend these types of "heavy work" activities for sensory regulation, and nature provides them naturally.
**Vestibular stimulation.** Swinging, spinning, rolling down hills, and balancing on logs all stimulate the vestibular system, which plays a critical role in body awareness and emotional regulation. Children who seek movement often find natural playground features more satisfying than manufactured equipment because the challenges are unpredictable and engaging.
**Tactile exploration.** Sand, water, mud, bark, leaves, grass, and stones offer an enormous range of textures. For children who are tactile seekers, this variety is deeply satisfying. For children who are tactile defensive, nature provides opportunities for gradual exposure in a low-pressure context, touching a leaf is less threatening than being asked to handle classroom art supplies.
**Auditory regulation.** Natural sounds, birdsong, running water, wind through branches, are processed differently by the brain than artificial sounds. Research on soundscapes has found that natural sounds activate the parasympathetic nervous system (the "rest and digest" response), while urban noise activates the sympathetic nervous system (the "fight or flight" response). For children with auditory sensitivities, natural environments often feel calmer and more tolerable.
## Practical Nature Activities by Sensory Profile
Different children benefit from different outdoor activities based on their sensory needs.
**For sensory seekers:**
- Jumping in puddles or mud
- Digging and building with sand or dirt
- Climbing over rocks and fallen trees
- Rolling down grassy hills
- Splashing in streams or using water play equipment
- Throwing and kicking piles of leaves
**For sensory avoiders:**
- Quiet nature walks on smooth paths
- Sitting under a tree and watching clouds
- Gentle gardening with soft soil
- Bird watching from a comfortable spot
- Walking barefoot on grass (if tolerated) for gradual exposure
- Blowing dandelion seeds or bubbles
**For children who need calming input:**
- Slow walks in wooded areas
- Sitting by running water and listening
- Lying in a hammock outdoors
- Cloud watching
- Mindful breathing exercises outside where air feels different
**For children who need alerting input:**
- Running on uneven terrain
- Climbing playground structures
- Racing between trees
- Playing catch with natural objects (pinecones, soft leaves)
- Obstacle courses using natural features
## Building Nature Into Your Routine
Consistency matters more than duration or location.
**Add outdoor time to the daily visual schedule.** When nature play appears on your child's visual routine, it becomes an expected part of the day rather than an optional addition. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual schedule feature lets you include outdoor time as a regular step, with images that show your child in outdoor settings.
**Start with what your child already enjoys.** If your child loves water, start with puddle jumping or a nature walk near a stream. If they love dinosaurs, look for rocks and fossils. Interest-driven nature engagement is more sustainable than generic "go outside and play" directives.
**Use nature play as a regulation tool.** When you notice your child is becoming dysregulated, an outdoor break can serve as a reset. "Let us go check on the garden" or "Let us walk to the mailbox" provides a sensory shift that indoor strategies cannot match.
**Prepare for sensory challenges outdoors.** Nature is not without sensory challenges: bugs, unexpected textures, temperature changes, and bright sunlight can all be triggers. Bring sunglasses, bug spray (fragrance-free if scent is a trigger), and allow your child to wear preferred clothing that protects against textures they find aversive.
**Track how nature affects your child's regulation.** Use [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking to log your child's emotional state before and after outdoor time. Over weeks, you will likely see clear evidence that nature exposure correlates with better regulation, which reinforces the habit for your whole family.
## Seasonal Nature Activities
Every season offers unique sensory opportunities.
**Spring:** Planting seeds, splashing in rain puddles, observing insects, feeling new grass grow **Summer:** Water play, sand exploration, longer outdoor time, nature scavenger hunts **Fall:** Collecting leaves, jumping in leaf piles, feeling cool breezes, observing seasonal changes **Winter:** Snow play (if climate allows), indoor seed starting, bird feeding, walking in quiet winter landscapes
Nature is not a cure for the challenges of neurodivergence. But it is a powerful, free, and consistently available tool that supports the regulation, attention, and emotional well-being your child needs to thrive. The outdoors was the original sensory gym, and it remains one of the most effective.

**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build daily routines that include nature play, track how outdoor time affects your child's mood and regulation, and create visual schedules that make the outdoors a consistent part of your family's rhythm. Just $6.99/month after your trial, no credit card required upfront.
---
## Helping Your Neurodivergent Child Through a Big Move
Published: 2026-02-10
URL: https://vizyplan.com/blog/moving-new-home-neurodivergent-child
Category: Strategies
Author: Justin Bowman
> How to help your autistic or ADHD child navigate the stress of moving to a new home, from preparation weeks in advance to settling into the new environment.
Moving to a new home is stressful for any family. For families with neurodivergent children, it can feel like dismantling the very foundation of your child's sense of safety. The bedroom they know by heart, the kitchen where breakfast always happens the same way, the route to school they have memorized, and the neighborhood sounds they have learned to tolerate. All of it changes at once.
Research on transition and change in autism consistently identifies environmental disruption as one of the most significant stressors for autistic individuals. The need for sameness that defines much of the autistic experience is directly challenged by a move. Every room is different. Every sound is new. Every routine must be rebuilt from scratch.
The good news is that with careful preparation, many neurodivergent children adjust to a new home more successfully than their parents expect. The key is starting early, providing concrete information in formats your child can process, and maintaining as much routine consistency as possible during the transition.
## Why Moving Is Especially Hard
Understanding the specific challenges helps you prepare for the right things.
**Environmental predictability is a regulatory tool.** Many neurodivergent children have memorized their home environment in extraordinary detail. They know exactly which floorboard creaks, where the light falls at different times of day, and how many steps it takes from their bed to the bathroom. This detailed environmental knowledge is not trivial. It serves as a regulatory foundation that reduces the cognitive load of navigating daily life. Losing it means every moment in the new home requires active processing that was previously automatic.
**Sensory environments vary dramatically between homes.** A new home has different acoustics, different lighting, different smells, different textures on the floors and walls, and different ambient sounds from the neighborhood. Each of these sensory changes requires adaptation from a system that may already be working at capacity.
**Routines break when spaces change.** Your child's bedtime routine was built around the specific layout of your current home: the hallway to the bathroom, the location of the light switch, the distance from the bed to the door. When the physical space changes, the routine that felt automatic no longer works. Every step must be consciously reconstructed.
**Uncertainty about the future creates anxiety.** Even with preparation, a child cannot fully understand what the new home will be like until they are living in it. For children who find safety in knowing exactly what to expect, this extended period of uncertainty leading up to and following the move generates chronic low-level anxiety that can manifest as increased rigidity, sleep disruption, behavioral changes, or regression in previously mastered skills.
## Preparing Weeks and Months in Advance
The preparation window for a neurodivergent child should be much longer than you might think.
**Introduce the concept gradually.** Use simple, concrete language: "Our family is going to live in a different house. We will bring all of our things with us." Do not overwhelm with details initially. Let your child absorb the basic concept before adding layers.
**Create a visual social story about moving.** Walk through the entire process: packing boxes, loading a truck, driving to the new house, unloading, and unpacking. Include specific details that will reassure your child: their bed is coming, their toys are coming, their favorite blanket is coming. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social story feature lets you create personalized narratives with AI-generated images, making the abstract concept of moving concrete and visible.
**Visit the new home multiple times before moving day.** If possible, take your child to the new house or apartment before the move. Let them explore each room. Take photos together. Show them where their bedroom will be, where the bathroom is, and where the kitchen is. These preview visits convert "the unknown new place" into "that house we visited."
**Create a visual countdown.** A calendar showing how many days until the move, with one day crossed off each evening, gives your child a concrete way to track the approaching change. Knowing "fourteen more sleeps in this house" is more manageable than the vague sense that change is coming eventually.
**Let your child participate in packing.** Involve them in packing their own room, especially their treasured items. This gives them a sense of control over the process and reassurance that their belongings are coming with them. Let them choose what goes in a special "first to unpack" box that will be opened immediately upon arrival.
## Maintaining Routines During the Move
Routines are your lifeline during a major transition.
**Preserve as many routines as possible.** The move changes the physical environment, but you can keep everything else the same. Same breakfast, same bedtime routine, same order of activities, same morning sequence. These consistent elements provide stability when the surroundings are unfamiliar.
**Recreate the room layout when possible.** Placing furniture in a similar arrangement to the previous home reduces the disorientation of the new space. If your child's bed was against the left wall with the nightstand on the right, recreating that arrangement provides instant familiarity.
**Unpack your child's room first.** Before you worry about the kitchen or the living room, get your child's space set up. Having their room feel familiar while the rest of the house is still in chaos gives them a safe base to retreat to when the change feels overwhelming.
**Update visual schedules immediately.** Create new visual routines for the new space, including step-by-step sequences for navigating the new bathroom, finding the kitchen for breakfast, and the new path from bedroom to front door. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) makes it easy to update visual schedules quickly as your environment changes, so your child has a current reference from day one.
**Bring comfort items to the new house first.** Your child's weighted blanket, favorite stuffed animal, white noise machine, and any other regulatory tools should be among the first items placed in the new home. These familiar sensory anchors ease the transition.
## Managing Moving Day
Moving day itself is the most chaotic part of the process. Plan for it specifically.
**Consider having your child elsewhere during the move.** If possible, have a trusted family member or friend spend the day with your child while the actual packing, loading, and unloading happens. The chaos of moving day can be sensory overload at its peak.
**If your child is present, create a designated safe space.** Set up a corner with their comfort items, snacks, and preferred activities away from the main action. A tablet with headphones, their favorite books, and a familiar blanket create a bubble of calm in the chaos.
**Prepare for a difficult first night.** The first night in a new home is often the hardest. New sounds, new shadows, new smells, and a profound sense of "not home" can make sleep nearly impossible. Have extra patience, extra comfort measures, and flexible expectations for the first several nights.
## Settling Into the New Home
Adjustment is not instant. Budget weeks, not days, for your child to settle in.
**Explore the new home together.** Walk through each room with your child. Name what happens in each space: "This is where we eat breakfast. This is where we watch movies." Connecting familiar activities to new spaces builds associations that replace the lost environmental knowledge.
**Create new visual maps.** A simple floor plan showing which room is which, where the bathroom is in relation to the bedroom, and where to find snacks helps your child build the mental map that was automatic in the previous home.
**Introduce the neighborhood gradually.** Walk the block together. Visit the nearest park. Drive the route to school or the store. Each outing builds familiarity with the surroundings, reducing the feeling of being in completely foreign territory.
**Track emotions through the transition.** [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking lets you monitor how your child is adjusting over time. You might see intense distress in the first week that gradually decreases, or you might identify specific triggers in the new environment that need addressing, like a bedroom that is too bright or a neighbor's dog that barks unpredictably.
**Expect regression and respond with patience.** Sleep disruption, increased meltdowns, clinginess, loss of previously mastered skills, and heightened rigidity are all normal adjustment responses. These are not permanent setbacks. They are temporary stress responses that will resolve as familiarity builds.
Moving is one of life's biggest transitions, and your neurodivergent child will need more support, more preparation, and more patience than typical. But with the right approach, the new home can become just as safe and familiar as the one you left.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Create social stories about moving, build visual schedules for the new home, and track your child's emotional adjustment through this big transition. Just $6.99/month after your trial, no credit card required upfront.
---
## Teaching Turn-Taking and Sharing to Neurodivergent Children
Published: 2026-02-09
URL: https://vizyplan.com/blog/teaching-turn-taking-sharing-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Evidence-based approaches to teaching turn-taking and sharing skills to children with autism and ADHD using visual supports, structured games, and social stories.
"It is my turn!" "I had it first!" "That is not fair!" If these phrases echo through your home on a daily basis, you are living the reality of teaching social sharing skills to a neurodivergent child. Turn-taking and sharing are among the earliest social expectations children encounter, and they are also among the most difficult for children whose brains process social situations differently.
The frustration is real for everyone involved. Your child struggles to wait, to relinquish a desired item, or to understand why another person's needs should temporarily take priority over their own. Siblings feel frustrated. Playdates become stressful. And you wonder whether your child will ever develop these fundamental social skills.
The good news is that turn-taking and sharing are teachable skills, not fixed personality traits. With visual supports, structured practice, and the right approach, neurodivergent children can absolutely learn to navigate these social expectations. The key is understanding why these skills are harder for their specific brain and building the instruction around that understanding.
## Why Turn-Taking Is Uniquely Challenging
Several neurological factors converge to make turn-taking especially difficult for neurodivergent children.
**Impulse control develops differently in ADHD.** The ability to inhibit an impulse, to stop yourself from grabbing a toy you want right now, relies on prefrontal cortex functions that develop more slowly in children with ADHD. Research consistently shows that response inhibition is one of the core deficits in ADHD. Your child may genuinely understand the rule of taking turns but be unable to override the impulse to act immediately when they want something.
**Perspective-taking requires abstract thinking.** Understanding that another person also wants a turn with the toy requires theory of mind, the ability to understand that others have thoughts, feelings, and desires different from your own. Many autistic children develop theory of mind skills on a different timeline. Without this understanding, turn-taking rules feel arbitrary rather than logical.
**Cognitive rigidity affects flexibility.** Some autistic children develop strong associations between themselves and specific objects or activities. "That is MY puzzle" or "I always go first" reflects rigid thinking patterns that make sharing feel like a violation of the rules as they understand them. This is not selfishness. It is a brain that craves consistency and resists changes to established patterns.
**Emotional regulation is tested.** Waiting for a turn or giving up a preferred item triggers strong emotions: frustration, anxiety, disappointment. For children whose emotional regulation is already working harder than typical, these feelings can escalate quickly into meltdowns that make the social situation worse.
## Visual Turn-Taking Cues
Making the abstract concept of "turns" concrete and visible dramatically improves comprehension and compliance.
**Use a physical turn-taking object.** A special "turn card," a designated hat, or a specific toy that indicates "it is your turn" gives the abstract concept a tangible form. Whoever holds the turn marker has the turn. When you pass it, the turn passes. This removes ambiguity about whose turn it is.
**Create a visual turn order.** A simple chart showing names or photos in order, with a movable marker indicating whose turn is current, lets everyone see the sequence. Your child can look at the chart and see that their turn is coming rather than relying on verbal promises that feel uncertain. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) lets you create personalized visual sequences that can include turn-taking steps within activities, making the structure clear and predictable.
**Use visual timers for timed turns.** When sharing a single toy or activity, set a visible timer for each person's turn. When the timer goes off, the turn changes. The timer is a neutral authority that removes the social negotiation that many neurodivergent children find overwhelming.
**Post turn-taking rules visually.** A simple poster with rules like "Look at the turn chart," "Wait for the timer," and "Say: Can I have a turn?" gives your child a reference they can check independently during play.
## Social Stories for Sharing
Social stories prepare your child cognitively and emotionally for sharing situations before they happen.
**Create stories for specific scenarios.** A story about sharing toys with a sibling during playtime, a story about taking turns on the playground swing, or a story about sharing materials in a classroom each addresses a different context your child encounters. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social story feature with AI-generated personalized images lets you build stories that look like your child in their actual environments, increasing engagement and relevance.
**Include the feelings of all parties.** A good sharing social story names how your child feels when they have to wait ("I might feel frustrated when it is not my turn. That is okay.") AND how the other person feels ("My friend feels happy when they get a turn too."). This dual perspective builds the empathy foundation that supports genuine sharing.
**Practice the story before the situation.** Read the social story about playground sharing before going to the park. Review the toy-sharing story before a playdate begins. This pre-teaching gives your child a script to follow when the real situation arises.
## Structured Games for Practice
Games provide a natural, low-pressure context for practicing turn-taking.
**Start with two-player games.** The simplest turn-taking structure involves just two people. Board games, card games, or simple activities like rolling a ball back and forth create frequent turn-taking opportunities with minimal wait time between turns.
**Choose games with short turns.** Games where each turn takes only a few seconds (rolling dice, drawing a card, placing a piece) minimize the waiting time between turns. Long turns, like extended puzzle-building or complex strategy, increase the difficulty of waiting.
**Use games your child is motivated by.** A child who loves dinosaurs will tolerate the waiting inherent in a dinosaur-themed game far better than a generic card game. Interest-based motivation compensates for the executive function demands of turn-taking.
**Gradually increase complexity.** Move from two-player to three-player games, from short turns to longer turns, and from adult-supervised games to peer-supervised play. Each step builds on the last, expanding your child's capacity gradually.
## Addressing Common Challenges
Even with preparation, specific challenges will arise.
**When your child grabs.** Respond calmly: "I see you want the truck. Right now it is Sam's turn. Your turn is next. Let us look at the timer." Redirect to the visual supports rather than lecturing about the rule. If grabbing persists, physically interrupt gently and help your child hand the item back, then immediately provide the visual timer showing when their turn begins.
**When your child refuses to give up their turn.** Offer a transition warning: "You have one more minute with the blocks, then it is your sister's turn." Use the visual timer. If the transition is still difficult, ensure the reward for taking turns is meaningful and immediate.
**When sharing triggers a meltdown.** Acknowledge the feeling first: "You are really upset because you wanted more time with that toy." Once your child is regulated, review the social story or visual rules. Do not try to teach during the meltdown. Regulation first, instruction second.
**When your child "shares" by controlling.** Some children learn to share technically but control the interaction entirely ("You can have it, but only if you use it this way"). This is a step in the right direction. Gently expand flexibility over time rather than correcting the control immediately.
## Building Toward Natural Sharing
The goal is not robotic compliance with turn-taking rules but genuine social understanding.
**Acknowledge when sharing happens naturally.** When your child spontaneously offers a toy or waits patiently for their turn, name it specifically: "You noticed your brother wanted the blue crayon and you handed it to him. That was really kind." Specific praise reinforces the behavior more effectively than generic "Good job."
**Use [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s reward system to track social wins.** Set up sharing and turn-taking as trackable goals. When your child earns points for successful sharing, the visual progress provides sustained motivation beyond the individual moment.
**Model sharing in your own interactions.** "I am going to share some of my snack with you because sharing feels good." "It is Dad's turn to pick the movie tonight. Tomorrow is your turn." Children learn social skills by watching the adults around them practice those same skills consistently.
Turn-taking and sharing are not skills that develop overnight. They build slowly through repeated practice, consistent visual supports, and a patient approach that respects the genuine neurological challenges your child faces. Every successful turn, every moment of willing sharing, is a step toward social competence that will serve them throughout their life.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Create social stories, visual turn-taking sequences, and reward systems that make learning to share structured and motivating. Just $6.99/month after your trial, no credit card required upfront.
---
## After-School Routines for Neurodivergent Children
Published: 2026-02-08
URL: https://vizyplan.com/blog/after-school-routine-transitions-neurodivergent-children
Category: Daily Routines
Author: Justin Bowman
> How to create smooth school-to-home transitions for neurodivergent children, including managing after-school meltdowns, decompression time, and visual afternoon schedules.
Your child holds it together all day at school. They follow directions, manage social interactions, cope with sensory input, and meet academic demands. Then they walk through the front door and everything falls apart. The tears, the screaming, the aggression, or the complete shutdown that happens within minutes of arriving home can be baffling and exhausting for parents who wonder what went wrong.
Nothing went wrong. What you are witnessing has a name: after-school restraint collapse. It is the result of your child spending their entire regulatory capacity at school, leaving nothing in reserve for the transition home. Therapists and educators increasingly recognize this pattern as one of the most common and least understood challenges facing neurodivergent families.
The good news is that a structured after-school routine, designed around your child's specific needs, can dramatically reduce the intensity and frequency of these meltdowns. The key is understanding that the after-school period is not the time to add more demands. It is the time to restore what school has depleted.
## Understanding After-School Restraint Collapse
The science behind after-school meltdowns explains why your well-behaved school student transforms at home.
**Masking depletes regulatory resources.** Many neurodivergent children, especially autistic children, engage in "masking" at school. They suppress natural behaviors like stimming, monitor their social responses constantly, and work to appear neurotypical. This sustained effort is cognitively and emotionally exhausting. Research on autistic masking, sometimes called camouflaging, has linked it to increased anxiety, depression, and burnout. When the child reaches the safety of home, the mask drops and the accumulated stress releases.
**Sensory overload accumulates throughout the day.** A school day is a marathon of sensory input: fluorescent lights, echoing hallways, crowded cafeterias, unexpected fire drills, the smell of markers and cafeteria food. Sensory input that would be manageable in isolation becomes overwhelming when experienced continuously for six to eight hours. By dismissal, the sensory cup is overflowing.
**Executive function fatigue is real.** Following multi-step instructions, transitioning between classes, organizing materials, planning assignments, and managing time all draw from the same executive function resources. For children with ADHD, these resources are already limited. A full school day can exhaust them completely.
**The transition itself is a trigger.** Moving from the structured, predictable school environment to the comparatively unstructured home environment requires significant cognitive flexibility. The rules change, the expectations shift, and the child must reorganize their understanding of what is expected. For children who struggle with transitions, this shift alone can push them past their threshold.
## Designing a Decompression Period
The first thirty to sixty minutes after school should focus entirely on regulation, not productivity.
**Build in a sensory break immediately.** Before homework, chores, questions about the school day, or any demands, give your child access to regulating activities. This might look like:
- Jumping on a trampoline or swinging for proprioceptive input
- Retreating to a quiet, dim room with a weighted blanket
- Watching a familiar, comforting show
- Eating a preferred snack in a calm environment
- Stimming freely without correction
- Listening to music with headphones
**Do not require conversation right away.** "How was school today?" is a well-meaning question that can feel like an interrogation to a depleted child. The demand to recall, organize, and verbalize information about the day requires executive function they may not have available. If you want to hear about their day, save it for later, after dinner or during a calm bedtime routine when some regulation has been restored.
**Respect the crash.** Some children need to lie on the floor, hide under blankets, or engage in behaviors that seem "unproductive." This is not laziness. It is a nervous system that needs time to decompress. Trying to redirect them immediately into the afternoon routine will likely backfire.
**Match the decompression to your child's sensory profile.** A child who is sensory-seeking may need intense physical activity. A child who is sensory-avoidant may need a dark, quiet space. A child who has been suppressing stimming all day may need permission to stim freely. There is no one-size-fits-all decompression strategy.
## Creating a Visual After-School Schedule
Once the decompression period ends, a visual schedule provides the predictable structure your child needs.
**Keep the afternoon schedule simple.** An after-school routine does not need to include eight activities. Four to six clearly defined steps are usually sufficient:
- Decompression time
- Snack
- Homework or independent play
- Free time or preferred activity
- Dinner preparation or family activity
**Post it where your child can see it.** The after-school visual schedule should be visible as soon as your child walks in the door. Seeing what the afternoon holds immediately provides the predictability that reduces anxiety about the unstructured hours ahead.
**Include preferred activities.** The schedule should not be all demands. When children can see that free time or a favorite activity is coming, they are more willing to tolerate the less preferred steps that come before it. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual schedule feature lets you create a personalized afternoon routine that balances obligations with restorative activities, with images your child connects to.
**Build in flexibility markers.** Some afternoons your child will need a longer decompression period or a simpler homework session. Having a "flex" option in the visual schedule, perhaps a choice card where they can pick between two acceptable activities, gives them agency without abandoning the routine entirely.
## Managing Homework After School
Homework is often the biggest flashpoint of the after-school period.
**Timing matters enormously.** Many neurodivergent children cannot do homework immediately after school. Their cognitive resources are depleted, and forcing academic work onto an exhausted brain leads to frustration, tears, and work that does not reflect their actual ability. Experiment with different timing: right after the decompression period, after dinner, or even in the morning before school.
**Break homework into visual chunks.** Rather than presenting the full homework assignment as one block, break it into small steps with a visual checklist. Each completed step gets checked off, providing visible progress and regular doses of accomplishment.
**Use a first-then board.** "First, complete five math problems. Then, ten minutes of tablet time." The visual structure makes the expectation and reward clear. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s first-then functionality provides this structure in a format your child can reference independently.
**Advocate for accommodations if needed.** If homework consistently causes significant distress, talk to your child's teacher or IEP team. Reduced homework, modified assignments, or alternative formats may be appropriate. The after-school hours are too important for family connection and regulation to be consumed entirely by academic battles.
## Tracking After-School Patterns
Understanding your child's after-school patterns helps you optimize the routine.
**Log the intensity of after-school meltdowns.** Using [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking, record how your child presents when they arrive home each day. Over time, patterns emerge. Maybe Mondays are hardest because the transition from weekend is still fresh. Maybe gym days are easier because physical activity at school provided some regulation.
**Note what helps.** Track which decompression activities actually reduce meltdown intensity and duration. You might discover that your child does best with twenty minutes of screen time followed by a physical activity, or that a specific snack consistently improves their afternoon mood.
**Communicate patterns to the school.** If tracking reveals that certain school activities consistently predict worse after-school collapse, sharing this data with teachers and therapists can lead to in-school accommodations that reduce the buildup.
**Adjust the routine seasonally.** After-school needs shift with the seasons. Longer daylight in summer may mean more outdoor decompression time. Winter darkness may require adjusting the schedule to accommodate your child's energy levels.
The after-school period is not a parenting failure. It is a natural consequence of the enormous effort your neurodivergent child puts in every day at school. By building a routine that prioritizes regulation before demands, you give your child the space to recover and the structure to navigate the afternoon successfully.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Create personalized after-school visual schedules, track emotional patterns, and build routines that turn chaotic afternoons into structured, manageable time. Just $6.99/month after your trial, no credit card required upfront.
---
## Teaching Waiting and Patience to Your Neurodivergent Child
Published: 2026-02-07
URL: https://vizyplan.com/blog/teaching-waiting-patience-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Why waiting is uniquely challenging for children with ADHD and autism, and research-backed strategies including visual timers, wait cards, and structured practice.
"Just wait a minute." For most children, this is a mildly frustrating instruction. For neurodivergent children, it can feel like being asked to hold their breath underwater with no idea when they will be allowed to come up for air. The concept of waiting, with its inherent uncertainty and invisible timeline, is one of the most fundamentally difficult skills for children with ADHD, autism, and other forms of neurodivergence.
If your child melts down in checkout lines, cannot wait for their turn in a game, or falls apart when dinner is not ready the moment they feel hungry, you are experiencing the real-world impact of neurological differences in time perception, impulse control, and tolerance for uncertainty. These are not behavioral choices. They are brain-based challenges that require specific strategies to address.
The good news is that waiting can be taught. Not through repeated lectures about patience, but through concrete, visual tools that make the invisible passage of time something your child can see, understand, and manage.
## Why Waiting Is So Hard
Understanding the neurology behind waiting difficulties changes how you respond to them.
**Time blindness is real.** Research on ADHD and time perception consistently shows that children with ADHD experience time differently than neurotypical peers. Studies published in neuropsychological journals have found that children with ADHD significantly overestimate how much time has passed during waiting periods. A two-minute wait can feel like ten minutes to a child with time processing differences. This is not impatience. It is a genuine perceptual difference.
**Impulse control develops on a different timeline.** The prefrontal cortex, which manages impulse control and delayed gratification, develops more slowly in children with ADHD. Research suggests that executive function development in ADHD may lag three to five years behind chronological age. A seven-year-old with ADHD may have the impulse control capacity of a four-year-old, which reframes their "impatient" behavior as developmentally appropriate for their executive function level.
**Uncertainty is intolerable for many autistic children.** When an autistic child asks "How long?" and receives a vague answer like "Soon" or "In a little bit," the lack of concrete information creates anxiety. Autistic brains often process information in concrete, specific terms. An undefined wait period is an unresolved variable that generates ongoing stress until it resolves.
**Emotional regulation is depleted by waiting.** Waiting requires sustained self-regulation, holding back an impulse or tolerating an unpleasant state over time. For children whose regulation capacity is already taxed by navigating a sensory and social world that was not designed for their neurology, the additional demand of waiting can exceed their available resources.
## Making Time Visible
The most powerful strategy for teaching waiting is making the invisible visible.
**Visual timers change the game.** A timer that shows time as a shrinking colored section, a sand timer with visible particles flowing, or a digital countdown with numbers all transform "wait" from an abstract concept into a concrete, observable process. Research on visual timer interventions for autistic children has shown significant reductions in challenging behavior during waiting periods when visual timers are used consistently.
**Choose the right timer for your child.** Sand timers work well for short waits (one to five minutes) and are satisfying to watch. Red-disk timers (like the Time Timer) show the passage of time as a shrinking colored segment. Digital countdowns work for children comfortable with numbers. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual schedule feature can incorporate timed waiting steps into your child's daily routine, making anticipated waits part of the predictable structure.
**Use specific time language.** Replace vague time words with concrete ones. Instead of "Soon," say "In five minutes." Instead of "Later," say "After lunch." Instead of "Not now," say "When the timer reaches zero." Every specific time reference reduces uncertainty and gives your child something concrete to anchor to.
**Create visual wait sequences.** For longer waits, like waiting for a special event, a visual countdown calendar showing how many days remain gives your child a way to track progress toward the goal. Crossing off each day makes the passage of time tangible.
## The Wait Card Strategy
Wait cards are a simple, powerful tool from behavioral research.
**How they work.** A wait card is a visual cue, often a card with a hand signal or the word "wait" with a picture, that you show your child when they need to wait. The card serves as an external signal that replaces the verbal instruction, which can be harder for some children to process during moments of heightened emotion.
**Pair with a visual timer.** Show the wait card and simultaneously start a visual timer. This combination tells your child both what to do (wait) and how long they need to do it. The timer removes the uncertainty that makes waiting so aversive.
**Start with very short waits.** Begin with ten-second waits and reward success immediately. Gradually extend the duration as your child builds tolerance. Going from ten seconds to thirty seconds to one minute to three minutes over weeks of practice builds genuine capacity.
**Reward waiting successfully.** When the timer ends and your child has waited, provide immediate positive reinforcement. A verbal acknowledgment, a sticker, a token toward a larger reward, or access to the desired activity all strengthen the connection between waiting and positive outcomes. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s reward system makes this tracking visual and motivating.
## Structured Practice in Low-Stakes Moments
Waiting skills are best learned during calm, controlled situations, not during the meltdown in the grocery checkout line.
**Practice at home first.** Set up deliberate waiting practice during relaxed moments. "I am going to set the timer for one minute. When it goes off, you can have your snack." Start when your child is regulated and motivated, not when they are already stressed.
**Use preferred activities as motivation.** "First we wait for two minutes, then we play your favorite game." When the reward on the other side of the wait is highly motivating, tolerance for the wait increases. Visual first-then boards make this structure clear and concrete.
**Build waiting into daily routines.** Embed small waiting moments throughout the day: waiting thirty seconds before screen time starts, waiting one minute between requesting a snack and receiving it, waiting for a sibling to finish before taking a turn. These micro-practices accumulate into genuine skill.
**Play games that involve waiting.** Board games with turn-taking, freeze dance, red-light-green-light, and other structured games provide fun contexts for practicing the skill of waiting. The game format makes the practice enjoyable rather than clinical.
## Managing Waiting in Public
Real-world waits are less predictable than practice sessions, but preparation helps.
**Bring a waiting toolkit.** A small bag with fidget toys, a favorite book, a drawing pad, or a handheld game gives your child something to do during unexpected waits. Occupied hands and an engaged mind make waiting far more tolerable.
**Preview expected waits.** Before going to the doctor's office, restaurant, or store, tell your child there will be waiting and show them approximately how long. Use [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social story feature to walk through the outing, including the waiting parts, so your child knows what to expect.
**Acknowledge the difficulty.** Saying "I know waiting is really hard for your brain, and you are doing a great job" validates your child's experience while reinforcing their effort. Dismissing the difficulty with "It is not that long" invalidates a genuine neurological experience.
**Have an exit plan.** For situations where waiting becomes genuinely intolerable, having a plan to step outside, take a movement break, or leave and return reduces the pressure on both you and your child.
## Tracking Progress
Waiting tolerance develops gradually, and tracking helps you see the growth.
**Log successful waits.** Note the duration, the context, and what strategies helped. Over time, you will see patterns: your child waits better in the morning, or with the sand timer, or when they have a fidget available. This data guides your approach.
**Use [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking.** Recording how your child feels during and after waiting periods reveals whether their tolerance is genuinely growing or whether they are simply complying while becoming increasingly distressed. Both pieces of information matter.
**Celebrate milestones.** The first time your child waits a full minute without distress, the first successful restaurant wait, the first time they independently use a coping strategy during a wait. These moments deserve recognition.
Patience is not a personality trait your child is lacking. It is a skill that can be built, one visible timer and one successful wait at a time.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build visual schedules with timed steps, reward systems that motivate, and social stories that prepare your child for waiting situations. Just $6.99/month after your trial, no credit card required upfront.
---
## Building a Teeth Brushing Routine That Works
Published: 2026-02-06
URL: https://vizyplan.com/blog/teeth-brushing-routine-autism-adhd
Category: Daily Routines
Author: Justin Bowman
> Evidence-based strategies for overcoming teeth brushing challenges in children with autism and ADHD, from sensory accommodations to visual step-by-step guides.
Teeth brushing is one of those daily tasks that sounds simple until you are standing in the bathroom with a screaming child who will not open their mouth. For families of neurodivergent children, this twice-daily routine can become one of the most dreaded parts of the day. The battles, the tears, and the guilt about whether you are doing enough for your child's dental health add up quickly.
Research reveals that children with autism and ADHD experience significantly higher rates of dental problems compared to neurotypical peers. Studies published in the Journal of Autism and Developmental Disorders have found that autistic children are more likely to have untreated cavities, partly because the sensory challenges of oral hygiene make consistent brushing so difficult. Understanding why brushing is hard is the first step toward making it easier.
The good news is that with the right accommodations, tools, and visual supports, most neurodivergent children can develop a functional teeth brushing routine. It may look different from what the dentist recommends in their standard pamphlet, and that is perfectly fine.
## Why Teeth Brushing Is So Challenging
The mouth is one of the most sensory-dense areas of the body. For children with sensory processing differences, oral care activates multiple triggers simultaneously.
**Tactile hypersensitivity in the mouth.** The bristles of a toothbrush create intense tactile input on the gums, tongue, teeth, and inner cheeks. For a child with oral tactile defensiveness, this sensation can feel genuinely painful rather than mildly uncomfortable. The pressure, the scrubbing motion, and the texture of bristles can all trigger a defensive response.
**Taste and texture of toothpaste.** Mint flavoring, which dominates the toothpaste market, creates a burning or tingling sensation that many neurodivergent children find intolerable. The foaming action of standard toothpaste adds another unwanted texture. Even the grittiness of the paste can trigger gagging in sensitive children.
**Vibration from electric toothbrushes.** While electric toothbrushes clean more effectively, the vibration can be overwhelming for sensory-sensitive children. The buzzing feeling that travels through the jaw and into the skull is a unique sensory input that many children reject.
**Executive function demands.** Brushing requires a multi-step sequence: get the toothbrush, apply toothpaste, brush all quadrants of the mouth systematically, spit, rinse, and put everything away. For children with ADHD or executive function challenges, maintaining this sequence twice daily requires more cognitive effort than adults typically realize.
**Interoception challenges.** Some neurodivergent children do not experience the "dirty mouth" feeling that motivates most people to brush. Without that internal signal, there is no natural motivation driving the behavior.
## Finding the Right Tools
The standard toothbrush and minty toothpaste combination is not the only option. Finding tools that work with your child's sensory profile makes everything easier.
**Toothbrush options:**
- Extra-soft bristle brushes reduce tactile intensity
- Finger brushes (silicone brushes that fit over your finger) give you more control and feel less invasive for younger children
- Three-sided toothbrushes clean all surfaces simultaneously, reducing the time spent brushing
- Vibrating toothbrushes with gentle settings may work for children who seek proprioceptive input
- Chewable toothbrushes allow biting rather than traditional brushing for children who resist having a brush placed in their mouth
**Toothpaste alternatives:**
- Unflavored toothpaste eliminates the taste barrier entirely
- Fruit-flavored children's toothpaste avoids the mint sensation
- Non-foaming formulas reduce the texture issue
- Training toothpaste without fluoride is safe to swallow, removing the spitting requirement for children who struggle with that step
- For some children, brushing with just water is better than not brushing at all
**Let your child choose.** Bring them to the store and let them touch different brush textures and smell different toothpaste flavors. Ownership over the tools increases willingness to use them.
## Creating a Visual Brushing Routine
Visual supports transform teeth brushing from an abstract demand into a concrete, step-by-step process.
**Break it down into manageable steps.** A visual sequence posted at your child's eye level in the bathroom might include:
- Pick up toothbrush
- Put toothpaste on brush
- Brush top teeth
- Brush bottom teeth
- Brush tongue (optional for some children)
- Spit
- Rinse mouth
- Put toothbrush away
**Use a visual timer.** Dentists recommend two minutes of brushing. A visual timer, whether a sand timer, a phone app, or a visual countdown, shows your child exactly how much time remains. Open-ended brushing feels infinite. Two minutes with a visible countdown feels manageable. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual schedule feature lets you create a personalized brushing sequence with timed steps, so your child knows exactly what comes next and how long each step lasts.
**Add brushing to the daily routine visual.** When teeth brushing appears as part of the morning and bedtime visual schedule, it becomes an expected part of the routine rather than a sudden demand. Predictability reduces resistance.
## Desensitization Strategies
For children with significant oral sensitivity, gradual exposure builds tolerance over time.
**Start outside the mouth.** Let your child hold the toothbrush and explore it with their hands. Touch it to their lips. Run it along their cheek. Each step builds familiarity before introducing the brush inside the mouth.
**Use oral massage as preparation.** Gently rubbing the outside of the jaw, the cheeks, and the lips before brushing provides proprioceptive input that can calm the oral area and reduce defensiveness. Occupational therapists often recommend this technique as a pre-brushing routine.
**Work in quadrants.** Instead of expecting full brushing from day one, start with one section of the mouth. Add another section when the first becomes tolerable. Building gradually prevents the overwhelming sensation of having the entire mouth stimulated at once.
**Pair brushing with preferred activities.** Some children tolerate brushing better while watching a favorite video or listening to a preferred song. The competing positive sensory input can reduce the focus on the unpleasant oral sensation.
**Consider timing within the routine.** Some children handle brushing better right after a bath when their body is warm and relaxed. Others do better when brushing is the very first step of the routine, before any other demands have depleted their regulation capacity. Track what works for your child using [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking to identify optimal timing patterns.
## Reward Systems for Brushing
Positive reinforcement builds the habit while reducing resistance.
**Immediate visual rewards work best.** A sticker on a chart right after brushing, a check mark on the visual schedule, or a token added to a jar provides instant positive feedback. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s built-in reward system makes tracking brushing success simple and visually motivating for your child.
**Reward effort and tolerance, not perfection.** In the early stages, reward any engagement with the toothbrush. Holding it. Touching it to their lips. Allowing one stroke. The goal is building positive associations, not achieving dental perfection immediately.
**Let your child see progress accumulating.** Visual trackers showing consecutive days of brushing, even partial brushing, build momentum. Children who can see their streak growing often become motivated to maintain it.
## Working With Your Dentist
A supportive dental team makes an enormous difference.
**Find a pediatric dentist experienced with neurodivergent children.** These practitioners understand sensory accommodations, can modify their approach, and will not shame your child or your family for imperfect oral hygiene.
**Share your visual tools with the dental team.** If your child uses a visual brushing sequence at home, bringing it to dental appointments creates continuity that reduces anxiety in the clinical setting.
**Be honest about your child's current routine.** A dentist who knows your child can only tolerate thirty seconds of brushing can provide targeted advice that meets your family where you are, rather than reciting the standard two-minute recommendation that feels impossible to achieve.
**Ask about sealants and other preventive measures.** If brushing remains extremely limited, dental sealants and fluoride varnish provide additional cavity protection while you continue working on building the brushing routine.
Progress with teeth brushing is often slow, and that is completely normal. A child who currently refuses to open their mouth will not transform into an enthusiastic brusher overnight. But with consistent, gentle exposure and the right visual supports, most children make meaningful progress over weeks and months.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Build personalized brushing routines with visual sequences, timers, and reward tracking that make oral hygiene achievable for your neurodivergent child. Just $6.99/month after your trial, no credit card required upfront.
---
## Sensory-Friendly Haircuts for Neurodivergent Children
Published: 2026-02-05
URL: https://vizyplan.com/blog/sensory-friendly-haircuts-neurodivergent-children
Category: Daily Routines
Author: Justin Bowman
> Practical strategies for making haircuts less stressful for children with autism and ADHD, including desensitization techniques, visual preparation, and sensory accommodations.
Few experiences capture the collision of sensory overload and loss of control quite like a haircut. The buzzing clippers, the cold spray bottle, the unfamiliar hands touching their head, the scratchy cape around their neck, and tiny hair clippings landing on skin. For neurodivergent children, what should be a routine grooming task can become a genuinely distressing experience that the whole family dreads.
If you have ever left a salon in tears, held your child through a meltdown in a barber chair, or simply given up and let their hair grow indefinitely, you are not alone. Haircut avoidance is one of the most commonly reported grooming challenges among families of neurodivergent children.
The good news is that with the right preparation, accommodations, and gradual exposure, haircuts can become manageable and even positive. It takes patience and a willingness to do things differently, but countless families have found their way through this challenge.
## Why Haircuts Are So Difficult
Understanding the specific triggers helps you address them systematically rather than guessing.
**Sensory overload is the primary barrier.** Research consistently shows that over 90% of autistic children experience some form of sensory processing difference. During a haircut, multiple sensory systems are activated simultaneously: tactile (touch on the head, neck, and face), auditory (clippers, scissors, background salon noise), visual (bright lights, mirrors, unfamiliar environment), and even olfactory (hair products, cleaning solutions). This sensory bombardment can overwhelm a nervous system that is already working harder than typical to filter input.
**Loss of control increases anxiety.** Haircuts require sitting still while someone else does something to your body. For children who find safety in predictability and autonomy, this forced passivity is deeply uncomfortable. They cannot control when the stylist touches them, what tool comes next, or how long it will take.
**Unpredictability compounds the stress.** Even with preparation, each haircut unfolds slightly differently. The stylist may use a different technique, the salon may be louder than last time, or the water may be a different temperature. For children who depend on sameness, these small variations can feel enormous.
**Past negative experiences create lasting associations.** One bad haircut experience can establish a fear response that persists for months or years. The child's brain has learned that haircuts equal distress, and that association is difficult to override without intentional, positive counter-experiences.
## Preparing Before the Haircut
Preparation is where most of the progress happens. The work you do in the days and weeks before the appointment matters far more than what happens in the chair.
**Create a visual social story about haircuts.** Walk through the entire experience step by step: driving to the salon, checking in, sitting in the chair, having a cape put on, hair getting wet, cutting with scissors or clippers, brushing off hair, and leaving. Use images your child can connect with. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social story feature lets you create personalized narratives with AI-generated images that look like your child in a salon setting, making the abstract idea of a haircut concrete and familiar.
**Practice sensory exposures at home.** Gradually introduce the sensations your child will encounter:
- Run a comb through their hair with gentle pressure
- Spray water from a spray bottle onto their arms, then neck, then hair
- Turn on an electric razor near them (without touching) to familiarize them with the sound and vibration
- Drape a towel or light blanket around their shoulders to simulate a cape
- Have them sit in a tall chair while you stand behind them
**Visit the salon without getting a haircut.** Take a trip just to look around. Let your child sit in the chair. Meet the stylist. Explore the space. This preview visit removes the novelty that contributes to anxiety on the actual appointment day.
**Schedule strategically.** Book the first appointment of the day when the salon is quietest. Ask for the last chair in the row, farthest from noise and foot traffic. Choose a time when your child is typically well-regulated, not hungry, tired, or already overstimulated.
## Sensory Accommodations During the Haircut
Small adjustments to the sensory environment make a significant difference.
**Noise management.** Bring noise-canceling headphones or earplugs. If your child tolerates it, playing familiar music or a favorite show on a tablet with headphones can provide a comforting auditory focus that masks the salon sounds.
**Tactile modifications.** Ask the stylist to use a soft cloth rather than a standard cape. Some children do better without a cape at all, even if it means more cleanup. Bring a familiar comfort item, a stuffed animal, a fidget toy, or a stress ball for their hands.
**Visual supports.** A visual countdown showing how many snips or sections remain gives your child a sense of progress and an end point. You can hold up fingers or use a simple number chart. Knowing "three more sections and we are done" is far more tolerable than an open-ended unknown.
**Minimize unnecessary touch.** Talk with the stylist beforehand about keeping extra touches to a minimum. Skip the shampoo if your child can have clean hair before arriving. Avoid blow-drying if the noise and sensation are triggering. Every eliminated step reduces the sensory load.
**Temperature matters.** Ask for lukewarm water instead of cold. Warm a towel before placing it around their neck. Cold sensations are a common trigger that is easy to prevent.
## Building a Positive Haircut Routine
Consistency and positive associations transform haircuts over time.
**Use the same stylist every time.** Familiarity with the person reduces anxiety significantly. Call ahead to explain your child's needs and find a stylist who is patient and willing to adapt. Many salons now have stylists trained in sensory-friendly techniques.
**Create a reward system.** A clear, visual reward that your child earns after the haircut provides motivation. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s reward system lets you set up a specific goal connected to the haircut experience, and your child can see their progress building toward something they value.
**Keep a consistent pre-haircut routine.** The same breakfast, the same drive, the same visual story reviewed beforehand, the same comfort items packed. Predictability in the steps leading up to the haircut builds a framework of safety around the experience.
**Celebrate every step.** Even if you only accomplish sitting in the chair for thirty seconds on the first visit, that is progress worth acknowledging. Build gradually: sit in the chair, then sit with the cape, then tolerate one snip, then five snips. Each successful exposure rewires the anxiety response.
## When to Consider Alternatives
Not every child will tolerate a traditional salon haircut, and that is completely okay.
**Home haircuts** offer a controlled environment where you manage every variable. You choose the lighting, the noise level, the timing, and the pace. Many parents learn basic cutting techniques to avoid the salon entirely.
**Mobile stylists** who come to your home combine professional skill with the comfort of a familiar environment. This option is increasingly available and worth exploring.
**Gradual exposure over multiple visits** works better than pushing through a single traumatic appointment. Five calm visits where very little cutting happens build more long-term tolerance than one visit where you hold your child down.
**Occupational therapy support** can help if sensory processing differences are severe. An OT can create a structured desensitization plan specific to haircut-related sensations and work with your child over weeks or months to build tolerance.
## Tracking Progress Over Time
Haircut tolerance rarely improves in a straight line. Tracking your child's experience across appointments reveals patterns that inform your approach.
**Note what works and what does not.** Did the headphones help? Was the morning appointment better than the afternoon one? Did the social story reduce anxiety? [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking feature lets you log how your child feels before, during, and after haircut-related activities, surfacing patterns you might miss otherwise.
**Adjust based on data, not assumptions.** You might discover that your child's haircut anxiety peaks on the drive rather than in the chair, which tells you to focus preparation on the transition. Or you might find that afternoon appointments consistently go better because morning sensory sensitivity is higher.
**Celebrate the trajectory.** If the first haircut involved forty-five minutes of crying and the fifth involved ten minutes of mild discomfort, that is enormous progress. Keep the long view in mind.
Haircuts do not have to be a family crisis. With sensory accommodations, gradual exposure, and the right visual supports, your child can build tolerance and even confidence around this essential life skill.
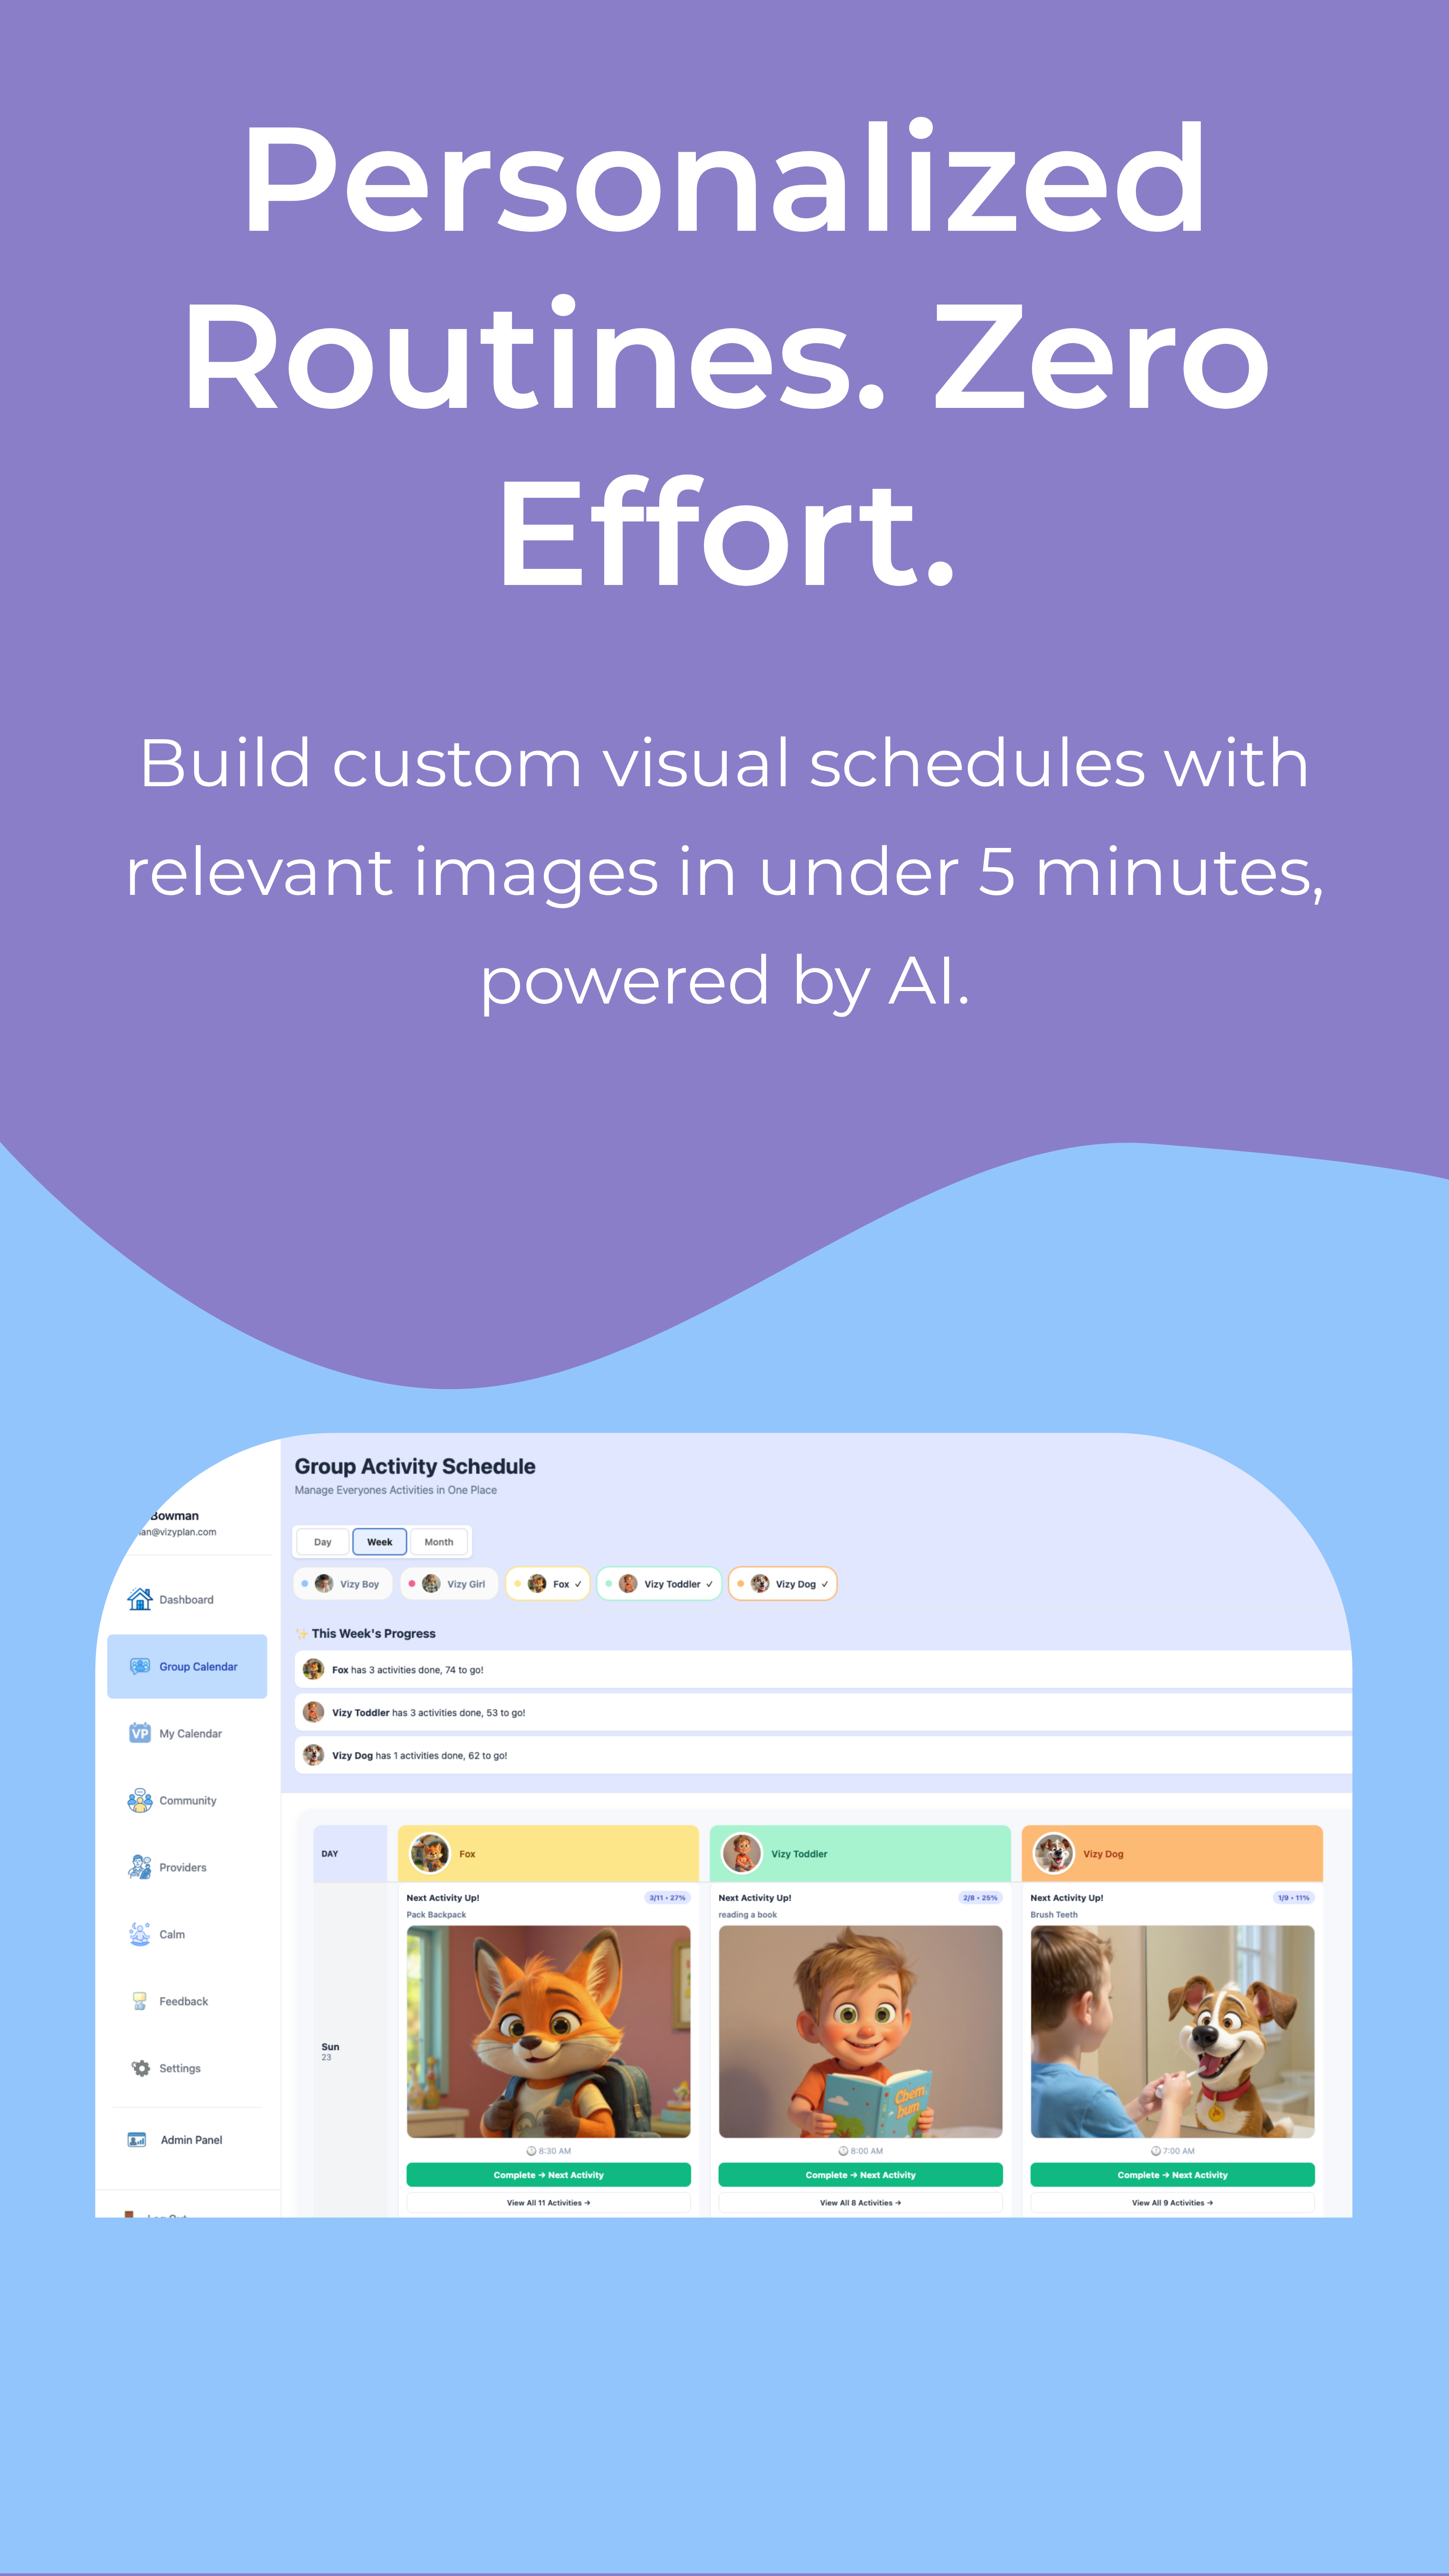
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** Create personalized social stories and visual routines that prepare your child for haircuts and other challenging sensory experiences. Just $6.99/month after your trial, no credit card required upfront.
---
## Getting Dressed: Clothing and Sensory Strategies for Neurodivergent Children
Published: 2026-02-04
URL: https://vizyplan.com/blog/getting-dressed-clothing-sensory-strategies-neurodivergent-children
Category: Daily Routines
Author: Justin Bowman
> Evidence-based strategies for making getting dressed easier for neurodivergent children, including sensory-friendly clothing, visual dressing sequences, and reducing morning decision fatigue.
For many families of neurodivergent children, the morning dressing routine can feel like navigating a minefield. What seems like a simple task, putting on clothes, actually involves a complex interplay of sensory processing, executive function, decision-making, and motor planning. If your child has ever melted down over a "wrong" pair of socks, refused to wear jeans, or taken 45 minutes to get dressed while you watch the clock tick toward school time, you are not alone.
The good news is that with the right strategies, tools, and understanding, getting dressed can become a smoother, more independent part of your child's day. This guide will walk you through evidence-based approaches to transform your morning routine from a daily battle into an opportunity for growth and connection.
## Why Getting Dressed Is So Challenging
Before we dive into solutions, it helps to understand why dressing presents such unique challenges for neurodivergent children. When we recognize the "why" behind the struggle, we can respond with empathy rather than frustration.
**Sensory Sensitivities**
Research shows that tactile sensitivities affect the majority of autistic children, and these sensitivities directly impact clothing tolerance. That tag your child insists feels like "needles" is not an exaggeration to them. Their nervous system is genuinely processing that sensation as painful or intolerable. Common sensory triggers include:
- Tags and labels that feel scratchy or poky
- Seams, especially in socks, that create uneven pressure
- Textures that feel "wrong" (too rough, too slippery, too fuzzy)
- Tightness around waists, wrists, or necks
- Temperature, either too warm or too cool against the skin
- The feel of new, unwashed fabric versus worn-in favorites
**Executive Function Demands**
Getting dressed is actually a multi-step sequence that requires planning, organization, and working memory. Your child needs to remember the order of steps, find each clothing item, manipulate buttons and zippers, and check that everything is on correctly. For children with ADHD, autism, or other conditions affecting executive function, this mental load can be overwhelming, especially first thing in the morning when their brain is still waking up.
**Decision Fatigue**
Opening a closet full of options can be paralyzing for a neurodivergent brain. Each choice, which shirt, which pants, which socks, requires mental energy. By the time your child has made several decisions, they may be depleted before they have even started actually getting dressed. This is why you might notice your child does better when choices are limited.
## Understanding Your Child's Sensory Clothing Profile
Every child's sensory system is unique. Taking time to observe and understand your child's specific profile will help you make informed choices about clothing and strategies.
**Tactile Defensive Children**
These children are over-responsive to touch sensations. They may:
- Pull at clothing constantly
- Refuse anything that is not 100% cotton
- Insist on wearing the same few "safe" items repeatedly
- Have strong reactions to new clothes
- Prefer loose, soft clothing
**Proprioceptive Seekers**
Some children actually crave deep pressure input, which can be regulating for their nervous system. These children may:
- Prefer tight clothing like compression shirts or leggings
- Love heavy fabrics or weighted items
- Feel calmer in snug-fitting clothes
- Seek out hugs and squeezes throughout the day
**Temperature Dysregulation**
Temperature dysregulation is common in autism and can significantly affect clothing comfort. Your child might:
- Feel too hot when others are comfortable
- Not notice they are cold until they are shivering
- Refuse to wear weather-appropriate clothing
- Need layers they can add or remove easily
Understanding which category (or combination) fits your child helps you build a wardrobe that works with their nervous system, not against it.
## Building a Sensory-Friendly Wardrobe
Once you understand your child's sensory profile, you can strategically build a wardrobe that sets them up for success.
**For Tactile Defensive Children:**
- **Tagless clothing:** Many brands now offer tagless options with printed labels instead of sewn-in tags. If tags remain an issue, carefully remove them with a seam ripper rather than scissors (which can leave scratchy remnants).
- **Seamless socks:** These are game-changers for many families. Look for socks specifically marketed as "sensory-friendly" with flat toe seams.
- **Soft, natural fabrics:** Cotton, bamboo, and modal tend to be well-tolerated. Pre-wash all new clothing several times to soften the fabric.
- **Inside-out options:** Sometimes wearing clothes inside-out eliminates seam discomfort. If your child prefers this, let them do it.
- **Elastic waistbands:** Skip buttons and zippers on pants when possible.
**For Proprioceptive Seekers:**
- **Compression clothing:** Undershirts, shorts, or full compression suits provide calming input throughout the day.
- **Fitted base layers:** Snug undershirts or leggings worn under regular clothes can provide the input they crave.
- **Weighted vests:** Some children benefit from weighted clothing, though consult an occupational therapist for proper use.
**General Tips:**
- When you find clothing that works, buy multiples in the same size and the next size up.
- Keep a "sensory-approved" section of the closet with only comfortable options.
- Involve your child in texture testing when shopping. Bring fabric swatches or let them feel items before purchasing.
## Visual Dressing Sequences: A Game-Changer
Visual schedules significantly improve dressing independence for neurodivergent children. Breaking down the dressing routine into clear, visual steps removes the executive function burden of remembering what comes next.
A basic visual dressing sequence might include:
- Underwear (image of underwear)
- Pants or shorts (image of pants)
- Shirt (image of shirt)
- Socks (image of socks)
- Shoes (image of shoes)
**Why Visual Sequences Work:**
- They provide external structure for internal executive function challenges
- Children can reference the sequence independently without asking for help
- Progress becomes visible and motivating
- The same sequence used consistently builds automatic habits over time
**Making It Personal:**
Generic clip art can work, but personalized visuals are even more effective. When children see images of their actual clothes, or even images that look like them, they connect more deeply with the routine. With [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), you can create personalized visual dressing sequences using AI-generated images that reflect your child's real wardrobe and experience.
Download on the App Store
## Reducing Decision Fatigue
Morning is not the time for unlimited choices. Here are strategies to minimize decision fatigue while still giving your child some autonomy:
**Lay Out Clothes the Night Before**
Make clothing selection part of the bedtime routine when your child's brain is not yet dealing with the pressure of getting out the door. This single change can transform mornings.
**Offer Two Choices, Not Ten**
Instead of "What do you want to wear?" try "Do you want the blue shirt or the green shirt?" Two options provide a sense of control without overwhelming decision-making.
**Create a Capsule Wardrobe**
Limit the active wardrobe to 7-10 complete outfits that all mix and match. Store out-of-season and backup clothes elsewhere. When everything in the drawer is an acceptable option, choosing becomes easier.
**Use Visual Choice Boards**
Take photos of approved outfit combinations and let your child pick from the board. This visual menu simplifies decision-making while ensuring all options are sensory-appropriate and weather-suitable.
**Designate "Uniforms" for Certain Days**
Some families assign specific outfits to certain days of the week. Monday is always the dinosaur shirt, Tuesday is stripes, and so on. Predictability reduces both decisions and arguments.
## Handling Seasonal Clothing Transitions
Changes in season mean changes in clothing, which can be particularly challenging for neurodivergent children who thrive on sameness and may need time to adjust to new textures.
**Introduce New Textures Gradually**
Do not wait until the first cold day to pull out winter clothes. Weeks before the season changes:
- Let your child touch and explore new seasonal clothing
- Have them try items on briefly, without pressure to wear them out
- Wash new items multiple times to soften them
- Pair new items with familiar favorites (new pants with beloved shirt)
**Use Social Stories About Weather-Appropriate Clothing**
Social stories can help children understand why we change our clothing with the seasons. A story might explain how our bodies feel cold when the temperature drops and how jackets help keep us comfortable and healthy. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social story feature lets you create these narratives with personalized visuals that make the concept concrete and relatable.
**Create Visual Weather Charts**
Post a simple chart showing:
- Sunny and hot = shorts and t-shirt
- Cloudy and cool = long pants and long sleeves
- Rainy = jacket and rain boots
- Cold = warm layers
Check the weather together each morning and reference the chart to make clothing selection feel logical rather than arbitrary.
.png)
## The "Wrong Socks" Meltdown and Other Common Battles
You have probably been there. Everything is going smoothly until suddenly, it is not. The socks are wrong. The shirt is itchy. The pants feel weird. What do you do?
**First, Validate**
Your child's distress is real. Even if you cannot see or feel what they are experiencing, their nervous system is sending genuine alarm signals. Saying "I can see those socks really bother you" goes further than "They are fine, just put them on."
**Investigate the Specific Trigger**
Is it the seam? The tightness? The texture? The way they are positioned on the foot? Understanding the precise issue helps you solve it and prevent future occurrences.
**Have Backups Ready**
Keep a stash of known-comfortable socks, underwear, and basic clothing items. When something feels "wrong," having an immediate alternative prevents escalation.
**Consider What Else Might Be Going On**
Sometimes sensory sensitivities increase when children are tired, hungry, stressed, or getting sick. A sock that was fine yesterday might be intolerable today because of these underlying factors. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking feature can help you identify patterns over time, noticing when clothing battles correlate with other stressors.
**Track Patterns**
Notice which items cause repeated problems and which are always accepted. Over time, you will build a reliable wardrobe and be able to identify what specific sensory features your child can and cannot tolerate.
## Using Reward Systems to Build Dressing Independence
Positive reinforcement can be a powerful motivator for building new habits. The key is making rewards meaningful to your child and connected to their effort and progress.
**Effective Reward Strategies:**
- **Immediate feedback:** A sticker on a chart right after getting dressed successfully
- **Celebration of small steps:** Reward putting on socks independently, even if other steps still need help
- **Choice of rewards:** Let your child help determine what they are working toward
- **Visual progress tracking:** Charts, token boards, or digital trackers make progress concrete
**What to Reward:**
- Completing steps independently
- Trying a new clothing item
- Getting dressed within a target time
- Following the visual sequence without reminders
- Handling a sensory discomfort calmly
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s built-in reward system makes tracking and celebrating progress simple. Set up personalized goals and let your child see their achievements accumulate, building both the dressing habit and their confidence.
**Important Notes:**
- Focus on effort and progress, not perfection
- Adjust expectations based on your child's developmental level
- Phase out rewards gradually as habits become automatic
- Never take away earned rewards as punishment
## Building Independence Over Time
Dressing independence develops gradually. Meeting your child where they are while gently encouraging growth creates lasting skills.
**Age-Appropriate Expectations:**
- **Ages 2-3:** Can help push arms through sleeves, pull up pants with help
- **Ages 3-4:** Can put on shirts with some help, pull up pants independently
- **Ages 4-5:** Can dress mostly independently with simple clothing, may need help with fasteners
- **Ages 5-6:** Can dress independently, including most fasteners
- **Ages 6 and up:** Can select weather-appropriate clothing and complete entire routine
**Remember:** These are general guidelines. Neurodivergent children may develop skills on different timelines, and that is okay.
**Building Skills Gradually:**
- Start by having your child complete the last step of each task (you pull up pants most of the way, they finish)
- Gradually have them complete more of each step
- Add new steps as current ones become automatic
- Use visual checklists to support independence
- Celebrate each new skill mastered
## How VizyPlan Supports Dressing Routines
Transforming the dressing routine takes consistency, the right tools, and a lot of patience. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was designed specifically to support neurodivergent children and their families through challenges exactly like this one.
With [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), you can:
- **Create personalized visual dressing sequences** with as many or as few steps as your child needs
- **Use AI-generated images** that look like your child, making the routine relatable and motivating
- **Track emotions** before, during, and after the dressing routine to spot patterns and identify what helps
- **Set up reward systems** to celebrate progress and build independence
- **Create social stories** about weather-appropriate clothing, trying new textures, or handling sensory discomfort
Morning routines set the tone for the entire day. When getting dressed goes smoothly, everyone starts the day calmer and more connected.
**[Download VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start your 7-day free trial today.** For just $6.99/month after your trial (no credit card required upfront), you will have everything you need to transform dressing time from a daily struggle into an opportunity for independence and connection.
Your child can do this. And with the right support, mornings can become something your whole family looks forward to.
---
## Bath Time and Personal Hygiene Routines for Neurodivergent Children
Published: 2026-02-03
URL: https://vizyplan.com/blog/bath-time-hygiene-routines-neurodivergent-children
Category: Daily Routines
Author: Justin Bowman
> Evidence-based strategies for making bath time, hair washing, toothbrushing, and grooming easier for neurodivergent children through sensory accommodations and visual supports.
If bath time in your home involves tears, negotiations, or full-on meltdowns, you are not alone. For many families raising neurodivergent children, personal hygiene routines rank among the most stressful parts of the day. What seems like a simple task to most people, lathering up some soap, rinsing off, brushing teeth, can feel genuinely overwhelming for a child whose nervous system processes sensory input differently.
The good news? With the right strategies, tools, and a whole lot of patience, hygiene routines can become manageable and even enjoyable. This guide is written parent-to-parent, drawing from evidence-based approaches and real-world experience to help you build bath time and hygiene routines that work for your unique child.
## Why Hygiene Routines Are Uniquely Challenging
Before we dive into solutions, it helps to understand why these routines are so hard in the first place. For neurodivergent children, particularly those with autism, ADHD, or sensory processing differences, hygiene tasks involve a perfect storm of challenges.
**Sensory overload is everywhere.** The bathroom is one of the most sensory-intense rooms in the house. Water temperature shifts, the sound of running faucets, the echo of tiles, slippery surfaces, bright overhead lights, and strong-smelling soaps all compete for your child's attention and can easily tip them into overwhelm.
**Vulnerability and loss of control.** Being undressed is an inherently vulnerable state. Many children feel a deep sense of unease when they lose the comforting pressure of their clothing. Add to that the unpredictability of water splashing on their face or someone else controlling the washcloth, and it is easy to see why bath time triggers a fight-or-flight response.
**Tactile defensiveness plays a major role.** Research suggests that tactile defensiveness affects up to 60% of autistic children, directly impacting their tolerance for hygiene-related sensations. The feeling of shampoo in hair, a toothbrush on gums, or a towel rubbing against skin can register as genuinely painful rather than merely uncomfortable.
**Executive function demands.** Hygiene routines involve multiple sequential steps, and for children with ADHD or executive function challenges, holding that sequence in mind while also managing sensory input is incredibly taxing.
Understanding these root causes is the first step toward compassion-driven problem solving. Your child is not being "difficult." Their nervous system is working overtime.
## Understanding the Sensory Landscape of the Bathroom
To build better routines, it helps to think like an occupational therapist and map out the sensory landscape your child is navigating.
**Tactile input** includes the feel of water (its pressure, temperature, and movement), soap and shampoo textures, washcloth or sponge roughness, towel fabric, and the sensation of wet skin meeting cool air. Each of these can be a trigger point.
**Proprioceptive input** refers to your child's awareness of their body in space. Bathrooms often have slippery surfaces, making children feel physically unstable. This lack of grounding can increase anxiety. On the flip side, proprioceptive input like deep pressure or heavy work before bath time can actually help regulate the nervous system.
**Interoception**, the sense of internal body signals, also plays a role. Some children struggle to gauge water temperature accurately or may not recognize when they are clean. This can lead to resistance ("I don't need a bath!") or difficulty knowing when a task is complete.
**Auditory input** in the bathroom is amplified by hard surfaces. Running water, the whir of an electric toothbrush, or even the echo of a parent's voice can be overwhelming in a small, tiled space.
**A practical starting point:** Before changing anything about your routine, spend a few days observing. Which specific moments cause the most distress? Is it the sound of the water filling the tub? The feeling of shampoo? The transition from dressed to undressed? Pinpointing the exact triggers will help you target your strategies effectively.
## Breaking Hygiene Into Manageable Visual Steps
One of the most evidence-based strategies for supporting neurodivergent children through hygiene routines is using visual schedules. Research consistently shows that visual schedules reduce anxiety by making sequences predictable. When a child can see exactly what is coming next, the uncertainty that fuels resistance melts away.
Rather than treating "bath time" as one large event, break it into smaller, distinct sequences.
**A bath time visual schedule might look like this:**
- Get towel and pajamas ready
- Undress and put clothes in hamper
- Get into the tub (or shower)
- Wet body
- Soap up with washcloth
- Rinse off
- Wash face
- Hair washing (if tonight is a hair wash night)
- Rinse hair
- Drain water and stand up
- Dry off with towel
- Put on pajamas
**A toothbrushing visual schedule:**
- Pick up toothbrush
- Put toothpaste on brush
- Brush top teeth
- Brush bottom teeth
- Brush tongue (if tolerated)
- Spit and rinse
- Put toothbrush away
The key is that each step is simple, concrete, and paired with a visual image your child can reference. With [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), you can create personalized visual schedules using AI-generated images that actually look like your child and your bathroom. This level of personalization makes the schedule feel familiar and relevant, which significantly increases buy-in from kids who might ignore generic clipart-style visuals.
**Pro tip:** Separate hair washing from the regular bath routine. Many children do much better when they know "tonight is NOT a hair wash night." Having a predictable schedule (for example, hair washing on Tuesdays and Saturdays) gives children a sense of control and reduces the nightly anxiety of wondering if tonight will involve the dreaded hair wash.
## Hair Washing Strategies: Tackling the Most Dreaded Task
Let's be honest. Hair washing is often the single biggest hygiene battle for sensory-sensitive children. Water running over the face and head can trigger an intense fight-or-flight response, and the sensation of fingers scrubbing the scalp can feel deeply uncomfortable.
Here are strategies that occupational therapists recommend:
**Start with dry runs.** Before introducing water, practice the motions. Let your child feel your fingers gently massaging their dry scalp. Use a dry washcloth on their forehead. Practice tilting their head back. This gradual desensitization builds tolerance over time.
**Rinse cups versus shower heads.** Many children do better with a rinse cup because it provides more predictable, controlled water flow. Others prefer a handheld shower head because the steady stream feels less shocking than poured water. Let your child experiment to find their preference.
**Visor shields are a game changer.** A simple shampoo visor (a soft silicone ring that sits on the forehead) keeps water from running into the eyes and face. For many children, this single tool transforms hair washing from unbearable to tolerable.
**Give your child the washcloth.** Allowing your child to hold a dry washcloth over their eyes during rinsing gives them a sense of control and protects the most sensitive area.
**Consider alternatives.** Dry shampoo, no-rinse cleansing caps, or even just rinsing without shampoo on some nights can reduce the frequency of full hair washes while keeping hair reasonably clean.
**Use gradual desensitization.** Start with just wetting the hair. Next time, add a tiny bit of shampoo. Build up slowly over weeks or even months. Progress is progress, no matter how small.
**Social stories can help prepare your child emotionally.** A social story about hair washing, walking through why we do it, what it will feel like, and what comes after, reduces the fear of the unknown. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social stories feature lets you create these narratives with personalized visuals, making them far more relatable for your child.
Download on the App Store
## Toothbrushing Solutions That Actually Work
Toothbrushing presents its own unique sensory challenges. The taste of toothpaste, the texture of bristles, the pressure on gums, and the sensation of foaming inside the mouth can all be problematic.
**Experiment with toothbrush types.** Electric toothbrushes provide proprioceptive input (vibration and deep pressure) that some children actually find regulating and calming. However, other children find the vibration overwhelming. There is no universal answer here. Try both manual and electric, and let your child's response guide you.
**Offer flavor choices.** Many children are sensitive to the strong mint flavor of standard toothpaste. Unflavored toothpaste, mild fruit flavors, or even brushing with just water initially can make the experience more tolerable. The goal is to build the habit first and optimize the toothpaste later.
**Use a visual timer.** A two-minute sand timer or a timer app gives toothbrushing a clear endpoint. Knowing exactly when it will be over helps children tolerate discomfort. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual schedules can include built-in timing cues so your child always knows how long each step will take.
**Let your child lead.** Whenever possible, let your child brush their own teeth first. Even if their technique is not perfect, the sense of control reduces resistance. You can do a quick "parent check" brushing afterward if needed, but framing it as teamwork rather than something being done to them makes a real difference.
**Positioning matters.** Some children do better standing, others sitting. Some prefer to look in the mirror while brushing, while others find it distracting. A few even prefer lying down with their head in a parent's lap, which provides the added comfort of deep pressure and physical closeness.
## Nail Clipping and Grooming: Small Tasks, Big Reactions
Nail clipping is a task that many parents dread almost as much as their children do. The sharp, sudden sensation of clippers and the sound of the clip can be genuinely distressing.
**Timing is everything.** Clip nails right after bath time when they are soft and pliable. This makes the process quicker and less physically intense.
**Try filing instead.** For children who cannot tolerate clippers at all, a nail file (or even an electric nail file designed for children) is a gentle alternative. It takes longer, but it eliminates the sharp sensation entirely.
**Deep pressure before grooming.** Occupational therapists often recommend providing proprioceptive input before grooming tasks. Firm squeezes to the hands, hand massages, or letting your child squeeze a stress ball can help regulate their nervous system before you begin.
**Distraction can be your friend.** Allow your child to watch a favorite show, listen to a story, or engage with a preferred toy during nail clipping. Pairing a non-preferred task with a preferred activity reduces overall distress.
**One nail at a time is okay.** If your child can only tolerate one or two nails per sitting, that is absolutely fine. It might take a few days to get through all ten fingers, and that is a perfectly valid approach.
.png)
## Building a Sensory-Friendly Bathroom
Small environmental changes to your bathroom can make a surprisingly big difference in your child's comfort and cooperation.
**Lighting.** Harsh overhead fluorescent lights are a common trigger. Consider a dimmer switch, warm-toned LED bulbs, or even battery-powered LED candles to create a softer atmosphere. Some children do well with color-changing lights that let them pick the hue.
**Temperature.** Warm up the bathroom before your child enters. A small space heater running for five minutes before bath time can eliminate the shock of cold tile and cold air. Have a warm towel ready (straight from the dryer is a wonderful sensory experience for many kids).
**Non-slip surfaces.** Feeling physically unstable on wet, slippery surfaces increases anxiety. Non-slip mats inside the tub and on the bathroom floor provide physical security and proprioceptive grounding.
**Sound.** Playing your child's favorite music, an audiobook, or a familiar podcast can mask the echoing sounds of the bathroom and create a more pleasant atmosphere. Some children prefer complete silence, so follow your child's lead.
**Predictable environment.** Keep bath supplies in the same place every time. Use the same towel, the same cup, the same order. Predictability is profoundly calming for neurodivergent children. A visual checklist posted on the bathroom wall (at your child's eye level) reinforces this consistency.
**Preferred items.** Let your child choose their own towel color, soap scent, or bath toys. These small choices build ownership of the routine and increase willingness to participate.
## Using Reward Systems to Build Hygiene Habits
Positive reinforcement is one of the most effective tools for building new habits, and hygiene routines are a perfect place to use it.
**Celebrate small wins.** Did your child let you pour one cup of water over their hair without crying? That is worth celebrating. Did they brush for thirty seconds instead of refusing entirely? Progress. Acknowledging small steps forward keeps motivation alive.
**Visual progress tracking.** Children respond powerfully to seeing their progress. A sticker chart, a marble jar, or a digital tracker where they can watch their achievements accumulate creates tangible motivation.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s built-in reward system makes this seamless. As your child completes each step of their hygiene routine, they earn rewards that are tracked visually within the app. Combined with emotion tracking, you can also see patterns over time. Maybe your child's mood is consistently better on nights when bath time includes their favorite music, or maybe shorter showers lead to less distress than longer baths. These insights help you continuously refine the routine.
**Keep rewards proportional and immediate.** For younger children, a small reward right after the routine (a favorite story, five minutes of screen time, a special sticker) is more effective than a distant reward promised for the end of the week.
**Fade rewards gradually.** The goal is for the routine itself to become familiar and tolerable. Over time, as your child builds comfort, you can gradually reduce external rewards as the routine becomes simply "what we do."
## Building Independence Over Time
The ultimate goal of any hygiene routine is for your child to eventually manage it independently, or as independently as their abilities allow.
**Set age-appropriate expectations.** A four-year-old might simply stand in the tub while you do everything. A seven-year-old might soap up their own body while you handle hair washing. A twelve-year-old might manage the entire shower independently with a visual checklist on the wall. Meet your child where they are.
**Visual checklists for self-care.** As children grow, transition from parent-led visual schedules to self-directed checklists. A laminated card hanging in the shower that your child can check off with a dry-erase marker builds executive function skills alongside hygiene independence.
With [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), you can evolve your child's visual schedules as they grow. Start with highly detailed, step-by-step routines with AI-generated images for younger children. As your child matures, simplify the schedules to serve as quick-reference checklists that support independence rather than directing every action. The flexibility to customize and update routines means the tool grows with your child.
**Practice during calm times.** Teach new hygiene skills when everyone is relaxed, not in the heat of a difficult bath time. Role-playing with dolls, watching video models, or reading social stories about hygiene during the day can prepare your child for nighttime success.
**Expect regression.** Illness, schedule changes, growth spurts, and transitions (like starting a new school year) can all cause regression in hygiene tolerance. This is normal. When it happens, temporarily scale back expectations, increase support, and slowly rebuild.
## How VizyPlan Supports Your Family's Hygiene Routines
Building consistent, calm hygiene routines for a neurodivergent child is one of the most challenging aspects of daily parenting. It requires patience, creativity, and the right tools.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was designed with exactly these challenges in mind. Here is how it can help:
- **Personalized visual schedules** let you break down bath time, toothbrushing, hair washing, and grooming into clear, predictable steps with AI-generated images tailored to your child.
- **Social stories** help prepare your child emotionally for challenging hygiene tasks, reducing fear and resistance before the routine even begins.
- **Emotion tracking** helps you identify patterns, discovering which strategies improve your child's experience and which need adjusting.
- **Reward systems** celebrate every small win and keep your child motivated as they build new habits.
- **Flexible, evolving routines** grow with your child, supporting detailed guidance for younger kids and promoting independence for older ones.
You know your child best. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) simply gives you the tools to turn that knowledge into structured, visual support that meets your child where they are.
**Start your [7-day free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) today. Just $6.99/month after that, no credit card required upfront.** Because every child deserves a hygiene routine that feels safe, predictable, and maybe even a little bit fun.
---
## Grocery Store Strategies: Running Errands with Your Neurodivergent Child
Published: 2026-02-02
URL: https://vizyplan.com/blog/grocery-store-strategies-errands-neurodivergent-child
Category: Daily Routines
Author: Justin Bowman
> Practical strategies for making grocery store trips and errands manageable for neurodivergent children, including sensory toolkits, visual shopping lists, and gradual exposure techniques.
If the thought of taking your neurodivergent child to the grocery store makes your stomach drop, you are not alone. For many families, what should be a simple errand can feel like navigating a minefield of sensory triggers, unexpected changes, and mounting anxiety. The bright lights, crowded aisles, unpredictable noises, and endless visual stimulation can turn a quick shopping trip into a full-blown crisis for a child with autism, ADHD, or sensory processing differences.
But here is the good news: with the right preparation, tools, and strategies, grocery store trips can become manageable and even enjoyable. Some families have transformed errands from their most dreaded activity into a genuine learning opportunity. It takes patience, planning, and a willingness to do things a little differently, but it is absolutely possible.
This guide will walk you through evidence-based strategies for every phase of the errand, from preparation at home to celebrating success afterward. Whether your child is new to grocery store visits or you are looking for ways to make existing trips smoother, these approaches can help your whole family feel more confident.
## Why Grocery Stores Are So Overwhelming
Before diving into strategies, it helps to understand exactly why retail environments are so challenging for neurodivergent children. When we see it through their eyes, the grocery store is genuinely intense.
**Fluorescent lighting** flickers at a frequency that many neurotypical people do not consciously notice, but for children with sensory sensitivities, it can feel like a strobe light. This alone can trigger headaches, visual discomfort, and irritability within minutes of entering a store.
**Auditory overload** comes from every direction. Scanners beeping, carts rattling, intercoms blaring, other shoppers talking, music playing overhead, freezer units humming. For a child who struggles to filter background noise, all of these sounds compete for attention at equal volume. Research on sensory processing in autism confirms that difficulty with auditory filtering is one of the most commonly reported challenges in public spaces.
**Crowds and unpredictability** remove a child's sense of control. People appear around corners, block aisles unexpectedly, and move in patterns that are hard to anticipate. For children who rely on predictability and routine, this can feel genuinely threatening.
**Temperature shifts** between sections (the freezer aisle versus the bakery, for example) add another layer of sensory input that the child's nervous system must process. **Visual clutter** from thousands of colorful packages, promotional signs, and display stands creates a constant stream of stimulation that can be impossible to tune out.
Understanding these triggers is not about avoiding stores forever. It is about recognizing that your child's distress is a real, physiological response to an environment that was not designed with their needs in mind. That awareness is the foundation for every strategy that follows.
## Preparing Before You Leave the House
The single most effective thing you can do to improve an errand outing happens before you ever start the car. Preparation is where you set the stage for success.
**Create a visual schedule for the errand.** A step-by-step visual sequence of what will happen removes the anxiety of the unknown. Your schedule might look something like this:
- Put on shoes and get in the car
- Drive to the grocery store
- Walk inside and get a cart
- Follow our shopping list together
- Pay at the checkout
- Walk back to the car and drive home
When children can see exactly what is coming next, their nervous system can relax. There are no surprises to brace for. Tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) make this incredibly simple by allowing you to build custom visual routines with **AI-generated personalized images** that actually look like your child's real life. Instead of generic clip art, your child sees images that reflect their world, which makes the schedule far more meaningful and engaging.
**Use a social story about the grocery store.** Social stories are short, descriptive narratives that explain a social situation in terms a child can understand. A grocery store social story might cover what the store looks like, what sounds they might hear, what they will do while there, and what happens if they feel overwhelmed. Reading through this story once or twice before leaving helps prime your child's expectations.
**Set clear, simple expectations.** Keep it to two or three rules at most. "We will stay together, we will use our shopping list, and we will use calm voices." Fewer rules are easier to remember and follow. Review them before you leave and again in the parking lot.
**Let your child help plan.** If your child is old enough, involve them in making the shopping list. Ask them to pick one or two items they would like to find at the store. This gives them something to look forward to and a sense of ownership over the trip. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s **visual schedules** can incorporate a personalized shopping checklist right into the routine, so everything your child needs to know is in one familiar place.
## Building a Sensory Toolkit
Think of your sensory toolkit as your errand survival kit. These are items that help regulate your child's sensory system while you shop. Not every child needs every item, so tailor this to what works for your family.
- **Noise-canceling headphones or ear defenders** to reduce auditory input. These can be the single most transformative tool for store visits.
- **Sunglasses or a hat with a brim** to reduce the impact of fluorescent lighting and visual clutter.
- **A comfort item** such as a small stuffed animal, a favorite blanket corner, or a specific toy that provides emotional grounding.
- **Fidget tools** like a stress ball, textured keychain, or fidget cube to give their hands something to do and channel nervous energy.
- **A chewy necklace or snack** for children who seek oral sensory input when stressed.
Pack these items in a dedicated bag that your child associates with outings. Over time, just having the bag nearby can become a source of comfort because it signals that their needs will be met.
## Creating a Visual Shopping List Your Child Can Follow
One of the most powerful strategies for errand success is giving your child an active role. Children who have a job to do are far less likely to become overwhelmed because their attention is channeled toward a purpose.
**Make a visual shopping list** with pictures of the items you need. For younger children or those who do not yet read, photos or simple drawings work beautifully. For older children, a written list with small images beside each item can work well.
Here is how to make it interactive:
- **Let your child hold the list.** This simple act of responsibility can shift their mindset from passive passenger to active participant.
- **Have them check off or cross out items** as you find them. The physical act of marking progress is satisfying and gives them a concrete sense of accomplishment.
- **Assign them a finding role.** "Can you spot the bananas? They are yellow and hanging up. Let me know when you see them!" This turns shopping into a scavenger hunt.
- **Start with a short list.** Five to seven items is plenty for early trips. You can always build up to larger shopping runs as confidence grows.
With [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), you can build a **visual checklist** right into your errand routine, complete with personalized images of the actual items you are shopping for. Your child can follow along on the screen, checking off items as they go. This combination of visual structure and active participation is backed by research showing that giving children a defined role during challenging activities significantly reduces anxiety and improves cooperation.
Download on the App Store
## Timing and Planning: Setting Yourself Up for Success
When you go matters just as much as how you prepare. Strategic timing can dramatically reduce the sensory load your child faces.
**Shop during quiet hours.** Many major retailers now offer designated sensory-friendly shopping times with dimmed lights, reduced music, and fewer announcements. Even without formal programs, early mornings (right when the store opens), late evenings, and mid-week days tend to be significantly calmer than weekends or after-school hours. A quick call to your local store can help you identify their quietest windows.
**Start with shorter trips.** Your first few practice runs should not be full weekly grocery hauls. Pick up three to five items and leave. The goal is to build a track record of successful visits, not to test your child's endurance. Each positive experience deposits into their confidence bank.
**Use gradual exposure.** If the grocery store is currently a no-go zone, start even smaller. Drive to the parking lot and sit in the car for a few minutes. Next time, walk to the entrance. Then go inside for just one item. This desensitization approach is well-supported by research and allows your child's nervous system to slowly adjust to the environment without being flooded.
**Have an exit plan.** Know that it is always okay to leave. Telling your child (and reminding yourself) that "we can leave whenever we need to" reduces pressure for everyone. Paradoxically, knowing they can leave often helps children feel safe enough to stay longer.
**Pick a familiar store.** Consistency helps. Using the same store means your child learns the layout over time. They will begin to predict what comes next and where things are, which builds the sense of control that neurodivergent children need to feel safe.
.png)
## During the Trip: Real-Time Strategies
Even with excellent preparation, you need in-the-moment strategies for navigating the store itself.
**Build in sensory breaks.** Plan one or two brief pauses during your trip. Step outside for a breath of fresh air, find a quiet corner near the back of the store, or sit on a bench near the entrance for a minute. These micro-breaks give your child's sensory system a chance to reset before overload builds to a tipping point.
**Use reward milestones.** Break the trip into smaller chunks and celebrate each one. "After we find the milk, bread, and eggs, you can pick a sticker from our reward bag." Small, immediate rewards keep motivation high and make the trip feel less endless. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s built-in **reward system** makes this seamless. You can set up milestone rewards within your errand routine so your child sees exactly what they are working toward and gets instant positive reinforcement when they reach each checkpoint.
**Watch for early signs of overwhelm.** Every child signals distress differently. Common early warning signs include covering ears, increased stimming, a glassy or distant look in the eyes, clinging, whining that escalates in pitch, or suddenly going very still and quiet. Learning your child's specific signals allows you to intervene with a sensory break or a coping strategy before a full meltdown develops.
**Use the visual schedule as an anchor.** When your child feels uncertain or anxious, pull up the visual routine and show them where they are and what comes next. "Look, we have already done these three steps. We only have two more, and then we are heading to the car." This visual proof of progress is incredibly reassuring.
**Narrate what is happening.** Simple, calm commentary helps your child process the environment. "It is a little loud near the registers right now. We will move to a quieter aisle." Acknowledging their experience validates their feelings and models how to label sensory input.
## After the Errand: Celebrating and Processing
What happens after the errand matters just as much as the trip itself. This is where you solidify positive associations and build toward future success.
**Do an emotion check-in.** Once you are back in the car or at home, take a moment to talk about how the trip felt. "How was that for you? Was anything really hard? What part did you like best?" For children who struggle with verbal expression, [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s **emotion tracking** feature provides visual options for identifying and communicating feelings. Your child can select images that match how they feel, giving you valuable insight into their experience even if they cannot find the words.
**Celebrate the accomplishment.** Every completed errand is a genuine achievement. Acknowledge it warmly and specifically. "You followed our whole shopping list today. I am really proud of how you handled the loud noises near the deli." Specific praise reinforces exactly which behaviors and coping skills you want to see again.
**Deliver on promised rewards.** If you set up a reward for completing the trip, follow through immediately. Consistency between what you promise and what you deliver builds the trust that makes future trips possible. Whether it is screen time, a favorite snack, a trip to the park, or earning points in [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s **reward system**, the key is reliability.
**Note what worked and what did not.** Take a mental note (or a quick note in your phone) of what went well and what was challenging. Did the headphones help? Was the store too crowded at that time? Did the visual list keep them engaged? This information helps you refine your approach for next time.
## Building Errand Tolerance Over Time
Errand tolerance is not built in a single trip. It is a gradual process that unfolds over weeks and months. Here is how to think about the longer arc.
**Increase complexity slowly.** Start with one short errand to a familiar store. Once that feels comfortable, try two quick stops in one outing. Eventually, you can work up to longer trips or less familiar locations. Let your child's comfort level guide the pace.
**Vary the environments gradually.** Once the grocery store feels manageable, try the pharmacy, the post office, or a hardware store. Each new environment will require some of the same preparation (visual schedules, social stories, sensory toolkit), but your child will begin to generalize their coping skills across settings.
**Track progress visually.** Children are often motivated by seeing how far they have come. A simple chart showing completed errands, or a digital tracker within [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), gives them a visual record of their growing confidence. Celebrate milestones like "our fifth grocery trip" or "our first time going to a new store."
**Expect setbacks and plan for them.** A rough trip does not erase all the progress you have made. Sensory tolerance fluctuates based on sleep, hunger, stress, illness, and countless other factors. If a trip goes poorly, be compassionate with your child and with yourself. Revisit your preparation steps, adjust your timing, and try again when everyone is ready.
**Involve your child in reflection.** As your child matures, they can take an increasingly active role in planning their own supports. "Last time the store was really bright. Would you like to bring your sunglasses this time?" This builds self-advocacy skills that will serve them well beyond childhood.
## How VizyPlan Supports Your Errand Routines
Running errands with a neurodivergent child asks a lot of parents. You are simultaneously shopping, monitoring sensory input, managing expectations, providing emotional support, and trying to remember whether you need milk. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built to take some of that weight off your shoulders.
With [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), you can create **personalized visual routines** for any errand, complete with AI-generated images that reflect your child's real world. Build a step-by-step grocery store routine, include a visual shopping checklist, set up reward milestones, and use emotion check-ins before and after the trip. Everything your child needs to feel prepared and confident lives in one place.
The app's **social story** capabilities let you walk your child through what to expect at the store before you ever leave home. **Emotion tracking** helps you understand how your child experiences these outings over time, revealing patterns that can guide your planning. And the built-in **reward system** makes positive reinforcement consistent and motivating.
Every family's errand experience looks different, and [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) adapts to yours. Start building your first errand routine today with a **7-day free trial**, no credit card required upfront. Plans are just **$6.99/month** after that.
[Download VizyPlan on the App Store](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and turn your next grocery run into a success story.
You and your child deserve errands that feel possible. With the right tools and a little preparation, they absolutely are.
---
## Teaching Self-Advocacy Skills to Your Neurodivergent Child
Published: 2026-02-01
URL: https://vizyplan.com/blog/teaching-self-advocacy-skills-neurodivergent-child
Category: Strategies
Author: Justin Bowman
> How to build self-advocacy skills in neurodivergent children through self-understanding, communication scripts, emotion literacy, and daily practice with visual supports.
Your child sat through an entire class with a headache and never told the teacher. They ate a food at a friend's house that made them gag rather than say "no thank you." They endured a scratchy shirt all day because they did not know how to ask for a different one. They are suffering in silence, not because they do not have needs, but because they do not yet have the skills to voice them.
Self-advocacy, the ability to understand who you are and communicate what you need, does not come naturally for most neurodivergent children. It has to be taught, practiced, and reinforced. And the stakes could not be higher: children who learn to speak up for themselves become adults who can navigate workplaces, relationships, and healthcare systems on their own terms.
## Why Self-Advocacy Matters for Neurodivergent Children
Research consistently shows that self-advocacy is one of the strongest predictors of positive outcomes for neurodivergent adults. People who can identify their needs and communicate them effectively are more likely to succeed in education, employment, and relationships.
But the benefits start long before adulthood.
**Building confidence from the inside out.** When a child successfully asks for what they need and gets a positive response, it reinforces a powerful message: "My voice matters." Over time, these small moments of agency build genuine self-confidence that no amount of external praise can replicate.
**Reducing frustration and meltdowns.** Many challenging behaviors stem from unmet needs that a child cannot articulate. A child who melts down at the grocery store may be overwhelmed by fluorescent lighting but lack the words or tools to say, "This is too bright for me." Teaching self-advocacy gives children a constructive path to express what they are experiencing before they reach a breaking point.
**Creating long-term independence.** The child who learns to say "I need a break" at age five becomes the teenager who can explain their accommodations to a teacher, and eventually the adult who can advocate for themselves in the workplace. Each stage builds on the last.
The disability rights movement gave us the phrase "Nothing about us without us." Teaching self-advocacy to our children honors that principle from the very beginning. We are not just helping them fit into the world. We are helping them shape it.
## What Self-Advocacy Looks Like at Different Ages
Self-advocacy is not a single skill. It is a developmental progression that looks different at every stage.
**Toddlers and preschoolers (ages 2 to 4):** At this stage, self-advocacy might look like a child pointing to a picture card to indicate they want a break, pushing away a food they do not like, or choosing between two activities. The goal is not eloquent communication. It is building the understanding that they have preferences and those preferences are valid.
**Early elementary (ages 5 to 7):** Children can begin using simple scripts like "I need help" or "Can I have a turn?" They can start identifying basic emotions ("I feel frustrated") and connecting those feelings to situations. They may begin to understand that their brain works differently from some of their peers, and that this is okay.
**Upper elementary (ages 8 to 10):** This is when self-advocacy becomes more nuanced. Children can learn to explain their needs to teachers ("I focus better when I can stand at my desk"), participate in parts of their IEP meetings, and begin to understand their specific strengths and challenges. They can practice more complex communication scripts for peer interactions.
**Tweens and beyond (ages 11+):** Older children can take increasing ownership of their accommodations, learn to politely but firmly set boundaries, and begin to develop a positive neurodivergent identity. They can practice self-advocacy in community settings like extracurricular activities and eventually in job or volunteer contexts.
No matter where your child falls on this spectrum, the key is to meet them where they are and build from there.
## Building Self-Understanding First
Here is something that often gets overlooked: self-advocacy requires self-understanding. A child cannot ask for what they need if they do not know what they need.
This is where intentional, everyday conversations and tools make a huge difference.
**Start with sensory preferences.** Help your child build awareness of their sensory world. Do they prefer dim lighting or bright rooms? Do certain textures bother them? Are they a child who seeks movement or one who prefers stillness? You can create a simple "sensory profile" together. Use pictures to identify things that feel good, things that feel bad, and things that are just okay.
**Name their strengths.** Neurodiversity-affirming approaches frame neurological differences as natural human variation, not deficits. Help your child understand what they are great at. Maybe they have an incredible memory for facts, a deep passion for specific topics, or an unusual ability to notice patterns. Knowing their strengths builds the confidence they need to also talk about their challenges.
**Explore how their brain works.** Age-appropriate conversations about neurodivergence help children develop a framework for understanding their experiences. You might say, "Your brain is wired to notice every sound in the room. That is a superpower sometimes, and sometimes it makes things feel overwhelming. Both of those things are true."
Tools like [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s **emotion tracking** features can be incredibly helpful here. When children regularly check in with their emotions using visual supports, they begin to notice patterns. "I always feel cranky after loud places." "I feel happy when I get to draw first thing in the morning." These insights become the raw material for self-advocacy.
## Teaching Communication Scripts
Once children begin to understand their own needs, they need the language to express them. For many neurodivergent children, especially those who are non-speaking, minimally speaking, or who struggle with spontaneous language, **visual scripts** are a game-changer.
Visual scripts are pre-taught phrases or sequences, often paired with pictures, that children can use in specific situations. They take the pressure off having to generate language in the moment and provide a reliable framework for communication.
**Essential self-advocacy scripts to teach:**
- **Requesting help:** "I need help with this, please." (Paired with a visual of a child raising their hand or approaching an adult.)
- **Asking for a break:** "I need a break." or "My body needs to move." (Paired with a visual of a calm-down corner or movement activity.)
- **Expressing sensory needs:** "It is too loud for me." or "I need my headphones." (Paired with visuals of the sensory trigger and the solution.)
- **Setting boundaries:** "I do not want a hug right now." or "Please stop, I do not like that." (Paired with visuals showing personal space.)
- **Asking for accommodations:** "Can I sit in the quiet area?" or "I work better when I can use my fidget." (Paired with visuals of the accommodation.)
You can create these scripts using **social stories** that walk through the situation step by step. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social story feature, combined with **AI-generated personalized images**, lets you build scripts that feature your child in familiar settings. When a child sees themselves in the story, it becomes more meaningful and easier to internalize.
Practice these scripts the way you would practice any skill: frequently, in low-pressure moments, with lots of encouragement.
Download on the App Store
## Practicing in Safe Environments
Knowing a script is one thing. Using it in real life is another. The bridge between the two is practice in safe, supportive environments.
**Role-play at home.** Set up common scenarios and practice together. You might pretend to be a teacher and have your child practice saying, "I need a break, please." Switch roles so they can see what it looks like from both sides. Keep it playful and low-stakes. Stuffed animals and action figures make excellent stand-ins for tricky social situations.
**Use social stories before challenging situations.** If your child has a field trip coming up, create a social story that walks through the day and includes moments where they might need to advocate for themselves. "If the museum is too loud, I can tell my teacher, 'I need to step into the quiet room.'" Reviewing the story beforehand gives your child a mental rehearsal that makes the real moment feel more familiar.
**Create a visual schedule that includes advocacy checkpoints.** Build moments into your child's daily routine where they practice making choices and expressing preferences. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s **visual schedule** feature makes this easy to do. You might include a "check-in" step where your child identifies how they are feeling, or a "choice time" where they pick between two activities. These small, embedded moments of self-advocacy add up over time.
**Celebrate the attempts, not just the outcomes.** Research shows that children who practice advocacy in safe environments are more likely to generalize those skills to new settings. Every practice session, even an imperfect one, is building neural pathways and muscle memory for the real thing.
.png)
## Emotion Literacy as a Foundation
Self-advocacy and emotion literacy are deeply intertwined. A child who can name what they are feeling is far better equipped to communicate what they need.
**Start with the basics.** Help your child identify and name the core emotions: happy, sad, angry, scared, surprised, and disgusted. Use picture cards, emotion charts, or apps with visual supports. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s **emotion tracking** tools give children a visual way to check in with their feelings throughout the day, building familiarity and fluency over time.
**Connect feelings to body sensations.** Many neurodivergent children experience emotions intensely but struggle to identify them. Teaching body awareness helps bridge this gap. "When your stomach feels tight and your fists are clenched, that might be anger." "When your chest feels fluttery and you want to run, that might be anxiety." Body maps where children color in where they feel different emotions can be a powerful tool.
**Link feelings to needs.** This is the crucial step that turns emotion literacy into self-advocacy. Help your child see that feelings carry information. "You are feeling frustrated. What do you think would help right now?" Over time, children learn to make these connections independently. "I am feeling overwhelmed. I think I need some quiet time."
**Expand the vocabulary.** As children grow, help them move beyond basic emotion words to more nuanced ones. "Frustrated" is more useful than "mad." "Overstimulated" is more specific than "bad." The richer their emotional vocabulary, the more precisely they can communicate their needs.
## Supporting Self-Advocacy at School
School is where self-advocacy skills get their biggest test. It is also where they matter most.
**Start with the IEP or 504 team.** If your child has an Individualized Education Program or a 504 plan, these meetings are natural opportunities to practice self-advocacy. Even very young children can participate in some way. A preschooler might choose a picture that represents their favorite part of school. An elementary student might share one thing that helps them learn. An older student can present their own strengths and accommodation needs.
**Prepare your child before meetings.** Use a visual schedule or social story to walk through what the meeting will look like, who will be there, and what your child might say. Practice key phrases like "I learn best when..." or "Something that is hard for me is..." The more prepared they feel, the more likely they are to participate.
**Partner with teachers.** Share your child's communication scripts with their teachers and support staff. Let them know what self-advocacy looks like for your child and how to respond when your child uses their scripts. A teacher who responds positively when a child says "I need a break" reinforces the skill far more effectively than one who says "Not right now."
**Create a self-advocacy toolkit for school.** This might include a small card with key phrases, a visual feelings chart in their binder, or a signal they can use with their teacher when they need something. The goal is to make advocacy accessible even in the structured, sometimes overwhelming environment of a classroom.
## Celebrating Self-Advocacy Moments
When your child speaks up for themselves, that deserves recognition. Positive reinforcement strengthens the connection between advocacy and positive outcomes, making it more likely your child will advocate again in the future.
**Be specific with your praise.** Instead of "Good job," try "I noticed you told your brother you needed space. That was really brave and it helped you stay calm." Specific praise helps children understand exactly what they did well.
**Use a reward system thoughtfully.** For some children, a visual reward system can provide extra motivation during the learning phase. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s **reward system** feature lets you set up personalized goals and track progress with visual tokens. You might create a goal around using advocacy scripts, with a small celebration when your child reaches a milestone.
**Share advocacy wins with the family.** At dinner or during a family meeting, highlight moments of self-advocacy you observed during the day. "Today your sister told her teacher she needed to sit in the quiet corner during reading time. That took a lot of courage." This normalizes advocacy and makes it a family value, not just a skill to practice.
**Let your child see you self-advocate.** Children learn by watching. Narrate your own self-advocacy moments: "I am going to ask the server if they can turn down the music. It is a little loud for me." Modeling shows children that advocacy is a normal, lifelong practice, not something only they have to do.
## Building Self-Advocacy Skills with VizyPlan
Teaching self-advocacy is not a single conversation or a one-time lesson. It is a daily practice woven into the fabric of your child's routine. And that is exactly where [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) can help.
With **visual schedules**, you can embed self-advocacy checkpoints into your child's day, giving them regular opportunities to check in with their feelings, make choices, and practice expressing their needs. The **emotion tracking** feature builds the emotional vocabulary that fuels self-advocacy, helping your child notice patterns and connect feelings to actions. **Social stories** with **AI-generated personalized images** let you create custom scripts for any situation your child might face, from asking for help at school to setting boundaries with a friend. And the **reward system** provides positive reinforcement that keeps your child motivated as they build these crucial skills.
Self-advocacy is one of the greatest gifts you can give your neurodivergent child. It says, "Your needs matter, your voice matters, and you are capable of speaking up for yourself." With patience, practice, and the right visual supports, every child can learn to be their own best advocate.
**Ready to start building self-advocacy skills into your child's daily routine?** [Download VizyPlan today](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and try it free for 7 days. No credit card required upfront, just $6.99/month after your trial. Because every child deserves the tools to speak up for themselves.
---
## Navigating Playdates and Social Gatherings with Your Neurodivergent Child
Published: 2025-01-31
URL: https://vizyplan.com/blog/navigating-playdates-social-gatherings-neurodivergent-child
Category: Strategies
Author: Justin Bowman
> Practical strategies for making playdates and social events successful for neurodivergent children, from preparation and interest-based socializing to sensory breaks and celebrating wins.
If your child freezes at the door of a birthday party, melts down after 20 minutes at a friend's house, or begs not to go to the neighborhood barbecue, you are not alone. Social gatherings that seem effortless for other families can feel like navigating a minefield when you are raising a neurodivergent child.
But here is the thing: your child is not "bad at socializing." Their brain simply processes social environments differently. And with the right preparation, accommodations, and support, playdates and social gatherings can become genuinely enjoyable experiences for the whole family.
This guide will walk you through evidence-based, neurodiversity-affirming strategies for before, during, and after social events. Whether your child is autistic, has ADHD, sensory processing differences, or any combination, these approaches can help build social confidence one small success at a time.
## Why Social Situations Are Uniquely Challenging
Before we dive into strategies, it helps to understand *why* social gatherings are so demanding for neurodivergent children. It is rarely about a lack of desire to connect. Most neurodivergent kids want friendships deeply. The challenge lies in the environment itself.
**Sensory overload.** Birthday parties, playdates at unfamiliar homes, and family gatherings bombard the senses. Loud music, competing conversations, unfamiliar smells, fluorescent lighting, and crowded rooms create a sensory storm that can overwhelm a child before any socializing even begins.
**Unstructured time.** Many neurodivergent children thrive with clear expectations and routines. "Go play!" is one of the most anxiety-inducing instructions for a child who does not intuitively know how to enter a group, initiate play, or figure out the "rules" of an unstructured social setting.
**Unwritten social rules.** Neurotypical social interaction is full of implicit expectations: when to make eye contact, how close to stand, when it is your turn to talk, how to read facial expressions. For many neurodivergent children, these "obvious" rules are anything but.
**Unpredictable environments.** New homes, unfamiliar adults, unexpected changes to the plan, surprise activities. Unpredictability is the enemy of regulation for many neurodivergent kids. When a child cannot predict what will happen next, their nervous system stays on high alert.
Understanding these challenges is not about lowering expectations. It is about building the right scaffolding so your child can succeed.
## Preparing Before the Playdate
The most important work happens before you ever leave the house. Preparation is your superpower as a parent of a neurodivergent child.
**Create a visual schedule of what to expect.** Children who struggle with uncertainty benefit enormously from knowing what is coming. A simple visual schedule that outlines the playdate step by step can transform anxiety into anticipation.
Your visual schedule might look something like this:
- Get dressed and pack our bag
- Drive to Marcus's house (10 minutes)
- Say hello to Marcus and his mom
- Play with Legos together
- Have a snack
- Play outside for a little while
- Say goodbye and drive home
The key is to be specific and honest. If you are not sure what activities will be available, it is perfectly fine to include "surprise activity" as a step so your child knows to expect something unplanned. Tools like **[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)** make this incredibly easy. You can build a personalized visual schedule with AI-generated images that match the specific details of your child's upcoming playdate. Instead of generic clip art, your child sees images that look like their actual experience, which makes the preparation feel real and relevant.
**Use social stories.** Social stories are short, simple narratives that walk a child through a social situation, including what will happen, how people might feel, and what they can do. Research consistently supports their effectiveness for helping neurodivergent children understand social expectations.
Before a playdate, you might create a social story about:
- **Sharing and turn-taking:** "When Marcus is playing with a toy I want, I can say 'Can I have a turn when you are done?' Then I can play with something else while I wait."
- **Joining play:** "When I get to the party, I can watch what the other kids are doing first. Then I can ask, 'Can I play too?'"
- **Handling disappointment:** "If we do not play the game I wanted, that is okay. I can take a deep breath and try the other game. I might even like it."
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s social story feature lets you create these narratives with personalized visuals, so your child sees themselves in the story. This personal connection makes social stories significantly more effective than generic versions.
**Choose the right environment.** Not all social settings are created equal. When possible, choose environments that set your child up for success:
- **Familiar locations** over new ones
- **Smaller groups** (one-on-one playdates are a great starting point) over large gatherings
- **Shorter durations** over marathon events
- **Activity-based gatherings** over unstructured free play
- **Quieter settings** over loud, chaotic ones
You know your child best. If the neighborhood block party with 40 people and a bouncy castle is going to be too much, there is no shame in suggesting a quieter one-on-one playdate with one friend from the party instead.
## The Power of Interest-Based Socializing
Here is one of the most important things to understand about neurodivergent social connection: it often works differently than neurotypical socializing, and that is perfectly okay.
Many neurodivergent children (and adults) connect most naturally through **shared interests**. This is sometimes called "interest-based socializing," and it is a genuine strength, not a deficit.
Instead of expecting your child to engage in free-form social chitchat, lean into their passions:
- If your child loves dinosaurs, invite a friend to visit a natural history museum together
- If they are into Minecraft, set up a side-by-side gaming session
- If they love building, plan a Lego or craft-based playdate
- If they are drawn to animals, visit a farm or pet store together
**Structured activities provide a shared focus**, which takes the pressure off constant social negotiation. Two kids building a Lego set together are naturally practicing turn-taking, communication, and collaboration without the overwhelming demand of unstructured "just play."
Research in play therapy supports this approach. Following the child's lead and building social opportunities around their genuine interests creates more authentic connection than forcing participation in activities that feel meaningless or distressing.
Download on the App Store
## During the Playdate: Strategies That Work
Even with great preparation, your child will likely need support during the event itself. Here are practical strategies to keep things on track.
**Use visual timers.** Many neurodivergent children struggle with the abstract concept of time. "We are leaving in 30 minutes" means very little to a child who cannot feel time passing. Visual timers make the invisible visible. Use a visual timer to show how long until transition points, turn-taking intervals, or how long until it is time to go home. When your child can see time moving, transitions become less jarring and conflicts over sharing become easier to navigate.
**Build in sensory breaks.** Do not wait for a meltdown to take a break. Proactively schedule sensory breaks into your playdate plan. This might look like a five-minute quiet time in a separate room, a walk around the block together, time with noise-canceling headphones, or a few minutes of deep pressure input. Normalize these breaks by building them into the visual schedule from the start. When a sensory break is just "step 4 on the schedule," it does not feel like punishment or failure. It feels like part of the plan.
**Adult facilitation (without hovering).** Your role during a playdate is to be a bridge, not a helicopter. This means narrating social cues your child might miss, offering language for tricky moments, stepping back when things are going well, and redirecting gently when things start to go sideways. The goal is to gradually reduce your involvement over time as your child builds their own social toolkit.
## Hosting vs. Attending: A Strategic Decision
Where the playdate happens matters more than you might think.
**The advantages of hosting:** When you host, your child has home-field advantage. They have a familiar sensory environment, access to comfort items, control over the space, and predictability. A helpful tip: before the friend arrives, let your child choose which toys they are willing to share and put away any special items that would cause distress. This prevents conflict and teaches self-advocacy.
**When you are attending:** If you are going to someone else's home or a public venue, visit the location beforehand if possible, bring a comfort kit (noise-canceling headphones, a favorite small toy, a chewy snack, sunglasses), identify a quiet space where your child can retreat, and have an exit plan discussed in advance. Knowing they have an escape route actually helps many neurodivergent children stay longer, because the option to leave reduces the feeling of being trapped.
## After the Playdate: Reflection and Celebration
What happens after the playdate is just as important as the preparation. This is where you reinforce learning and build confidence for next time.
**Emotion check-ins.** Give your child space to process how they felt. For children who struggle to name emotions verbally, emotion tracking tools can be incredibly helpful. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion check-in feature lets children identify how they are feeling using visual supports, which builds emotional vocabulary over time and helps you spot patterns. Maybe your child consistently feels drained after gatherings longer than an hour, or maybe they feel happiest after playdates that involve building activities. These insights help you plan better next time.
**Celebrate successes with reward systems.** Every successful social interaction, no matter how small, deserves recognition. Did your child say hello to the host? Share a toy without a meltdown? Ask for a break instead of hitting? Stay for the whole playdate? Reward systems that acknowledge effort help neurodivergent children associate social situations with positive feelings. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s reward system lets you set up personalized goals and celebrations, so your child sees their social bravery reflected back to them in a concrete, motivating way.
Be specific with your praise: "I noticed you waited your turn with the train set even though it was really hard. That took a lot of patience, and I am so proud of you."
## Building Social Skills Gradually Over Time
Social skill development is not a straight line. There will be wonderful playdates and terrible ones. The research is clear: short, successful interactions build more social confidence than long, overwhelming ones. It is better for your child to leave a playdate after 20 happy minutes than to push through 90 miserable ones. Success breeds success. Each positive experience lays the foundation for the next one.
A neurodiversity-affirming approach means we are not trying to make our children "look neurotypical" in social settings. We are trying to help them build genuine connections in ways that honor how their brains work. That might mean side-by-side play instead of face-to-face conversation. It might mean bonding over shared facts about marine biology instead of small talk. It might mean two kids happily stimming together while watching a favorite show. All of these are valid, meaningful social connections.
## How VizyPlan Supports Your Child's Social Journey
Everything we have discussed in this guide, from visual schedules and social stories to emotion check-ins and reward systems, comes together in [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118).
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) is an AI-powered visual routines app designed specifically for neurodivergent children. It helps you:
- **Build personalized visual schedules** for playdates and social events with AI-generated images that match your child's real life
- **Create social stories** that prepare your child for specific social situations
- **Track emotions** before and after social gatherings to spot patterns and celebrate growth
- **Set up reward systems** that motivate and recognize social bravery
- **Use visual timers** that make transitions smoother and more predictable
Social situations do not have to be a source of dread for your family. With the right preparation, the right tools, and a neurodiversity-affirming mindset, your child can build meaningful friendships at their own pace, in their own way.
**Start your free 7-day trial of [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) today. No credit card required.** Plans start at just $6.99/month. [Download VizyPlan on the App Store](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and start building visual supports for your child's next playdate.
You know your child better than anyone. Trust that knowledge, lean into their strengths, and remember: every small step forward is a victory worth celebrating.
---
## Starting School: How to Prepare Your Neurodivergent Child for the Classroom
Published: 2025-01-30
URL: https://vizyplan.com/blog/starting-school-prepare-neurodivergent-child-classroom
Category: Strategies
Author: Justin Bowman
> Evidence-based strategies for preparing neurodivergent children for school, including visual schedules, social stories, morning routines, and classroom accommodations.
Starting school is one of the biggest transitions in any child's life. For neurodivergent children, including those with autism, ADHD, sensory processing differences, or developmental delays, this milestone comes with a unique set of challenges that can feel overwhelming for both kids and parents alike. The bright fluorescent lights, the unpredictable noise of a crowded hallway, the unspoken social rules that seem to come naturally to other children. It can be a lot.
But here is the good news: with the right preparation, your child can walk into that classroom feeling more confident, more regulated, and more ready to learn. Research consistently shows that visual supports, gradual exposure, and predictable routines are among the most effective tools for reducing anxiety and supporting successful school transitions for neurodivergent kids.
Whether your child is starting school for the very first time or transitioning to a new grade or new building, this guide will walk you through practical, evidence-based strategies to make the process smoother for your whole family.
## Why Starting School Is Uniquely Challenging for Neurodivergent Children
Before we dive into preparation strategies, it helps to understand why school can feel so different for neurodivergent kids. When we understand the "why," we can better anticipate what our children need.
**Sensory overload is real.** Schools are loud, bright, and busy places. The hum of fluorescent lights, the echo of sneakers in a gymnasium, the smell of cafeteria food, the feel of a stiff new uniform. For children with sensory processing differences, these inputs can be physically painful or deeply disorienting. What looks like a "meltdown" is often a nervous system that has simply hit its limit.
**New routines demand enormous cognitive energy.** Neurodivergent children often thrive on predictability. School introduces dozens of new micro-routines all at once: where to hang your backpack, when to line up, how to ask for help, what happens after lunch. Each of these requires working memory, flexibility, and executive functioning skills that may still be developing.
**Social expectations are often unspoken.** The classroom is a social environment with countless invisible rules. Raise your hand before speaking. Wait your turn. Make eye contact when the teacher talks to you. Share materials with a partner. For children who process social information differently, these expectations can feel like trying to follow a game where nobody explained the rules.
**Communication demands increase dramatically.** At home, you understand your child's communication style. You know their gestures, their expressions, their unique ways of telling you what they need. At school, they will need to communicate with new adults and peers who do not yet have that understanding. This can be exhausting and frustrating for children, especially those who use alternative communication methods.
Understanding these challenges is not about expecting the worst. It is about being prepared so you can set your child up for success.
## Preparing Weeks Before: Laying the Foundation
The most effective school preparation does not start the night before. It starts weeks, or even months, in advance. Gradual exposure and practice are two of the most powerful tools in your toolkit.
**Visit the school ahead of time.** Many schools will accommodate pre-visit requests, especially when you explain your child's needs. Try to visit when the building is quiet so your child can explore without the added stress of crowds. Walk the hallways. Find the bathroom. Sit in the classroom. Touch the desk. Let your child build a mental map of the space in a low-pressure environment. If possible, visit more than once so the environment starts to feel familiar rather than foreign.
**Create a visual schedule of the school day.** Research shows that visual schedules significantly reduce anxiety by giving children a concrete sense of what comes next. A visual schedule transforms the abstract concept of "a school day" into a predictable sequence your child can reference and rely on. Break the day into clear, visual steps: arrival, morning circle, reading time, snack, recess, lunch, afternoon activities, dismissal. Use pictures or icons that your child connects with.
With [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), you can build a detailed visual schedule for the school day using AI-generated personalized images that actually look like your child's school experience. Instead of generic clipart, your child sees images that reflect their world, which makes the schedule more meaningful and easier to engage with.
**Use social stories to explain classroom expectations.** Social stories, a strategy developed by Carol Gray, are short narratives that describe a situation, the expected behaviors, and the perspectives of others involved. They are incredibly effective for helping neurodivergent children understand new environments. Create simple stories about things like: "What happens when I get to school," "How to ask my teacher for help," or "What to do at recess." Read these stories together daily in the weeks leading up to the first day.
**Practice, practice, practice.** Do a "dress rehearsal" of the school morning routine. Drive or walk the route to school. Practice putting on the backpack, opening the lunchbox, using the zipper on the jacket. The more your child physically rehearses these actions, the less cognitive energy they will need on the real day.
## Morning Routine Strategies: Starting the Day Strong
The morning sets the tone for the entire school day. A chaotic, rushed morning can dysregulate your child before they even walk through the school doors. A calm, predictable morning gives them the best possible foundation.
**Build a visual morning checklist.** Break the morning into small, manageable steps with a visual checklist your child can follow independently. This might include: wake up, use the bathroom, get dressed, eat breakfast, brush teeth, put on shoes, grab backpack, go to the car. Each step should have a clear image and be presented in order.
**Prepare the night before.** Reduce morning decision-making by laying out clothes the night before, packing the backpack, and preparing lunch. For children with ADHD or executive functioning challenges, fewer decisions in the morning means less opportunity for the routine to go off track.
**Make getting dressed easier.** Sensory sensitivities can turn getting dressed into a daily battle. Wash new clothes several times before the first day to soften them. Cut out tags. Let your child choose between two pre-selected outfits rather than facing an open closet. If your child has strong sensory preferences, honor them whenever school dress codes allow.
**Build in transition time.** Many neurodivergent children need extra time to shift from one activity to the next. Build buffer time into your morning so transitions do not feel rushed. A five-minute warning before it is time to leave the house can make a world of difference.
**Use a reward system for morning wins.** Positive reinforcement is one of the most well-supported strategies in behavioral research. Celebrate small victories in the morning routine. Finished getting dressed without a reminder? That earns a star. Completed the whole checklist? Choose a favorite activity after school. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s built-in reward system makes it easy to track these wins and keep your child motivated with visual progress they can see and feel proud of.
Download on the App Store
## Classroom Preparation: Setting Up for Success
You cannot control everything that happens in the classroom, but you can prepare your child and collaborate with their teacher to create the best possible environment.
**Introduce sensory tools early.** Talk to your child's teacher about sensory supports that can help your child stay regulated during the school day. This might include noise-canceling headphones for loud environments, a fidget tool for focused work time, a wiggle cushion for sitting, or a designated quiet space your child can use when they feel overwhelmed. The key is to introduce these tools as normal and helpful, not as something that sets your child apart.
**Create communication cards or supports.** For children who struggle with verbal communication under stress, visual communication cards can be a lifeline. Simple cards that say "I need a break," "I need help," or "I feel upset" give your child a way to advocate for themselves when words are hard to find. Practice using these at home so they feel natural at school.
**Collaborate with the teacher before day one.** Schedule a meeting with your child's teacher before school starts. Share what works for your child: what calms them, what triggers dysregulation, how they communicate best, and what their strengths are. Teachers want to support your child, and the more information they have, the better equipped they will be. Bring a one-page summary they can reference easily.
**Prepare for transitions between activities.** Transitions are one of the hardest parts of the school day for many neurodivergent children. Moving from free play to structured work, from the classroom to the cafeteria, from recess back inside. Ask the teacher if they can give your child advance notice before transitions and whether visual or auditory cues are used in the classroom. Practice transitions at home by using timers and visual countdowns so your child develops familiarity with the concept.
**Identify a safe person.** Help your child identify one trusted adult at school they can go to if they feel overwhelmed. This might be their teacher, a school counselor, or a special education aide. Knowing there is a safe person available can reduce anxiety significantly.
.png)
## After-School Decompression: The Recovery Period
Here is something many parents do not realize until they experience it: your child may come home from school completely drained. They have spent the entire day masking, processing, adapting, and holding it together. After-school meltdowns are common, and they are not a sign that school is failing. They are a sign that your child has been working incredibly hard all day and finally feels safe enough to let go.
**Create a predictable after-school routine.** Just as the morning routine sets the tone for the day, a consistent after-school routine helps your child decompress and transition back to home life. This might include: a quiet snack, 20 minutes of free choice time (screens, sensory play, or just lying on the couch), followed by a brief check-in about the day.
**Do emotion check-ins, not interrogations.** Instead of asking "How was school?" (which is overwhelming and vague for many neurodivergent kids), try more specific and visual approaches. Use an emotion chart, a feelings thermometer, or a simple thumbs-up/thumbs-down system. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking feature makes this easy by giving your child a visual way to express how they are feeling after school. Over time, you will start to see patterns. Maybe Tuesdays are always harder because of gym class. Maybe Fridays are better because of art. These patterns help you anticipate and plan.
**Protect decompression time fiercely.** It can be tempting to fill after-school hours with homework, therapy appointments, and extracurricular activities. But neurodivergent children often need significant downtime to recover from the sensory and social demands of school. Be intentional about building in unstructured, low-demand time, especially in the early weeks.
**Let them stim, move, and regulate.** If your child needs to jump on a trampoline, spin in circles, listen to the same song on repeat, or retreat to a dark room after school, let them. These are not "bad habits." These are self-regulation strategies. Your child is doing exactly what their nervous system needs to recover.
## Handling Setbacks and Building Resilience
No matter how well you prepare, there will be hard days. There will be meltdowns in the parking lot, tears at drop-off, notes from the teacher, and evenings where your child says they never want to go back. This does not mean you have failed. It means school is hard, and your child is still learning.
**Normalize difficulty without dismissing feelings.** Saying "School is hard sometimes, and it is okay to feel that way" validates your child's experience while also communicating that hard things are survivable. Avoid minimizing ("You'll be fine!") or catastrophizing ("Oh no, what happened?!"). Aim for calm, steady reassurance.
**Look for patterns, not just incidents.** When a rough day happens, resist the urge to react to the single event. Instead, look at the bigger picture. Is there a specific time of day that is consistently difficult? A particular activity or environment? A social situation that keeps coming up? Patterns point you toward solutions. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s emotion tracking can be especially helpful here, giving you a visual record of your child's emotional landscape over time so you can spot trends and adjust strategies accordingly.
**Celebrate progress, not perfection.** Your child does not need to have a flawless school day to be succeeding. Did they walk into the building without crying today? That is progress. Did they use their communication card to ask for a break? That is a win. Did they try a new food at lunch? Incredible. Reward systems that acknowledge effort and small steps forward build the kind of intrinsic motivation that lasts. Focus on what went right, even on the days that feel mostly wrong.
**Stay in communication with the school team.** Regular check-ins with your child's teacher, counselor, or special education team help you stay ahead of problems rather than reacting to crises. A quick weekly email or a shared communication journal can keep everyone on the same page.
**Give it time.** Adjustment to school does not happen overnight. Many neurodivergent children need several weeks, sometimes longer, to truly settle into a new routine. Be patient with the process and with yourself. You are doing harder parenting work than most people realize, and you are doing it with love.
## How VizyPlan Supports School Transitions
Preparing a neurodivergent child for school involves a lot of moving pieces: visual schedules, social stories, morning routines, emotion tracking, reward systems, and constant communication. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) brings all of these tools together in one app, designed specifically for families like yours.
With [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118), you can:
- **Build personalized visual schedules** for school mornings, the school day itself, and after-school routines, complete with AI-generated images that reflect your child's real life
- **Create social stories** to help your child understand new classroom expectations, recess, lunch, and transitions
- **Track emotions** daily to spot patterns in school-related stress and celebrate emotional growth
- **Use built-in reward systems** to reinforce positive school behaviors and morning routine wins
- **Adjust and adapt easily** as your child's needs change throughout the school year
Every child's school journey looks different. [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) gives you the flexibility to create routines and supports that fit your child, not the other way around.
**[Start your 7-day free trial today](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)** and build your child's school routine before the first bell rings. It is $6.99/month after the trial, with no credit card required upfront.
You know your child better than anyone. Trust that knowledge, prepare with intention, and remember: the goal is not a perfect first day. The goal is a child who knows they are supported, no matter what the school day brings.
---
## Preparing Your Neurodivergent Child for a New Baby
Published: 2025-01-29
URL: https://vizyplan.com/blog/preparing-neurodivergent-child-new-baby-sibling
Category: Strategies
Author: Justin Bowman
> Practical strategies for helping autistic and ADHD children navigate the arrival of a new sibling, from pregnancy preparation through the first months at home.
A new baby changes everything for a family. For neurodivergent children, that change carries extra weight. The disrupted routines, unpredictable noises, shifted attention, and reorganized living spaces can create genuine distress that goes beyond typical sibling jealousy.
The good news is that with intentional preparation, most neurodivergent children adjust well to a new sibling. The key is starting early, using strategies that align with how your child processes information, and maintaining the stability they depend on even as the family grows.
## Why This Transition Is Harder for Neurodivergent Children
Understanding the specific challenges helps you prepare for the right things rather than guessing.
**Routine disruption is the biggest threat.** Neurodivergent children often rely on predictable routines to feel safe. A new baby disrupts nearly every routine in the household, from morning schedules to bedtime, mealtimes, and weekend activities. For a child who depends on consistency, this level of change can feel overwhelming.
**Sensory overload from baby sounds.** Baby crying is loud, unpredictable, and impossible to control. For children with auditory sensitivities, this is not just annoying, it can be genuinely painful and distressing. The cry of a newborn can reach 100 decibels, roughly equivalent to a power tool.
**Abstract concepts are hard to grasp.** "You're going to be a big brother" is an abstract idea. Neurodivergent children who are concrete thinkers may not understand what a baby actually means for their daily life until it happens, which means the reality hits harder than expected.
**Attention changes feel personal.** When a parent who previously provided focused one-on-one time suddenly splits their attention with a demanding newborn, neurodivergent children may interpret this as rejection rather than a temporary adjustment.
**New items in the environment cause stress.** A bassinette in the bedroom, a changing table in the bathroom, a swing in the living room. These physical changes to familiar spaces can create anxiety for children who find comfort in environmental consistency.
## Starting Preparation During Pregnancy
The preparation window is longer than most parents realize. Begin months before the due date.
**Introduce the concept gradually.** Use simple, concrete language: "A baby is growing in Mommy's tummy. The baby will come to live with us." Avoid overloading with information. Let your child absorb one concept before adding more.
**Read social stories about new babies.** Visual stories that walk through what to expect, what babies look like, what they sound like, and how the family will change provide concrete previews of an abstract future. Reading the same story repeatedly helps neurodivergent children process and internalize the information at their own pace.
**Create a visual story personalized to your family.** Generic social stories help, but personalized ones are more effective. A visual narrative showing your child's actual home, their room, and where the baby will sleep makes the upcoming change concrete rather than theoretical. Tools that let you create custom visual stories using images your child recognizes turn an abstract "someday" into something they can actually picture.
**Introduce baby items slowly.** Rather than transforming the house overnight when the baby arrives, bring in items gradually over weeks. Set up the crib early. Place baby blankets where they will eventually go. Let your child adjust to each physical change before adding the next one. Some therapists recommend moving a baby doll through these spaces so the child can see how the items will be used.
**Practice with a baby doll.** Role-playing with a doll helps your child rehearse interactions they will have with the baby. Show them how to hold, feed, and be gentle. This builds familiarity and can also increase pretend play and social skills.
**Begin adjusting routines before the baby arrives.** If the baby's arrival will require schedule changes, like a new bedtime routine or a different morning sequence, make those changes now. Your child will have enough to adjust to when the baby arrives. Separating routine changes from the baby's arrival prevents your child from associating all disruption with the new sibling.
## Preparing for Sensory Challenges
Baby sounds are the most commonly cited challenge for neurodivergent children adjusting to a new sibling.
**Desensitize to baby crying gradually.** Play recordings of baby sounds at low volume during calm, positive moments. Gradually increase the volume over days and weeks. Pair the sounds with preferred activities or small rewards so your child builds tolerance while associating the sound with positive experiences rather than anxiety.
**Have noise-reducing tools ready.** Noise-canceling headphones, earplugs, or a white noise machine in your child's room provide immediate relief when the baby cries. These are not avoidance tools, they are regulation tools that let your child manage their sensory input.
**Create a sensory-safe retreat.** Designate a quiet space in your home where your child can go when they feel overwhelmed. Stock it with calming items: a weighted blanket, fidget tools, favorite books, or whatever helps your child regulate. Make sure they know this space is always available to them.
**Prepare for new smells and textures.** Babies bring new sensory experiences beyond sound: diaper smells, formula, lotion, wet wipes. Introduce these products before the baby arrives so they become familiar rather than surprising.
## Updating Visual Routines for the New Reality
Your child's daily routine will change when the baby arrives. Visual schedules help make those changes predictable rather than chaotic.
**Add baby-related activities to the existing schedule.** Rather than creating an entirely new routine, modify your child's current visual schedule to include baby-related moments: "Baby eats," "Quiet time while baby sleeps," "Help with baby." Seeing these new activities within their familiar routine framework reduces anxiety.
**Build in protected one-on-one time and make it visible.** Schedule specific time for just you and your older child, and put it on their visual schedule where they can see it. When a child can look at their day and see "Special time with Mom" or "Park with Dad" clearly marked, the reassurance is concrete rather than a vague promise that may or may not happen.
**Use first-then boards for difficult moments.** "First, quiet time while baby naps. Then, playground." When the "then" is clearly visible and motivating, your child can tolerate the "first" more easily because they know exactly what comes next.
**Keep the visual schedule accessible.** During the chaotic newborn period, the visual schedule becomes even more important. It is the one constant your child can rely on when everything else feels unpredictable. Make sure it is always visible and updated.
## Tracking Emotions Through the Adjustment
The weeks and months after a new baby arrives are emotionally complex for neurodivergent children. Tracking how your child feels during this transition reveals patterns you might otherwise miss.
**Watch for regression signals.** Returning to behaviors they had outgrown, like bedwetting, baby talk, thumb sucking, or increased clinginess, often signals that your child is struggling with the adjustment. These behaviors are communication, not defiance.
**Log emotions alongside daily activities.** Paying attention to when your child seems most stressed versus most regulated can reveal specific triggers. Maybe they struggle most during feeding times when your attention is divided, or maybe bedtime is harder because the baby disrupts the routine. Tracking feelings tied to specific activities surfaces patterns that inform your approach. You might discover that mornings are fine but afternoons are consistently difficult, which tells you where to add extra support.
**Distinguish jealousy from sensory overload.** A child refusing to be in the same room as the baby might be jealous, or they might be overwhelmed by the noise and unpredictability. The intervention is completely different depending on the cause. Emotion tracking over time helps you identify which factor is driving the behavior.
**Celebrate positive moments with the baby.** When your child shows interest, gentleness, or curiosity toward the baby, acknowledge it. A reward system where positive interactions earn points toward something your child wants reinforces the behaviors you hope to see more of. Small, immediate rewards for gentle touches, sharing space calmly, or helping with the baby build motivation organically.
## The First Week Home
The initial days after bringing the baby home set the tone.
**Introduce the baby during a calm moment.** Avoid the chaos of arriving home from the hospital. If possible, have your child meet the baby in a quiet, familiar setting when they are regulated and not hungry or tired.
**Bring a gift "from the baby."** A small present that the baby "brought" for their big sibling starts the relationship with a positive association.
**Maintain the first day's routine as closely as possible.** The day your family comes home with the baby should feel as normal as possible for your child. Same meals. Same activities. Same bedtime. The baby is the new element, everything else stays familiar.
**Let your child lead their level of interaction.** Some children want to hold the baby immediately. Others need days before they are ready to be close. Follow your child's lead without forcing interaction.
**Keep visitors manageable.** Well-meaning family and friends can overwhelm your home with noise, unfamiliar people, and disrupted routines. Limit visitors in the first few days, or create a visitor schedule that protects your child's need for predictability.
.png)
## Handling Behavioral Changes
Expect some behavioral changes and plan for them rather than reacting in the moment.
**Increased meltdowns are normal.** Your child's emotional regulation capacity is being stretched by enormous change. More frequent meltdowns in the first weeks do not mean the adjustment is failing. They mean your child is processing.
**Attention-seeking behavior is communication.** If your child starts acting out, getting louder, or doing things they know are against the rules, they are telling you they need more connection. The behavior is the message, not the problem.
**Avoid punishing regression.** Punishing a child for bedwetting, baby talk, or clinginess during this transition adds shame to an already difficult adjustment. Address the underlying need instead.
**Reinforce the "big kid" identity positively.** Rather than "You're a big kid now, you should know better," try "You're such a great big brother. Look how gentle you were." Frame their new role as something to be proud of rather than a responsibility to live up to.
**Keep therapy and support services in place.** If your child receives OT, speech therapy, ABA, or other services, maintain these sessions during the transition. This is not the time to pause supports. If anything, consider increasing session frequency temporarily.
## Building the Sibling Relationship Over Time
The first months are about survival. The relationship builds gradually.
**Create supervised interaction rituals.** Short, structured moments of interaction are better than long, unstructured time together. Five minutes of the older child "reading" to the baby or showing them a toy is more manageable than an open-ended expectation to "play together."
**Narrate the baby's responses.** "Look, the baby is smiling at you! She likes when you talk to her." This helps your child see the baby as a person who responds to them, building connection.
**Give your child a specific role.** A "job" related to the baby, like picking out the outfit, bringing a diaper, or singing a specific song, gives your child purpose and ownership in the new family structure.
**Photograph positive moments together.** Show your child pictures of themselves with the baby. Seeing visual evidence of their sibling relationship reinforces their identity as a big sibling.
**Be patient with the timeline.** Some neurodivergent children warm up to a new sibling in days. Others take months. Both timelines are normal. Avoid comparing your family's adjustment to anyone else's.
## When to Seek Additional Support
Some signs indicate your child may need professional support beyond your home strategies.
**Persistent aggression toward the baby** requires immediate professional guidance, even if the behavior stems from frustration rather than intent to harm.
**Regression lasting more than a few weeks** may indicate the child is stuck rather than processing. A therapist can help identify what is driving the continued struggle.
**Severe sleep disruption** that does not improve with routine adjustments may need professional evaluation.
**Complete withdrawal** from family interaction, including avoiding the baby entirely after the initial adjustment period, warrants attention.
**Your own burnout.** If you are stretched too thin to implement strategies effectively, reaching out for support is not a failure. It is parenting.
## The Bigger Picture
Adding a sibling to a neurodivergent family is a significant transition, but it is also an opportunity. Siblings of neurodivergent children often develop extraordinary empathy, patience, and advocacy skills. And neurodivergent children who adjust to a new sibling are practicing flexibility, sharing, and emotional regulation in ways that build lifelong skills.
The preparation matters more than perfection. You will not get everything right, and some days will be genuinely hard. What matters is that your child feels seen, supported, and secure in their place in the family, even as that family grows.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps families navigate big transitions with visual routines, social stories, emotion tracking, and reward systems that support your child through every change. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child the visual support they need.
---
## Why Personalized Visuals Help Neurodivergent Kids Follow Routines
Published: 2025-01-28 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/personalized-visuals-neurodivergent-children-routines
Category: Visual Supports
Author: Justin Bowman
> Research shows neurodivergent children engage more deeply with visual routines when they see themselves in the images. Here is why personalized visuals outperform generic ones.
Most parents of neurodivergent children have tried visual schedules at some point. Maybe you printed clip art from the internet, bought a laminated chart, or downloaded a free template. It worked for a while, or maybe it did not work at all. The images felt disconnected. Your child glanced at the chart but did not engage with it the way you hoped.
You are not imagining the gap. Research consistently shows that personalized visual supports are more effective than generic ones, and the difference is not small. When a child sees themselves reflected in their routine, something fundamental shifts in how they process, connect with, and follow through on what they see.
## The Problem With Generic Visual Supports
Traditional visual supports rely on stock images, clip art, or cartoon illustrations. These tools are widely available and easy to access, which explains their popularity. However, they carry significant limitations for neurodivergent learners.
**Concrete thinkers need concrete images.** Many autistic children process information in a literal, concrete manner. They focus on direct, tangible details rather than abstract concepts. A cartoon child brushing teeth does not look like their bathroom, their toothbrush, or their face. For a concrete thinker, that disconnect matters. The image represents someone else doing something somewhere else, not them doing their task in their space.
**Visual thinkers process in photo-realistic detail.** Temple Grandin's research on thinking styles in autism identifies visual thinkers as people who process information through photorealistic mental images. They form concepts by sorting pictures into categories based on real-world associations. A generic illustration does not activate the same neural pathways as an image that matches their lived experience.
**Generic images fail the recognition test.** Research on mirror neuron systems shows that children with autism respond differently to familiar versus unfamiliar visual stimuli. A UC San Diego study found that EEG measurements showed the greatest neural activation when autistic children watched videos of themselves, with slightly lower activation for familiar people, and the least activation for strangers. This finding suggests that familiarity, and particularly self-recognition, plays a direct role in how deeply autistic children engage with visual information.
**One size does not fit all families.** Stock images rarely reflect the diversity of real families. A child's race, hair texture, glasses, mobility aids, hearing devices, or family structure may be completely absent from generic visual tools. When children do not see themselves, the tool feels like it belongs to someone else.
## What Happens When Children See Themselves
The shift from generic to personalized visuals is not just a nice upgrade. It changes how the child's brain and emotional system respond to the information.
**Self-recognition activates deeper processing.** Neuroimaging studies have found that both typically developing children and children with autism activate a right prefrontal system when identifying images of their own face. For autistic children specifically, this system was most active when viewing images containing their own likeness, suggesting that self-referential visual content engages cognitive processing that generic images do not reach.
**Belonging and identity are reinforced.** Psychology research on disability representation consistently demonstrates that when children see themselves reflected in their tools and media, it strengthens self-esteem, sense of belonging, and identity formation. Conversely, a lack of representation can lead to feelings of exclusion and diminished self-worth (Santuzzi et al., 2014; Calderon & Mavrides-Calderon, 2023). Visual routines are something a child interacts with every day, often multiple times a day. That daily visual either affirms or ignores their identity.
**Abstract instructions become concrete actions.** When a child sees a personalized image of themselves brushing their teeth in their own bathroom, the instruction stops being theoretical. It becomes a concrete, recognizable action they can picture themselves completing. Research supports that visualization bridges the gap from abstract understanding to independent action, especially for children with developmental differences.
**Emotional connection drives engagement.** Children care more about tools that feel personal. A visual schedule populated with images that look like a stranger performing tasks in an unfamiliar setting does not create the same emotional pull as images that mirror the child's own world. Engagement is not optional for effectiveness. It is the foundation.
## The Research Behind Personalization
The evidence base for personalized visual supports continues to grow.
**Visual schedules are an established evidence-based practice.** The National Clearinghouse on Autism Evidence and Practice recognizes visual schedules as one of 28 evidence-based practices for autism. Studies consistently demonstrate positive effects on appropriate engagement, transitions, and independence.
**Personalization increases effectiveness.** Research in ABA therapy and visual supports shows that tailoring visual tools to individual needs, interests, and comprehension levels maximizes their effectiveness. A visual schedule incorporating pictures that resonate with the child's own experiences enhances engagement and significantly aids understanding and execution of daily routines.
**Home visual support interventions improve quality of life.** A piloted study of home-based visual support interventions for autistic children found statistically significant improvements in parent-reported quality of life (p = 0.005) and parent-reported perception of autism-specific difficulties (p = 0.006). Importantly, the researchers emphasized that visual supports should be neurodiversity-affirming, using strengths-based language rather than deficit-focused framing.
**Digital tools amplify personalization.** A comprehensive study involving over 2,000 students across 150 schools found that students using appropriately matched digital tools showed a 42% increase in task completion rates compared to traditional methods. The key insight: neurodivergent learners are not deficient, they process information through alternative pathways, and personalized digital tools create bridges that align with these natural processing patterns.
## What Personalized Visuals Actually Look Like
Understanding the concept is one thing. Knowing what to look for is another.
**Images that reflect your child's appearance.** Not a generic cartoon, but a visual representation that matches your child's hair, skin tone, features, and the things that make them recognizable to themselves.
**Settings that match real environments.** Your child's bedroom, your kitchen, their school building. When the background matches reality, the visual instruction carries more weight for a concrete thinker.
**Routines that mirror your actual steps.** Your family's breakfast is not the same as the stock photo family's breakfast. Your bedtime routine has specific steps in a specific order. Personalized visuals reflect what your child actually does, not a generic approximation.
**Interests and motivations that resonate.** A child who loves dinosaurs engages differently with a visual schedule that incorporates dinosaurs than one with generic smiley faces. Personal interests are powerful engagement levers.
**Representation of assistive tools and supports.** If your child wears glasses, uses a communication device, or has a weighted blanket as part of their routine, those details should be visible in their visuals. These are not extras. They are part of your child's identity.
.png)
## Why Generic Tools Persist Despite the Evidence
If personalized visuals are more effective, why do so many families still rely on generic ones?
**Accessibility and cost.** Custom visual supports traditionally required working with a therapist, printing materials, or creating images manually. The time and cost barriers kept personalization out of reach for many families.
**Lack of awareness.** Many families receive visual schedule recommendations without guidance on personalization. The emphasis is often on "use a visual schedule" rather than "use a visual schedule your child can see themselves in."
**Limited technology options.** Until recently, creating personalized visual content required graphic design skills or expensive professional services. Families used what was available, which meant clip art and stock images.
**The assumption that any visual is better than none.** This is partially true. A generic visual schedule is better than no visual schedule. But the gap between generic and personalized represents a significant missed opportunity for deeper engagement and effectiveness.
## Moving From Generic to Personal
The transition does not need to happen overnight. Small changes create meaningful differences.
**Start with high-frequency routines.** Personalize the visual supports your child uses most often. Morning routines, bedtime sequences, and daily transitions are used repeatedly and offer the most return on personalization.
**Involve your child.** When children participate in choosing or approving their visual representations, ownership and engagement increase. Ask which images feel most "like them."
**Update as your child grows.** Personalized visuals need to evolve. A visual that matched your child at age 4 may not resonate at age 7. Regular updates keep the tool effective.
**Track what changes.** When you switch from generic to personalized visuals, pay attention. Does your child look at the schedule more often? Follow steps more independently? Show less resistance? These observations confirm what the research predicts.
## The Deeper Message of Seeing Yourself
Beyond the practical benefits of improved routine adherence and greater independence, personalized visuals communicate something that matters enormously to neurodivergent children: you belong here.
Every time a child looks at their visual schedule and sees themselves, the implicit message is clear. This tool was made for you. This routine is yours. You are capable of doing this.
Research on autistic identity development shows that positive self-concept and a sense of belonging are indicators of higher self-esteem and wellbeing. The tools children interact with daily, their visual schedules, social stories, and routine supports, are opportunities to reinforce that positive self-image or to miss it entirely.
For concrete thinkers who process the world through what they can see and touch, representation is not an abstract concept. It is the difference between a tool that feels foreign and a tool that feels like theirs.
---
[VizyPlan](https://vizyplan.com) creates personalized visual routines using AI-generated images that help your child see themselves succeeding. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and give your child visuals that actually look like their life.
---
## Potty Training Your Neurodivergent Child: A Visual Support Guide
Published: 2025-01-27
URL: https://vizyplan.com/blog/potty-training-autism-adhd-visual-supports
Category: Daily Routines
Author: Justin Bowman
> Evidence-based strategies for potty training children with autism and ADHD, including visual schedules, sensory accommodations, and reward systems that actually work.
Potty training is challenging for any family. For parents of neurodivergent children, the process often takes longer, requires more creativity, and demands patience that can feel endless. Standard advice rarely works, and well-meaning comparisons to other children only add stress.
The good news is that with the right approach, neurodivergent children can absolutely master toileting. Understanding why this milestone is uniquely challenging for your child, and implementing strategies designed for their specific needs, makes all the difference.
## Why Potty Training Is Different for Neurodivergent Children
Before adjusting your approach, it helps to understand the specific obstacles your child faces.
**Interoception challenges affect body awareness.** Interoception is the ability to sense internal body signals like hunger, thirst, and the need to use the bathroom. Many neurodivergent children have difficulty recognizing these signals until the urge is urgent or has already passed. Traditional "watch for signs they need to go" advice fails when children genuinely do not perceive those signs.
**Sensory sensitivities create barriers.** The bathroom presents numerous sensory challenges: the cold toilet seat, the loud flush, bright overhead lights, the echo of tiles, unfamiliar textures of toilet paper, and the vulnerable physical position of sitting. Any of these can trigger avoidance or anxiety.
**Routine rigidity complicates flexibility.** A child who masters the home bathroom may refuse to use any other toilet. The need for sameness can create rigid rules about which bathroom, which seat, or which time of day toileting must happen.
**Communication difficulties add complexity.** Children with limited verbal skills need alternative ways to communicate toileting needs. Without reliable communication, accidents become more likely and frustration grows for everyone.
**Executive function challenges affect the sequence.** Using the toilet involves multiple steps in sequence: recognizing the need, stopping current activity, getting to bathroom, managing clothing, sitting, wiping, flushing, washing hands. Each transition between steps requires executive function that may be limited.
**Anxiety can develop quickly.** One negative experience, an unexpected flush, a fall, or public embarrassment, can create lasting anxiety around toileting that sets progress back significantly.
## Readiness Signs Look Different
Traditional readiness checklists may not apply to your child. Consider a modified view of readiness.
**Physical readiness matters most.** Can your child stay dry for at least two hours? Do they show some awareness of wet or soiled diapers, even if just discomfort? Physical readiness is the foundation, even if behavioral readiness looks different.
**Interest may be absent.** Many neurotypical readiness lists include "shows interest in the toilet." Your child may never show spontaneous interest, and that is okay. You can build interest through preparation and positive associations.
**Resistance is not necessarily unreadiness.** A child who actively resists may be anxious rather than unready. Addressing the underlying concern often unlocks progress.
**Later timelines are normal.** Research shows autistic children often complete toilet training between ages 3.5 and 5, later than neurotypical peers. This is a developmental difference, not a failure.
## Building Foundation Before Training
Preparation significantly improves success rates.
**Desensitize to the bathroom environment.** Before any training expectations, spend time making the bathroom comfortable. Adjust lighting if it is too harsh. Add a padded seat if cold bothers your child. Let them flush toilet paper to hear the sound without pressure. These exposures reduce sensory barriers.
**Create a visual toilet routine.** Break the process into clear steps with pictures: pull down pants, sit on toilet, try to go, wipe, pull up pants, flush, wash hands. Having the visual posted in the bathroom provides a reference that reduces cognitive load during the actual task.
**Read social stories about using the toilet.** Stories that normalize the process, explain what happens to waste, and describe what using the toilet feels like prepare your child cognitively and emotionally before physical training begins.
**Choose equipment thoughtfully.** Some children do better on small potty chairs that feel more secure. Others prefer a seat insert on the regular toilet. A step stool that allows feet to rest flat provides stability and helps with pushing. Experiment before committing.
**Establish bathroom comfort.** Before training, have your child sit on the toilet (clothed or in a diaper initially) just to practice being there. Read books together, sing songs, or bring a favorite toy. The goal is positive associations with the location.
## Using Visual Schedules for Toilet Training
Visual supports are particularly effective for potty training.
**Create a step-by-step visual sequence.** Each step of the toileting process should have its own image: walking to bathroom, pulling down pants, sitting down, trying to go, using toilet paper, standing up, flushing, washing hands. Post this sequence at your child's eye level in the bathroom.
**Add the toilet to the daily routine visual.** Show bathroom breaks within the context of the whole day. After breakfast, try the potty. Before leaving the house, try the potty. Seeing it as part of the predictable routine reduces resistance.
**Use first-then boards for motivation.** "First sit on potty, then play with trains." The visual format makes the expectation and reward clear. Keep the "then" activity genuinely motivating.
**Track attempts and successes visually.** A simple chart showing bathroom trips helps both you and your child see patterns. You might notice they are most successful after meals or that mid-morning attempts rarely work. This data informs your approach.
## Implementing Effective Reward Systems
Motivation through rewards is particularly important for toilet training.
**Provide immediate rewards.** The connection between sitting on the potty and receiving a reward must be instant. A single M&M or sticker given immediately after sitting is more effective than a bigger reward promised for later.
**Make rewards visible.** A clear jar filling with tokens, a sticker chart showing progress, or a digital tracker where your child can see points accumulating provides ongoing motivation. Visual progress is more motivating than abstract promises.
**Reward effort, not just success.** In early stages, reward sitting on the toilet regardless of results. Reward trying. Reward telling you they need to go, even if you do not make it in time. Reward any step in the right direction.
**Create a rewards menu.** Let your child choose what they are working toward. Some days they might want to earn screen time; other days a small toy appeals more. Choice increases motivation.
**Scale rewards appropriately.** Small rewards for attempts, medium rewards for success, bigger rewards for milestones like a dry day. The system should be calibrated so success happens often enough to maintain motivation.
**Celebrate without pressure.** When success happens, celebrate genuinely but briefly. Excessive celebration can create performance anxiety. A simple "You did it! Here's your sticker!" is sufficient.
## Tracking Emotions Around Toileting
Understanding your child's emotional relationship with toileting provides crucial information.
**Notice patterns in resistance.** Is your child more resistant at certain times of day? In certain locations? After certain activities? Tracking when resistance peaks helps identify triggers you can address.
**Monitor anxiety levels.** Some children develop significant anxiety around toileting. If you see increasing distress, fear, or avoidance, pause and address the emotional component before pushing forward. Forcing through fear creates lasting problems.
**Identify sensory-related emotions.** Your child may not be able to articulate that the flush scares them or the seat feels wrong. Watching their emotional response during different parts of the process reveals sensory issues to address.
**Track progress over time.** Looking back at emotional data over weeks shows patterns that daily experience obscures. You might see that early morning attempts consistently produce anxiety while post-nap attempts are calmer, information that shapes your schedule.
**Connect emotions to activities.** Understanding which parts of the toileting routine trigger negative emotions and which feel manageable helps you focus support where it is needed most.
.png)
## Addressing Common Sensory Challenges
Sensory issues require specific accommodations.
**Sound sensitivity.** If flushing frightens your child, let them leave the bathroom before you flush, or flush after they have washed hands and are moving away. Some children do better with lids closed during flushing to muffle sound.
**Temperature sensitivity.** Padded toilet seats stay warmer than plastic. Running warm water over the seat before use helps. Toilet paper can also feel uncomfortably cold; store it at room temperature rather than in a cold bathroom cabinet.
**Visual sensitivity.** Bright bathroom lights can be harsh. Try dimmer switches, battery-operated stick-on lights for gentler illumination, or simply leaving the door partially open to use hallway lighting.
**Positional discomfort.** The position required for toileting is physically unusual and can feel unstable. A step stool that lets feet rest flat, handles to grip, or a smaller seat opening all increase physical security.
**Wiping challenges.** The sensation of toilet paper and the motor planning required for wiping can both be difficult. Flushable wipes may be more tolerable. Practice wiping motions outside the bathroom to build the skill without time pressure.
## Managing Setbacks and Regressions
Progress is rarely linear. Expect and plan for setbacks.
**Regressions are normal.** A child who was making progress may suddenly refuse the toilet, have frequent accidents, or develop new fears. This is common during stress, illness, or transitions. Do not interpret it as failure.
**Return to basics calmly.** If regression occurs, go back to an earlier stage without shame or frustration. "Let's practice just sitting for now" removes pressure while maintaining routine.
**Look for underlying causes.** New anxiety, schedule changes, illness, sensory changes (new toilet paper brand, different lighting), or life stressors can all trigger regression. Address the root cause when possible.
**Never punish accidents.** Punishment creates shame and anxiety that makes future success harder. Accidents are information, not misbehavior. Clean up neutrally and move on.
**Maintain the routine even during setbacks.** Continue scheduled bathroom trips and the visual routine even when success is not happening. Consistency during difficult periods builds long-term habits.
## Building Flexibility Over Time
Eventually, your child needs to use toilets beyond the familiar home bathroom.
**Introduce variety gradually.** Once home toileting is reliable, practice at one familiar location, perhaps a grandparent's house. Master that before adding another location.
**Prepare for new bathrooms visually.** Before visiting somewhere new, show your child pictures of that bathroom if possible. Describe what will be the same and what will be different from home.
**Create a portable routine.** A small visual schedule that travels with you provides familiar structure in unfamiliar bathrooms. The same steps apply everywhere, even if the environment changes.
**Address public bathroom challenges.** Automatic flushers, hand dryers, and busy environments create additional challenges. Sticky notes covering automatic flush sensors, noise-canceling headphones, and choosing less busy times all help.
**Celebrate flexibility.** When your child successfully uses an unfamiliar toilet, acknowledge the accomplishment. "You used Grandma's bathroom! That takes flexibility."
## When to Seek Professional Help
Some situations benefit from professional guidance.
**Medical issues should be ruled out.** If your child experiences pain during toileting, chronic constipation, or physical symptoms, consult with a pediatrician before assuming the issue is behavioral.
**Persistent anxiety may need support.** If bathroom-related anxiety is severe or increasing despite your efforts, a therapist familiar with neurodivergent children can help.
**Occupational therapy can address sensory and motor issues.** OTs can help with interoception awareness, sensory accommodations, and the motor planning required for toileting.
**Behavioral specialists offer structured approaches.** If your child's team includes a BCBA or behavioral specialist, they can design individualized protocols based on your child's specific needs.
**There is no shame in asking for help.** Potty training a neurodivergent child is genuinely harder than typical toilet training. Professional support is a reasonable and often helpful step.
## Celebrating Success
Toilet training success deserves recognition.
**Acknowledge the real difficulty.** Your child worked hard to master a complex, multi-step process with sensory challenges, executive function demands, and interoception difficulties. This is a significant accomplishment.
**Mark milestones meaningfully.** First successful use, first dry day, first week without accidents, first use of a new bathroom. Each milestone deserves celebration in whatever way is meaningful to your child.
**Build confidence for future challenges.** The skills your child developed, following visual routines, managing sensory challenges, building flexibility, transfer to other areas of life. Point out how capable they have become.
**Share progress with your support team.** Grandparents, teachers, and therapists who have supported the journey deserve to know about success. This also helps ensure consistency across environments.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create visual toilet routines, track bathroom attempts, monitor emotions around toileting, and celebrate success with meaningful rewards. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and support your child's potty training journey with tools designed for neurodivergent families.
---
## Screen Time Management for Neurodivergent Children
Published: 2025-01-26
URL: https://vizyplan.com/blog/screen-time-management-autism-adhd
Category: Daily Routines
Author: Justin Bowman
> Practical strategies for managing screen time with neurodivergent children, including setting boundaries, preventing meltdowns during transitions, and using screens as effective tools.
You said "five more minutes" ten minutes ago. Now the timer has gone off, and your child is screaming, crying, or pretending they cannot hear you. The iPad might as well be welded to their hands. You are caught between knowing screens are the only thing giving you a break right now and worrying you are making everything worse.
Here is what most screen time advice gets wrong: the problem is not screens themselves. For many neurodivergent children, screens provide genuine benefits including regulation, learning, social connection, and joy. The real challenge is managing them in ways that work for your child and your family.
## Why Screen Time Is Uniquely Challenging
Understanding the specific difficulties helps target your approach.
**Hyperfocus makes stopping difficult.** Many neurodivergent children experience hyperfocus, intense concentration that makes awareness of time and external demands nearly impossible. When hyperfocused on a screen, children genuinely do not hear requests to stop or recognize that time is passing.
**Screens provide powerful regulation.** For children with sensory processing differences or anxiety, screens offer predictable, controllable sensory input. The regulation screens provide is real, making it harder to transition away from this calming experience to less predictable activities.
**Transition difficulty is amplified.** If your child struggles with transitions generally, transitioning away from a preferred activity like screens will be especially hard. The screen is not the only issue, it is transitions that are difficult, and screens make the transition even more challenging.
**Dopamine dynamics are intense.** ADHD brains in particular seek dopamine, and screens deliver it efficiently. The neurological draw to screens is stronger for some children than others, making willpower-based approaches ineffective.
**Social interaction is easier online.** For children who struggle with face-to-face social dynamics, online interactions may feel safer and more manageable. Taking away screens can mean taking away their primary social connection.
## Setting Up for Success
Effective screen time management begins with structure.
**Establish clear, consistent rules.** Ambiguity creates conflict. Decide when screens are allowed, for how long, and under what conditions. Write these rules down and post them visibly. When the rules are clear and consistent, arguments decrease.
**Use visual schedules.** Show screen time in the context of the daily schedule. Children can see when screen time is coming and what comes after. Visual representation makes the time limit concrete rather than abstract.
**Create a dedicated screen time space.** Having a specific location for screen use helps establish boundaries. Screens in common areas are easier to monitor and transition away from than screens in bedrooms.
**Charge devices in a central location.** When devices charge outside bedrooms overnight, temptation decreases and sleep improves. Make this a household rule that applies to everyone, including adults.
**Choose content intentionally.** Not all screen time is equal. Educational content, creative apps, and social connection serve different purposes than passive consumption. Be intentional about what fills your child's screen time.
## Preventing Transition Meltdowns
The transition away from screens is often harder than the screen time itself.
**Give multiple warnings.** A single "time's up" does not work. Give warnings at 10 minutes, 5 minutes, and 1 minute before screen time ends. Use visual timers so the warning is visible, not just verbal.
**Make the time limit visible throughout.** A timer running on the screen itself or nearby helps children track remaining time without relying on internal time awareness they may not have.
**End at natural stopping points when possible.** Requiring a child to stop mid-level in a game or mid-episode in a show makes transitions harder. When possible, align the end of screen time with natural breaks in the content.
**Have the next activity ready.** Transitioning from screens to "nothing" is harder than transitioning to something specific. Have the next activity prepared and appealing before screen time ends.
**Use first-then language.** "First we put away the tablet, then we have a snack" makes the transition concrete and provides motivation. The visual first-then format works especially well.
**Acknowledge the difficulty.** Saying "I know it is hard to stop" validates your child's experience without changing the limit. Feeling understood reduces resistance more than dismissing the difficulty.
**Avoid surprise endings.** Never abruptly take a device away. The betrayal of an unexpected ending makes future compliance less likely and damages trust.
## Using Visual Supports for Screen Time
Visual supports work as well for screens as for other routines.
**Create a visual screen time routine.** Show the steps: ask permission, set the timer, use the screen, five-minute warning, put the device away. Having a routine makes each screen session predictable.
**Use visual choice boards for content.** Let children choose from approved options using a visual board. This provides agency while keeping choices within acceptable limits.
**Display the rules visually.** A posted list of screen time rules, when, where, how long, reduces repeated negotiations. Point to the rules instead of re-explaining them each time.
**Track earned screen time visually.** If screen time is earned, use a visual chart to show progress toward earning it and how much has been accumulated. Seeing progress motivates and reduces arguments.
.png)
## Making Screen Time Work as a Tool
Screens can be genuinely helpful when used intentionally.
**Use screens for regulation intentionally.** If your child uses screens to calm down, acknowledge this as a legitimate coping strategy. Build in designated "regulation screen time" separate from entertainment screen time.
**Leverage screens for learning.** Many neurodivergent children learn effectively through digital content. Educational games, videos, and apps can supplement other learning in valuable ways.
**Support social connection online.** For children who struggle with in-person friendships, online gaming communities or video calls with friends provide important social experiences. Value these connections.
**Use screens to prepare for challenges.** Social stories, visual schedules, and preparation videos can all be delivered via screens. Technology can support the very strategies that help your child succeed.
**Distinguish between tool use and consumption.** Purposeful apps designed for specific tasks, like visual schedule apps, routine builders, or communication tools, function differently than entertainment. A few minutes checking a visual schedule or reviewing a social story before an activity is not the same as passive screen consumption. These brief, intentional interactions support your child without contributing to overall screen time concerns.
**Model healthy screen use yourself.** Children notice when adults are constantly on phones. Modeling balanced screen use teaches more than lectures about screen limits.
## Addressing Common Screen Time Challenges
Specific situations require specific strategies.
**When demands trigger meltdowns.** Some children use screens to escape demands. Address the underlying demand avoidance while also providing appropriate breaks. Screens should not be the only escape valve.
**When screens disrupt sleep.** Blue light and stimulating content interfere with sleep. End screen time at least an hour before bed, and use blue light filters in the evening. Keep devices out of bedrooms overnight.
**When nothing else interests your child.** If screens seem to be the only interest, introduce alternatives gradually. Find aspects of screen content that translate to offline activities, if they love Minecraft, try building with blocks.
**When siblings have different needs.** Different children may need different screen rules. Be clear that fairness means everyone getting what they need, not everyone getting the same thing. Explain differences openly.
**When screen time is the only reward that works.** If screens are the primary motivator, use this intentionally rather than fighting it. Screen time can be a powerful earned reward. Just ensure it is not the only positive experience in the day.
## Building Healthy Long-Term Habits
The goal is teaching self-regulation, not lifelong dependence on external limits.
**Gradually increase self-monitoring.** Over time, shift from externally set timers to children setting their own. Practice stopping at natural points. Build the internal skills while keeping external supports available.
**Discuss screen effects openly.** Age-appropriately talk about how screens make your child feel, both the good parts and the difficult parts. Self-awareness supports self-regulation.
**Create screen-free zones and times.** Establish that certain places (dinner table) or times (first hour after school) are consistently screen-free. Predictable boundaries are easier to maintain than constantly negotiated ones.
**Focus on what screens add, not just what they take.** Balance discussions of limits with acknowledgment of what screens contribute. A purely negative view of screens creates conflict; a balanced view enables partnership.
**Adjust as your child grows.** Needs change over time. A rule that worked at age six may not fit at age ten. Revisit screen time agreements regularly and adjust based on current needs and maturity.
## When Screen Time Is Significantly Problematic
Some situations require more intensive intervention.
**Seek support if screens dominate everything.** If your child cannot engage in any activity without screens, refuses all alternatives, or has severe meltdowns despite consistent strategies, consult with professionals who understand both technology and neurodevelopment.
**Consider underlying needs.** Extreme screen reliance often signals unmet needs, for regulation, escape from demands, social connection, or control. Addressing underlying needs reduces screen dependency more effectively than simply limiting access.
**Rule out addiction carefully.** While true screen addiction exists, many behaviors that look like addiction are actually intense interest, difficulty with transitions, or regulation-seeking. Accurate understanding leads to effective intervention.
**Get professional guidance when needed.** Occupational therapists, psychologists, and other providers can help develop individualized screen time plans that account for your child's specific profile and needs.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create visual screen time routines and transition supports that reduce daily battles. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring more peace to your family's relationship with technology.
---
## Preparing Your Neurodivergent Child for Holidays and Special Events
Published: 2025-01-25
URL: https://vizyplan.com/blog/holiday-special-events-autism-adhd
Category: Strategies
Author: Justin Bowman
> Practical strategies to help neurodivergent children navigate holidays, birthdays, and special events with less stress and more enjoyment for the whole family.
Holidays and special events are supposed to be joyful occasions. But for families with neurodivergent children, these celebrations often bring overwhelming sensory experiences, disrupted routines, social demands, and unexpected changes that lead to meltdowns instead of memories.
The good news is that with thoughtful preparation, holidays and special events can become more manageable, and even enjoyable. Understanding why these occasions are difficult and implementing targeted strategies makes all the difference.
## Why Holidays and Special Events Are Challenging
Before diving into strategies, it helps to understand the specific difficulties these events present.
**Routine disruption is significant.** Holidays often mean different wake times, different meal schedules, different activities, and different people in the home. For children who depend on predictability, this wholesale change to normal life creates anxiety that manifests as challenging behavior.
**Sensory environments intensify.** Holiday gatherings assault multiple senses simultaneously. Flashing lights on decorations, loud music, strong food smells, crowded spaces with overlapping conversations, and unfamiliar textures in special clothing combine to overwhelm sensory systems quickly.
**Social expectations increase.** Special events often require greeting relatives, making conversation, accepting gifts gracefully, participating in group activities, and tolerating physical affection from people seen rarely. These social demands exhaust children who struggle with social interaction.
**Anticipation builds anxiety.** The buildup to holidays can be as difficult as the events themselves. Weeks of hearing about what is coming, seeing decorations appear, and feeling others' excitement creates mounting pressure that some children cannot manage.
**Flexibility demands are high.** Plans change during special events. The party runs late. A family member cancels. The restaurant is closed. The gift was not what was expected. Each change requires adaptation that depletes limited coping resources.
## Preparing Weeks in Advance
Successful special events begin with early preparation.
**Create visual calendars.** Mark the event on a calendar your child can see daily. Count down the days together. Knowing when the event will happen, and seeing normal days between now and then, provides a sense of control.
**Build social stories about the event.** Write or create visual stories that walk through what will happen. Include who will be there, what activities will occur, what foods might be served, and what your child can do if they feel overwhelmed. Review these stories repeatedly before the event.
**Preview the environment.** If possible, visit the location beforehand when it is quiet. If the event is at a relative's house, show photos of their home and the people who will be there. Familiarity reduces anxiety about the unknown.
**Practice specific skills.** If the event requires particular behaviors, saying thank you for gifts, shaking hands with relatives, sitting through a long meal, practice these specific skills before the event. Role-play challenging scenarios.
**Prepare for sensory experiences.** If you know decorations will be bright, practice being around bright lights. If the food will be unfamiliar, introduce similar foods at home first. Gradual exposure to expected sensory elements reduces their impact.
**Discuss what will be different.** Be explicit about how this day will differ from normal days. Meals will be at different times. There will be more people. The schedule will be different. Naming these changes helps children prepare mentally.
## Managing the Day of the Event
The day itself requires careful management and realistic expectations.
**Maintain morning routines when possible.** Even on special event days, keep morning routines as normal as possible. A predictable start to the day provides stability before the disruption begins.
**Use visual schedules throughout.** Create a visual schedule for the event day. Show what will happen and in what order. Update it as plans change. Having a visual anchor helps children understand where they are in the sequence.
**Arrive prepared with sensory supports.** Bring noise-canceling headphones, fidget toys, sunglasses, and other sensory tools your child uses. Having these available prevents reaching the breaking point without options.
**Identify a quiet space.** Before the event begins, identify where your child can go to decompress. A bedroom, a quiet corner, or even the car can serve as a retreat when overwhelm builds. Make sure your child knows where this space is and that using it is acceptable.
**Build in breaks proactively.** Do not wait for signs of overwhelm. Schedule regular breaks into the event. A five-minute walk outside every half hour prevents escalation better than trying to recover after a meltdown has begun.
**Bring familiar foods.** If your child has food restrictions or preferences, bring safe foods to the event. Having something they can eat prevents food-related stress and ensures they stay fueled.
**Set realistic expectations.** Your child may not be able to participate in everything. They may need to leave early. They may need accommodations others do not understand. Setting expectations internally helps you respond calmly when adjustments are needed.
## Navigating Social Demands
Social expectations during special events require particular attention.
**Prep relatives in advance.** Tell family members what to expect and what helps. Explain that your child may not make eye contact, may not want hugs, or may need to take breaks. Most people want to help, they just need to know how.
**Create scripts for common interactions.** Practice specific phrases your child can use. "Thank you for coming." "I need a break." "Nice to see you." Having rehearsed responses reduces the cognitive load of social interaction.
**Allow alternative greetings.** If hugs are overwhelming, offer alternatives. A high five, a wave, or a simple hello can replace physical affection. Giving your child control over their body during social interactions reduces stress.
**Prepare for gift-giving situations.** Practice appropriate responses to receiving gifts, even disappointing ones. Role-play scenarios: "What do you say when you get a gift?" "What if it is not what you wanted?" Having these scripts ready prevents awkward moments.
**Have an exit strategy.** Know how you will leave if needed. Have a code word or signal your child can use to communicate they need to go. Knowing escape is possible often makes staying easier.
.png)
## Managing Sensory Overload
Sensory challenges require proactive strategies.
**Layer clothing strategically.** Dress your child in comfortable base layers under event-appropriate clothing. If the special outfit becomes unbearable, they can remove a layer while still being dressed appropriately.
**Control exposure to decorations.** If blinking lights or loud music are problematic, position your child away from these stimuli. Sit in quieter corners. Face away from flashing decorations. Small positioning changes reduce sensory input significantly.
**Provide sensory input your child seeks.** If your child needs movement, build in physical activity. If they need oral input, bring chewy snacks. If deep pressure helps, consider a compression shirt under their outfit. Meeting sensory needs proactively prevents seeking them inappropriately.
**Watch for early warning signs.** Learn your child's signals that sensory overload is building. Increased movement, covering ears, becoming very quiet, or getting silly can indicate overwhelm before meltdown. Respond to early signs before crisis hits.
**Remove from stimulation when needed.** When you see signs of overload, move to the quiet space without waiting. A short break to regulate often allows return to the event. Pushing through typically ends worse than a preventive break.
## Handling Gift-Giving Occasions
Birthdays and holidays with gifts present unique challenges.
**Prepare for anticipation.** The excitement of waiting for gifts can be as difficult as opening them. Use visual timers or clear schedules so children know when gift time will happen and what comes before it.
**Consider opening gifts privately.** Some children do better opening gifts without an audience. Opening presents in a quiet space first, then showing them to relatives, removes performance pressure from an already overwhelming experience.
**Practice disappointment tolerance.** Not every gift will be wanted. Practice phrases like "Thank you, this is nice" even when it is not. Discuss privately afterward if a gift was unwanted, rather than expressing disappointment publicly.
**Manage overstimulation from gifts.** Multiple new items at once can overwhelm. Consider spacing out gift opening. Put some gifts away to explore later. Rotating through new items over days prevents the chaos of everything at once.
**Prep relatives about gift preferences.** If there are specific items your child cannot tolerate, certain textures, loud toys, things requiring assembly, let gift-givers know in advance. Providing a wish list with specific items prevents well-meaning but problematic gifts.
## After the Event
Recovery after special events matters as much as preparation.
**Expect recovery time.** Plan for a quiet day after significant events. Neurodivergent children often need time to process and recover from overstimulating experiences. Do not schedule additional activities immediately following.
**Return to routines immediately.** Get back to normal schedules as quickly as possible. Familiar routines help children regulate after the disruption of special events. The sooner normalcy returns, the faster recovery happens.
**Process the experience together.** Talk about or review photos from the event. Discuss what was fun and what was hard. This processing helps children make sense of their experience and builds learning for future events.
**Note what worked.** After each special event, record what strategies helped and what to try differently next time. This information makes future events more successful. Patterns emerge over time that inform better preparation.
**Celebrate successes.** Acknowledge what your child managed, even if the event was not perfect. Attending for an hour is success. Saying thank you once is success. Each managed challenge builds confidence for future events.
## Building Toward Better Events Over Time
Each special occasion teaches something.
**Start with shorter events.** If large gatherings are new or have been difficult, begin with brief attendance. Arriving late, leaving early, or attending for a short time builds tolerance gradually.
**Increase complexity slowly.** Master smaller gatherings before attempting larger ones. Success at a quiet birthday dinner prepares for a bigger party next time.
**Adjust family expectations.** Your family's holiday celebrations may look different from others'. Smaller gatherings, quieter environments, and more accommodations are not failures, they are smart adaptations that allow participation.
**Involve your child in planning.** As children grow, include them in decisions about events. What parts do they want to participate in? What do they need to feel comfortable? Building agency improves outcomes.
**Keep trying.** Difficult events do not mean you should avoid all celebrations. Each experience, even challenging ones, builds skills and understanding. Special occasions can become more manageable with practice and preparation.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create visual schedules and social stories that prepare your child for holidays and special events. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and make your next celebration more successful for the whole family.
---
## Travel and Vacation Tips for Neurodivergent Families
Published: 2025-01-24
URL: https://vizyplan.com/blog/travel-vacation-tips-autism-adhd
Category: Strategies
Author: Justin Bowman
> Practical strategies for successful family travel with neurodivergent children, from preparation weeks before departure to managing unexpected changes on the road.
Family vacations should create joyful memories. But for families with neurodivergent children, travel often brings anxiety, meltdowns, and exhaustion instead of relaxation. The disruption to routines, unpredictable environments, and sensory overload can make even a simple weekend trip feel overwhelming.
With the right preparation and supports, travel can become manageable, even enjoyable. The key is understanding why travel is difficult for neurodivergent children and implementing strategies that address those specific challenges.
## Why Travel Is Challenging
Understanding the difficulties helps you prepare more effectively.
**Routine disruption is significant.** Many neurodivergent children rely heavily on predictable daily routines to feel safe. Travel eliminates nearly every familiar anchor, different beds, different mealtimes, different everything. This loss of predictability creates anxiety that manifests as behavioral challenges.
**Sensory environments are unpredictable.** Airports, hotels, beaches, and tourist attractions assault multiple senses simultaneously. Crowds, noise, unfamiliar smells, and temperature changes combine to overwhelm sensory systems already working hard to process a new environment.
**Transition demands increase dramatically.** A typical travel day involves dozens of transitions, getting into the car, getting out, entering new buildings, changing activities. Each transition requires cognitive effort that depletes limited resources.
**Sleep disruption compounds everything.** Different beds, different sounds, different light levels, and different time zones all interfere with sleep. Sleep deprivation worsens every other challenge.
**Flexibility demands are high.** Travel rarely goes exactly as planned. Delayed flights, closed attractions, and changed reservations require the kind of flexibility that is genuinely difficult for many neurodivergent children.
## Preparation Weeks Before Travel
Successful trips begin long before departure day.
**Start talking about the trip early.** Give your child time to process what is coming. For some children, this means weeks of gradual exposure to the idea. For others who perseverate on upcoming events, shorter notice works better. Know your child.
**Create a visual trip preview.** Assemble photos of where you will go, the hotel room, the airport, the beach or theme park. Looking at images repeatedly builds familiarity before arrival. Search online for photos or videos of your specific destination.
**Build a travel countdown.** Visual calendars showing days until departure help children understand when change is coming. Crossing off days provides a sense of control over the approaching disruption.
**Practice new experiences when possible.** If your child has never flown, visit the airport beforehand just to walk through. If you are staying at a hotel, practice the concept, explain that it is like a bedroom away from home. Some families do practice "hotel nights" at home with sleeping bags.
**Write social stories about travel.** Stories that walk through what will happen, checking in at the airport, finding seats on the plane, arriving at the hotel, reduce uncertainty. Include potential challenges: "Sometimes planes are delayed. We might need to wait. That is okay."
**Involve your child in planning.** When children have input into the itinerary, they feel more control. Let them choose one activity or meal. Show them the hotel and ask which bed they want. Small choices build investment in the trip.
## Packing Strategically
What you bring significantly affects trip success.
**Pack comfort items.** Whatever helps your child regulate at home should come on the trip. Favorite stuffed animals, weighted blankets, noise-canceling headphones, fidgets, these familiar items provide sensory anchors in unfamiliar environments.
**Bring familiar foods.** If your child has food restrictions or preferences, pack reliable options. Having safe foods available prevents meltdowns when restaurant options are unacceptable.
**Prepare a sensory toolkit.** Include items for various sensory needs: chewy snacks for oral input, fidget toys for hands, sunglasses for visual sensitivity, and earplugs or headphones for sound. A small backpack of these items should be accessible at all times.
**Pack entertainment strategically.** Long travel days require activities. Download shows and games to tablets before departure. Bring books, coloring supplies, and small toys. Having options prevents boredom-driven escalation.
**Create visual supports for the trip.** Pack printed visual schedules, first-then boards, or have them ready on a phone or tablet. You will use these throughout the trip to communicate what is happening.
## Managing Travel Days
The journey itself requires careful management.
**Build in extra time.** Rushing escalates everyone's stress. Arrive at airports early. Leave buffer time between activities. The pace of travel should feel slower than you think necessary.
**Use visual schedules throughout.** Before each transition, show your child what is happening next. "First we go through security, then we find our gate." Visual supports work just as well at airports as they do at home.
**Plan for sensory breaks.** Identify quiet spaces at airports for decompression. During road trips, stop regularly even if your child does not ask. Sensory overload builds gradually and prevention is easier than recovery.
**Bring familiar bedtime supports.** Recreating sleep routines in new environments helps. If your child uses a white noise machine, bring it. If they have a specific bedtime sequence, maintain it as closely as possible. Sleep supports travel success more than any other single factor.
**Prepare for waits.** Travel involves waiting, for planes, for food, in lines. Have activities ready. Set visual timers when possible so children understand how long waits will last. Waiting without knowing when the wait ends is much harder than waiting with a visible endpoint.
.png)
## Navigating the Destination
Once you arrive, different challenges emerge.
**Keep some routines intact.** Even on vacation, maintaining meal times and bedtimes provides stability. If your child normally eats lunch at noon, try to keep that consistent. If bedtime is 8pm, shifting it by hours will backfire.
**Build in downtime.** Do not schedule every moment. Neurodivergent children need recovery time after stimulating activities. A morning at a busy theme park might require a quiet afternoon at the hotel pool or in the room.
**Create a home base.** Whether it is a hotel room or vacation rental, make one space feel safe and familiar. Unpack some comfort items. Establish where things go. Having a retreat space for when overwhelm hits is essential.
**Prepare for each activity.** Before going somewhere new, review what will happen using photos or social stories. "We are going to the aquarium. It will be dark inside. There will be fish behind glass. Some children might be loud." Preparing for specific sensory elements helps.
**Have an exit plan.** Know that you might need to leave activities early. Identify quiet spaces at each location. Have the car accessible for breaks. Giving yourself permission to leave reduces pressure and paradoxically often means you can stay longer.
## Managing the Unexpected
Travel plans change. How you handle changes matters.
**Model flexibility yourself.** Children learn from watching adults. If a restaurant is closed, demonstrate calm problem-solving out loud: "That is disappointing. Let us find another place to eat. I see one across the street."
**Use visual supports to explain changes.** Crossing out items on a visual schedule and adding new ones helps children see that plans can change while maintaining some structure.
**Validate frustration.** When plans change, acknowledge that it is hard. "You were expecting the pool to be open. It is closed for cleaning. That is frustrating." Validation does not mean the situation changes, but it helps children feel understood.
**Have backup plans ready.** For key activities, know alternatives. If the beach is too crowded, have another option. If the restaurant wait is too long, know where else to eat. Prepared parents stay calmer, which helps children stay calmer.
## Returning Home
The transition back home is often underestimated.
**Expect reentry difficulty.** Many children struggle more coming home than leaving. The return to routine after disruption requires adjustment time. Plan for a quiet day before returning to school or normal activities.
**Rebuild routines immediately.** Get back to normal mealtimes and bedtimes as quickly as possible. Familiar routines help children regulate after the stimulation of travel.
**Process the trip together.** Looking at photos, talking about favorite moments, and reviewing what happened helps children make sense of the experience. This processing can happen over days or weeks.
**Note what worked and what did not.** After each trip, record what strategies helped and what to change next time. This information makes future travel easier.
## Building Travel Confidence Over Time
Each trip teaches you something.
**Start small.** If travel is new or has been difficult, begin with short trips close to home. A one-night stay at a nearby hotel builds skills for longer adventures later.
**Celebrate successes.** When your child manages something difficult, waiting patiently, trying a new food, sleeping in a hotel bed, acknowledge the achievement. Building positive associations with travel makes future trips easier.
**Adjust expectations.** A successful family vacation with a neurodivergent child might look different from other families' trips. Fewer activities, more downtime, earlier departures, these adaptations are not failures but smart strategies.
**Keep trying.** Difficult trips do not mean you should never travel again. Each experience, even challenging ones, builds skills and understanding. Travel can become easier with practice and preparation.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create visual travel schedules and social stories that prepare your child for new adventures. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and make your next family trip more successful.
---
## Mealtime Strategies for Neurodivergent Children
Published: 2025-01-23
URL: https://vizyplan.com/blog/mealtime-strategies-picky-eating-autism-adhd
Category: Daily Routines
Author: Justin Bowman
> Practical strategies to reduce mealtime stress and support neurodivergent children who struggle with food textures, routines, and sensory sensitivities.
Mealtime can be one of the most stressful parts of the day for families with neurodivergent children. Between sensory sensitivities, rigid food preferences, difficulty sitting still, and the social demands of eating together, what should be nourishing family time often becomes a daily battle.
Understanding why mealtimes are challenging, and implementing targeted strategies, can transform this experience for everyone at the table.
## Why Mealtimes Are Difficult
Before implementing strategies, it helps to understand the specific challenges neurodivergent children face around food and eating.
**Sensory processing differences** affect how children experience food. Textures that seem normal to others may feel unbearable. Temperatures, smells, and even the appearance of food can trigger intense negative reactions that are not within the child's control.
**Need for sameness and predictability** leads many autistic children to prefer eating the same foods repeatedly. New foods represent unpredictability, which triggers anxiety.
**Executive function challenges** make the multi-step process of eating difficult. Sitting down, using utensils, pacing bites, and staying at the table all require executive function skills that may be limited.
**Interoception difficulties** mean some children struggle to recognize hunger and fullness cues. They may not feel hungry at mealtimes or may not recognize when they have eaten enough.
**Motor planning challenges** can make using utensils frustrating, adding another layer of difficulty to an already demanding activity.
## Creating a Sensory-Friendly Eating Environment
The environment where meals happen significantly impacts success.
**Reduce visual clutter** at the table. A calm, organized eating space is easier to manage than a chaotic one with distractions competing for attention.
**Consider lighting carefully.** Bright overhead lights can be overwhelming. Softer, natural lighting often supports calmer mealtimes.
**Manage noise levels.** Background noise from TVs, loud conversations, or kitchen appliances may make focusing on eating difficult. Some children do better with quiet mealtimes; others benefit from soft background music.
**Offer appropriate seating.** Some children need foot support to feel stable. Others benefit from wobble cushions or being able to stand at the table. The right seating reduces the physical effort required to participate.
**Use preferred dishware.** Plate colors, textures, and even the sound utensils make against dishes can affect the eating experience. Finding what works for your child removes unnecessary barriers.
## Visual Supports for Mealtime Routines
Visual supports bring the same benefits to mealtimes that they bring to other routines.
**Visual meal schedules** show what will happen during the meal. Seeing the sequence, sit down, napkin on lap, eat meal, ask to be excused, provides predictability that reduces anxiety.
**Visual timers** help children understand how long they need to stay at the table. Open-ended mealtimes feel overwhelming; knowing there is an end point makes participation more manageable.
**Choice boards for food selection** give children agency while keeping options within acceptable boundaries. Offering three acceptable choices rather than asking "What do you want?" prevents overwhelming open-ended decisions.
**First-Then boards** work well for mealtimes. First we try two bites of vegetables, then we can have preferred food. The visual makes the expectation and reward clear.
## Addressing Sensory Food Challenges
Sensory issues with food require patience and gradual approaches.
**Respect genuine sensory aversions.** A child who gags on certain textures is not being defiant. Their sensory system is genuinely overwhelmed. Forcing foods that trigger this response creates negative associations and makes progress harder.
**Introduce new foods gradually.** The goal is not eating the new food immediately but building tolerance. Start by having the food on the table, then on the plate, then touched, then tasted, without pressure to swallow.
**Consider food properties systematically.** Is it the texture, temperature, color, smell, or taste that bothers your child? Understanding the specific issue helps find acceptable alternatives.
**Serve safe foods alongside new ones.** Having at least one accepted food at every meal ensures nutrition while reducing the pressure around new foods.
**Separate foods on the plate.** Many children become distressed when foods touch. Using divided plates or serving foods separately removes this trigger.
## Managing the ADHD Mealtime Challenge
ADHD presents its own set of mealtime difficulties.
**Movement needs do not stop at mealtime.** Expecting a child who needs to move to sit completely still during meals sets everyone up for frustration. Consider allowing standing, using a wobble cushion, or taking brief movement breaks during longer meals.
**Attention wanders from eating.** Children with ADHD may get distracted and forget to eat, leading to meals that drag on indefinitely. Visual timers and clear expectations help maintain focus.
**Impulsivity affects eating pace.** Some children eat too quickly, barely chewing before swallowing more. Others get distracted between bites and take forever to finish. Visual pacing supports can help regulate eating speed.
**Medication may affect appetite.** Many ADHD medications suppress appetite during peak effectiveness. Working with your doctor to time meals around medication schedules helps ensure adequate nutrition.
.png)
## Building Positive Mealtime Associations
Long-term success requires making mealtimes feel positive rather than stressful.
**Reduce pressure around eating.** High-pressure mealtimes increase anxiety and decrease willingness to try foods. A relaxed approach, paradoxically, often leads to better eating over time.
**Connect mealtimes with positive experiences.** Family conversation, sharing highlights of the day, or other positive rituals build good associations with being at the table.
**Praise participation, not just eating.** Acknowledge sitting at the table, trying a smell of new food, or using utensils well. Celebrating these steps builds confidence.
**Avoid making food a battleground.** The more meals become power struggles, the more negative associations build. Choose your battles carefully and let some things go.
## When to Seek Professional Help
Some mealtime challenges require professional support.
**Feeding therapy** with an occupational therapist or speech-language pathologist can address significant sensory aversions, oral motor difficulties, or severe food restrictions.
**Medical evaluation** is important if a child's diet is extremely limited, if they are not growing appropriately, or if there are signs of nutritional deficiency.
**Mental health support** may help if anxiety around food is severe or if there are signs of developing disordered eating patterns.
## Practical Tips for Everyday Meals
Small adjustments make daily meals more manageable.
**Prep preferred foods in advance.** Having acceptable options ready reduces stress when you are also managing meal preparation.
**Maintain consistent meal times.** Predictable schedules help children anticipate and prepare for mealtimes.
**Keep portions small.** Large portions can be overwhelming. Starting with small amounts and allowing seconds feels more manageable.
**Model rather than lecture.** Children learn more from watching others eat varied foods calmly than from being told to eat their vegetables.
**Accept that some days are harder.** Progress is not linear. A child who tried something new yesterday may refuse it today. This is normal.
## Building Long-Term Healthy Relationships with Food
The goal is not just getting through today's meal but building lifelong healthy eating patterns.
**Expand the repertoire gradually.** Over months and years, most children with support can expand their accepted foods significantly.
**Involve children in food preparation.** Children who help prepare food are often more willing to try it. Even small tasks like washing vegetables or stirring create investment.
**Teach about nutrition without pressure.** Understanding why varied foods matter can motivate older children without the pressure of being forced to eat.
**Celebrate progress.** When your child tries something new or sits through a meal calmly, recognize the achievement. These moments build toward lasting change.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create visual mealtime routines that reduce stress and build positive eating habits. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring calm to your family's mealtimes.
---
## Why Tracking Emotions to Activities Changes Everything
Published: 2025-01-22
URL: https://vizyplan.com/blog/tracking-emotions-activities-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Discover how connecting your child's emotions to specific activities reveals patterns that transform meltdowns into manageable moments.
What if you could predict when your child might struggle, before the meltdown happens? For parents of neurodivergent children, understanding the connection between emotions and activities is one of the most powerful tools available. When you track how your child feels during specific parts of their day, patterns emerge that can change everything.
## The Missing Link: Emotions and Activities
Most parents track behaviors. They note meltdowns, difficult moments, and challenging transitions. But behavior is the end result, what happened before the behavior is where the real insights hide.
**Emotions during activities tell a different story.** When you know that your child consistently feels worried during homework time, or sad after dinner, you gain actionable information. The behavior (resistance, meltdown, withdrawal) suddenly has context.
**Patterns become visible over time.** A single data point means little. But when you track emotions across days and weeks, you start to see which activities reliably trigger stress and which ones support regulation.
**Interventions become targeted.** Instead of general strategies, you can address specific activity-emotion connections with precision.
## What Emotion Tracking Reveals
When families begin tracking emotions connected to activities, they often discover surprising patterns.
**Time-of-day effects become clear.** Many children show different emotional patterns in morning versus evening activities. A child who handles morning routines well might consistently struggle with the same tasks at night when tired.
**Specific activities emerge as triggers.** You might discover that it is not "transitions" generally that are hard, but specifically the transition from screen time to dinner. This precision allows for targeted support.
**Positive patterns also appear.** Tracking is not just about problems. You will also see which activities consistently support positive emotions, information that helps you build more of these moments into the day.
**Weekly rhythms become visible.** Some children have predictable patterns across the week. Monday mornings might be harder than other days. Fridays might bring more anxiety about weekend schedule changes.
## How to Track Emotions to Activities
Effective emotion tracking does not require complex systems. Simple, consistent approaches work best.
**Keep it simple.** Track just a few basic emotions: happy, calm, worried, sad, excited. More nuanced tracking can come later once the habit is established.
**Connect to specific activities.** Rather than logging emotions at random times, connect them to defined activities in your child's routine: waking up, eating breakfast, getting dressed, leaving for school, homework time, dinner, bedtime.
**Make it visual.** For many neurodivergent children, selecting an emoji or pointing to a feeling face is easier than verbal reporting. Visual emotion check-ins during or after activities provide more reliable data.
**Track consistently.** Daily tracking over several weeks reveals patterns that occasional logging misses. Build emotion check-ins into your existing routines.
**Involve your child when possible.** Children who participate in tracking their own emotions develop greater self-awareness. Even young children can point to how they feel during different activities.
## Understanding the Data
Once you have collected emotion data, interpretation becomes the key skill.
**Look for frequency patterns.** If your child reports feeling worried four out of five homework sessions but happy during most other activities, homework is a clear target for intervention.
**Notice intensity alongside frequency.** An activity that occasionally produces mild worry is different from one that consistently triggers intense distress.
**Compare across time periods.** Are mornings consistently harder than afternoons? Are weekdays different from weekends? These patterns inform scheduling decisions.
**Watch for changes.** When you implement a new support or strategy, tracking shows whether emotions around that activity improve.
## Acting on What You Learn
Data without action is just information. The value of emotion tracking comes from using insights to make changes.
**Modify challenging activities.** If getting dressed consistently triggers worry, consider what about the activity is difficult. Is it the clothing choices? The time pressure? The transition from another activity? Target your intervention to the specific challenge.
**Add support before difficult moments.** When you know an activity typically brings stress, you can proactively add regulation supports before the activity begins, not after distress is already escalating.
**Build on positive activities.** If certain activities consistently support positive emotions, look for ways to extend or replicate these moments. What makes them work? Can elements be added to more challenging activities?
**Adjust timing.** Sometimes the issue is not the activity itself but when it happens. Homework immediately after school might fail while homework after a movement break might succeed. Emotion data helps you experiment systematically.
**Communicate with providers.** Emotion-activity data is powerful information to share with therapists, teachers, and other providers. It helps them understand your child's experience and target their support effectively.
.png)
## The Role of Self-Awareness
Tracking emotions builds self-awareness in children over time.
**Recognition develops.** Children who regularly check in about their emotions become better at recognizing their internal states, even when not prompted.
**Language grows.** The vocabulary of emotions expands as children practice identifying and naming how they feel.
**Anticipation becomes possible.** Children who understand their patterns can eventually anticipate challenging moments and ask for support proactively.
**Self-advocacy emerges.** A child who knows they struggle with a particular activity can learn to communicate this and request accommodations.
## Common Patterns Parents Discover
Certain patterns appear frequently when families track emotions to activities.
**Transition stress.** Many neurodivergent children show negative emotions around transitions between activities, regardless of what the activities are.
**End-of-day depletion.** Emotions often deteriorate as the day progresses, with evening routines showing more distress than morning ones, even for identical tasks.
**Post-school crash.** Children who mask at school often show challenging emotions during the first activities after returning home, even preferred ones.
**Anticipatory anxiety.** Some children show stress during activities that come just before known challenges, worry during dinner because bedtime comes next.
**Hunger and fatigue effects.** Activities that happen when children are hungry or tired consistently show poorer emotional outcomes than the same activities when needs are met.
## Technology Makes It Easier
While emotion tracking can be done with paper and pencil, digital tools offer significant advantages.
**Automatic pattern detection.** Apps can analyze your data and surface patterns you might miss.
**Visual reports.** Seeing emotion frequency as charts and graphs makes patterns obvious at a glance.
**Historical comparison.** Digital tracking allows you to compare current patterns to previous weeks or months, showing progress over time.
**Easy sharing.** Digital reports can be shared with providers, creating a common understanding of your child's experience.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s new Emotion Insights feature lets you track how your child feels during specific activities, see patterns across days and weeks, and filter by individual activities to understand exactly where support is needed most.
## Starting Your Tracking Journey
Begin with small, manageable steps.
**Choose three to five activities.** Do not try to track everything. Start with a few key activities where you want to understand emotions better.
**Pick a simple emotion set.** Happy, calm, worried, sad, and excited cover most experiences without overwhelming anyone.
**Commit to two weeks.** Give yourself enough time to see patterns before drawing conclusions.
**Review data weekly.** Set a specific time to look at what the data shows and consider what adjustments might help.
**Celebrate insights.** Every pattern you discover is useful information, even when it reveals challenges. Understanding is the first step to improvement.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s Emotion Insights helps you track your child's feelings across activities and discover patterns that inform better support. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and turn emotion data into actionable insights.
---
## Staying Regulated During Transitions: A Guide for Parents
Published: 2025-01-21 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/staying-regulated-during-transitions
Category: Strategies
Author: Justin Bowman
> Discover how to help your child maintain emotional regulation during transitions and what to do when dysregulation happens between activities.
"Time to turn off the TV." Instant tears. "We need to leave the playground." Full meltdown. "Dinner is ready, come to the table." They act like you just asked them to climb Everest. Every single transition, all day long, feels like you are dragging your child through an invisible wall of resistance.
It is not stubbornness. It is not defiance. For neurodivergent children, every transition requires their brain to disengage from one thing, process that it is ending, and prepare for something entirely new. That mental shifting demands enormous cognitive and emotional effort, and when it goes wrong, the nervous system responds with fight, flight, or freeze.
## The Transition-Regulation Connection
When children struggle with transitions, we often focus on the behavioral symptoms, resistance, meltdowns, refusal to move. But beneath these behaviors lies a nervous system that is working overtime to process change.
**Transitions demand cognitive flexibility.** The brain must disengage from one activity, process that something is ending, and prepare for something new. For children with autism or ADHD, this mental shifting requires significant effort and can trigger a stress response.
**Uncertainty activates the nervous system.** Even when children know what comes next, the act of changing states feels unpredictable to their bodies. This uncertainty can push a regulated child into dysregulation within moments.
**Sensory shifts compound the challenge.** Moving from a quiet activity to a loud environment, or from movement to stillness, requires the sensory system to recalibrate quickly, something many neurodivergent children find difficult.
## Proactive Regulation Before Transitions
The best strategy for staying regulated during transitions is to enter them from a regulated state. Building regulation opportunities into the moments before transitions makes a significant difference.
**Check in before announcing changes.** Before telling your child it is time to transition, observe their current state. Are they calm and engaged, or already showing signs of stress? A child who is already dysregulated will struggle more with any transition.
**Use calming activities as bridges.** Before difficult transitions, incorporate a brief regulating activity. This might be deep breathing, a quick movement break, or a moment of deep pressure through a firm hug.
**Provide sensory input proactively.** If your child seeks proprioceptive input, have them do a heavy work task before the transition, carrying something, pushing against a wall, or doing jumping jacks. This input helps organize the nervous system for the change ahead.
**Lower demands before high-stress transitions.** If you know a particular transition is challenging, reduce other demands in the minutes leading up to it. A child who has just finished a frustrating task will have fewer resources for the transition.
## Visual Supports That Promote Regulation
Visual supports do more than communicate what happens next, they provide the predictability that keeps nervous systems calm.
**Include regulation cues in visual schedules.** Your visual schedule can show not just the next activity, but also what regulation strategy to use before moving. A picture of deep breaths between activities normalizes regulation as part of the routine.
**Use emotion check-ins during transitions.** A simple visual emotion scale can help children identify their state before, during, and after transitions. This builds awareness and gives you information about what support they need.
**Show the regulation space on the schedule.** If your child has a calm-down corner or regulation tools, include these as options within the transition routine. Seeing that regulation support is available can itself be calming.
**Create visual countdown systems.** Visual timers and countdown boards show that the transition is approaching gradually rather than appearing suddenly. Watching time pass helps children mentally prepare, keeping their nervous systems more settled.
## When Dysregulation Happens During Transitions
Even with excellent preparation, dysregulation will sometimes occur during transitions. Having a plan for these moments helps everyone.
**Pause and co-regulate first.** When a child becomes dysregulated during a transition, stop and focus on regulation before anything else. The transition can wait. Getting to the next activity while dysregulated will only make things harder.
**Reduce sensory input immediately.** Lower your voice, reduce visual clutter if possible, and give physical space. A dysregulated nervous system is overwhelmed, adding more input makes it worse.
**Offer rather than demand regulation tools.** Instead of saying "You need to calm down," try offering: "Would you like your squeeze ball?" or "Let's take some breaths together." Demands increase stress; offers provide support.
**Use minimal language.** When a child is dysregulated, processing verbal information becomes harder. Use short phrases, visual cues, or gestures instead of explanations or reasoning.
**Allow recovery time before proceeding.** After the intense moment passes, give additional time before completing the transition. Rushing a child who has just been dysregulated often triggers another episode.
## Building Regulation Into Transition Routines
Rather than treating regulation as something to do only when problems arise, build it directly into your transition routines.
**Create a transition ritual that includes regulation.** Every transition could follow the same pattern: warning, regulation activity, movement to the next activity. When regulation is part of the routine, children begin doing it automatically.
**Use movement as the transition.** Instead of asking children to simply stop and start, incorporate movement into the change itself. Walking to the next activity while doing arm movements, or hopping between rooms, channels transition energy productively.
**Include choice within regulation.** "It's almost time to transition. Do you want to do five jumps or squeeze your hands?" Offering choice gives children control while ensuring regulation happens.
**Practice transitions when calm.** During relaxed moments, practice the physical act of transitioning between activities while using regulation strategies. This builds muscle memory for difficult moments.
.png)
## Recognizing Early Signs of Dysregulation
Catching dysregulation early, before it escalates, allows for faster recovery and smoother transitions.
**Watch for changes in movement.** Increased fidgeting, pacing, or sudden stillness can signal that a child's nervous system is becoming overwhelmed. These physical signs often appear before behavioral changes.
**Notice changes in tone or volume.** A child whose voice gets louder, faster, or higher is showing signs of activation. Similarly, a child who becomes very quiet may be shutting down.
**Pay attention to sensory seeking or avoiding.** A child who suddenly covers their ears, squints, or moves away from sensory input is signaling overwhelm. A child who increases stimming or sensory-seeking behaviors is trying to regulate.
**Track patterns over time.** Many children show consistent early warning signs. Learning your child's specific signals helps you intervene earlier.
## Environmental Modifications That Support Regulation
The physical environment plays a significant role in whether children can maintain regulation during transitions.
**Create clear transition pathways.** When the physical path from one activity to another is cluttered or confusing, it adds cognitive load that depletes regulation resources. Clear, consistent pathways support smoother transitions.
**Reduce sensory intensity at transition points.** If transitions happen in spaces with bright lights, loud sounds, or visual clutter, children enter them already somewhat activated. Calmer transition spaces support calmer transitions.
**Make regulation tools accessible.** Fidgets, weighted items, or comfort objects should be easily available during transitions, not stored away where children cannot access them when needed.
**Design spaces with regulation in mind.** Having a quiet corner near common transition points gives children a place to pause and regulate if needed before completing the change.
## The Role of Caregiver Regulation
Children co-regulate with the adults around them. Your own state significantly impacts their ability to stay regulated during transitions.
**Monitor your own stress.** Rushed, anxious adults create rushed, anxious transitions. When you feel yourself becoming activated, take a breath before initiating or continuing the transition.
**Model regulation strategies.** Narrate your own regulation during transitions: "I'm feeling a little stressed about time. I'm going to take a deep breath." Children learn from watching you regulate.
**Adjust expectations when you are dysregulated.** If you are having a hard day, recognize that transitions will be harder for everyone. Simplify what you can and extend grace to yourself and your child.
**Build in buffers that protect your regulation.** Running late makes everything harder. Building in extra time for transitions protects your own nervous system, which in turn supports your child's.
## Progress Takes Time
Building regulation skills during transitions is a gradual process. Celebrate small improvements rather than expecting immediate transformation.
**Notice effort, not just success.** A child who tried to use a regulation strategy, even if they still became upset, is building skills. Acknowledge the attempt.
**Track patterns over time.** What seemed impossible three months ago may now happen occasionally. This is meaningful progress even if daily struggles continue.
**Adjust strategies as children grow.** What works at age five may not work at age eight. Stay curious about what helps your specific child at their current stage.
---
[VizyPlan](https://vizyplan.com) helps you create visual transition supports with built-in regulation cues. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring more calm to your family's transitions.
---
## The Power of Social Stories for Children with Autism
Published: 2025-01-21 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/social-stories-autism-guide
Category: Strategies
Author: Justin Bowman
> Learn how social stories help autistic children understand new situations, navigate social expectations, and feel prepared for life's challenges.
Your child has a birthday party on Saturday and you can already feel both of your stress levels rising. What will happen when we get there? Will it be loud? Do I have to sing? What if I do not like the cake? The questions start days in advance because your child's brain needs answers before it can feel safe walking into the unknown.
What if you could give them a preview of exactly what to expect, written in their language, from their perspective, before they ever walk through the door? That is exactly what social stories do, and they have been transforming how neurodivergent children navigate the world since Carol Gray developed them in 1991.
## What Are Social Stories?
Social stories are short, personalized narratives that describe a situation, skill, or concept in terms of relevant social cues, perspectives, and appropriate responses. They are written from the child's perspective and provide clear, concrete information about what to expect and how to respond.
Unlike typical stories meant for entertainment, social stories serve a specific purpose: to increase understanding and reduce anxiety around particular situations or social expectations.
**A social story might cover topics like:**
- Going to the dentist
- Starting at a new school
- What to do when feeling angry
- How to join a group of children playing
- What happens during a fire drill
- Meeting a new family member
## Why Social Stories Work
Children with autism often experience the world differently. What seems intuitive to neurotypical children, reading social cues, understanding unwritten rules, predicting what will happen next, can be genuinely puzzling for autistic children.
**Social stories work because they:**
**Make the implicit explicit.** Many social expectations are never directly taught, we assume children will "just know." Social stories spell out what others might take for granted.
**Reduce anxiety through predictability.** When children know what to expect, anxiety decreases. Social stories provide a roadmap for unfamiliar situations.
**Present information visually and verbally.** Many autistic children are visual learners. Social stories combine words with images, making information more accessible.
**Allow for repeated practice.** Reading a social story multiple times helps children internalize the information before they need to use it.
**Provide perspective-taking support.** Social stories often include information about how others might feel or think, supporting development of theory of mind.
## Key Components of Effective Social Stories
Carol Gray's guidelines provide a framework for writing effective social stories. Understanding these components helps whether you're creating stories yourself or evaluating pre-made resources.
**Descriptive sentences** provide factual information about the situation. "The dentist's office has a waiting room with chairs and magazines."
**Perspective sentences** describe the thoughts, feelings, or beliefs of others. "The dentist wants to help keep my teeth healthy."
**Directive sentences** suggest appropriate responses. "I can try to sit still in the dentist's chair."
**Affirmative sentences** express a shared value or reassure. "It is important to take care of our teeth."
**Control sentences** are written by the child to identify personal strategies for remembering information. "I can think of the dentist as a tooth helper."
The ratio matters, effective social stories have significantly more descriptive and perspective sentences than directive ones. The goal is understanding, not just compliance.
## When to Use Social Stories
Social stories are versatile tools that can address many different situations.
**Preparing for new experiences.** Doctor visits, airplane flights, starting school, attending a birthday party, any new situation benefits from advance preparation through a social story.
**Teaching social skills.** Making friends, taking turns, understanding personal space, and responding to greetings can all be addressed through social stories.
**Explaining changes in routine.** When schedules must change, a substitute teacher, a canceled activity, a different route to school, social stories help children understand and adapt.
**Addressing challenging behaviors.** When a child engages in behavior that causes problems, a social story can explain why the behavior is problematic and suggest alternatives, without shame or punishment.
**Processing difficult events.** After upsetting experiences, social stories can help children make sense of what happened and feel more prepared if it happens again.
## Creating Personalized Social Stories
While pre-made social stories exist for common situations, the most effective stories are personalized to your specific child and their specific circumstances.
**Use your child's name and specific details.** "Marcus is going to Dr. Johnson's office on Oak Street" is more meaningful than a generic story about "going to the doctor."
**Include photographs when possible.** Pictures of the actual location, people, or objects your child will encounter make the story concrete and recognizable.
**Match the language level to your child.** Use vocabulary and sentence structure your child can understand. Simpler is usually better.
**Keep it accurate.** Never promise something that might not happen. If getting a shot is possible, the story should include that possibility.
**Be positive but honest.** Focus on what your child CAN do while acknowledging that things might be challenging.
**Involve your child in creation.** Older children can help write their own social stories, which increases engagement and ownership.
## How to Use Social Stories Effectively
Having a well-written social story is only the beginning. How you use it determines its effectiveness.
**Read it in advance.** Introduce the social story well before the situation occurs, ideally days before for major events, and multiple times leading up to it.
**Read it consistently.** Make reading the social story part of the routine. Repetition helps the information become familiar and accessible.
**Read it calmly.** Social stories work best when introduced during relaxed moments, not during times of stress or as a response to meltdowns.
**Keep it available.** The social story should be accessible so your child can review it independently or carry it to the situation as a reference.
**Update as needed.** As your child masters a skill or situation, the story can be retired. When circumstances change, stories may need updating.
**Don't force it.** If your child resists a particular social story, consider whether the format, content, or approach needs adjustment.
.png)
## Social Stories in the Digital Age
While traditional social stories on paper remain effective, digital formats offer new possibilities.
**Interactive elements** can increase engagement. Tapping to reveal the next part of the story or hearing audio can make social stories more appealing.
**Easy personalization** through apps allows for quick creation and modification of stories with personal photos and details.
**Portability** means stories are always available on a tablet or phone, ready to review before or during challenging situations.
**Multimedia options** allow for including video, audio, and animation, which may resonate more strongly with some children.
[VizyPlan](https://vizyplan.com)'s Vizy Stories feature makes creating personalized social stories simple, with the ability to add custom images, multiple pages, and covers that make each story unique to your child.
## Beyond Basic Social Stories
As children develop, social story approaches can evolve.
**Comic strip conversations** use simple drawings to represent conversations, helping children understand the back-and-forth of social interaction.
**Video modeling** shows real or animated people demonstrating social skills, providing a dynamic visual example.
**Social scripts** provide exact words children can use in specific situations, helpful for children who struggle to generate language in the moment.
**Self-created stories** allow older children to write stories about their own experiences, processing events and planning for future situations.
## Measuring Success
How do you know if social stories are helping?
**Observe behavior changes.** Is your child more cooperative or less anxious in situations addressed by social stories? Are challenging behaviors decreasing?
**Ask your child.** If developmentally appropriate, ask how they feel about the situations covered in social stories. Do they feel more prepared?
**Monitor over time.** Keep notes about how situations go before and after introducing social stories. Patterns emerge over time.
**Adjust as needed.** If a social story does not seem to help, consider revising the content, trying a different format, or consulting with a professional who can provide guidance.
## Working with Professionals
While parents can create effective social stories independently, professionals can provide valuable support.
**Speech-language pathologists** often use social stories as part of social communication intervention.
**Behavior analysts** can help identify which situations would benefit most from social stories and how to measure their effectiveness.
**Teachers and special educators** use social stories in classroom settings and can coordinate with home use.
**Occupational therapists** may incorporate social stories into sensory and self-regulation work.
---
[VizyPlan](https://vizyplan.com)'s Vizy Stories feature helps you create personalized social stories with custom images and multiple pages. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and help your child feel prepared for any situation.
---
## VizyPlan Is Officially Live on the App Store
Published: 2025-01-20
URL: https://vizyplan.com/blog/vizyplan-now-live-on-app-store
Category: Announcements
Author: Justin Bowman
> What started as a personal project has become something so much bigger. VizyPlan uses custom AI-generated images to support neurodivergent learners in visualizing routines and seeing themselves succeeding.
Big news , [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) is officially live on the App Store!
Download on the App Store
What started as a personal project has become something so much bigger, and watching it turn into reality has been surreal and truly meaningful.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) uses custom AI-generated images to support neurodivergent learners and all learning styles in visualizing routines and seeing themselves succeeding throughout their day. Our hope is to spark confidence, independence, and a little more joy in the everyday.
## What You'll Find in VizyPlan
We've packed [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) with tools designed to make daily life easier for families navigating autism, ADHD, and visual learning needs.
**Visual Routines and Schedules**
- Visual step-by-step routines and picture schedules
- First-Then visual sequences and picture cards
- Choice boards for routines and rewards
- Daily routine planner for families
**AI-Powered Features**
- Custom AI image creation
- Vizy AI Advocate to support service provider meetings
**Learning and Story Tools**
- Social stories and story-based learning tools
- Story Time mode for guided reading and visual modeling
- Build-a-Story creator for personalized narratives
**Regulation and Transition Support**
- Visual timers with clear, easy-to-read cues
- Calming and sensory-friendly regulation tools
- Transition support features
- Emotion check-in activities
**Motivation and Rewards**
- Points, stickers, and motivational rewards
**Family and Provider Collaboration**
- Family calendar and shared schedules
- Provider goals, strategies, and session notes
- Progress insights for families and care teams
**Easy to Use**
- Easy drag-and-drop editing
- Designed with input from parents and service providers
## Built with Families in Mind
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was designed with direct input from parents and service providers who understand the daily realities of supporting neurodivergent children. Every feature reflects real needs and real feedback from the community we serve.
Whether you're a parent looking for tools to support your child at home, or a therapist seeking resources for your sessions, [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) was built with you in mind.
## Our Hope for VizyPlan
Our hope is simple: to spark confidence, independence, and a little more joy in the everyday.
We know that every child is different. What works for one may not work for another. That's why [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) offers so many different tools and approaches, so you can find what resonates with your child and your family.
## What Comes Next
We're so proud of how far this has come, and so excited for what comes next. This is just the beginning.
We're committed to continuing to improve [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) based on your feedback. The families and providers who use our app are our greatest resource, and we're listening.
---
Ready to try [VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)? [Download it free on the App Store](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and see how visual supports can transform your daily routines.
---
## Creating Calmer Bedtimes for Children with Autism and ADHD
Published: 2025-01-19 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/bedtime-routine-autism-adhd
Category: Daily Routines
Author: Justin Bowman
> Discover proven strategies and visual supports to transform chaotic bedtimes into peaceful, predictable routines for neurodivergent children.
It is 9:47 PM. Bedtime was supposed to be 8:00. Your child has asked for water three times, needed the bathroom twice, rearranged their stuffed animals four times, and is now wide-eyed and wired while you are running on fumes. You have read every sleep tip on the internet, and none of them seem to account for the child who literally cannot stop their brain from spinning.
You are not doing bedtime wrong. The neurodivergent brain genuinely struggles with the shift from stimulation to stillness, and standard sleep advice was not built for kids whose nervous systems do not have an easy off switch. Here is what actually works.
## Why Bedtime Is Particularly Challenging
Children with autism often thrive on predictability, yet bedtime introduces multiple transitions in quick succession. Children with ADHD struggle to shift from the stimulation of the day to the quiet stillness required for sleep.
Both conditions can involve sensory processing differences that make certain bedtime elements uncomfortable, scratchy pajamas, room temperature, or ambient sounds that neurotypical children might not notice.
Understanding these challenges is the first step toward addressing them effectively.
## Building a Visual Bedtime Routine
Visual supports work exceptionally well for bedtime because they remove ambiguity. When a child can see exactly what comes next, anxiety decreases and cooperation increases.
**Create a clear sequence** that includes every step from the start of the bedtime routine to lights out. For many children, this might include:
- Bath or shower time
- Putting on pajamas
- Brushing teeth
- Using the bathroom
- Reading a story
- Goodnight hugs
- Lights out
**Use images that resonate** with your specific child. Some children respond best to photographs of themselves doing each activity. Others prefer simple illustrations or icons.
**Keep it visible** by placing the visual schedule where your child can reference it throughout the routine, on the bathroom mirror, bedroom door, or a tablet they carry with them.
## Sensory Considerations for Better Sleep
Many bedtime battles are actually sensory battles in disguise. Addressing sensory needs proactively can transform the experience.
**Evaluate pajamas carefully.** Tags, seams, and fabric textures that seem minor to adults can be intensely uncomfortable for sensory-sensitive children. Seamless, tagless options in soft fabrics often make a significant difference.
**Consider room environment.** Temperature, lighting, and sound all play a role. Some children sleep better with white noise or a fan. Others need complete silence. Blackout curtains help children who are light-sensitive.
**Create a calming transition.** Dim lights 30-60 minutes before bedtime to signal to the brain that sleep is approaching. Reduce screen exposure during this window, as blue light can interfere with natural sleep hormones.
## Timing and Consistency Matter
The ADHD and autistic brain benefits enormously from consistency. When bedtime happens at the same time, in the same order, every night, the routine becomes internalized over time.
**Set a consistent bedtime** and work backward to determine when the routine should start. If your child needs 45 minutes to complete the routine, and bedtime is 8:00 PM, the routine starts at 7:15 PM.
**Build in buffer time** for difficult nights. Rushing creates stress, and stress makes everything harder. Having extra time removes pressure from both parent and child.
**Use visual timers** to help children understand how much time remains for each activity. Abstract time is difficult for many neurodivergent children to grasp, but watching time visually count down makes it concrete.
.png)
## Managing Bedtime Resistance
Even with perfect planning, some nights will be harder than others. Having strategies ready helps you stay calm and consistent.
**Validate feelings without abandoning boundaries.** It is okay to say, "I understand you don't want to stop playing. It's still time for bed. Let's check your schedule for what comes next."
**Offer limited choices** within the routine. "Do you want to brush teeth first or put on pajamas first?" gives a sense of control without derailing the schedule.
**Use First-Then language.** "First we finish our routine, then you can have extra story time tomorrow" connects current cooperation with future rewards.
## The Power of Wind-Down Activities
The transition from active play to sleep readiness needs a bridge. Calming activities before the formal bedtime routine begins can make a significant difference.
**Consider quiet activities** like puzzles, coloring, listening to calm music, or gentle stretching. These activities lower arousal levels gradually rather than expecting an abrupt shift.
**Avoid screens and stimulating play** in the hour before bed whenever possible. While this can be challenging, the impact on sleep quality is substantial.
**Deep pressure input** through weighted blankets, compression pajamas, or firm hugs before bed can help regulate the sensory system and prepare the body for rest.
## Celebrating Progress
Change takes time, especially when establishing new routines. Focus on progress rather than perfection.
Notice and acknowledge small improvements. A child who completed three steps independently tonight is making progress, even if the whole routine was not perfect.
Be patient with setbacks. Illness, travel, or schedule disruptions may temporarily derail progress. The visual supports will help you get back on track faster.
---
[VizyPlan](https://vizyplan.com) helps you create calming visual bedtime routines. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring peace to your evenings.
---
## Helping Autistic Children Navigate Transitions Successfully
Published: 2025-01-18
URL: https://vizyplan.com/blog/transition-strategies-autism
Category: Strategies
Author: Justin Bowman
> Learn effective strategies and visual supports to help children with autism move between activities with less anxiety and resistance.
They were happily building with LEGOs. You gave a five-minute warning. You gave a two-minute warning. You said, "Time to clean up for dinner," and the room exploded. The LEGOs are now scattered across the floor, your child is sobbing, and dinner is getting cold. You did everything "right," and it still fell apart.
Transitions are the invisible landmines of neurodivergent family life. They happen dozens of times a day, and each one is a potential trigger. But here is what changes everything: when you understand why your child's brain fights transitions so hard, you can stop battling through them and start designing around them.
## Why Transitions Are So Difficult
For neurotypical children, shifting between activities happens relatively automatically. For children with autism, transitions require significant cognitive and emotional effort.
**Difficulty with cognitive flexibility** makes it hard to mentally shift gears. When a child is engaged in an activity, their brain may become deeply focused, making disengagement feel jarring or even distressing.
**Need for predictability** means that changes, even expected ones, can trigger anxiety. The familiar activity feels safe; the next activity, even if known, feels uncertain.
**Processing time differences** mean autistic children often need more time to understand that a transition is coming and to prepare mentally for the change.
## Visual Warnings and Countdowns
One of the most effective transition strategies is giving children advance warning in a format they can understand and reference.
**Visual timers** show time passing in a concrete way. When a child can watch the remaining time shrink, the transition becomes predictable rather than sudden.
**Countdown warnings** at consistent intervals help children prepare. Many families use a "5 minutes, 2 minutes, 1 minute, time to transition" sequence. The key is consistency, use the same intervals every time.
**Visual schedules** let children see what comes next. When the next activity is visible, it becomes less unknown and therefore less anxiety-provoking. Pointing to the schedule during warnings reinforces what is coming.
## Transition Objects and Rituals
Many children benefit from having a consistent element that bridges activities and provides comfort during the change.
**Transition objects** are items a child carries from one activity to the next. This might be a small toy, a comfort item, or even a picture card representing the next activity.
**Transition songs or phrases** create auditory cues that signal change. When the same song plays before every transition, the child's brain begins associating that sound with "change is coming."
**Physical rituals** like a specific handshake, high-five sequence, or movement pattern can help mark the end of one activity and the beginning of another.
## The Power of Choice Within Transitions
Offering limited choices during transitions gives children a sense of control without derailing the necessary change.
**Let children choose the order** when possible. "We need to clean up and wash hands before lunch. Which do you want to do first?"
**Offer how, not whether.** The transition is not negotiable, but how it happens can be. "Time to go to the car. Do you want to walk or hop?"
**Allow bringing something along** when appropriate. "Time to leave the playground. You can bring one rock to show me in the car."
## Managing Transition Hotspots
Certain transitions are predictably more difficult. Identifying and proactively planning for these moments prevents many meltdowns.
**Leaving preferred activities** is often hardest. Extra warnings, visual supports, and clear information about when the preferred activity will happen again all help.
**Arriving at new or less preferred places** triggers anxiety about what will happen. Social stories, visual previews of the location, and clear schedules for the time there can reduce uncertainty.
**Transitions involving sensory changes** require attention to sensory needs. Moving from a quiet space to a loud one, or from indoors to outdoors, may need additional preparation and support.
.png)
## Using Social Stories for Recurring Transitions
Social stories are short, personalized narratives that explain what will happen during a transition and how the child can respond.
**Keep stories simple and accurate.** Describe what will happen, why it happens, and what the child can do.
**Include the child's perspective.** "Sometimes I feel sad when playtime ends. That is okay. I can take a deep breath and look at my schedule."
**Read the story regularly**, not just during the difficult moment. Repeated exposure helps the information become familiar and accessible when needed.
## Creating Transition-Friendly Environments
The physical environment can either support or hinder smooth transitions.
**Clear visual boundaries** help children understand when one activity space ends and another begins. Defined areas for different activities make transitions more concrete.
**Reduced clutter and distractions** during transition times help children focus on the change at hand rather than being pulled toward other stimuli.
**Consistent physical locations** for routine transitions help build automatic responses over time. When teeth-brushing always happens at the same sink, the location itself becomes a cue.
## When Transitions Still Go Wrong
Even with excellent preparation, some transitions will be difficult. Having a plan for these moments helps everyone recover.
**Stay calm yourself.** Children pick up on adult stress, which amplifies their own. Your regulated presence is a powerful support.
**Reduce verbal language.** During moments of overwhelm, less talking is better. Point to the visual schedule, use simple words, and wait.
**Allow recovery time** after difficult transitions before expecting engagement in the new activity. Pushing too quickly often extends the distress.
## Building Transition Tolerance Over Time
With consistent support, most children with autism can develop increased tolerance for transitions.
**Start with easier transitions** and build success before tackling harder ones. Confidence from mastering simpler changes supports tackling more challenging ones.
**Gradually reduce supports** as skills develop. The child who needs five warnings now may need only two in six months.
**Celebrate progress** consistently. Notice when transitions go well and acknowledge the effort involved.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create visual supports for smoother transitions. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and reduce transition stress.
---
## Using Visual Supports for Emotional Regulation in Children
Published: 2025-01-17 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/emotional-regulation-visual-supports
Category: Strategies
Author: Justin Bowman
> Explore how visual tools help neurodivergent children identify, understand, and manage their emotions more effectively.
"Use your words." You have said it a hundred times. But your child cannot use their words because they do not have words for what they are feeling. They are drowning in a feeling so big it has taken over their entire body, and telling them to "calm down" is like telling someone underwater to just breathe.
This is the core challenge of emotional regulation for neurodivergent children: the feelings are intense, the ability to name them is limited, and the path from overwhelmed to okay is invisible. Visual supports change that equation by making the invisible visible, giving children a concrete map from "I am falling apart" to "I know what to do."
## Why Emotional Regulation Is Challenging
Children with autism frequently experience alexithymia, difficulty identifying and describing their own emotions. A child may feel intensely without being able to name or understand what they are feeling.
Children with ADHD often experience emotions with greater intensity and have difficulty modulating their responses. The gap between feeling an emotion and acting on it may be much shorter than for neurotypical peers.
Both conditions can involve sensory processing differences that amplify emotional experiences or make it harder to distinguish between physical sensations and emotions.
## Visual Emotion Identification Tools
Before children can regulate emotions, they need to recognize them. Visual tools make this abstract skill concrete.
**Emotion charts with pictures** help children match their internal experience to a named emotion. Charts showing faces with different expressions give children a reference point for identifying what they feel.
**Feeling thermometers or scales** help children identify the intensity of emotions, not just the type. Learning to distinguish between "a little frustrated" and "very frustrated" supports more proportional responses.
**Body maps** show where different emotions are felt physically. This helps children connect physical sensations like a tight chest or warm face to specific emotions, building emotional awareness.
## Creating a Visual Calm-Down Sequence
When emotions become overwhelming, having a visual guide for calming down removes the need to think clearly during a difficult moment.
**Include specific strategies** the child has practiced and can use independently:
- Take three deep breaths
- Count to ten
- Squeeze a stress ball
- Find a quiet space
- Ask for help
**Keep it accessible.** The calm-down sequence should be posted where the child can see it during difficult moments, not tucked away in a drawer.
**Practice during calm times.** Children cannot learn new strategies while dysregulated. Practice the calm-down sequence when everyone is relaxed so it becomes familiar and automatic.
## Zones of Regulation and Color Coding
Many families and educators find success with color-coded systems that categorize emotional states into zones.
**The basic concept** assigns colors to different energy and emotional states. For example, blue might represent low energy or sad feelings, green represents calm and focused, yellow represents heightened energy or worry, and red represents intense emotions.
**Visual check-ins** using these colors help children communicate their state quickly. A child can point to a color to show how they are feeling when words are difficult.
**Matching strategies to zones** helps children learn that different emotional states call for different responses. Yellow zone feelings might need movement or deep breaths, while blue zone feelings might need connection or a change of activity.
## Visual Supports for Recognizing Triggers
Helping children identify what triggers difficult emotions builds self-awareness and prevention skills.
**Trigger identification charts** help children learn patterns in their emotional responses. Visual representations of common triggers, transitions, sensory experiences, social situations, give children vocabulary for understanding their experiences.
**Routine reviews** using visuals can help identify when in the day difficult emotions are most likely to occur, allowing for proactive support during those times.
**Pattern tracking** over time, even with simple visual logs, helps both children and caregivers understand emotional patterns and plan accordingly.
## Social Stories for Emotional Situations
Social stories can teach children how to handle emotionally challenging situations before they occur.
**Normalize difficult emotions.** Stories can convey that everyone feels angry, sad, or frustrated sometimes, and that these feelings are okay even when the behaviors that follow might not be.
**Provide specific scripts.** What can a child say or do when they feel overwhelmed? Social stories can suggest exact words and actions to use.
**Include successful outcomes.** Showing the positive results of using coping strategies motivates children to try them.
## Building an Emotional Vocabulary
Many children with autism and ADHD have limited emotional vocabulary, which restricts their ability to process and communicate about feelings.
**Visual word banks** with emotion words paired with images expand vocabulary over time. Moving beyond basic "happy, sad, mad" to include words like "frustrated, disappointed, excited, nervous" gives children more precise language.
**Daily check-ins** using visual supports create regular opportunities to practice identifying and naming emotions in low-pressure situations.
**Modeling emotional language** while using visual supports teaches children how to express emotions. When caregivers point to emotion visuals and name their own feelings, children learn by example.
## Visual Coping Strategy Cards
Individual coping strategy cards give children a menu of options when they need to regulate.
**Create cards for strategies that work** for your specific child. What helps one child may not help another. Build a personalized collection based on what you observe actually helps.
**Make them portable.** A small set of cards on a ring can travel in a backpack, giving children access to their strategies anywhere.
**Include sensory strategies** alongside cognitive ones. Deep pressure, movement, fidgets, and other sensory inputs are often as important as breathing or counting for neurodivergent children.
## Teaching Emotional Regulation Takes Time
Building self-regulation skills is a long-term process. Visual supports help, but patience and consistency are equally important.
**Expect gradual progress.** A child who melts down daily now may melt down weekly in six months and monthly in a year. This is significant progress even if it feels slow.
**Adjust supports as needed.** As children grow and change, their emotional needs and effective strategies will evolve. Revisit and update visual supports regularly.
**Celebrate effort, not just success.** A child who tried to use a coping strategy, even if it did not fully work, is building skills and deserves recognition.
---
[VizyPlan](https://vizyplan.com) helps you create visual emotional regulation tools for your child. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and support your child's emotional growth.
---
## Creating Effective Homework Routines for ADHD and Autism
Published: 2025-01-16
URL: https://vizyplan.com/blog/homework-routine-adhd-autism
Category: Daily Routines
Author: Justin Bowman
> Practical strategies and visual supports to help neurodivergent children complete homework with less stress and greater independence.
Homework time can be a daily battleground for families of children with ADHD or autism. Executive function challenges, sensory sensitivities, fatigue from masking at school, and difficulty transitioning from preferred activities all combine to make homework one of the most stressful parts of the day.
With thoughtful structure and visual supports, homework can become more manageable for everyone involved.
## Understanding the Homework Challenge
Children with ADHD struggle with the executive functions homework demands, initiating tasks, sustaining attention, managing time, and organizing materials. After a full day of school, these capacities may be particularly depleted.
Children with autism may find homework distressing because it involves open-ended expectations, ambiguous instructions, or topics outside their areas of interest. The unstructured nature of homework time contrasts with the clear structure of the school day.
Both groups often experience significant fatigue from the effort of navigating the school environment, leaving little energy for additional academic work at home.
## Setting Up the Homework Environment
Where and how homework happens significantly impacts success.
**Create a consistent homework space** with minimal distractions. Some children work best at a clear desk; others need movement and may do better standing at a counter or sitting on an exercise ball.
**Address sensory needs proactively.** Noise-canceling headphones, fidget tools, appropriate lighting, and comfortable seating all support focus. Identify what helps your specific child concentrate.
**Gather materials before starting.** Hunting for pencils and erasers wastes mental energy and creates opportunities for distraction. Having everything ready reduces friction.
## The Power of Visual Homework Schedules
A visual homework routine removes ambiguity and reduces the mental load of figuring out what to do.
**Break the session into clear phases:**
- Unpack backpack and organize materials
- Review assignments
- Complete priority task
- Take a short break
- Complete remaining tasks
- Check work
- Pack backpack for tomorrow
**Make the sequence visible** throughout homework time. Checking off completed steps provides satisfaction and shows progress toward the finish.
**Include break times visually.** When children can see that a break is coming, they are more likely to sustain effort until that point.
## Breaking Down Assignments
Large assignments overwhelm children with executive function challenges. Breaking work into smaller chunks makes it achievable.
**Chunk worksheets visually.** Cover all but the first few problems, or fold the paper to show only a portion at a time. Completing visible sections provides repeated feelings of accomplishment.
**Use task cards for multi-step assignments.** Write each step on a separate card that can be checked off or turned over when complete.
**Set micro-goals with visual timers.** "Do these five problems before the timer goes off" is more concrete and achievable than "finish your math."
## Managing Time Visually
Abstract time management is particularly difficult for children with ADHD. Visual time supports make homework sessions more structured.
**Visual timers** show time passing in a concrete way. Seeing that 15 minutes remains is more meaningful than being told "you have 15 more minutes."
**Time estimates for each task** help children learn to predict how long things take. Initially, adults may need to provide estimates, but over time, children can learn this skill.
**Scheduled breaks** at predictable intervals prevent burnout. Many families find success with work periods of 10-20 minutes followed by 5-minute breaks, depending on the child's attention span.
## First-Then Strategies for Homework
First-Then approaches provide motivation by connecting less-preferred work to more-preferred rewards.
**Make the reward visible.** Place a picture of the reward activity next to the "Then" portion of a First-Then board so the child can see what they are working toward.
**Choose meaningful rewards.** The "Then" needs to be something genuinely motivating to your child. A reward that adults think should be motivating may not work if the child disagrees.
**Follow through consistently.** If the child completes the First, they must receive the Then. This builds trust in the system.
.png)
## Addressing Homework Avoidance
When children consistently resist or avoid homework, investigate the underlying cause rather than simply pushing harder.
**Is the work too difficult?** Children may avoid homework that they genuinely do not understand. This signals a need for additional support or communication with teachers.
**Is there a sensory issue?** Some children resist writing due to fine motor challenges or discomfort with pencil grip. Occupational therapy tools or accommodations may help.
**Is fatigue the problem?** Some children need significant downtime after school before they can engage in homework. Adjusting the schedule may help more than pushing through.
## Communication with School
Homework success often requires partnership between home and school.
**Share what works** with teachers. If visual supports help at home, similar approaches might benefit your child at school as well.
**Advocate for appropriate accommodations.** Reduced homework volume, extended time, or alternative formats may be appropriate for children with documented needs.
**Report struggles honestly.** Teachers need to know if homework is taking excessively long or causing significant distress. This information helps them adjust expectations and support your child appropriately.
## Building Independence Gradually
The goal is for children to develop homework skills they can eventually use independently.
**Start with high support** and fade gradually. Initial success builds confidence; too little support leads to frustration and negative associations with homework.
**Teach organizational systems explicitly.** Do not assume children will naturally develop systems for tracking assignments or organizing materials. Model and practice these skills directly.
**Celebrate effort and progress.** A child who struggled through homework with supports today is building skills for greater independence tomorrow.
## When Homework Becomes Too Much
If homework consistently causes hours of conflict and distress, it may be time to reconsider.
**Quality over quantity.** Thirty minutes of focused work may be more valuable than two hours of battles.
**Communicate with the school** about what is reasonable. Many children with IEPs or 504 plans have homework modifications written into their plans.
**Protect family time.** Homework should not consume entire evenings and damage family relationships. Finding a sustainable balance matters for everyone's wellbeing.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create visual homework routines that reduce stress. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and make homework time easier.
---
## Supporting Sensory Processing Needs Through Daily Routines
Published: 2025-01-15
URL: https://vizyplan.com/blog/sensory-processing-daily-routines
Category: Daily Routines
Author: Justin Bowman
> Learn how to design daily routines that accommodate sensory sensitivities and help children with sensory processing differences thrive.
The tag in their shirt is "burning." The seam on their sock is "stabbing." The sound of the blender makes them cover their ears and scream. Meanwhile, their sibling does not even notice any of it. You are not imagining the difference, and your child is not being dramatic. Their brain is literally processing sensory input differently than most people's, and it affects every single part of their day.
Understanding how your child experiences the world through their senses is one of the most game-changing things you can do as a parent. Once you get it, everything from morning routines to mealtimes to school starts making a lot more sense.
## Understanding Sensory Processing Differences
Every person processes sensory information differently, but children with sensory processing differences experience these inputs in ways that can significantly impact their daily lives.
**Hypersensitivity** means sensory input feels more intense than typical. A tag that most people would not notice feels unbearable. Sounds that others ignore are overwhelming. Certain food textures trigger strong negative reactions.
**Hyposensitivity** means sensory input is under-registered. Children may seek intense sensory experiences, spinning, crashing, touching everything, to get the input their nervous system craves.
**Mixed patterns** are common. A child might be hypersensitive to certain sounds while being hyposensitive to touch, requiring different accommodations for different sensory channels.
## Building Sensory-Aware Morning Routines
Mornings involve multiple sensory experiences in rapid succession. Thoughtful planning makes a significant difference.
**Consider clothing carefully.** Seams, tags, waistbands, and fabric textures that feel fine to others may be intolerable. Identify clothing that works and have multiple similar items available.
**Address grooming sensitivities.** Hair brushing, teeth brushing, and face washing can be intensely unpleasant for sensory-sensitive children. Softer brushes, vibrating toothbrushes, warm water, and gentle techniques can help.
**Manage auditory environment.** Some children do better with background music; others need quiet. Identify what helps your child and create that environment consistently.
**Build in movement.** Children who need proprioceptive input may function better if morning routines include heavy work activities like carrying their backpack, doing wall push-ups, or helping with physical tasks.
## Visual Schedules for Sensory Predictability
Visual schedules support children with sensory processing differences by providing predictability about what sensory experiences are coming.
**Include sensory information** in visual schedules when relevant. If a child knows that hair brushing comes after getting dressed, they can mentally prepare for that sensory experience.
**Show available supports.** If a child uses a weighted lap pad during breakfast or wears headphones during a noisy part of the routine, including these in the visual schedule reminds them to use their tools.
**Allow processing time.** Transitions between activities involve sensory shifts. Building brief pauses into the visual schedule respects the time needed to adjust.
## Mealtime and Sensory Considerations
Eating involves multiple sensory systems simultaneously, taste, smell, texture, temperature, and even sounds. For sensory-sensitive children, meals can be overwhelming.
**Respect sensory limits** while gently expanding over time. Forcing a child to eat foods that trigger sensory distress rarely leads to positive outcomes.
**Consider the environment.** Bright lights, strong smells from cooking, and chaotic family meals may make eating difficult. Some children do better with calmer, less stimulating mealtime environments.
**Be aware of utensil and dishware preferences.** Some children are sensitive to certain materials or textures in their eating utensils. Metal versus plastic, certain bowl depths, or specific cup types may matter.
**Visual mealtime routines** can help children know what to expect and feel more in control of the experience.
## Sensory Breaks Within Routines
Building sensory regulation opportunities into daily routines prevents overload and supports sustained functioning.
**Movement breaks** benefit children who are hyposensitive to proprioceptive or vestibular input. Jumping, swinging, spinning, or climbing between activities can help regulate the nervous system.
**Quiet retreats** benefit children who are hypersensitive and need breaks from stimulation. A designated calm space with reduced lighting and sound can provide necessary recovery.
**Fidget and tactile tools** can be used during activities that require sitting still. Having these tools available and normalized within the routine supports self-regulation.
## Homework and Sensory Needs
Homework time places significant demands on children who are already sensory-depleted from the school day.
**Allow decompression first.** Many children need 30-60 minutes of sensory regulation activities before they can engage with homework.
**Provide sensory supports during work.** Fidgets, wobble cushions, chewing gum, or background music may help sustain focus.
**Break homework into segments** with sensory breaks between. Short bursts of work followed by movement may be more effective than long continuous periods.
## Bathtime and Hygiene Sensory Strategies
Personal hygiene activities involve intense sensory experiences that can be distressing for sensitive children.
**Water temperature and pressure** matter. Some children prefer very warm or very cool water. Adjustable showerheads that allow different spray patterns give children more control.
**Product sensitivities** are common. Unscented products with gentle formulations may be better tolerated. When a child finds products that work, buy in bulk.
**Tactile experiences** like nail trimming, hair washing, and tooth brushing require patience and adaptation. Breaking these into smaller steps with visual supports helps children know what to expect.
**Create predictable sequences.** When bath time follows the same visual routine every time, the sensory experiences become more predictable and therefore more manageable.
## Bedtime Sensory Considerations
The sensory environment of the bedroom significantly impacts sleep quality.
**Bedding textures** deserve attention. Some children need very soft, smooth sheets while others prefer heavier textures. Weighted blankets provide deep pressure that many sensory-seeking children find calming.
**Room temperature and air flow** affect comfort. Fans provide both white noise and air movement that some children find regulating.
**Darkness levels** matter. Some children need complete darkness; others feel more secure with a dim nightlight.
**Pajama sensitivities** can prevent sleep. Seamless, tagless options in comfortable fabrics are worth seeking out.
## Creating a Sensory-Friendly Home
Beyond specific routines, overall home environment modifications support children with sensory processing differences.
**Designated calm spaces** give children a place to retreat when overwhelmed. These spaces should have dim lighting, comfortable seating, and minimal visual clutter.
**Noise management** throughout the home helps. Rugs, curtains, and soft furnishings absorb sound. Awareness of loud appliances and when they run supports sensitive children.
**Visual calm** comes from reducing clutter and visual chaos. Organized spaces with clear purposes are easier to navigate than overwhelming, busy environments.
## Working with Professionals
Occupational therapists who specialize in sensory processing can provide invaluable guidance for supporting your child.
**Sensory evaluations** identify your child's specific profile of sensitivities and preferences.
**Sensory diet recommendations** provide structured activities throughout the day that support regulation.
**Strategies for specific challenges** address your child's particular areas of difficulty with evidence-based approaches.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create sensory-friendly visual routines for your child. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and support your child's sensory needs.
---
## How Visual Schedules Help Children with Autism Thrive
Published: 2025-01-14 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/visual-schedules-for-autism
Category: Visual Supports
Author: Justin Bowman
> Discover why visual schedules are one of the most effective tools for helping autistic children understand routines and reduce anxiety.
You have told your child the plan for today three times already, and they are still asking "what are we doing next?" every five minutes. Or maybe they are not asking at all. Maybe they are just melting down at every transition because the next thing always feels like a surprise, even when you warned them verbally two minutes ago.
Here is what most parents do not realize: for many autistic children, verbal instructions vanish the moment you finish speaking. But a picture on a wall stays. Visual schedules work because they turn invisible words into something your child can see, touch, and check whenever they need reassurance.
## Why Visual Schedules Work
Children with autism often process visual information more effectively than verbal instructions. A visual schedule takes abstract concepts like time and sequence and makes them concrete and understandable.
When a child can see their day laid out in front of them, they feel more in control. This sense of control directly reduces anxiety and meltdowns that often come from unexpected transitions.
## Key Benefits
**Reduced Anxiety**: Knowing what comes next eliminates the fear of the unknown.
**Increased Independence**: Children can check their schedule themselves instead of constantly asking "what's next?"
**Smoother Transitions**: Moving between activities becomes easier when it's visually anticipated.
**Improved Communication**: Schedules give children and parents a shared reference point.
## How to Get Started
Start simple. Pick one routine, like your morning routine, and create a visual sequence with 3-5 steps. Use clear images that your child can easily recognize.
Be consistent. Use the schedule at the same time each day until it becomes second nature.
Celebrate progress. When your child follows a step independently, acknowledge it. Small wins build confidence.
.png)
## Making It Personal
Every child is different. Some respond better to photographs, others to simple illustrations. Some need very detailed steps, while others do better with broader categories.
[VizyPlan](https://vizyplan.com) was built to make this personalization easy. You can create custom visual routines with AI-generated images tailored to your child's needs and preferences.
## The Long-Term Impact
Families who consistently use visual schedules often see improvements that extend far beyond daily routines. Children develop better time management skills, increased flexibility, and greater confidence in navigating new situations.
The investment in visual supports today pays dividends for years to come.
---
Ready to create visual schedules for your child? [Start your free trial of VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and see the difference visual clarity can make.
---
## First-Then Boards: A Complete Guide for Parents
Published: 2025-01-13 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/first-then-boards-guide
Category: Strategies
Author: Justin Bowman
> Learn how to use First-Then boards to help your child understand expectations and complete tasks with less resistance.
"Put your shoes on and THEN we can go to the park." You have said it clearly. Your child heard you. But five minutes later they are still sitting on the floor, shoeless, because the connection between "do this boring thing" and "get this fun thing" did not stick. The words evaporated before the motivation could form.
A First-Then board takes that invisible verbal promise and makes it real. Two pictures, side by side: what they need to do, and what they get after. It sounds almost too simple to work, but for neurodivergent children, seeing the payoff changes everything.
## What is a First-Then Board?
A First-Then board shows two things: what the child needs to do FIRST, and what happens THEN (usually something preferred or rewarding).
For example:
- FIRST: Brush teeth → THEN: Story time
- FIRST: Homework → THEN: iPad time
- FIRST: Get dressed → THEN: Breakfast
## Why They Work
First-Then boards work because they:
**Create Clear Expectations**: The child knows exactly what's expected before they get what they want.
**Build Motivation**: Seeing the reward helps children push through less preferred tasks.
**Reduce Power Struggles**: It's not you versus your child, it's simply how things work.
**Support Language Development**: The structure reinforces sequencing concepts.
## Tips for Success
**Keep it Simple**: Only show two items at a time. More than that defeats the purpose.
**Use Real Motivators**: The "Then" needs to be something your child genuinely wants.
**Be Consistent**: Follow through every time. If they do the First, they get the Then.
**Make it Visual**: Use pictures, not just words. Photos of actual items often work best.
.png)
## Common Mistakes to Avoid
Don't use First-Then boards as punishment. They should feel like a helpful structure, not a threat.
Don't make the "First" too overwhelming. Break big tasks into smaller First-Then sequences if needed.
Don't forget to fade support over time. As children internalize the routine, they'll need the visual less.
## When to Use First-Then Boards
They're particularly helpful for:
- Non-preferred activities (chores, homework, hygiene)
- Transitions between activities
- New or challenging situations
- Building independence
---
[VizyPlan](https://vizyplan.com) makes creating First-Then boards easy with customizable visuals. [Try it free](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and see how visual structure can transform your daily routines.
---
## 7 Morning Routine Tips for Kids with ADHD
Published: 2025-01-12
URL: https://vizyplan.com/blog/morning-routine-tips-adhd
Category: Daily Routines
Author: Justin Bowman
> Practical strategies to make mornings smoother and less stressful for families navigating ADHD.
It is 7:42 AM. School starts in 18 minutes. Your child is still in pajamas, has not touched breakfast, cannot find their left shoe, and just remembered they need something signed for school today. You are repeating instructions for the fourth time while simultaneously making lunches, and the stress level in the house is through the roof.
Sound familiar? For families navigating ADHD, mornings are not just busy. They are a collision of every executive function challenge your child faces, compressed into the most time-pressured hour of the day. Here are seven strategies that actually change the equation.
## 1. Prepare the Night Before
The morning battle is often won or lost the night before. Lay out clothes, pack backpacks, and prepare breakfast items before bed.
This reduces the number of decisions and tasks that need to happen during the already-challenging morning hours.
## 2. Use Visual Checklists
Children with ADHD often struggle to remember multi-step sequences. A visual checklist they can see and check off removes the need to hold everything in working memory.
Post it where they'll see it, bathroom mirror, bedroom door, or on a tablet they carry with them.
## 3. Build in Buffer Time
Whatever amount of time you think you need, add 15-20 minutes. This removes the pressure that makes everything worse.
Rushed mornings trigger the ADHD brain's stress response, making focus even harder.
## 4. Create Consistent Routines
The same sequence, every day, in the same order. Consistency allows routines to become automatic, requiring less mental effort over time.
Wake up → Bathroom → Get dressed → Breakfast → Teeth → Backpack → Shoes → Out the door.
.png)
## 5. Minimize Distractions
Keep screens off until ready to leave. Put away toys that might catch attention. Create a clear path from bedroom to door.
The ADHD brain is easily pulled off task. Remove temptations proactively.
## 6. Use Timers Visually
Abstract time is hard for kids with ADHD to grasp. Visual timers that show time "running out" make the abstract concrete.
"You have 10 minutes" means little. Watching a timer countdown means something.
## 7. Celebrate Small Wins
Positive reinforcement works better than criticism. Notice when things go well, even partially.
"You got dressed without a reminder today, that's awesome!" builds motivation for tomorrow.
## The Bigger Picture
Morning struggles aren't character flaws, they're executive function challenges. With the right supports, kids with ADHD can learn to navigate mornings successfully.
Consistency, visual supports, and patience are your best tools.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create visual morning routines customized for your child. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring calm to your mornings.
---
## How AI-Generated Images Transform Visual Supports for Neurodivergent Children
Published: 2025-01-11 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/ai-generated-images-visual-supports
Category: Technology
Author: Justin Bowman
> Discover how AI image generation creates personalized visual supports that help children see themselves succeeding in their daily routines.
You downloaded the free visual schedule printable. You laminated it, hung it on the wall, and waited for the magic to happen. Your child glanced at it once and never looked at it again. The generic clip art kid brushing their teeth looked nothing like your child. The cartoon bedroom looked nothing like their room. And somewhere in the gap between those stock images and your child's actual life, the whole system fell apart.
You are not imagining the disconnect. Research consistently shows that personalized visual supports outperform generic ones, and now AI-generated images are closing that gap in ways that were impossible just a few years ago.
## The Limitation of Generic Visual Supports
Traditional visual supports typically rely on stock images, clip art, or generic illustrations. While these can be helpful, they often have significant limitations.
**They may not look like your child.** A visual schedule showing a generic cartoon child brushing teeth may not resonate with a child who looks nothing like that image.
**They may not show your actual environment.** Images of a generic bathroom or kitchen do not prepare a child for their specific surroundings.
**They may not match your routines.** Stock images of breakfast might show foods your family never eats, creating disconnect between the visual and reality.
**They may not represent your child's interests.** Generic images cannot incorporate the specific characters, themes, or interests that motivate your particular child.
For children who are concrete thinkers, as many autistic children are, these disconnects can significantly reduce the effectiveness of visual supports.
## What AI Image Generation Offers
AI image generation technology creates custom images based on text descriptions. For visual supports, this means the ability to create images that:
**Match your child's appearance.** Create images featuring a child who looks like your child, similar hair, skin tone, and features.
**Show your actual spaces.** Generate images that represent your home, your child's school, or specific locations you visit.
**Depict your specific routines.** Create images of exactly what your family does, how you do it, and in what order.
**Incorporate your child's interests.** Add favorite characters, colors, themes, or objects that increase engagement and motivation.
**Illustrate any scenario.** Whether you need an image for going to a new doctor, visiting grandma's house, or handling a fire drill, AI can create it.
## Why Personalization Matters
The research on visual supports consistently shows that personalization increases effectiveness. When children see themselves in the images, engagement and understanding improve.
**Recognition is easier.** A child more quickly recognizes and connects with an image that looks familiar rather than abstract.
**Abstract concepts become concrete.** Seeing themselves in an image makes the instruction feel real and achievable rather than theoretical.
**Emotional connection increases.** Children care more about visual supports that feel personal to them.
**Generalization is supported.** When images match real environments, skills learned through visual supports transfer more easily to actual situations.
**Self-identity is affirmed.** Seeing themselves represented in their tools sends a message that they matter and belong.
## Practical Applications of AI-Generated Visuals
The possibilities for AI-generated visual supports extend across many areas of daily life.
**Morning and bedtime routines** can feature images of your child's actual bedroom, bathroom, and the specific steps in your family's routine.
**School preparation** might include images of your child's school building, classroom, teacher, and school-day activities.
**New experience preparation** can show the specific doctor's office, restaurant, or vacation destination your child will visit.
**Emotional regulation tools** can feature your child using specific coping strategies in situations where they typically struggle.
**Social stories** come alive when the child in the story looks like your child and the settings match their world.
**First-Then boards** become more motivating when both the "First" and "Then" images feel relevant and real.
## Getting the Best Results
When using AI image generation for visual supports, several strategies improve outcomes.
**Be specific in descriptions.** Rather than "a child eating breakfast," describe "a 7-year-old girl with brown curly hair eating pancakes at a round wooden table."
**Include relevant details.** If your child always wears glasses, mention that. If they have a favorite shirt they wear constantly, include it.
**Consider the background.** The setting matters. Describe whether the scene is indoors or outdoors, what room it is in, and any relevant details.
**Match the style to your child's preferences.** Some children respond better to realistic images, others to cartoon-style or illustrated looks. Experiment to find what works.
**Keep it clear and simple.** Busy, complex images can be overwhelming. Request clean, simple images that clearly communicate one idea.
## Integrating AI Images Into Your Visual Systems
Once you have custom images, integrate them thoughtfully into your visual support systems.
**Replace generic images gradually.** You do not need to overhaul everything at once. Start with the visual supports your child uses most frequently.
**Maintain consistency.** Once you establish a visual style that works, maintain it across different supports so your child has a cohesive visual language.
**Update as needed.** As your child grows, their appearance changes, their interests shift, and their needs evolve. Update images to keep them current and relevant.
**Create a library.** Build a collection of custom images that can be reused across different visual supports, the same image of your child brushing teeth can appear in morning routine charts, bathroom visuals, and dental preparation stories.
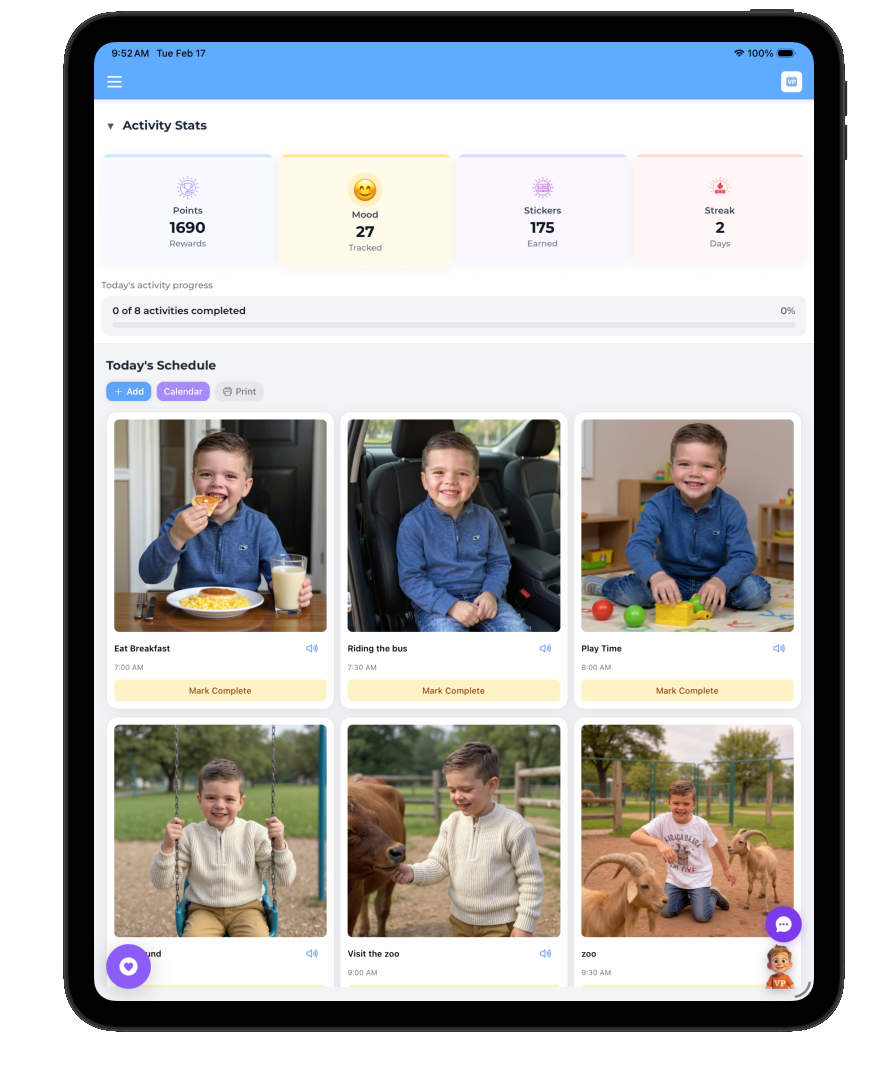
## Beyond Individual Images
AI image generation enables not just individual images but comprehensive visual systems.
**Sequential routine images** can show your child at each step of a multi-step routine, creating a visual narrative they can follow.
**Emotion scales** can feature your child's face showing different emotions, helping them identify their own feelings.
**Choice boards** can show actual options available to your child, their real toys, their real snack options, their real activity choices.
**Social narratives** can tell complete stories with consistent characters that look like the people in your child's life.
## Accessibility and Equity
AI-generated images address a long-standing problem in visual supports: representation.
**Diverse representation.** Children from all backgrounds can now see themselves in their visual supports, regardless of race, ethnicity, or physical characteristics.
**Disability representation.** Images can include mobility aids, hearing devices, glasses, and other assistive technology that are part of your child's daily life.
**Family representation.** Images can reflect your family structure, whatever that looks like, single parents, same-sex parents, grandparent caregivers, and more.
**Cultural representation.** Clothing, foods, celebrations, and environments can reflect your family's cultural background and practices.
## Privacy Considerations
When using AI image generation, consider privacy and consent.
**You do not need actual photos.** AI generates new images based on descriptions, you do not need to upload photographs of your child.
**Control over sharing.** Images you create remain yours to use as you choose, without your child's actual image being stored elsewhere.
**Age-appropriate decisions.** As children grow, involve them in decisions about how they are represented in their visual supports.
## The Future of Personalized Visual Supports
AI technology continues to evolve rapidly. Current capabilities are just the beginning.
**Increasing realism** will make generated images even more recognizable and effective.
**Easier creation** will make the technology accessible to more families.
**Better integration** with other tools will create seamless visual support systems.
**More customization options** will allow for even more precise personalization.
---
[VizyPlan](https://vizyplan.com) uses AI to generate personalized images that help your child see themselves succeeding. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and experience the power of truly personalized visual supports.
---
## Creating a Happy Place: Mindfulness and Calm Strategies for Neurodivergent Children
Published: 2025-01-10
URL: https://vizyplan.com/blog/happy-place-mindfulness-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Help your child build an internal sanctuary through visualization, mindfulness, and personalized calm-down strategies that work for their unique brain.
The meltdown is building. You can see it in their eyes, the overwhelm rising like a wave. You are in the middle of a grocery store, or a classroom, or a family dinner, and there is no calm-down corner, no weighted blanket, no escape route. But what if your child could close their eyes and go somewhere safe in an instant?
That is the power of a "Happy Place," a personalized mental sanctuary that neurodivergent children can access anywhere, anytime, no tools required. It is one of the most portable self-regulation strategies that exists, and it can be taught at any age.
## What Is a Happy Place?
A Happy Place is a personalized mental sanctuary, a calm, safe space that a child can visualize and mentally "visit" when they need to regulate their emotions. Unlike physical calm-down corners (which are also valuable), a Happy Place exists in the imagination and is therefore always accessible.
**The Happy Place might be:**
- A favorite real location (grandma's house, a beloved beach, their bedroom)
- An imaginary space (a cloud castle, an underwater world, a magical forest)
- A fantasy environment based on interests (inside a favorite video game, on a spaceship, in a dinosaur world)
The key is that it feels safe, calm, and personally meaningful to the child.
## Why Visualization Works for Neurodivergent Children
While mindfulness and visualization are sometimes assumed to be difficult for neurodivergent children, with proper adaptation, they can be remarkably effective.
**Visual thinking is a strength.** Many autistic children are highly visual thinkers. Visualization leverages this strength rather than fighting against it.
**Concrete imagery helps abstract concepts.** The abstract idea of "calming down" becomes concrete when associated with a specific visualized place.
**Special interests provide engagement.** When the Happy Place incorporates a child's intense interests, engagement and motivation increase significantly.
**It provides control.** Children who feel out of control in the real world can have complete control over their imaginary space.
**Portable regulation.** Unlike physical tools that might not always be available, a Happy Place travels with the child.
## Building the Happy Place
Creating a Happy Place is a process best done during calm moments, not during distress. Take time to build it thoughtfully with your child.
**Start with what feels safe.** Ask your child where they feel most calm, safe, and happy. This might be a real place or somewhere imagined.
**Add sensory details.** What do they see in their Happy Place? What colors? What sounds? What does it feel like? What do they smell? Building rich sensory details makes the visualization more immersive.
**Include comfort elements.** Are there favorite toys, pets, people, or characters in the Happy Place? Who or what would help them feel calm?
**Let them have control.** In their Happy Place, they make the rules. They decide what exists there and what happens.
**Create a visual representation.** Draw, paint, or create a digital image of the Happy Place. This physical representation helps cement the concept and can serve as a reminder.
## Teaching the Visualization Process
Once the Happy Place is established, children need to learn how to access it.
**Practice when calm.** The first many times visiting the Happy Place should happen during relaxed moments, not crises. This builds the neural pathways.
**Guide the journey.** Walk through the visualization with your child: "Close your eyes. Take a deep breath. Now imagine you're walking toward your Happy Place. What do you see as you get closer?"
**Engage all senses.** Prompt them to notice what they see, hear, feel, and smell in their Happy Place. Multi-sensory engagement deepens the experience.
**Establish an entrance ritual.** Having a consistent way to "enter" the Happy Place creates a helpful routine, maybe three deep breaths, or a specific phrase, or imagining opening a door.
**Keep initial sessions short.** One to two minutes is plenty at first. Duration can increase as the skill develops.
## Adapting for Different Needs
Not every child will connect with traditional visualization approaches. Adaptations make this tool accessible to more children.
**For children who struggle to close their eyes:** They can look at a picture of their Happy Place instead of visualizing with eyes closed.
**For children who need movement:** The Happy Place can include imagined movement, flying, swimming, swinging, that provides mental proprioceptive input.
**For children who are highly concrete:** The Happy Place can be a real location they know well, with minimal imagined elements.
**For children with limited language:** Build the Happy Place primarily through drawing, crafting, or pointing at pictures rather than verbal description.
**For children who resist adult direction:** Let them lead the entire process, creating their Happy Place with minimal input from you.
## Complementary Calm Strategies
The Happy Place works best as part of a broader toolkit of calm strategies. Consider combining it with:
**Breathing exercises.** Simple breathing techniques can serve as the "entrance" to the Happy Place or complement it during use.
**Sensory tools.** Physical fidgets, weighted items, or comfort objects can be used while mentally visiting the Happy Place.
**Movement breaks.** For children who need to move, gentle stretching or rocking while visualizing combines physical and mental regulation.
**Counting and grounding.** Techniques like counting objects or using the 5-4-3-2-1 senses exercise can precede or follow Happy Place visits.
**Music or sounds.** Some children benefit from calm music or nature sounds while practicing visualization.

## Using the Happy Place During Distress
Once the Happy Place is well-established through practice, it can be accessed during difficult moments.
**Catch early signs.** The Happy Place is most effective when accessed before full dysregulation. Help your child recognize early warning signs.
**Offer it as an option.** "Would you like to visit your Happy Place?" is better than "Go to your Happy Place!" Demands rarely help during distress.
**Provide scaffolding as needed.** Some children can self-guide; others need you to talk them through it even after much practice.
**Do not force it.** If the child is too dysregulated to visualize, try other strategies first and return to the Happy Place later.
**Debrief afterward.** Once calm returns, briefly acknowledge: "Your Happy Place helped you feel better." This reinforces the tool.
## Building Independence
The ultimate goal is for children to access their Happy Place independently when needed.
**Create reminders.** A small picture of the Happy Place in their pocket, on a keychain, or in their desk reminds them this tool exists.
**Practice in different settings.** Practice using the Happy Place at home, at school, in the car, anywhere they might need it.
**Role-play scenarios.** "Imagine you're at school and feeling overwhelmed. What could you do?" Practice makes access more automatic.
**Celebrate independent use.** When your child uses their Happy Place without prompting, acknowledge it: "I noticed you took a breath and got calm. Did you visit your Happy Place?"
**Fade your support gradually.** Move from guiding the visualization to simply prompting it to simply noticing when they use it independently.
## Beyond the Happy Place
The skills learned through Happy Place visualization transfer to other areas.
**General visualization skills** can help with test anxiety, performance situations, and imagining successful outcomes.
**Body awareness** developed through sensing the calm of the Happy Place helps with recognizing stress earlier.
**Self-advocacy** grows as children learn to say "I need a moment" and use their internal tools.
**Resilience** builds as children experience repeatedly that they can move from distress to calm through their own actions.
## Digital Tools for Happy Place Creation
Technology offers new ways to build and access Happy Places.
**Digital design tools** let children create visual representations of their Happy Place that can be viewed on any device.
**Guided meditation apps** designed for children can support visualization practice.
**Personalized image generation** can create images of the Happy Place that match what the child imagines.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s Happy Place feature lets children create personalized calm spaces with images, colors, and elements they choose, available anytime they need to reset.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps your child build a personalized Happy Place and access calming tools whenever they need them. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and bring more calm to your family's daily life.
---
## Using Points and Rewards to Motivate Neurodivergent Children
Published: 2025-01-09 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/points-rewards-motivation-neurodivergent
Category: Strategies
Author: Justin Bowman
> Learn how to create effective reward systems that motivate your child, build positive habits, and celebrate progress without creating dependency.
You have asked six times. You have pleaded, bribed with dessert, threatened to cancel screen time, and now you are standing in the hallway wondering why your child will not just put on their shoes. The thing that takes other kids 30 seconds has become a 20-minute standoff, and you are running out of ideas.
Here is what is happening: your child's brain is not wired to connect "put on shoes now" with "we will have fun at the park later." The dopamine system that drives motivation in ADHD and autistic brains works differently, and understanding that difference is the key to building reward systems that actually work.
## Understanding Motivation in Neurodivergent Children
Before implementing any reward system, it helps to understand why motivation works differently for many neurodivergent children.
**Executive function challenges** make it hard to connect current effort with future benefits. A reward that comes immediately is more motivating than a grade on a report card months away.
**Dopamine differences** in ADHD brains mean that interest-based motivation is stronger than importance-based motivation. Points and rewards add an element of interest to otherwise unengaging tasks.
**Difficulty with abstract rewards** makes concrete, visible reward systems more effective than vague promises.
**Need for predictability** means children do better when they know exactly what they need to do to earn a reward.
**Intense interests** can be leveraged, rewards connected to special interests are exponentially more motivating than generic rewards.
## Principles of Effective Reward Systems
Not all reward systems work equally well. These principles increase the likelihood of success.
**Make it visual.** Points on a chart, tokens in a jar, or digital tracking that children can see makes progress tangible and motivating.
**Keep it simple.** Complex systems with multiple levels, conditions, and exceptions are hard to follow. Clear, straightforward systems work better.
**Ensure success is achievable.** If children rarely earn rewards, they give up. The system should be calibrated so success happens regularly.
**Provide immediate feedback.** The shorter the gap between behavior and reward, the stronger the connection. Digital systems that update instantly have an advantage here.
**Include choice.** When children choose their rewards, motivation increases. A menu of options is more effective than a single predetermined reward.
**Be consistent.** The rules should be clear and applied consistently. Unpredictability undermines trust in the system.
## Types of Rewards That Work
Different rewards motivate different children. Consider what actually matters to your child, not what you think should matter.
**Activity rewards:** Extra screen time, a special outing, playing a favorite game, choosing the family movie, staying up 15 minutes later.
**Tangible rewards:** Small toys, collectibles related to special interests, stickers, art supplies, favorite snacks.
**Social rewards:** One-on-one time with a parent, inviting a friend over, video calling a grandparent, choosing where to go for dinner.
**Privilege rewards:** Sitting in the front seat, making a decision for the family, getting to be first in line, choosing the day's breakfast.
**Sensory rewards:** Time with favorite sensory items, a special bath with bubbles, wearing a favorite outfit, visiting a sensory-friendly location.
**Interest-based rewards:** Anything connected to your child's special interests, these are often the most powerful motivators of all.
## Setting Up a Points System
A well-designed points system has several components working together.
**Define what earns points.** Be specific. "Being good" is too vague. "Completing morning routine by 7:30," "Using words instead of whining," or "Putting dishes in the sink after meals" are specific and measurable.
**Assign point values thoughtfully.** Harder tasks or behaviors you especially want to encourage might earn more points. This helps children prioritize.
**Establish clear rewards and costs.** Children should know exactly how many points they need for each reward. Posting this visibly helps.
**Choose an appropriate scale.** Small numbers (1-10 points) work for younger children or when rewards come frequently. Larger numbers work for longer-term goals with older children.
**Decide on frequency.** Some children do better cashing in points daily; others can work toward bigger weekly rewards. Match the system to your child's needs.
## Implementing the System
How you introduce and maintain the system matters as much as how it is designed.
**Introduce it positively.** Frame the system as a way to earn fun things, not as a punishment system. "I wanted to create a way for you to earn some of the things you love!"
**Start easy.** In the first days, make points relatively easy to earn so your child experiences success and buys into the system.
**Give immediate points.** When your child earns points, acknowledge it right away. "You just earned 5 points for putting your shoes on by yourself!"
**Track visibly.** Whether on a chart, app, or token board, the child should be able to see their progress at any time.
**Celebrate redemptions.** When your child cashes in points for a reward, make it feel good. This reinforces the value of the system.
**Review and adjust.** No system is perfect from the start. Check in regularly about what is working and what needs tweaking.
.png)
## Common Challenges and Solutions
Even well-designed systems encounter obstacles. Here are common challenges and how to address them.
**"My child is not motivated by any rewards."** Dig deeper into their interests. Sometimes the rewards need to be more specific or connected to special interests. Also consider whether the required effort is too high for the reward offered.
**"They want to renegotiate constantly."** Set clear boundaries at the outset about how and when changes can be made. "We can discuss changes to the system on Sundays, but not during the week."
**"They earn points but never redeem them."** Some children become hoarders. This is fine unless it causes problems. If needed, set a maximum balance or create time-limited rewards.
**"The system is creating arguments."** Clarify the rules and put them in writing. If arguments persist, the system may need to be simplified or the child may need more involvement in designing it.
**"Siblings complain it is unfair."** Different children may need different systems. It is okay to explain that everyone gets what they need, and what one person needs is not always what another needs.
**"We forget to give points."** Use reminders, make tracking easy, or tie point-giving to existing routines. Consistency is crucial for the system to work.
## Avoiding Pitfalls
Some approaches backfire. Avoid these common mistakes.
**Do not take away earned points as punishment.** Points earned should stay earned. Losing points undermines trust and motivation. Use separate consequences for misbehavior.
**Do not make rewards impossible to reach.** If the goal feels unattainable, children stop trying. Adjust the system to ensure regular success.
**Do not use it for everything.** Not every behavior needs to be part of the point system. Focus on a few key behaviors rather than tracking every aspect of life.
**Do not use it during meltdowns.** In moments of dysregulation, point systems will not help and may make things worse. These are tools for building skills, not crisis management.
**Do not compare to siblings.** Each child's system should be about their own progress, not competition with others.
## Transitioning and Fading
Reward systems are ideally scaffolds, not permanent fixtures. Over time, the goal is for behaviors to become habitual and for intrinsic motivation to develop.
**Thin the reinforcement gradually.** Once a behavior is consistent, you might move from points every time to points sometimes, or make the behavior expected rather than rewarded.
**Celebrate growth.** When a behavior no longer needs points, acknowledge the accomplishment. "You've been putting your dishes away every day without reminders. I'm so proud of you, you don't need points for that anymore!"
**Add new challenges.** As some behaviors become routine, the point system can shift focus to new skills or behaviors your child is working on.
**Follow your child's lead.** Some children naturally lose interest in the system as behaviors become automatic. Others benefit from point systems longer. There is no shame in using helpful tools.
## Digital Point Systems
Technology offers advantages for tracking and managing reward systems.
**Easy tracking** eliminates lost charts and forgotten marks.
**Immediate updates** provide instant feedback when points are earned.
**Engaging interfaces** with visual displays, animations, and progress indicators increase motivation.
**Flexibility** to adjust point values, add rewards, and modify the system as needed.
[VizyPlan](https://vizyplan.com) includes a points and rewards system that makes tracking progress visual and fun, with a rewards store where children can see what they are working toward.
---
[VizyPlan](https://vizyplan.com) helps you create motivating reward systems with visual point tracking, a customizable rewards store, and Visual Routines and Planning that tie it all together. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and celebrate your child's progress.
---
## Collaborating with Providers: Using Visual Tools for IEP Meetings and Therapy
Published: 2025-01-08
URL: https://vizyplan.com/blog/provider-collaboration-iep-preparation
Category: Strategies
Author: Justin Bowman
> Learn how to leverage visual documentation, progress tracking, and collaborative tools to strengthen partnerships with your child's therapists, teachers, and care team.
You just sat through an IEP meeting where the therapist said your child is "making great progress," but at home you are seeing the opposite. The teacher describes a completely different kid than the one you live with. And the behavioral specialist is recommending strategies that contradict what the OT told you last week. Everyone is supposedly on the same team, but nobody seems to be reading the same playbook.
This is one of the most frustrating realities of raising a neurodivergent child: the team that is supposed to help your kid often struggles to communicate with each other, let alone with you. The good news is that the right documentation and visual tools can change that entirely.
## The Challenge of Team-Based Care
When multiple providers support your child, coordination challenges inevitably arise.
**Information silos** develop when each provider has partial information about your child, seeing only what happens in their sessions or classroom.
**Inconsistent approaches** occur when different providers use different strategies, potentially confusing your child or undermining progress.
**Missed progress** happens when wins in one setting are not communicated to other team members who might build on them.
**Parent overwhelm** results from trying to be the communication hub for an entire team while also managing daily life.
**Meeting unpreparedness** leads to IEP meetings, therapy reviews, and medical appointments that do not result in the best outcomes for your child.
## The Power of Visual Documentation
Visual documentation provides concrete evidence that words alone cannot convey.
**Progress photos and videos** show skills in action. A short video of your child completing a routine independently is more compelling than describing it.
**Visual schedules and charts** used at home demonstrate the structures that support your child's success, allowing providers to implement similar approaches.
**Data visualizations** of behavior patterns, sleep, eating, or other tracked information reveal trends that might otherwise be missed.
**Before and after comparisons** powerfully demonstrate growth over time when you document the starting point and current state.
**Work samples** whether academic, artistic, or skill-based, provide tangible evidence of what your child can do.
## Preparing for IEP Meetings
IEP (Individualized Education Program) meetings are high-stakes conversations that shape your child's educational experience. Preparation makes them more productive.
**Gather documentation in advance.** Collect visual evidence of your child's abilities and challenges at home. What can they do that the school may not have seen? What difficulties occur that you want addressed?
**Organize your priorities.** What are the most important goals for the coming year? Visual supports can help you communicate these clearly, show what you're working toward.
**Create a parent input document.** Schools often focus on their assessments. Coming with organized observations and data gives your perspective equal weight.
**Prepare visual examples.** If you want a particular accommodation or support, showing how it works at home is more persuasive than just describing it.
**Track progress toward current goals.** If your child has made progress on existing IEP goals, bring documentation. If progress is insufficient, bring that evidence too.
## Sharing Information with Therapists
Therapists, speech-language pathologists, occupational therapists, behavioral therapists, and others, do their best work when they understand your child fully.
**Share what works at home.** When you discover strategies that help your child, document them visually and share with providers. What works in one setting may transfer to others.
**Report on carryover.** Therapists need to know whether skills practiced in sessions are appearing at home. Visual logs or quick notes help track this.
**Communicate about challenges.** If a particular skill is difficult at home despite progress in therapy, sharing specific examples helps the therapist adjust their approach.
**Provide context about daily life.** Therapists may not know what your mornings look like or how homework goes. Sharing visual routines and documentation helps them understand the full picture.
**Ask for visual resources.** Many therapists can provide visual supports, social stories, or picture-based materials that extend therapy work into the home.
## Creating Consistent Approaches Across Settings
When home and school or therapy use similar approaches, children learn faster and generalize skills more successfully.
**Share your visual systems.** If your visual schedule format works at home, share it with teachers and therapists. Consistency in format reduces cognitive load for your child.
**Request information about school approaches.** What visual supports does the classroom use? Can you implement similar ones at home to create continuity?
**Agree on common language.** If therapists use specific terms or phrases, use the same language at home. If your child calls something by a particular name, share that with providers.
**Coordinate on goals.** When everyone works on the same skills, progress accelerates. Regular communication ensures alignment.
**Document what each setting is doing.** Keeping track of approaches used in different settings helps identify what is consistent and what varies.
## Tools for Ongoing Communication
Beyond formal meetings, ongoing communication keeps the team coordinated.
**Shared digital records** allow everyone to see progress, notes, and data. With appropriate privacy protections, shared access reduces communication burden.
**Regular update exchanges** even brief weekly updates between home and key providers maintain connection without requiring meetings.
**Quick video shares** can capture a skill demonstration, a challenging moment, or a strategy in action in seconds, worth much more than a written description.
**Standardized reporting formats** make it easy to provide information providers need without recreating documentation for each one.
**Communication logs** track what was shared with whom, creating a record that prevents information from falling through the cracks.
.png)
## Advocating Effectively
Sometimes collaboration requires advocacy, pushing for services, supports, or accommodations your child needs.
**Lead with evidence.** Visual documentation of challenges and needs is more persuasive than assertions alone.
**Show what works.** When you are requesting a specific support, demonstrating how it works at home strengthens your case.
**Know your rights.** Familiarize yourself with special education law and your child's entitlements. Visual organization of this information helps you reference it quickly.
**Document meetings.** Keep records of what was discussed and agreed upon. If possible, record meetings where permitted.
**Build relationships.** Advocacy is easier when you have established collaborative relationships with providers. Documentation of your engagement demonstrates partnership.
## Using Technology for Collaboration
Digital tools streamline the collaboration process.
**Shared apps and platforms** allow multiple care team members to see the same information, reducing the need for repeated updates.
**Cloud-based storage** keeps visual documentation organized and accessible from anywhere.
**Progress tracking features** automatically compile data over time, creating reports suitable for sharing with providers.
**Secure communication tools** allow sharing of sensitive information about your child safely.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) includes provider tools designed specifically for this purpose, session notes, goal tracking, strategy documentation, and progress insights that can be shared with your child's care team.
## Involving Your Child
When appropriate, involving your child in collaboration with providers has significant benefits.
**Self-advocacy skills** develop when children learn to communicate their own needs, preferences, and experiences.
**Ownership increases** when children understand their goals and participate in tracking progress toward them.
**Valuable perspective** comes from the child themselves, they know things about their experience that adults may miss.
**Dignity is preserved** when children are partners in their own support rather than subjects of adult conversations.
Visual supports make this involvement more accessible, children can point to pictures, track their own progress on charts, and participate in goal-setting using visual tools.
## Building Long-Term Systems
The most effective collaboration systems are sustainable over time.
**Start simple.** You do not need perfect systems immediately. Begin with basic documentation and build from there.
**Make it routine.** Build documentation into your regular activities rather than treating it as a separate task.
**Choose tools that work for you.** The best system is one you will actually use. Experiment with different approaches.
**Review and refine.** Periodically assess what is working and what needs adjustment in your collaboration systems.
**Share what works.** When you find effective approaches, share them with other families navigating similar journeys.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) includes tools designed for provider collaboration, goal tracking, session notes, and progress insights that keep your whole care team aligned. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and strengthen your partnership with your child's providers.
---
## Building Independence: Helping Your Child Do More on Their Own
Published: 2025-01-07
URL: https://vizyplan.com/blog/building-independence-visual-supports
Category: Strategies
Author: Justin Bowman
> Discover how to use visual supports to help your neurodivergent child develop independence in daily tasks while building confidence and reducing dependence on prompts.
Your seven-year-old still needs you to walk them through every step of getting dressed. Your ten-year-old cannot make a sandwich without forgetting half the steps. You catch yourself doing things for your child that their peers do alone, and you wonder: will they ever be able to do this on their own?
They will. But the path to independence for neurodivergent children looks different. It requires more explicit teaching, more visual supports, and more patient scaffolding than the parenting books describe. The reward, a child who manages parts of their day with genuine confidence, is worth every step.
## Why Independence Matters
Independence is about more than convenience for parents. For children, developing independence builds self-esteem, reduces anxiety, and prepares them for the increasing demands of school, community, and eventually adult life.
**Confidence grows with capability.** Every skill a child masters becomes proof that they can learn and succeed. This builds a foundation for tackling future challenges.
**Anxiety decreases with competence.** Children who know they can handle tasks feel less anxious about facing them. Dependence on others, conversely, can increase anxiety.
**Self-advocacy develops.** Children who practice independence learn what they can do, what they need help with, and how to communicate about both.
**Future success is built now.** The independent skills children develop in childhood become the foundation for adult functioning.
## Common Barriers to Independence
Understanding what stands in the way of independence helps target interventions effectively.
**Executive function challenges** make it hard to initiate tasks, remember sequences, and manage the multiple steps that independence requires.
**Processing differences** may mean children can do tasks but take longer or need information presented differently.
**Sensory sensitivities** can make certain independent tasks uncomfortable or overwhelming without accommodations.
**Anxiety about failure** may lead children to avoid trying things independently, preferring the safety of adult help.
**Well-meaning over-helping** from adults who do things for children rather than teaching them to do things themselves.
## The Power of Visual Task Analysis
Breaking tasks into small, visual steps is fundamental to building independence.
**Task analysis means identifying every step.** What adults do automatically involves many small steps. Brushing teeth includes getting the toothbrush, getting the toothpaste, removing the cap, applying toothpaste, wetting the brush, and more.
**Visual representation removes memory burden.** When steps are visible, children do not have to hold the sequence in working memory, they just follow what they see.
**Consistent sequences build automaticity.** When the same steps happen in the same order every time, the routine eventually becomes automatic.
**Self-checking becomes possible.** Children can compare what they have done to what the visual shows, rather than depending on adult feedback.
## Starting Points for Building Independence
Choose starting points strategically rather than trying to build independence in everything at once.
**Start with motivated tasks.** Independence in getting a snack or starting a preferred activity often comes more easily than independence in non-preferred tasks.
**Choose tasks with clear endpoints.** Tasks that have an obvious "done" are easier to master than ongoing or ambiguous tasks.
**Select developmentally appropriate targets.** Match expectations to your child's current capabilities plus a small stretch.
**Consider safety and natural consequences.** Some tasks allow natural learning from mistakes; others require more supervision during the learning process.
## Creating Effective Visual Supports for Independence
Not all visual supports are equally effective. Design matters.
**Use images your child understands.** Photos, drawings, or icons, whatever your child processes most easily.
**Show one step per image.** Combining multiple steps in one image creates confusion and defeats the purpose.
**Place visuals where tasks happen.** The handwashing visual belongs at the sink, not across the room.
**Make them durable and accessible.** Laminated cards, waterproof materials, or digital displays that will not be destroyed with use.
**Update as skills develop.** As children master steps, supports can be simplified or combined.
## The Prompting Hierarchy
Moving from dependence to independence requires systematic fading of support.
**Physical prompts** involve hand-over-hand guidance through a task. This is the most supportive and should be faded first.
**Modeling** shows the child what to do without physical contact. "Watch me do it, then you try."
**Gestural prompts** point or gesture toward what comes next without modeling the entire action.
**Verbal prompts** tell the child what to do. These are often overused and hard to fade.
**Visual prompts** (the schedule or task analysis) should be the last prompt standing, children can use these independently.
**Independence** means completing the task with only the visual support, which they access themselves.
## Fading Support Systematically
Moving down the prompting hierarchy requires intentional practice.
**Fade from most intrusive to least.** Physical prompts fade before verbal, verbal before gestural, gestural before visual.
**Fade within prompt types.** Full hand-over-hand fades to light touch, which fades to touch at the elbow, which fades to no touch.
**Wait before prompting.** Give children processing time. Jumping in too quickly creates prompt dependence.
**Celebrate independence at each level.** Recognition of progress motivates continued effort.
.png)
## Building Independence in Morning Routines
Morning routines offer an excellent opportunity for independence building.
**Create a visual sequence** showing every step from waking to leaving. Position it where your child can see and access it independently.
**Prepare the night before.** Clothes laid out, backpack packed, and breakfast items ready reduce the cognitive load of morning decisions.
**Build in extra time.** Rushing undermines independence. Children doing things themselves take longer than adults doing things for them.
**Start with one section.** Perhaps just getting dressed independently, then expand from there.
**Resist the urge to help.** It is faster to tie shoes yourself, but every time you do, you delay your child learning to do it.
## Building Independence in Self-Care
Hygiene and self-care tasks involve many steps that can be systematically taught.
**Break down bathroom routines** into component parts. Handwashing alone might be six or more steps.
**Address sensory barriers.** If tooth brushing is difficult because of the toothpaste flavor, find an acceptable alternative. Solve sensory problems before expecting independence.
**Use timers for tasks with duration.** Visual timers show how long to brush teeth or wash hands when "long enough" is too abstract.
**Check but don't redo.** If your child washes their hands independently but imperfectly, resist the urge to rewash. Acknowledge the independence and work on thoroughness separately.
## Building Independence in Household Tasks
Contributing to household tasks builds competence and family belonging.
**Match tasks to abilities and interests.** A child who loves organizing might excel at sorting laundry. A child who enjoys water might be your dish-rinsing expert.
**Teach explicitly.** Demonstrate, practice together, then gradually step back. Do not assume children will figure out how to do tasks they have never been taught.
**Accept imperfection.** A child-folded towel may not be perfect. A child-made bed may be lumpy. Prioritize independence over perfection.
**Make tasks routine.** The same chore at the same time each day or week builds automaticity.
## Using Technology to Support Independence
Digital tools offer unique advantages for building independence.
**Visual schedules on tablets** are always available and can include audio or video supports.
**Timers and alarms** provide cues without parent involvement.
**Video modeling** shows tasks being completed, which children can watch and rewatch.
**Progress tracking** makes growth visible and celebrates achievement.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s visual routine builder creates customizable, accessible supports that travel with your child and grow with their developing independence.
## Common Mistakes to Avoid
Certain approaches undermine independence rather than building it.
**Over-prompting** creates children who wait for instructions rather than initiating.
**Impatience** leads to adults taking over, which teaches children that if they wait, help will come.
**Inconsistency** confuses children about what they are expected to do independently versus what will be done for them.
**All-or-nothing thinking** expects full independence rather than celebrating partial independence.
**Negative feedback** about imperfect attempts discourages future effort.
## Celebrating Progress
Recognition and celebration reinforce independent behavior.
**Notice and name independence.** "You got dressed all by yourself this morning, that's independence!"
**Track progress visually.** Charts showing growth over time motivate continued effort.
**Share successes.** Telling grandparents or teachers about new independent skills builds pride.
**Connect independence to benefits.** "Because you got ready so fast by yourself, we have time to play before school."
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create visual supports that build your child's independence one step at a time. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and watch your child's confidence grow.
---
## Supporting Sibling Relationships in Neurodivergent Families
Published: 2025-01-06
URL: https://vizyplan.com/blog/sibling-relationships-neurodivergent-families
Category: Strategies
Author: Justin Bowman
> Practical strategies for nurturing healthy sibling relationships when one or more children in the family are neurodivergent.
Your neurotypical child just whispered, "You always pay more attention to them." Your neurodivergent child is mid-meltdown, and their sibling is watching from the doorway with a look you cannot quite read. Is it fear? Resentment? Empathy? Maybe all three.
Sibling dynamics in neurodivergent families carry a weight that most parenting advice never addresses. The relationships are complex, sometimes strained, and often deeper than anyone outside the family can understand.
## The Sibling Experience
Siblings of neurodivergent children have experiences that shape them in profound ways. Understanding these experiences is the first step toward supporting healthy sibling relationships.
**They witness more than adults realize.** Siblings see meltdowns, hear difficult conversations, and observe their parents' stress, even when parents try to shield them.
**They may feel overlooked.** When one child requires more intensive support, siblings may feel their needs are secondary, even if this is not parents' intention.
**They often become helpers.** Many siblings naturally step into supportive roles, which can be positive but also burdensome if taken too far.
**They develop unique strengths.** Siblings of neurodivergent children often develop above-average empathy, patience, flexibility, and advocacy skills.
**They have complex feelings.** Love, frustration, protectiveness, embarrassment, pride, and resentment can coexist in siblings' hearts.
## Common Challenges in Sibling Relationships
Certain issues arise frequently in families with neurodivergent children.
**Unequal attention** is perhaps the most common complaint from neurotypical siblings. The child who needs more may get more, leaving siblings feeling like they matter less.
**Different expectations** can feel unfair. Why does their sibling get to skip chores, eat different food, or have different rules? Explaining this requires nuance.
**Disrupted activities** happen when family plans change due to a sibling's needs. Missed events, shortened outings, or cancelled activities build resentment.
**Peer relationships** may be affected when siblings feel embarrassed about their brother or sister's behavior in public or avoid inviting friends over.
**Physical safety** becomes a concern if a neurodivergent child sometimes becomes physically aggressive during meltdowns.
**Lack of typical sibling interaction** occurs when differences make it hard to play together, share interests, or communicate easily.
## Creating Individual Connection Time
One-on-one time with each child is essential and often the first thing to sacrifice when families are stretched thin.
**Schedule it intentionally.** If it is not on the calendar, it often will not happen. Regular, predictable one-on-one time tells children they are priorities.
**Let the child choose the activity.** During their special time, siblings should get to do what they want to do, not what is easiest for parents.
**Protect it fiercely.** Cancelling one-on-one time because something came up with the other child confirms siblings' fears that they come second.
**Quality over quantity.** Fifteen minutes of fully focused attention is more valuable than hours of distracted presence.
**Make it reliable.** Consistency matters more than duration. A child who knows they get Dad every Saturday morning builds trust in their importance.
## Teaching Siblings About Neurodivergence
Age-appropriate education helps siblings understand their brother or sister's differences.
**Use concrete, simple explanations.** "His brain works differently" is a starting point that can be expanded over time.
**Focus on how it affects what they see.** "That's why loud noises bother her so much" or "That's why he needs the schedule to stay the same."
**Normalize differences.** "Everyone's brain is a little different. Some people need glasses to see, some people need quiet to think."
**Answer questions honestly.** Siblings are often curious. Honest, age-appropriate answers build trust and understanding.
**Use books and resources.** Many children's books address having a neurodivergent sibling. These can open conversations and help siblings feel less alone.
## Addressing the Fairness Question
"It's not fair!" is a common refrain that deserves a thoughtful response.
**Acknowledge the feeling.** "You're right that it feels unfair sometimes" validates the emotion without denying reality.
**Reframe fairness.** Fair does not mean everyone gets the same, it means everyone gets what they need. A child who needs glasses gets glasses; a child who does not, does not.
**Point out what each child gets.** The sibling may have freedoms, activities, or allowances that the neurodivergent child does not have.
**Be honest about the limitations.** "I wish I had more time for just us. Let's make sure we protect our special time together."
**Check for legitimate concerns.** Sometimes complaints about fairness reveal real imbalances that need addressing.
## Supporting Positive Interactions
Help siblings build positive experiences with each other.
**Find common ground.** What interests, activities, or experiences can both children enjoy? Build on these shared spaces.
**Structure interactions.** Free play may not work well. Structured activities with clear rules and endpoints often go better.
**Teach interaction skills explicitly.** The neurodivergent child may need explicit teaching about how to play with their sibling. The neurotypical sibling may need strategies for communicating effectively.
**Supervise actively during early stages.** Be present to redirect, support, and help interactions succeed. Success breeds more attempts.
**Celebrate positive moments.** When siblings interact well, notice and acknowledge it. "You two are having so much fun together!"

## Creating Space and Boundaries
Siblings also need appropriate boundaries and personal space.
**Respect bedroom privacy.** Each child deserves a space that belongs to them, even if bedrooms are shared.
**Allow separate activities.** It is okay for siblings to do different things, have different friends, and have experiences without each other.
**Teach both children about boundaries.** The neurotypical sibling needs to respect their brother or sister's needs; the neurodivergent child needs to respect their sibling's belongings and space.
**Provide escape routes.** During meltdowns or difficult moments, siblings should have a designated safe space to go.
## Helping Siblings Manage Their Feelings
Siblings need space to process their own emotions about their family situation.
**Create safe spaces to vent.** Let siblings express frustration, sadness, or anger without judgment. "It's okay to feel frustrated. That doesn't mean you don't love your brother."
**Distinguish feelings from actions.** "You can feel angry. You cannot hit." This allows emotions while maintaining behavior standards.
**Watch for warning signs.** Anxiety, depression, social withdrawal, or acting out may indicate a sibling needs additional support.
**Consider sibling support groups.** Many communities offer support groups for siblings of special needs children. Connecting with peers who understand can be powerful.
**Provide professional support if needed.** Some siblings benefit from their own therapy to process their experiences and feelings.
## Avoiding Common Pitfalls
Certain well-intentioned approaches can backfire.
**Parentification** occurs when siblings take on too much caretaking responsibility. Children should help, not be responsible for, their sibling.
**Forced tolerance** of difficult behavior because "they can't help it" builds resentment. Boundaries and expectations should exist for everyone, even if they look different.
**Ignoring sibling complaints** by always defending the neurodivergent child dismisses legitimate concerns and builds resentment.
**Comparing children** in either direction damages both. Neither "Why can't you be patient like your sister?" nor "Why can't you behave like your brother?" helps anyone.
**Keeping siblings in the dark** about what is happening in their own family creates anxiety and distrust.
## Building Family Identity
Strong sibling relationships exist within strong family systems.
**Create family traditions** that include everyone, with accommodations as needed to make them work.
**Tell positive family stories.** "Remember when we all went to the beach and..." builds shared identity and positive memories.
**Present a united front.** Siblings should see parents working together to support all family members.
**Acknowledge the hard parts.** "Our family faces some challenges. We also love each other and figure things out together."
**Celebrate the family you are.** Pride in your family, with all its complexities, models acceptance for everyone.
## The Long View
Sibling relationships evolve over the lifespan.
**Childhood difficulties often improve.** Siblings who struggle to connect as children may develop closer relationships as they mature.
**Understanding deepens with age.** Older siblings often develop greater appreciation for their brother or sister's challenges and strengths.
**Adult siblings often become advocates.** Many neurotypical siblings channel their experiences into careers in education, therapy, advocacy, or related fields.
**Long-term thinking matters.** The sibling relationship may be the longest relationship in your child's life. Investing in it now pays dividends for decades.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps families create routines and structures that support all children. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and build a stronger family system.
---
## Choice Boards: Empowering Your Child to Make Decisions
Published: 2025-01-05
URL: https://vizyplan.com/blog/choice-boards-empowering-decisions
Category: Visual Supports
Author: Justin Bowman
> Learn how choice boards give neurodivergent children a voice, reduce power struggles, and build decision-making skills through visual options.
"What do you want for breakfast?" Silence. "Do you want eggs or cereal?" Still nothing. "How about pancakes?" A meltdown. You just asked a simple question, and somehow it became the hardest part of the morning.
For neurodivergent children, open-ended questions can feel paralyzing and even "this or that" verbal choices can overwhelm a brain already working overtime to process the day. Choice boards change the game entirely, replacing invisible verbal options with visible, concrete pictures your child can simply point to.
## What Are Choice Boards?
A choice board is a visual display showing available options that a child can select from. Rather than asking "What do you want to eat?" and waiting for a verbal response, you present a board showing pictures of available foods, and the child points to, touches, or otherwise indicates their choice.
**Choice boards can be physical or digital.** Printed boards with pictures, boards with velcro attachments, or tablet-based systems all serve the same purpose.
**They communicate what is actually available.** Unlike asking an open question, choice boards show concrete options that the child can actually have.
**They remove the language burden.** Children who struggle with word retrieval, verbal expression, or processing verbal questions can still communicate preferences.
**They provide visual processing time.** Looking at options gives children time to think without the pressure of someone waiting for a verbal response.
## Why Choice Boards Work
The effectiveness of choice boards stems from how they align with neurodivergent learning styles and needs.
**Reduced demand for language processing.** Receptive language challenges make verbal questions difficult. Visual options bypass this barrier.
**Concrete rather than abstract.** "What do you want?" is abstract. Pictures of specific options are concrete.
**Lowered anxiety.** Knowing the options are limited and defined reduces the stress of decision-making.
**Increased sense of control.** Having choices, even limited ones, gives children agency in their lives.
**Reduced power struggles.** When children feel they have a voice, resistance often decreases.
## Types of Choice Boards
Different situations call for different choice board formats.
**Simple two-choice boards** work well for children just starting with choice-making or for quick decisions. "Red shirt or blue shirt?"
**Category boards** show options within a specific category, snack choices, activity choices, toy choices.
**Schedule choice boards** let children choose the order of activities or select preferred activities to include in their day.
**Reward choice boards** display options for reinforcers, letting children select what they are working toward.
**Communication choice boards** support children in expressing needs, feelings, or requests throughout the day.
## Creating Effective Choice Boards
Design decisions significantly impact how well choice boards work for your child.
**Use images your child understands.** Photos, icons, drawings, or even words, whatever your child processes most easily.
**Include actually available options.** Never include an option you cannot or will not provide. This destroys trust in the system.
**Limit the number of options.** More is not better. Two to four options are often ideal. Too many choices overwhelms rather than empowers.
**Consider the visual layout.** Consistent placement helps children learn to scan and select efficiently.
**Make them durable.** Choice boards get handled frequently. Lamination, card stock, or digital formats prevent quick deterioration.
## Using Choice Boards Throughout the Day
Choice boards can support decision-making in many daily situations.
## Meal and Snack Time
Instead of asking what a child wants to eat, which may result in requests for unavailable items, verbal struggles, or "I don't know", present a board showing what is actually available.
**Breakfast options** might show cereal, toast, pancakes, or eggs.
**Snack boards** display the acceptable snack options for that time of day.
**Drink choices** help children select their beverage without verbal negotiation.
**Restaurant prep** can show menu items from a restaurant you are about to visit, allowing the child to decide before the pressure of ordering.
## Activity and Play Time
Open-ended free time can be overwhelming. Choice boards provide structure.
**Play activity boards** show available toys, games, or activities.
**Outdoor play options** might include swinging, sandbox, bikes, or sidewalk chalk.
**Screen time choices** display allowed apps, shows, or games.
**Art activity boards** show available craft projects or art supplies.
.png)
## Clothing and Getting Dressed
Morning battles over clothing often decrease when children have visual choices.
**Outfit choice boards** let children pick between two or three acceptable options.
**Weather-appropriate options** only show choices that suit the day's weather.
**Pajama choices** make bedtime smoother by offering selection within limits.
## Emotional Expression
For children who struggle to verbally express how they feel, choice boards provide a way to communicate emotional states.
**Feeling boards** display emotion faces, allowing children to point to how they feel.
**Need boards** show options like "I need a break," "I need help," or "I need a hug."
**Calm-down strategy boards** present options for regulation activities the child can choose.
## Common Implementation Challenges
Anticipating challenges helps you navigate them successfully.
**Child always chooses the same thing.** This is often fine, predictability is comforting. If variety is needed, rotate what appears on the board or use "one of these, then one of these" approaches.
**Child wants something not on the board.** Acknowledge the want, then redirect to available choices. "I know you want ice cream. These are the snacks we have right now. Which would you like?"
**Child refuses to choose.** Offer a "no choice" option, give more time, or make the choice for them with a cheerful "I'll pick this time." Remove pressure and try again later.
**Child removes or destroys board.** This may signal that choices feel overwhelming, the options are not motivating, or the child is not ready for this format. Simplify or pause and reassess.
**Other family members do not use the board consistently.** Everyone interacting with the child needs to use the same system. Inconsistency undermines effectiveness.
## Teaching Choice-Making Skills
Some children need explicit teaching to use choice boards effectively.
**Start with preferred vs. non-preferred.** Offer a choice between something the child loves and something they would never choose. This teaches the concept that pointing gets the selected item.
**Graduate to two preferred options.** Once the connection is made, offer two options the child would both enjoy.
**Add complexity gradually.** Increase the number of options, introduce new categories, and add less-preferred options only after the skill is established.
**Practice when stakes are low.** Build the skill during calm, low-pressure times before relying on it during difficult moments.
## Building Toward Greater Independence
Choice boards can be stepping stones to broader decision-making skills.
**Self-selection** eventually allows children to take choice boards themselves and make selections without adult presentation.
**Verbal bridging** may develop as children begin verbalizing their choices while pointing, building toward spoken requests.
**Expanded options** can gradually increase as children demonstrate the ability to handle more choices without overwhelm.
**Generalization** to new contexts happens as children learn that the skill of choosing applies everywhere, not just with familiar boards.
## Digital Choice Board Benefits
Technology offers advantages for choice board creation and use.
**Easy customization** allows adding new options, swapping images, and updating choices quickly.
**Portability** means choice boards travel on a phone or tablet, available anywhere.
**Audio support** can include options that play a sound or speak the choice name when selected.
**Data collection** in some apps tracks choices over time, revealing patterns and preferences.
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118)'s customizable features help you create visual choice boards that grow with your child and adapt to your family's needs.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you create personalized choice boards that empower your child's voice. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and reduce daily power struggles through the power of choice.
---
## Recognizing Triggers: How to Identify What Leads to Meltdowns
Published: 2025-01-04
URL: https://vizyplan.com/blog/recognizing-triggers-meltdowns-neurodivergent-children
Category: Strategies
Author: Justin Bowman
> Learn to identify the emotional, sensory, and situational cues that signal your child is heading toward a meltdown, and how to intervene before it escalates.
Meltdowns rarely come out of nowhere. For parents of neurodivergent children, what looks like a sudden explosion is often the final step in a chain of escalating signals that went unnoticed or unaddressed. Learning to recognize these triggers and early warning signs transforms reactive parenting into proactive support.
## The Anatomy of a Meltdown
Before we can prevent meltdowns, we need to understand what they actually are. A meltdown is not a tantrum, it is a neurological event that occurs when a child's nervous system becomes overwhelmed beyond its capacity to cope.
**Meltdowns happen when demands exceed capacity.** Every child has a threshold for what their nervous system can handle. When sensory input, emotional stress, cognitive demands, or physical needs push past that threshold, the brain essentially goes into crisis mode.
**The buildup is often invisible to adults.** What parents see is the explosion. What they often miss are the thirty minutes of accumulating stress that preceded it. Understanding this timeline is key to prevention.
**Recovery requires time and safety.** Once a meltdown begins, it must run its course. The goal shifts from prevention to minimizing harm and providing a safe space for recovery. This is why early recognition matters so much.
## Types of Triggers
Triggers generally fall into several categories. Most children have triggers across multiple categories, and triggers often interact and compound each other.
## Sensory Triggers
For many neurodivergent children, sensory input is the most common trigger category. What feels normal to neurotypical individuals can be genuinely painful or overwhelming for sensory-sensitive children.
**Auditory triggers** include loud noises, unexpected sounds, certain frequencies, overlapping conversations, and background noise that others might not notice.
**Visual triggers** include bright lights, flickering lights, visual clutter, certain colors, and rapid movement in the environment.
**Tactile triggers** include clothing textures, tags, seams, unexpected touch, certain food textures, and temperature extremes.
**Olfactory triggers** include strong smells, perfumes, cleaning products, certain foods cooking, and environments with unfamiliar scents.
**Vestibular and proprioceptive triggers** include feeling off-balance, certain movements, lack of movement when movement is needed, or insufficient deep pressure input.
## Emotional Triggers
Emotional experiences can quickly push children past their coping capacity.
**Disappointment and unmet expectations** happen when plans change, a desired outcome does not occur, or something does not match what the child anticipated.
**Perceived unfairness** is a powerful trigger, when children feel rules are applied inconsistently or that others receive better treatment.
**Frustration with tasks** builds when children cannot do something they are attempting, especially if they believe they should be able to do it.
**Social rejection or confusion** occurs when children feel excluded, misunderstand social situations, or experience peer conflict.
**Anxiety and fear** can accumulate throughout the day, reaching a breaking point that looks sudden but has been building for hours.
## Situational Triggers
Certain situations reliably increase the likelihood of meltdowns.
**Transitions** between activities require cognitive flexibility and often involve leaving preferred activities for less preferred ones.
**Unexpected changes** disrupt the predictability that many neurodivergent children depend on for regulation.
**High-demand situations** like school, social events, or activities requiring sustained attention deplete coping resources.
**End-of-day fatigue** means evenings are often harder than mornings, as children have used their coping capacity throughout the day.
**Hunger, thirst, and tiredness** are physical needs that directly impact emotional regulation capacity.
## Recognizing Early Warning Signs
Children typically display warning signs before reaching meltdown. Learning your specific child's signals allows for early intervention.
## Physical Warning Signs
Bodies often show stress before behavior escalates.
**Changes in movement** might include increased fidgeting, pacing, rocking, hand-flapping, or conversely, becoming unusually still.
**Facial expressions shift** as stress increases, tension in the jaw, furrowed brow, widened eyes, or a blank, "checked out" look.
**Breathing changes** become faster, shallower, or irregular as the nervous system activates.
**Skin color changes** may include flushing, pallor, or blotchiness as stress responses engage.
**Covering ears or eyes** signals sensory overwhelm and is often a child's attempt to reduce input.
## Behavioral Warning Signs
Behavior typically changes as children approach their threshold.
**Increased rigidity** shows in insistence on specific rules, order, or ways of doing things.
**Withdrawal from interaction** might look like turning away, avoiding eye contact, or seeking isolation.
**Repetitive questioning** or repeatedly making the same statement often indicates anxiety.
**Decreased frustration tolerance** means small things that normally would not bother your child suddenly become major issues.
**Seeking sensory input** through crashing, squeezing, or deep pressure may indicate attempts to self-regulate.
## Verbal Warning Signs
What children say, and how they say it, provides important information.
**Volume changes** in either direction, much louder or much quieter, can signal distress.
**Rate changes** where speech becomes much faster or slower than typical indicate nervous system activation.
**Content changes** such as more negative statements, catastrophizing, or repetitive phrases suggest escalating stress.
**Echolalia increases** in some children when stressed, returning to scripted or repeated phrases.
**Decreased verbal output** may mean the child is losing access to language as stress increases.

## Creating a Trigger Tracking System
Identifying patterns requires systematic observation over time.
**Keep a simple log** noting what happened before challenging moments. Include time of day, what was happening, who was present, and any sensory factors.
**Look for patterns** after collecting data for a few weeks. Do meltdowns cluster at certain times? After certain activities? With certain people present?
**Note what was happening in the hours before** the meltdown, not just the immediate trigger. Often the "last straw" is less important than the cumulative load.
**Include "near misses"** when your child almost had a meltdown but recovered. What helped them regulate? What was different?
**Involve your child** when developmentally appropriate. Some children can identify their own triggers with support.
## Environmental Modifications
Once triggers are identified, environment changes can prevent many meltdowns.
**Reduce sensory load** in spaces where your child spends significant time. Dimmer lights, reduced clutter, and noise management all help.
**Create predictability** through visual schedules, advance warnings about changes, and consistent routines.
**Build in regulation breaks** before children show signs of distress, not just after.
**Ensure basic needs are met** by maintaining regular meal times, adequate sleep, and hydration throughout the day.
**Plan for high-risk situations** by adding extra support during times you know are typically difficult.
## Teaching Self-Awareness
Helping children recognize their own warning signs builds long-term self-regulation skills.
**Use concrete language** like "I notice your fists are tight. That sometimes means your body is feeling frustrated."
**Create visual scales** that help children identify where they are on a calm-to-upset continuum.
**Practice during calm times** rather than during escalation. "Let's think about what your body feels like when you're getting upset."
**Celebrate self-awareness** when children identify their own states, even if they still need help with next steps.
**Link awareness to action** by connecting recognition of warning signs to specific coping strategies.
## Intervention Strategies for Different Stages
Different levels of escalation require different responses.
## Early Signs (Green Zone)
When you notice the first warning signs, gentle prevention is possible.
**Offer a sensory break** before asking if anything is wrong. Movement, deep pressure, or quiet time may be all that is needed.
**Reduce demands** by postponing non-essential tasks and simplifying what must happen.
**Use calm connection** through your presence, a gentle touch if welcome, or quiet company.
**Check basic needs** including hunger, thirst, temperature, and fatigue.
## Moderate Signs (Yellow Zone)
When warning signs increase, more active intervention is needed.
**Clearly reduce stimulation** by moving to a quieter space or reducing sensory input.
**Offer limited choices** that give your child a sense of control within safe boundaries.
**Use minimal language** as processing ability decreases with stress.
**Stay calm yourself** because your regulated presence helps your child regulate.
## High Alert (Red Zone)
When meltdown is imminent or occurring, focus on safety.
**Prioritize safety** by removing dangerous objects and ensuring physical space.
**Stop talking** beyond essential safety directions.
**Do not try to reason or teach** during this phase, the learning brain is offline.
**Wait it out** while staying present but not demanding interaction.
---
[VizyPlan](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) helps you track patterns and create visual supports that prevent meltdowns before they start. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and gain insights into your child's triggers.
---
## Preparing Your Neurodivergent Child for Doctor and Dentist Visits
Published: 2025-01-03 · Updated: 2026-05-12
URL: https://vizyplan.com/blog/preparing-doctor-dentist-visits-autism-adhd
Category: Strategies
Author: Justin Bowman
> Help your child feel prepared and reduce anxiety around medical appointments with visual supports, social stories, and proven preparation strategies.
The last time you took your child to the dentist, it took three adults to hold them in the chair. The time before that, you left the pediatrician's office in tears, yours and theirs, after a blood draw that felt more like a wrestling match. Now you have another appointment coming up and your stomach is already in knots.
You are not failing at this. Medical appointments combine every challenge neurodivergent children face into one high-stakes experience: unfamiliar environments, unexpected sensations, unpredictable timing, and strangers touching their body. The good news is that with the right preparation, these visits can become manageable and even routine.
## Why Medical Visits Are Challenging
Understanding the specific difficulties helps target your preparation efforts.
**Sensory overload is common.** Medical offices assault multiple senses simultaneously, bright fluorescent lights, chemical smells, strange sounds, and uncomfortable physical sensations during examinations.
**Unpredictability creates anxiety.** Children may not know what will happen, how long it will take, or whether something will hurt. This uncertainty is particularly difficult for children who rely on predictability to feel safe.
**Loss of control is inherent.** Being examined requires allowing someone to touch your body, open your mouth, or hold you in certain positions. For children who struggle with autonomy and control, this feels threatening.
**Past negative experiences compound fear.** One difficult appointment can create lasting anxiety about all future medical visits. The anticipatory fear becomes as problematic as the visit itself.
**Communication challenges** make it hard for some children to express their discomfort, ask questions, or understand explanations from medical professionals.
## The Power of Preparation
Research consistently shows that preparation reduces anxiety and improves medical visit outcomes for children with autism and ADHD.
**Familiarity reduces fear.** When children know what to expect, the unknown becomes known. Anxiety decreases when uncertainty decreases.
**Practice builds skills.** Children who have rehearsed opening their mouth or holding still have those skills available when needed, reducing the difficulty of the actual appointment.
**Emotional preparation is possible.** Children can process their feelings about upcoming visits in advance rather than being flooded with emotions during the appointment.
**Parents feel more confident.** When you have prepared your child, you feel more equipped to support them, which children sense and respond to.
## Creating Social Stories for Medical Visits
Social stories are particularly effective for medical appointment preparation.
**Be specific to your child's actual experience.** A story about visiting Dr. Smith at the building with the blue door is more useful than a generic doctor visit story.
**Include sensory information.** Describe what the child will see, hear, smell, and feel. This prepares their sensory system for the experience.
**Explain the sequence of events.** What happens first? What comes next? Knowing the order provides predictability.
**Acknowledge that things might be uncomfortable.** Honest stories that say "The dentist will count your teeth. It might feel strange but it will not hurt" build trust better than pretending everything will be easy.
**Include coping strategies.** "If I feel scared, I can squeeze my stress ball" gives children tools to use in the moment.
**Show the positive outcome.** The story ends with the visit being over and the child feeling proud of themselves.
## Visual Schedules for Appointments
Visual schedules for medical visits function like any other visual schedule but require some specific considerations.
**Start from leaving home.** The schedule might begin with getting in the car, driving to the office, walking inside, and sitting in the waiting room before any medical procedures.
**Include waiting time.** Medical offices often involve unpredictable waits. Acknowledging this in the schedule, and having strategies for waiting, prevents surprises.
**Show each step of the examination.** For a dental visit, this might include: sit in the special chair, wear the special glasses, open mouth, dentist counts teeth, dentist cleans teeth, rinse and spit, get a prize.
**Use photos when possible.** Pictures of the actual waiting room, the actual exam room, and even the actual doctor or dentist create maximum familiarity.
**Make it portable.** Bring the visual schedule to the appointment so your child can reference it and mark completed steps.
## Practice and Role Play
Hands-on practice at home reduces anxiety about unfamiliar medical procedures.
**Practice opening mouth wide.** For dental visits, practice at home with a mirror. How long can they hold their mouth open? Make it a game.
**Practice the examination position.** Whether lying on an exam table or sitting in a dental chair, practice the physical positions at home where it feels safe.
**Use play medical kits.** Let your child examine stuffed animals or family members. Being the "doctor" helps demystify the experience.
**Practice specific procedures.** If your child needs blood drawn, practice holding their arm still and looking away. If they need to wear a blood pressure cuff, try one at home first if possible.
**Rehearse coping strategies.** Practice deep breathing, using fidgets, or whatever calming techniques your child will use during the appointment.
.png)
## Sensory Preparation and Accommodation
Addressing sensory needs improves appointment tolerance.
**Visit the office beforehand if possible.** A brief trip to see the waiting room and meet the receptionist reduces unfamiliarity on appointment day.
**Bring sensory supports.** Headphones or earplugs for noise sensitivity. Sunglasses for bright lights. A comfort object or fidget tool. Whatever helps your child regulate.
**Request accommodations in advance.** Call ahead to ask about dimming lights, scheduling first appointments of the day to avoid waiting, or using a quieter exam room.
**Prepare for specific sensory experiences.** If your child hates the taste of fluoride at the dentist, ask if alternatives are available. If they cannot tolerate the paper gown, ask if they can keep their own shirt on.
**Plan sensory recovery time.** After a challenging appointment, schedule quiet time rather than going straight to another activity.
## Communicating with Medical Providers
Partnering with providers improves outcomes.
**Call ahead to explain your child's needs.** Let the office know your child has autism or ADHD and what accommodations help.
**Provide written information if helpful.** Some families create a one-page summary of their child's communication style, sensory sensitivities, and what helps them cope.
**Ask about the provider's experience.** Some doctors and dentists have training in working with neurodivergent children. Seeking these providers makes a significant difference.
**Request modifications to standard procedures.** Can the exam be done in parts with breaks? Can explanations be given in simpler language? Can the child stay in a parent's lap?
**Advocate for your child.** If something is not working, speak up. If the provider is not accommodating, it may be time to find a different provider.
## Managing the Appointment Day
Even with preparation, appointment day requires careful management.
**Time the appointment strategically.** Early morning often works better before children are tired or overstimulated. Avoid scheduling after school when reserves are depleted.
**Build in transition time.** Arrive early enough that you are not rushed, but not so early that waiting becomes excessive.
**Bring support tools.** Visual schedule, comfort items, fidgets, headphones, preferred snacks for after, whatever your child needs.
**Stay calm yourself.** Children pick up on parent anxiety. If you are nervous, they will be too. Your regulated presence helps them regulate.
**Use the coping strategies you practiced.** Remind your child of their tools. "Remember, you can squeeze your ball if you feel nervous."
**Celebrate completion.** Acknowledge the accomplishment, regardless of how smoothly it went. Every completed appointment builds tolerance for the next one.
## Building Long-Term Medical Comfort
The goal is not just surviving one appointment but building comfort with medical care over time.
**Maintain regular appointments.** Avoiding doctors and dentists increases fear. Regular visits build familiarity.
**Process each experience.** After appointments, talk about what happened, what was hard, and what helped. This processing supports future visits.
**Track progress over time.** Note what worked and what did not. Share this information with providers at future appointments.
**Adjust preparation as children grow.** What works at age five differs from what works at age ten. Update your strategies as your child develops.
---
[VizyPlan](https://vizyplan.com) helps you create social stories and visual schedules that prepare your child for medical appointments. [Start your free trial](https://apps.apple.com/us/app/vizyplan-visual-routines/id6756069118) and reduce anxiety around doctor and dentist visits.
---